Fleck Sign | Modified Thompson | Olecranon Avulsion | Active Extension Loss
- Most ruptures are AVULSIONS off the olecranon - the tendon-bone junction (enthesis) is the weak point, not the tendon midsubstance
- Fleck sign on a lateral elbow radiograph (a small avulsed bony flake from the olecranon) is the pathognomonic plain-film clue - always get an X-ray
- Test active extension against gravity: ask the patient to extend the elbow with the arm overhead/horizontal. A modified Thompson-type squeeze of the triceps belly should produce passive extension if the tendon is intact
- Complete tears in active patients are repaired surgically; partial tears (less than 50%) with preserved antigravity extension can be treated non-operatively
- Risk factors: anabolic steroids, local or systemic corticosteroid, chronic kidney disease, hyperparathyroidism, weightlifting and olecranon bursitis injection
- “Antigravity extension can be preserved despite a complete tear because the anconeus and intact lateral tendinous expansion compensate - so always palpate for a gap AND get an X-ray
- “Suture anchor repair has lower re-rupture and complication rates than transosseous bone-tunnel repair in recent systematic reviews
- “A partial tear that fails a non-operative trial, or any tear in a high-demand athlete, should be repaired
- “Delayed/chronic tears retract and scar - they may need V-Y turndown or tendon (e.g. Achilles) allograft augmentation
Triceps Tendon Rupture
Overview & Epidemiology
Triceps tendon rupture is the rarest of the major tendon ruptures, roughly 1-2% of all tendon injuries. Because it is so rare, the diagnosis is frequently missed at first presentation, and a missed tear becomes a chronic, retracted tear that is harder to repair.
Who. It occurs most often in men aged 40-60. The classic story is weightlifting, a forced eccentric contraction at the end of a bench-press lockout, or a fall on an outstretched hand that suddenly flexes a contracting elbow. A direct blow can also cause it.
Risk factors. Ask about each of these; several also predict trouble after repair:
- Anabolic-androgenic steroids
- Local or systemic corticosteroid, including repeated local steroid injection for olecranon bursitis, which degrades the insertion
- Fluoroquinolones
- Chronic kidney disease, especially in dialysis and transplant patients
- Hyperparathyroidism and renal osteodystrophy, which weaken the enthesis
- Diabetes and other metabolic or degenerative tendinopathy
- Weightlifting and bodybuilding
Associated injuries. Up to a third of cases have an associated injury: a radial head fracture, olecranon bursitis, or a wrist or forearm injury from the same fall. Examine the whole limb.
Pathophysiology & Anatomy
The tendon. The three heads of triceps brachii, long, lateral and medial, converge into a common tendon that inserts on the posterior olecranon. Triceps is the primary elbow extensor.
Two layers. The distal tendon is bilaminar. A thick superficial layer from the long and lateral heads inserts more proximally, and a deep layer, mainly the medial head, inserts more distally and broadly. MRI tear classification is built on this two-layer structure.


The lateral expansion. A lateral tendinous expansion blends with the forearm fascia and anconeus. While it is intact, the anconeus and the expansion allow weak residual extension even after a complete central tear, which is the source of the antigravity trap.
How it fails. The tendon fails under eccentric overload, a sudden force against an actively contracting, decelerating triceps; the lockout of a heavy bench press is the textbook example. The failure propagates through the enthesis, the mechanically weakest link, so the injury is almost always an avulsion off the olecranon rather than a midsubstance tear. Sometimes it lifts a thin cortical flake of olecranon with it, the fleck sign.
Why the tendon was weak. Pre-existing tendinopathy weakens the insertion. Anabolic steroids, fluoroquinolones, repeated local steroid injection for olecranon bursitis and metabolic bone disease (renal failure, hyperparathyroidism) all degrade collagen and predispose to rupture at lower loads.
Classification
Clinical Presentation
History. Sudden pain and a "pop" at the back of the elbow during a lift or after a fall, followed by weakness extending the elbow: difficulty pushing up from a chair or doing press-ups. Ask specifically about steroid use, renal disease and previous olecranon injections.
Examination. Work through inspection, palpation and two tests of extension:
- Inspection - posterior elbow swelling, ecchymosis, sometimes a visible defect
- Palpation - a palpable gap just proximal to the olecranon is the most useful sign
- Active extension against gravity - position the shoulder so the elbow must extend against gravity, with the arm overhead or horizontal. Inability, or marked weakness, suggests a complete tear
- Modified Thompson (squeeze) test - with the arm supported and the elbow flexed, squeeze the triceps belly. An intact tendon passively extends the elbow; absence of extension indicates a complete rupture
Antigravity extension may be partly preserved even with a complete tear. A patient who can "just about" straighten the arm can still have a complete rupture, so palpate for a gap and image.
GAPDiagnosis Triad
Hook:Mind the GAP: gap on palpation, antigravity loss, plain-film fleck.
Investigations
Radiographs first. An AP and lateral elbow series looks for the fleck sign, an avulsed flake of olecranon cortex that is pathognomonic of a triceps avulsion and easy to miss. The films also exclude associated radial head and olecranon fractures. A normal radiograph does not exclude a tear: if clinical suspicion persists, proceed to MRI or ultrasound.

Ultrasound. Cheap, dynamic and operator-dependent. It is good for confirming a tear and assessing the gap, and useful in resource-limited settings.


MRI. A confident clinical diagnosis, gap plus antigravity loss plus fleck sign, needs no advanced imaging before surgery. MRI is the test for equivocal cases, suspected partial tears and surgical planning: it quantifies the percentage of tendon torn, which layers are involved, the gap and retraction, and muscle quality in chronic tears. Sagittal fat-saturated sequences show fluid at the footprint and each layer separately.
Reading the MRI: The Layered (Bilaminar) Tear Pattern
The commonest pattern. The typical injury is a superficial-layer full-thickness tear with the deep layer still partly attached. The intact deep layer, with the anconeus and lateral expansion, preserves weak extension and masks the superficial avulsion, which is why the tear is easily under-called.
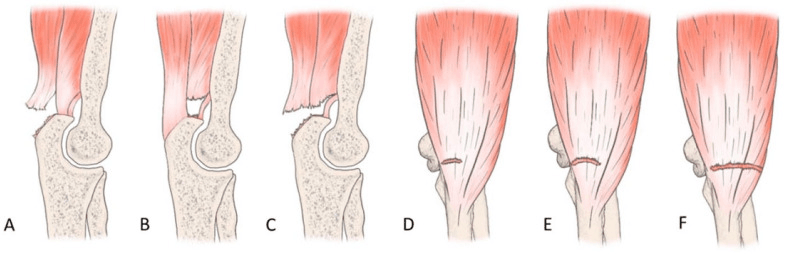
What the report must answer. Three findings change the operation:
- Which layers are torn
- The percentage of tendon width involved
- The retraction or gap
How it changes the repair. A superficial tear with a substantial intact deep layer may suit a single-row or limited repair. A full bilaminar avulsion needs a footprint-restoring double-row or suture-bridge construct.
The practical rule. When the extension weakness is worse than the tear looks, suspect an occult superficial-layer avulsion sitting over a still-attached deep layer, and image both layers before committing to partial versus complete. Systematic elbow imaging is developed in the imaging-elbow-systematic topic.


Management
Treatment hinges on the completeness of the tear and the patient's demands.
Who. Partial tears (less than 50%) with preserved antigravity extension, and low-demand or high-surgical-risk patients who decline or cannot tolerate surgery.
Protocol.
- Splint or brace at 30-40 degrees of flexion for about 4 weeks, then progressive range of motion
- Avoid resisted extension for 6 weeks; graded strengthening thereafter
Follow-up. Monitor closely. A partial tear that progresses, stays painful or fails to regain strength should be converted to surgical repair.


Reconstructing the Chronic, Retracted Triceps
Why primary repair fails late. By around 6 weeks the muscle-tendon unit shortens and adheres, so dragging it back to the olecranon either fails under tension or blocks flexion. Assess muscle quality on MRI first: a fatty, atrophic triceps predicts a poorer result whatever is done.
Setting the length. The normal distal tendon runs from the olecranon tip to the myotendinous junction, and reconstruction has to respect that relationship. Left too long, the triceps is weak with an extension lag; left too short, it restricts flexion.

The options. Three reconstructions are described:
- V-Y triceps turndown (lengthening) - a proximally based inverted-V tongue of the scarred aponeurosis is turned distally to bridge the gap and reattached to the olecranon, lengthening the musculotendinous unit so native tissue reaches bone. The donor defect is closed side to side, and no graft is needed.
- Achilles tendon allograft - its calcaneal bone block is fixed to the olecranon and its tendinous fan woven into the triceps. The workhorse for a large irreparable gap; semitendinosus or hamstring and fascia lata grafts are alternatives.
- Anconeus rotation flap - rotated to reconstruct a smaller distal-triceps defect

Counselling. Reconstruction is less reliable than acute repair, with weaker extension, some extension lag and stiffness, which is why the diagnosis should be made and the tendon repaired within about 3 weeks. The underlying tendon-healing biology is developed in the tendon-healing topic.
Complications & Prognosis
- Approx. rate
- 2-7%
- Notes
- Higher with transosseous tunnels and in anabolic steroid users; early non-compliance a key cause
- Approx. rate
- Up to ~10%
- Notes
- Nerve runs medially near the field; usually transient, occasionally needs release/transposition
- Approx. rate
- Common (~9 degrees mean)
- Notes
- More frequent after suture-anchor-only repair in one large cohort; usually minor
- Approx. rate
- Low (a few %)
- Notes
- Higher in dialysis/transplant and diabetic patients
- Approx. rate
- ~3-15%
- Notes
- Overall surgery has a relatively high reoperation rate regardless of technique
Who does badly. A large insurance-database cohort identified male sex, age over 60, ischaemic heart disease, rheumatoid arthritis and chronic kidney disease as risk factors for complications, and prior anabolic steroid use as the strongest predictor of needing revision surgery.
Prognosis. Across systematic reviews, surgical repair gives excellent patient-reported outcomes: a mean Mayo Elbow Performance Score of about 92, high satisfaction, about 92% returning to pre-injury function, and essentially all patients regaining at least grade 4/5 extension strength. Outcomes are best for acute repairs; chronic, retracted tears requiring grafting do less well.
Key Exam Points
Because the anconeus and the intact lateral tendinous expansion of the triceps provide weak residual extension. This is the "antigravity trap" - never exclude a complete tear on partial extension alone. Palpate for a gap and obtain a radiograph (fleck sign) or MRI.
The fleck sign - a small avulsed flake of cortical bone pulled off the posterior olecranon - best seen on the lateral radiograph. It confirms an avulsion-type rupture at the enthesis.
A suture-anchor (double-row/footprint-restoring) repair is reasonable: systematic reviews show lower complication and re-rupture rates than transosseous tunnels, and biomechanically it restores far more of the native footprint with higher load to failure. Transosseous tunnels remain an acceptable, familiar alternative.
Acute repair (less than 3 weeks) allows direct anatomic reattachment. In chronic tears the tendon retracts and scars, so plan for V-Y triceps turndown or Achilles tendon allograft augmentation, and counsel the patient that outcomes are less reliable than acute repair.
Guidelines, Registries & Global Practice
There is no large randomised trial or dedicated society guideline for this rare injury, so practice is guided by systematic reviews and expert consensus. Practice is broadly consistent worldwide.
- Consensus position
- Surgical repair, ideally within ~3 weeks
- Source/evidence
- Systematic reviews (Tran 2022; Alnaji 2021)
- Consensus position
- Non-operative trial; repair if it fails or progresses
- Source/evidence
- Narrative reviews (Keener & Sethi, Hand Clin 2015)
- Consensus position
- Footprint-restoring suture anchors trending over transosseous tunnels
- Source/evidence
- Lower complication/retear rates (Tran 2022; biomechanics Scheiderer 2018)
- Consensus position
- Counsel renal, rheumatoid, cardiac and steroid users on higher complication/revision risk
- Source/evidence
- Large database cohort (Lee 2022)
Registry note: Unlike arthroplasty, there are no national joint-registry data for triceps tendon repair; the strongest population-level evidence comes from large insurance-claims database cohorts (e.g. Lee 2023), which inform risk-factor counselling rather than implant choice - and which count coded events within 90 days, not clinical failure at the point the patient returns to loading.
Related pages: Distal Biceps Rupture is the exact counterpart at the other end of the same joint and the comparison worth holding in mind - a similar enthesial avulsion in a similar patient, with the same anabolic-steroid and fluoroquinolone associations, but a far higher index of clinical suspicion because the deformity is obvious; Olecranon Fractures share the insertion and the differential, since a triceps avulsion can carry a flake of olecranon and an olecranon fracture disrupts the extensor mechanism by a different route, and Olecranon Stress Fracture is the overuse mimic in throwing athletes; Tendon Healing supplies the enthesial biology that explains why the tendon-bone junction is the weak link and why protected motion is staged as it is; Imaging the Elbow Systematically covers the lateral radiograph and the MRI sequences that show the layered tear; Elbow Stiffness and Contracture is the commonest functional complication of over-protective rehabilitation after repair; Achilles Tendon Rupture, Quadriceps Tendon Rupture and Patellar Tendon Rupture are the other major tendon ruptures and share the systemic risk factors - renal failure, steroids, hyperparathyroidism - that make a spontaneous rupture a reason to investigate the patient, not just the tendon.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 46-year-old male recreational weightlifter presents 4 days after feeling a sudden pop at the back of his right (dominant) elbow during the lockout phase of a heavy bench press. He has posterior elbow swelling and bruising and complains of weakness straightening the arm. On examination there is a tender boggy swelling and a subtle palpable defect just above the olecranon. When you ask him to extend the elbow with the shoulder flexed to 90 degrees, he can produce weak extension. A lateral radiograph shows a small flake of bone lifted off the olecranon. He mentions he occasionally uses anabolic steroids. How do you assess, investigate and manage him, and how would you counsel him about his steroid use?”
“A 39-year-old manual labourer fell onto an outstretched hand and has posterior elbow pain and mild weakness extending the elbow against resistance. There is tenderness over the olecranon insertion but you cannot feel a definite gap, and he can extend the elbow against gravity, though it is painful and slightly weak. The plain radiograph is normal with no fleck sign. How do you work out whether this is a partial or complete tear, and how does that change your management?”
Must-Know Facts
- Rarest major tendon rupture (1-2% of tendon injuries); men aged 40-60
- Almost always an AVULSION off the olecranon (enthesis is the weak link)
- Mechanism: eccentric load (bench-press lockout) or fall on outstretched hand
- Risk: anabolic steroids, corticosteroid, renal failure, hyperparathyroidism, olecranon bursitis injection
Diagnosis
- GAP: palpable defect proximal to olecranon
- Antigravity extension loss (but weak residual extension does NOT exclude complete tear)
- Modified Thompson (squeeze) test: no passive extension = complete tear
- Fleck sign on lateral X-ray = pathognomonic; MRI for equivocal/partial tears
Management
- Partial (less than 50%) with preserved extension: non-operative brace trial + close follow-up
- Complete / high-grade partial / athlete: surgical repair, ideally within 3 weeks
- Suture anchors (footprint-restoring): lower complication and re-rupture rates than transosseous tunnels
- Chronic retracted tear: V-Y turndown or Achilles allograft augmentation
Outcomes & Complications
- ~92% return to pre-injury function; mean Mayo Elbow score ~92; high satisfaction
- Re-rupture 2-7% (higher with transosseous and in steroid users)
- Ulnar neuropathy up to ~10% (usually transient); minor extension loss common
- Counsel renal/rheumatoid/cardiac patients and steroid users on higher complication/revision risk
Evidence Base
The evidence below was retrieved from PubMed for this topic. Triceps rupture is rare, so the literature is dominated by systematic reviews of observational series, large database cohorts, and biomechanical/cadaveric studies rather than randomised trials.
Surgical Repair Outcomes - Systematic Review (suture anchor vs transosseous)
- Systematic review of 16 studies of distal triceps repair; mean DASH 4, mean Mayo Elbow Performance Score 92, mean isokinetic strength 87% of normal
- 95% of patients were satisfied and 92% returned to pre-injury function; 100% regained at least grade 4/5 gross strength
- Overall complication rate 15%, with retears ~5%
- Transosseous repair had a higher complication rate (18% vs 8%) and higher retear rate (7% vs 2%) than suture anchor repair
Surgical Management - Systematic Review of Techniques
- 19 studies, 560 patients (565 tendons), 78.6% male, mean age 46 years, mean follow-up 32 months
- Overall complication rate 14.9%; by technique: direct repair 29.2%, transosseous 15.2%, suture anchor 7.7%
- Re-rupture: transosseous 4.3%, suture anchor 2.1%, direct repair 0%
- Significant postoperative improvement in pain, strength and range of motion across all techniques
Footprint Restoration & Repair Strength - Biomechanics
- 24 cadaveric elbows: transosseous cruciate vs knotless suture-bridge vs V-shaped unicortical button repair
- Transosseous repair restored only 37% of the native footprint vs ~85-89% for the suture-bridge and V-shaped button techniques
- Mean peak load to failure: V-shaped button 732 N, suture-bridge 505 N, transosseous cruciate 281 N
- Footprint-restoring constructs also showed less gap formation than transosseous repair
Primary Repair in a General Population - Multicentre Series
- 28 primary triceps reinsertions (23 acute, 5 chronic), mean age 45 years, mean follow-up 47.5 months
- Mean Mayo Elbow Performance Score 94, mean QuickDASH 10; satisfactory results in 93%
- Strength 5/5 in 18 and 4/5 in 10 tendons; only one re-rupture (a patient with chronic renal failure)
- Both transosseous and suture-anchor reinsertion gave satisfactory results in acute and chronic tears
Trends, Outcomes & Risk Factors - Large Database Cohort
- 8143 distal triceps repairs from an insurance claims database; most common in men aged 40-59
- 90-day complication rate 5.8%; 1-year revision rate 2.6%
- Risk factors for 90-day complications: male sex, age over 60, ischaemic heart disease, rheumatoid arthritis, chronic kidney disease
- Prior anabolic steroid use significantly increased the risk of 1-year revision surgery