Cock-Robin Torticollis | Fixed C1-C2 Rotation | Grisel Syndrome | Dynamic CT | Reduce Early to Avoid Chronic Fixation
- Cock-robin posture: head tilted to one side, chin rotated to the OPPOSITE side, with painful resistance to correction
- The deformity is FIXED - unlike muscular torticollis, the patient cannot rotate past midline toward the chin side
- Dynamic (3-position) CT confirms a fixed C1-C2 relationship that does not correct on attempted counter-rotation
- Grisel syndrome = non-traumatic AARS after head/neck infection or ENT surgery - the worst prognosis
- Chronicity drives outcome - early closed reduction; chronic or recurrent cases need C1-C2 fusion
- “AARS is the dangerous mimic of common childhood torticollis - do not just prescribe stretches
- “On open-mouth (odontoid) view the lateral mass rotated forward looks wider and closer to the dens (wink sign)
- “The key distinction from muscular torticollis: SCM on the side TOWARD which the chin points may be contracted (paradoxical), and rotation is fixed
- “Pang dynamic CT motion analysis grades pathological stickiness (Type I worst, Type III best)
Overview and Epidemiology
Atlantoaxial rotatory subluxation (AARS) is an abnormal, locked rotation of the atlas (C1) on the axis (C2); when fixed and persistent it is often called atlantoaxial rotatory fixation (AARF). The patient presents with a painful, fixed torticollis, the cock-robin posture, which unlike ordinary muscular torticollis cannot be voluntarily corrected.
Why it matters. This is the classic "dangerous torticollis" that must not be missed. Recognise it, image it correctly with dynamic CT, and treat it early, before the rotation becomes permanently fixed.
Who. Children are the predominant group. A 15-year paediatric series of 55 children with AARS/F had a mean age of about 8.5 years with a roughly even sex distribution [Spinnato 2020]. Adults can develop AARF, almost always after trauma: a systematic review of published adult cases found a mean age of about 36 years, with motor-vehicle accidents and falls the leading mechanisms [Zafarshamspour 2024].
Aetiology. Three main settings account for the cases:
- Typical setting
- Children, often trivial event
- Key point
- Most common; frequently resolves with early treatment
- Typical setting
- After pharyngitis, otitis, retropharyngeal abscess, or ENT surgery
- Key point
- Worst prognostic group
- Typical setting
- Adults and adolescents
- Key point
- Higher-energy; look for associated fractures and ligament injury
Pathophysiology and Anatomy
The joint. The C1-C2 complex provides roughly 50% of all cervical rotation, about 45 degrees to each side, pivoting around the dens. There is no intervertebral disc, so stability depends entirely on bone shape and ligaments: the joint is shallow and ligamentously dependent. The transverse ligament is the primary restraint, holding the dens against the anterior arch of C1 and preventing anterior translation; the alar ligaments check rotation and the capsular ligaments of the facet joints stabilise the lateral masses.
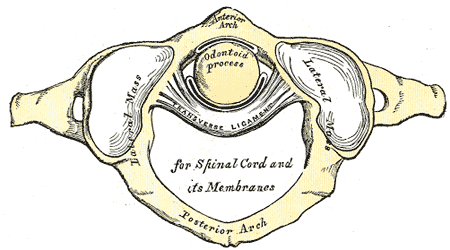
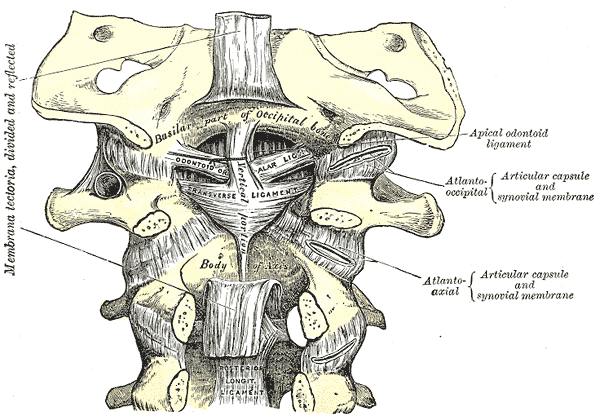
The normal rhythm. Normative CT motion studies in children showed a highly reproducible pattern as the head turns: C1 first moves alone (the single-motion phase), then C1 and C2 move together with C1 faster (the double-motion phase), and beyond about 65 degrees they move in unison with a fixed maximal separation [Pang 2010]. AARF is a loss of this normal, predictable C1-on-C2 rhythm: the two vertebrae stay locked together regardless of how the head is turned.
The mechanical lesion. The atlas rotates on the axis and then fails to return to neutral. Proposed mechanisms include the lateral mass capsule and synovium becoming caught or swollen, the facet articulation effectively over-riding or jamming, and muscle splinting that maintains the abnormal position. Once locked, the joint behaves like a fixed deformity rather than a transient spasm.
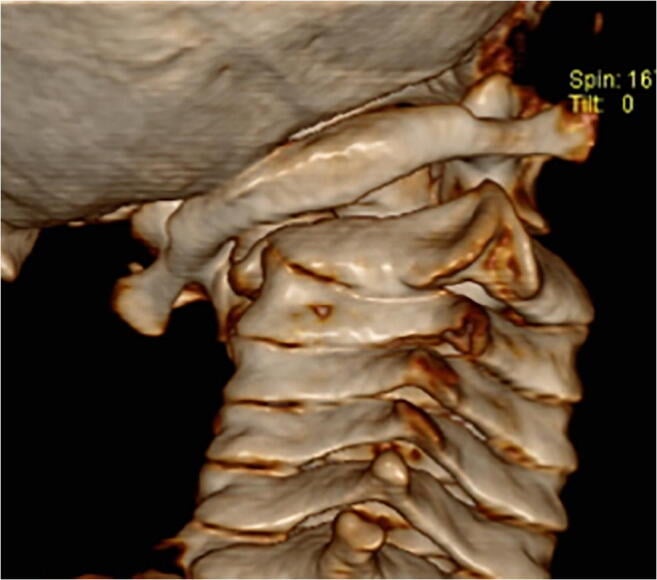
Why inflammation locks it (Grisel syndrome). Infection or inflammation in the pharynx or retropharyngeal space, or after ENT surgery (post-adenoidectomy or tonsillectomy is a classic trigger), spreads to the upper cervical region. The classic explanation is drainage through the pharyngovertebral (periodontoidal) venous plexus, causing local hyperaemia, ligamentous laxity and decalcification around the C1-C2 joint, which lets the atlas slip and lock. Abnormally lax soft tissues and a diagnosis that is often delayed are the reasons this group carries the worst prognosis: it is the subgroup most likely to need prolonged treatment or fusion.
Why children. Compared with adults, children have more horizontal (less locked) facet joints, greater ligamentous laxity, a relatively large head and incompletely ossified bony stabilisers. These features allow a larger physiological range of C1-C2 rotation and make the joint easier to lock, so relatively minor force or inflammation can lock C1 on C2.
Children with chronic AARF develop increasing occiput-C1 laxity and separation as a compensation to keep the eyes level; the mean occiput-C1 angle was markedly higher in chronic than acute cases [Pang and Li 2005]. The whole craniocervical junction adapts to the malalignment, which is why a long-standing deformity becomes structural and harder to reverse.
Certain underlying disorders weaken the C1-C2 complex and lower the threshold for rotatory subluxation or frank atlantoaxial instability. Their presence should heighten suspicion and caution, including before intubation or general anaesthesia, and a torticollis in such a child deserves a particularly low threshold for imaging and specialist involvement. They fall into ligamentous laxity, bony anomaly and inflammatory destruction:
- Down syndrome - generalised ligamentous laxity, transverse-ligament incompetence and occasional os odontoideum; a recognised cause of atlantoaxial instability
- Mucopolysaccharidoses, especially Morquio syndrome - odontoid hypoplasia/dysplasia with instability
- Os odontoideum - a separate ossicle in place of the dens, allowing C1-C2 translation
- Juvenile idiopathic arthritis and rheumatoid arthritis - erosive/inflammatory C1-C2 instability
- Connective-tissue disorders - Ehlers-Danlos, Marfan
- Congenital craniocervical anomalies - e.g. Klippel-Feil
Classification Systems
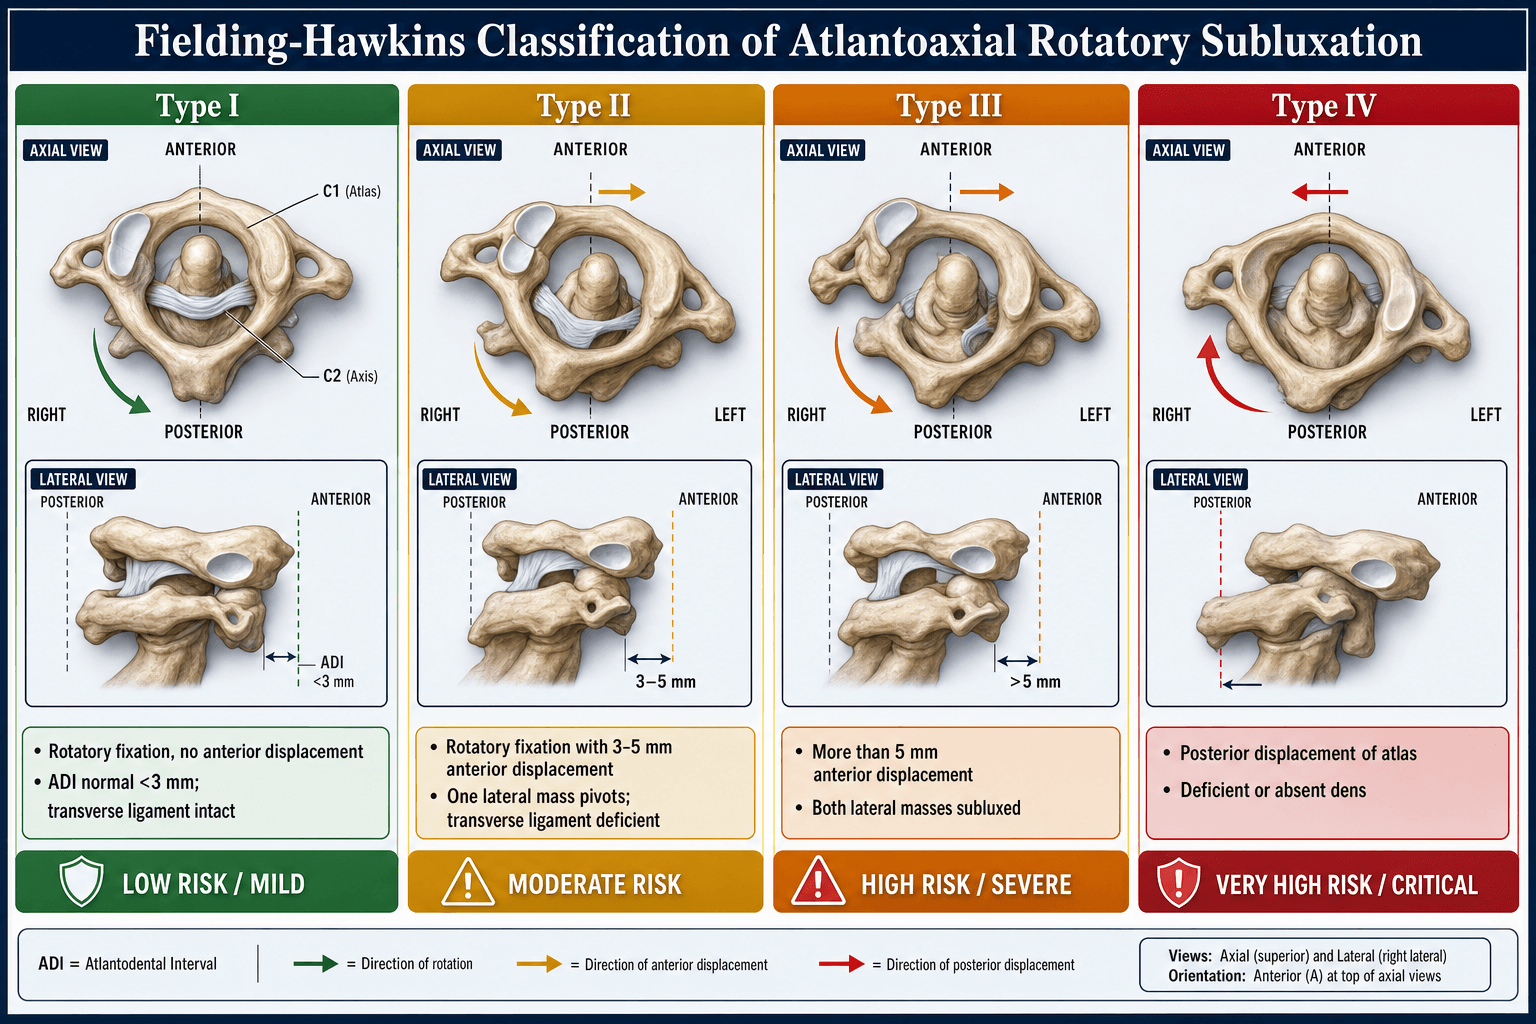
Two systems are in use and they grade different things. Fielding-Hawkins, the traditional anatomy-based system, grades the degree of anterior atlantodental shift; Pang grades how "stuck" the C1-C2 joint is on 3-position dynamic CT rather than the static shift, and adds a chronicity grading that runs alongside as a prognostic axis independent of type.
- Description
- Rotatory fixation without anterior displacement
- Anterior shift
- None
- Ligament status
- Transverse ligament intact
- Treatment emphasis
- Collar, gentle reduction
- Description
- Rotatory fixation with anterior displacement; one lateral mass acts as pivot
- Anterior shift
- 3-5mm
- Ligament status
- Transverse ligament deficient
- Treatment emphasis
- Halter traction
- Description
- Rotatory fixation with anterior displacement of both lateral masses
- Anterior shift
- Greater than 5mm
- Ligament status
- Transverse and secondary ligaments incompetent
- Treatment emphasis
- Traction, likely fusion
- Description
- Rotatory fixation with posterior displacement
- Anterior shift
- Posterior
- Ligament status
- Odontoid deficiency or disruption (for example os odontoideum, aplasia or fracture)
- Treatment emphasis
- Rare, careful reduction, fusion
Type I (no anterior shift) is by far the most common, especially in children; in adult traumatic series it was also the most common pattern [Zafarshamspour 2024]. The higher types (II-IV) imply progressive transverse ligament incompetence and are more likely to need surgical stabilisation.
Clinical Presentation
History. Acute onset of a painful, twisted neck, often in a child. A trigger may be identified: minor trauma, or a recent upper respiratory or ENT infection or ENT surgery (Grisel). The head is held in a characteristic position and the patient resists attempts to straighten it.
The cock-robin deformity. The head is tilted toward one side and the chin rotated to the opposite side, with slight flexion; the posture resembles a robin cocking its head to listen. The sternocleidomastoid that looks contracted is typically on the side the chin points to. It is splinting, not the primary cause, which is the key difference from congenital muscular torticollis, where the tight SCM is on the side opposite the chin.
Examination. The most useful bedside question is whether the patient can rotate the head past the midline toward the side the chin points to. In AARS this movement is blocked and painful because the joint is mechanically fixed; in muscular torticollis it is usually possible, if uncomfortable.
- AARS (rotatory fixation)
- Acute, often after trauma/infection
- Congenital muscular torticollis
- Present at or shortly after birth
- AARS (rotatory fixation)
- Fixed; cannot rotate past midline toward chin side
- Congenital muscular torticollis
- Usually can be coaxed past midline
- AARS (rotatory fixation)
- Often painful
- Congenital muscular torticollis
- Usually painless
- AARS (rotatory fixation)
- None
- Congenital muscular torticollis
- Palpable pseudotumour may be present
- AARS (rotatory fixation)
- On the side the chin points to (splinting)
- Congenital muscular torticollis
- Opposite the chin (primary contracture)
A torticollis that is new, painful, follows trauma or infection, has no palpable SCM mass, or fails to correct is not muscular torticollis until proven otherwise. The two dangerous misses are atlantoaxial rotatory fixation and a posterior fossa / spinal tumour.
Most AARS, especially type I, has no neurological deficit, but large anterior or posterior displacement can narrow the space available for the cord. Always perform and document a full neurological examination; any deficit, or a high-grade displacement, mandates urgent MRI and cord protection.
Differential Diagnosis of Paediatric Torticollis
AARS is only one cause of a child holding the head twisted. The examinable skill is a structured differential that separates the benign, the time-critical and the dangerous. Each of these causes is worked up in its own right in torticollis in children, and two of the structural mimics have dedicated accounts: Klippel-Feil syndrome and pseudosubluxation of the cervical spine, the normal paediatric variant that is misread as displacement.
- Distinguishing features
- Acute, painful, FIXED cock-robin posture; cannot rotate past midline toward chin side
- Action
- Dynamic CT; reduce early
- Distinguishing features
- Infant; palpable SCM pseudotumour; painless; correctable past midline; tight SCM opposite the chin
- Action
- Stretching/physiotherapy; surgery if persistent
- Distinguishing features
- Compensatory head tilt for strabismus/superior oblique palsy; DISAPPEARS when the eye is covered or during sleep; no neck pathology
- Action
- Ophthalmology referral
- Distinguishing features
- Progressive, morning/night symptoms, headache, ataxia, cranial-nerve or long-tract signs
- Action
- URGENT MRI brain and whole spine
- Distinguishing features
- Fever, raised inflammatory markers, dysphagia/drooling; can itself trigger Grisel AARS
- Action
- MRI, antibiotics, drainage as needed
- Distinguishing features
- After metoclopramide/antipsychotics; acute, fluctuating, often with oculogyric crisis
- Action
- Stop the drug; anticholinergic (e.g. procyclidine)
- Distinguishing features
- Painless, long-standing, low hairline/short neck; restricted motion; structural on radiograph
- Action
- Imaging; screen for associated anomalies
- Distinguishing features
- Recurrent self-limiting episodes in infants, often with pallor/vomiting; normal between attacks (migraine variant)
- Action
- Reassurance; exclude posterior fossa lesion
Investigations
Plain radiographs screen. On the open-mouth (odontoid) view the lateral mass that has rotated forward looks wider and closer to the dens, while the contralateral mass looks narrower and further away: the asymmetric "wink" appearance. Asymmetry of the dens-lateral mass spaces raises suspicion. The lateral view may show the assimilated posterior arch of C1 and an increased atlantodental interval if there is anterior shift. Plain films are suggestive, not confirmatory: positioning the twisted neck reproducibly is difficult, and a normal film does not exclude AARS.
CT confirms. CT is the diagnostic test of choice. A static CT demonstrates the rotational malalignment of C1 on C2, but a single scan can show rotation that is actually within physiological range if the head happened to be turned. The 3-position dynamic protocol (neutral, then maximal active rotation to each side) settles the question: in a normal child the C1-C2 relationship changes predictably, whereas in AARF the atlas and axis stay locked together and the pathological rotation persists. The same study both confirms AARF and grades it, because Pang's normative and prospective studies established the protocol as the means to diagnose and grade AARF by plotting the C1-C2 motion curve against a normal template [Pang 2010; Pang and Li 2005].
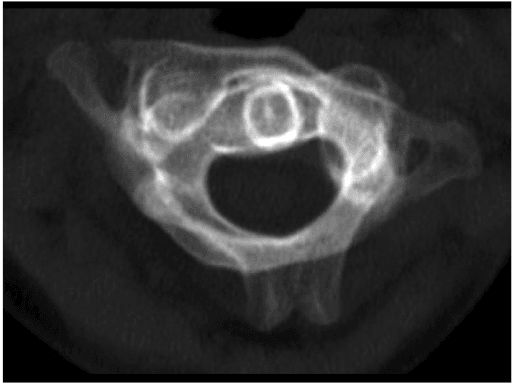
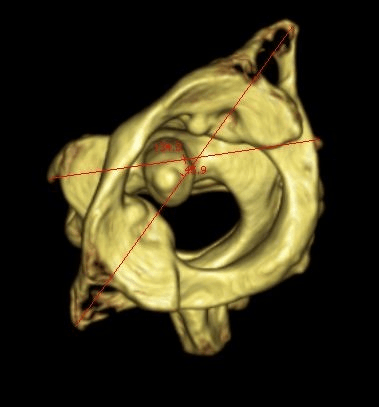
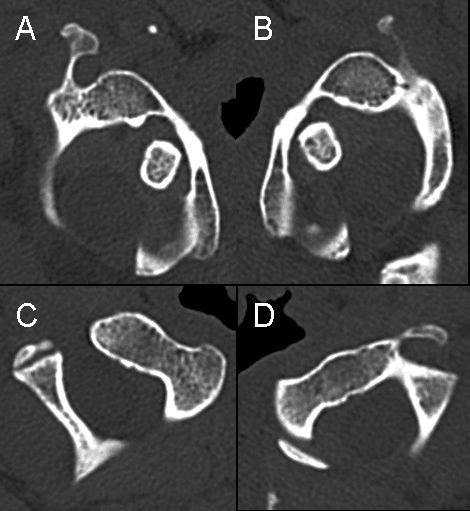
Dynamic CT delivers a real radiation dose to a child's neck and thyroid. Use it deliberately, when the diagnosis is clinically suspected and will change management, rather than as a screening study for every stiff neck.
MRI is selective. It is indicated if there are neurological signs, to assess the cord and the space available for the cord, and to evaluate soft-tissue or inflammatory change in Grisel syndrome. It also helps exclude a posterior fossa or cord tumour in atypical torticollis.
Measurements. The key measurements and what each tells you:
- What it assesses
- Anterior C1 arch to dens
- Relevance in AARS
- Increased shift signifies transverse ligament incompetence (Fielding II+)
- What it assesses
- Posterior dens to posterior arch of C1
- Relevance in AARS
- Falls with large displacement; cord at risk if narrowed
- What it assesses
- Degree of fixed rotation on CT
- Relevance in AARS
- Correlates with recovery time (higher = slower)
- What it assesses
- Compensatory occipitocervical change
- Relevance in AARS
- Markedly raised in chronic cases
Both the Fielding-Hawkins type and the measured C1-C2 rotation degree correlated significantly with recovery time in a paediatric series [Spinnato 2020].
Management
The principle. Reduce early, before the joint becomes permanently fixed. Most acute cases respond to conservative measures; chronicity and recurrence drive the need for surgery.
The first week. Analgesia and muscle relaxants break the splinting cycle, and a soft collar with activity rest suits the very acute, low-grade case. Many early, low-grade (type I) cases reduce spontaneously or with gentle measures within days.
Traction. When the deformity persists or is higher grade, traction reduces the locked joint gradually: halter traction for lower-grade cases, skeletal calipers (Gardner-Wells) for higher-grade or chronic ones, with regular neurological checks throughout.
Holding the reduction. Immobilisation in a collar, SOMI brace or halo, chosen by type and chronicity, maintains alignment while the soft tissues settle.
Grisel syndrome. The same ladder, plus appropriate antibiotics for the underlying infection and attention to any persisting ENT source. Prompt diagnosis can avert surgery.
What the series show. In adult traumatic AARF, conservative management was used in the majority of acute cases but in only a minority of chronic cases, and acutely diagnosed patients were more often treated successfully without surgery [Zafarshamspour 2024]. In children, conservative treatment is effective in most, with delayed recovery concentrated in Grisel cases and higher-grade, larger-rotation deformities [Spinnato 2020; Pang and Li 2005].
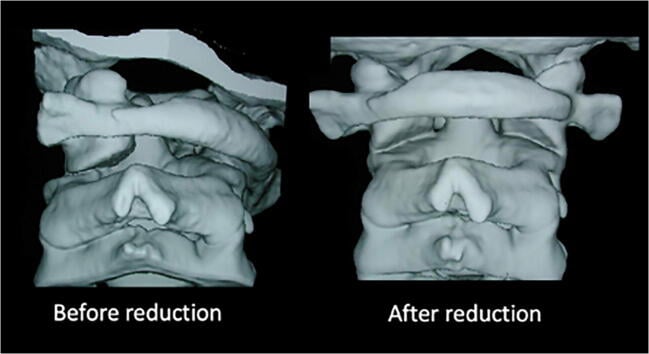
- Findings
- Fielding type I-II, no anterior shift or minimal
- Management
- Analgesia, soft collar, early reduction - many resolve quickly
- Findings
- Type I-III, fixed on dynamic CT
- Management
- Halter (or caliper) traction, muscle relaxants, monitor neurology
- Findings
- Pathological stickiness, occiput-C1 compensation
- Management
- More aggressive traction; higher chance of irreducibility and fusion
- Findings
- Loss of normal C1-C2 dynamics, ligament failure
- Management
- Posterior C1-C2 fusion in best achievable alignment
- Findings
- Large anterior or posterior shift, narrowed SAC
- Management
- Urgent MRI, protect the cord, surgical stabilisation
Complications
Chronic fixation. The principal complication of late diagnosis. A long-standing locked joint develops the compensatory occipitocervical changes described above, becomes irreducible, and leaves a permanent cosmetic and functional torticollis, which is the main reason early reduction is stressed.
Recurrence. Re-slippage after reduction is common in higher-grade and chronic cases and predicts a worse outcome. Recurrent AARF patients did markedly worse on every measure, and recurrence was driven by both higher type and greater chronicity [Pang and Li 2005]; recurrent AARF is a leading trigger for moving to fusion.
Loss of C1-C2 rotation. Even after successful treatment, some patients permanently lose normal atlantoaxial rotation. Fusion deliberately sacrifices C1-C2 rotation, about half of cervical rotation, for stability.
Neurological injury. Uncommon but serious with large displacement or during manipulation or surgery. Vertebral artery injury and cord compromise are the feared operative complications.
Delay leads to fixation, fixation leads to recurrence, and recurrence leads to fusion.
Clinical Relevance and Exam Approach
A viva answer on a child with acute torticollis is best built in this order:
- Recognise the red flags - acute, painful, post-trauma or post-infection, fixed deformity, no SCM mass
- Differentiate AARS from muscular torticollis, ocular torticollis, posterior fossa tumour, and infection (osteomyelitis/discitis)
- Image correctly - plain films to screen, dynamic CT to confirm and grade, MRI if neurology or tumour suspected
- Classify - Fielding-Hawkins (displacement) and Pang (dynamic, with chronicity)
- Treat by a ladder - analgesia/collar then traction then bracing then fusion, reducing early
- Address the cause in Grisel syndrome - antibiotics plus neck treatment
Guidelines, Registries & Global Practice
AARS/AARF is a rare condition managed largely on the basis of case series and expert consensus rather than randomised trials or implant registries, so practice is guided by the principles below rather than by a single national guideline.
Points of broad international agreement:
- Consensus position
- Dynamic (3-position) CT is the reference standard for confirming and grading fixation; plain films screen only
- Consensus position
- Early reduction is universally emphasised; chronicity predicts irreducibility and fusion across paediatric and adult series
- Consensus position
- Conservative care (analgesia, muscle relaxant, traction, immobilisation) for most acute cases
- Consensus position
- Reserved for irreducible, recurrent, chronic, neurologically compromised or unstable cases - posterior C1-C2 fusion
- Consensus position
- Treat the underlying infection alongside the neck; maintain a low threshold for imaging after ENT procedures
- Classification preference - the displacement-based Fielding-Hawkins system remains the most widely quoted internationally, while the dynamic-CT-based Pang system is favoured where the 3-position protocol is available and where grading guides treatment intensity.
- Traction method and setting - halter traction at home or on the ward versus inpatient skeletal (caliper) traction varies with resources and chronicity.
- Brace choice after reduction - soft collar, SOMI brace and halo are all used, selected by type, chronicity and local practice.
unlike hip and knee arthroplasty, there is no dedicated international registry for C1-C2 fusion in AARF; when fusion is performed, technique (screw-rod versus historical wiring) follows the wider upper-cervical fixation literature.
Present AARS as a time-critical diagnosis: anywhere in the world the message is the same - recognise the fixed cock-robin deformity, confirm with dynamic CT, reduce early, treat any inflammatory source, and reserve C1-C2 fusion for the chronic, recurrent or unstable joint.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 7-year-old is brought in with a sudden painful twisted neck that started 3 days after a sore throat. The head is tilted to the right and the chin points to the left, and the child cries when you try to straighten it. How do you assess and manage this child?”
“A 10-year-old presents with a 4-month history of a fixed twisted neck that was initially treated as torticollis. Dynamic CT shows a Pang type I rotatory fixation that does not correct on counter-rotation, and previous traction reduced it but it re-slipped. How do you manage this now?”
“A 30-year-old presents to the emergency department after a motor vehicle accident with neck pain and a rotated head posture. CT shows a Fielding-Hawkins type I atlantoaxial rotatory fixation with no other injury and a normal neurological examination. How do you proceed?”
Definition and Buzzwords
- Fixed abnormal rotation of C1 on C2 - painful torticollis
- Cock-robin posture: head tilted one way, chin rotated the opposite way
- AARS (subluxation) becomes AARF (fixation) when persistent
- Grisel syndrome = non-traumatic AARS after head/neck infection or ENT surgery
Who Gets It
- Children predominate (mean age around 8 years; shallow, ligament-dependent joint)
- Adults: almost always traumatic (mean age around 36, MVA and falls)
- Three buckets: idiopathic/minor trauma, Grisel (inflammatory), major trauma
- Grisel cases have the worst prognosis
Diagnosis
- Key test: dynamic 3-position CT - relationship is FIXED and does not correct
- Open-mouth view: forward-rotated lateral mass looks wider and nearer the dens
- MRI if neurological signs or to assess cord / exclude tumour
- Differentiate from muscular torticollis (fixed deformity, no SCM mass)
Classification
- Fielding-Hawkins I-IV by displacement (I none, II 3-5mm, III greater than 5mm, IV posterior)
- Type I most common; higher types = transverse ligament incompetence
- Pang I-III by dynamic stickiness - Type I is WORST, Type III best
- Chronicity (acute less than 1mo / subacute 1-3mo / chronic greater than 3mo) is independent prognostic axis
Management Ladder
- Acute low-grade: analgesia, muscle relaxant, soft collar
- Persistent/higher grade: halter then caliper traction to reduce, then brace/halo
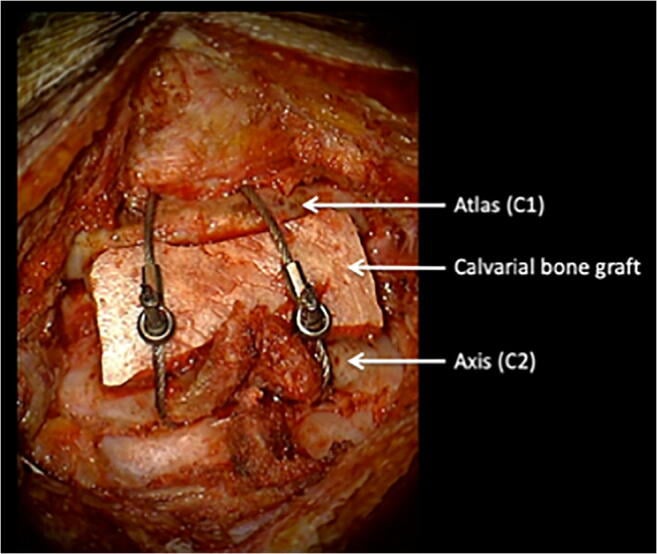
- Recurrent or irreducible or chronic: posterior C1-C2 fusion (Goel-Harms)
- Grisel: add antibiotics and treat the ENT source
- Reduce EARLY - chronicity is the modifiable enemy
Complications and Viva Essentials
- Chronic fixation, recurrence, permanent loss of C1-C2 rotation
- Vertebral artery injury is the feared operative complication - CT angiography to plan
- Recurrence is driven by higher type and greater chronicity
- Fusion sacrifices about 50% of cervical rotation for stability
- Always document neurology; escalate urgently if any deficit
Evidence Base
Pang and Li - Atlantoaxial Rotatory Fixation: Part 3, Prospective Study of Clinical Manifestation, Diagnosis, Management and Outcome in Children
- In 50 children with painful torticollis studied with the 3-position dynamic CT protocol, 29 had true AARF (8 Type I, 11 Type II, 10 Type III). Treatment difficulty, irreducibility, need for halo and fusion, and loss of normal C1-C2 rotation were significantly worse with Type I than Type III, and far worse in chronic than acute cases. The worst subgroup was chronic Type I and the best was acute Type III; recurrence worsened all outcomes. Chronic cases developed marked compensatory occiput-C1 separation (mean 31.2 degrees vs 5 degrees acute).
Pang - Atlantoaxial Rotatory Fixation: Normative CT Motion Analysis and Classification
- CT motion analysis in children aged 0-18 defined a highly concordant normal C1-C2 rotation curve (single-motion, double-motion and unison-motion phases). Against this template, three AARF types were defined by descending pathological stickiness (Type I locked regardless of counter-rotation; Type III crosses only with extreme counter-rotation), plus a diagnostic gray zone. A 3-position CT protocol allows both diagnosis and severity grading, with closed traction reduction recommended immediately and C1-C2 fusion for recurrent or irreducible cases.
Spinnato et al - AARS/F and Grisel's Syndrome in Children: Clinical and Radiological Prognostic Factors
- Across 55 children (mean age 8.5 years) treated conservatively over 15 years, 16.4% had late recovery (persistence or relapse at 3 months). A concomitant head/neck infection or inflammation (Grisel's syndrome) was the strongest predictor of late recovery (p less than 0.001). Fielding-Hawkins type (p = 0.019) and the measured C1-C2 rotation degree (p = 0.027) also correlated significantly with recovery time.
Zafarshamspour et al - Traumatic Atlantoaxial Rotatory Fixation in Adults: a Systematic Review of Published Cases
- Across 61 articles of adult AARF, mean age was about 36 years (54% male). Motor-vehicle accidents (38%) and falls (22%) were the leading mechanisms, and Fielding-Hawkins type I predominated (63%). Conservative management was used in 65% of acute and only 29% of chronic cases; acutely diagnosed patients were more often successfully treated conservatively, while chronically diagnosed patients more often required surgery. Neurological deficits were uncommon.