Bisphosphonates
Overview
Bisphosphonates are the most widely used anti-resorptive drugs in orthopaedic and metabolic bone practice, and the first-line pharmacological treatment for osteoporosis. They reduce bone turnover by inhibiting osteoclasts, which slows bone loss, raises bone mineral density and lowers fracture risk.
Three threads run through the topic and through the exam. How they work is a clean piece of basic science. What they prevent is backed by strong randomised evidence. What can go wrong is where the rare but heavily examined atypical femoral fracture and osteonecrosis of the jaw sit, and where the drug-holiday question comes from.
Indications
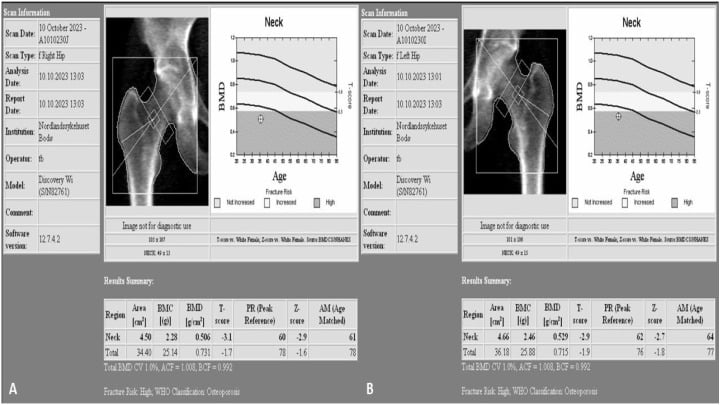
Osteoporosis is the commonest indication and the first-line pharmacological therapy for fracture prevention, covering postmenopausal, male and glucocorticoid-induced disease.
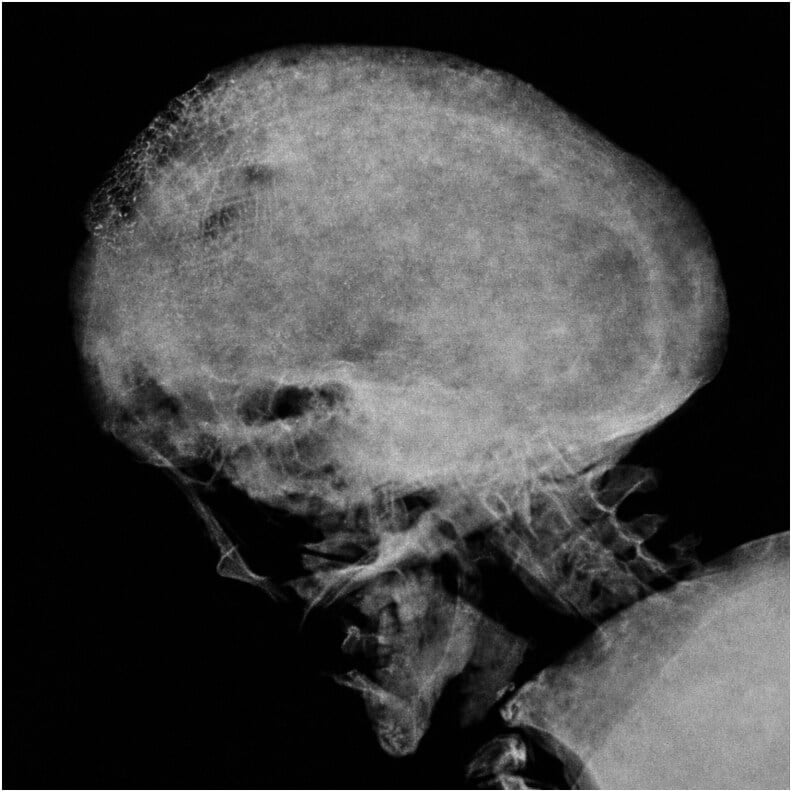
Paget disease of bone. Treatment reduces pain and disordered bone turnover, and a single zoledronic acid infusion gives durable suppression of the elevated alkaline phosphatase.
Malignancy. Bisphosphonates treat hypercalcaemia of malignancy and reduce skeletal-related events in bone metastases and multiple myeloma, usually at higher and more frequent dosing than in osteoporosis.
Paediatric practice. In moderate to severe osteogenesis imperfecta, cyclical intravenous pamidronate reduces fracture rate and bone pain.
Mechanism of Action
The molecule. Bisphosphonates are stable synthetic analogues of pyrophosphate, in which the central oxygen is replaced by a carbon atom — the P-C-P backbone. That carbon makes them resistant to enzymatic breakdown, and the two side chains divide the work between them: one, usually a hydroxyl, gives high affinity for bone mineral, while the second determines anti-resorptive potency.
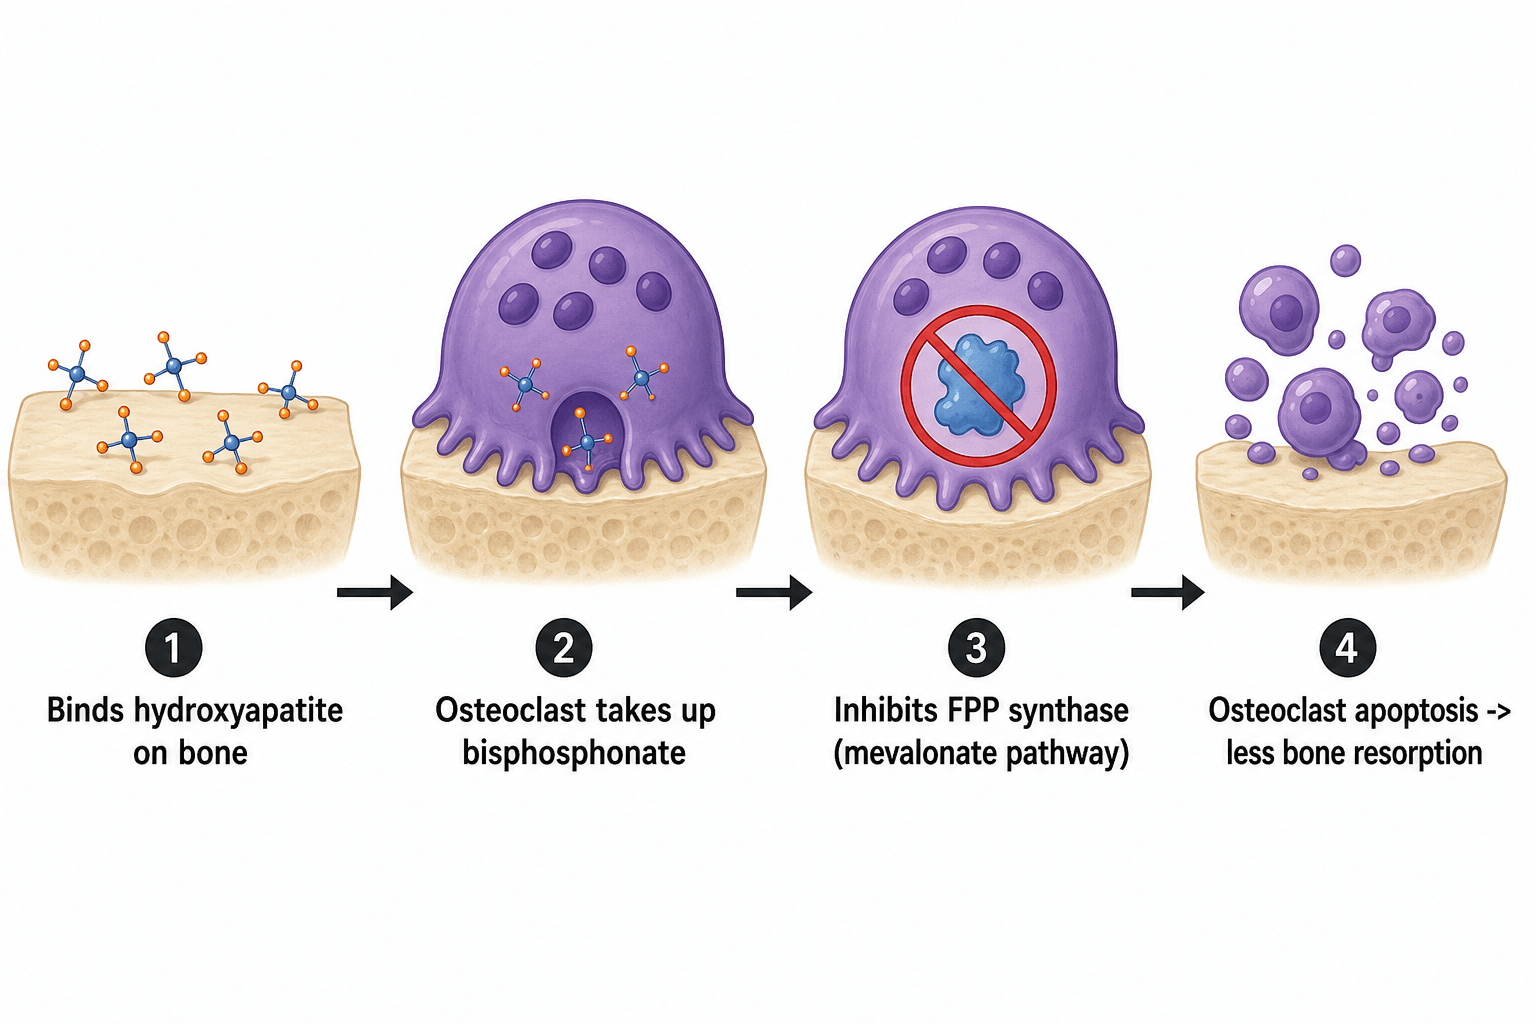
Getting into the cell. After absorption the drug binds hydroxyapatite at sites of active bone remodelling, where mineral is exposed. During resorption the osteoclast ingests bone mineral and takes the bound bisphosphonate in with it.
What happens inside. The drug disrupts osteoclast function, the ruffled border is lost, and the cell undergoes apoptosis. Osteoclast-mediated resorption falls, the remodelling space closes, secondary mineralisation continues, and bone mineral density rises.
Two chemical classes. The modern agents contain nitrogen and the older ones do not, and the two groups reach the same endpoint by different intracellular routes.
- Non-nitrogen (older)
- Etidronate, clodronate, tiludronate
- Nitrogen-containing (modern)
- Alendronate, risedronate, ibandronate, zoledronate
- Non-nitrogen (older)
- Incorporated into non-hydrolysable ATP analogues that poison the osteoclast
- Nitrogen-containing (modern)
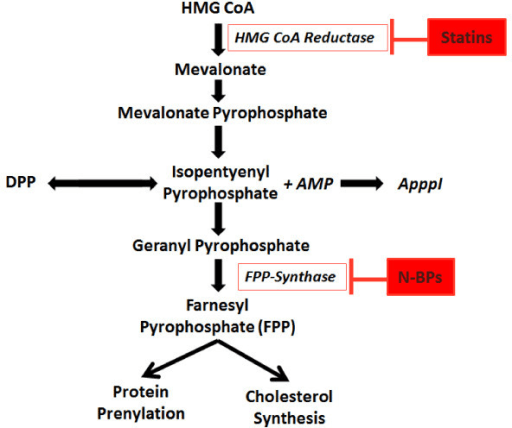
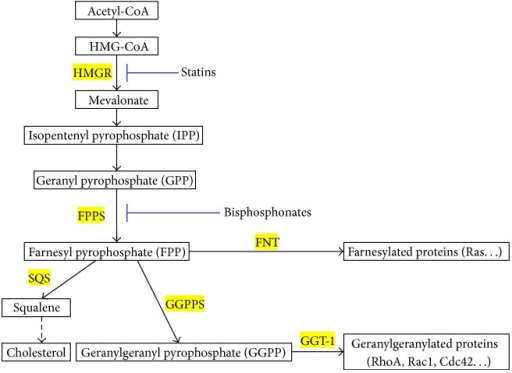
- Inhibit farnesyl pyrophosphate synthase in the mevalonate pathway
- Non-nitrogen (older)
- Direct cytotoxicity to the osteoclast
- Nitrogen-containing (modern)
- Loss of GTPase prenylation (Ras, Rho, Rac), so the osteoclast cannot ruffle or survive
- Non-nitrogen (older)
- Lower potency, largely historical
- Nitrogen-containing (modern)
- High potency, first-line agents today
The mevalonate step is the high-yield detail. Nitrogen-containing bisphosphonates block farnesyl pyrophosphate synthase, so the small GTPases the osteoclast depends on are never prenylated — never lipid-anchored to the membrane. Statins act on the same pathway higher up, at HMG-CoA reductase, which is a favourite linking question.
Agents, Potency and Routes
In osteoporosis the choice is between a weekly oral tablet and a yearly infusion; the non-nitrogen agents are largely historical.
- Class
- Nitrogen-containing
- Typical route and dose
- Oral 70mg weekly
- Notes
- Most widely used first-line oral agent
- Class
- Nitrogen-containing
- Typical route and dose
- Oral 35mg weekly
- Notes
- Alternative oral agent, similar efficacy
- Class
- Nitrogen-containing
- Typical route and dose
- IV 5mg once yearly (osteoporosis)
- Notes
- Most potent, useful if oral not tolerated
- Class
- Nitrogen-containing
- Typical route and dose
- IV infusion
- Notes
- Paget disease, hypercalcaemia, paediatric osteogenesis imperfecta
- Class
- Non-nitrogen
- Typical route and dose
- Oral
- Notes
- Older agent, can impair mineralisation if used continuously
Relative potency runs zoledronate greater than risedronate greater than ibandronate greater than alendronate greater than etidronate, reflecting both binding affinity for bone mineral and how strongly each inhibits the target enzyme.
Pharmacokinetics
Three things examiners link together come out of the pharmacokinetics: the strict oral regimen, the renal caution and the drug holiday.
Absorption. Oral bioavailability is under about 1 per cent, and it is further abolished by food, calcium and other cations, which chelate the drug. That is the pharmacological reason for the regimen: on an empty stomach after waking, with a full glass of plain water, upright for 30 to 60 minutes, and nothing else — food, calcium or other drugs — inside that window. Poor administration is the commonest cause of treatment failure and intolerance.
Distribution and elimination. Bisphosphonates are not metabolised, so there is no hepatic biotransformation and no cytochrome interaction. Roughly half the absorbed drug is taken up rapidly by bone at sites of active remodelling and the remainder is excreted unchanged by the kidney, which is why zoledronate is avoided at a low eGFR and given as a slow, well-hydrated infusion.
Two half-lives. The plasma half-life is short, but the skeletal half-life is extremely long — years, estimated at up to roughly a decade for alendronate — because the drug is buried in bone and only slowly liberated during later remodelling.
Why a pause is possible. That long skeletal residence is the basis of the drug holiday: fracture protection persists for a period after stopping because the bone-bound drug keeps acting. An agent that never binds bone cannot be treated the same way.
Complications
Most of what goes wrong is predictable from the pharmacology and is dealt with at the point of prescribing. The two that carry the exam weight are rare, duration-dependent, and have the rest of this section.
- Who and when
- Oral agents, poor administration
- Key point
- Prevented by the oral administration rules above
- Who and when
- First IV dose
- Key point
- Flu-like fever and myalgia for 1 to 3 days - warn and pre-hydrate
- Who and when
- Vitamin D deficient or untreated
- Key point
- Correct calcium and vitamin D before starting
- Who and when
- IV zoledronate
- Key point
- Avoid if eGFR is less than 35, infuse slowly, ensure hydration
- Who and when
- Long-duration use
- Key point
- Subtrochanteric or diaphyseal, transverse, thigh-pain prodrome
- Who and when
- IV / oncology dosing, dental work
- Key point
- Exposed necrotic jaw bone for more than 8 weeks
Atypical Femoral Fracture (AFF)
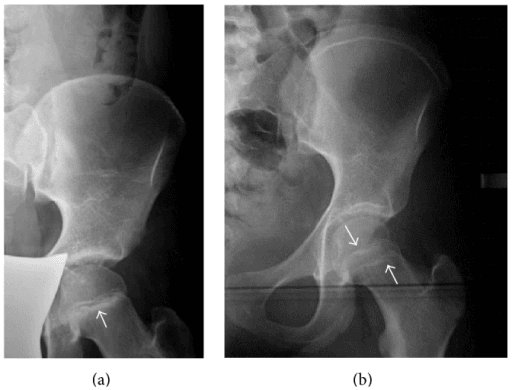
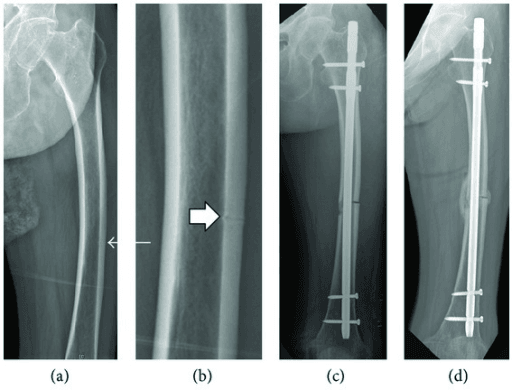
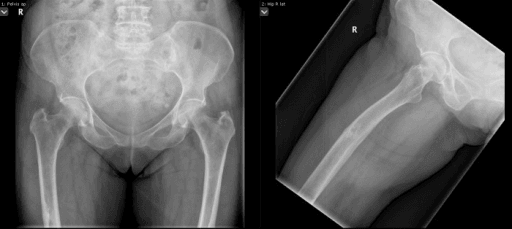
The pattern. AFFs occur in the subtrochanteric region or femoral diaphysis and look the part: a transverse or short-oblique fracture line that begins at the lateral cortex, focal thickening (beaking) of that lateral cortex, a medial spike, minimal comminution, and frequent bilateral involvement. The beaking is localised and lateral, on the tension side, which is what distinguishes it from the diffuse cortical thickening of chronic loading. Image the other femur in every case: a substantial minority are bilateral, and the second side is often still incomplete. These fractures heal slowly and fail fixation often, which is part of the risk calculus when the drug is stopped. Many patients describe prodromal thigh or groin pain for weeks to months.
The full diagnostic criteria and the operative management are on the atypical femoral fractures page. What belongs here is the drug question: how much risk the bisphosphonate actually adds, and what happens to that risk when it is stopped.
Say the numbers, not "low". "The risk is small but rises with duration" is the answer that gets probed, because the size and the shape of that rise are what decide whether a patient continues. Against less than 3 months of use, the adjusted hazard of AFF rises to 8.86 at 3 to under 5 years and 43.51 at 8 years or more — a steep, duration-driven curve. Yet the absolute risk stays very small and is dwarfed by what the drug prevents: over 3 years of treatment in white women, 149 hip fractures prevented for every 2 bisphosphonate-associated AFFs.
The risk is not banked. It falls rapidly once the drug is stopped rather than being locked in by the cumulative dose already given, which is precisely what makes a drug holiday a meaningful intervention rather than a gesture.
Ethnicity shifts the balance sharply. Asian women carry an adjusted hazard of 4.84 versus white women, and the same 3-year window yields 91 hip fractures prevented against 8 AFFs — still favourable, but a far narrower margin, and a real consideration in counselling. Other independent risk factors are glucocorticoid use, greater height and lower weight.
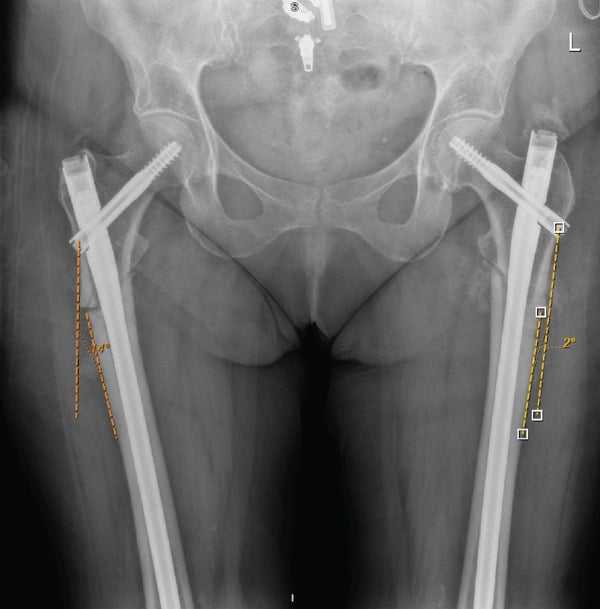
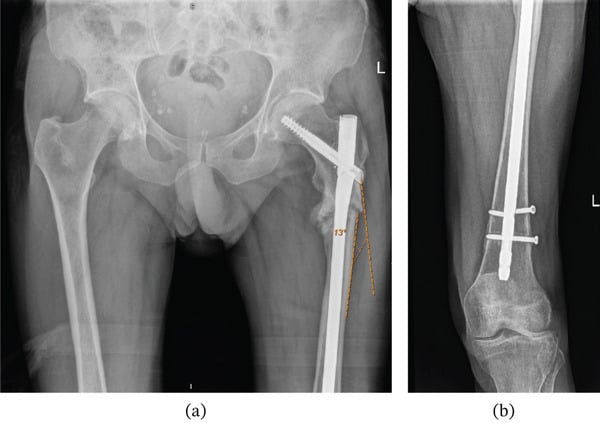
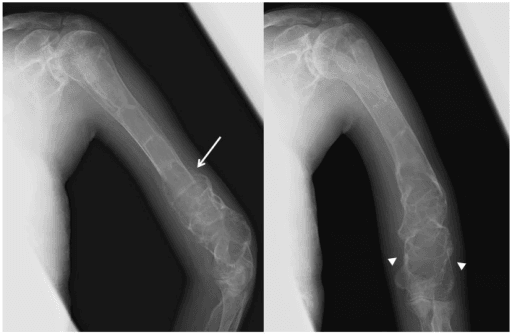
Atypical Femur Fracture Risk versus Fragility Fracture Prevention with Bisphosphonates
- 196,129 women aged 50+ on bisphosphonates, radiographically adjudicated fractures; 277 atypical femur fractures
- Adjusted hazard versus less than 3 months of use: 8.86 at 3 to under 5 years, rising to 43.51 at 8 years or more
- Risk fell rapidly after discontinuation - the excess risk is not fixed by cumulative dose already taken
- Asian versus white hazard ratio 4.84; glucocorticoid use, greater height and lower weight also independent
- Benefit dominates: over 3 years, 149 hip fractures prevented versus 2 atypical fractures in whites (91 versus 8 in Asians)
New or worsening thigh pain in a patient on a bisphosphonate is an atypical femoral fracture until proven otherwise - image BOTH femurs (full-length views). An incomplete AFF with pain often needs prophylactic intramedullary nailing; a complete fracture needs fixation.
Medication-Related Osteonecrosis of the Jaw (MRONJ)
The staging system, the surgical options and the dental-clearance pathway are covered on medication-related osteonecrosis of the jaw. The point that belongs to the drug is the dose gap: MRONJ is rare at osteoporosis dosing and an order of magnitude more common at oncology dosing, so the same molecule carries a very different consent conversation depending on why it is being given.
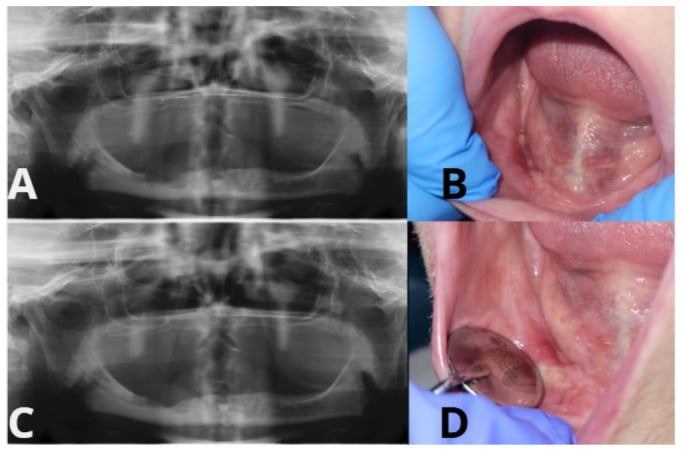
MRONJ Definition and Management (AAOMS Position Paper, 2022 Update)
- MRONJ: exposed jaw bone, or bone probed through a fistula, persisting for more than 8 weeks
- Occurs in a patient on antiresorptive or antiangiogenic therapy with no history of jaw radiotherapy
- Risk is markedly higher with intravenous and oncology-dose therapy and after dental extraction
- Prevention centres on dental assessment and treatment before starting therapy where feasible
The Drug Holiday
The rare complications are linked to cumulative duration, and the AFF risk falls once the drug is stopped, while the fracture benefit persists for a time after stopping because the bisphosphonate stays bound to bone. That asymmetry is what a holiday exploits, and guidelines suggest reassessing after about 3 to 5 years of oral therapy or 3 years of intravenous therapy.
- Lower risk patients (good bone density gain, no recent fracture): consider a drug holiday and reassess every 1 to 3 years
- Higher risk patients (previous hip or vertebral fracture, very low bone density, ongoing steroids): continue treatment, as the fracture-prevention benefit dominates
- Either way it is a pause with planned review, not permanent cessation: bone density and fracture risk are reassessed and treatment restarted when indicated
Where Bisphosphonates Sit Among Osteoporosis Drugs
Examiners frequently ask you to place bisphosphonates within the wider armamentarium and to contrast them with denosumab — the comparison that most often catches candidates out. The disease these drugs treat is on osteoporosis, with the steroid-driven form and its distinct treatment threshold on glucocorticoid-induced secondary osteoporosis; the two comparators with pages of their own are denosumab and teriparatide.
- Class / mechanism
- Anti-resorptive — FPP synthase inhibition
- Bound to bone?
- Yes
- Key exam point
- Effect persists after stopping; drug holiday possible
- Class / mechanism
- Anti-resorptive — monoclonal antibody to RANKL (blocks osteoclast formation)
- Bound to bone?
- No
- Key exam point
- Reversible; stopping causes a REBOUND with multiple vertebral fractures — no drug holiday
- Class / mechanism
- Anti-resorptive — selective oestrogen-receptor modulator
- Bound to bone?
- No
- Key exam point
- Reduces vertebral (not hip) fracture; lowers breast-cancer risk but raises VTE
- Class / mechanism
- Anabolic — PTH / PTHrP analogue (intermittent dosing builds bone)
- Bound to bone?
- No
- Key exam point
- For severe/high-risk disease; limited course (about 2 years); follow with an anti-resorptive
- Class / mechanism
- Dual — sclerostin monoclonal antibody (builds bone and reduces resorption)
- Bound to bone?
- No
- Key exam point
- Potent for very high risk; cardiovascular caution; follow with an anti-resorptive
Denosumab has NO drug holiday — this is the contrast examiners want. Because denosumab is a circulating antibody and is not bound to bone, its effect reverses completely on cessation: stopping (or even delaying) a dose triggers a rebound surge in bone turnover and a risk of multiple spontaneous vertebral fractures within months. Denosumab must therefore be continued indefinitely or, if stopped, followed promptly by a bisphosphonate to lock in the gains. Bisphosphonates are the exception precisely because they are buried in bone — which is why a planned holiday is safe for them but not for denosumab. (Anabolic agents — teriparatide, abaloparatide, romosozumab — must likewise be followed by an anti-resorptive, or their gains are lost.)
Guidelines, Registries and Global Practice
- Osteoporosis guidelines (for example AAOS/AOA bone-health initiatives, NICE/NOGG in the UK, and endocrine society guidance) consistently place bisphosphonates as first-line pharmacological therapy for fracture prevention, with intravenous zoledronate favoured where oral agents are not tolerated or adherence is poor.
- Fracture liaison services and bone-health programmes worldwide use bisphosphonates as the backbone of secondary fracture prevention after a fragility fracture.
- The drug holiday concept is endorsed across major guidelines as a way to balance long-term fracture benefit against the duration-dependent risks of AFF and MRONJ, with high-risk patients continued on therapy.
- MRONJ guidance (AAOMS position paper) standardises the definition, staging, and the emphasis on pre-treatment dental optimisation across settings.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 68-year-old woman with postmenopausal osteoporosis is started on weekly alendronate. The examiner asks you to explain how it works and what you would check and counsel before prescribing.”
“A 74-year-old woman on alendronate for 8 years reports several weeks of dull right thigh pain with no injury. She is still walking but the pain is worse on weight-bearing. How do you proceed?”
Mechanism
- Pyrophosphate analogues - bind hydroxyapatite, taken up by osteoclasts
- Nitrogen-containing: inhibit farnesyl pyrophosphate synthase (mevalonate pathway)
- Non-nitrogen: form toxic ATP analogues
- Net effect: less resorption, higher bone mineral density
Key Efficacy
- Zoledronic acid: vertebral fracture down about 70 percent, hip about 41 percent
- Alendronate: guideline-standard oral first-line agent
- First-line for osteoporosis fracture prevention
Before Prescribing
- Correct calcium and vitamin D
- Check renal function - avoid zoledronate if eGFR less than 35
- Oral: empty stomach, full glass of water, upright 30 to 60 minutes
- Arrange dental review where feasible
Red Flags
- Thigh pain on long-term therapy - image both femurs for AFF
- Exposed jaw bone for more than 8 weeks - MRONJ
- First IV dose flu-like acute phase reaction
- Reassess for a drug holiday at 3 to 5 years
Evidence for Fracture Prevention
Once-Yearly Zoledronic Acid Reduces Fractures (HORIZON-PFT)
- Double-blind RCT, 7765 postmenopausal women, annual 5mg zoledronic acid infusion vs placebo over 3 years
- Morphometric vertebral fracture reduced by about 70 percent (3.3 vs 10.9 percent)
- Hip fracture reduced by about 41 percent (1.4 vs 2.5 percent)
- Serious atrial fibrillation occurred more often with zoledronic acid (50 vs 20 patients)
Alendronate as the Standard Active Comparator (ARCH)
- RCT in 4093 high-risk postmenopausal women using oral alendronate 70mg weekly as the active comparator
- Confirms alendronate as an effective, guideline-standard anti-resorptive for fracture prevention
- Romosozumab followed by alendronate lowered new vertebral fracture by 48 percent versus alendronate alone
- Adjudicated osteonecrosis of the jaw and atypical femoral fracture were rare events in both arms