The Rarest Surface Osteosarcoma
- Surface (juxtacortical) osteosarcomas arise on the bone surface rather than within the medulla: parosteal (low-grade, commonest), periosteal (intermediate-grade) and high-grade surface (the rarest). They behave very differently and must not be lumped together.
- High-grade surface osteosarcoma behaves like conventional intramedullary osteosarcoma, with the aggressive behaviour, metastatic potential and prognosis of a high-grade osteosarcoma.
- Grade determines treatment and prognosis: low-grade parosteal lesions are treated by wide resection alone; high-grade surface and dedifferentiated parosteal lesions need systemic chemotherapy as well.
- The most-quoted series is 18 patients, only 4 of them high-grade surface: local recurrence 6 of 18, lung metastases 8 of 18, death 6 of 18 at a mean of 12 months, every death in a high-grade lesion.
- Response to chemotherapy was poor in all cases, but only 6 of the 18 received neoadjuvant chemotherapy - poor response in six treated patients, not established chemoresistance.
- Grade on a properly planned biopsy at the unit that will treat it, stage with local MRI and chest CT, then treat like conventional high-grade osteosarcoma: neoadjuvant and adjuvant chemotherapy around wide resection.
- “Three SURFACE (juxtacortical) osteosarcomas: PAROSTEAL (low-grade, commonest, posterior distal femur, best prognosis) - PERIOSTEAL (intermediate, chondroblastic, diaphyseal) - HIGH-GRADE SURFACE (rarest, behaves like conventional OS).
- “GRADE drives treatment: low-grade parosteal → WIDE RESECTION alone; high-grade surface (and dedifferentiated parosteal) → CHEMOTHERAPY + wide resection.
- “Quote the outcome figures with their denominator: in the standard 18-patient series (11 parosteal - 6 dedifferentiated, 3 periosteal, 4 high-grade surface; mean age 25, 61% female), local recurrence 6/18, lung metastases 8/18 and death 6/18 at a mean of 12 months, EVERY death in a high-grade lesion. The 'poor chemotherapy response' finding covers only the 6 patients who received it.
- “Properly planned biopsy + grading at a sarcoma unit; stage (MRI + chest CT); manage like conventional high-grade osteosarcoma. Don't treat a high-grade surface OS like a benign or low-grade surface lesion.
The Three Surface Osteosarcomas
Surface, or juxtacortical, osteosarcomas arise on the bone surface rather than within the medulla. There are three, of differing grade, and they behave so differently from one another that they must not be lumped together.
High-grade surface osteosarcoma. The rarest of the three. It is a high-grade malignancy that sits on the surface of the bone but behaves like conventional intramedullary osteosarcoma, with the same aggressive biological behaviour and metastatic potential, and it carries the worst prognosis of the three. The soft-tissue counterpart, with no bone attachment at all, is extraskeletal osteosarcoma.
Parosteal osteosarcoma. The commonest surface osteosarcoma, and low-grade. It is classically a "stuck-on" ossified mass on the posterior distal femur, indolent, with the best prognosis of the three. It can dedifferentiate, developing a high-grade component, and a dedifferentiated parosteal tumour is treated as high-grade.
Periosteal osteosarcoma. Intermediate-grade and chondroblastic, a surface lesion of the diaphysis.
Grade decides. Histological grade is the single most important point to assess in a surface osteosarcoma, because it determines both treatment and prognosis. Low-grade lesions are treated by wide resection alone; high-grade lesions, high-grade surface and dedifferentiated parosteal alike, need systemic chemotherapy in addition to wide resection.
- Parosteal
- Low
- Periosteal
- Intermediate
- High-grade surface
- High
- Parosteal
- Commonest surface OS
- Periosteal
- Less common
- High-grade surface
- Rarest
- Parosteal
- Posterior distal femur (metaphysis)
- Periosteal
- Diaphysis (tibia/femur)
- High-grade surface
- Long bones (femur/tibia)
- Parosteal
- Indolent (worse if dedifferentiated)
- Periosteal
- Intermediate
- High-grade surface
- Like conventional OS (metastasises)
- Parosteal
- Wide resection alone
- Periosteal
- Wide resection +/- chemotherapy
- High-grade surface
- Chemotherapy + wide resection
Presentation, Diagnosis & Management
Presentation. A surface bone mass, commonly of the long bones (femur or tibia), with the imaging features of a surface lesion.
Biopsy and grade. A properly planned biopsy, taken at the unit that will treat the patient, is mandatory before definitive surgery; the rules are set out in biopsy principles. Grading on that biopsy is decisive, separating high-grade surface from low-grade parosteal and intermediate periosteal osteosarcoma, and grading at a specialist sarcoma centre is essential.
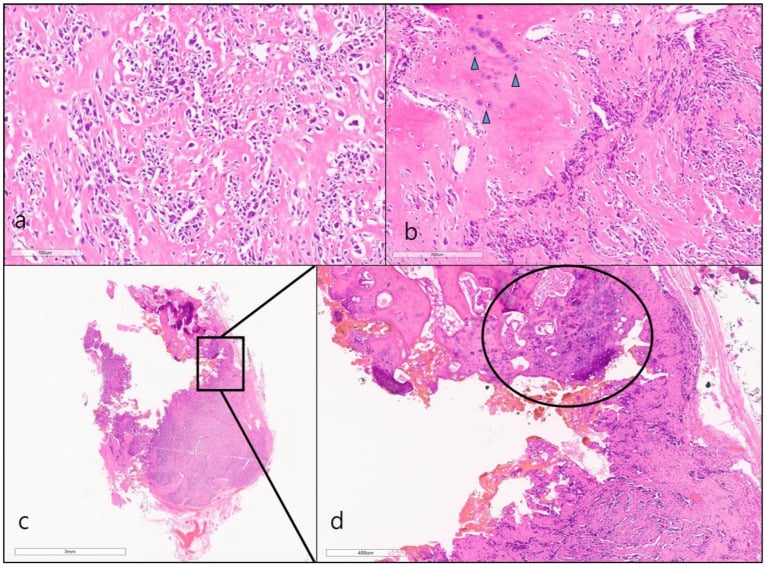
Staging. Local MRI and chest CT, because a high-grade tumour has metastatic potential.
Treating the high-grade lesion. Management mirrors that of conventional high-grade osteosarcoma: neoadjuvant and adjuvant chemotherapy around wide resection with clear margins, by limb salvage where feasible or otherwise amputation, in a specialist sarcoma multidisciplinary unit.
Treating the other two. Low-grade parosteal osteosarcoma can be cured by wide resection alone, which usually suffices. Examine the whole specimen, though: 6 of 11 parosteal tumours in the standard series had dedifferentiated, so a low-grade label on a surface lesion is not durable. Periosteal osteosarcoma is treated by wide resection, with chemotherapy often added.
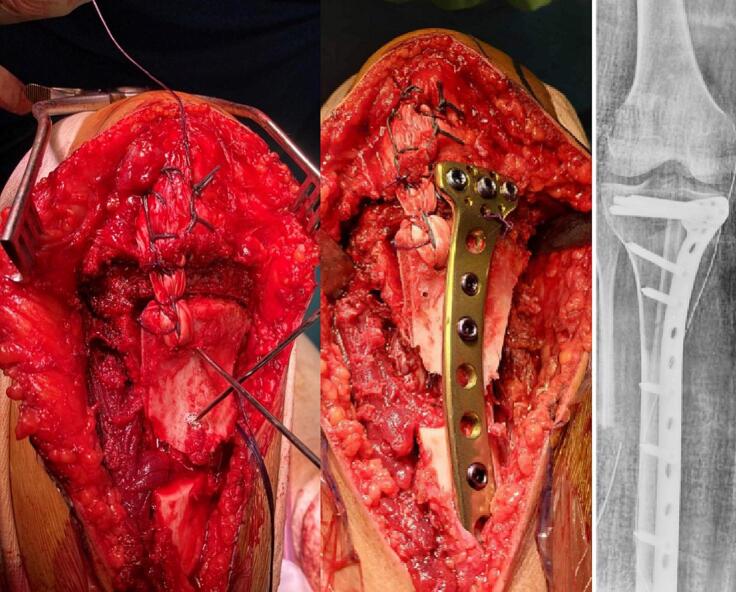
The danger with high-grade surface osteosarcoma is to mistake it for a benign surface lesion or for the indolent parosteal osteosarcoma, and so under-treat it. As with all bone sarcomas, an unplanned excision of an undiagnosed surface mass compromises subsequent limb salvage and outcome, so a suspected surface osteosarcoma must be referred before any surgery.
Imaging: Telling the Three Surface Osteosarcomas Apart
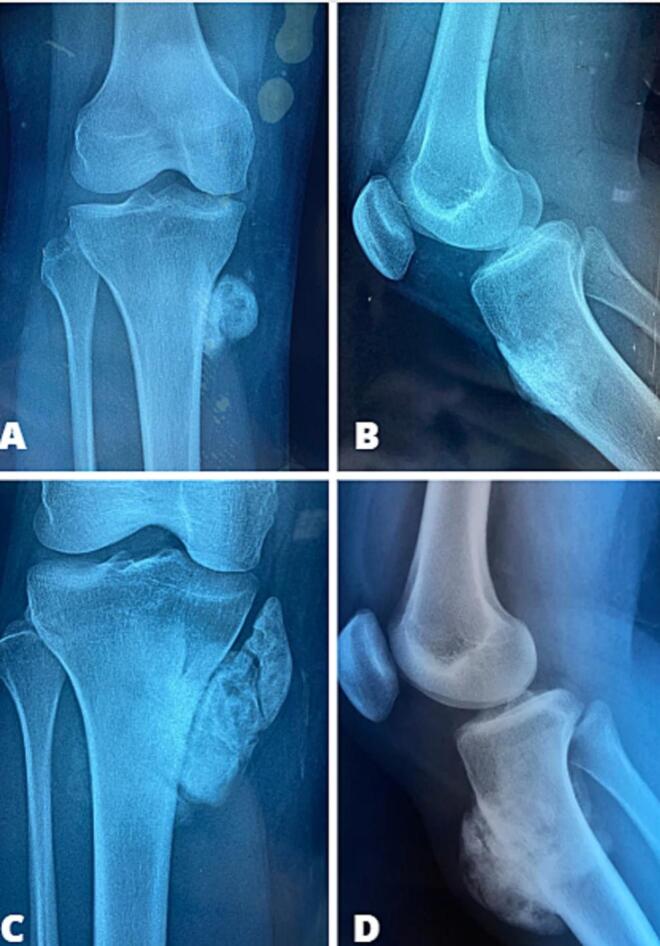
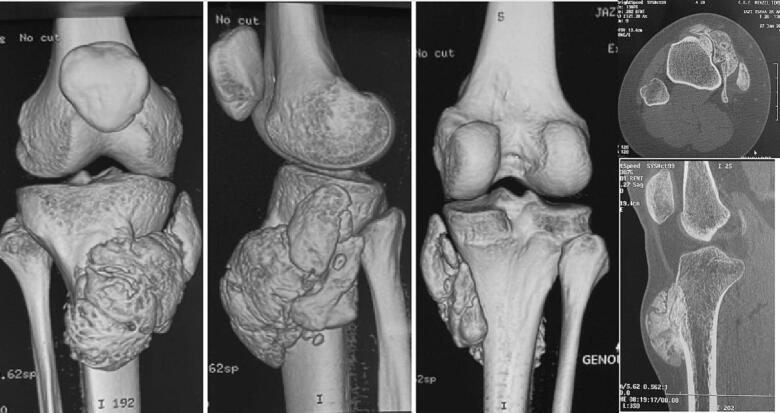
- Parosteal. A densely ossified, lobulated "stuck-on" mass on the posterior distal femoral metaphysis, with a radiolucent cleft (the cleavage plane) between the mass and the cortex and mineralisation densest centrally. CT or MRI looks for medullary invasion, which worsens the prognosis.
- Periosteal. A diaphyseal, broad-based surface mass with perpendicular spiculated, "sunburst" periosteal reaction and a Codman triangle, cortical thickening or scalloping at the base, and a chondroblastic matrix, less densely mineralised than parosteal.
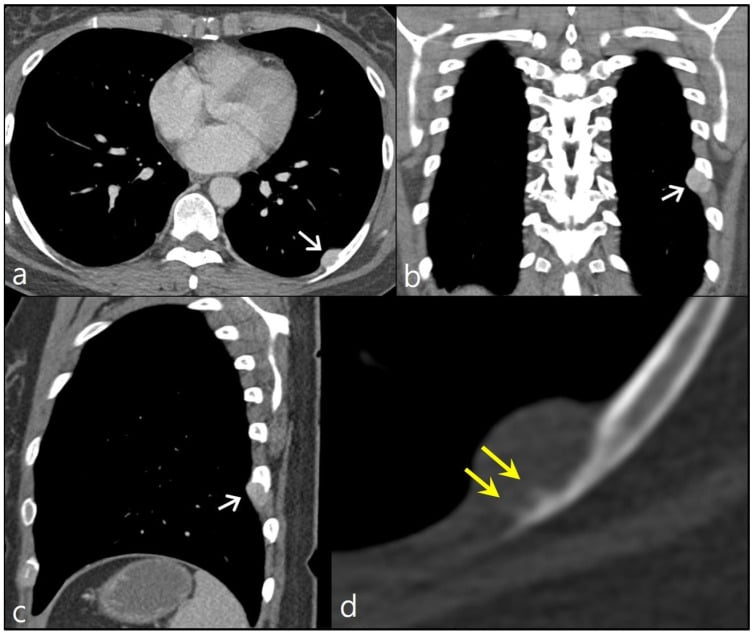
- High-grade surface. A more aggressive, destructive surface mass, with cortical destruction, an associated soft-tissue mass and often medullary extension, and variable, patchy mineralisation, resembling a conventional osteosarcoma sitting on the surface.
The Differential of a Surface Bone Lesion
The differential of a surface bone mass runs from benign lesions to malignant mimics.
- Myositis ossificans, the key benign mimic, shows zonal maturation: it matures from the periphery inwards, leaving a mature, ossified peripheral rim around a lucent centre, the reverse of parosteal osteosarcoma, which is dense centrally. It is separated from the cortex by a cleft and matures or regresses over time, so a history of trauma, the peripheral-rim pattern and serial maturation favour it.
- Osteochondroma shows cortico-medullary continuity with the parent bone, the pathognomonic feature, and a cartilage cap: a bony outgrowth, not a "stuck-on" mass.
- Other benign surface lesions, parosteal (juxtacortical) osteoma, surface (periosteal) chondroma and florid reactive periostitis, are well defined, without an aggressive soft-tissue mass.
- Malignant surface mimics are surface or periosteal chondrosarcoma, with its chondroid matrix, part of the wider chondrosarcoma family, and dedifferentiated parosteal osteosarcoma.
The rule. Any surface bone mass with aggressive features (cortical destruction, a soft-tissue component, medullary extension) or an atypical maturation pattern is biopsied at a sarcoma unit, not assumed benign.
The Outcome Figures - and How Few Patients They Rest On
The teaching that grade determines everything in surface osteosarcoma comes largely from one retrospective series from two Tunisian centres: 18 patients over seven years, 11 parosteal (6 of them dedifferentiated), 3 periosteal and only 4 high-grade surface. Mean age was 25 years (16 to 55) and 61 percent were female, with 11 femoral and 7 tibial lesions. At a mean follow-up of 34.5 months, 6 of 18 (33.3 percent) recurred locally, 8 of 18 (44.4 percent) developed lung metastases, and 6 of 18 (33.3 percent) died at a mean of only 12 months, and every death was in a patient with a high-grade lesion. That observation is genuinely important and is the right thing to quote, but a candidate who adds "in a series of eighteen" gives the better answer.
The chemoresistance claim is thinner still. "Histological response to chemotherapy was poor in all cases" is repeated widely, but only 6 of those 18 patients received neoadjuvant chemotherapy. The finding is poor response in six treated patients, not a demonstration that surface osteosarcoma is chemoresistant, and no trial compares regimens in this entity. It is a reason to temper expectation, not to withhold treatment from a high-grade lesion.
The margins. Three of the 18 resections were intralesional, which is the margin failure that surface tumours invite when they are mistaken for something benign and shelled out.
Mnemonics & Memory Aids
GRADEGrade Sets the Operation - GRADE
Hook:GRADE decides it: low-grade resected, high-grade gets chemo plus resection - and the dedifferentiated parosteal hides in the low-grade pile.
ZONALThe Benign Mimics - ZONAL
Hook:ZONAL maturation is the benign signature - peripheral rim, lucent centre, a cleft from the cortex; destruction or atypical maturation goes to biopsy.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A surface bone lesion of the femur is reported as a surface osteosarcoma. Why does the grade matter, and how would you manage a high-grade surface variant?”
Surface osteosarcomas
- Parosteal: low-grade, commonest, posterior distal femur, best prognosis - but can dedifferentiate (6 of 11 in one series)
- Periosteal: intermediate-grade, chondroblastic, diaphyseal
- High-grade surface: rarest, behaves like conventional OS
Key principle
- Histological grade determines treatment and prognosis
- Grade on a planned biopsy at a sarcoma unit
- In the standard 18-patient series: recurrence 33 percent, lung metastases 44 percent, death 33 percent - all deaths high-grade
- 'Poor chemo response' derives from the 6 of 18 who actually received it
Management
- High-grade surface OS: like conventional OS - neoadjuvant/adjuvant chemo + wide resection
- Stage: local MRI + chest CT
- Low-grade parosteal: wide resection alone
Evidence & Key Studies
Surface osteosarcoma: clinical features and therapeutic implications
- Retrospective bicentric Tunisian series of 18 surface osteosarcomas treated between 2006 and 2013: 11 parosteal (6 of them dedifferentiated), 3 periosteal and 4 high-grade surface. Mean age 25 years (range 16 to 55), 61 percent female; 11 lesions in the femur and 7 in the tibia.
- All 18 were resected - margins wide in 15 and intralesional in 3 - but only 6 received neoadjuvant chemotherapy. Histological response to chemotherapy was poor in all of those 6, which is the basis of the widely repeated claim that these tumours respond poorly.
- At a mean follow-up of 34.5 months, 6 patients (33.3 percent) had a local recurrence, 8 (44.4 percent) developed lung metastases, and 6 (33.3 percent) died of disease at a mean of 12 months (range 6 to 30) - all of the deaths occurring in patients with high-grade lesions. The series is small, retrospective and from two centres, and its 4 high-grade surface cases cannot establish outcomes for that subtype on their own.
High grade surface osteosarcoma: a clinicopathologic study of 46 cases
- The largest series of the actual entity: 46 high-grade surface osteosarcomas (13 Mayo Clinic, 33 from the authors' files), comprising only 8.9% of surface osteosarcomas at the study institution.
- Definite male predominance; 70% of patients in the second and third decades; 44 of 46 in long bones, the mid-femur commonest; histology identical to conventional osteosarcoma.
- Five-year survival 46.1%; marginal excision independently increased local recurrence, and Broders grade 3 fared worse.
- The authors' conclusion: prognosis is SIMILAR TO CONVENTIONAL osteosarcoma, and wide excision plus effective systemic chemotherapy are associated with better outcomes.
Parosteal osteosarcoma: a clinicopathological study of 226 cases
- The reference parosteal series: 226 patients (67 managed at the Mayo Clinic, 159 from consultation files), defined as well-differentiated (grade 1-2) surface lesions with less than 25% medullary involvement.
- Dedifferentiation occurred in 16% - MORE common than previously reported - and carried a poor prognosis.
- Cross-sectional imaging showed medullary involvement in 22%, which is why CT/MRI assessment of the medulla matters before resection.
Periosteal osteosarcoma - a European review of outcome (EMSOS)
- European Musculo-Skeletal Oncology Society collaborative dataset of 119 periosteal osteosarcomas - the intermediate-grade member of the surface family; femur then tibia predominated.
- All but 2 patients had surgery (9 amputations, the rest limb salvage); 81 had chemotherapy, 50 of them neoadjuvant, all doxorubicin-based but with no standard regimen.
- Overall survival 89% at 5 years and 83% at 10 years - markedly better than conventional or high-grade surface osteosarcoma.
- The value of chemotherapy in periosteal osteosarcoma remained unresolved - the honest position between 'resection alone' and 'always add chemo'.
The classification of surface osteosarcomas into parosteal, periosteal and high-grade surface variants with differing behaviour, the central role of histological grade in determining treatment and prognosis, the poor chemotherapy response, and the worse outcome of high-grade lesions come from the cited Nouri series. The specific features of parosteal (low-grade, posterior distal femur, dedifferentiation) and periosteal (intermediate-grade, chondroblastic, diaphyseal) osteosarcoma, the staging/biopsy principles, and management of high-grade surface OS like conventional osteosarcoma are standard, well-established teaching. That series is retrospective, from two centres, and contains only 4 high-grade surface tumours and 6 patients who received chemotherapy, so its recurrence, metastasis and mortality proportions describe surface osteosarcoma as a whole rather than the high-grade subtype specifically. The subtype anchors are now cited: high-grade surface survival (46.1% at 5 years, marginal excision driving recurrence) from the Okada 46-case series, parosteal dedifferentiation (16%) and medullary involvement (22%) from the Okada 226-case series, and periosteal survival (89% at 5 years) from the EMSOS review. Beyond these there is no trial comparing chemotherapy regimens in surface disease, and no agreed proportion that each of the three subtypes contributes - the ordering parosteal, periosteal, high-grade surface by frequency is the conventional teaching rather than a figure from a defined population.