Six-axis simultaneous correction via a Stewart-Gough platform and web-based software
- The hexapod is a Stewart-Gough platform: any position of one ring relative to the other in 6 degrees of freedom (3 translations, 3 rotations) is achievable purely by changing the six strut lengths — no physical hinges.
- Deformity analysis precedes frame application: CORA on standing long-leg films, joint orientation angles (mLDFA 85-90 degrees, MPTA 85-90 degrees, PPTA 77-84 degrees), and CT rotational profile.
- Software needs three data sets: deformity parameters (6), frame parameters (ring sizes, strut numbers/lengths), and mounting parameters (reference ring position relative to the origin/CORA).
- Residual deformity is corrected by re-measuring and re-programming a new schedule — the decisive advantage over classical Ilizarov hinges, which require physical hinge repositioning.
- Correction speed is limited by the distraction rate at the regenerate (about 1 mm per day at the fastest-moving cortex) and by soft-tissue tolerance, particularly nerve stretch in lengthening and rotation.
- Low-energy osteotomy (percutaneous corticotomy or Gigli saw) preserves periosteum and endosteal blood supply and is essential for reliable regenerate formation.
- “The 1 mm/day rule applies to the fastest-distracting point of the osteotomy, not the axis of the frame — in angular correction the convex cortex moves fastest and governs the schedule.
- “Rotational correction stretches nerves circumferentially: external rotation of the distal tibia tensions the common peroneal nerve — monitor for first web space sensory change.
- “Steady-state healing index: months of frame time per centimetre of lengthening; typically 1 to 1.5 months per cm in adults, faster in children.
- “Premature consolidation presents as sudden strut pain and rising strut loads mid-programme — confirm on radiographs and re-osteotomise if the regenerate has bridged.
An inaccurate CORA or mounting parameter set produces secondary translation or an unexpected residual deformity. The frame does exactly what it is told — garbage in, garbage out. Always verify with intra-operative imaging and repeat long-leg films early in correction.
Lengthening greater than about 1 mm/day or rapid rotational correction risks traction neuropathy (peroneal nerve at the fibular neck most classically). New neurological symptoms mandate slowing or temporarily reversing the programme, not analgesia alone.
Femoral lengthening can sublux the knee and hip (especially with pre-existing dysplasia or cruciate deficiency); tibial lengthening drives equinus and can sublux the ankle. Prophylaxis: spanning the joint, aggressive physiotherapy, and radiographic joint surveillance every visit.
Removing the frame before three cortices show mature regenerate on orthogonal views risks fracture or re-deformation. Dynamise the frame or destabilise struts before removal; consider prophylactic bracing or conversion to internal fixation in poor regenerate.
Principle: The Stewart-Gough Platform
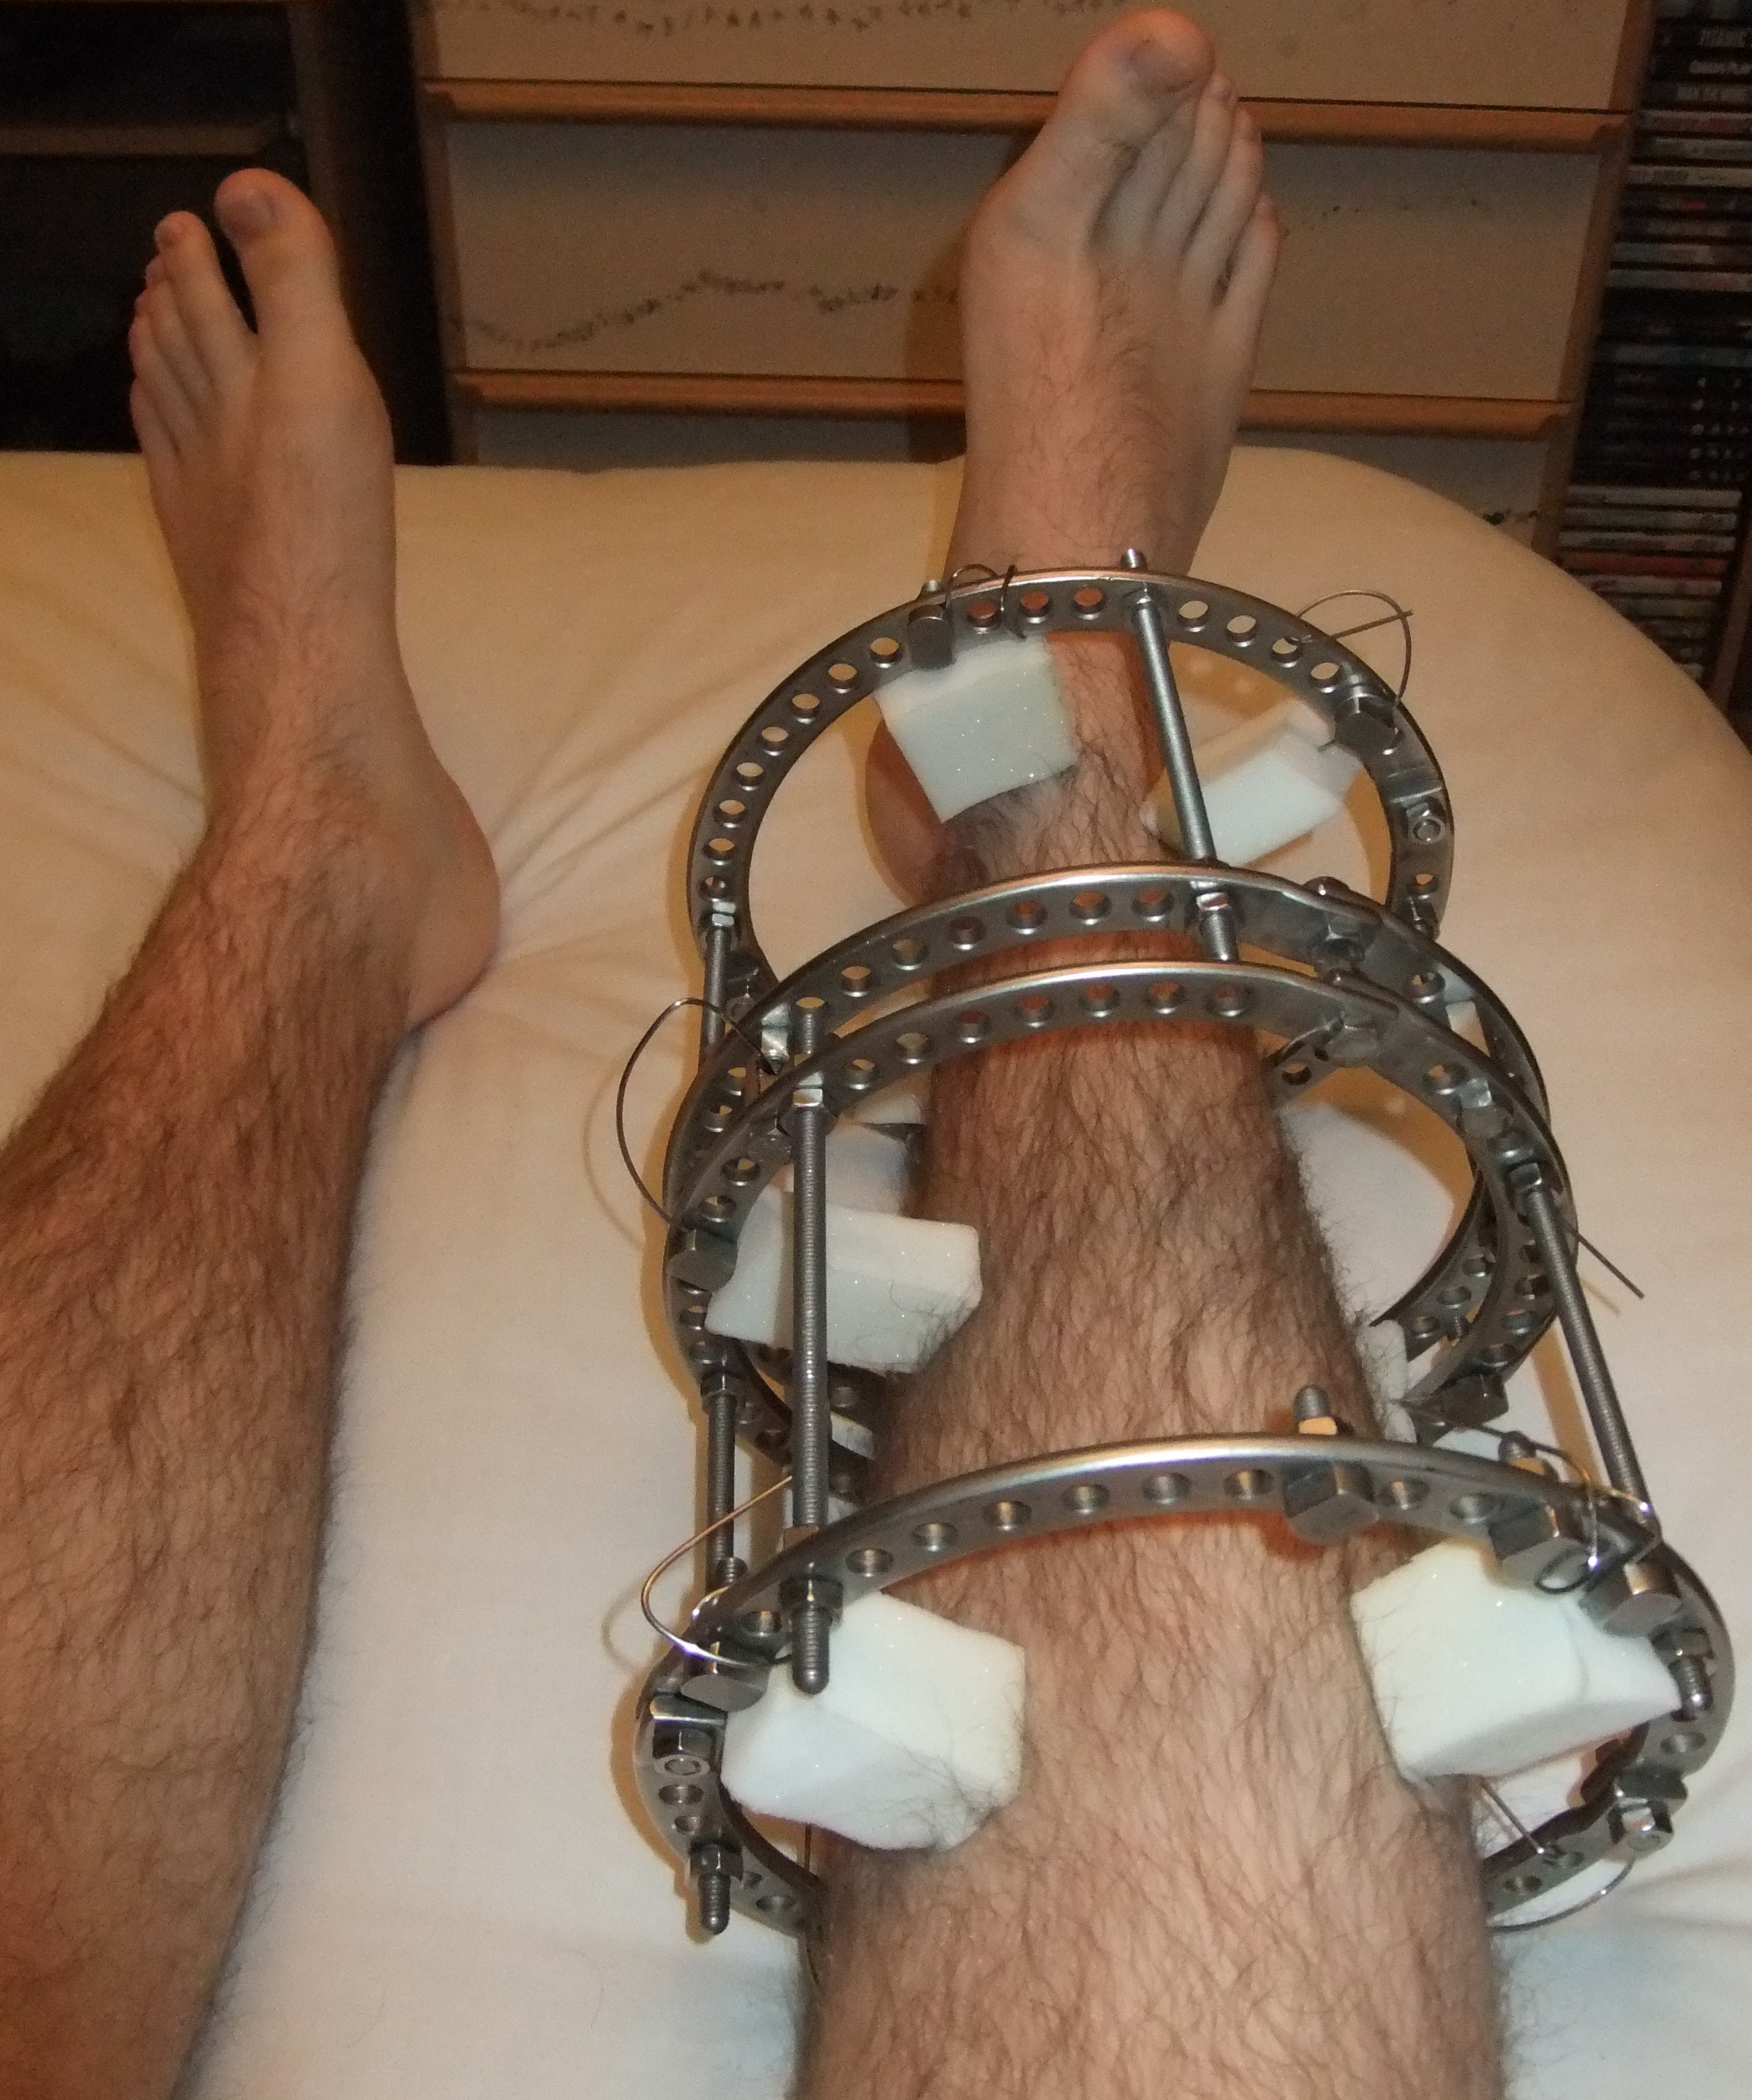
Classical Ilizarov correction uses rings connected by threaded rods and physical hinges placed at the CORA. Each additional plane of deformity requires additional hinges, and any hinge malposition produces secondary deformity that requires the frame to be dismantled and re-built.
The hexapod concept (Taylor Spatial Frame and equivalents such as TL-Hex and Orthex) replaces rods and hinges with six oblique telescopic struts connecting two rings at special joints — a Stewart-Gough platform, the same kinematic architecture used in flight simulators.
- Because the six struts define the position of one ring relative to the other in all six degrees of freedom (coronal angulation and translation, sagittal angulation and translation, axial rotation, and length), any combination of deformities can be corrected simultaneously by an appropriate schedule of strut length changes.
- The surgeon enters the deformity into web-based software; the software outputs a daily strut adjustment prescription for the patient to perform.
- The mathematical hinge exists only in software — the "virtual hinge" — and can be placed anywhere in space (including outside the frame, e.g. at the ankle joint for foot correction) without any hardware change.
Chronic vs total residual programmes: the deformity can be entered as the original deformity (chronic correction from day one) or, after acute partial correction on the table, the residual deformity can be measured on post-operative radiographs and a total residual programme generated. The residual method is forgiving of mounting imprecision and is the workhorse technique in most units.
Deformity Analysis: The Non-Negotiable Prerequisite
Standing long-leg alignment radiograph (hip to ankle, patellae forward, calibrated):
- Mechanical axis: line from centre of femoral head to centre of ankle plafond. Normally passes just medial to the centre of the knee (about 8 mm medial, or within the middle of the tibial spines). Mechanical axis deviation (MAD) quantifies malalignment.
- Joint orientation angles (Paley method — draw the mechanical axis of each segment and the joint orientation line, measure the angle on the named side):
- mLDFA (mechanical lateral distal femoral angle): normal 85 to 90 degrees (mean 87). Abnormal value localises deformity to the distal femur.
- MPTA (medial proximal tibial angle): normal 85 to 90 degrees (mean 87). Low MPTA = tibial varus (e.g. Blount disease).
- LDTA (lateral distal tibial angle): normal 86 to 92 degrees.
- Sagittal: PPTA (posterior proximal tibial angle) normal 77 to 84 degrees (tibial slope); PDFA (posterior distal femoral angle) normal about 79 to 87 degrees.
- CORA (centre of rotation of angulation): intersection of the proximal and distal segment axes. Malorientation of a joint line with normal diaphyseal axes places the CORA at juxta-articular level.
Osteotomy rules (Paley):
- Rule 1: osteotomy and hinge (virtual hinge) through the CORA — pure angular correction, axes realign without translation.
- Rule 2: hinge at the CORA but osteotomy at a different level — correction produces intentional translation that keeps the axes co-linear.
- Rule 3: hinge away from the CORA — creates secondary translational deformity. With a hexapod this is avoided by programming the virtual hinge at the true CORA regardless of where the frame or osteotomy sits.
Operative Technique
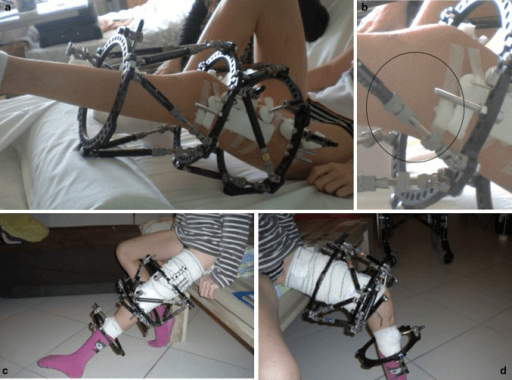
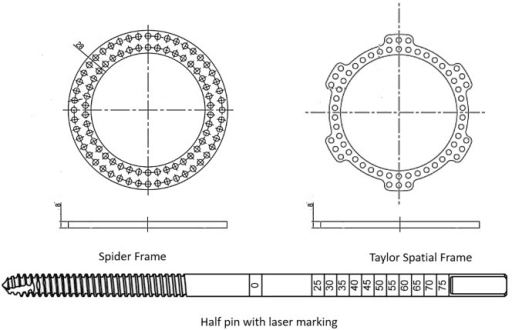
Hexapod frame: theatre set-up to frame removal
Supine on a radiolucent table with a bump under the ipsilateral buttock for tibial work to neutralise rotation. Image intensifier from the opposite side; obtain true AP and lateral of the segment before draping. Tourniquet available but usually not inflated for the corticotomy — bleeding bone confirms the low-energy technique is safe.
Rings sized for two fingerbreadths of circumferential soft-tissue clearance, more posteriorly in the calf to allow for swelling. Mount the reference ring orthogonal to the reference fragment on both AP and lateral views and centred — this dramatically simplifies the mounting parameters. Fix each ring with fine tensioned wires at 90 to 130 kg tension plus hydroxyapatite-coated half pins, respecting safe corridors (tibia: anteromedial face for half pins), avoiding the anterior compartment neurovascular structures and transfixion of muscle bellies.
Osteotomy performed after frame application so the fragments stay controlled. Percutaneous technique: 1 cm incision, minimal periosteal elevation, multiple drill holes across the cortex with a sharp drill under saline cooling, completed with an osteotome; alternatively pass a Gigli saw subperiosteally and cut under tension. Confirm completeness by gently distracting or rotating through the frame under imaging. Never use a power saw — thermal necrosis kills the regenerate.
Common peroneal nerve at the fibular neck with proximal tibial wires and fibular osteotomy; saphenous vein and nerve medially; posterior tibial neurovascular bundle with transfixion wires; superficial peroneal nerve in the distal third. In the femur, avoid excessive quadriceps transfixion (knee stiffness) and respect the femoral vessels medially.
Loose skin closure at the corticotomy and release of any tented skin around wires and pins. Record strut numbers and acute settings. Post-operative orthogonal radiographs give the mounting and residual deformity parameters from which the correction schedule is generated.
Latency of 5 to 10 days before distraction begins — shorter in children, longer in poor hosts. No strut adjustment during this window.
Patient-performed strut adjustments 3 to 4 times daily following the printed prescription, totalling about 1 mm per day at the fastest-moving cortex. Full weight bearing as tolerated in the tibia. Radiographs every 1 to 2 weeks during correction. The 1 mm per day rule is a starting point: slow the programme for wispy or absent callus on the regenerate check film, neurological symptoms, uncontrolled pain, or a joint contracture progressing despite physiotherapy; accelerate cautiously in children or when premature consolidation threatens.
The frame stays until the regenerate shows mature bridging on at least three of four cortices on orthogonal views. Consider dynamisation by loosening the struts before removal, and test with a period of strut disconnection or clinical stress if in doubt. Remove in clinic or as day surgery; brace with graduated loading for 4 to 6 weeks afterwards.
tibial malunion/nonunion with deformity (particularly multiplanar or with shortening, infection or poor soft tissues), gradual correction of Blount disease, congenital pseudarthrosis of the tibia, deformity correction combined with lengthening, complex foot deformity (with foot "butt" frame constructs), acute fractures with severe soft-tissue injury where staged correction is anticipated.
patient/family unable to comply with strut adjustments and pin care, severe psychiatric illness, heavy smoking and uncontrolled diabetes (regenerate failure risk — optimise first), uncorrectable vascular insufficiency.
Why hexapod over acute correction (plate/nail)? Gradual correction protects soft tissues and nerves in large or multiplanar deformities, allows simultaneous lengthening, permits weight bearing throughout, works in infected or previously infected bone without internal implants, and residual deformity is correctable without re-operation.
Supine on a radiolucent table, bump under ipsilateral buttock for tibial work to neutralise rotation. Image intensifier from the opposite side; obtain true AP and lateral of the segment. Tourniquet available but usually not inflated for corticotomy (bleeding confirms low-energy technique is safe).
Choose rings allowing two fingerbreadths of circumferential soft-tissue clearance (more posteriorly in the calf to allow for swelling). Mount the reference ring orthogonal to the reference fragment on both AP and lateral views — an orthogonal, centred reference ring dramatically simplifies mounting parameters. Fix each ring with a combination of fine tensioned wires (90 to 130 kg tension) and hydroxyapatite-coated half pins, respecting safe corridors (tibia: anteromedial face for half pins; avoid the anterior compartment neurovascular structures and transfixion of muscle bellies where possible).
Perform the osteotomy after frame application so the fragments are controlled. Percutaneous technique: 1 cm incision, elevate periosteum minimally, multiple drill holes across the cortex with a sharp drill under saline cooling, complete with an osteotome ('corticotomy') — or pass a Gigli saw subperiosteally and cut under tension. Confirm completeness by gently distracting or rotating through the frame under imaging. Avoid power saws: thermal necrosis kills the regenerate.
Common peroneal nerve at the fibular neck (proximal tibial wires and fibular osteotomy), saphenous vein/nerve medially, posterior tibial neurovascular bundle with transfixion wires, superficial peroneal nerve in the distal third. In the femur: avoid transfixing quadriceps excessively (knee stiffness) and respect the femoral vessels medially.
Loose skin closure at the corticotomy, release any tented skin around wires/pins. Record strut numbers and acute settings. Post-operative orthogonal radiographs for mounting/residual deformity measurement; generate the correction schedule.
Latency 5 to 10 days (shorter in children, longer in poor hosts), then patient-performed strut adjustments 3 to 4 times daily per the printed prescription, totalling about 1 mm/day at the fastest-moving cortex. Full weight bearing as tolerated in the tibia. Radiographs every 1 to 2 weeks during correction.
After correction, the frame remains until the regenerate shows mature bridging on at least three of four cortices on orthogonal views. Consider dynamisation (loosening struts) before removal; test with a period of strut disconnection or clinical stress if in doubt. Remove in clinic or day surgery; brace and graduated loading for 4 to 6 weeks after removal.
The 1 mm/day rule is a starting point, not a law. Slow the programme for: poor regenerate (wispy or absent callus on the "regenerate check" film), neurological symptoms, uncontrolled pain, or joint contracture progressing despite physiotherapy. Accelerate cautiously in children or when premature consolidation threatens.
Hexapod vs Ilizarov vs Acute Internal Correction
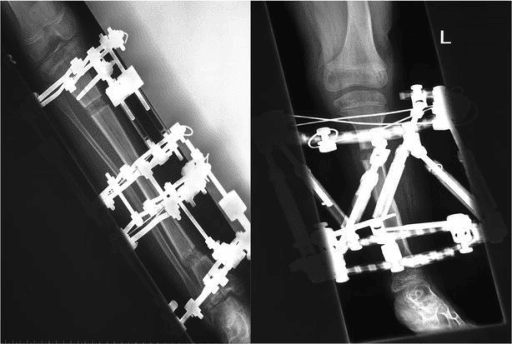
- Hexapod frame
- Simultaneous 6-axis correction delivered as a single software programme
- Classical Ilizarov hinges
- Sequential corrections; hinges physically repositioned for each plane
- Acute correction (plate or nail)
- Difficult to execute; real risk of under-correction and residual translation
- Hexapod frame
- Re-programme only — the 'virtual hinge' is moved in software, no return to theatre
- Classical Ilizarov hinges
- Physical hinge re-siting means a frame rebuild
- Acute correction (plate or nail)
- Revision surgery required
- Hexapod frame
- Yes, integrated into the same correction programme
- Classical Ilizarov hinges
- Yes
- Acute correction (plate or nail)
- Limited — lengthening nails are a separate technology
- Hexapod frame
- Gradual distraction is protective of nerve and skin
- Classical Ilizarov hinges
- Gradual distraction is protective
- Acute correction (plate or nail)
- Acute stretch risk; restricted to modest-magnitude corrections
- Hexapod frame
- Excellent — no internal implant left in the zone
- Classical Ilizarov hinges
- Excellent
- Acute correction (plate or nail)
- Relative contraindication
- Hexapod frame
- Months in frame, daily strut adjustments, ongoing pin-site care
- Classical Ilizarov hinges
- Months in frame
- Acute correction (plate or nail)
- Short recovery, no external frame
- Hexapod frame
- Software planning plus accurate mounting-parameter measurement are critical
- Classical Ilizarov hinges
- Hinge geometry demanding to plan and place
- Acute correction (plate or nail)
- Familiar to most surgeons
- Hexapod frame
- Complex multiplanar or rotational deformity, deformity with shortening, infected or poor-quality bone
- Classical Ilizarov hinges
- Multiplanar correction where hexapod struts are unavailable or cost-limited
- Acute correction (plate or nail)
- Uniplanar deformity of modest magnitude in healthy soft tissues
- Hexapod frame
- Simultaneous 6-axis correction, one programme
- Classical Ilizarov hinges
- Sequential corrections; hinges repositioned per plane
- Acute correction (plate/nail)
- Difficult; risk of under-correction
- Hexapod frame
- Re-programme only ('virtual hinge')
- Classical Ilizarov hinges
- Physical hinge re-siting — frame rebuild
- Acute correction (plate/nail)
- Revision surgery required
- Hexapod frame
- Yes, integrated in programme
- Classical Ilizarov hinges
- Yes
- Acute correction (plate/nail)
- Limited (lengthening nails separate technology)
- Hexapod frame
- Gradual — protective
- Classical Ilizarov hinges
- Gradual — protective
- Acute correction (plate/nail)
- Acute stretch risk; limited to modest corrections
- Hexapod frame
- Excellent — no internal implant
- Classical Ilizarov hinges
- Excellent
- Acute correction (plate/nail)
- Relative contraindication
- Hexapod frame
- Months in frame, daily adjustments, pin care
- Classical Ilizarov hinges
- Months in frame
- Acute correction (plate/nail)
- Short recovery, no frame
- Hexapod frame
- Software planning and mounting accuracy critical
- Classical Ilizarov hinges
- Hinge geometry demanding
- Acute correction (plate/nail)
- Familiar to most surgeons
Comparative series show hexapod frames achieve more accurate correction of complex multiplanar deformity than hinged Ilizarov constructs, at the cost of strut hardware expense; acute correction with internal fixation remains appropriate for uniplanar deformities of modest magnitude in healthy soft tissues.
Pin-Site Care and Infection Grading
Some degree of pin-site inflammation or infection is near-universal over a treatment course of many months — patients must be counselled and taught structured pin care. Two parts of the usual prescription are worth separating, because the evidence treats them very differently.
- Frequency: it probably does not matter. The only randomised comparison (W-Dahl, 50 patients) found no difference between daily and weekly pin-site care in infection frequency or severity, in pain, or in antibiotic use. Set the interval by what the patient will actually sustain across six months in a frame, not by reflex.
- Solution: it does. In the same unit's comparative study, 2 mg/ml chlorhexidine beat 9 mg/ml saline — grade 1 infection 8.5 versus 14 per cent, grade 2 infection 0.5 versus 3 per cent, a relative risk of 1.7 for a positive culture and 3.3 for Staphylococcus aureus with saline, plus fewer antibiotics and less pain at 6 and 10 weeks.
Dry dressings with gentle compression reduce skin-pin motion, which is the mechanical driver behind most of it.
Checketts-Otterburn classification:
- Grade 1: slight discharge/redness — improved pin care only.
- Grade 2: redness, discharge, tenderness — pin care plus oral antibiotics.
- Grade 3: as grade 2 but not improving with antibiotics — affected pin re-sited or removed; frame continues.
- Grade 4: severe soft-tissue infection involving multiple pins — frame must be abandoned.
- Grade 5: as grade 4 with radiographic bone involvement.
- Grade 6: infection persisting after frame removal — pin-track osteomyelitis requiring curettage and antibiotics.
Checketts is the only pin-site system that pairs a visual grade with a treatment, which is why it is universally used. It has been formally tested exactly once, and it did not do well. Across 134 photographs, inter-rater reliability between limb reconstruction surgeons was poor to moderate (ICC 0.56, then 0.48), agreement on the resulting treatment decision was poor (kappa 0.30 and 0.22), and surgeons' own confidence in their grade was low. Reliability was worse for dark skin than light skin among the surgeons — a difference the patient and carer group did not show.
Two consequences. Clinically: grade the pin, then decide on the whole picture — pain, pin stability, systemic signs and the trajectory over days — because the grade alone will not carry the decision, and erythema is a poor signal on pigmented skin, where warmth, tenderness, swelling and discharge matter more. Academically: a pin-site infection rate quoted from the literature is not a hard number, because the instrument producing it disagrees with itself.
Prevention. Hydroxyapatite-coated half pins reduce loosening and infection; meticulous insertion technique (sharp drills, saline cooling, no skin tension); release tented skin; minimise pin-soft tissue motion. Note where the trouble concentrates — in W-Dahl's randomised series every clinically loose pin at removal was a proximal pin.
Complications: Prevention and Management
- Mechanism / risk factors
- Smoking, diabetes, NSAIDs, high-energy osteotomy, excessive distraction rate
- Recognition
- Healing index rises above the expected 1 to 1.5 months per cm of lengthening in adults; lucent or hourglass regenerate on serial films
- Prevention
- Low-energy percutaneous osteotomy, adequate latency, distraction at physiological rate, weight bearing, optimise host and stop smoking
- Salvage
- Slow or pause distraction, 'accordion' manoeuvre of alternating compression and distraction, encourage weight bearing; persisting failure needs bone grafting or exchange to internal fixation
- Mechanism / risk factors
- Premature removal before the regenerate can carry load
- Recognition
- Angulation or fracture through the regenerate in the days to weeks after removal
- Prevention
- Three-cortex rule before removal, dynamisation trial in the frame, bracing after removal
- Salvage
- Re-application of the frame or conversion to internal fixation
- Mechanism / risk factors
- Prolonged latency period, paediatric patients with high osteogenic potential
- Recognition
- Sudden pain on adjustment and struts that will not advance; bridging bone on radiograph
- Prevention
- Shorten latency in children, begin distraction promptly, monitor radiographs closely
- Salvage
- Re-osteotomy and restart the distraction programme
- Mechanism / risk factors
- Gastrocsoleus tension producing equinus in tibial lengthening; knee flexion contracture in femoral lengthening
- Recognition
- Progressive loss of ankle dorsiflexion or knee extension at each visit
- Prevention
- Daily physiotherapy, night splints, extend the frame to the foot with a spanning construct in long tibial lengthenings, prophylactic gastrocnemius recession in high-risk cases
- Salvage
- Intensify therapy, add foot ring or dynamic splint, pause lengthening; gastrocnemius recession or soft tissue release if fixed
- Mechanism / risk factors
- Hip and knee during femoral lengthening, especially with dysplasia or cruciate-deficient knee; ankle in tibial lengthening
- Recognition
- Radiograph the adjacent joints at every visit; new pain or loss of congruency
- Prevention
- Pre-operative assessment of joint stability, span the joint prophylactically if at risk
- Salvage
- Stop lengthening immediately, span and reduce the joint
- Mechanism / risk factors
- Traction neuropathy during lengthening or rotational correction; peroneal nerve most commonly affected
- Recognition
- Dysaesthesia, loss of dorsiflexion or eversion during the distraction programme
- Prevention
- Prophylactic peroneal decompression in high-risk correction, controlled rate, regular neurological examination
- Salvage
- Slow or reverse the distraction programme; decompress at the fibular neck if symptoms persist
- Mechanism / risk factors
- Pin-bone interface loosening and thermal or mechanical necrosis at insertion
- Recognition
- Graded by the Checketts-Otterburn system - but grade it alongside pain, pin stability and systemic signs, because inter-rater reliability is only 0.48 to 0.56 and is worse on darker skin
- Prevention
- Meticulous pin insertion technique, hydroxyapatite-coated pins, chlorhexidine rather than saline for cleansing, avoid heat necrosis. Cleaning FREQUENCY did not matter in the one randomised trial - sustainability over months beats intensity
- Salvage
- Antibiotics for early grades; exchange or remove and re-site the pin, debride and curette the track for osteomyelitis
- Mechanism / risk factors
- Months in frame, appearance, sleep disturbance and dependence on strut adjustment schedule
- Recognition
- Missed adjustments, prescription drift, disengagement at clinic
- Prevention
- Pre-operative counselling, realistic expectation of total frame time, family and psychological support, written adjustment schedule
- Salvage
- Re-counsel, simplify or shorten the programme, consider early exchange to internal lengthening or fixation
Applications
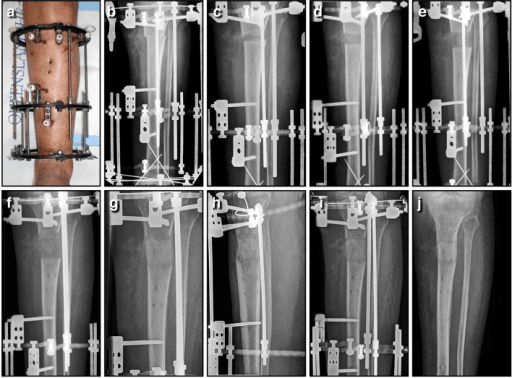
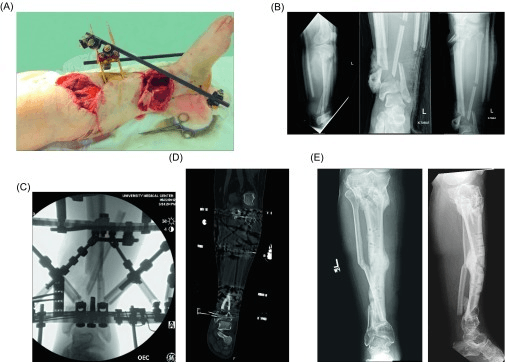
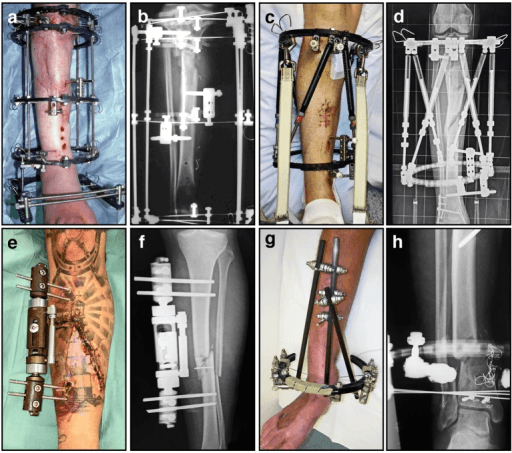
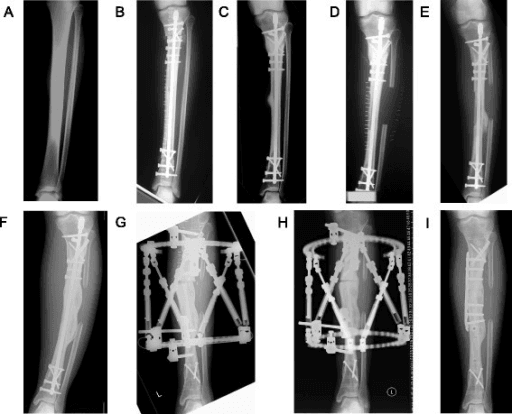
The classic indication: multiplanar deformity with shortening, poor soft tissues or prior infection. Hexapod allows deformity correction, compression across a nonunion, or bone transport for segmental defects, all with weight bearing.
Gradual correction of proximal tibial varus, procurvatum and internal torsion (low MPTA, multiplanar CORA). Gradual correction reduces peroneal nerve and compartment risk versus acute osteotomy in large deformities and adolescents; simultaneous limb-length equalisation possible.
Circular fixation permits resection, compression, correction and lengthening through a proximal corticotomy; often combined with intramedullary rodding and biological adjuncts. Refracture risk remains high — frames are one tool in a staged strategy.
Rigid equinocavovarus (relapsed clubfoot, post-traumatic, neurological): forefoot and hindfoot half-rings butted to a tibial ring allow gradual distraction correction with or without osteotomy, the virtual hinge programmed at the deformity apex or joint axis.
CAT-SAR-L (Coronal Angulation/Translation, Sagittal Angulation/Translation, Rotation, Length)Six Deformity Parameters
Hook:Three planes, each with an angulation and a shift — plus rotation and length make six, matching the six struts.
DFM — Deformity, Frame, MountingFrame Programming Inputs
Hook:Don't Forget Mounting — mounting parameter error is the commonest cause of an unexpected residual deformity.
Guidelines, Registries & Global Practice
- Global epidemiology and practice variation: post-traumatic tibial deformity is the dominant indication worldwide; in high-income settings hexapod frames increasingly replace hinged Ilizarov constructs for multiplanar corrections, while classical Ilizarov frames remain the mainstay in many low- and middle-resource settings because of hardware cost — strut sets are substantially more expensive than threaded rods and hinges, although the ring-and-wire skill base is shared.
- Society guidance: the BOA/BAPRAS open fracture standards (BOAST) frame the use of circular fixation in the reconstruction of open tibial fractures with bone loss within an ortho-plastic service; AO and limb reconstruction society (ASAMI/ILLRS) consensus material addresses distraction osteogenesis principles — latency, rate/rhythm, low-energy osteotomy — which apply directly to hexapod programmes. No major guideline mandates a specific hexapod system; principles, not brands, are examinable.
- Registries: no arthroplasty-style implant registry exists for circular frames; evidence is drawn from limb reconstruction unit series and multicentre cohorts. Reported accuracy of hexapod correction to within a few degrees and millimetres of target is consistent across series.
- Resource-setting adaptation: where software access or strut cost is limiting, hybrid strategies (acute partial correction plus simple frame, or classical Ilizarov) remain entirely legitimate; the deformity analysis (CORA, joint orientation angles) is identical whatever hardware is used.
Controversies & Areas of Uncertainty
- Latency duration: classic teaching is 5 to 10 days, but evidence for the optimal latency is weak; some units start correction (though not lengthening) almost immediately, particularly for pure angular correction without distraction.
- Rate and rhythm: 1 mm/day in four increments derives from Ilizarov's canine work; motorised or high-frequency adjustment devices question whether more, smaller increments improve regenerate quality — unproven clinically.
- Pin-site care protocols: no regimen (chlorhexidine vs saline, daily vs weekly, crust removal or not) has been shown clearly superior in randomised comparisons; consistency and patient education appear to matter more than the specific solution.
- Frame versus lengthening nail: for deformity correction with lengthening in intact soft tissues and non-infected bone, magnetically driven intramedullary lengthening nails increasingly compete with frames, avoiding pin sites at the cost of less multiplanar versatility and unsuitability in infection or small canals.
- Acute plus gradual hybrid: whether to acutely correct part of the deformity on the table (residual programme) or run the entire correction chronically is surgeon preference; acute partial correction shortens frame time but sacrifices some of the gradual-correction soft-tissue advantage.
- Cost-effectiveness: strut hardware cost versus re-operation savings from re-programmability has not been rigorously established; in resource-limited settings classical Ilizarov remains standard.
MCQ Practice Points
A: The Stewart-Gough platform — six telescopic struts between two platforms provide six degrees of freedom, so any relative ring position (three translations, three rotations) is achieved solely by changing strut lengths.
A: Both 85 to 90 degrees (mean about 87). A low MPTA indicates proximal tibial varus; a high mLDFA indicates distal femoral varus. PPTA (posterior tibial slope angle) is normally 77 to 84 degrees.
A: At the fastest-moving point of the osteotomy — the convex cortex during angular correction — not at the frame axis or the CORA. The software schedules struts so this point does not exceed the set rate.
A: Residual deformity is simply re-measured and a new strut schedule generated (the virtual hinge is repositioned in software). Hinged Ilizarov frames require physical dismantling and hinge re-siting.
A: Grades 4 and above — major infections involving soft tissue around multiple pins (grade 4), with bone involvement (grade 5), or persisting after removal as pin-track osteomyelitis (grade 6). Grades 1 to 3 are managed with pin care, antibiotics or single pin exchange.
A: Total time in the frame divided by centimetres of new bone formed (months per cm) — typically about 1 to 1.5 months/cm in adults, lower in children. A rising index flags delayed consolidation and prompts host optimisation or rate adjustment.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 34-year-old manual worker presents 18 months after a conservatively treated tibial fracture with a painful limp. Standing long-leg films show 15 degrees varus, 10 degrees procurvatum, 15 mm shortening; clinically the foot is internally rotated 20 degrees. How do you assess and manage this?”
“Three weeks into a hexapod programme correcting tibial varus with external rotation and 4 cm of lengthening, the patient reports new numbness in the first dorsal web space and weakness of toe dorsiflexion. What is happening and what do you do?”
“A 14-year-old with a BMI on the 99th centile has adolescent Blount disease: MPTA of 72 degrees, 15 degrees procurvatum, internal tibial torsion and 2 cm shortening. The family asks why you are not simply performing an acute osteotomy with a plate.”
“Six weeks into a correction-plus-lengthening programme, the patient reports increasing pain with each adjustment and says two struts have become very stiff. Radiographs show dense bone bridging the osteotomy. What has happened and what are your options?”
Principle
- Stewart-Gough platform: 2 rings, 6 oblique telescopic struts, 6 degrees of freedom
- Simultaneous correction of angulation, translation, rotation and length in all planes
- Virtual hinge programmed in software — residual deformity fixed by re-programming, not re-operation
- Inputs: deformity parameters (6), frame parameters, mounting parameters (reference ring vs origin)
Planning
- Standing long-leg films: mechanical axis deviation, CORA
- mLDFA 85-90, MPTA 85-90, LDTA 86-92, PPTA 77-84 degrees
- CT rotational profile for torsion; calibrated films/scanogram for length
- Paley osteotomy rules: hinge at CORA avoids secondary translation
Technique & Programme
- Reference ring orthogonal and centred; tensioned wires plus HA-coated half pins in safe corridors
- Low-energy percutaneous corticotomy or Gigli osteotomy after frame application; confirm completeness
- Latency 5-10 days; 1 mm/day at fastest cortex in 3-4 daily adjustments; weight bear
- Remove frame only with mature regenerate on 3 of 4 cortices; healing index about 1-1.5 months/cm
Complications
- Pin-site infection near-universal minor — Checketts-Otterburn grades 1-3 minor, 4-6 major
- Nerve stretch (peroneal) in lengthening/rotation — reverse programme, decompress if persistent
- Joint contracture/subluxation — physiotherapy, spanning constructs, surveillance films
- Poor regenerate: slow/pause, accordion, graft; premature consolidation: re-osteotomy
- Regenerate fracture after early removal — dynamise, brace, respect the three-cortex rule
Evidence Base
Does the Taylor Spatial Frame Accurately Correct Tibial Deformities?
- 102 patients and 122 tibiae corrected by percutaneous osteotomy and gradual hexapod correction - the largest accuracy series for this device
- Minimum follow-up 10 months after frame removal, average 48 months, range 10 to 98 months
- Proximal osteotomies: medial proximal tibial angle went from 80 to 89 degrees in varus and from 96 to 85 degrees in valgus
- Distal osteotomies: lateral distal tibial angle went from 77 to 86 degrees in valgus and from 101 to 90 degrees in varus
- Middle-third osteotomies: ALL patients finished with under 5 degrees of coronal deformity and 15 of 17 with under 5 degrees of sagittal deformity
Accuracy of Correction of Tibia Vara - Acute Versus Gradual Correction
- 14 tibiae corrected acutely and held in a monolateral fixator versus 18 corrected gradually with six-axis analysis and a hexapod frame
- Residual mechanical axis deviation was 17.1 mm after acute correction versus 3.1 mm after gradual correction
- Posterior proximal tibial angle deviated 5.6 degrees after acute versus 1.9 degrees after gradual correction
- Accurate translation correction (within 5 mm of the required value) was achieved in 18 of 18 gradual cases versus 7 of 14 acute
- Accurate angulation correction was achieved in 17 of 18 gradual cases versus 7 of 14 acute; every tibia with a rotational deformity was corrected accurately in both groups
Femoral Deformity Correction in Children and Young Adults Using Taylor Spatial Frame
- 20 patients (22 limbs) aged 5.9 to 24.6 years - the femur, which is far less studied than the tibia for this device
- Frontal and sagittal plane deformities were corrected to within normal values; mean time in frame was 6.2 months
- Mean lengthening of 4.9 cm in eight femora, with an external fixation index of 2.2 months per centimetre
- 15 complications occurred in 13 limbs - pin-tract infection, knee stiffness, delayed union, skin irritation and POSTERIOR KNEE SUBLUXATION
- Nine limbs had no complications at all