The Superomedial Strut Between Neck and Scapula
- Origin from the posterior tubercles of the transverse processes of C1 to C4; insertion on the medial border of the scapula between the superior angle and the root of the scapular spine.
- Dual innervation: direct branches from the C3 and C4 ventral rami plus the dorsal scapular nerve (C5). In a cadaveric series of 23 dorsal scapular nerves the nerve supplied levator scapulae in every specimen, and in about half of those it supplied levator alone without continuing to the rhomboids.
- The fibres twist through nearly 180 degrees on their way down, so the fibres from C1 insert most inferiorly on the scapula.
- It is a DOWNWARD rotator of the glenoid; with the scapula fixed it laterally flexes and ipsilaterally rotates the cervical spine.
- The superomedial angle is the commonest bony site in snapping scapula; resecting it necessarily detaches the levator insertion, which must be repaired.
- “Scapulothoracic arthroscopy portals must be placed INFERIOR to the scapular spine and three to four fingerbreadths medial to the vertebral border - superomedial portals endanger the dorsal scapular and transverse cervical neurovascular structures and the spinal accessory nerve.
- “Levator scapulae syndrome is pain and a trigger point at the superomedial angle insertion, frequently with a normal scapulothoracic articulation - it is an enthesopathy, not a bursopathy.
- “Because the levator shares the dorsal scapular nerve with the rhomboids, an EMG showing denervated rhomboids AND levator localises the lesion to the dorsal scapular nerve or the C5 root, not to the middle scalene alone.
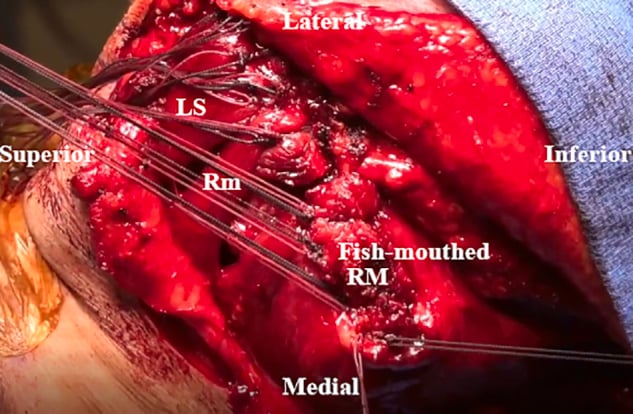
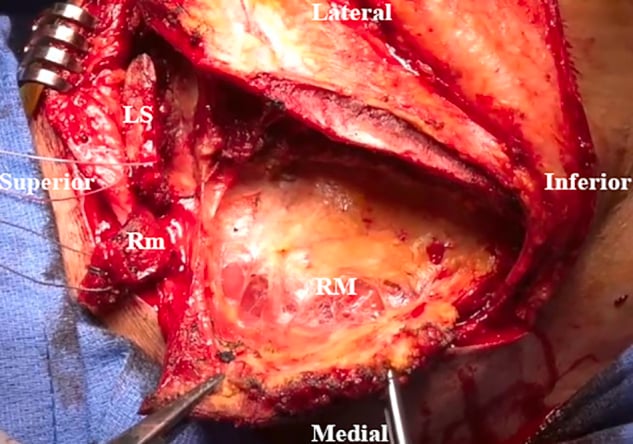
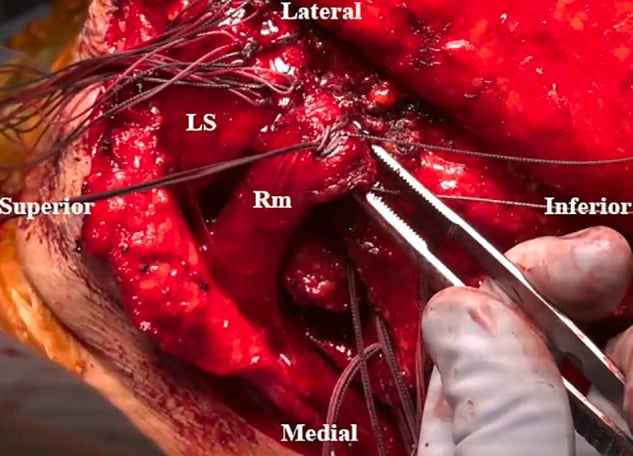
- “In the modified Eden-Lange transfer the levator is taken further laterally, toward the lateral scapular spine or acromion, because its upward-rotation moment arm is too short in the classical position.
Overview
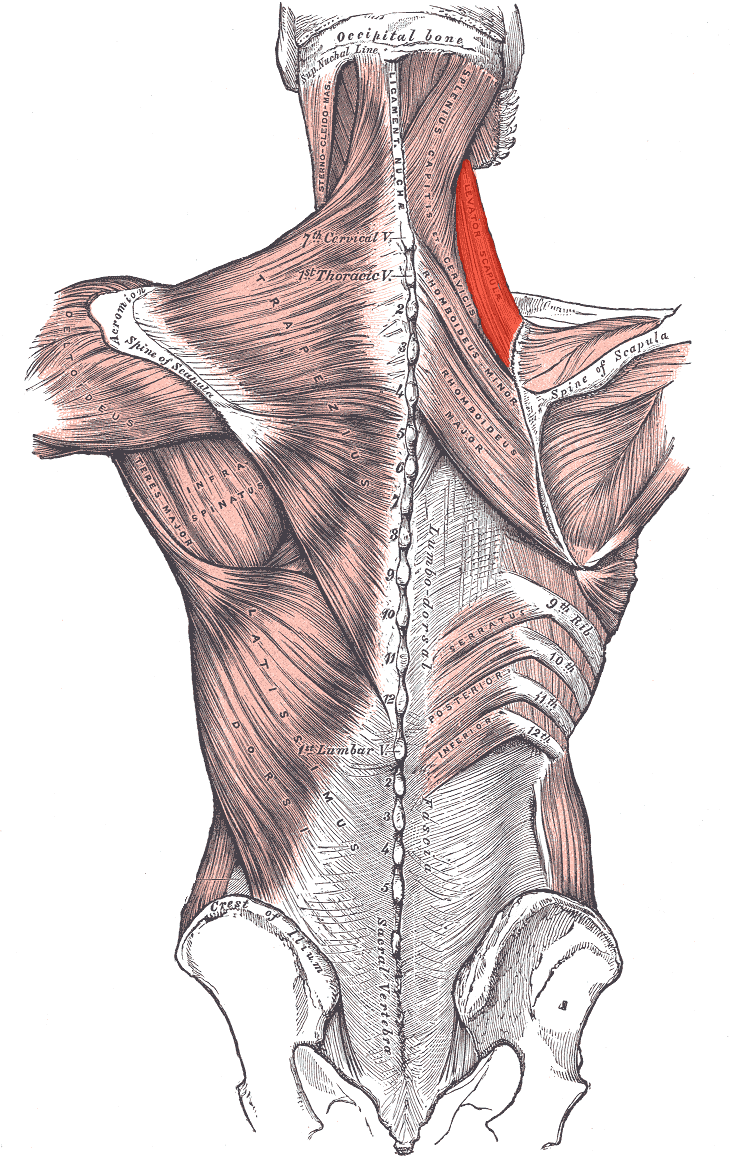
Levator scapulae is a strap-like muscle that runs obliquely from the upper cervical transverse processes to the superomedial corner of the scapula, lying deep to the trapezius and superficial to the splenius and the posterior scalene. It is the direct mechanical link between the cervical spine and the shoulder girdle, and it works in both directions: with the neck fixed it lifts and downwardly rotates the scapula; with the scapula fixed it side-bends and rotates the neck toward the same side.
Why it matters. Three features make it surgically important out of proportion to its size. Its insertion crowns the superomedial angle of the scapula, the corner that snaps, that gets resected, and whose resection destabilises the muscle. Its innervation is dual, from the cervical plexus and from the dorsal scapular nerve, which makes it an electrodiagnostic discriminator. And it is the upper limb of the Eden-Lange transfer, so its integrity determines whether an irreparable trapezius palsy can be reconstructed.
Attachments, Innervation and Relations
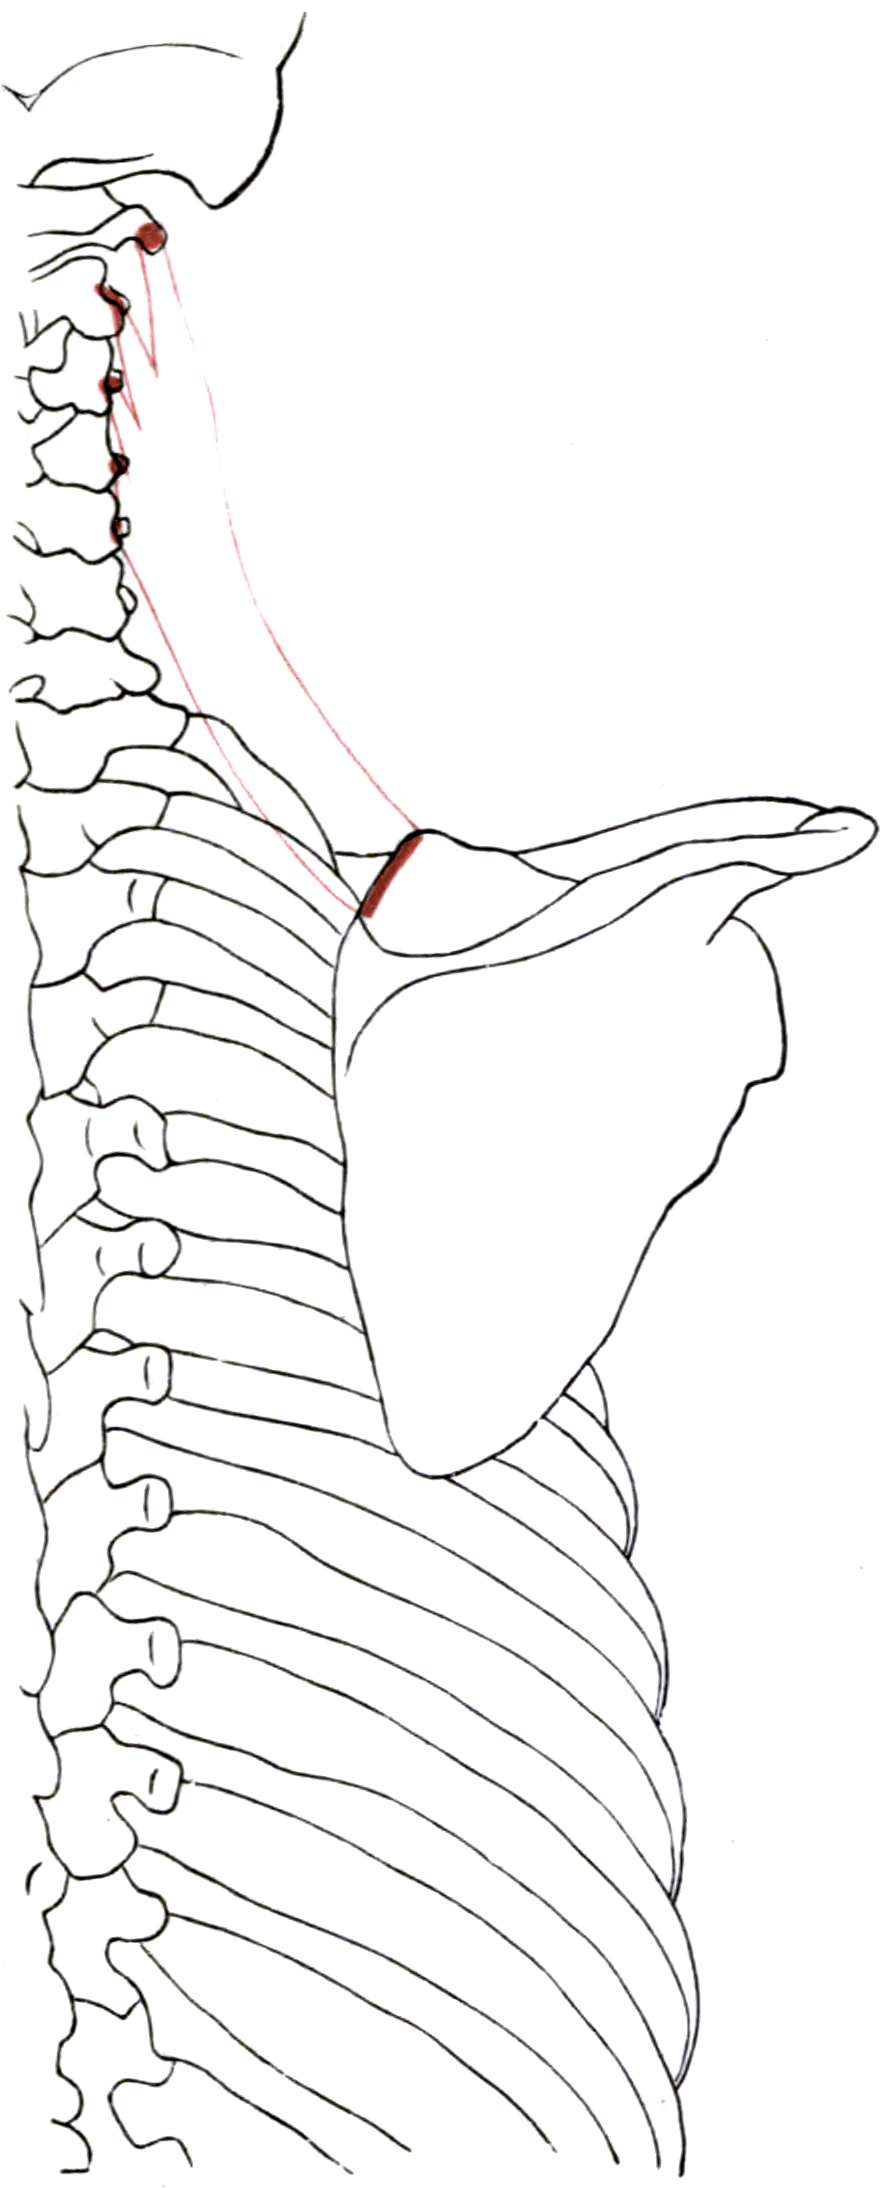
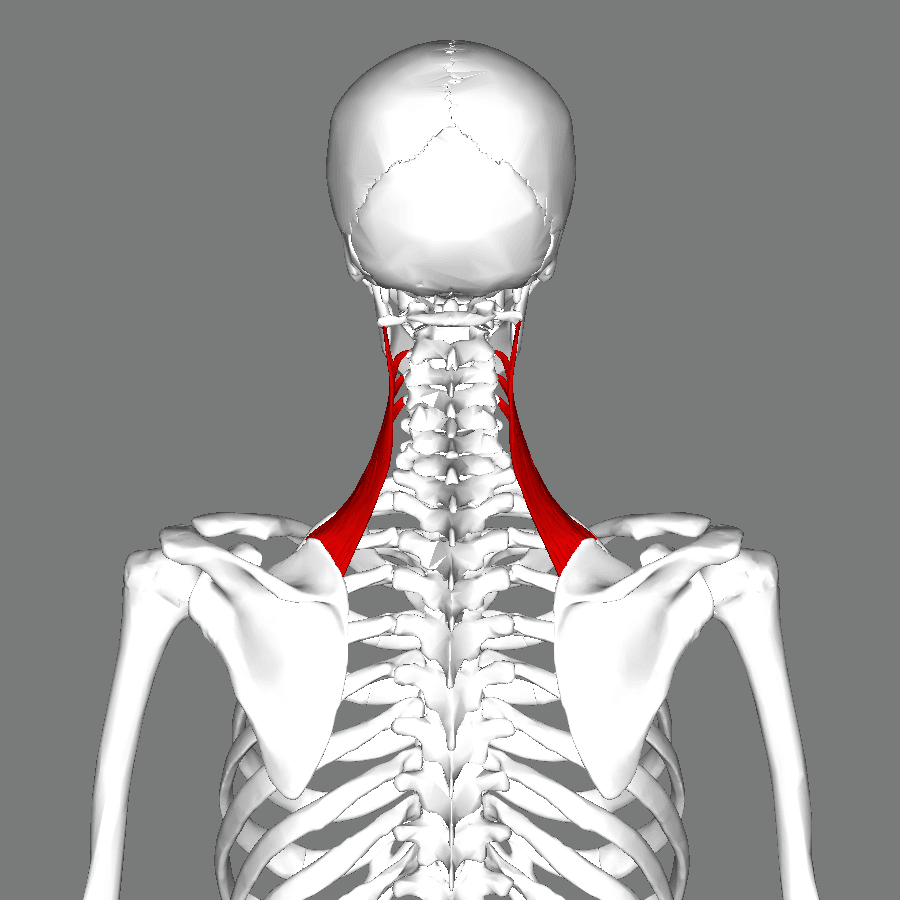
Origin. Four separate tendinous slips from the posterior tubercles of the transverse processes of C1 to C4. The C1 (atlas) and C2 (axis) slips arise from the transverse processes themselves, the C3 and C4 slips from the posterior tubercles, and the four fuse into a single flattened belly as they descend inferolaterally.
Insertion. The medial (vertebral) border of the scapula, from the superior angle down to the root of the scapular spine, a footprint typically 3 to 5 cm long. The bulk of the insertion is concentrated at and just below the superomedial angle, where the tendon is thickest, and some fibres blend with the deep surface of the rhomboid minor insertion, so the two are difficult to separate cleanly at the border.
The 180-degree twist. The fibres rotate through almost 180 degrees as they descend: the slip from C1, the most cranial origin, inserts most caudally on the scapula, and the slip from C4 inserts most cranially at the superior angle. The spiral is a favourite anatomical question with a practical consequence: the muscle cannot be split longitudinally along an internervous plane, because the fibres from different roots are interleaved.
The bone at the insertion. The superomedial angle is thin, and its ventral surface may carry a hooked or curled, anteriorly projecting prominence known as Luschka's tubercle. It is a recognised cause of mechanical scapulothoracic snapping and is the target of superomedial angle resection.
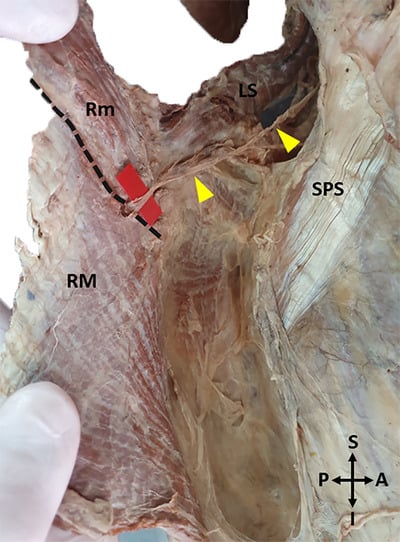
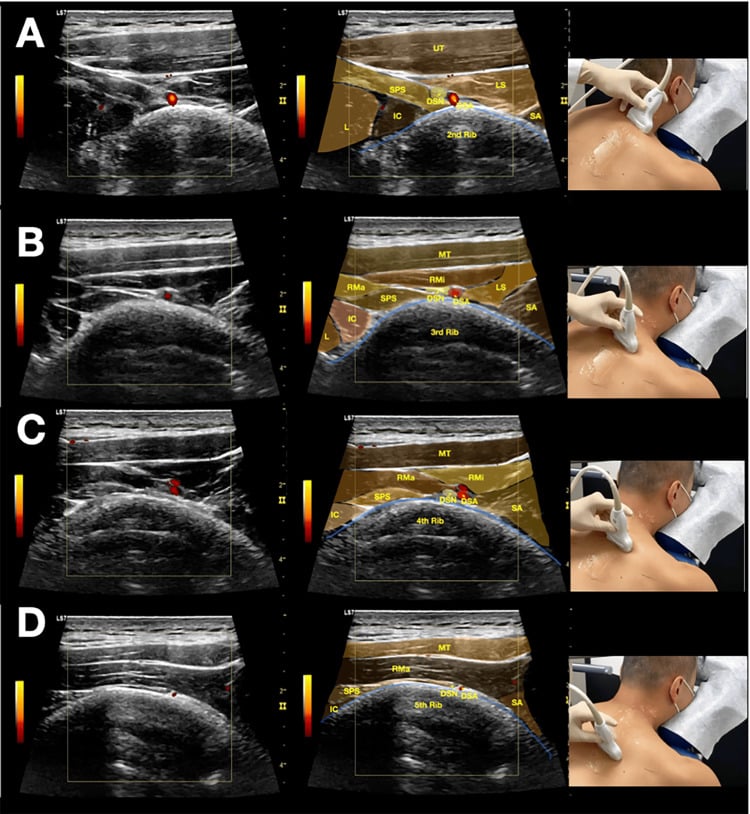
Within a few centimetres of the superomedial angle of the scapula lie the dorsal scapular nerve and artery, the transverse cervical vessels, the spinal accessory nerve on the surface of the levator and, immediately deep to the angle and millimetres away during angle resection or bursectomy, the second and third ribs and the parietal pleura. Every portal, osteotome and needle on this page is planned around that corner.
Action and Biomechanics
The line of pull. The levator inserts on a short segment of the medial border above the root of the scapular spine, well above the scapular rotation axis, and pulls superomedially and slightly anteriorly toward the cervical transverse processes. Three consequences follow directly.
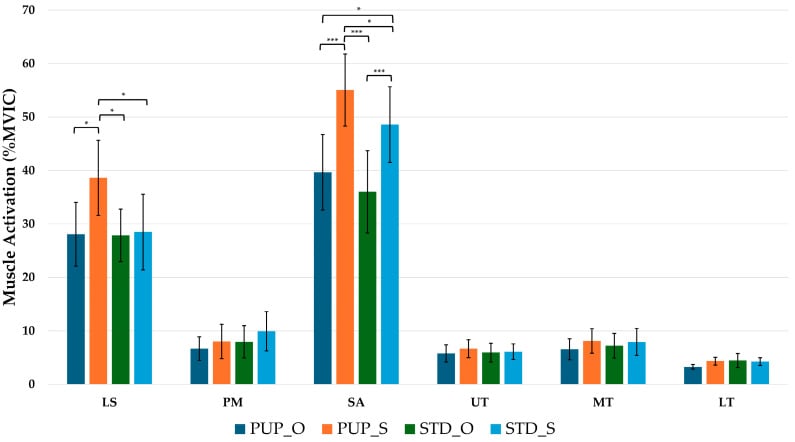
Elevation and downward rotation. With the neck fixed the levator elevates the scapula, the shrug component that survives a trapezius palsy, and because the pull is applied above the axis it swings the glenoid inferiorly. The levator is therefore an antagonist of the trapezius-serratus upward-rotation couple and a synergist of the rhomboids, and when it is tight it limits terminal elevation.
Why the superomedial angle snaps. The anterior component of the pull tilts the superior angle forward and presses the superomedial corner of the scapula against the second and third ribs. That corner is thin, its ventral surface is often prominent or hooked, and it slides across the ribs with every arm elevation, which is precisely why it is the commonest bony source of scapulothoracic crepitus.
Neck-shoulder coupling. Because the muscle spans both joints, a patient who fixes the scapula in elevation (habitual shrugging, an antalgic posture after cuff pain, carrying a bag) holds the levator short. Far more often than a weak levator you will meet this over-active, shortened one, doing the work of a failing trapezius or a painful cuff: it produces the taut, tender band at the superomedial angle, restricted contralateral cervical side-bending, and a scapula held in elevation and downward rotation. Chronic shortening is the substrate of levator scapulae syndrome, and treating the snap by resecting the angle without addressing the shortened, over-active muscle leaves the patient with the same pain and a destabilised scapula.
With the scapula fixed the actions reverse onto the neck:
- Ipsilateral lateral flexion of the cervical spine, so the neck pain is reproduced by contralateral side-bending
- Ipsilateral rotation of the cervical spine, through the oblique line of pull onto the transverse processes, which distinguishes it from sternocleidomastoid, which rotates contralaterally
- Acting bilaterally, extension of the cervical spine through the paired posterior vectors, contributing to the forward-head compensatory pattern
Moment arm and length-tension. The levator has a short moment arm for scapular rotation and a relatively long excursion for its size, which is what makes it usable as a transfer donor. During arm elevation it works eccentrically, paying out as the scapula upwardly rotates, and loss of that eccentric control is one contributor to scapular dyskinesis.
Synergists and antagonists. The levator shares elevation with one group and rotation with another:
- Synergists: rhomboid minor and major (downward rotation and elevation), upper trapezius (elevation only), pectoralis minor and latissimus dorsi (downward rotation)
- Antagonists: serratus anterior and the trapezius as a whole for upward rotation; lower trapezius and pectoralis minor for depression
The upper trapezius and levator are a curious pair: they agree on elevation and disagree on rotation. In a patient who shrugs to elevate the arm both are firing, and the levator's downward-rotation moment is part of why the compensation is inefficient. Isolated levator palsy, by contrast, is essentially never seen, because of the dual innervation.
Surface Anatomy and Examination
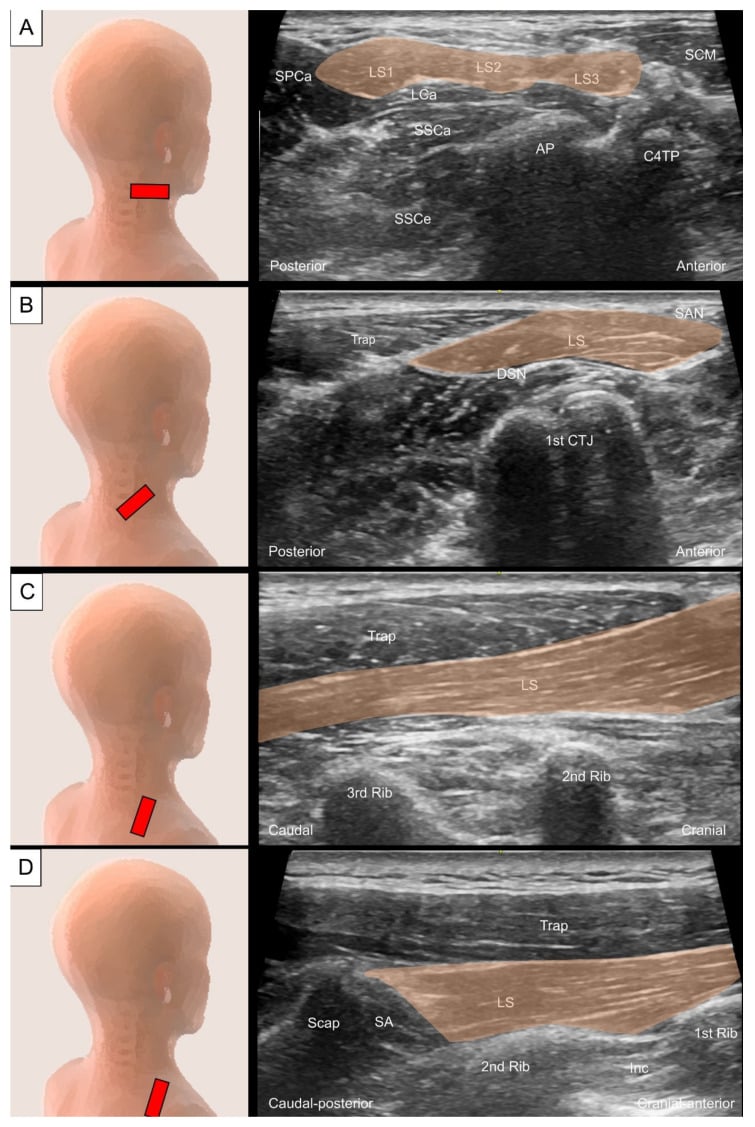
Finding it. Identify the superomedial angle of the scapula, which lies at roughly the T2 spinous process level with the arm at the side; the levator insertion is directly on it and just below it. Ask the patient to place the hand behind the back and then lift the hand away from the back, which rotates the medial border away from the chest wall and brings the insertion under the finger. Traced proximally, the muscle becomes palpable again as a firm cord deep to the anterior border of the trapezius in the posterior triangle when the patient shrugs against resistance with the head side-bent toward the same side.
Examination. Four tests, each answering a different question:
- How
- Patient supine or seated. Passively flex the cervical spine, then side-bend and rotate the head away from the tested side; depress the shoulder on the tested side while maintaining the head position
- Positive
- Reproduction of the familiar pain at the superomedial angle, or a firm end-feel with restricted range compared with the other side
- Means
- A shortened, over-active levator; the test assesses shortening rather than weakness
- How
- With the hand behind the back, press firmly at the superior angle just above the medial border
- Positive
- Exquisite, focal, familiar pain with a palpable taut band, often referring into the neck
- Means
- Levator insertional enthesopathy, which can be present with an entirely normal scapulothoracic articulation and normal imaging
- How
- Patient seated, examiner's palm flat over the superomedial angle and the medial border; the patient elevates and lowers the arm repeatedly through full range, then circumducts
- Positive
- Palpable or audible grating, clunking or snapping localised to the superomedial corner, reproducing the patient's symptom
- Means
- Symptomatic snapping scapula. Grating alone is common and often painless; it must reproduce the complaint to be relevant
- How
- Ultrasound-guided local anaesthetic into the superomedial scapulothoracic bursa, the needle directed tangentially
- Positive
- Abolition of the pain and of the painful crepitus for the duration of the anaesthetic
- Means
- The pain generator is at the superomedial angle and bursectomy with or without angle resection is likely to help. This is the decisive test before surgery; a negative response should stop you operating
Pitfalls. Four ways to get this wrong:
- Painless crepitus is normal in a large proportion of asymptomatic people. Never operate on a noise
- Referred pain from the cervical spine (C3-C4 facet joints, C5 radiculopathy) reproduces exactly the same superomedial and interscapular distribution. Examine the neck in every case and consider a diagnostic facet or root block
- Missing the trapezius or serratus palsy underneath. A patient whose levator is over-working is often compensating for a failing scapular stabiliser; test the shrug, the wall push and eccentric lowering before labelling the problem "levator scapulae syndrome"
- Blind injection at the superomedial angle risks pneumothorax. The pleura is millimetres deep to the angle; use ultrasound, and a shallow, tangential needle direction is mandatory
Complications
Pain that persists after bursectomy or angle resection. The commonest reason is that the pain generator was never the bursa: an unrecognised cervical radiculopathy, a levator enthesopathy that was not treated, or a scapular dyskinesis that was never rehabilitated. A negative diagnostic block should be treated as a contraindication to surgery.
Scapular destabilisation. Resecting too much of the superomedial angle detaches the levator and rhomboid minor insertions entirely and leaves nothing to repair to, and detaching them without reattachment does the same damage. The result is a painful, unstable, laterally translated, downwardly rotated scapula with medial border prominence. Keep the resection modest, and always reattach.
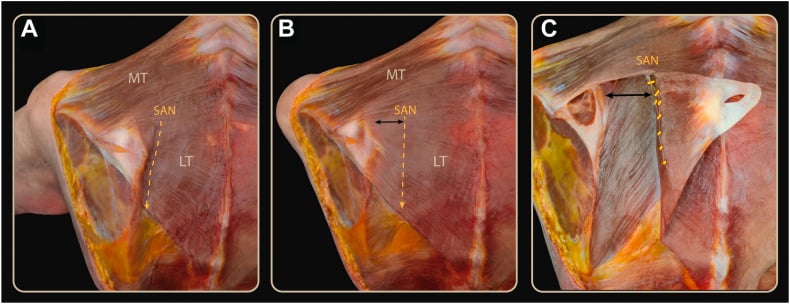
Neurovascular injury. The dorsal scapular nerve and artery, during a superomedial dissection or through a superomedial portal, producing rhomboid weakness and a subtle wing, or brisk bleeding that retracts into the paraspinal muscle. The spinal accessory nerve, if the incision or dissection extends cranially into the posterior triangle over the surface of the levator: the same nerve, in the same plane, as in a node biopsy.
Pneumothorax. From an arthroscope or instrument angled perpendicular to the chest wall, from an osteotome passing ventral to the angle, or from a blind trigger point injection. Suspect it with new pleuritic pain or desaturation and obtain a chest radiograph.
Fluid extravasation. Scapulothoracic arthroscopy has no contained joint. Use low pump pressures and short operating times; substantial extravasation into the chest wall and neck has been reported and can compromise the airway if it tracks cranially.
Recurrence. Recurrent crepitus after bursectomy alone is described where a bony prominence was the true cause and was not addressed. Recurrence after angle resection usually reflects continuing scapular dyskinesis rather than inadequate bone removal.
Donor morbidity after transfer. Loss of the levator as an independent elevator, with a slightly lower resting scapular position; and, if the dorsal scapular nerve is later injured, the loss of all three Eden-Lange donors together.
Clinical Relevance
The condition. Snapping (or crepitant) scapula syndrome is painful, audible or palpable crepitus arising from the scapulothoracic articulation, at the superomedial angle first and the inferior angle second.
The space. Cadaveric work has defined two triangular scapulothoracic spaces separated obliquely by serratus anterior:
- The serratus anterior (infraserratus) space, bounded by the chest wall anteriorly, serratus anterior posteriorly and the rhomboids medially. It contains a well-defined bursa and is the space entered at arthroscopy
- The subscapularis (supraserratus) space, bounded by serratus anterior anteriorly, subscapularis posteriorly and the axilla laterally
In addition, adventitial bursae develop at the superomedial angle and at the inferior angle in response to chronic friction. These are acquired, not constant, and they are the ones that hurt.
Causes of the snap. Six categories:
- Cause
- Luschka's tubercle (hooked, anteriorly curled superomedial angle); scapular osteochondroma; malunited scapular fracture
- Detection
- 3D CT of the scapula in the plane of the blade
- Cause
- Rib osteochondroma, malunited rib fracture, thoracic kyphosis, rib exostosis
- Detection
- CT chest wall; often missed on plain films
- Cause
- Bursitis of the superomedial or inferior angle bursa; fibrosis after trauma
- Detection
- Ultrasound, MRI, and the response to a diagnostic block
- Cause
- Atrophy of serratus anterior or subscapularis reducing the cushioning layer; muscle fibrosis after denervation
- Detection
- Clinical, plus MRI showing fatty infiltration
- Cause
- Scapular dyskinesis with excessive anterior tilt and downward rotation, thoracic hyperkyphosis
- Detection
- Dynamic observation; often reversible with rehabilitation
- Cause
- Elastofibroma dorsi at the inferior angle deep to serratus
- Detection
- MRI - a characteristic striated soft-tissue mass; often bilateral
The pathway. Three steps, in order:
- Non-operative first, and for at least 3 to 6 months: postural correction, scapular retraction and upward-rotation strengthening (serratus and lower trapezius), levator and pectoralis minor stretching, activity modification, and analgesia
- Ultrasound-guided bursal injection, both therapeutic and, crucially, diagnostic
- Surgery only for the patient whose pain is abolished by the diagnostic block and who has failed structured rehabilitation: bursectomy alone, or bursectomy with superomedial angle resection where imaging shows a bony prominence, performed open or arthroscopically
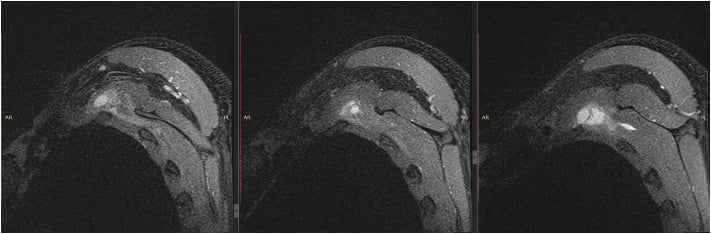
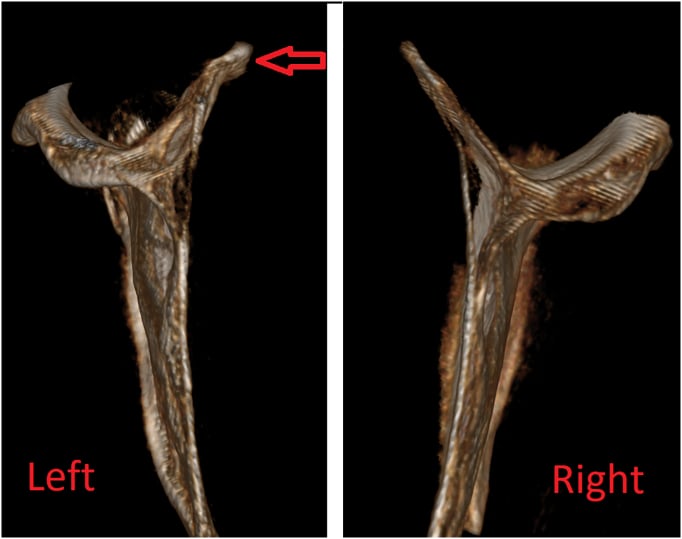
The differential. Four diagnoses share the territory:
- Character
- Mechanical, motion-related
- Discriminating features
- Crepitus with arm elevation reproducing the pain; a bony prominence or bursa on CT or MRI; a diagnostic bursal block abolishes it
- Character
- Enthesopathic, position-related
- Discriminating features
- Focal tenderness at the insertion with no crepitus; restricted contralateral cervical side-bending; imaging usually normal
- Character
- Neurogenic or facetogenic
- Discriminating features
- C3-C4 facet or C5 root referral to the identical area; neck movement reproduces it, local palpation may not. Treated by addressing the cervical spine; a missed radiculopathy is the classic reason a bursectomy fails
- Character
- A mass, not a mechanical problem
- Discriminating features
- Deep to serratus anterior at the INFERIOR angle, often bilateral, commoner in older women, with a characteristic striated fat-and-fibrous appearance on MRI. Observed if asymptomatic and marginally excised if painful; do not mistake it for a sarcoma or for bursitis
Surgical Relevance
Indication. Symptomatic snapping scapula localised to the superomedial angle, in the patient the pathway selects: pain abolished by a diagnostic bursal block, structured rehabilitation failed, and a bony prominence or symptomatic bursa demonstrated on CT or MRI.
The operation. Prone or lateral position, with the arm draped free so it can be placed in the "chicken wing" position (internal rotation with the hand behind the back), which lifts the medial border away from the chest wall. Then, in order:
- Incision along the medial border from the superior angle distally for 6 to 8 cm
- The trapezius is split or elevated, and levator scapulae and rhomboid minor are detached from the superomedial angle, leaving tendinous cuffs on the muscle for repair. The detachment is unavoidable: the levator insertion sits on the bone being removed
- The infraserratus (scapulothoracic) bursa is excised
- The superomedial angle is resected with an osteotome or saw as a triangular wedge, the plane developed from below under direct visualisation. Resection is deliberately limited, a wedge of the order of 2 cm along each of the superior and medial borders; larger resections increase the risk of destabilising the scapula and of straying toward the dorsal scapular neurovascular structures
- Levator and rhomboid minor are reattached through drill holes in the fresh cancellous edge or with suture anchors. Omitting this step is the classic technical error
- Sling for 2 to 3 weeks with early passive motion, then progressive scapular strengthening, with return to sport at 4 to 6 months
Structures at risk. Each has a position relative to the angle and a rule for avoiding it:
- Relation to the Superomedial Angle
- Enter the deep surface near the angle, then descend 1-2 cm medial to the medial border
- Avoidance
- Stay on bone; do not dissect medially off the border
- Relation to the Superomedial Angle
- Cross the posterior triangle on the superficial surface of levator, just cranial to the angle
- Avoidance
- Do not extend the dissection cranially beyond the levator insertion
- Relation to the Superomedial Angle
- Lies on the surface of levator scapulae in the posterior triangle, cranial to the angle
- Avoidance
- Never extend a medial border incision into the posterior triangle
- Relation to the Superomedial Angle
- Immediately deep (ventral) to the angle
- Avoidance
- Subperiosteal dissection on the ventral scapular surface; keep the osteotome tangential
- Relation to the Superomedial Angle
- At the suprascapular notch, well lateral - 2-3 cm medial to the coracoid base
- Avoidance
- Not usually in the field, but relevant if the exposure is extended along the spine
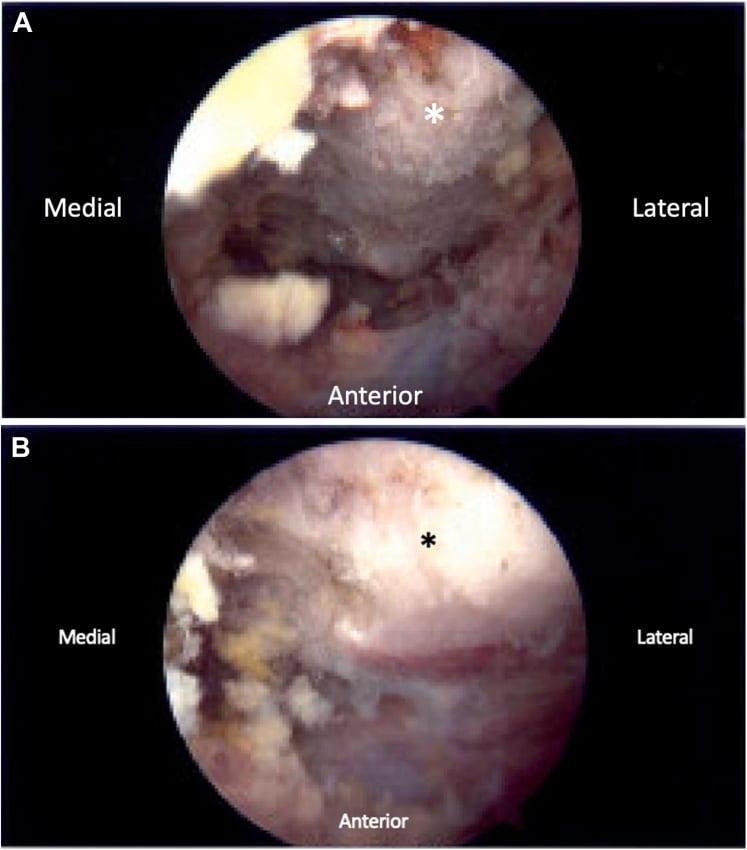
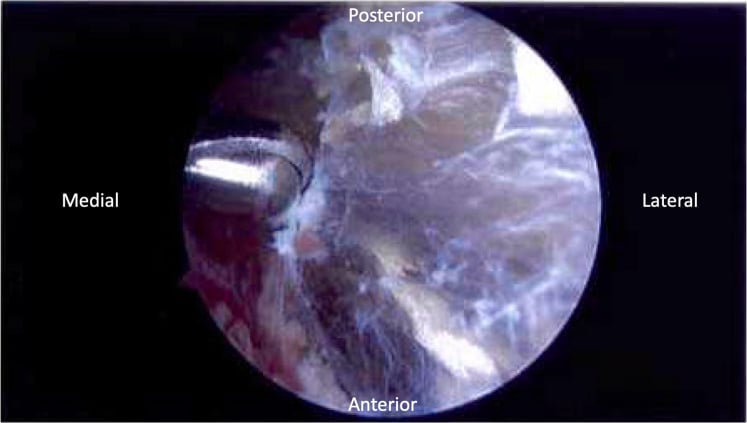
Guidelines, Registries & Global Practice
Anatomical variation
- Dorsal scapular innervation of levator scapulae was present in every specimen of the cadaveric series, and in roughly half of them the nerve supplied levator alone without continuing to the rhomboids. This is the single most clinically relevant variation.
- Accessory slips to the mastoid process, the occiput or the first rib (levator claviculae and related variants) are described and can be mistaken for pathological bands at operation.
- Luschka's tubercle - a prominent, anteriorly curled superomedial angle - is present in a minority of scapulae and is not always symptomatic; its presence on CT does not by itself justify resection.
- Omovertebral bar occurs in a substantial proportion of Sprengel deformities and passes in the plane of the levator.
- Painless scapulothoracic crepitus is demonstrable in a large minority of asymptomatic adults, which is why the diagnostic block, rather than the imaging, defines the surgical candidate.
Practice framing across bodies
- Position Relevant to Levator Scapulae and the Scapulothoracic Articulation
- Structured non-operative management is first-line for snapping scapula; surgery is reserved for pain reproduced and abolished by a diagnostic injection after failed rehabilitation.
- Position Relevant to Levator Scapulae and the Scapulothoracic Articulation
- Emphasise assessment of the cervical spine and of scapular dyskinesis before attributing periscapular pain to the scapulothoracic bursa.
- Position Relevant to Levator Scapulae and the Scapulothoracic Articulation
- Portal placement inferior to the scapular spine and well medial to the vertebral border, with instruments parallel to the chest wall and low pump pressures, is standard teaching.
- Position Relevant to Levator Scapulae and the Scapulothoracic Articulation
- Resection of the superomedial angle and the omovertebral bar before caudal translation reduces brachial plexus traction during the Woodward procedure.
Resource-dependent practice
- Well-resourced settings: ultrasound-guided diagnostic and therapeutic bursal injection, 3D CT reconstruction of the scapula, and arthroscopic bursectomy.
- Limited-resource settings: the diagnosis is clinical and the diagnostic block can be performed by careful landmark technique with a tangential needle; open bursectomy and modest angle resection require only standard instruments, and the outcome depends far more on correct patient selection than on the technique used.
Global framing of the condition
- Snapping scapula is a clinical diagnosis with no registry data and no randomised comparison of arthroscopic versus open treatment; the published literature is case series. Recommendations across international sources are consistent nonetheless: rehabilitation first, block to confirm, surgery last, and always restore the medial soft-tissue attachments.
- Occupational and sporting exposure drives incidence: overhead athletes, swimmers, and workers holding sustained protracted postures.
MCQ Practice Points
Q: From where does levator scapulae arise? A: The posterior tubercles of the transverse processes of C1 to C4, by four separate slips.
Q: Where does it insert? A: The medial border of the scapula between the superior angle and the root of the scapular spine, with the bulk at the superomedial angle.
Q: What is the nerve supply? A: Direct branches from the C3 and C4 ventral rami, plus the dorsal scapular nerve (C5), which in about half of specimens supplies levator alone.
Q: Does levator scapulae upwardly or downwardly rotate the glenoid? A: Downwardly - it is an antagonist of the trapezius-serratus upward-rotation couple.
Q: With the scapula fixed, which way does levator scapulae rotate the neck? A: Ipsilaterally (and side-bends ipsilaterally) - the opposite of sternocleidomastoid, which rotates contralaterally.
Q: Which origin slip inserts most inferiorly on the scapula? A: The C1 slip. The fibres twist through nearly 180 degrees during their descent.
Q: What is the commonest bony site of snapping scapula? A: The superomedial angle, often with a hooked or curled anterior prominence known as Luschka's tubercle.
Q: Where are scapulothoracic arthroscopy portals placed? A: Inferior to the scapular spine and three to four fingerbreadths medial to the vertebral border, in the infraserratus space, with instruments parallel to the chest wall.
Q: Name the two anatomical scapulothoracic spaces. A: The serratus anterior (infraserratus) space between serratus and the chest wall, and the subscapularis (supraserratus) space between subscapularis and serratus. Adventitial bursae at the superomedial and inferior angles are acquired.
Q: What must be done after resecting the superomedial angle? A: Reattach the levator scapulae and rhomboid minor through drill holes or anchors. Failing to do so destabilises the scapula.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 28-year-old swimmer describes a grinding, clunking sensation under the top inner corner of the left shoulder blade with every overhead stroke, with a deep ache afterwards. How do you work this up and what would you offer?”
“A patient returns six months after an open superomedial angle resection elsewhere. The crepitus has gone but the pain is worse, the shoulder blade sticks out medially and sits low. What has happened?”
“You are planning an Eden-Lange transfer for a chronic trapezius palsy. The EMG report says the rhomboids are normal but does not comment on levator scapulae. Does it matter, and what is the levator's innervation?”
Anatomy
- Origin: posterior tubercles of C1-C4 transverse processes
- Insertion: medial border, superior angle to root of scapular spine
- Nerve: C3-C4 ventral rami plus dorsal scapular nerve (C5); in about half the nerve supplies levator alone
- Fibres twist nearly 180 degrees - C1 slip inserts most caudally
Function
- Elevates the scapula and downwardly rotates the glenoid
- Presses the superomedial angle onto the second and third ribs
- Scapula fixed: ipsilateral cervical side-bend and rotation
- Antagonist of the trapezius-serratus upward-rotation couple
Clinical
- Superomedial angle is the commonest snapping site (Luschka's tubercle)
- Levator scapulae syndrome is an enthesopathy, not a bursopathy
- Diagnostic block, not crepitus, selects the surgical candidate
- Elastofibroma dorsi sits at the INFERIOR angle deep to serratus
Surgical
- Portals inferior to the scapular spine, three to four fingerbreadths medial to the border
- Resect a modest wedge, of the order of 2 cm, and always reattach levator and rhomboid minor
- Pleura is millimetres deep to the angle - keep instruments parallel to the ribs
- Levator is the upper limb of Eden-Lange; lateralise it in the modified transfer
Evidence Base
Scapulothoracic Anatomy for the Arthroscopist
- Sixteen fresh cadaveric shoulders studied by dissection alone and by dissection after arthroscopy
- Two triangular scapulothoracic spaces identified - the serratus anterior space and the subscapularis space - divided obliquely by serratus anterior
- A well-defined bursa occupies the serratus anterior space; its boundaries are the chest wall anteriorly, serratus anterior posteriorly and the rhomboids medially
- Portals should be placed inferior to the spine of the scapula and three to four fingerbreadths from the vertebral border to avoid the superomedial neurovascular structures and the dorsal scapular nerve and artery, and to prevent perpendicular orientation of the scope to the chest wall
An Alternative Portal for Scapulothoracic Arthroscopy
- Access to the superior angle of the scapula during scapulothoracic arthroscopy is difficult with the standard portals
- A safe and effective alternative portal located SUPERIOR to the scapula is described
- The portal enables easier resection of the superomedial angle in the treatment of snapping scapula
- The description is based on cadaveric evaluation
The Painful Scapulothoracic Articulation - Surgical Management
- 16 patients with refractory scapulothoracic pain and snapping treated over 5 years by one of five methods of surgical decompression
- Most had resection of the scapulothoracic bursa with excision of the superomedial portion of the scapula, performed open, arthroscopically, or by a combined approach
- At a mean of 36 months, 81 per cent were satisfied and said they would undergo the procedure again for the pain relief obtained
- There was no statistically significant difference between techniques, though the authors favoured the combined open and arthroscopic approach
A Cadaveric Investigation of the Dorsal Scapular Nerve
- 23 dorsal scapular nerves documented in 20 embalmed adult cadavers
- Approximately 70 per cent of the nerves originated from C5, and 74 per cent pierced the middle scalene muscle
- About 48 per cent supplied levator scapulae alone, while 52 per cent supplied both levator scapulae and the rhomboids
- Measured from a transverse plane at the laryngeal prominence, the nerve entered, crossed and exited the middle scalene at mean distances of 1.50 cm, 1.79 cm and 2.08 cm
Transfer of the Levator Scapulae, Rhomboid Major and Rhomboid Minor for Paralysis of the Trapezius
- 22 patients with trapezius paralysis from spinal accessory nerve injury underwent transfer of levator scapulae and both rhomboids
- Aetiology was cervical node biopsy in 13, trauma in 7 and radical neck dissection in 2
- All had pain, neckline asymmetry, a drooping girdle with lateral displacement of the scapula and weak active elevation
- 14 patients had been given an incorrect clinical diagnosis and 12 had had an inaccurate or incomplete electromyographic examination
- At a mean of 7.5 years the result was excellent in 13, satisfactory in 6 and unsatisfactory in 3, with adequate pain relief and functional improvement in all but 3
Outcome of Triple-Tendon Transfer, an Eden-Lange Variant, to Reconstruct Trapezius Paralysis
- 22 patients with persistent trapezius paralysis after spinal accessory nerve injury underwent a triple-tendon transfer
- The levator scapulae was taken to the LATERAL aspect of the scapular spine, rhomboid minor just medial to it, and rhomboid major to the medial spine, each with its bony insertion
- At a mean of 35 months winging was corrected in every patient with improved shoulder asymmetry
- Active abduction improved from a mean of 71 to 118 degrees and flexion from 102 to 150 degrees, with significant gains in Constant score, subjective shoulder value and DASH