The Muscle That Splits the Obturator Nerve
- Adductor brevis is the muscle that separates the anterior and posterior divisions of the obturator nerve: the anterior division lies on its anterior surface, the posterior division on its posterior surface.
- Origin is the outer surface of the body and inferior ramus of the pubis, between the gracilis origin below and the obturator externus above; insertion is the upper third of the medial lip of the linea aspera, proximal to the adductor longus insertion.
- It is innervated by the anterior division of the obturator nerve in most individuals, with a contribution from the posterior division in a substantial proportion — a genuine variation worth knowing.
- The medial circumflex femoral artery — the dominant blood supply to the adult femoral head — lies deep and posterior to the pectineus and adductor brevis, which is why the safe plane in the medial approach to the hip is anterior to the adductor brevis.
- The fascia overlying the short adductor at the exit from the obturator canal is the site of obturator nerve entrapment in athletes, and its release is the definitive treatment.
- “If asked how the obturator nerve divisions are separated, the single-word answer is adductor brevis — and in the pelvis it is the obturator externus that separates them first.
- “The Ferguson modification of the Ludloff approach works anterior to adductor brevis precisely to avoid the posterior division of the obturator nerve and the medial circumflex femoral artery; the original Ludloff interval went behind the brevis.
- “Adductor brevis is deep to both pectineus and adductor longus and superficial to adductor magnus — a three-layer sandwich in which the nerve divisions and the profunda femoris perforators are found.
- “Adductor brevis is not a useful flap or graft donor: it has no single dominant pedicle and its short broad architecture gives little excursion. This negative is worth stating explicitly.
Overview
The adductor brevis occupies the middle plane of the adductor compartment, deep to the pectineus and adductor longus and superficial to the adductor magnus. It is short, triangular and functionally unremarkable: it adducts the hip along with its neighbours and does nothing they do not also do.
Why it matters. Its importance is entirely topographical. Two structures of major surgical consequence are defined by their relationship to it:
- The anterior and posterior divisions of the obturator nerve run in front of and behind it respectively. It is the plane that separates them.
- The medial circumflex femoral artery, the dominant blood supply to the adult femoral head, lies deep and posterior to the pectineus and adductor brevis.
Every safe medial approach to the hip is built on the same instruction: stay anterior to the adductor brevis.
The Obturator Nerve and Its Two Divisions
The obturator nerve is a two-division nerve, and knowing what separates the divisions at each level is the answer examiners are looking for.
Course. The nerve arises from the anterior divisions of the ventral rami of L2, L3 and L4 in the lumbar plexus. It descends on the medial border of the psoas major within the psoas substance, emerges at that border, crosses the pelvic brim behind the common iliac vessels and runs forward along the lateral pelvic wall above the obturator vessels. It leaves the pelvis through the obturator canal, at the upper part of the obturator foramen above the obturator membrane, roughly 2-3 cm inferolateral to the pubic tubercle.
Where the divisions separate. In the pelvis and canal the obturator externus separates them: the anterior division passes in front of it, the posterior division through or behind it. In the thigh the adductor brevis separates them: the anterior division lies on its anterior surface, posterior to pectineus and adductor longus, and the posterior division lies on its posterior surface, in front of adductor magnus.
What each division supplies.
- Muscles
- Adductor longus, adductor brevis, gracilis, pectineus
- Other branches
- Cutaneous branch to the distal medial thigh; articular branch to the hip joint
- Muscles
- Adductor magnus (adductor part), adductor brevis (variably), obturator externus
- Other branches
- Articular branch to the knee, running with the popliteal artery through the adductor hiatus
Why the posterior division matters. Its articular branch descends through the adductor hiatus with the popliteal artery to the posterior knee capsule. That is the anatomical basis of referred medial knee pain in hip disease, and one reason a child with hip pathology presents complaining of the knee: a slipped upper femoral epiphysis, Perthes disease or a septic hip can present as knee pain with a normal knee, and all are missed this way. A child with knee pain and a normal knee examination must have the hip examined and imaged.
Why the separation matters. Selective anterior branch block or neurectomy is possible precisely because the divisions are separated by a muscle, and the same fact is what keeps a surgeon working anterior to the brevis away from the posterior division and from the medial circumflex femoral artery.
Attachments, Shape and Relations
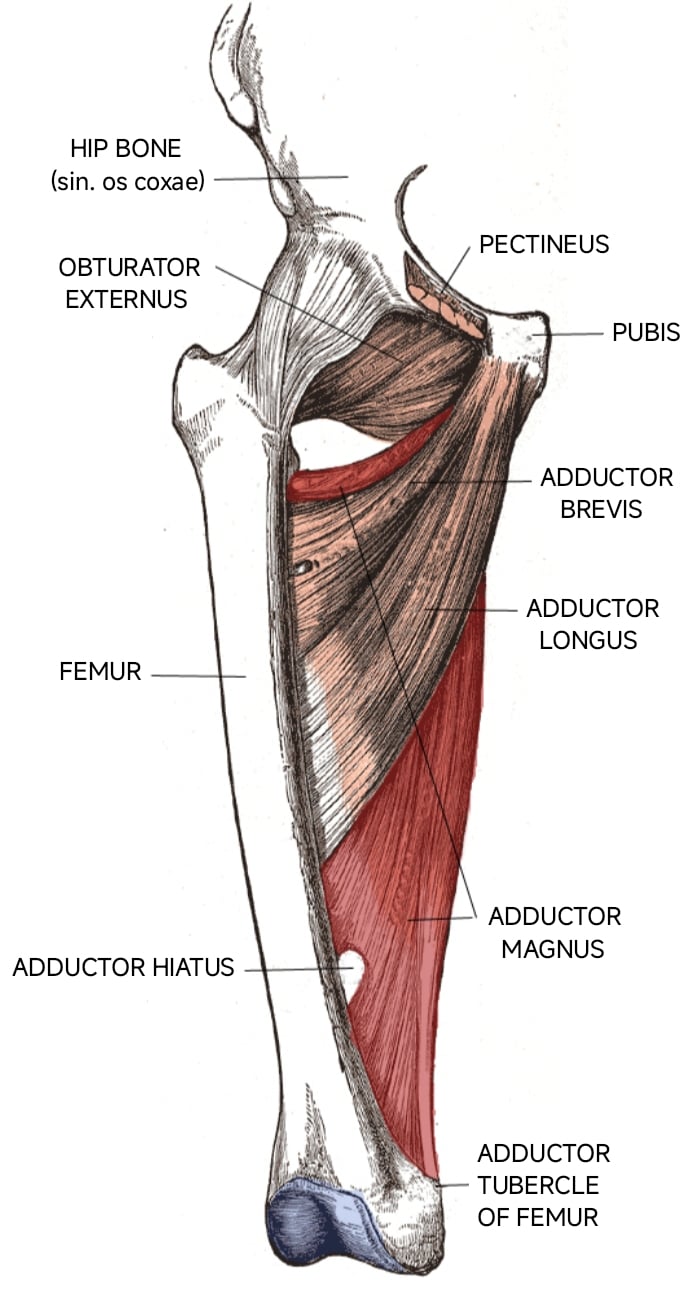
Origin. The outer (anterior) surface of the body of the pubis and the inferior pubic ramus, between the origin of the gracilis below and medially and the origin of the obturator externus above and laterally. The origin is broader and more inferior than that of the adductor longus, whose narrow tendon lies immediately above it on the pubic body, just below the pubic tubercle; the brevis origin lies below and lateral to the tubercle on the inferior ramus.
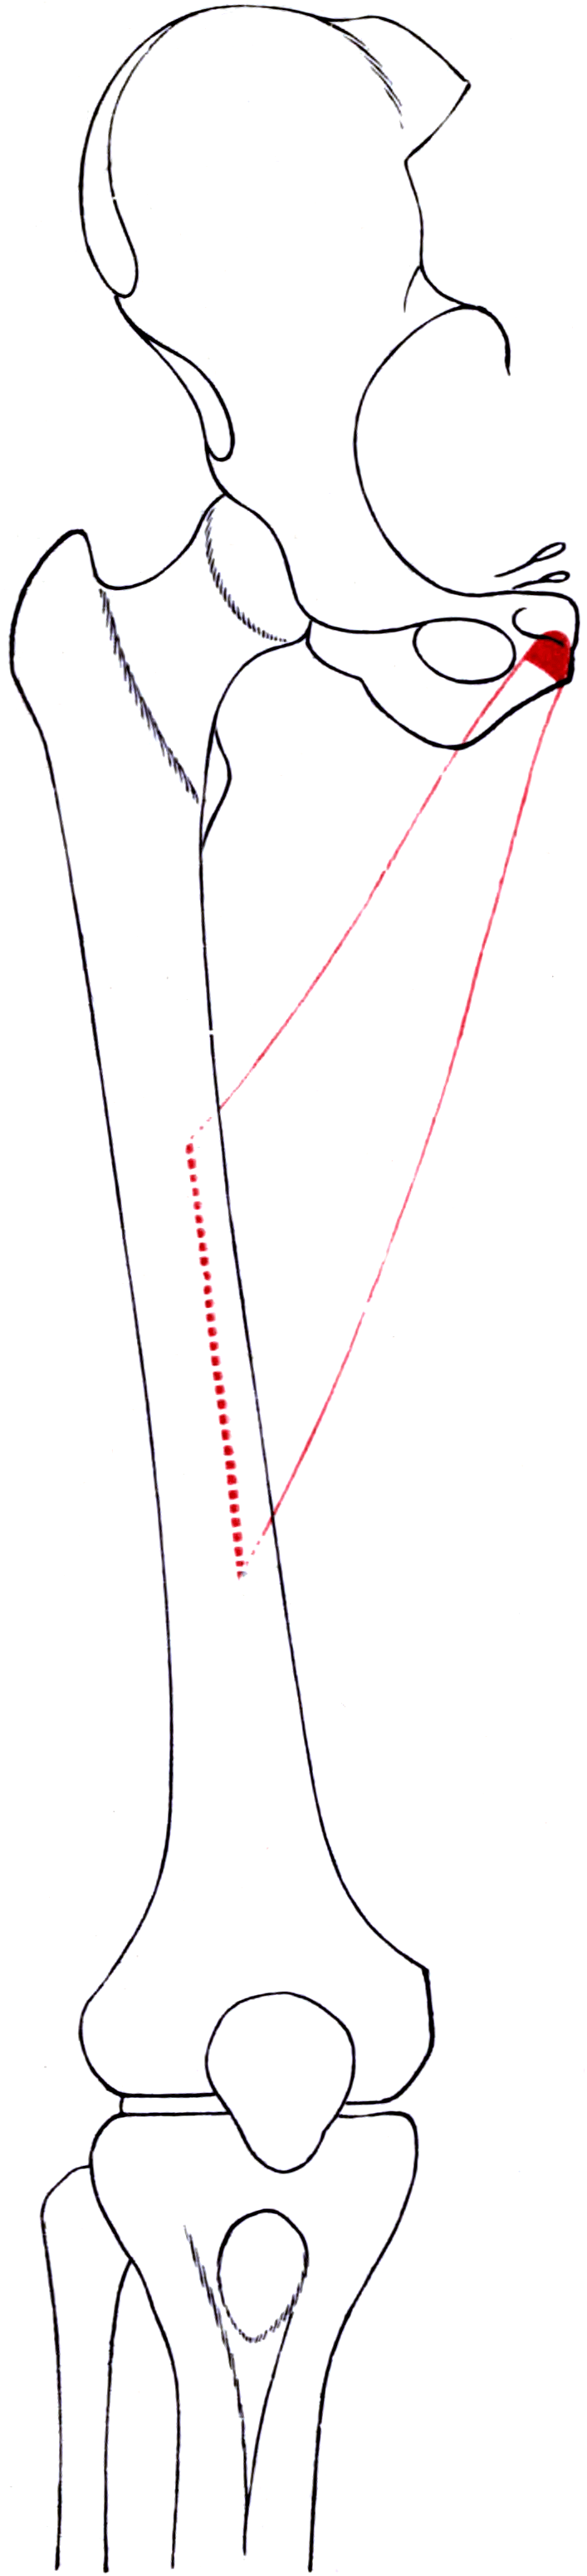
Insertion. The upper third of the medial lip of the linea aspera and the adjacent pectineal line of the femur, by an aponeurosis. This is proximal to the adductor longus insertion, which takes the middle third of the medial lip, and anterior to the adductor magnus insertion, and it defines the depth of the middle plane at the femur. Because the insertion is proximal and the muscle short, its fibres are relatively transverse.
Shape and plane. Triangular and short (hence brevis), broad at its femoral insertion, with the gracilis medial and superficial to the whole group. Its superior border relates to the obturator externus and the hip joint capsule, its inferior border to the adductor magnus.
Relations. Surface by surface:
- Anterior (superficial): pectineus proximally and adductor longus distally; the anterior division of the obturator nerve running distally on the anterior surface, the key relation; further anteriorly the femoral vessels, in the femoral triangle on the floor formed by iliopsoas and pectineus
- Posterior (deep): the posterior division of the obturator nerve, on the anterior surface of the adductor magnus; the adductor magnus itself; the perforating branches of the profunda femoris passing through toward the posterior compartment
- Superior: obturator externus and the hip joint capsule, the depth limit of a medial approach and the target in open reduction of a dislocated hip; the medial circumflex femoral artery passing posteriorly, deep to the pectineus
- Inferior and medial: adductor magnus inferiorly; gracilis medially and superficially
Innervation
Supply. The anterior division of the obturator nerve (L2, L3, L4) is the principal supply, its branches entering the anterior surface of the muscle. The posterior division also contributes in a substantial proportion of individuals, its branches, where present, entering the posterior surface. This dual contribution is described in anatomical studies and is a legitimate variation to mention.
The nerve defines the muscle, not the other way round. In a medial approach, finding the anterior division running distally on the anterior surface of adductor brevis confirms both that you have identified the correct muscle and that you are in the safe plane. The same accessibility is why the anterior branch can be divided selectively for adductor spasticity, though because the brevis may also receive posterior division fibres, an anterior neurectomy does not necessarily denervate it completely.
Localising a lesion. Hip adduction is L2/L3/L4 through the obturator nerve, and sensation over the distal medial thigh is the obturator cutaneous branch from the anterior division. Weak adduction with a medial thigh sensory patch therefore localises to the obturator nerve; add quadriceps weakness and the lesion is proximal, in the lumbar plexus or the L2-L4 roots, from a retroperitoneal haematoma, abscess or tumour.
What an obturator lesion does. A complete obturator nerve lesion denervates adductor longus, brevis, gracilis and the adductor part of magnus, but adduction is weakened, not abolished, because the pectineus retains a femoral nerve branch and the ischiocondylar part of adductor magnus retains a tibial (sciatic) supply. On MRI the same selective pattern, denervation oedema and later fatty atrophy with relative sparing of pectineus and the ischiocondylar adductor magnus, is a reliable localiser for an obturator lesion and should prompt a search for a pelvic cause.
Blood Supply
Arterial supply. The anterior and posterior branches of the obturator artery supply the proximal muscle, entering close to the nerve after emerging from the obturator canal; the anterior branch also gives the acetabular branch running in the ligamentum teres. The medial circumflex femoral artery supplies the proximal muscle as it passes deep to the pectineus and adductor brevis. Muscular branches of the profunda femoris are the dominant supply to the body of the muscle.
The perforators go through it. Typically three to four perforating branches of the profunda femoris pass from the anterior to the posterior compartment, piercing the adductor brevis and the adductor magnus and also the intermuscular septa. Dividing either muscle without vision therefore bleeds from a vessel that then retracts into muscle. The same vessels are the ones divided in the lateral approach to the femur when the vastus lateralis is elevated off the lateral intermuscular septum.
The medial circumflex femoral artery. It arises from the profunda femoris (occasionally directly from the femoral artery), passes posteriorly between the pectineus and the psoas major, then continues between the obturator externus and the quadratus femoris to reach the posterior aspect of the hip. Its deep branch and the terminal retinacular (lateral epiphyseal) vessels entering the posterosuperior head-neck junction are the dominant blood supply to the adult femoral head. In the proximal medial thigh it therefore lies deep and posterior to the pectineus and adductor brevis: dissection carried posterior to the adductor brevis in a medial approach risks it, and its injury causes avascular necrosis of the femoral head.
Not a flap. The adductor brevis has no single dominant pedicle and a short, broad, low-excursion architecture, so it is not used as a muscle flap or as a tendon transfer donor, a negative worth stating explicitly in a viva. The useful medial thigh flap and graft donor is the gracilis, on the ascending branch of the medial circumflex femoral artery, with a long tendon and a single dominant nerve.
Dividing the adductor brevis blindly, for example during an extended adductor release, produces brisk bleeding from a vessel that then retracts into muscle. Divide the muscle under direct vision, control any perforator deliberately, and do not chase a retracted vessel posteriorly toward the sciatic nerve territory.
Action and Biomechanics
Actions by plane. Adduction is the dominant action; the others depend on the position of the hip.
- Action
- Hip adduction
- Position of greatest efficiency
- Hip abducted
- Note
- The dominant action
- Action
- Hip flexion when the hip is extended; contributes to extension in deep flexion
- Position of greatest efficiency
- Depends on hip angle relative to the crossover point
- Note
- The same position-dependent reversal as adductor longus
- Action
- Contributes to rotation, direction depending on hip position
- Position of greatest efficiency
- Variable
- Note
- Described inconsistently; state the mechanism, not a fixed direction
- Action
- Stabilises the pelvis in single-leg stance with the rest of the adductor group
- Position of greatest efficiency
- Weight-bearing
- Note
- The functionally significant contribution
Architecture and moment arm. Short, broad, relatively transverse fibres with a proximal femoral insertion give a good adduction moment arm but a small total excursion: the muscle can generate force through a limited range but cannot lengthen much. The clinical consequence is that the brevis contributes disproportionately to a fixed adduction contracture. In spastic hip disease, once adductor longus and gracilis have been released and abduction remains limited, the brevis is often the residual restraint, precisely because its short fibres tolerate lengthening poorly.
Redundant, but indispensable. Every action of the adductor brevis is duplicated by the adductor longus, adductor magnus and pectineus, so isolated loss of the muscle has no detectable clinical consequence. Its indispensability is entirely as a surgical landmark and as the plane separating the obturator nerve divisions, and it is worth saying this explicitly in a viva: the muscle matters for where it is, not for what it does.
In gait. The adductor group is active in loading response and pre-swing, contributing to pelvic stability and to the transition between stance and swing rather than to gross adduction. In spastic hip disease the adductors are overactive throughout the cycle, producing a scissoring gait and, over time, progressive hip displacement as the head is levered out of a shallow acetabulum.
Synergists and antagonists. The adduction synergists are adductor longus and magnus, pectineus, gracilis, the inferior fibres of gluteus maximus and quadratus femoris; the antagonists are gluteus medius and minimus and tensor fascia lata.
Contracture. Fixed adduction presents as reduced abduction with a hard end-feel, apparent limb shortening, difficulty with hygiene and positioning, and progressive hip displacement in the growing child with spasticity.
Surface Anatomy and Examination
Palpation. The adductor brevis is not palpable as a discrete muscle, because it lies deep to the pectineus and adductor longus; saying so is the correct answer and a distinguishing feature. Orientate from the structures that can be felt:
- Pubic tubercle: the reference point for the whole compartment
- Adductor longus tendon: the prominent cord just below and medial to the tubercle, best seen with the hip flexed, abducted and externally rotated; the adductor brevis lies immediately deep to it
- Gracilis: the most medial strap, palpable along the medial thigh, its tendon easily traced distally to the pes anserinus
- Obturator canal: appreciable only as a soft depression in a slim patient; the block target and the site of entrapment
Deep palpation in the proximal medial thigh, lateral to the adductor longus tendon and medial to the femoral pulse, reaches the plane of the brevis. Deep tenderness here in an athlete with exertional pain raises obturator nerve entrapment.
Named tests and their interpretation.
- How to perform
- Supine, pelvis squared; abduct with the knee extended, then repeat with the knee flexed
- Positive finding
- Abduction improves markedly with the knee flexed
- What it means
- The limiting structure crosses the knee, that is the gracilis; unchanged restriction implicates the monoarticular adductors including brevis
- How to perform
- Assess the quality of the end-point on gentle passive abduction under relaxation
- Positive finding
- Hard, abrupt end-feel
- What it means
- Fixed contracture (or a bony block); a soft springy end-feel suggests a dynamic or spastic restraint
- How to perform
- Compare passive abduction awake and under general anaesthesia
- Positive finding
- Marked improvement under anaesthesia
- What it means
- The restraint is dynamic spasticity rather than fixed contracture, which changes the operative plan
- How to perform
- Supine; squeeze the examiner's fist or a dynamometer between the knees at 0, 45 and 90 degrees of hip flexion
- Positive finding
- Pain and/or reduced force
- What it means
- Adductor-related groin pain, or adductor weakness in an obturator lesion
- False positives
- Pubic-related, inguinal-related and hip-related groin pain
- How to perform
- Light touch over the distal medial thigh
- Positive finding
- Reduced sensation
- What it means
- Obturator nerve cutaneous branch involvement, which arises from the anterior division
- False positives
- Overlap with the medial cutaneous nerve of the thigh from the femoral nerve
- How to perform
- Examine adduction power and medial thigh sensation immediately after exercise provocation
- Positive finding
- Weakness and paraesthesia appearing only after exertion
- What it means
- Obturator nerve entrapment at the fascia over the short adductor at the canal exit
- False positives
- Fatigue; pain inhibition
- How to perform
- In a patient presenting with medial knee pain, examine the hip fully including log roll, FADIR and FABER
- Positive finding
- Hip signs with a normal knee examination
- What it means
- Hip pathology referring to the knee via the obturator posterior division articular branch, the classic paediatric trap
- How to perform
- Standardised AP pelvis with the legs in neutral; measure the proportion of femoral head width lateral to Perkins' line
- Positive finding
- Greater than 30 percent
- What it means
- Hip displacement requiring intervention in spastic hip disease
- False positives
- Poorly positioned radiograph; pelvic obliquity; rotation
Square the pelvis. Always square the pelvis before measuring abduction, or a pelvic obliquity will masquerade as an adductor contracture.
Complications
- Mechanism
- Medial circumflex femoral artery injury or spasm from dissection posterior to the adductor brevis, excessive traction, forced reduction, or extreme abduction in the spica
- Avoidance / management
- Work anterior to adductor brevis; limit posterior dissection; never force reduction; human position spica
- Mechanism
- Dissection behind the adductor brevis
- Avoidance / management
- Identify the anterior division as the marker and stay anterior to the muscle
- Mechanism
- Division during adductor release or medial exposure
- Avoidance / management
- Identify the nerve on the anterior surface of the brevis before dividing any muscle; neurectomy should be deliberate rather than incidental
- Mechanism
- Perforating branches of profunda femoris divided blindly as they pass through adductor brevis and magnus
- Avoidance / management
- Divide the muscle under direct vision; control perforators deliberately; do not chase a retracted vessel posteriorly
- Mechanism
- Anastomotic vessel across the superior pubic ramus divided during anterior pelvic exposure
- Avoidance / management
- Inspect and ligate within 3-6 cm of the symphysis before plating
- Mechanism
- Complete anterior branch obturator neurectomy combined with an extensive adductor release
- Avoidance / management
- Avoid or limit neurectomy; release only to about 40-45 degrees of abduction per side
- Mechanism
- Accessory obturator nerve, femoral supply to pectineus, or failure to block both divisions in a distal interfascial technique
- Avoidance / management
- Inject both interfascial planes; anticipate a residual adductor twitch; warn the operating urologist
- Mechanism
- Capsulorrhaphy and pelvic osteotomy are not possible through the medial approach
- Avoidance / management
- Counsel about the likely need for later pelvic surgery; consider an anterior approach where a bony procedure is anticipated
- Mechanism
- Release performed too late, with a high migration percentage or a deficient acetabulum
- Avoidance / management
- Adhere to surveillance schedules; add femoral and pelvic osteotomy when indicated
- Mechanism
- Crush, haematoma in an anticoagulated patient, reperfusion, prolonged compression
- Avoidance / management
- High suspicion; pain on passive hip abduction; medial thigh fasciotomy
- Mechanism
- Extensive muscle dissection, acetabular fracture surgery, head or spinal cord injury
- Avoidance / management
- Gentle handling, haemostasis, prophylaxis in high-risk patients; excise only when mature
- Mechanism
- Posterior division articular branch refers hip pain to the medial knee
- Avoidance / management
- Examine and image the hip in any child with knee pain and a normal knee
- Mechanism
- Moist contaminated area, particularly in a child in a spica or an incontinent adult
- Avoidance / management
- Meticulous closure, careful cast padding, hygiene planning, early review
Clinical Relevance
Purpose. Direct access to the inferomedial hip capsule and the structures blocking reduction of a dislocated hip. It is principally used for open reduction of developmental dysplasia of the hip in the infant, commonly quoted as most suitable under about 12-18 months, and occasionally for psoas release or biopsy of a medial lesion.
Positioning and incision. Supine with the hip flexed, abducted and externally rotated, the frog-leg position. The incision is transverse or short longitudinal over the adductor longus, beginning roughly 1-2 cm distal to the pubic tubercle and extending 4-6 cm distally and posteriorly.
The two described intervals. Know both, and know which is safer:
- Plane
- Between adductor longus and gracilis superficially, then between adductor brevis and adductor magnus deeply
- Relationship to the danger structures
- Passes POSTERIOR to the adductor brevis, bringing the surgeon close to the posterior division of the obturator nerve and to the medial circumflex femoral artery
- Plane
- Between adductor longus and adductor brevis, that is ANTERIOR to the brevis
- Relationship to the danger structures
- Keeps the surgeon anterior to the brevis, therefore away from the posterior division and further from the medial circumflex femoral artery
Sequence using the safer plane.
- Identify and tenotomise the adductor longus close to its origin
- Identify the anterior division of the obturator nerve on the anterior surface of the adductor brevis, which confirms the plane
- Develop the interval anterior to the adductor brevis, retracting the pectineus anteriorly, which also shields the femoral vessels lying on its anterior surface in the iliopectineal groove
- Identify and release the iliopsoas tendon at the level of the lesser trochanter under direct vision, a major block to reduction
- Perform the capsulotomy, excise the ligamentum teres and the pulvinar, and divide the transverse acetabular ligament
- Reduce concentrically without force, and immobilise in the human position, approximately 100 degrees of flexion and 45-55 degrees of abduction
Limitations. Capsulorrhaphy is not possible through this approach, a genuine and important limitation, and nor is a concurrent pelvic osteotomy. Residual acetabular dysplasia is common and may require later surgery. Avascular necrosis is the feared complication, with rates varying widely between series.
Injury to the medial circumflex femoral artery, or spasm from excessive traction, causes avascular necrosis of the femoral head; the original Ludloff interval passed behind the adductor brevis and brought the surgeon close to it. The safeguards: use the Ferguson modification and work anterior to the adductor brevis, take the anterior division of the obturator nerve as your marker for that plane, do not dissect posteriorly beyond what the reduction requires, never force a reduction, and avoid extreme abduction in the postoperative spica.
Surgical Relevance
Procedure by procedure, this is where the adductor brevis is met and what lies beside it at that moment:
- How adductor brevis is involved
- The defining landmark: work anterior to it (Ferguson) rather than behind it (original Ludloff)
- Structures at risk with location
- Medial circumflex femoral artery deep and posterior; posterior division of the obturator nerve behind the muscle; femoral vessels anteriorly on the pectineus
- How adductor brevis is involved
- Third structure released, partially, after adductor longus and gracilis
- Structures at risk with location
- Perforating branches of profunda femoris passing through it; posterior division of the obturator nerve behind it
- How adductor brevis is involved
- Injection anterior to it blocks the anterior division; posterior to it blocks the posterior division
- Structures at risk with location
- Femoral vessels anteriorly; obturator vessels at the canal; incomplete block if only one plane is injected
- How adductor brevis is involved
- The anterior division lies on its anterior surface and is accessible there
- Structures at risk with location
- Complete neurectomy risks an abduction contracture; the brevis may retain posterior division fibres
- How adductor brevis is involved
- The fascia over the short adductor at the obturator canal exit is divided
- Structures at risk with location
- Obturator artery branches adjacent to the nerve; the nerve itself
- How adductor brevis is involved
- Origin elevated from the inferior pubic ramus
- Structures at risk with location
- Corona mortis within 3-6 cm of the symphysis; obturator neurovascular bundle; external iliac vessels
- How adductor brevis is involved
- The compartment containing it is decompressed
- Structures at risk with location
- Perforating branches passing through the adductors; obturator nerve; saphenous vein
- How adductor brevis is involved
- The adductor brevis is the adjacent deeper muscle; gracilis must not be confused with adductor longus or brevis
- Structures at risk with location
- Ascending branch of the medial circumflex femoral artery (the gracilis pedicle); anterior division of the obturator nerve
Guidelines, Registries & Global Practice
Variation and prevalence
- The posterior division contribution to the adductor brevis is reported in a substantial proportion of anatomical dissections, so the innervation should be described as "principally the anterior division, with a variable posterior division contribution" rather than as a fixed fact.
- The level at which the obturator nerve divides varies from within the obturator canal to several centimetres distal in the thigh, which affects the reliability of a proximal versus a distal block and of a selective anterior branch neurectomy.
- An accessory obturator nerve is present in a minority of individuals, arising from L3 and L4 and crossing over the superior pubic ramus rather than through the canal. It supplies the pectineus and sometimes the hip joint, and is a recognised cause of an incomplete block.
- Corona mortis prevalence and calibre vary between anatomical series, with venous connections more frequent than arterial. The practical instruction is always to inspect and ligate rather than to rely on an expected absence.
Differences in described technique
- Emphasis relating to adductor brevis
- Describe the original Ludloff interval as passing between adductor brevis and adductor magnus; modern surgical practice has largely adopted the Ferguson modification anterior to the brevis.
- Emphasis relating to adductor brevis
- Medial open reduction generally reserved for the young infant; many surgeons prefer the anterior approach because it allows capsulorrhaphy and a concurrent pelvic procedure, citing avascular necrosis concerns with the medial route.
- Emphasis relating to adductor brevis
- Similar caution regarding medial open reduction; strong emphasis on newborn examination and selective ultrasound screening so that open reduction is needed less often.
- Emphasis relating to adductor brevis
- Stratified radiographic surveillance by GMFCS level with migration percentage as the measurement; adductor release triggered by radiographic displacement rather than by symptoms.
- Emphasis relating to adductor brevis
- Explicit warning about the corona mortis crossing the superior pubic ramus in anterior pelvic approaches and about the obturator neurovascular bundle during anterior column fixation.
- Emphasis relating to adductor brevis
- Ultrasound-guided distal interfascial obturator block using the adductor brevis as the sonographic landmark, with separate injections for each division; proximal canal block where a single injection is preferred.
Registry and outcome signals
- Hip surveillance programmes for cerebral palsy have demonstrated a measurable reduction in the rate of hip dislocation where implemented systematically, which is the strongest argument for programme-based rather than opportunistic radiographic review.
- Developmental dysplasia screening programmes determine how often open reduction is needed at all: the requirement for open reduction is strongly dependent on age at diagnosis, so effective newborn examination and selective ultrasound screening reduce the number of medial and anterior open reductions performed.
- There is no registry of adductor surgery, and reported outcomes for adductor release in cerebral palsy come from single-centre cohorts. Note that the intuitive selection variables do not survive contact with the data: in the carded Presedo series neither age at surgery nor preoperative migration percentage predicted outcome, while ambulatory status did, and the migration percentage at one year after surgery was the strongest predictor of all. Plan on walking ability, then watch the one-year film.
High- versus limited-resource practice
- Well-resourced settings: preoperative arthrography before open reduction, ultrasound-guided obturator nerve blocks with interfascial targeting, MRI and post-exercise electromyography for suspected obturator neuropathy, 3D CT for acetabular fracture planning including corona mortis identification, and digital measurement of migration percentage within a formal surveillance programme.
- Limited-resource settings: the medial approach is attractive because it is small, quick and needs no special equipment, but it demands anatomical discipline — work anterior to the adductor brevis and use the anterior division of the obturator nerve as the marker. Hip surveillance in cerebral palsy needs only a correctly positioned AP pelvis radiograph and a ruler, which makes it one of the highest-value low-cost interventions in paediatric orthopaedics. Adductor release requires no implants. A landmark obturator nerve block at the canal is entirely feasible without ultrasound.
- Universal principles: name what separates the obturator divisions; work anterior to the adductor brevis in any medial hip exposure; divide the adductors under direct vision because the profunda femoris perforators pass through them; inspect for a corona mortis before plating the superior pubic ramus; measure migration percentage rather than waiting for pain; and never promise that an obturator block or neurectomy will abolish adduction.
Related pages: Obturator Nerve Anatomy is the structure this muscle is defined by - the anterior division in front of it, the posterior division behind - and the page to read alongside this one. Adductor Longus, Adductor Magnus, Gracilis and Pectineus complete the medial compartment and its layered planes, with adductor brevis lying deep to pectineus and longus and superficial to magnus. Adductor Groin Strain, Athletic Groin Pain and Athletic Pubalgia are the differential for the exertional medial thigh pain that obturator entrapment imitates. Developmental Dysplasia of the Hip and DDH Treatment Options are the setting for the medial (Ludloff) approach in which the safe plane runs anterior to this muscle, and Avascular Necrosis of the Hip is what that discipline exists to prevent. Cerebral Palsy Hip Surveillance and Windswept Deformity frame the adductor release, where migration percentage rather than symptoms drives the decision.
MCQ Practice Points
Q: Which muscle separates the anterior and posterior divisions of the obturator nerve in the thigh? A: The adductor brevis. The anterior division lies on its anterior surface, the posterior division on its posterior surface. In the pelvis and canal it is the obturator externus that separates them.
Q: Give the origin and insertion of the adductor brevis. A: Origin — the outer surface of the body and inferior ramus of the pubis, between the gracilis origin below and the obturator externus above. Insertion — the upper third of the medial lip of the linea aspera (proximal to the adductor longus insertion).
Q: Which plane is safest in the medial approach to the hip, and why? A: Anterior to the adductor brevis (Ferguson modification). The posterior division of the obturator nerve and the medial circumflex femoral artery both lie posterior to the brevis, and the MCFA is the dominant blood supply to the adult femoral head.
Q: What supplies the adductor brevis? A: Principally the anterior division of the obturator nerve (L2, L3, L4), with a contribution from the posterior division in a substantial proportion of individuals.
Q: Which vessels pass through the adductor brevis and adductor magnus? A: The perforating branches of the profunda femoris artery, typically three to four, on their way to the posterior compartment. Blind division bleeds from a vessel that retracts into muscle.
Q: Why does hip pathology refer pain to the medial knee? A: The posterior division of the obturator nerve gives an articular branch to the knee, descending with the popliteal artery through the adductor hiatus to the posterior capsule. A child with knee pain and a normal knee must have the hip examined.
Q: In what order are the adductors released for spastic hip displacement, and what is the target? A: Adductor longus, then gracilis, then adductor brevis (partial), then pectineus if needed. Target approximately 40-45 degrees of abduction per side.
Q: Why is the adductor brevis often the residual restraint after longus and gracilis release? A: Its fibres are short and relatively transverse, so it has a good adduction moment arm but very little excursion and tolerates lengthening poorly.
Q: Why does a distal ultrasound-guided obturator nerve block require two injections? A: Because the adductor brevis separates the divisions. Injection anterior to it blocks the anterior division; injection posterior to it blocks the posterior division. A single plane blocks only one division.
Q: Give three anatomical reasons an obturator nerve block may fail to abolish adduction. A: An accessory obturator nerve passing over the superior pubic ramus rather than through the canal; the femoral nerve branch to the pectineus; and the tibial (sciatic) supply to the ischiocondylar part of adductor magnus. Add failure to block both divisions in a distal technique.
Q: Is the adductor brevis useful as a flap or transfer donor? A: No — it has no single dominant pedicle and a short, broad, low-excursion architecture. The useful medial thigh donor is the gracilis, on the ascending branch of the medial circumflex femoral artery with a long tendon and a single dominant nerve.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are performing a medial open reduction for a dislocated hip in a 9-month-old. Your consultant asks you to describe exactly which plane you will use and to justify it anatomically. What do you say?”
“A urologist calls you for anatomical advice. During transurethral resection of a lateral bladder wall tumour, the patient's leg jerked into adduction despite what the anaesthetist described as a successful obturator nerve block. Explain why, using the anatomy.”
“You are performing an adductor release in a 6-year-old with spastic diplegia and a migration percentage of 38 percent. After adductor longus tenotomy and gracilis release, passive abduction is only 25 degrees. What do you do next and what are you cutting toward?”
Anatomy
- Origin: outer surface of body and inferior ramus of pubis, between gracilis below and obturator externus above
- Insert: upper third of the medial lip of the linea aspera
- Middle plane: deep to pectineus and adductor longus, superficial to adductor magnus
- Short, triangular, transverse fibres — good moment arm, little excursion
- Nerve: obturator anterior division principally, variable posterior division contribution, L2-L4
The Nerve Landmark
- Anterior division lies ANTERIOR to adductor brevis
- Posterior division lies POSTERIOR to adductor brevis
- In the pelvis, obturator externus separates the divisions
- Anterior division: longus, brevis, gracilis, pectineus, medial thigh skin, hip joint
- Posterior division: adductor magnus (adductor part), obturator externus, KNEE joint branch
Medial Approach
- Ludloff original: BEHIND adductor brevis (brevis / magnus)
- Ferguson modification: ANTERIOR to adductor brevis — safer
- MCFA deep and posterior: femoral head blood supply
- Release psoas at lesser trochanter, ligamentum teres, pulvinar, transverse acetabular ligament
- No capsulorrhaphy possible
- Spica: 100 degrees flexion, 45-55 degrees abduction
Blocks and Nerve Problems
- Obturator canal 2-3 cm inferolateral to pubic tubercle
- Distal interfascial block needs TWO injections (either side of brevis)
- Incomplete block: accessory obturator nerve, femoral supply to pectineus, ischiocondylar magnus via sciatic
- Entrapment site: fascia over the short adductor at the canal exit
- Post-exercise EMG of adductors is the key test
- Posterior division knee branch explains referred medial knee pain
Release and Pitfalls
- Order: longus, gracilis, brevis (partial), pectineus; target 40-45 degrees
- Brevis is often the residual restraint (short transverse fibres)
- Profunda femoris perforators pass THROUGH brevis and magnus
- Avoid complete obturator neurectomy — abduction contracture
- Migration percentage over 30 percent triggers release; over 50-60 percent needs bony surgery
- Not a flap or transfer donor — use gracilis instead
Evidence Base
Anatomy of the Medial Femoral Circumflex Artery and Its Surgical Implications
- Detailed cadaveric dissection of the medial femoral circumflex artery and its terminal branches
- The deep branch is the dominant blood supply to the femoral head, entering at the posterosuperior head-neck junction
- The vessel passes deep to the pectineus and between the obturator externus and the quadratus femoris
- Defined safe zones for surgical hip exposure based on preserving this vessel
Open Reduction Through a Medial Approach for Congenital Dislocation of the Hip: A Critical Review of the Ludloff Approach in Sixty-Six Hips
- Critical review of a consecutive series of hips treated by medial open reduction
- Reduction was achieved in the majority through a small incision with minimal blood loss
- Avascular necrosis occurred in a substantial minority of hips
- Capsulorrhaphy is not possible through the medial approach, and residual dysplasia often required later surgery
Obturator Nerve Entrapment: A Cause of Groin Pain in Athletes
- Series of athletes with exercise-induced medial thigh pain due to obturator nerve entrapment
- Pain began after minutes of exercise, with adductor weakness and medial thigh paraesthesia
- Electromyography performed after exercise provocation was the most useful diagnostic test
- Surgical release of the fascia over the short adductor at the obturator canal exit allowed return to sport
Soft-Tissue Releases to Treat Spastic Hip Subluxation in Children with Cerebral Palsy
- 65 children (129 hips) with cerebral palsy treated by open adductor tenotomy plus psoas recession or iliopsoas tenotomy, followed for a mean of 10.8 years
- Outcomes: 49% good, 17% fair, 4% poor and 30% OUTRIGHT FAILURE - soft-tissue release prevented dislocation long term in 67% overall
- 19 of 65 children required subsequent OSSEOUS reconstruction and 11 required repeat soft-tissue release
- NEITHER preoperative migration percentage NOR age at surgery significantly affected the outcome - a direct contradiction of the usual teaching that these are the selection variables
- The two factors that did predict success were the ability to WALK preoperatively and a spastic diplegic pattern (p=0.01); the migration percentage at ONE YEAR POSTOPERATIVELY was the strongest predictor of all (p=0.001)
Hip Displacement in Cerebral Palsy
- Population-based study of hip displacement in children with cerebral palsy
- Overall incidence of hip displacement was approximately one in three children
- Incidence rose progressively with GMFCS level, from very low in GMFCS I to the majority in GMFCS V
- Displacement related to gross motor function rather than to clinical subtype alone
Ultrasound-Guided Obturator Nerve Block: A Focused Review on Anatomy and Updated Techniques
- Review of obturator nerve anatomy and of ultrasound-guided block techniques, classified by whether the approach is distal or proximal
- Indications include preventing the thigh adductor jerk during transurethral resection of bladder tumour, analgesia for knee surgery, hip pain and persistent hip adductor spasticity
- In the distal approach the transducer is placed at the inguinal crease and the anterior and posterior branches are blocked by two separate injections into the interfascial planes
- The proximal approach targets the common obturator nerve before it divides and therefore needs a single injection