The Biarticular Engine and the Workhorse Flap of the Proximal Tibia
- Two heads: the medial from the posterior aspect of the medial femoral condyle above the adductor tubercle, the lateral from the lateral aspect of the lateral femoral condyle.
- The medial sural cutaneous nerve (which becomes the sural nerve) arises from the tibial nerve and runs in the groove BETWEEN the two heads before piercing the deep fascia at about mid-calf.
- Each head is supplied by its own sural artery from the popliteal artery, entering the deep surface within about 3-5 cm of the origin — a Mathes-Nahai type I muscle.
- The medial head is longer than the lateral by roughly 3-5 cm, has a wider arc, and is not adjacent to the common peroneal nerve — which is why it is the flap of choice.
- The Silfverskiold test separates isolated gastrocnemius contracture (dorsiflexion improves with the knee flexed) from a combined gastrocnemius-soleus contracture.
- “The fabella is a sesamoid in the lateral head of gastrocnemius, present in a variable minority of knees, and can be mistaken for a loose body.
- “An aberrant medial head of gastrocnemius is the commonest anatomical cause of popliteal artery entrapment syndrome.
- “In cerebral palsy, over-lengthening the Achilles produces an irreversible calcaneus gait and crouch — this is why gastrocnemius recession is preferred in ambulant diplegia.
- “Tennis leg is a tear at the medial gastrocnemius musculotendinous junction, not a plantaris rupture.
Overview
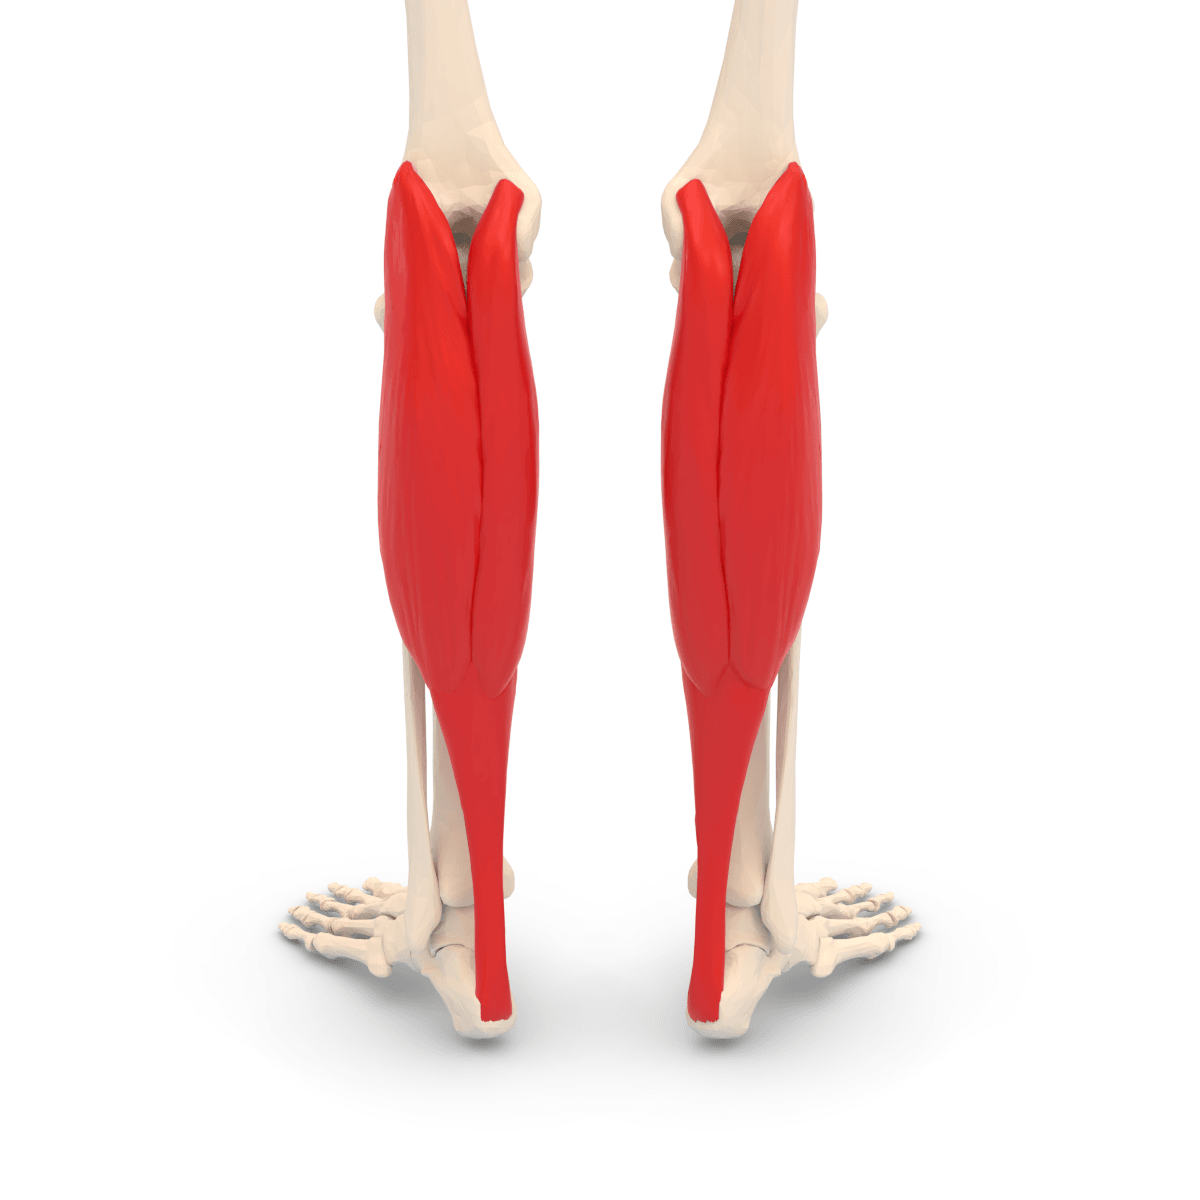
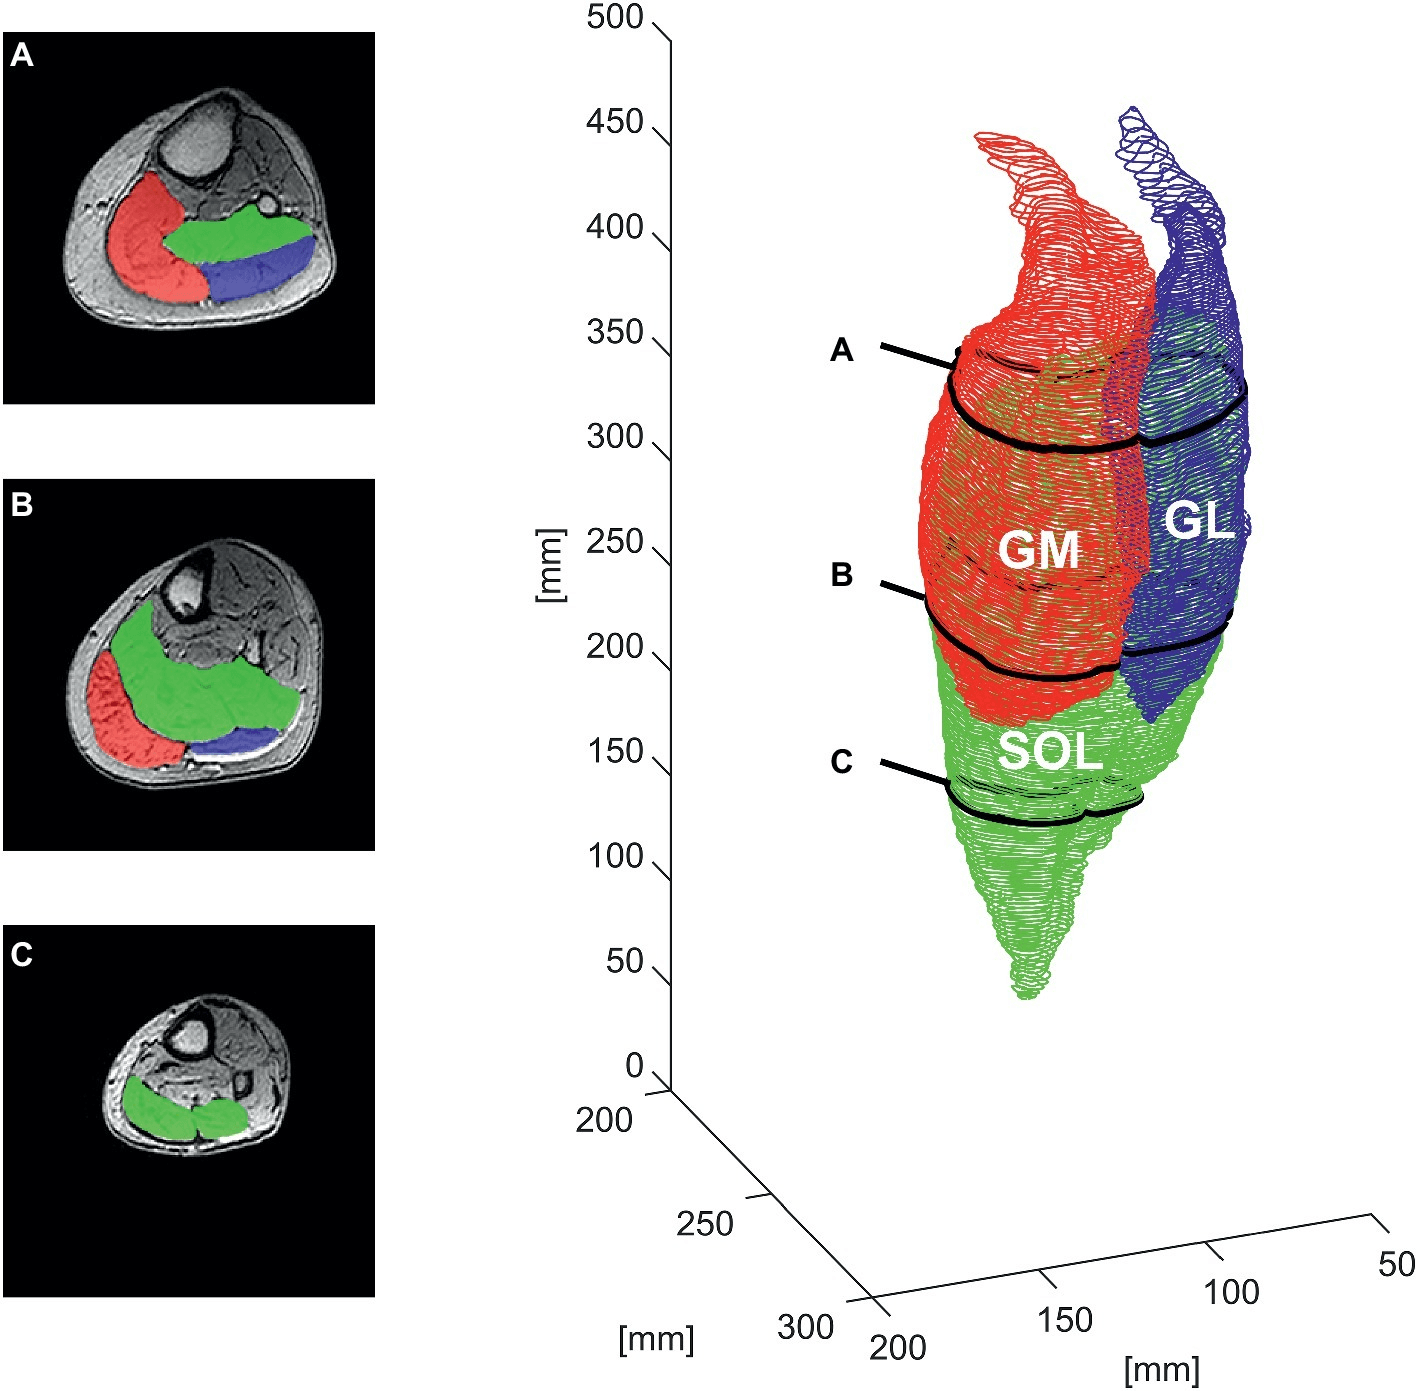
Gastrocnemius is the most superficial and most powerful muscle of the calf, forming the visible bulk of the posterior leg. It arises by two heads from the posterior aspect of the femoral condyles, and with soleus it forms the triceps surae, converging into the Achilles (calcaneal) tendon. Three features recur in every clinical question about it.
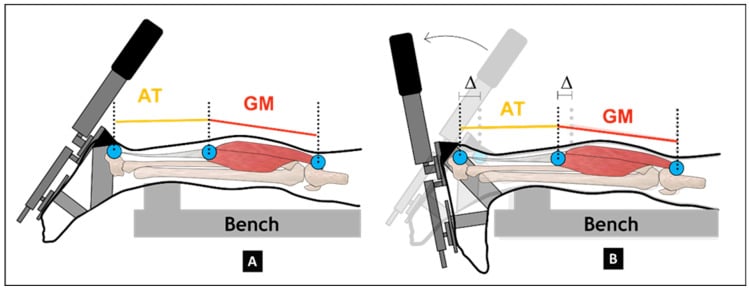
It is biarticular. Crossing both the knee and the ankle, its effective length depends on knee position, which is the entire basis of the Silfverskiold test and of gastrocnemius recession as a procedure distinct from Achilles lengthening.
It has a single dominant pedicle to each head. It is a Mathes-Nahai type I muscle, meaning the whole head survives on one artery. This is what makes the medial gastrocnemius rotation flap the workhorse for soft tissue cover over the knee and the proximal third of the tibia.
Its medial musculotendinous junction is a common injury site. The muscle is biarticular, has a high proportion of type II fast-twitch fibres, and is loaded eccentrically at high length: the classic recipe for a musculotendinous strain, and the pathology of tennis leg.
Attachments, Innervation and Relations
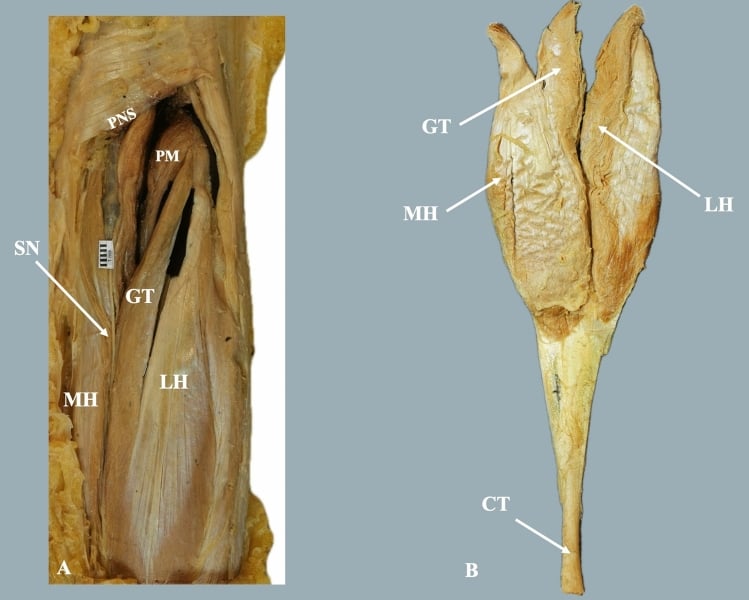
Origins. The medial head arises from the posterior aspect of the medial femoral condyle, immediately proximal and posterior to the adductor tubercle, and from the adjacent posterior capsule of the knee; it is the larger and longer of the two. The lateral head arises from the lateral aspect of the lateral femoral condyle, immediately proximal to the lateral epicondyle, and from the adjacent posterior capsule and the supracondylar line. Both heads receive a contribution from the oblique popliteal ligament and the posterior capsule.
The fabella. A sesamoid bone within the tendon of the lateral head, present in a variable minority of knees. It articulates with the lateral femoral condyle and gives attachment to the fabellofibular ligament. It is a recognised radiographic mimic of a loose body and a rare cause of posterolateral knee pain (fabella syndrome) and of common peroneal nerve irritation.
Length asymmetry, the flap number. The medial head extends 3-5 cm further distally than the lateral head, the single most practically useful dimension on this page. The medial head is therefore longer, has a larger surface area and reaches further, which, combined with the absence of the common peroneal nerve on the medial side, is why it is the flap of choice and the lateral head a second choice used mainly for lateral defects.
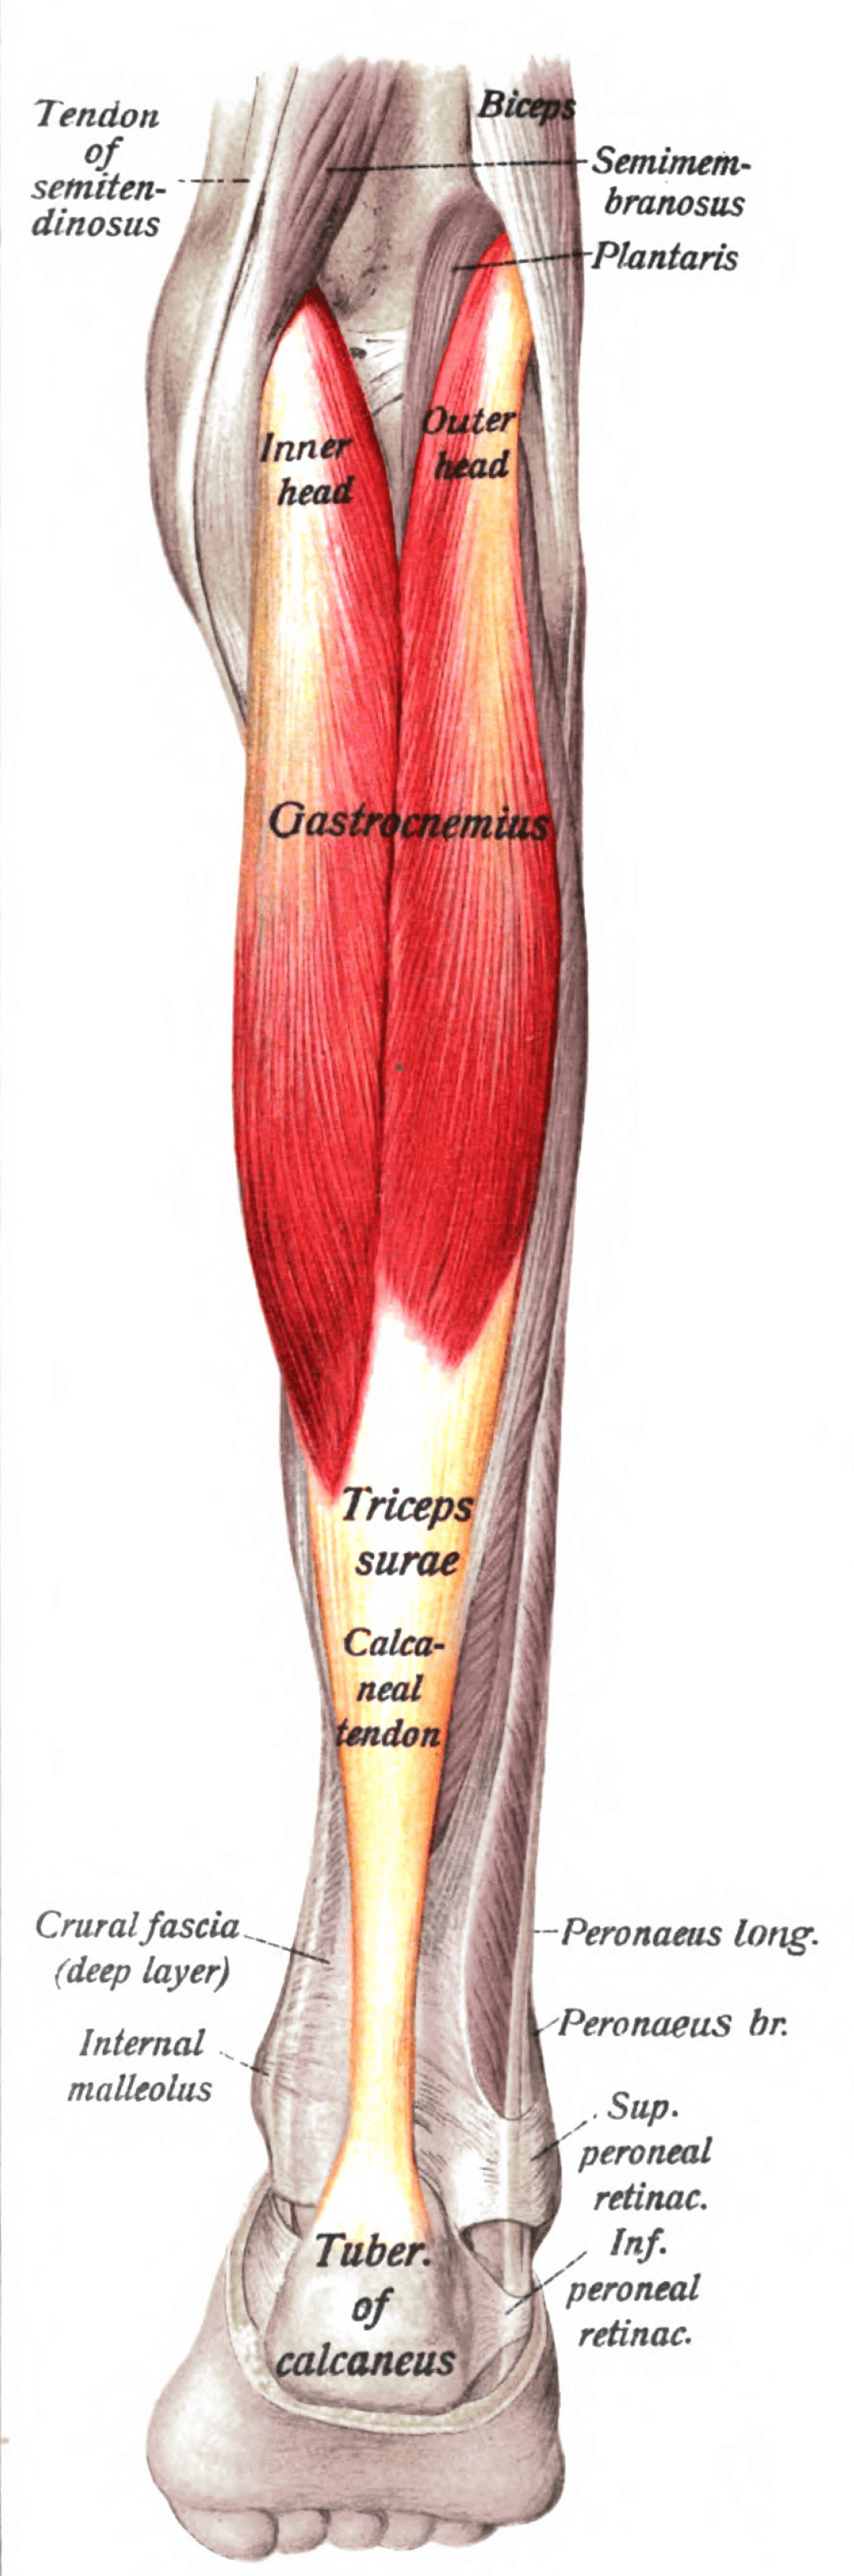
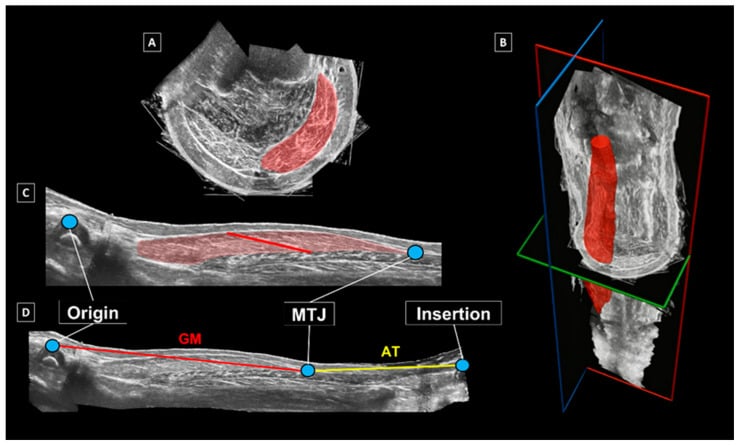
Insertion. The two heads converge and their aponeuroses fuse at about the midpoint of the calf, forming a broad aponeurosis on the deep surface. This fuses with the aponeurosis of soleus to form the Achilles tendon, typically at the junction of the middle and distal thirds of the leg, and the tendon inserts into the middle third of the posterior surface of the calcaneal tuberosity, with the retrocalcaneal bursa deep to it and the subcutaneous (superficial) calcaneal bursa between the tendon and the skin.
The spiral. The Achilles tendon spirals through roughly 90 degrees as it descends, so that fibres originating medially insert posterolaterally on the calcaneus. The spiral concentrates stress at the hypovascular watershed zone 2-6 cm above the insertion, the site of both midportion tendinopathy and the majority of ruptures.
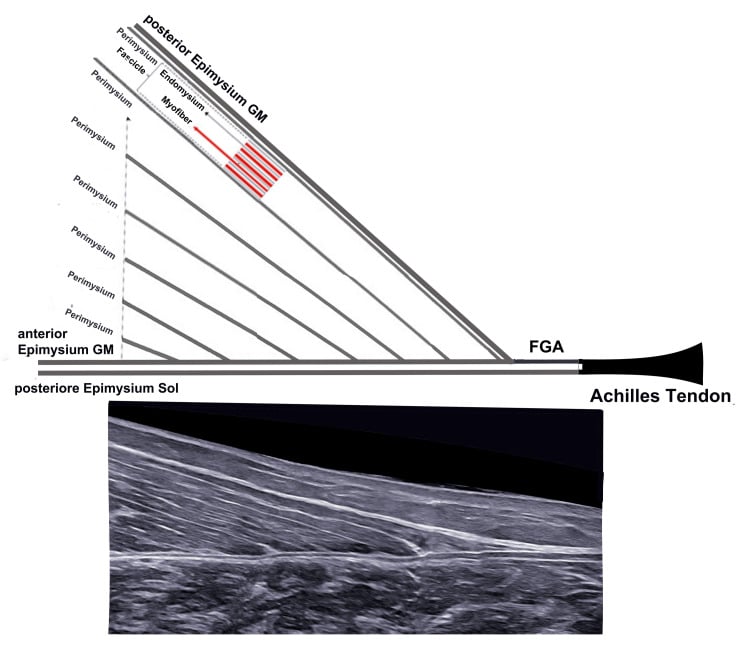
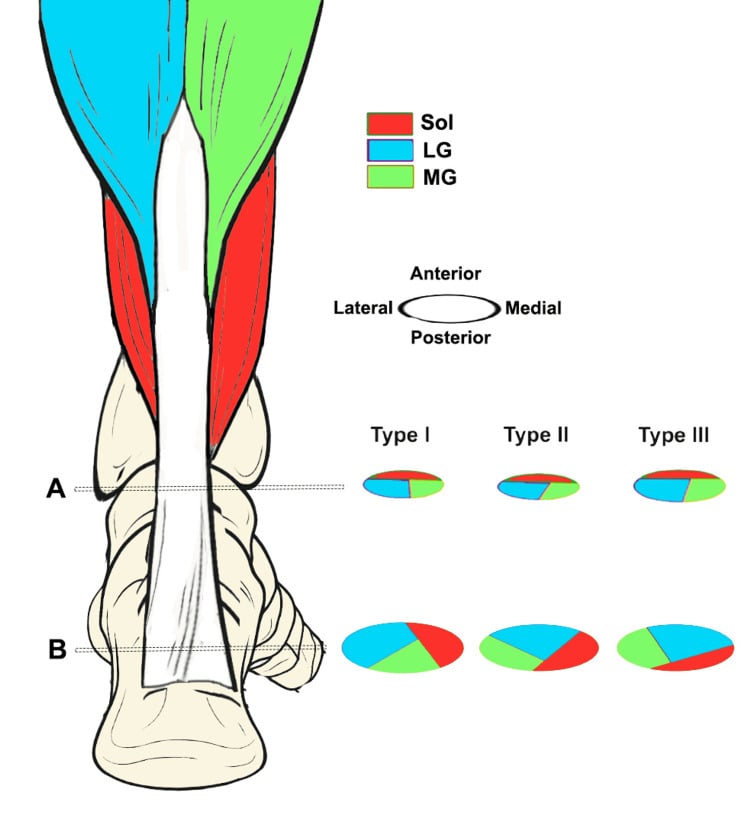
The musculotendinous junction. The medial gastrocnemius musculotendinous junction lies roughly at the junction of the middle and distal thirds of the calf. It is the site of the tennis leg tear and the level at which a Strayer recession divides the aponeurosis.
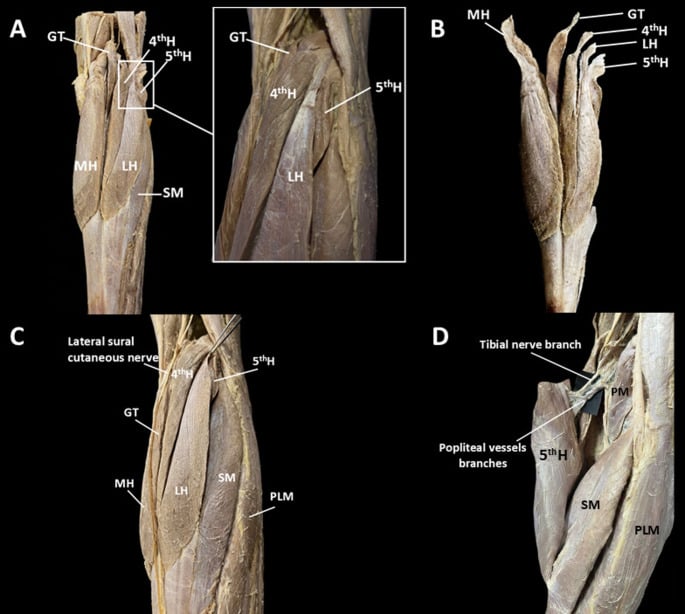
Variants. Accessory heads occur. A five-headed gastrocnemius is a popliteal fossa variant whose accessory heads can lie beside the neurovascular bundle and alter dissection planes or compress the popliteal vessels and tibial nerve. Gastrocnemius tertius is an accessory head that may arise from either condyle and pass close to the popliteal neurovascular bundle; recognise it on imaging and during posterior approaches.
Action and Biomechanics
Actions. Ankle plantar flexion is the dominant action, and the power source for push-off in gait and for jumping and sprinting. Knee flexion is a secondary action, most effective when the ankle is dorsiflexed, and the heads reinforce the posterior capsule and contribute to resisting hyperextension. In stance the muscle decelerates forward progression of the tibia over the fixed foot, an eccentric role that dominates mid-stance and is the reason a contracture is so disabling.
Fibre type. Gastrocnemius is relatively rich in type II (fast-twitch) fibres, suited to rapid, powerful, short-duration contraction: sprinting, jumping, push-off. Soleus is predominantly type I (slow-twitch), suited to sustained postural work and standing balance. The difference explains the injury patterns, gastrocnemius sustaining acute strains during explosive eccentric loading and soleus sustaining overuse injuries in endurance runners, and it sets the rehabilitation: load gastrocnemius with knee-extended heel raises and plyometrics, and soleus with knee-flexed heel raises. Both are needed.
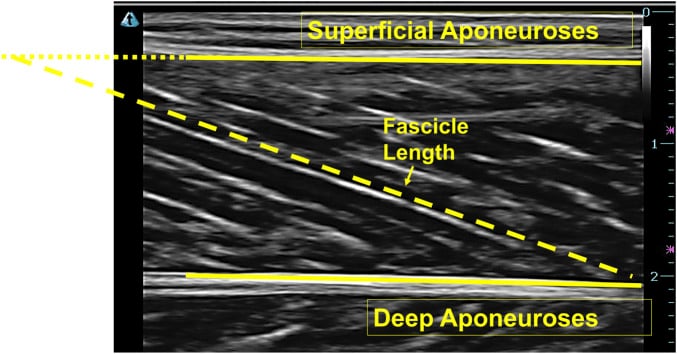
The biarticular consequence. Gastrocnemius cannot shorten maximally at both joints at once: it is at maximal length with the knee extended and the ankle dorsiflexed, and at minimal length with the knee flexed and the ankle plantar flexed. With the knee extended it is at its longest, so ankle dorsiflexion is limited by whatever tightness exists in it; flex the knee to 90 degrees and the femoral origin moves closer to the calcaneus, the muscle slackens, and any remaining limitation to dorsiflexion must come from soleus, the Achilles tendon or the joint itself. That is the whole logic of the Silfverskiold test.
Maximal length is the position of injury as well as the test position: the lunge with the knee extending and the ankle dorsiflexing is the mechanism of tennis leg. At the other extreme, with the knee fully flexed gastrocnemius cannot generate effective plantar flexion (active insufficiency), which is why a knee-flexed heel raise tests soleus.
The equinus cascade. An isolated gastrocnemius contracture limits ankle dorsiflexion in stance with the knee extended, and the body must find dorsiflexion somewhere. The compensations, in order of appearance:
- Early heel rise in terminal stance
- Increased forefoot loading and metatarsalgia
- Midfoot dorsiflexion: the foot breaks in the middle, producing midfoot pain and, over time, arch collapse
- Subtalar eversion and forefoot abduction, contributing to adult acquired flatfoot deformity
- Increased plantar fascia strain, producing plantar fasciitis
- Genu recurvatum at the knee in some patients
In the neuropathic foot this cascade produces forefoot ulceration and, in the presence of Charcot neuroarthropathy, midfoot collapse. An equinus contracture is therefore a driver of forefoot and midfoot pathology, not merely an incidental finding, and correcting it is a legitimate adjunct in the treatment of plantar fasciitis, metatarsalgia, flatfoot and the neuropathic ulcer.
Surface Anatomy and Examination
Palpation. The two heads are readily visible and palpable in the proximal calf, particularly on a single-leg heel raise; the medial head is the larger and more prominent and extends further distally. The medial musculotendinous junction, the tennis leg site, is palpable medially at the junction of the middle and distal thirds of the calf. The Achilles tendon is palpable throughout, and the watershed zone is where a rupture gap is usually found. The sural nerve may be rollable subcutaneously just lateral to the Achilles in a thin patient.
Named tests. Comparing a knee-extended with a knee-flexed heel raise is the functional equivalent of the Silfverskiold test; the rest of the table covers the tendon, the injury and the nerve.
- How to perform
- Measure ankle dorsiflexion with the hindfoot held in neutral and the knee extended, then with the knee flexed to 90 degrees
- Positive finding
- Dorsiflexion improves by more than about 10 degrees with the knee flexed
- What it means
- Isolated gastrocnemius contracture — amenable to gastrocnemius recession
- False positives
- Allowing subtalar and midfoot motion to masquerade as ankle dorsiflexion — the commonest error; always lock the hindfoot in neutral
- How to perform
- Prone, feet over the end of the couch; squeeze the calf mass
- Positive finding
- No passive plantar flexion of the foot
- What it means
- Complete Achilles rupture
- False positives
- An intact deep posterior compartment can produce a small misleading movement — squeeze firmly and compare sides
- How to perform
- Prone; the patient actively flexes both knees to 90 degrees
- Positive finding
- The affected foot falls into neutral or dorsiflexion instead of resting plantar flexion
- What it means
- Achilles rupture; complements the Thompson test
- False positives
- Ankle stiffness or a fixed contracture altering the resting position
- How to perform
- Standing on one leg, repeated heel raises to full height
- Positive finding
- Fewer than about 25 repetitions, or inability to reach full height
- What it means
- Gastrocnemius weakness or Achilles insufficiency
- False positives
- Pain inhibition; poor balance; hallux rigidus limiting the windlass
- How to perform
- Same, with the knee flexed about 20-30 degrees
- Positive finding
- Weakness in this position with a normal knee-extended raise
- What it means
- Soleus-specific weakness — gastrocnemius is slackened and cannot compensate
- False positives
- Quadriceps fatigue from maintaining knee flexion
- How to perform
- Palpate the medial musculotendinous junction at the junction of the middle and distal thirds of the calf
- Positive finding
- Focal tenderness with or without a palpable defect and distal ecchymosis
- What it means
- Medial gastrocnemius musculotendinous tear
- False positives
- Deep vein thrombosis; ruptured Baker cyst; soleus strain
- How to perform
- Percuss just lateral to the Achilles tendon, 9-12 cm above the insertion
- Positive finding
- Radiating dysaesthesia to the lateral foot and fifth toe
- What it means
- Sural nerve injury or neuroma after calf or Achilles surgery
- False positives
- Any healing incision producing local sensitivity
The Silfverskiold test, done properly. Hold the hindfoot in neutral (or slight inversion) with the subtalar joint locked, and measure ankle dorsiflexion with the knee extended and then flexed to 90 degrees. If the hindfoot is not locked, the midfoot and subtalar joint contribute apparent dorsiflexion and you will underestimate the contracture; this is the single most common examination error, and getting it wrong is how a combined contracture gets a gastrocnemius recession and fails. Apply the dorsiflexion force through the heel, not the forefoot, since pushing on the forefoot dorsiflexes the midfoot rather than the ankle, and measure with a goniometer against the lateral border of the leg and the plantar aspect of the heel.
Reading it. Dorsiflexion that improves with the knee flexed means an isolated gastrocnemius contracture, because gastrocnemius is the only structure that changed. Dorsiflexion equally limited in both positions means a combined gastrocnemius-soleus contracture, or a bony block, and the operation is chosen accordingly under Contracture and Recession.
Thresholds, and why the number you choose decides the answer. Ankle dorsiflexion of less than 5 to 10 degrees with the knee extended, improving by more than about 10 degrees with the knee flexed, defines an isolated gastrocnemius contracture. Different authors quote different cut-offs, and the difference is not cosmetic. In DiGiovanni's matched case-control study, defining contracture as 5 degrees or less found it in 65 per cent of symptomatic patients against 24 per cent of asymptomatic controls; relaxing the definition to 10 degrees or less found it in 88 per cent of patients but also in 44 per cent of controls. At the looser cut-off nearly half of normal people test positive, so a positive Silfverskiold at 10 degrees is close to a coin toss for abnormality. Use the 5-degree threshold when the test is being used to decide, and treat the result as one finding among several rather than an indication in itself.
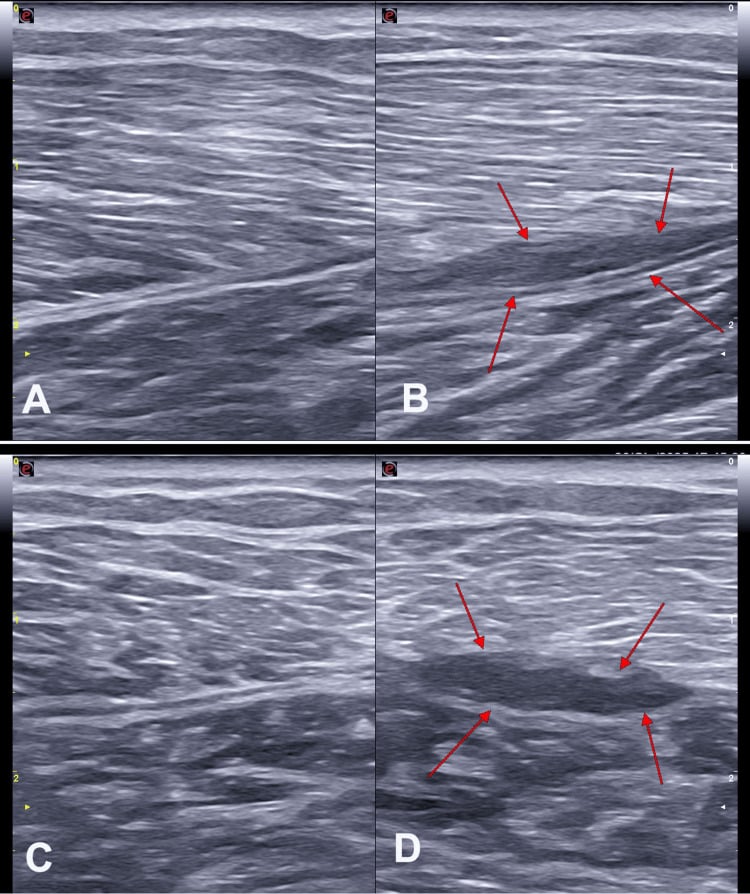
Imaging. Ultrasound is the investigation of choice for tennis leg, showing a hypoechoic collection between the medial gastrocnemius and soleus with or without a visible disruption, and for assessing the Achilles. MRI grades the extent of a musculotendinous tear and identifies free tendon involvement, the main prognostic factor for return to sport. Duplex venous ultrasound is mandatory in any acute painful swollen calf before attributing it to a muscle tear or a ruptured cyst. Weight-bearing lateral foot radiographs are used in the assessment of equinus-associated midfoot collapse and flatfoot, and CT or MR angiography with provocative manoeuvres where popliteal artery entrapment is suspected.
Complications
Flap-related. Flap necrosis, partial or complete, comes most often from a strangling tunnel, excessive tension, or pedicle injury during the origin release, and is prevented by identifying the pedicle early, a generous tunnel and a tension-free inset. Distal skin paddle necrosis in a myocutaneous flap follows a paddle designed beyond the reliable perforator territory, and skin graft failure over the transposed muscle follows haematoma, shear or infection. The donor morbidity, contour deformity, reduced plantar flexion endurance and sural nerve injury from a raphe divided blind, is set out under The Flap.
Recession-related. Sural nerve injury is the commonest complication of a Strayer recession, because the nerve lies exactly at the operative level, and is prevented by an open technique with the nerve identified. Over-lengthening and plantar flexion weakness is mild after a gastrocnemius recession and potentially severe after an Achilles lengthening; calcaneus gait and crouch is the catastrophic and irreversible complication of over-lengthening the Achilles in an ambulant child with cerebral palsy. Under-correction and recurrence occur particularly with a Baumann recession, in growing children, and where a combined contracture was misdiagnosed as isolated; reassess the Silfverskiold test intra-operatively. Wound problems in the calf are commoner in diabetic and vasculopathic patients, and a percutaneous lengthening can produce an iatrogenic Achilles rupture.
Injury-related. A missed deep vein thrombosis in a patient with an acute calf haematoma is the single most dangerous diagnostic error in this territory. The others are a missed Achilles rupture from relying on a single Thompson test, a missed deep posterior compartment at fasciotomy from inadequate detachment of soleus from the tibia, and chronic calf pain and recurrent strain after an inadequately rehabilitated tennis leg, the muscle needing to be loaded with the knee both extended and flexed.
Clinical Relevance
The workhorse. The medial gastrocnemius flap is the workhorse for soft tissue cover over the knee and the proximal third of the tibia; for a fellowship examination, this is the single most important thing to know about gastrocnemius. The tibia is reconstructed by thirds, and the table gives the first choice for each.
- First-choice flap
- Medial gastrocnemius rotation flap
- Rationale
- Type I muscle, reliable single pedicle, adequate arc, low donor morbidity
- Caveats
- Reach limited to the superior pole of the patella; score the aponeurosis for more
- First-choice flap
- Soleus flap, medially based
- Rationale
- Segmental supply from the posterior tibial artery permits a proximally based rotation
- Caveats
- Less reliable than gastrocnemius; check the vascular status of the leg
- First-choice flap
- Free tissue transfer
- Rationale
- No local muscle has adequate reach; the local tissue is often traumatised
- Caveats
- Requires microsurgical facilities and a suitable recipient vessel
- First-choice flap
- Lateral gastrocnemius flap
- Rationale
- Local, adequate for lateral defects
- Caveats
- Shorter reach; common peroneal nerve at risk; may need fibular head osteotomy
- First-choice flap
- Both gastrocnemius heads, or a free flap
- Rationale
- Maximises local coverage
- Caveats
- Significant plantar flexion loss; make it a conscious decision
For the distal third, a local fasciocutaneous or perforator flap is the alternative to free tissue transfer.
Why the medial head rather than the lateral. Its extra length and size give greater reach, and its arc of rotation covers the medial and anterior knee and proximal tibia more effectively. The common peroneal nerve lies adjacent to the lateral head at the fibular neck and is at risk during a lateral harvest, and a lateral harvest may require fibular head osteotomy to gain reach, further endangering the nerve.
Arc of rotation and reach. The standard reach is the superior pole of the patella anteriorly, the medial and anterior knee, and the proximal third of the tibia. To gain further reach, in escalating order:
- Complete release of the muscle's origin from the femoral condyle, which adds several centimetres
- Scoring the deep aponeurosis transversely in multiple places (like scoring a mesh graft), which lengthens the flap without dividing muscle fibres; the most useful and the safest manoeuvre
- Dividing the Achilles insertion of the medial head aponeurosis distally, extending the flap distally
- Tunnelling the flap beneath the deep fascia to the defect, with a tunnel generous enough not to strangle the pedicle
- Freeing the pedicle back toward the popliteal artery, the last resort, and the one that risks the flap
Both heads can be raised together for a very large defect, at the cost of significant plantar flexion power, which is generally acceptable in a limb-salvage setting but should be a conscious decision.
Harvest.
- Position supine with a tourniquet and the knee flexed, or lateral. Mark the posterior midline of the calf and the medial border of the tibia
- A longitudinal posteromedial incision approximately 2 cm posterior to the posteromedial border of the tibia, from just below the knee to the mid-calf; keeping 2 cm posterior to the tibial border protects the subcutaneous perforators of the skin over the tibia
- Incise the deep fascia and identify the medial head
- Develop the plane between gastrocnemius and soleus, the key interval: a clean, avascular plane, but the plantaris tendon runs within it and can be divided
- Identify the midline raphe between the two heads, where the sural nerve lies; protect it, and divide the raphe to separate the medial head from the lateral
- Divide the distal aponeurosis of the medial head, taking as much length as the defect requires
- Identify and protect the medial sural artery pedicle entering the deep surface
- Release the origin and score the aponeurosis if more reach is needed
- Tunnel or rotate the flap to the defect and inset without tension
- Cover the muscle with a split-thickness skin graft, immediately or as a delayed procedure
- Close the donor site over a drain; the defect is closed directly in almost all cases
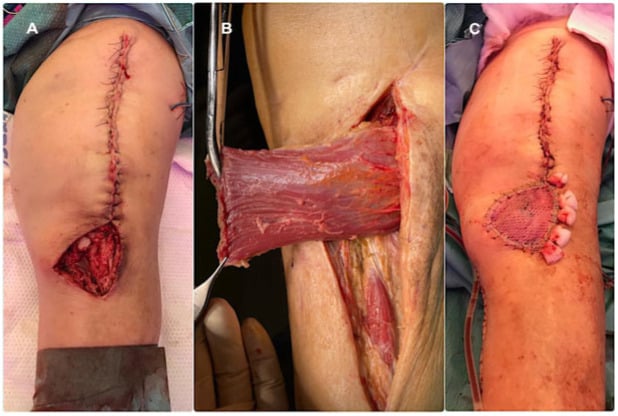
Donor morbidity. Plantar flexion power is reduced but generally well compensated by the soleus and the remaining head; most patients regain the ability to perform a single-leg heel raise, though with reduced endurance. There is a contour deformity, a visible flattening of the medial calf which some patients find cosmetically troubling, and the risks of sural nerve injury if the intermuscular raphe is divided without identifying the nerve, and of donor site seroma and haematoma. The overall morbidity is low enough that the flap remains the first choice for the proximal third, even in comparison with free tissue transfer.
Salvage. Monitor the flap clinically, by colour, turgor and bleeding on pinprick, and with a monitoring skin island where one is available. Venous congestion is the commoner failure mode, a dusky, swollen flap with brisk dark bleeding; check the tunnel first, because a tight tunnel strangling the pedicle is the commonest correctable cause. Arterial insufficiency gives a pale, cool flap with no bleeding: check for a kinked or twisted pedicle, excessive tension, or a haematoma compressing the pedicle.
Take the patient back early. A flap that is failing at 6 hours is salvageable; one that is failing at 48 hours is not. Prevention is a generous tunnel or an open transposition, tension-free inset, meticulous haemostasis, and a drain that does not lie on the pedicle.
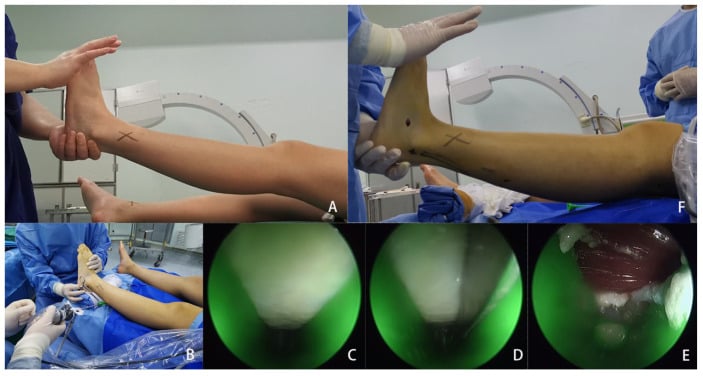
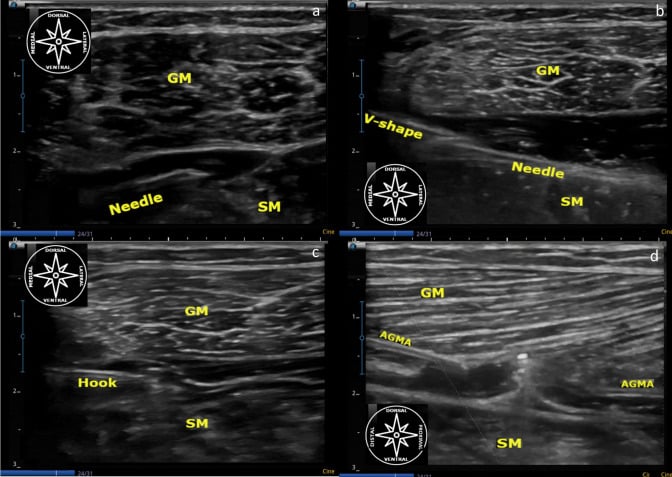
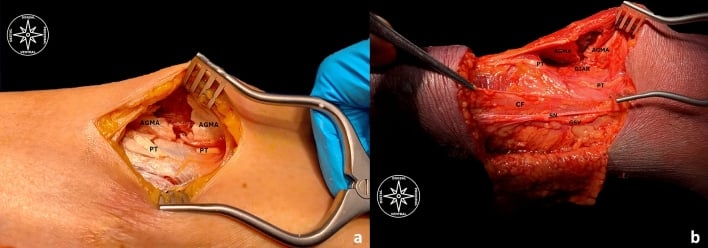
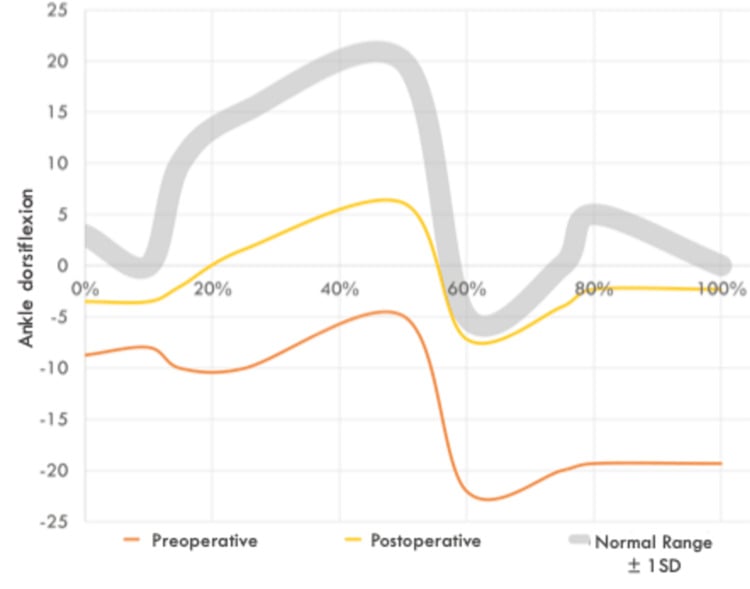
Surgical Relevance
Structures at risk. Each is set against its landmark, with the manoeuvre that protects it.
- Location relative to a landmark
- Between the two heads proximally; pierces the deep fascia at mid-calf; crosses the lateral border of the Achilles 9-12 cm above the insertion
- How to protect it
- Identify before dividing the intermuscular raphe or the aponeurosis; perform recessions open, not blind
- Location relative to a landmark
- On the deep surface of the muscle; closest to bone at the posterior joint line
- How to protect it
- Retract the medial head posterolaterally to shield them; flex the knee for posterior work
- Location relative to a landmark
- Adjacent to the lateral head; crosses the fibular neck 2-4 cm distal to the fibular head tip
- How to protect it
- Identify before any lateral head harvest; a principal reason to prefer the medial head
- Location relative to a landmark
- Enters the deep surface of the medial head within 3-5 cm of its origin
- How to protect it
- Identify and protect before releasing the origin; the flap's entire blood supply
- Location relative to a landmark
- Subcutaneous with the sural nerve, in the groove between the heads distally
- How to protect it
- Preserve with the nerve; ligate side branches rather than avulsing
- Location relative to a landmark
- Enter the deep surface of each head in the proximal third, near the pedicle
- How to protect it
- Preserve for a contractile flap; divide deliberately if a non-contractile flap is preferred
- Location relative to a landmark
- Subcutaneous, along the medial tibial border
- How to protect it
- Place the flap harvest incision 2 cm posterior to the posteromedial tibial border
Approaches involving gastrocnemius, and what each is used for:
- Posteromedial approach to the knee: between the medial head of gastrocnemius, retracted posterolaterally with the neurovascular bundle, and the semimembranosus and posteromedial capsule, retracted anteromedially. Used for posterior horn medial meniscal root repair, posteromedial tibial plateau fixation and Baker cyst excision
- Direct posterior (Trickey or Burks-Schaffer) approach to the knee: between the two heads, with the sural nerve identified in the raphe and the neurovascular bundle exposed. Used for PCL tibial inlay and posterior capsular procedures
- Posteromedial approach to the tibia: gastrocnemius and soleus are retracted posteriorly, and the deep compartment is entered by detaching soleus from the tibia, the same step a fasciotomy depends on
- Achilles surgery: the medial paratenon approach for tendinopathy and repair, with the sural nerve the structure at risk laterally
Guidelines, Registries & Global Practice
Anatomical Variation Across Populations
- The fabella is the most population-variable structure associated with gastrocnemius. Its reported prevalence varies widely between series and is consistently higher in East Asian populations than in European ones, and several studies have suggested its prevalence has increased over the last century, plausibly related to changes in body mass and nutrition. It matters as a radiographic mimic of a loose body and as an occasional cause of posterolateral pain and peroneal nerve irritation.
- Aberrant slips of the medial head underlie most anatomical popliteal artery entrapment. Their prevalence is low but not negligible, and the diagnosis is far more often missed than absent.
- Accessory heads of gastrocnemius and a third head arising from the popliteal surface of the femur are described, and are a rare cause of popliteal vessel and tibial nerve compression.
- The prevalence of isolated gastrocnemius contracture in asymptomatic populations is substantial, which is why the finding must be interpreted alongside symptoms rather than treated in isolation.
Differences in Described Practice
- Position
- Gastrocnemius recession is an established adjunct in flatfoot reconstruction, recalcitrant plantar fasciitis, metatarsalgia and the neuropathic diabetic foot with a positive Silfverskiold test.
- Position
- Emphasises a prolonged and properly conducted non-operative programme before considering gastrocnemius recession for plantar fasciitis or Achilles tendinopathy.
- Position
- Gastrocnemius recession over Achilles lengthening in ambulant spastic diplegia; single-event multilevel surgery planned on instrumented gait analysis; botulinum toxin and casting first in the young child.
- Position
- Medial gastrocnemius flap for the proximal third of the tibia and the knee; soleus for the middle third; free tissue transfer for the distal third.
- Position
- Combined orthoplastic care, early definitive soft tissue cover, and coverage of open tibial fractures within a defined timeframe by a combined orthopaedic and plastic surgical team.
- Position
- Popliteal artery entrapment must be imaged with provocative manoeuvres; early release prevents arterial damage in a young patient.
Practice Signals
- Open tibial fracture standards internationally — the British Orthopaedic Association and British Association of Plastic, Reconstructive and Aesthetic Surgeons standards being the most explicit — emphasise combined orthoplastic decision-making and early definitive soft tissue coverage. The medial gastrocnemius flap is central to delivering that for the proximal third.
- The evidence for gastrocnemius recession in the adult foot is largely level 3 and 4 cohort data, consistently showing pain improvement and improved dorsiflexion with low complication rates, with sural nerve symptoms as the main morbidity. There are no large randomised trials, and this should be stated honestly.
- In cerebral palsy, the strongest and most consistent signal in the literature is the superiority of gastrocnemius-specific lengthening over Achilles lengthening in ambulant children, driven entirely by the risk of iatrogenic crouch. This is one of the few statements in paediatric orthopaedics that can be made without qualification.
- There is no registry for gastrocnemius flaps, recessions or calf muscle injuries.
High- and Limited-Resource Practice
- Well-resourced settings: instrumented gait analysis for surgical planning in cerebral palsy, free tissue transfer for distal third defects, medial sural artery perforator flaps to preserve the muscle, ultrasound and MRI for calf injury, and provocative angiography for popliteal entrapment.
- Limited-resource settings: the medial gastrocnemius flap is one of the highest-value operations in reconstructive orthopaedics — it needs no microsurgery, no implants and no specialised equipment, and it reliably covers exposed bone and metalwork over the knee and proximal tibia. Where free tissue transfer is unavailable, extending the gastrocnemius arc by releasing the origin and scoring the aponeurosis, and combining it with a soleus flap, covers a great deal.
- The Silfverskiold test costs nothing and is the single most valuable clinical tool on this page. Performing it correctly — with the hindfoot locked in neutral — determines whether a patient gets the right operation anywhere in the world.
- Botulinum toxin availability is a genuine limiting factor in paediatric practice in many settings; serial casting and orthoses remain effective, low-cost alternatives for dynamic equinus.
MCQ Practice Points
Q: Where does each head of gastrocnemius arise? A: The medial head from the posterior aspect of the medial femoral condyle just above the adductor tubercle; the lateral head from the lateral aspect of the lateral femoral condyle. The medial head is larger and extends 3-5 cm further distally.
Q: Which nerve runs between the two heads of gastrocnemius? A: The medial sural cutaneous nerve, from the tibial nerve. It pierces the deep fascia at mid-calf and, joined by the sural communicating branch of the common peroneal nerve, becomes the sural nerve.
Q: What Mathes-Nahai type is gastrocnemius? A: Type I — a single dominant vascular pedicle to each head, entering the deep surface within 3-5 cm of the origin. This is why the flap is so reliable.
Q: Which flap for which third of the tibia? A: Proximal third and knee — medial gastrocnemius. Middle third — soleus. Distal third — free tissue transfer.
Q: What defines a positive Silfverskiold test? A: Ankle dorsiflexion improves by more than about 10 degrees when the knee is flexed to 90 degrees, with the hindfoot held in neutral — an isolated gastrocnemius contracture.
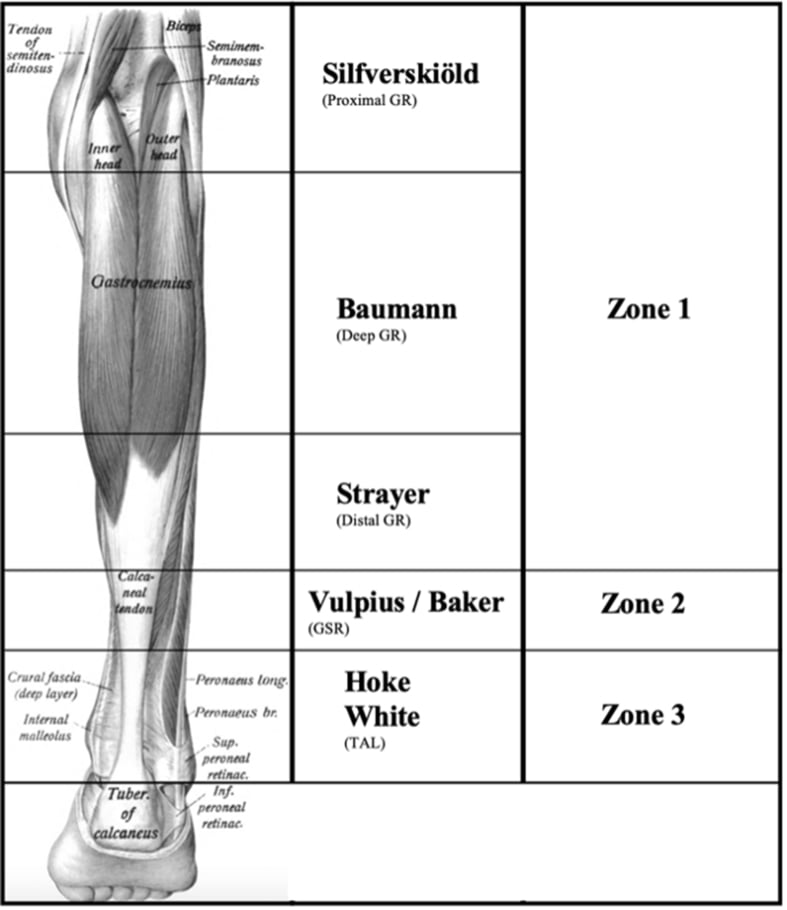
Q: Positive Silfverskiold test — what operation? A: A gastrocnemius recession (Strayer or Baumann), NOT an Achilles lengthening. A negative test means a combined contracture and needs a Vulpius-type or Achilles lengthening.
Q: How do Strayer and Baumann recessions differ? A: Strayer divides the gastrocnemius aponeurosis completely at the gastrocnemius-soleus junction and lets the muscle recess. Baumann makes one or two transverse intramuscular cuts in the aponeurosis on its deep surface, more proximally — a graduated, less powerful lengthening.
Q: Why is Achilles over-lengthening catastrophic in ambulant cerebral palsy? A: It destroys the plantar flexion-knee extension couple, so the ground reaction force falls behind the knee and the child develops an irreversible calcaneus gait and crouch.
Q: What is the commonest anatomical cause of popliteal artery entrapment syndrome? A: An aberrant medial head of gastrocnemius, arising too laterally and displacing the artery medially. Image with provocative manoeuvres, not at rest.
Q: What is the pathology of tennis leg? A: A tear at the medial gastrocnemius musculotendinous junction, with fluid between the medial gastrocnemius and soleus on ultrasound. Not a plantaris rupture. Always exclude an Achilles rupture and a deep vein thrombosis.
Q: Where is the fabella and why does it matter? A: A sesamoid in the tendon of the lateral head of gastrocnemius, present in a variable minority of knees. It mimics a loose body on radiographs and can cause posterolateral pain and peroneal nerve irritation.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 44-year-old man has an open proximal tibial fracture fixed with a plate. Two weeks on there is a 6 by 4 cm area of skin necrosis over the anteromedial proximal tibia with exposed plate and bone. The wound is clean after debridement. How do you achieve cover?”
“A 7-year-old boy with spastic diplegic cerebral palsy walks on his toes. He is a community ambulator, GMFCS level II. Ankle dorsiflexion is minus 10 degrees with the knee extended and plus 15 degrees with the knee flexed. What does that tell you and how would you manage him?”
“A 52-year-old woman has 18 months of plantar heel pain. She has done a supervised stretching and strengthening programme, worn orthoses and had two corticosteroid injections. Dorsiflexion is 0 degrees with the knee extended and 20 degrees with the knee flexed. What now?”
Core Anatomy
- Medial head: posterior medial femoral condyle above the adductor tubercle
- Lateral head: lateral aspect of the lateral femoral condyle; contains the fabella
- Nerve: tibial, S1-S2, separate branch to each head
- Sural nerve runs BETWEEN the two heads, pierces the fascia at mid-calf
Flap Numbers
- Mathes-Nahai type I: one sural artery pedicle per head
- Pedicle enters the deep surface within 3-5 cm of the origin
- Medial head is 3-5 cm longer and avoids the peroneal nerve
- Proximal third and knee = gastrocnemius; middle = soleus; distal = free flap
- Reach extended by releasing the origin and scoring the aponeurosis
Contracture
- Silfverskiold: dorsiflexion improves more than 10 degrees with the knee flexed
- Lock the hindfoot in neutral or you will underestimate it
- Positive test: Strayer or Baumann recession
- Negative test: combined contracture — Vulpius or Achilles lengthening
- Target about 10 degrees dorsiflexion with the knee extended
Clinical Traps
- Never over-lengthen the Achilles in ambulant cerebral palsy — irreversible crouch
- Tennis leg is a medial gastrocnemius tear, not plantaris
- Exclude DVT and Achilles rupture in any acute painful calf
- Aberrant medial head is the commonest cause of popliteal artery entrapment
- Deep posterior compartment needs soleus detached from the tibia at fasciotomy
Evidence Base
The Versatile Gastrocnemius Myocutaneous Flap
- Described the medial and lateral gastrocnemius myocutaneous flaps
- Demonstrated their use as direct flaps without a delay procedure in lower extremity reconstruction
- In the authors' practice the flap supplanted the cross-leg flap for most lower extremity reconstruction
- Case series establishing the gastrocnemius myocutaneous flap in clinical practice
Making the Most of the Gastrocnemius Muscles
- Thirty-four consecutive gastrocnemius muscle flaps performed on a single service were evaluated
- The two heads were described as easily mobilised and very dependable
- The gastrocnemius was the authors' first choice for local muscle transposition in and about the knee
- Seven manoeuvres and associated technical points were presented to maximise the usefulness of the two muscle heads
Recession of the Gastrocnemius: An Operation to Relieve Spastic Contracture of the Calf Muscles
- The original description of gastrocnemius recession as an operation for spastic contracture of the calf muscles
- The procedure lengthens the gastrocnemius selectively rather than lengthening the Achilles tendon
- The operation gives its name to the recession still performed at the gastrocnemius-soleus junction
- No structured abstract is indexed for this 1950 paper; the findings above are those stated in its title and indexing
Isolated Gastrocnemius Tightness
- Prospective case-control study: 34 consecutive patients with metatarsalgia or related midfoot and forefoot symptoms against 34 age, weight and sex-matched asymptomatic controls, measured with a purpose-built electrogoniometer
- Knee EXTENDED, mean maximal dorsiflexion was 4.5 degrees in patients versus 13.1 degrees in controls (p less than 0.001); knee FLEXED to 90 degrees it was 17.9 versus 22.3 degrees (p = 0.09, NOT significant) - the difference vanishes once the gastrocnemius is relaxed, which is the entire logic of the Silfverskiold test
- THE PREVALENCE DEPENDS ENTIRELY ON THE THRESHOLD: at dorsiflexion of 5 degrees or less, contracture was present in 65% of patients and 24% of controls; at 10 degrees or less it was present in 88% of patients but ALSO in 44% of controls
- Combined gastrocnemius-soleus contracture, defined as 10 degrees or less with the knee flexed, was found in 29% of patients and 15% of controls
Gastrocnemius Recession to Treat Isolated Foot Pain
- 29 patients (34 feet) with chronic foot pain and an isolated gastrocnemius contracture, followed for a mean of 19.5 months
- Average pain score improved from 8 out of 10 preoperatively to 2 out of 10 postoperatively
- 27 patients (93.1 per cent) were satisfied and would recommend the procedure
- 23 of 25 patients who had a unilateral procedure would have the contralateral side done if needed
Tennis Leg: Clinical US Study of 141 Patients and Anatomic Investigation of Four Cadavers with MR Imaging and US
- Ultrasound findings in 141 patients referred with a clinical diagnosis of tennis leg, with cadaveric MR and ultrasound correlation
- Rupture of the medial head of gastrocnemius was found in 94 patients (66.7 per cent)
- Fluid between the aponeuroses of the medial gastrocnemius and soleus without muscle rupture was found in 30 patients (21.3 per cent)
- Rupture of the plantaris tendon was found in only 2 patients (1.4 per cent)
- Isolated deep vein thrombosis was identified in 14 patients (9.9 per cent)