The Unique Hamstring
- Only hamstring muscle that does NOT originate from the Ischial Tuberosity.
- Only hamstring muscle that does NOT cross the Hip Joint (Knee flexor ONLY).
- Innervated by the Common Peroneal Division of the Sciatic Nerve (not Tibial).
- Originates from the Linea Aspera and Lateral Supracondylar Ridge.
- Joins with Long Head BF to form common tendon inserting on Fibular Head.
- “The Short Head is the key landmark for identifying the Common Peroneal Nerve.
- “Isolated Short Head weakness suggests High Common Peroneal Nerve lesion.
- “The two heads of Biceps Femoris are embryologically different structures.
- “Sciatic Nerve bifurcation typically occurs at the level of the Short Head origin.
Overview
The short head is the odd member of the hamstring group, and the pages around it treat the others: hamstring injuries for the muscle-belly strains, proximal hamstring avulsion for the ischial-origin injury the short head does not share, and sciatic nerve anatomy for the division that gives it its unique innervation.
What makes it different. The short head is anatomically and embryologically distinct from every other hamstring. The long head, semitendinosus and semimembranosus all originate from the ischial tuberosity and cross both hip and knee; the short head arises from the femur itself and acts only at the knee. That distinction is what makes it useful for localising nerve lesions and for understanding hamstring biomechanics.
Where it lies. The muscle belly sits deep to the long head and is often not appreciated during a superficial dissection. Its primary clinical significance is its intimate relationship with the common peroneal nerve.
- Short Head BF
- Linea Aspera
- Long Head BF
- Ischial Tuberosity
- Semitendinosus
- Ischial Tuberosity
- Short Head BF
- None
- Long Head BF
- Extension
- Semitendinosus
- Extension
- Short Head BF
- Flexion + ER
- Long Head BF
- Flexion + ER
- Semitendinosus
- Flexion + IR
- Short Head BF
- Common Peroneal
- Long Head BF
- Tibial
- Semitendinosus
- Tibial
- Short Head BF
- Fibular Head
- Long Head BF
- Fibular Head
- Semitendinosus
- Pes Anserinus
Detailed Anatomy
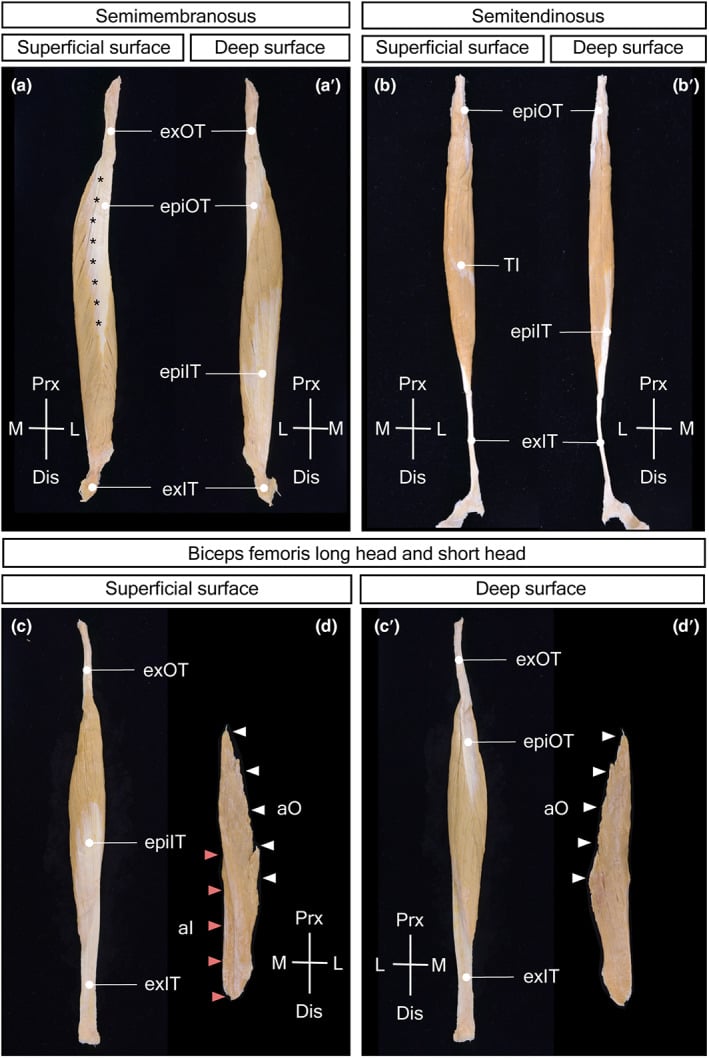
Origin. The short head arises from the lateral lip of the linea aspera in the middle third of the femur and extends proximally along the lateral supracondylar ridge, with a minor contribution from the lateral intermuscular septum. The origin spans approximately the middle third of the femoral shaft, lateral and deep to the long head.
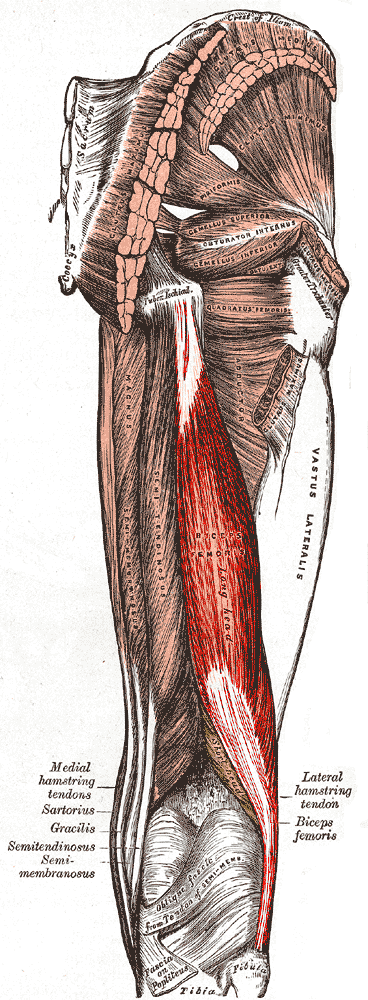
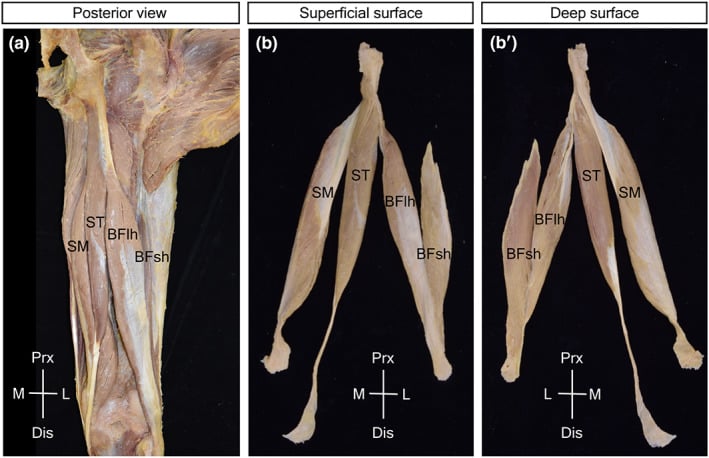
Course. It runs inferolaterally in the posterior compartment of the thigh, deep to the long head for most of its length, and becomes visible laterally in the distal third of the thigh as it joins the long head.
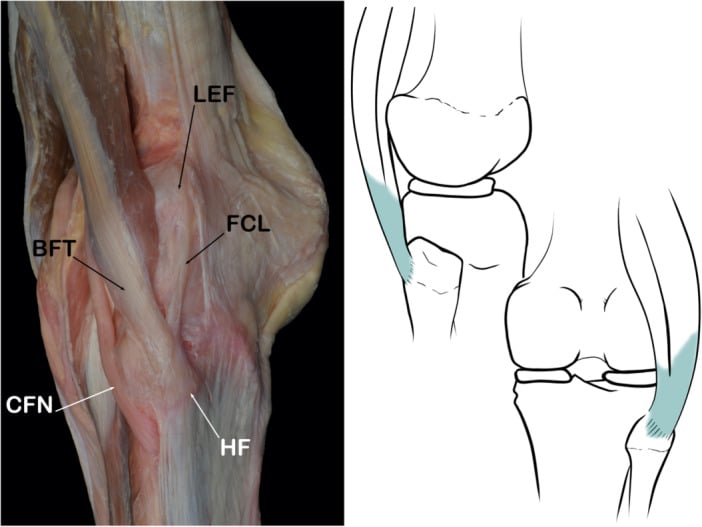
Insertion. The two heads merge into the common bicipital tendon approximately 7-10 cm proximal to the knee. The tendon inserts on the lateral aspect of the fibular head and sends a fascial expansion to the lateral collateral ligament and the crural fascia; it is palpable as the prominent lateral hamstring tendon behind the knee.
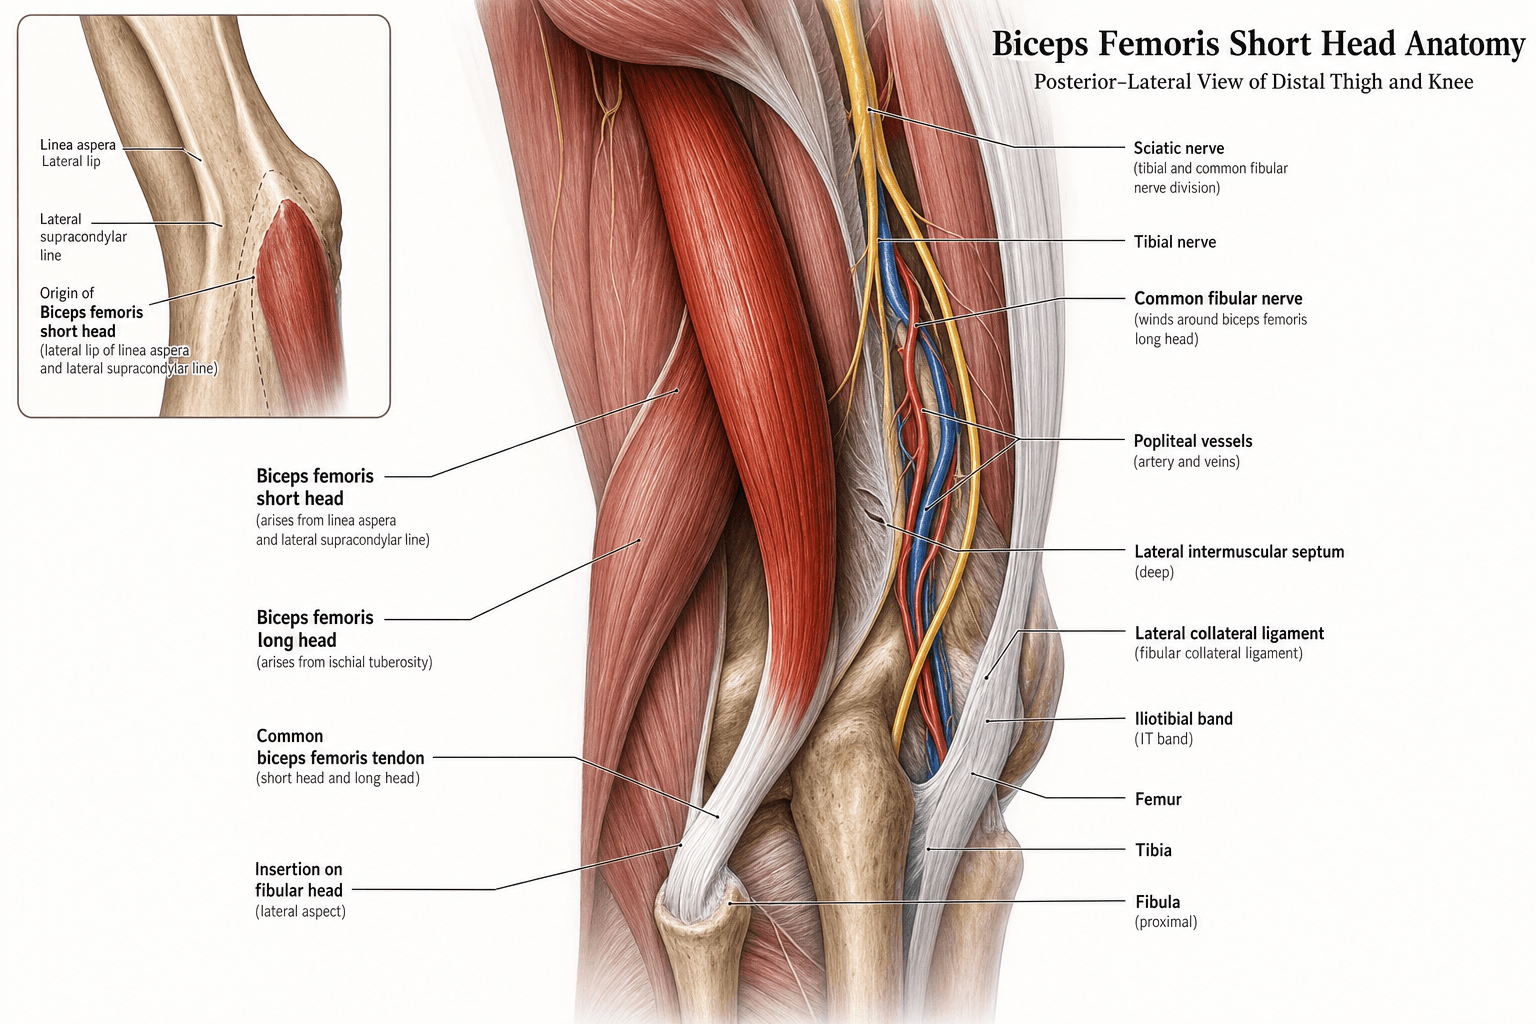
The posterolateral corner. The conjoined tendon has several arms: a direct arm to the fibular head, an anterior arm, and reflected and capsular expansions to the lateral collateral ligament, the posterolateral capsule and the iliotibial tract, with the short head contributing to the deep capsulo-osseous layer. Through them the biceps femoris is a primary dynamic stabiliser of the posterolateral corner: it dynamises the LCL and resists varus and external-rotation (posterolateral) instability, complementing the static stabilisers (LCL, popliteus, popliteofibular ligament). The tendon is also a graft and tenodesis source in PLC reconstruction, and the PLC and the common peroneal nerve are injured together, which is taken up under Pathology.
Relations. The muscle forms part of the lateral border of the popliteal fossa, with the common peroneal nerve tracking along its medial edge:
- Superficial: the long head of biceps femoris covers it
- Deep (anterior): vastus lateralis and the lateral intermuscular septum
- Medial: the sciatic nerve and its common peroneal division
- Lateral: the iliotibial band
- Distal: the common peroneal nerve winds around the fibular neck
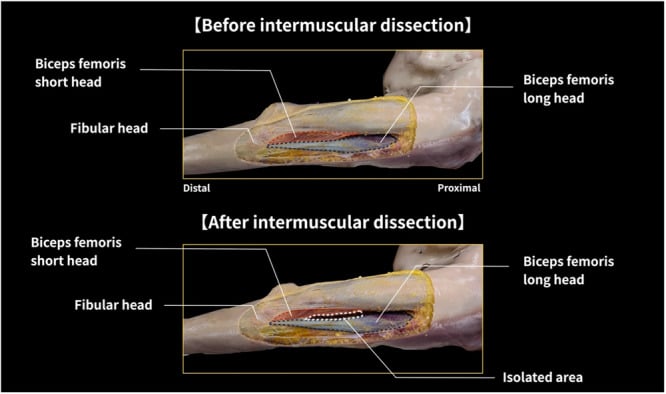
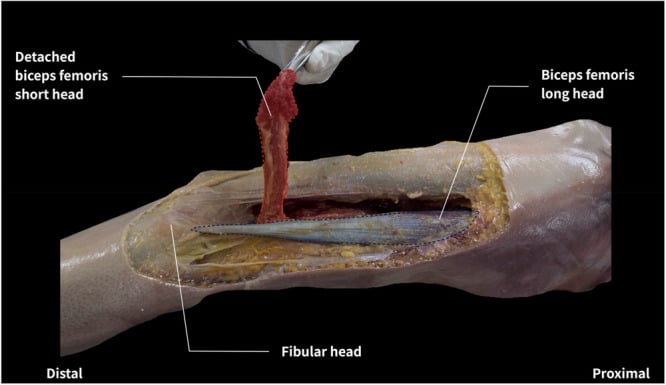
Neurovascular Supply
Nerve. The common peroneal (fibular) division of the sciatic nerve, roots L5, S1, S2, the lateral division of the sciatic nerve. Every other hamstring is supplied by the tibial division, and this is the defining feature of the short head. The nerve enters the deep (medial) surface of the muscle in the mid-thigh, and the common peroneal division then tracks along the medial border of biceps femoris towards the fibular neck.
The bifurcation. Classical teaching places the division of the sciatic nerve into tibial and common peroneal divisions at mid-thigh, at the level of the short head origin. The cadaveric data are less tidy. In Tomaszewski's meta-analysis (J Orthop Res 2016) a single-trunk sciatic nerve exits below piriformis in about 85% of limbs and the division most often occurs distally, a mean of about 65 mm proximal to the popliteal fossa; the nerve deviates from the classic pattern in nearly 15% of limbs, including an intrapelvic split with the common peroneal division piercing piriformis in about 10%. The split can therefore occur anywhere from the pelvis to the popliteal fossa, and the point at which the nerve enters the short head remains a reliable intra-operative landmark for the common peroneal division.
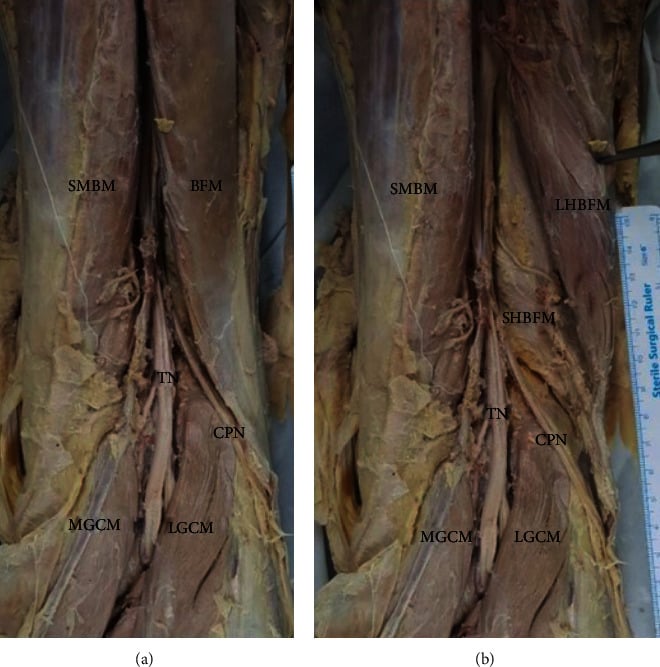
Arteries. Perforating branches of the profunda femoris artery supply the proximal and middle parts of the muscle; the distal part takes branches of the superior lateral genicular and popliteal arteries. The supply is segmental, which theoretically permits the muscle to be used as a rotational flap for knee coverage, though this is rarely performed.
Veins and lymphatics. Venous drainage follows the accompanying perforating and popliteal veins, and lymph drains to the deep inguinal and popliteal nodal chains.
Functional Anatomy
Actions. The short head is a prime mover of knee flexion, with the long head and the other hamstrings, and with the knee flexed it rotates the tibia laterally (externally) on the femur. Biceps femoris is the lateral hamstring, and lateral rotation is the rotation it produces.
No hip action. The muscle does not cross the hip joint, so it has no action on the hip. This is unique among the hamstrings and is why isolated short head weakness does not affect hip extension: it is a knee flexor without the hip extension function of the others.
Gait and posture. It is active during the terminal swing phase of gait, decelerating knee extension. Its postural role is minimal compared with the long head, because it has no hip control.
Pathology
Incidence and mechanism. Short head strains account for less than 10% of hamstring strains and are less common than long head or proximal hamstring injuries. The mechanism is eccentric overload during the terminal swing phase of sprinting, and the tear is usually mid-belly rather than proximal as in the long head.
Clinical features. Lateral posterior thigh pain, with tenderness in the lateral thigh at mid-level, and knee flexion weakness that is subtle because the long head compensates.
Differential. The long head strain, which is more common and proximal; iliotibial band syndrome, which is lateral rather than posterior; and lateral femoral cutaneous nerve compression, which gives numbness without weakness.
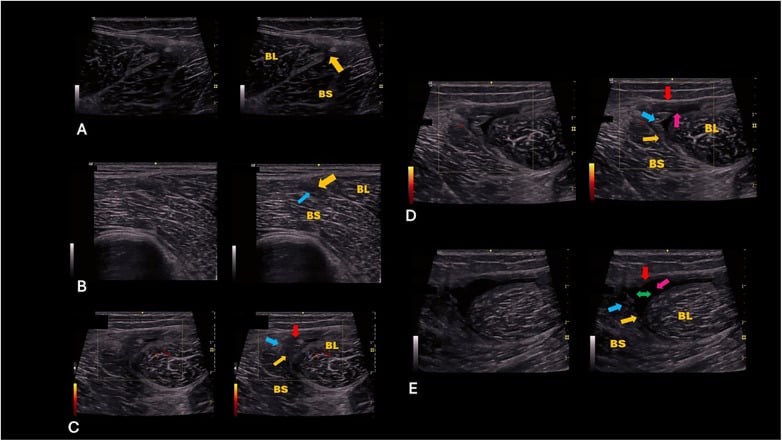
Clinical Significance
Localising a foot drop. The common peroneal division enters the short head in the mid-thigh, so the strength of one muscle places a foot drop above or below that point:
- Weak short head with foot drop: a high common peroneal lesion, proximal to the mid-thigh entry point
- Preserved short head with foot drop: a low lesion, at the fibular neck
- Weak short head and weak long head: a sciatic nerve lesion, or the L5/S1 root
An L5 radiculopathy may show preferential weakness of the short head (L5 predominance), and an injury at the sciatic bifurcation leaves the long head normal with the short head weak. Isolated short head weakness is clinically rare but diagnostically significant.
The branches beyond the neck. Once the nerve passes the short head and winds round the fibular neck it divides into two branches, and knowing the split completes the localisation the short head begins:
- Deep peroneal nerve: motor to tibialis anterior, extensor hallucis longus, extensor digitorum longus and peroneus tertius (ankle and toe dorsiflexion); sensation to the first web space. Its loss is the main cause of the foot drop
- Superficial peroneal nerve: motor to peroneus longus and brevis (foot eversion); sensation to the lateral leg and dorsum of the foot, sparing the first web space
A high lesion weakens the short head and both branches, so dorsiflexion and eversion go together; a fibular-neck lesion spares the short head. A deep-branch-predominant pattern, dorsiflexion weak with eversion relatively spared, is common in early or partial compression and can mimic an L5 radiculopathy; the short head, the hip abductors and EMG distinguish them.
- Short Head Status
- Normal
- Discriminating Feature
- Foot drop, weak eversion, intact knee flexion; Tinel at fibular neck
- Short Head Status
- Weak
- Discriminating Feature
- Foot drop PLUS weak short head; lesion proximal to mid-thigh muscle entry
- Short Head Status
- Variable (L5 input)
- Discriminating Feature
- Weak hip abduction and EHL, back/radicular pain, paraspinal denervation on EMG
- Short Head Status
- Normal
- Discriminating Feature
- Proximal posterior thigh pain, no neurological deficit, no foot drop
- Short Head Status
- Normal
- Discriminating Feature
- Lateral knee pain on flexion-extension, no weakness, no sensory loss
- Short Head Status
- Normal
- Discriminating Feature
- Pain out of proportion, tense compartment; or central/cauda findings
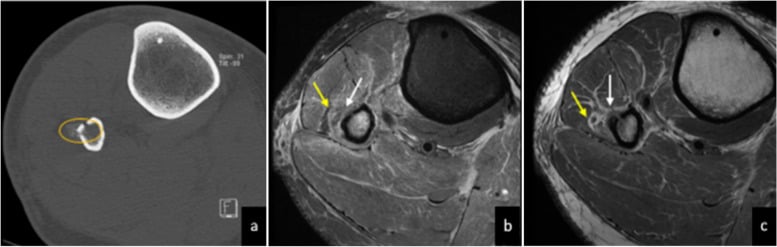
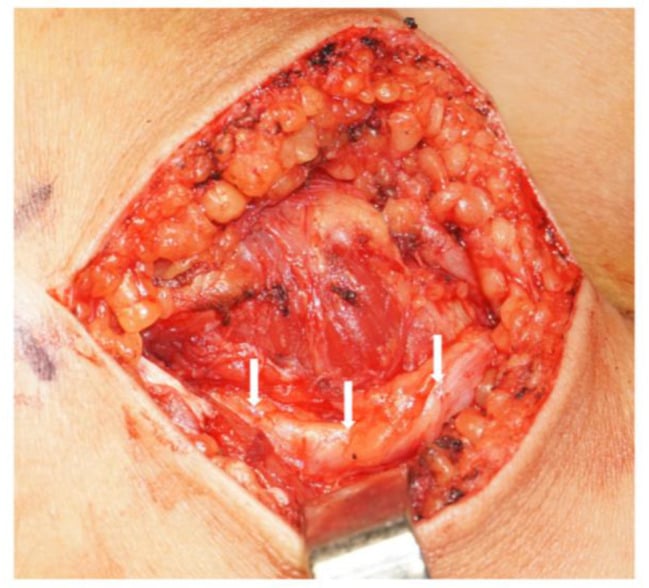
The nerve on the medial border. The common peroneal nerve runs along the medial border of biceps femoris, both heads, and is tethered at the fibular neck and at the sciatic bifurcation. An iliotibial band release or plating of the fibula can injure it, and the result is a foot drop; during fibular plating the nerve is protected deep to the muscle.
The variable bifurcation. A high or anomalous division increases the vulnerability of the common peroneal division during gluteal, posterior thigh and hip approaches. Assuming standard anatomy during hamstring harvest or total hip arthroplasty risks inadvertent division of the nerve when the split is high.
Not a graft. The short head is not harvested for grafts: it is too short, and it carries the wrong nerve.
Investigations
Examination. Inspect the lateral thigh for wasting, the sign of chronic denervation, and palpate for tenderness (a strain) or a mass (a haematoma). Strength is tested by resisted knee flexion with the tibia externally rotated and compared with the other side; the short head cannot be tested in isolation from the long head clinically, so it is graded on the MRC 0-5 scale as part of the hamstring group.
What else to look for. A foot drop, if present, indicates common peroneal involvement. Straight leg raise, extensor hallucis longus strength and ankle dorsiflexion test for an L5 radiculopathy. Clinical examination is usually sufficient for diagnosis.
Management Strategy
Conservative, like the other hamstrings. Short head strains are managed conservatively like other hamstring injuries, and surgery is rarely indicated. Eccentric training with the Nordic hamstring curl is the gold standard for both prevention and rehabilitation, and with conservative management 90% return to sport within 6-12 weeks. The phased programme is set out under Rehabilitation Protocol.
Complications
The complications to anticipate after a strain or a nerve injury:
- Chronic pain: persistent lateral thigh pain after a strain, rare and usually resolving
- Re-injury: higher risk if the return to sport is premature, before 6 weeks
- Nerve injury: common peroneal palsy from surgical trauma, in fibular plating or the reduction of a knee dislocation
- Contracture: Achilles contracture if a foot drop is not managed with an ankle-foot orthosis
Rehabilitation Protocol
- Action
- RICE, analgesia, protected weight bearing
- Timeline
- Immediate
- Action
- Gentle stretching, isometric strengthening
- Timeline
- Week 1-2
- Action
- Progressive eccentric loading, running
- Timeline
- Week 2-6
- Action
- Sport-specific training, gradual return
- Timeline
- Week 6-12
How the phases progress. The acute phase adds gentle range of movement to rest, ice, compression, elevation and pain control; the strengthening phase pairs the eccentric loading with concentric exercise; the final phase adds plyometrics and sport-specific drills before the gradual return. Return to play needs full strength, full range of movement and sport-specific functional tests.
Key exercises
- Nordic hamstring curl: eccentric loading to prevent re-injury
- Single-leg deadlift: functional strengthening
- Sprint mechanics: a gradual return to high-speed running
Guidelines, Registries & Global Practice
Global Epidemiology
- Hamstring strain burden: Hamstring injury is the single most common time-loss injury in football/soccer worldwide, with biceps femoris involved in roughly 80% of strains and accounting for essentially all re-injuries (Ekstrand, Br J Sports Med 2012).
- Short head share: Isolated short head strains are uncommon relative to proximal long-head/myotendinous injuries, but the biceps femoris long-head muscle-tendon junction is the dominant strain site across all sporting populations.
- Common peroneal nerve palsy: Reported in up to 50% of knee dislocations and is a leading driver of poor functional outcome after multiligament knee injury (Cush, Sports Med Arthrosc Rev 2011).
Side-by-Side Guideline & Society Positions
- Domain
- Strain classification
- Recommendation
- MRI grading (Peetrons / British Athletics) stratifies lay-off and return-to-play; intramuscular tendon involvement extends recovery
- Domain
- Prevention
- Recommendation
- Eccentric Nordic hamstring programme endorsed as primary prevention in elite and amateur football
- Domain
- CPN palsy after knee dislocation
- Recommendation
- Early documentation, expectant management if nerve in continuity, AFO to prevent equinus; explore for laceration or no recovery
- Domain
- Foot drop rehab
- Recommendation
- Ankle-foot orthosis and supervised physiotherapy as first-line; tendon transfer for permanent palsy
Practice Variation: High vs Limited Resource
- High-resource settings: Routine MRI grading for prognosis, EMG/nerve conduction studies to localise peroneal lesions, microsurgical nerve grafting and intra-operative nerve monitoring during complex knee or hip reconstruction.
- Limited-resource settings: Diagnosis rests on clinical localisation (short head function distinguishes high from low common peroneal lesions); management centres on a low-cost ankle-foot orthosis and physiotherapy, with tendon transfer reserved for established permanent palsy where microsurgery is unavailable.
Exam Focus
- Short head anatomy and its common peroneal innervation is a classic basic-science viva question in fellowship examinations worldwide. The reliable discriminator examiners seek is the use of short head function to separate a high (proximal) from a low (fibular neck) common peroneal lesion.
Controversies & Areas of Uncertainty
- Bifurcation level is genuinely variable. Older teaching of a fixed "mid-thigh" sciatic split overstates consistency; cadaveric series place most divisions far more distally near the popliteal fossa, while others split high in the pelvis. The short head innervation point is therefore a more reliable surgical landmark than any single quoted bifurcation level.
- Timing of surgery for peroneal palsy after knee dislocation. Early exploration versus expectant management remains debated. Most palsies in nerves in continuity are observed for several months, but late intervention has a poor prognosis, so the optimal window is contested.
- Embryological "dual origin" of biceps femoris. The two heads arise from different myotomal/innervation territories (long head from the tibial-supplied flexor mass, short head from the peroneal-supplied extensor-derived mass), which underpins the split innervation. The precise developmental explanation is still discussed in the anatomical literature.
- Short head as a flap or graft. Although a segmental blood supply theoretically permits rotational use, the short head is essentially never harvested for ACL grafting (inadequate length, wrong nerve) and is rarely used as a flap; its surgical relevance is overwhelmingly as a nerve-localising landmark.
MCQ Practice Points
Q: Which nerve innervates the Short Head of Biceps Femoris? A: Common Peroneal Nerve. (All other hamstrings: Tibial Nerve)
Q: Where does the Short Head of Biceps Femoris originate? A: Linea Aspera (lateral lip) and Lateral Supracondylar Ridge. (NOT Ischial Tuberosity)
Q: Does the Short Head of Biceps Femoris extend the hip? A: No. It only crosses the knee joint, so it only flexes the knee.
Q: A patient has foot drop and weak Short Head of Biceps Femoris. Where is the lesion? A: High Common Peroneal Nerve lesion (proximal to Short Head innervation).
Q: Where does the Short Head of Biceps Femoris insert? A: Fibular Head (via common tendon with Long Head).
Viva Scenarios
Practise clinical reasoning and management decisions out loud
“Which hamstring muscle has a different nerve supply from the others, and what is that nerve?”
“What makes the Short Head of Biceps Femoris unique among the hamstring muscles?”
“A patient has foot drop. Knee flexion strength is normal. Where is the Common Peroneal Nerve lesion?”
Anatomy
- Origin: Linea Aspera
- Insert: Fibular Head
- Nerve: Common Peroneal
- Roots: L5, S1, S2
Function
- Action: Knee Flexion ONLY
- No Hip Extension
- Lateral Rotation of Tibia
- Only 1-joint hamstring
Clinical
- CPN runs medial border
- Weak + foot drop = High CPN
- Normal + foot drop = Low CPN
- Rarely injured vs Long Head
Evidence Base
Surgical Anatomy of the Sciatic Nerve: A Meta-Analysis
- Pooled analysis of 45 studies and 7068 lower limbs - the largest dataset on sciatic anatomy
- Normal Type A pattern (single trunk exiting below piriformis) in 85.2%; the nerve deviates from this course in nearly 15%
- Mean distance of bifurcation into tibial and common fibular divisions was 65.4 mm proximal to the popliteal fossa
- Type B (intrapelvic split, common peroneal piercing piriformis) in 9.8%
Sciatic Nerve Bifurcation Level: A Cadaveric Cohort
- 338 formalin-fixed limbs dissected with a reproducible bifurcation level index
- Bifurcation in the popliteal fossa (Type F) was most common at 79.6%
- No intrapelvic bifurcations (Types B and C) were observed in this cohort
- Provides a quantifiable framework for comparing bifurcation level across populations
Hamstring Injuries in Professional Football: MRI and Return to Play
- Prospective cohort of 516 hamstring injuries across 23 European professional teams
- Biceps femoris was the injured muscle in 83% of cases; every re-injury (16% of all injuries) occurred in biceps femoris
- Higher modified Peetrons MRI grade predicted longer lay-off (8, 17, 22 and 73 days for grades 0 to 3)
- 70% of injuries were grade 0 or 1 with no fibre disruption yet caused most absence days
Nordic Hamstring Exercise Prevents Acute Hamstring Injury (RCT)
- Cluster-randomised controlled trial of 942 male soccer players (50 teams)
- Eccentric Nordic hamstring training cut overall acute hamstring injuries by ~70% (rate ratio 0.29, 95% CI 0.15-0.57)
- Recurrent injuries reduced most dramatically (rate ratio 0.14); number needed to treat to prevent one recurrence was 3
- Number needed to treat to prevent any acute hamstring injury was 13 players
Nordic Hamstring Exercise in Amateur Soccer (RCT)
- Randomised controlled trial of 579 male amateur players from 40 teams
- Nordic hamstring exercise reduced injury risk (odds ratio 0.28, 95% CI 0.11-0.72; P = .005)
- Injury incidence fell from 0.8 to 0.25 per 1000 player-hours
- Programme compliance was 91%, confirming feasibility outside elite settings
Drop Foot After Knee Dislocation: Evaluation and Treatment
- Common peroneal nerve palsy incidence after knee dislocation reported as high as 50%
- Palsy is most associated with open and rotatory dislocations and posterolateral corner injury
- Late surgical nerve treatment carries a poor prognosis; early documentation and follow-up are critical
- Reconstructive options include neurolysis, repair, grafting and posterior tibial tendon transfer