The Vestigial Tendon That Still Causes Trouble
- Plantaris was absent in 13 per cent of 46 cadaveric knees and varied from the standard description in a further 30 per cent — always confirm its presence before planning to use it as a graft.
- It arises from the lateral supracondylar line of the femur just above the lateral head of gastrocnemius, and from the oblique popliteal ligament.
- Its long tendon runs obliquely between soleus and the medial head of gastrocnemius to insert on the calcaneus, usually medial to the Achilles tendon.
- Tennis leg is almost always a tear of the medial gastrocnemius musculotendinous junction, not a plantaris rupture.
- The plantaris tendon is implicated in recalcitrant medial midportion Achilles tendinopathy, where it compresses and abrades the Achilles.
- “The muscle belly is only 2-4 cm long but the tendon is 30-40 cm — the longest tendon in the body relative to its muscle belly.
- “Plantaris is the lower limb equivalent of palmaris longus: variably absent, functionally negligible, and prized as a graft.
- “In tennis leg, ultrasound classically shows fluid between the medial gastrocnemius and soleus; plantaris rupture accounts for only a small minority of cases.
- “The plantaris tendon is safely sacrificed — there is no functional deficit after excision or harvest.
Overview
What it is. Plantaris is a small, vestigial muscle of the superficial posterior compartment of the leg. A muscle belly only 2-4 cm long gives rise to a tendon 30-40 cm long, the greatest tendon-to-muscle length ratio in the body. It is the lower limb's counterpart to the palmaris longus: variably absent, functionally trivial, and valued mainly for what can be done with its tendon.
Why it is still examined. Three clinical facts keep it firmly on the syllabus:
- It is a graft donor. A long, thin, strong free tendon whose harvest requires no functional sacrifice.
- It is the classical wrong answer for tennis leg. For most of the twentieth century, acute midcalf pain with a snap was attributed to "rupture of the plantaris tendon". Imaging studies have shown this to be almost always a tear of the medial gastrocnemius musculotendinous junction.
- It is a genuine cause of recalcitrant medial Achilles pain. In a subset of patients with midportion Achilles tendinopathy the plantaris tendon lies against, or is invaginated into, the medial Achilles and abrades it, and excising the plantaris relieves symptoms in that subgroup.
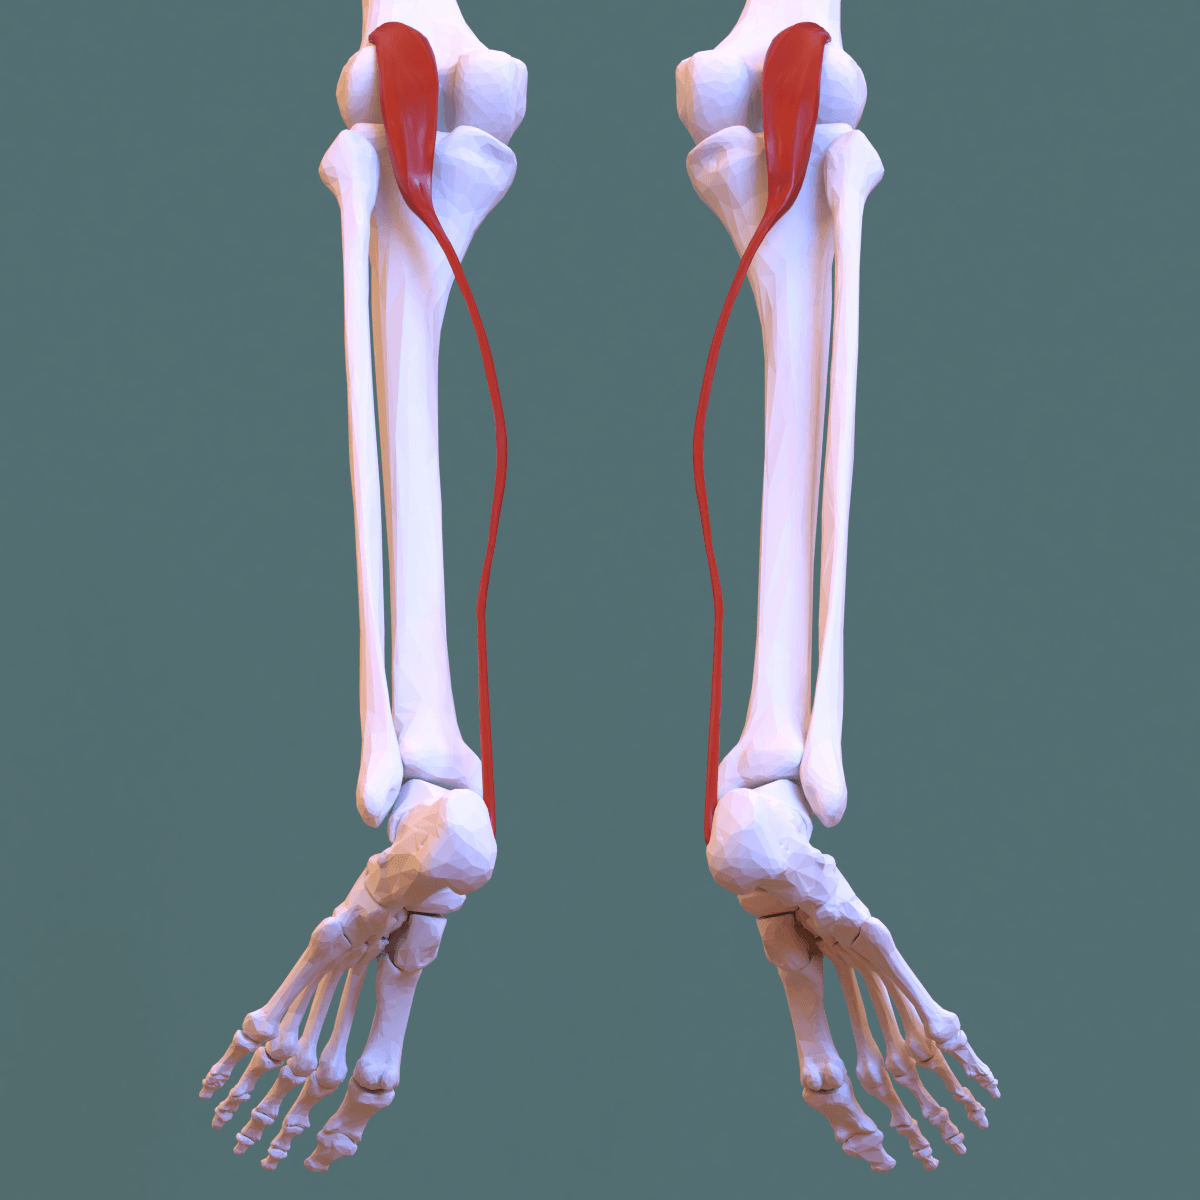
Attachments, Innervation and Relations
Origin. Plantaris arises from the inferior part of the lateral supracondylar line of the femur, immediately proximal and medial to the origin of the lateral head of gastrocnemius. It has an additional origin from the oblique popliteal ligament, the broad superolateral expansion of the semimembranosus tendon across the posterior capsule. The belly is small, thin and fusiform, typically 7-10 cm long overall with only 2-4 cm of true muscle fibres, and it runs obliquely.
Course. The belly runs inferomedially between the lateral head of gastrocnemius behind it and the popliteus and knee capsule in front. The tendon becomes free at about the level of the gastrocnemius musculotendinous junction and then runs obliquely and medially in the plane between soleus (deep) and the medial head of gastrocnemius (superficial). That oblique course, lateral proximally to medial distally, is the defining anatomical feature, and it is why the tendon crosses the very plane in which a tennis leg haematoma collects. In the distal third of the leg it runs along the medial border of the Achilles tendon.
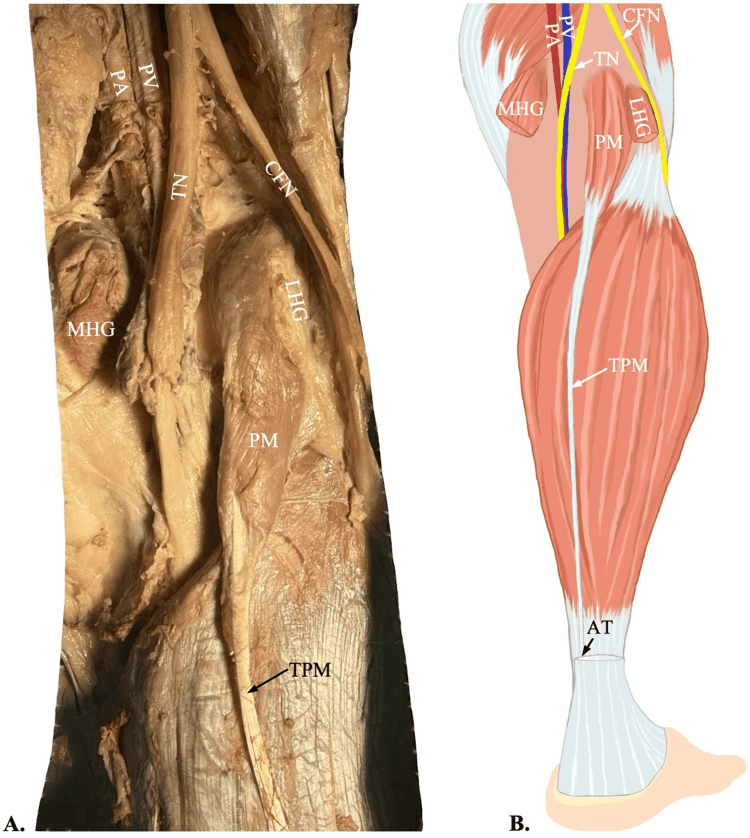
Insertion. Most commonly the tendon inserts on the posterior surface of the calcaneus, medial to the Achilles insertion, either separately or blending with the medial edge of the Achilles. The insertion pattern determines whether plantaris can be harvested as a free tendon and how easily it separates from the Achilles, and the variants change what you find at surgery:
- Blending entirely with the medial Achilles several centimetres above the calcaneus
- Into the flexor retinaculum or the deep crural fascia
- Into the medial calcaneal periosteum, separate from the Achilles
- Rarely, into the plantar aponeurosis, the ancestral insertion that gives the muscle its name
Dimensions for graft planning. The tendon is occasionally longer than 40 cm. It is approximately 3-5 mm wide, flattening distally, and approximately 1-2 mm thick. Its tensile strength is substantial for its size: the collagen density is high, and the strength comfortably exceeds the requirements of most reconstructions for which it is used.
Variants. In Freeman's series of 46 cadaveric knees the muscle varied from the standard description in 30 per cent, including interdigitation with the lateral head of gastrocnemius (about 20 per cent) and a strong fibrous extension to the patella (about 11 per cent), the latter implicated in patellofemoral pain; how often it was absent is discussed in the alert below. Aberrant origins are also described from the posterior capsule, the lateral meniscus, or the medial rather than the lateral supracondylar line.
A hypertrophied or aberrant plantaris has been implicated as a rare cause of popliteal artery entrapment syndrome and of posterior knee impingement, though the far commoner cause of the former is an aberrant medial head of gastrocnemius.
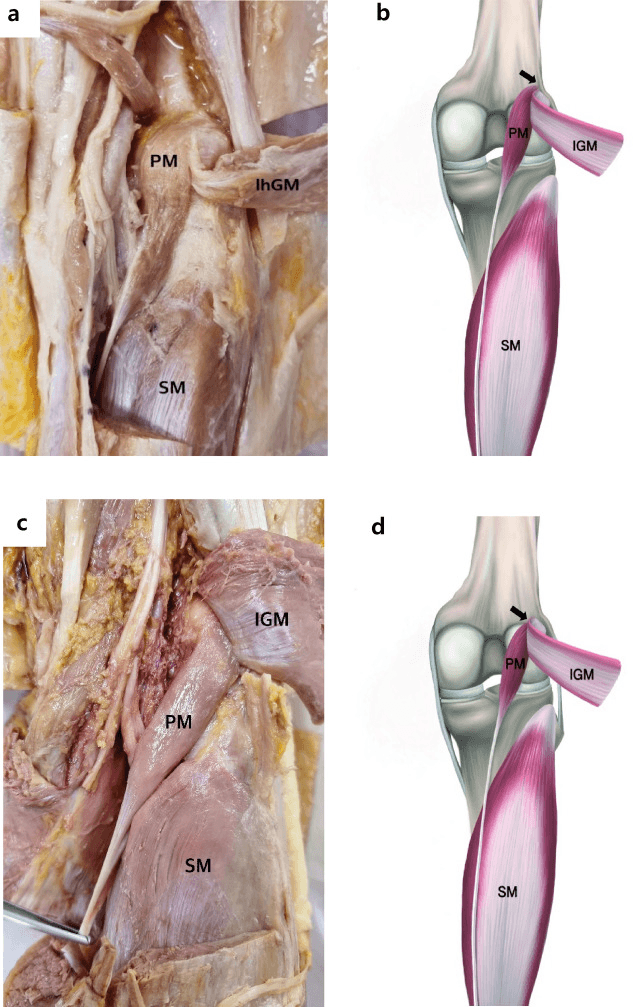
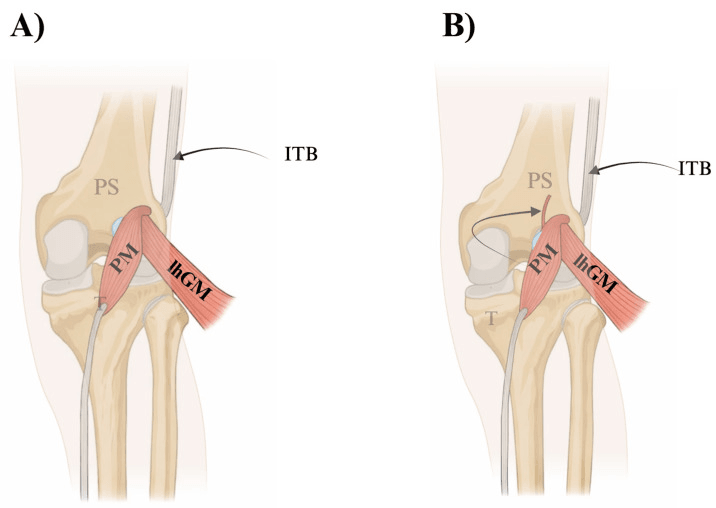
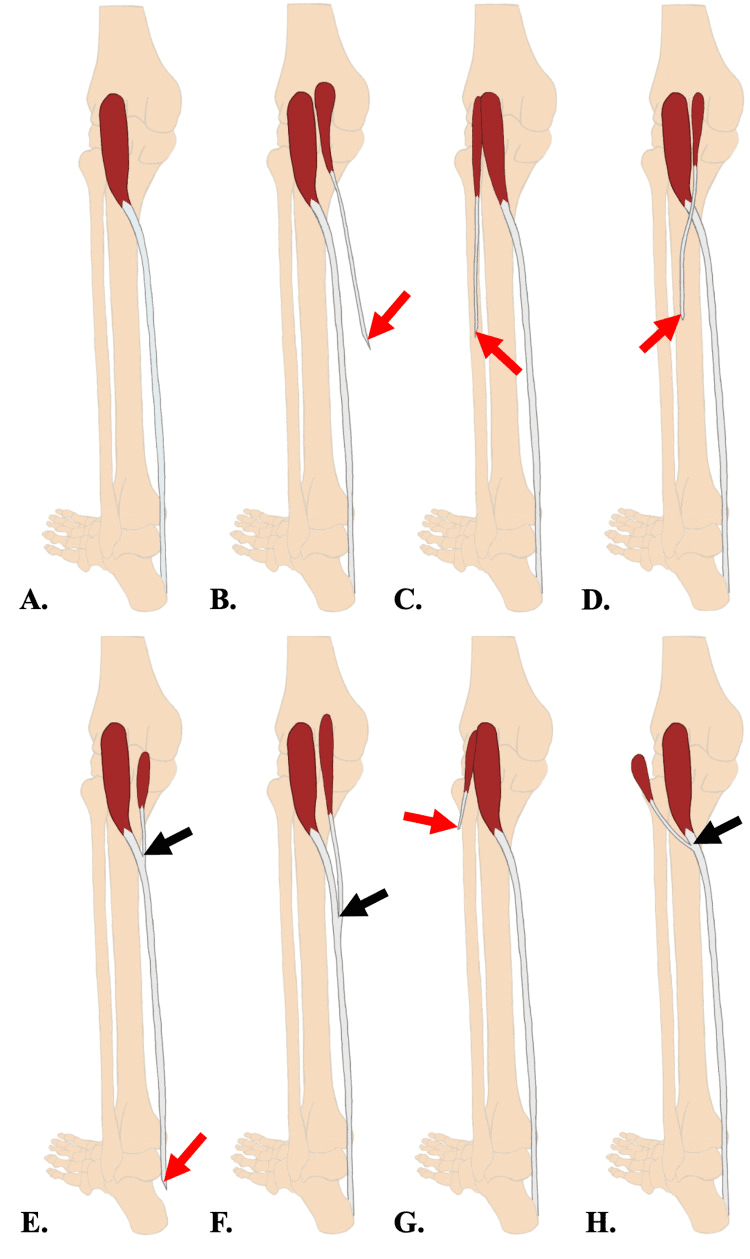
The absence rate depends entirely on what you call "the plantaris" and where you look for it, and the three studies on this page report 13 per cent, 9 per cent and 0 per cent. Freeman dissected the muscle at the knee in 46 cadaveric knees and found it absent in 6 (13 per cent). Simpson found the tendon present in 21 of 23 (91 per cent) at posterior leg surgery. Van Sterkenburg dissected the tendon from behind in 107 limbs and identified one in every specimen.
These are compatible rather than contradictory: a fan-shaped tendinous slip onto the calcaneus can exist where no recognisable muscle belly is found at the knee. For graft planning the number that matters is the surgical one, about one limb in ten will not yield a usable tendon, and the muscle may be absent unilaterally. Do not assume the contralateral side will have one; check both if the reconstruction depends on it.
Confirm its presence before you commit, by pre-operative ultrasound or MRI or by exploring the distal medial Achilles border before making the proximal incision. Always have a plan B, consented and available.
Action and Biomechanics
Actions. Plantaris is a weak plantar flexor of the ankle, contributing an estimated 1-2 per cent of the triceps surae plantar flexion moment, and, because it crosses the knee joint, a weak flexor of the knee. It has no clinically detectable function: excision produces no measurable deficit in plantar flexion power, endurance or hop testing.
Evolution. In most primates plantaris is a substantial muscle that inserts into the plantar aponeurosis and flexes the digits, and the name reflects that ancestral insertion. In humans the plantar aponeurosis insertion has been almost entirely lost as the foot evolved into a rigid propulsive lever, and the muscle has regressed accordingly to a functionally negligible remnant. The rare human variant inserting into the plantar aponeurosis is an atavism and of anatomical interest only.
The proprioceptive hypothesis. Plantaris has a high density of muscle spindles relative to its size, which has led to the suggestion that its principal role in humans is proprioceptive: an organ of muscle-length sensing for the triceps surae complex rather than a force generator. This remains a hypothesis, not an established fact. It is worth stating, labelled as such, if asked why an apparently useless muscle has been retained in evolution, and it does not translate into any clinical caution about excising the tendon: patients who have had plantaris excised for Achilles tendinopathy report no proprioceptive deficit.
Why the length ratio matters. A belly that short on a tendon that long makes the muscle-tendon unit almost entirely elastic. It can store and return energy but can generate almost no active shortening, and that has two consequences:
- For grafting, the tendon is long, of uniform calibre and of high collagen density, precisely the properties required of a free tendon graft
- For tendinopathy, the small contractile element means its excursion during ankle motion differs markedly from that of the Achilles
How it injures the Achilles. Why does an apparently vestigial tendon cause tendinopathy in a structure a hundred times its size? The plantaris tendon usually runs along the medial border of the Achilles for the distal several centimetres before inserting on the calcaneus, and in a substantial minority it is adherent to, invaginated into, or shares a paratenon with the medial Achilles. Because the two muscle-tendon units have different properties and different excursions, the tendons slide against each other during ankle motion; where adhesions tether them, that sliding generates shear stress and local compression on the medial Achilles.
The stiffness mismatch. The plantaris tendon is also stiffer per unit cross-sectional area than the Achilles. A tethered plantaris therefore acts like a bowstring against the medial Achilles fibres.
Surface Anatomy and Examination
Palpation. The plantaris muscle belly is not palpable: it is small and lies deep to the lateral head of gastrocnemius in the popliteal fossa. The tendon is occasionally palpable as a fine cord along the medial border of the Achilles in a thin patient with the ankle dorsiflexed, but this is unreliable, and failing to feel it does not mean the tendon is absent.
There is no test of plantaris function, and that is the correct answer if an examiner asks for one. The relevant examination is of the structures around it: the Achilles tendon, the medial gastrocnemius musculotendinous junction and the calf compartment.
- How to perform
- Prone, feet over the end of the couch; squeeze the calf
- Positive finding
- No passive plantar flexion of the foot
- What it means
- Complete Achilles tendon rupture
- False positives
- An intact plantaris or an intact deep flexor group can produce a small, misleading movement — squeeze properly and compare sides
- How to perform
- Prone, patient actively flexes both knees to 90 degrees
- Positive finding
- The foot on the affected side falls into neutral or dorsiflexion instead of resting plantar flexion
- What it means
- Achilles rupture; complements the Thompson test
- False positives
- Ankle stiffness; a contracture masking the resting position
- How to perform
- Palpate along the Achilles with the ankle passively dorsiflexed
- Positive finding
- A palpable defect 2-6 cm above the insertion
- What it means
- Achilles rupture
- False positives
- Haematoma filling the gap after 48-72 hours can mask it
- How to perform
- Palpate the medial border of the Achilles 2-7 cm above the insertion with the ankle relaxed
- Positive finding
- A discrete medial tender point rather than diffuse fusiform tenderness
- What it means
- Plantaris-associated midportion Achilles tendinopathy
- False positives
- Generalised tendinopathy; a partial tear
- How to perform
- Palpate the medial musculotendinous junction of gastrocnemius, roughly at the junction of the middle and distal thirds of the calf
- Positive finding
- Focal tenderness with or without a palpable defect
- What it means
- Medial gastrocnemius musculotendinous tear
- False positives
- Soleus strain; deep vein thrombosis; ruptured Baker cyst
- How to perform
- Ankle dorsiflexion measured with the knee extended, then flexed to 90 degrees
- Positive finding
- Dorsiflexion improves by more than 10 degrees with the knee flexed
- What it means
- Isolated gastrocnemius contracture — plantaris contributes negligibly
- False positives
- Subtalar motion mistaken for ankle dorsiflexion; measure with the hindfoot in neutral
The Thompson test caveat. A commonly repeated teaching point is that an intact plantaris can produce a small amount of passive plantar flexion in a completely ruptured Achilles, generating a false negative Thompson test. The more important source of a false negative is the intact deep posterior compartment, because tibialis posterior, flexor hallucis longus and flexor digitorum longus can plantar flex the foot. Squeeze the whole calf mass firmly, compare with the other side, combine the Thompson test with the Matles test and palpation for a gap, and do not exclude a rupture on a single test.
Imaging. Ultrasound in the plane between soleus and medial gastrocnemius, or an axial MRI of the mid-calf, reliably demonstrates the tendon, and imaging is how its presence is confirmed. Ultrasound is also the investigation of choice for tennis leg, showing a hypoechoic fluid collection between the medial gastrocnemius and soleus, with or without a visible musculotendinous disruption. Duplex venous ultrasound is mandatory in any acute painful swollen calf before the picture is attributed to a muscle tear or a ruptured cyst.
Complications
After harvest. Sural nerve injury is the main risk, from a distal incision placed too laterally, and produces numbness over the lateral foot and fifth toe and occasionally a painful neuroma. The Achilles itself can be injured by mistaking a medial Achilles fibre bundle for the plantaris and stripping it. The remaining problems are failing to find the tendon because it is absent, a graft cut short by a stripper deviating along an adhesion, and wound complications in a posteromedial distal calf with a genuinely high complication rate.
After excision for tendinopathy. Persistent pain usually means the diagnosis was wrong, and the commonest reason is operating on a patient who has not completed a proper loading programme, or on one with diffuse rather than medial-sided pain. A plantaris that is merely released rather than resected can re-adhere. Wound breakdown over the Achilles and sural nerve injury from a lateral incision apply here too, and Achilles rupture, very rare, is a risk if the medial Achilles fibres are inadvertently divided during the release.
Diagnostic errors. Missing a deep vein thrombosis in an acute painful swollen calf is the error with the most serious consequences, and it is entirely preventable with a duplex scan. An Achilles rupture is missed by relying on a single Thompson test in a patient with an intact deep flexor group. Attributing tennis leg to plantaris rupture means failing to counsel the patient correctly on the healing timeline of a medial gastrocnemius tear, and recalcitrant medial Achilles pain should not be attributed to a plantaris in a patient who has not done the rehabilitation.
- Mechanism
- Distal incision placed laterally, where the nerve crosses the Achilles
- Prevention
- Keep the distal incision on the medial border; blunt subcutaneous dissection
- Mechanism
- Mistaking a medial Achilles bundle for the plantaris
- Prevention
- Confirm by traction producing proximal calf movement; trace to a discrete calcaneal insertion
- Mechanism
- Plantaris absent in about 13 per cent of knees
- Prevention
- Pre-operative ultrasound or MRI; consent for an alternative graft
- Mechanism
- Stripper deviating along an adhesion
- Prevention
- Keep the stripper coaxial and never force it
- Mechanism
- Plantaris released rather than resected
- Prevention
- Resect a segment of several centimetres
- Mechanism
- Attributing an acute swollen calf to a muscle tear
- Prevention
- Duplex ultrasound in every acute painful swollen calf
- Mechanism
- Relying on a single Thompson test with an intact deep flexor group
- Prevention
- Combine Thompson, Matles and palpation; compare with the other side
- Mechanism
- Wrong patient selection
- Prevention
- Require medial-sided pain, imaging evidence, and failure of 12 weeks of proper loading
- Mechanism
- Poor skin handling in a region of precarious perfusion
- Prevention
- Minimal skin handling, no undermining, tension-free closure, optimise smoking and diabetes
Clinical Relevance
The syndrome. Tennis leg describes acute midcalf pain with a sudden snap or the sensation of being struck on the calf. It typically affects a middle-aged recreational athlete pushing off with the knee extended and the ankle dorsiflexed, the lunge in racquet sports.
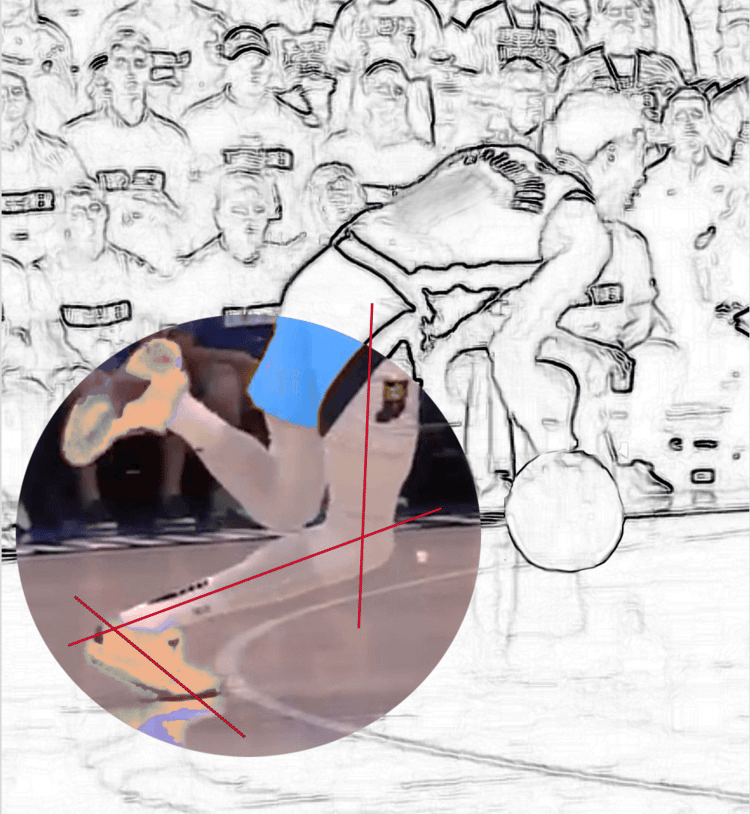
The misattribution. The historical teaching attributed tennis leg to rupture of the plantaris tendon, an inference from anatomy rather than evidence. Ultrasound and MRI studies of large consecutive series overturned it: the great majority of patients have a tear at the medial gastrocnemius musculotendinous junction, with fluid collecting between the medial gastrocnemius and soleus, and plantaris rupture accounts for only a small minority. In Delgado's 141 patients referred with the diagnosis, two thirds had a medial gastrocnemius rupture, a further fifth had fluid between the two muscles without a rupture, and 1.4 per cent had a plantaris rupture.
The examination answer. Tennis leg is a medial gastrocnemius musculotendinous tear. Plantaris rupture exists, but it is uncommon and is not the explanation for the syndrome.
Clinical features. The patient feels sudden sharp pain in the medial calf with an audible or perceived snap, often described as being hit with a ball or a racquet, and has immediate difficulty weight-bearing, with pain on push-off and on passive dorsiflexion. Tenderness is focal at the medial musculotendinous junction. Ecchymosis develops over 24-72 hours and tracks distally to the ankle and foot under the influence of gravity.
Plantar flexion. Power is reduced but present; completely absent plantar flexion or a positive Thompson test means an Achilles rupture, not a tennis leg.
Isolated plantaris rupture. It gives an identical history, a snap and midcalf pain, but a much less impressive clinical picture, with less swelling, less ecchymosis and a faster recovery. Ultrasound or MRI shows a retracted plantaris tendon with the medial gastrocnemius intact. Management is entirely non-operative: it heals or it does not, and either way the patient is unaffected.
- Key discriminator
- Snap with pain at the mid-calf; tender at the medial musculotendinous junction; Thompson negative
- Confirmatory finding
- Fluid between medial gastrocnemius and soleus on ultrasound
- Key discriminator
- Snap at the heel; palpable gap 2-6 cm above the insertion; Thompson positive; Matles positive
- Confirmatory finding
- Tendon discontinuity on ultrasound or MRI
- Key discriminator
- Swelling, warmth, no clear snap; risk factors present
- Confirmatory finding
- Duplex ultrasound — mandatory before excluding it
- Key discriminator
- Prior knee effusion or arthritis; ecchymosis around the malleoli (crescent sign)
- Confirmatory finding
- Ultrasound showing a decompressed cyst and fluid tracking into the calf
- Key discriminator
- More insidious onset, deeper and more diffuse pain, worse with knee-flexed calf raises
- Confirmatory finding
- Soleus signal change on MRI
- Key discriminator
- Identical history to tennis leg but a much less impressive clinical picture
- Confirmatory finding
- Retracted plantaris tendon on ultrasound or MRI — uncommon
- Key discriminator
- Exercise-induced, reproducible, resolves with rest; no acute snap
- Confirmatory finding
- Elevated post-exercise intracompartmental pressures
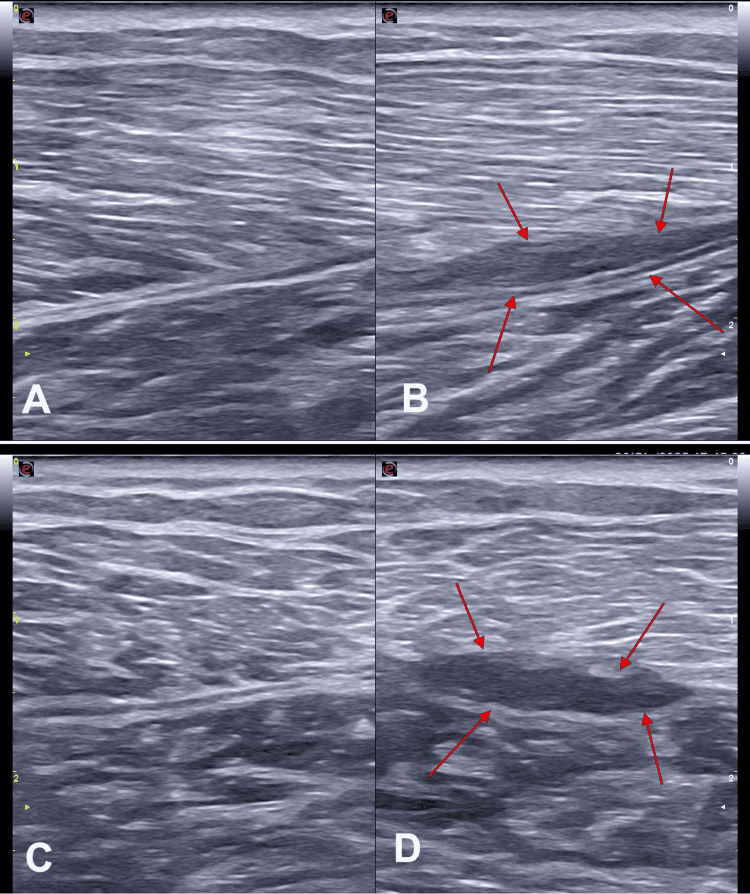
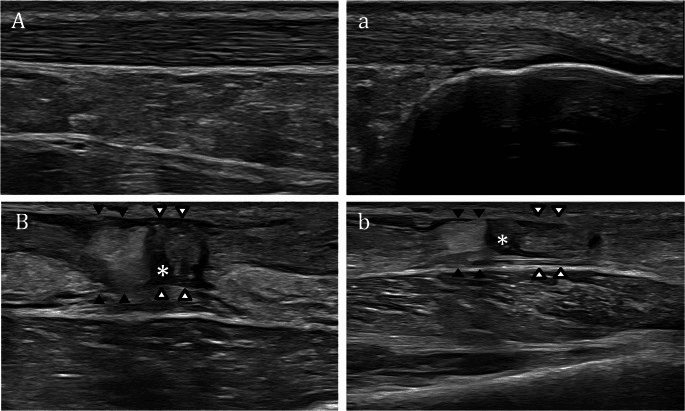
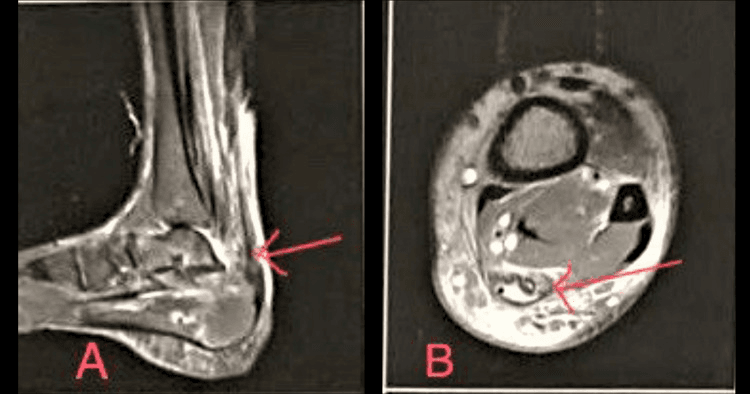
Management. Tennis leg is managed non-operatively in essentially all cases, and the muscle heals reliably.
- Acute phase (0-72 hours): relative rest, ice, compression, elevation and analgesia, with a heel raise to shorten the muscle-tendon unit and ease pain
- Subacute phase: progressive weight-bearing and gentle range of motion, then eccentric and concentric calf loading with the knee both extended and flexed, to load gastrocnemius and soleus separately
- Return to sport typically at 4-8 weeks for a partial tear, longer for a large tear with a substantial haematoma
- Surgery only for the rare large symptomatic haematoma requiring drainage and the very rare complete rupture with a functional deficit
Thrombosis risk. A significant calf haematoma with reduced mobility raises the risk of DVT, and a substantial proportion of tennis leg patients have been shown to develop one. Assess the risk formally, and consider prophylaxis and a duplex scan.
Surgical Relevance
Structures at risk. Each is listed with the landmark that locates it and the manoeuvre that protects it.
- Location relative to a landmark
- Subcutaneous, with the small saphenous vein, crossing the lateral border of the Achilles in the distal third of the leg, approximately 10 cm above the calcaneal insertion
- How to protect it
- Place the distal harvest incision on the MEDIAL border of the Achilles; blunt subcutaneous dissection
- Location relative to a landmark
- Immediately lateral to the plantaris tendon in the distal leg, sharing a paratenon in some limbs
- How to protect it
- Dissect the plantaris free sharply along its medial side without incising the Achilles; confirm identity by proximal traction before dividing
- Location relative to a landmark
- Deep to soleus, in the deep posterior compartment; at risk only if the dissection is taken too deep
- How to protect it
- Do not dissect deep to soleus; the plantaris tendon is superficial to it
- Location relative to a landmark
- Medial and deep to the plantaris belly in the popliteal fossa
- How to protect it
- Do not force a tendon stripper into the popliteal fossa; stop when it reaches the musculotendinous junction
- Location relative to a landmark
- Accompanies the sural nerve posterolaterally
- How to protect it
- Same medial-incision discipline as for the sural nerve
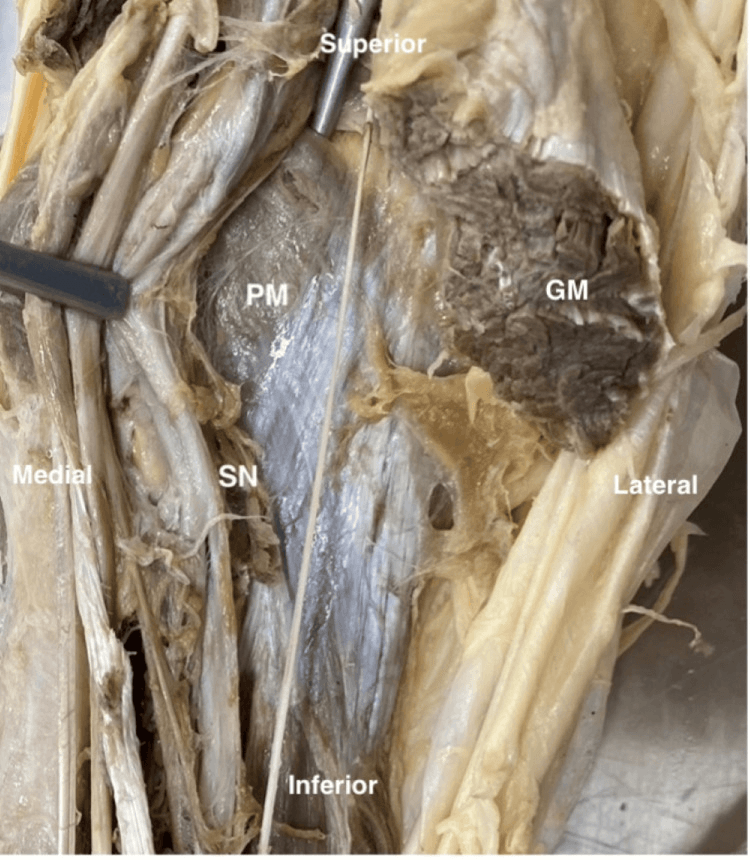
Approaches in which plantaris is encountered. Beyond its own harvest and excision, it is met in these exposures:
- Posterior (Achilles) approach to the ankle - the tendon is found on the medial border of the Achilles and is preserved, used as an augmentation graft, or excised if it is implicated in the tendinopathy
- Achilles tendon repair - some techniques use it as a local augmentation, either as a free graft or as a distally based turn-down strip
- Posteromedial approach to the distal tibia - it lies in the superficial posterior compartment, superficial to soleus
- Posterior approach to the knee - the belly lies between the lateral head of gastrocnemius and popliteus, medial to the common peroneal nerve and lateral to the neurovascular bundle, and is routinely divided without consequence to improve exposure
Fasciotomy. Plantaris lies in the superficial posterior compartment with gastrocnemius and soleus. In a fasciotomy for compartment syndrome that compartment is released longitudinally over the calf through the medial incision, and plantaris is encountered incidentally within it. The deep posterior compartment, containing tibialis posterior, flexor digitorum longus, flexor hallucis longus and the posterior tibial neurovascular bundle, is released through the same incision by detaching soleus from the tibia, a step frequently done inadequately, leaving the deep compartment unreleased.
Plantaris excision for Achilles tendinopathy.
- Confirm the diagnosis, which requires medial-sided midportion pain, imaging showing plantaris applied to or invaginated into the medial Achilles, and failure of at least 12 weeks of properly conducted loading.
- Position prone with the feet over the end of the table.
- Incise longitudinally over the medial border of the Achilles, a short incision centred at the point of maximal tenderness, typically 2-7 cm above the insertion.
- Open the paratenon medially, taking care not to raise a skin flap that will devascularise the wound edge.
- Identify the plantaris tendon medial to the Achilles, often adherent to it or invaginated into its medial fibres.
- Release all adhesions between plantaris and the Achilles along the length of the symptomatic segment.
- Excise a segment of the plantaris tendon. Most surgeons resect several centimetres rather than performing a simple release, to prevent re-adherence.
- Release the medial paratenon and any thickened adherent tissue over the medial Achilles, addressing the neovascular interface.
- Close the skin without tension. The paratenon is not formally repaired over the released area.
- Rehabilitate with early mobilisation, weight-bearing as comfortable, and return to running at approximately 6-12 weeks depending on symptoms.
Wound healing. The posteromedial ankle and distal calf have a precarious skin blood supply and a high wound complication rate after Achilles surgery, and a wound breakdown over an Achilles is a serious complication. Handle the skin as little as possible, avoid undermining, and close without tension. Before elective posterior ankle surgery consider the patient's smoking status, diabetes and vascular disease, the strongest predictors of a wound problem.
Guidelines, Registries & Global Practice
Variation in Reported Prevalence
- Reported prevalence of plantaris absence varies between series. In the best-characterised cadaveric study, 46 knees were dissected and the muscle was absent in 13 per cent, conformed to standard descriptions in 57 per cent and varied from them in 30 per cent. Much of the between-study variation is methodological: series that count a rudimentary or fascial remnant as present report lower absence rates than those requiring a discrete tendon.
- A single universal figure is not defensible, because the studies are small and the definitions inconsistent. The safe examination answer is that plantaris is absent in roughly one in eight limbs, citing the 13 per cent figure from the 46-knee cadaveric series, with the caveat that the definition of absence matters.
- Variant insertions — into the flexor retinaculum, the crural fascia, the medial calcaneal periosteum, and rarely the plantar aponeurosis — are described in all populations.
- The practical corollary is universal: whatever the local prevalence, confirm the tendon before planning a reconstruction around it.
Differences in Described Practice
- Position
- Recognises plantaris involvement as a distinct and treatable subgroup of midportion Achilles tendinopathy; advocates ultrasound and Doppler-guided excision after failed loading.
- Position
- Emphasises a properly conducted loading programme of at least 12 weeks as first-line treatment for midportion Achilles tendinopathy before any intervention.
- Position
- Similar loading-first approach; surgery reserved for recalcitrant cases with a defined structural target.
- Position
- Plantaris is an accepted alternative to palmaris longus for small tendon grafts, with the caveat of variable presence.
- Position
- Tennis leg is classified as a medial gastrocnemius musculotendinous injury; classification and return-to-play are based on imaging extent and free tendon involvement.
Practice Signals
- The most consistent signal across the literature is that midportion Achilles tendinopathy responds to a properly conducted loading programme in the majority of patients, and that surgery of any kind should follow, not precede, at least 12 weeks of that. This applies equally to plantaris excision.
- There is no registry for plantaris surgery or for tennis leg, and the evidence base is imaging series, small surgical series and cadaveric anatomy. The statements that are safe to make in an examination are: tennis leg is a medial gastrocnemius tear; plantaris is absent in a significant minority; plantaris involvement is a recognised and treatable subgroup of medial midportion Achilles tendinopathy; and plantaris is a good, functionally free tendon graft.
- Deep vein thrombosis after calf muscle injury is consistently reported at a rate high enough that a duplex scan and a formal thromboprophylaxis risk assessment should be routine in any patient with an acute calf haematoma and reduced mobility. This is the single most important practice point on this page.
High- and Limited-Resource Practice
- Well-resourced settings: ultrasound with Doppler for both diagnosis and minimally invasive treatment, MRI for graft planning, and duplex scanning on demand.
- Limited-resource settings: the diagnosis of tennis leg is clinical, and the discriminators that matter — a palpable Achilles gap, the Thompson and Matles tests, and the site of tenderness — cost nothing. Ultrasound is the single highest-value investment in this area: it confirms tennis leg, excludes an Achilles rupture, identifies a plantaris before a planned graft harvest, and screens for deep vein thrombosis. Where ultrasound is unavailable, clinical assessment plus a Wells score and D-dimer where available should guide thrombosis management, and a plantaris graft should not be planned as the sole option.
MCQ Practice Points
Q: How often is plantaris absent? A: 13 per cent of 46 knees in a dedicated cadaveric study, which also found the muscle varied from the standard description in a further 30 per cent. Reported rates differ between series with the definition used.
Q: Where does plantaris arise? A: The lateral supracondylar line of the femur, just above and medial to the lateral head of gastrocnemius, and from the oblique popliteal ligament.
Q: In which plane does the plantaris tendon run in the calf? A: Between soleus (deep) and the medial head of gastrocnemius (superficial) — the same plane in which a tennis leg haematoma collects.
Q: What is the pathology of tennis leg? A: A tear at the medial gastrocnemius musculotendinous junction, with fluid between the medial gastrocnemius and soleus on ultrasound. Not plantaris rupture.
Q: What are the dimensions of the plantaris tendon? A: Approximately 30-40 cm long, 3-5 mm wide and 1-2 mm thick, arising from a muscle belly of only 2-4 cm.
Q: What supplies plantaris? A: The tibial nerve, S1-S2, the same supply as gastrocnemius and soleus.
Q: A runner has medial-sided midportion Achilles pain and has failed eccentric loading. What should you look for? A: Plantaris involvement — the tendon applied to or invaginated into the medial Achilles, with neovascularisation on Doppler at the interface.
Q: Which side should the distal harvest incision be on and why? A: Medial. The sural nerve crosses the lateral border of the Achilles with the small saphenous vein and is the structure most easily injured.
Q: What is the upper limb equivalent of plantaris? A: Palmaris longus — variably absent, functionally negligible and prized as a graft. Both are absent in a comparable proportion of people.
Q: Can an intact plantaris cause a false negative Thompson test? A: It is classically taught, but the more important source of a false negative is the intact deep posterior compartment. Squeeze the whole calf, compare sides, and combine with the Matles test and palpation.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 48-year-old recreational tennis player feels a sudden snap in his left calf while lunging for a shot. He thought someone had hit him with a ball. Two days later his calf is swollen and bruised down to the ankle. Walk me through your assessment.”
“A 41-year-old distance runner has 14 months of Achilles pain. She has completed a supervised 12-week eccentric loading programme without benefit. Her pain is sharply localised to the medial side of the Achilles about 4 cm above the heel. The tendon is only mildly thickened. What are you thinking?”
“You are performing a reconstruction of the thumb ulnar collateral ligament and have planned to use a plantaris tendon graft. You make your distal incision and cannot find a plantaris. What now?”
Core Anatomy
- Origin: lateral supracondylar line and oblique popliteal ligament
- Insertion: calcaneus, medial to the Achilles tendon
- Nerve: tibial, S1-S2
- Belly 2-4 cm; tendon 30-40 cm
Key Numbers
- Absent in about 13 per cent of knees (46-knee cadaveric series)
- Tendon 3-5 mm wide, 1-2 mm thick
- Runs between soleus and medial gastrocnemius
- Medial to the Achilles at the watershed zone 2-6 cm above the insertion
Clinical
- Tennis leg = medial gastrocnemius musculotendinous tear, NOT plantaris
- Always exclude DVT and Achilles rupture in an acute painful calf
- Medial midportion Achilles pain that fails loading: think plantaris
- Excision costs nothing functionally
Graft
- Confirm presence by ultrasound or MRI before planning
- Distal incision MEDIAL — the sural nerve crosses laterally
- Confirm identity: traction moves the proximal calf
- Alternatives: palmaris longus, extensor slips, split peroneal, allograft
Evidence Base
Tennis Leg: Clinical US Study of 141 Patients and Anatomic Investigation of Four Cadavers with MR Imaging and US
- Ultrasound findings in 141 patients referred with a clinical diagnosis of tennis leg, with cadaveric MR and ultrasound correlation
- Rupture of the medial head of gastrocnemius was found in 94 patients (66.7 per cent)
- Fluid between the aponeuroses of the medial gastrocnemius and soleus without muscle rupture was found in 30 patients (21.3 per cent)
- Rupture of the plantaris tendon was found in only 2 patients (1.4 per cent)
- Isolated deep vein thrombosis was identified in 14 patients (9.9 per cent)
Midportion Achilles Tendinosis and the Plantaris Tendon
- 73 consecutive tendons with chronic painful midportion Achilles tendinosis treated by ultrasound and Doppler-guided scraping through a medial incision
- An invaginated or closely located enlarged plantaris tendon was found in 58 of 73 tendons (80 per cent)
- Where present, the plantaris tendon was extirpated as part of the procedure
- Preliminary clinical results of combined scraping and plantaris extirpation were reported as promising
Anatomical Variations of the Plantaris Muscle and a Potential Role in Patellofemoral Pain Syndrome
- 46 cadaveric knees dissected to document plantaris anatomy and its variations
- The muscle conformed to standard descriptions in 26 knees (56.5 per cent), varied from them in 14 (30.4 per cent) and was absent in 6 (13.0 per cent)
- Distinct interdigitations with the lateral head of gastrocnemius were present in 9 knees (19.6 per cent)
- A strong fibrous extension of the plantaris to the patella was present in 5 knees (10.9 per cent)
- The interdigitations support the view that plantaris supplements the lateral head of gastrocnemius
The Plantaris Tendon and a Potential Role in Mid-Portion Achilles Tendinopathy: An Observational Anatomical Study
- 107 lower extremities dissected to define the relationship between the plantaris and calcaneal tendons
- A plantaris tendon was identified in every specimen
- Nine different sites of insertion were found, most often medial and fan-shaped onto the calcaneus
- Firm connections to the calcaneal tendon at the level of its mid-portion were present in 11 specimens (10 per cent)
- The authors noted that midportion Achilles pain is most prominent medially, 2 to 7 cm from the calcaneal insertion, where the plantaris tendon lies
The Plantaris Tendon Graft: An Ultrasound Study
- Ultrasound performed on 26 legs in 25 patients undergoing posterior leg surgery, with sonographic findings compared against the status of the plantaris at operation
- The plantaris was present in 21 of 23 patients, a prevalence of 91 per cent
- Ultrasound sensitivity for detecting the tendon was 86 per cent, rising to 95 per cent for a tendon suitable for grafting, with 100 per cent specificity
- Two of the three false-negative results were tendons less than 2 mm thick, considered inadequate for grafting
- A learning curve for the reporting radiologist was demonstrated
Achilles Tendinopathy: Do Plantaris Tendon Removal and Achilles Tendon Scraping Improve Tendon Structure?
- Prospective case series of 9 tendons in 8 active patients with chronic midportion Achilles tendinopathy and suspected plantaris involvement
- Treatment was excision of the plantaris tendon plus scraping of the ventromedial Achilles under local anaesthetic
- Ultrasound tissue characterisation at 6 months showed a significant increase in organised matrix and decrease in disorganised matrix
- VISA-A score improved from 56.8 preoperatively to 93.3 postoperatively
- Seven of eight patients were satisfied