Seronegative Spondyloarthropathy
Overview & Epidemiology
The seronegative spondyloarthropathies are a unifying rheumatology framework the exam loves: one family, one shared biology, and a distinctive orthopaedic hazard in the fracture-prone ankylosed spine. Recognise the pattern (seronegative, HLA-B27, enthesis-centred, new-bone-forming) and you can place any individual subtype.
Who. Onset is typically in the third decade. Axial SpA has a male predominance of about 2:1 for the radiographic form, ankylosing spondylitis, and roughly 1:1 for non-radiographic axial SpA.
Heritability. Ankylosing spondylitis is strongly heritable, at over 90%, and HLA-B27 is the dominant genetic association.
A spectrum. The subtypes are a spectrum rather than separate silos, linked by the gut-joint axis and the IL-23/IL-17 pathway. They are compared under the family section below.
Pathophysiology: enthesitis, HLA-B27 & the IL-23/IL-17 axis
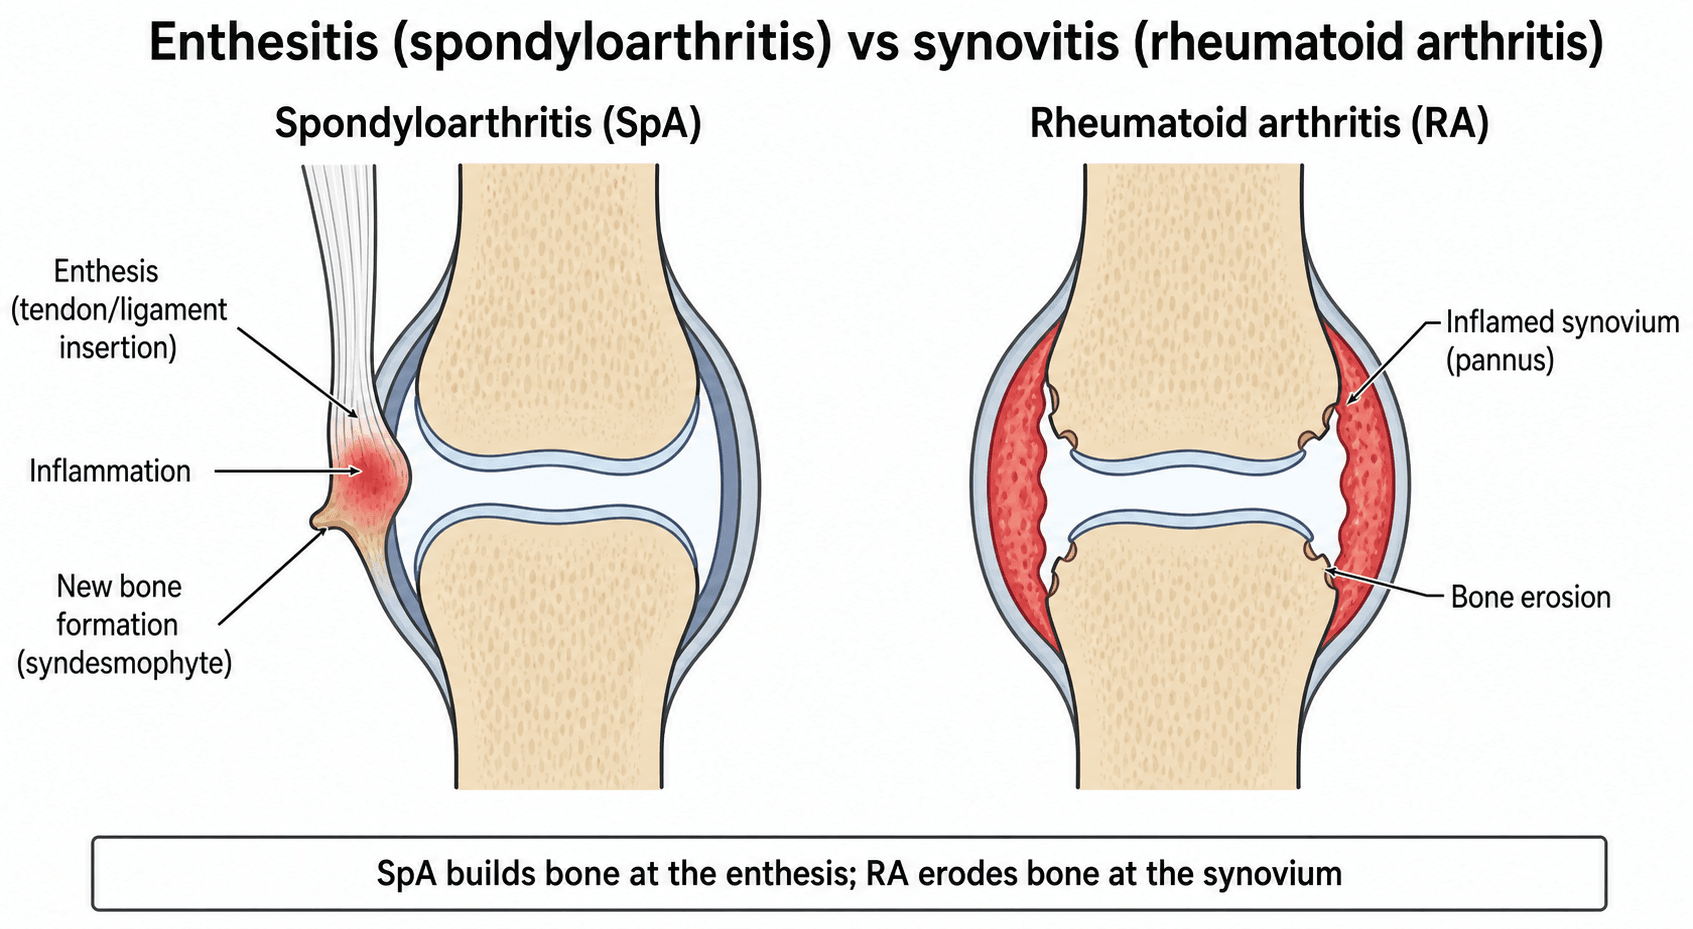
The enthesis is the primary site. Inflammation begins where tendon, ligament or capsule inserts into bone, whereas RA is seropositive, symmetric and small-joint, with the synovium as its primary site. Enthesitis is the defining lesion of SpA, and it explains the dactylitis, the Achilles and plantar heel pain, and the spinal disease.
HLA-B27. It is the dominant genetic association, but its precise pathogenic role (the misfolding, 'arthritogenic peptide' and free heavy-chain hypotheses) remains debated. It is a marker, neither necessary nor sufficient.
The IL-23/IL-17 axis. Together with TNF-α, this pathway drives the inflammation, which is the rationale for anti-TNF and anti-IL-17 therapy. The gut-joint axis links subclinical bowel inflammation to joint disease: joint and gut inflammation are intimately linked, with shared genetics and the same IL-23/IL-17 pathway.
Repair by ossification. The erosive synovitis of RA destroys bone at the joint margin. SpA enthesitis instead heals by new-bone formation, producing syndesmophytes, ankylosis and eventually the bamboo spine, so SpA characteristically builds bone while RA erodes it.
The family & what unites it
What they share. The family is rheumatoid-factor and anti-CCP negative, hence 'seronegative', and carries the HLA-B27 marker. Its members share axial and peripheral arthritis, dactylitis, enthesitis and extra-articular manifestations.
The members. Ankylosing spondylitis, now within the axial spondyloarthritis concept, is the prototype. Around it sit psoriatic arthritis, reactive arthritis, enteropathic (IBD-associated) arthritis and juvenile-onset or undifferentiated SpA.
- Distinguishing features
- Inflammatory back pain, sacroiliitis, ascending ankylosis; strongest HLA-B27 link
- Distinguishing features
- Psoriasis, nail pitting/onycholysis, DIP involvement, dactylitis; axial or peripheral patterns
- Distinguishing features
- 1–4 weeks after GU (Chlamydia) or GI infection; arthritis + urethritis + conjunctivitis
- Distinguishing features
- Arthritis with Crohn's/ulcerative colitis; peripheral often mirrors gut activity, axial does not
- Distinguishing features
- Childhood onset; or SpA features not meeting a single subtype
PAIRThe family
Hook:The seronegative SpA family is a PAIR: Psoriatic, Ankylosing, IBD-associated, Reactive (+ juvenile/undifferentiated).
Where ankylosing spondylitis starts. It characteristically begins at the sacroiliac joints and lower spine and ascends; inflammatory back pain and sacroiliitis with a gradually stiffening axial skeleton are the hallmark. That axial pattern is distinct from the peripheral, symmetrical small-joint pattern of rheumatoid arthritis.
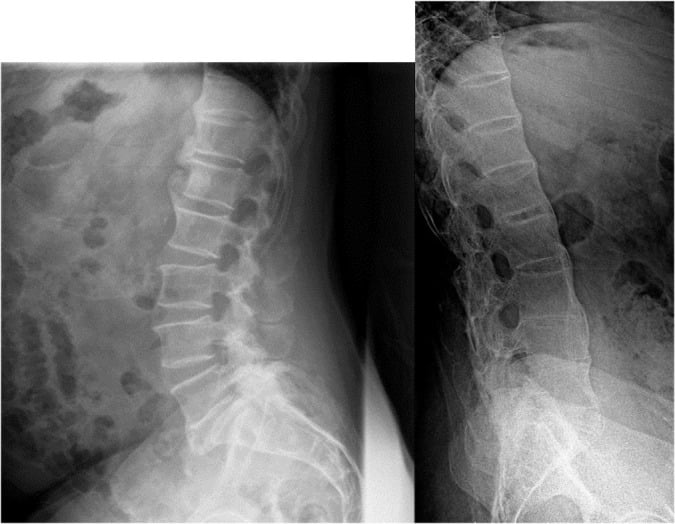
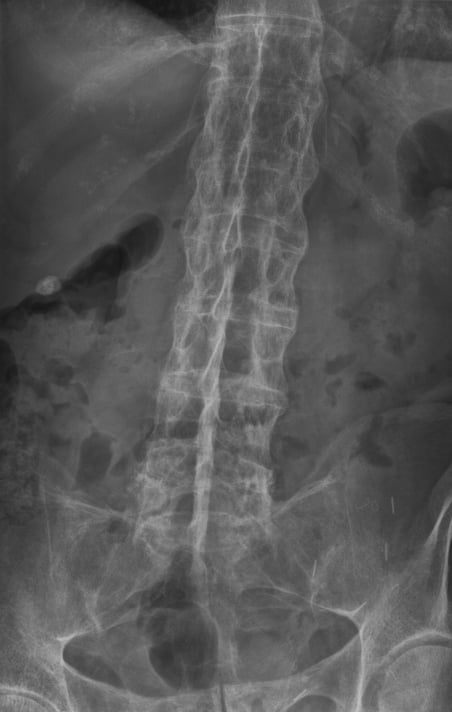
Two ways of building bone. Axial psoriatic arthritis and ankylosing spondylitis both form new bone in the spine, but the pattern differs. Axial psoriatic arthritis makes chunky, non-marginal syndesmophytes; ankylosing spondylitis makes the thin bridges of the bamboo spine, and it is the bamboo column that behaves like a long bone when it is injured.
Investigations
Bloods. RF and anti-CCP are negative. HLA-B27 is positive in most patients, most strongly in AS, but it is neither necessary nor sufficient: a marker, not a diagnostic test. CRP and ESR are raised in active disease.
Radiographs. The plain-film signs are sacroiliitis (erosion, sclerosis, fusion), syndesmophytes, vertebral 'squaring' and, in advanced AS, the fused bamboo spine. Radiographic sacroiliitis is the late hallmark: it diagnoses radiographic axial SpA but does not catch early disease.
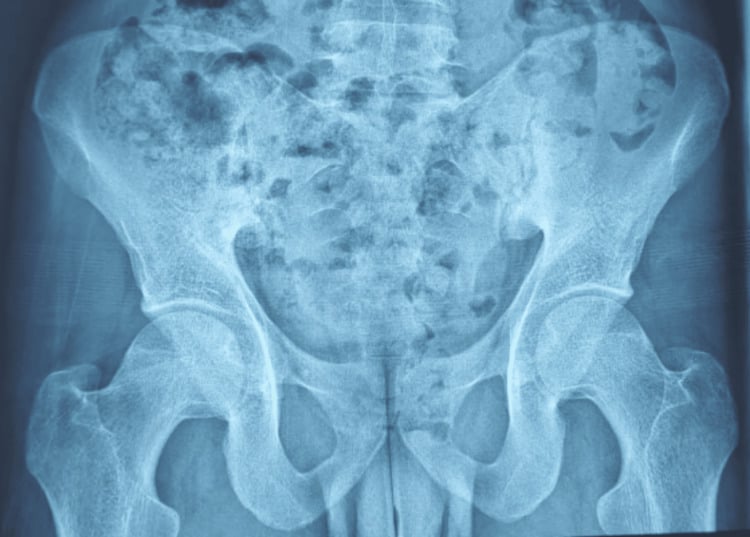
MRI. If the radiograph is still clean and the story is inflammatory, MRI is the next test. It detects early disease as bone-marrow oedema at the sacroiliac joints or spine, defining non-radiographic axial SpA before any radiographic change appears, so there is no need to wait for a bamboo spine. Active sacroiliitis on MRI with inflammatory back pain is enough to start the treatment ladder.
Reading the sacroiliac MRI. On STIR, subchondral marrow oedema shows as bright signal and erosions as cortical breaks. Oedema with erosion is established sacroiliitis rather than a sports strain, and that combination is what ASAS wants on MRI. A single bright patch without an erosion still counts if it is clearly periarticular and the clinical picture matches.
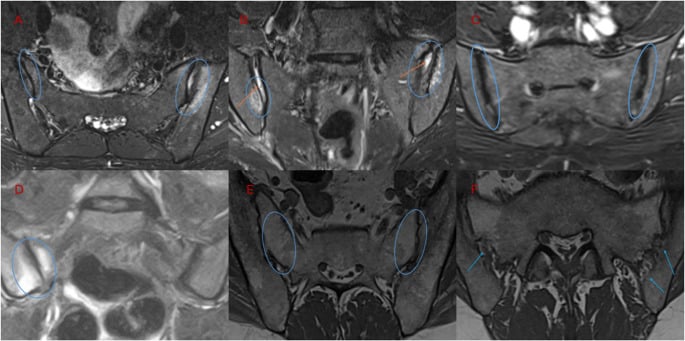
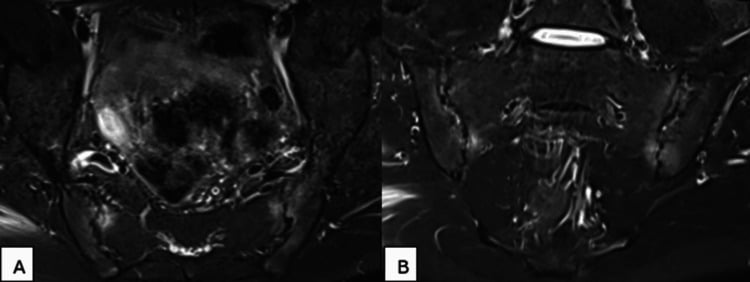
Classification. The ASAS criteria, for axial and for peripheral SpA, integrate clinical features, HLA-B27, CRP and imaging.
DISH, the classic mimic. The other ankylosed spine that fractures dangerously is DISH (diffuse idiopathic skeletal hyperostosis, Forestier disease), a non-inflammatory mimic that examiners set against AS and the comparator in the Tan evidence card. The spinal, sacroiliac and facet features of DISH in the table are its Resnick criteria.
- DISH
- Non-inflammatory
- Ankylosing spondylitis
- Inflammatory
- DISH
- Flowing, bulky, non-marginal ossification ('dripping candle wax') along the anterolateral aspect of at least four contiguous vertebrae, with preserved disc heights
- Ankylosing spondylitis
- Thin, marginal, vertical syndesmophytes; vertebral squaring
- DISH
- No erosive sacroiliitis
- Ankylosing spondylitis
- Erosive, bilateral, symmetrical sacroiliitis (the hallmark)
- DISH
- No fusion
- Ankylosing spondylitis
- Ankylosis
- DISH
- Older (typically over 50), male; type-2 diabetes, metabolic syndrome, obesity
- Ankylosing spondylitis
- Younger (third decade)
- DISH
- Not associated
- Ankylosing spondylitis
- Associated
Telling them apart. Both ankylose and both fracture dangerously as a long bone, so the fracture pattern does not discriminate: sacroiliitis does. Only AS shows sacroiliitis and erosion, and AS patients are more frail, with higher fracture-fixation morbidity (Tan). Do not call dripping candle wax a bamboo spine.
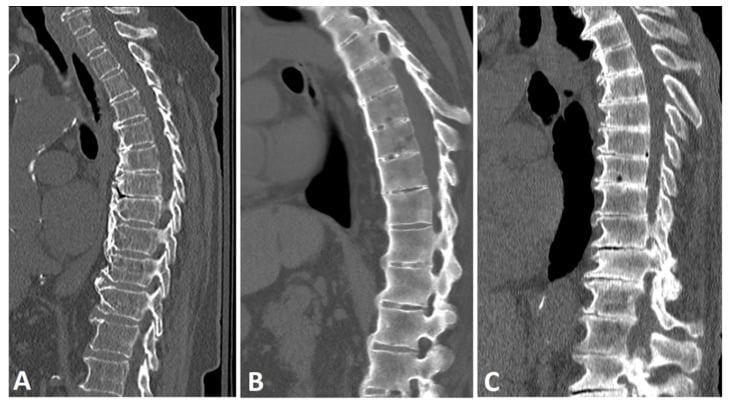
Other sacroiliitis mimics.
- Osteitis condensans ilii: triangular iliac-side sclerosis in parous women, with no erosion
- Osteoarthritis: sclerosis and osteophytes, with no erosion
- Septic sacroiliitis: usually unilateral
Management
Axial disease. First line is NSAIDs with a structured exercise and physiotherapy programme, the cornerstone of axial SpA. Conventional DMARDs (sulfasalazine, methotrexate) are not effective for axial disease.
Peripheral disease. Conventional DMARDs do help peripheral arthritis, alongside NSAIDs.
Escalation. Active or refractory disease, axial or peripheral, escalates to a biologic, anti-TNF or anti-IL-17 (secukinumab), or to a JAK inhibitor.
Tailor to the extra-articular manifestations. An anti-TNF monoclonal suits coexisting IBD or recurrent uveitis, and IL-17 inhibition is avoided in active IBD. NSAID use is controversial when IBD coexists because NSAIDs are associated with flares (Wang and Tsai, in the evidence below).
The whole patient. Care is treat-to-target, built on early diagnosis and on managing comorbidities, osteoporosis and cardiovascular risk among them. It is multidisciplinary: rheumatology with gastroenterology, dermatology and ophthalmology for the EAMs.
Complications
The fractured ankylosed spine. The fused bamboo spine, often osteoporotic too, behaves biomechanically like a long bone. Even low-energy trauma can cause a highly unstable, often extension-type (AO B3) three-column fracture, frequently through the rigid disc and bone segment.
Why it goes wrong. These fractures are easily missed on plain films, the cervical spine especially, and the fracture may lie remote from the painful level. They are prone to displacement and epidural haematoma, and carry a high risk of spinal-cord injury.
Never treat new spinal pain in an ankylosing-spine patient as 'mechanical'. After even trivial trauma it is an unstable fracture until proven otherwise, so keep a low threshold to suspect one. CT (and often MRI) the whole spine, involve spinal surgery early, and immobilise in the patient's habitual posture: never force a fixed-kyphosis patient flat.
Treatment. Treat it as unstable. The fractured ankylosed spine needs urgent work-up and usually long-segment surgical stabilisation, with a low threshold to fix and a high complication rate and morbidity.
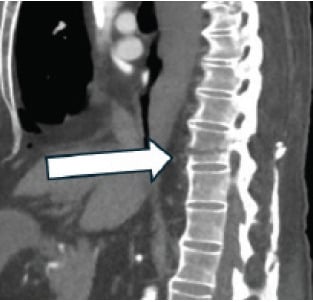
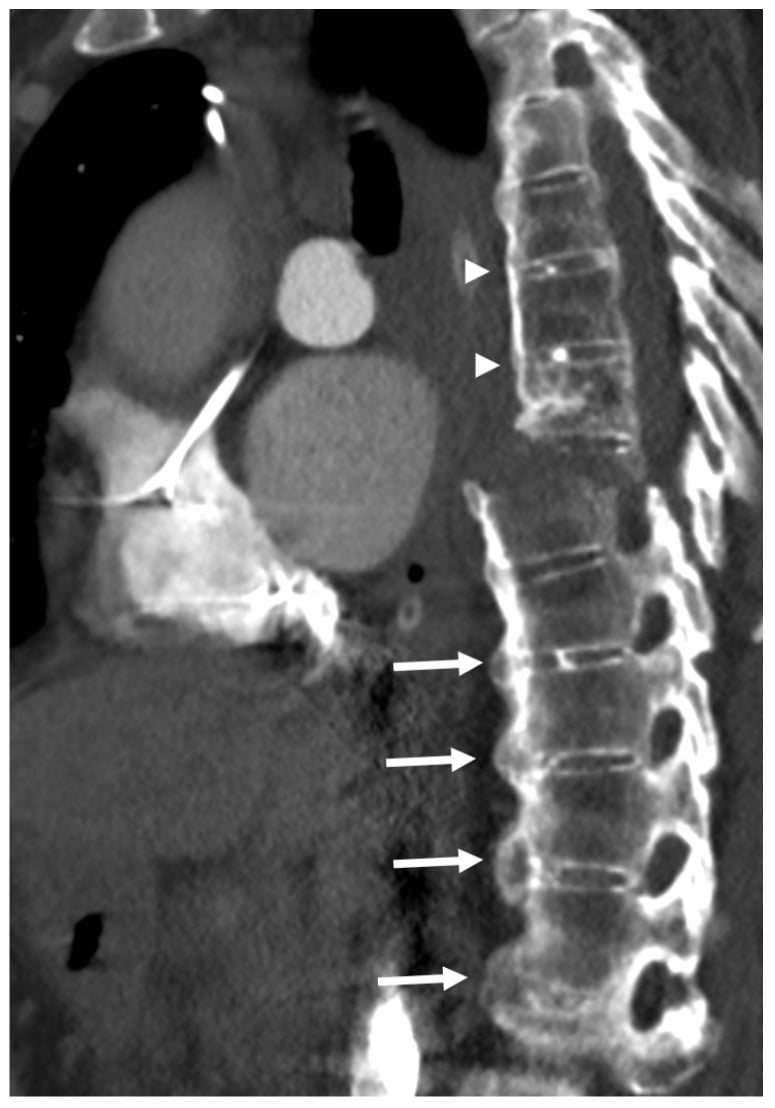
Progressive fixed kyphosis. The deformity progresses and may need corrective osteotomy in selected patients.
Osteoporosis. It compounds the fracture risk; treat it proactively.
Viva practice
Viva practice
Practise clinical reasoning and management decisions out loud
“What unifies the seronegative spondyloarthropathies, what conditions are in the family, and how do they differ from rheumatoid arthritis?”
“An ankylosing spondylitis patient with a fused spine presents with new neck pain after a minor fall. Why does this worry you, and how do you investigate and manage it?”
Exam cheat sheet
The family & what unites it
- RF/anti-CCP negative; HLA-B27 associated
- AS/axial SpA, psoriatic, reactive (Reiter's), enteropathic (IBD), juvenile/undifferentiated
- Shared: inflammatory back pain/sacroiliitis, enthesitis, dactylitis, EAMs (uveitis/psoriasis/IBD)
vs RA
- SpA: seronegative, axial/asymmetric large-joint, enthesis-centred, NEW bone (syndesmophytes/ankylosis)
- RA: seropositive, symmetric small-joint, erosive
- Enthesitis is the defining lesion of SpA
Investigations
- RF/anti-CCP negative; HLA-B27 (not necessary/sufficient); CRP/ESR up
- X-ray: sacroiliitis, syndesmophytes, bamboo spine
- MRI: sacroiliac bone-marrow oedema (non-radiographic axial SpA); ASAS criteria
Management & ortho hazard
- NSAIDs + exercise first-line (axial); DMARDs for peripheral only; biologics (anti-TNF/IL-17, JAK)
- Treat-to-target; manage EAMs and comorbidities (osteoporosis, CV risk)
- Ankylosed (bamboo) spine: unstable extension fractures from minor trauma - CT whole spine, treat as unstable
Evidence Base
Axial spondyloarthritis
- Axial SpA spans non-radiographic and radiographic (ankylosing spondylitis) disease; onset in the third decade, M:F ~2:1 for radiographic and ~1:1 for non-radiographic.
- Over 90% heritability, with HLA-B27 the strongest genetic association (its pathogenic role still debated); TNF-α and IL-17 are central to pathogenesis.
- MRI is the most important imaging method for early diagnosis; NSAIDs and TNF blockers are effective, and IL-17 blockade is a relevant newer option.
Seronegative spondyloarthropathy-associated inflammatory bowel disease
- Seronegative SpA starts in the third decade with negative rheumatoid factor and the HLA-B27 marker, and features spinal and peripheral arthritis, dactylitis, enthesitis and extra-articular manifestations.
- It is classified as ankylosing spondylitis, psoriatic arthritis, reactive arthritis, enteropathic arthritis or juvenile-onset SpA, with joint and gut inflammation intricately linked (shared genetic/immunopathogenic mechanisms).
- NSAIDs are recommended as initial therapy for peripheral and axial SpA, but their use is CONTROVERSIAL in inflammatory bowel disease because they are associated with disease flares - the single most important caveat when the two coexist.
- Conventional DMARDs benefit peripheral arthritis but are ineffective for axial SpA and for IBD; anti-TNF monoclonal antibodies are indicated in both diseases and are the drug of choice for SpA-associated IBD; JAK inhibitors, approved in SpA and in ulcerative colitis, are promising where the two coexist.
- The authors call for joint gastroenterology-rheumatology management, from accurate early diagnosis to prompt therapy.
Clinical management of psoriatic arthritis
- Psoriatic disease is a multi-organ inflammatory disorder (skin and joints) with extra-articular manifestations, comorbidities and a substantial clinical burden.
- Early identification, timely diagnosis and treatment are crucial to prevent long-term structural damage and disability.
- Biologic and targeted synthetic DMARDs have transformed treatment; strategies include treat-to-target, early remission-induction and tapering.
AS-related AO Type B3 thoracolumbar fractures: increased frailty and morbidity vs DISH
- AO Type B3 hyperextension fractures are the commonest fracture subtype in ankylosing spinal disorders; medical/surgical complications occurred in 10 of 14 (71.4%) surgically-managed patients.
- The 14 patients split into just SIX with ankylosing spondylitis and EIGHT with DISH; mean age 72.8 +/- 10.2 years and 78.6 per cent were neurologically intact at presentation.
- Against DISH, the AS group were more likely to have fractured in a low fall (OR 35.0, P=0.026), were more frail (modified frailty index OR 30.6, P=0.015) and averaged more postoperative complications per patient (1.8 versus 0.5, P=0.024).
- Underscores that AS-related spinal fractures are low-energy, high-morbidity injuries requiring careful, individualised surgical management.
The axial-SpA concept, the HLA-B27/IL-23-17 biology and the MRI-led early diagnosis come from Sieper & Poddubnyy 2017 (DOI); the family classification, gut-joint axis and treatment ladder from Wang & Tsai 2023 (DOI); the treat-to-target/biologic strategy from Van den Bosch & Coates 2018 (DOI); and the ankylosed-spine fracture morbidity from Tan et al. 2019 (DOI). The ASAS classification, inflammatory-back-pain features and enthesitis biology are standard, well-established teaching. Each member of the family is covered in detail separately: ankylosing spondylitis, psoriatic arthritis and reactive arthritis; for the seropositive contrast see rheumatoid arthritis, and for the main radiographic mimic of the ankylosed spine see DISH.