Narrow-Thorax & Limb-Shortening Dysplasias
- Jeune syndrome is a short-rib thoracic dysplasia; its thoracic insufficiency can be life-threatening in infancy, and it carries progressive renal (and hepatic) disease
- Severity in 9 DYNC2H1 patients: mild 4, moderate 2, severe or lethal 3; polydactyly in only 4 of 9
- VEPTR in Jeune: 68% survival against a reported 70-80% mortality untreated, but FVC fell from 34% to 27% predicted and complications are frequent
- C1 stenosis and scoliosis are both common in Jeune - examine the cervical spine, not only the thorax
- Ellis-van Creveld: autosomal recessive (EVC/EVC2), postaxial polydactyly, nail and teeth defects, congenital heart disease
- Metatropic dysplasia: TRPV4, coccygeal tail, platyspondyly, dumbbell bones, severe progressive kyphoscoliosis
- Management is multidisciplinary and complication-directed: thorax and kidneys in Jeune, heart in Ellis-van Creveld, spine in metatropic
- “Narrow thorax + short ribs + renal disease = Jeune; postaxial polydactyly + nails/teeth + single atrium = Ellis-van Creveld; coccygeal tail + platyspondyly + dumbbell bones = metatropic
- “Thoracic expansion buys survival and chest width, not lung function: FVC fell from 34% to 27% predicted, migration in 12 of 24, infection 4.6% per procedure
- “Earlier antenatal presentation and femoral shortening/bowing predict a worse outcome in Jeune
Overview
Jeune asphyxiating thoracic dysplasia, Ellis-van Creveld syndrome and metatropic dysplasia are rare skeletal dysplasias that share a small thorax and limb shortening. A handful of hallmarks tells them apart, and each carries its own systemic association.
The two threats. The life- and function-threatening problems converge on the respiratory system. Thoracic insufficiency, the small thorax restricting respiration, is prominent in Jeune and contributory in metatropic dysplasia and Ellis-van Creveld. Progressive spinal deformity, especially the severe kyphoscoliosis of metatropic dysplasia, with a risk of atlantoaxial or cervical instability in some, can compromise the airway and respiration as well.
Diagnosis. The diagnosis rests on the clinical and radiographic phenotype with genetic confirmation. It is completed by looking for the systemic associations: renal and hepatic disease in Jeune, the heart in Ellis-van Creveld, the spine and airway in metatropic dysplasia.
- Hallmarks
- Narrow bell-shaped thorax, short ribs, short limbs (+/- polydactyly)
- Major threat / association
- Thoracic insufficiency (life-threatening infancy); renal/hepatic disease
- Hallmarks
- Postaxial polydactyly, short (acromesomelic) limbs, nail/teeth defects
- Major threat / association
- Congenital heart disease (single atrium/ASD); narrow thorax overlap
- Hallmarks
- Coccygeal 'tail', platyspondyly, dumbbell long bones; changing pattern
- Major threat / association
- Severe progressive kyphoscoliosis; respiratory compromise; cervical instability risk
Jeune Asphyxiating Thoracic Dysplasia
The phenotype. Jeune syndrome, the asphyxiating thoracic dysplasia, is now classified within the short-rib thoracic dysplasias (SRTD), which are often ciliopathies. The thorax is narrow and bell-shaped with short ribs, the long bones are shortened, and there is sometimes polydactyly.
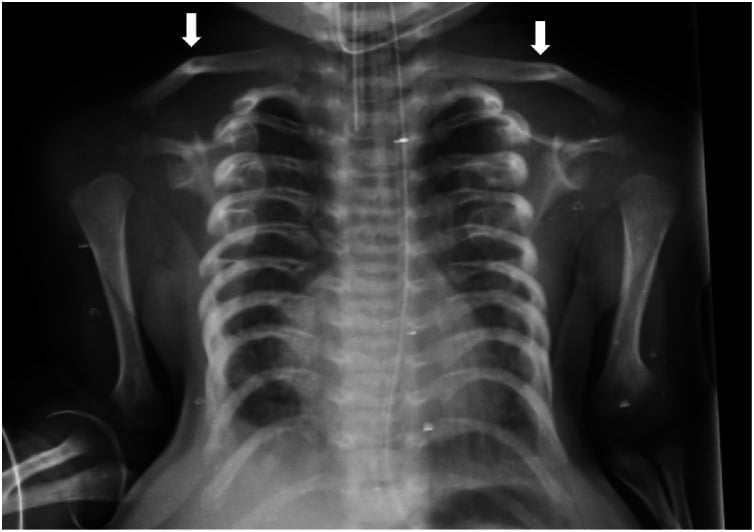
Thoracic insufficiency. The small rib cage restricts lung growth and ventilation. The result is a restrictive lung disease that can be fatal in infancy and may require thoracic-expansion surgery.
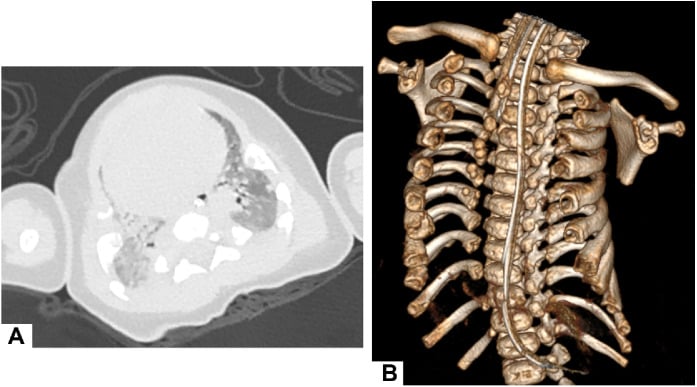
Beyond the skeleton. Progressive renal (and hepatic) disease accompanies the thoracic dysplasia and must be monitored.
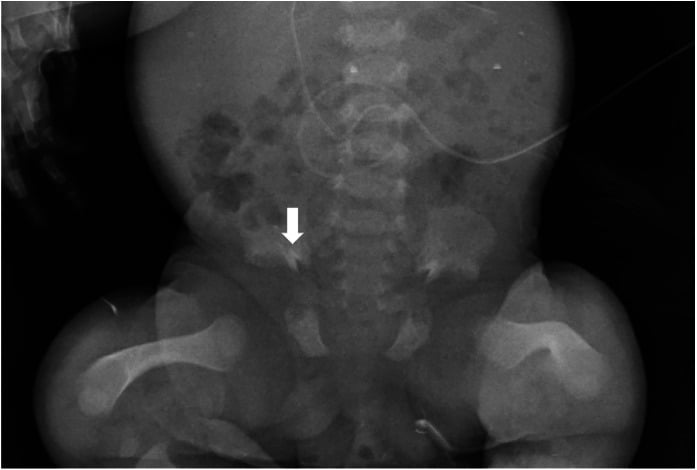
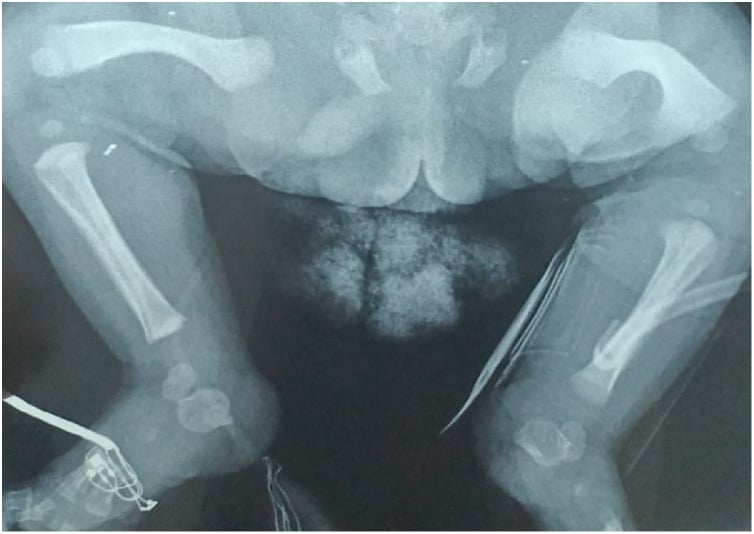
Variable severity. The phenotype is highly variable, from mild to lethal. Earlier antenatal presentation and greater femoral shortening and bowing predict a poorer prognosis.
How few patients sit behind the proportions. Pattani's series is just 9 individuals from 8 families across three English centres, all with DYNC2H1-related disease, so its proportions are indicative only.
- Severity was mild in 4, moderate requiring respiratory support in 2, and severe or lethal in 3: roughly a third severe or lethal, fewer than half mild
- All nine had a narrow thorax and 8 had shortened long bones
- Polydactyly was present in only 4 of 9, a minority feature rather than a defining one
- Eight of the nine presented antenatally, between 14 and 36 weeks
- No clear genotype-phenotype correlation was found, a finding made within DYNC2H1 rather than across the whole SRTD spectrum
Ellis-van Creveld Syndrome
The phenotype. Ellis-van Creveld syndrome, the chondroectodermal dysplasia, is autosomal recessive and combines:
- Postaxial polydactyly, extra ulnar or fibular digits
- Short, acromesomelic limbs
- Ectodermal defects: dysplastic nails and teeth, sparse hair
- Congenital heart disease, classically a single atrium (atrial septal defect)
The heart. The cardiac lesion is the dominant systemic risk and an important cause of morbidity. It must be assessed and treated alongside the polydactyly and ectodermal features.
Overlap with Jeune. A narrow thorax also occurs, placing Ellis-van Creveld alongside the short-rib dysplasias. The pelvis shows the characteristic trident acetabular roof with spurring and dysplastic iliac wings.
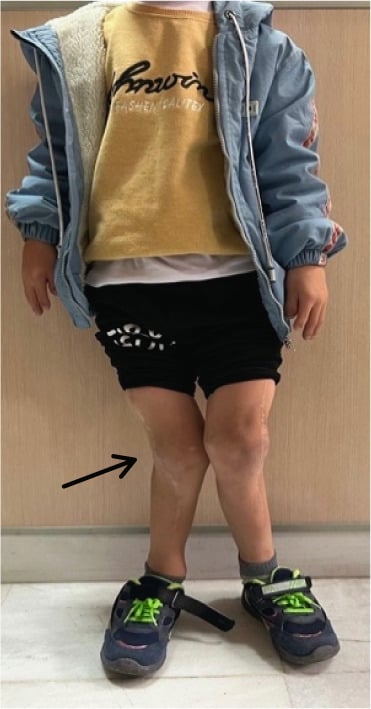
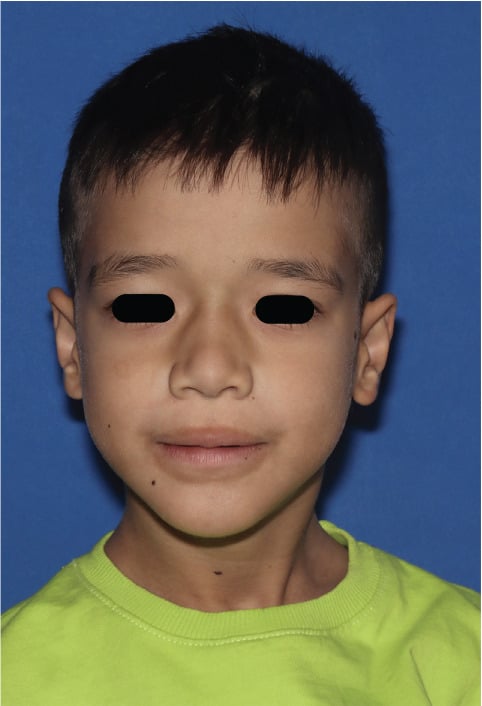
Metatropic Dysplasia
The changing pattern. The name comes from the Greek metatropos, changing. The child is short-limbed in infancy and becomes short-trunked with growth.
The hallmarks. Look for a coccygeal 'tail-like' appendage, platyspondyly (flat vertebrae), and 'dumbbell'-shaped long bones with large joints and contractures.
The spine. The threat is a severe, progressive kyphoscoliosis. Together with the platyspondyly and the small thorax it compromises respiration and the cord, and there is a risk of cervical or atlantoaxial instability.
Molecular Genetics and the Ciliopathy Mechanism
- Jeune (SRTD). Autosomal-recessive ciliopathies of retrograde intraflagellar transport and the dynein-2 motor. The commonest gene is DYNC2H1 (the dynein-2 heavy chain), with IFT80, WDR19, IFT140, TTC21B and others; all disrupt the primary cilium.
- Ellis-van Creveld. Autosomal recessive, EVC or EVC2, adjacent head-to-head genes on 4p16 encoding basal-cilium proteins that regulate Hedgehog signalling. Classically seen in the Old Order Amish, a founder effect.
- Metatropic dysplasia. Autosomal dominant, usually de novo, TRPV4 (a calcium-permeable cation channel). It is allelic with a family of TRPV4 skeletal dysplasias (spondylometaphyseal dysplasia Kozlowski, brachyolmia) and, separately, the TRPV4 neuropathies.
Why 'ciliopathy'. The primary cilium is an antenna-like organelle on growth-plate chondrocytes, built and maintained by intraflagellar transport: anterograde transport (kinesin-2) assembles it and retrograde transport (dynein-2) recycles it. It is the signalling hub for Hedgehog. A defective cilium cannot transduce Hedgehog properly, so chondrocyte proliferation and digit patterning fail, producing short ribs, short limbs and polydactyly. That is why these are skeletal ciliopathies.
The short-rib spectrum. These disorders form a phenotypic continuum, from the lethal neonatal short-rib polydactyly syndromes (historically Saldino-Noonan, Majewski, Verma-Naumoff) through the viable Jeune to Ellis-van Creveld. They are now unified genetically as the short-rib thoracic dysplasias with overlapping IFT and dynein genes, which is why genotype predicts phenotype poorly and the entities overlap.
Management
Care is multidisciplinary and complication-directed, delivered within a skeletal-dysplasia team, with genetic diagnosis and counselling for every family.
- Jeune. Respiratory support and thoracic-expansion surgery (expansion thoracoplasty or VEPTR-type devices) for thoracic insufficiency, with renal and hepatic monitoring.
- Ellis-van Creveld. Cardiac assessment and repair of the single atrium or ASD, polydactyly surgery, and dental and limb care.
- Metatropic. Vigilant spinal surveillance and timely management of the kyphoscoliosis, by bracing, growth-friendly or definitive spinal surgery; watching for cervical instability; and respiratory care.
Jeune has a neck and a spine too. The largest surgical series reports that C1 stenosis and scoliosis are both common in Jeune syndrome, and essentially every child develops scoliosis during treatment whether or not it was present at the outset. The cervical spine therefore needs assessing, rather than attention going only to the chest; neither problem is a metatropic-only concern.
Across this group the orthopaedic and life-limiting issues converge on the respiratory system: the narrow thorax in Jeune, the progressive kyphoscoliosis in metatropic dysplasia. In Ellis-van Creveld the dominant systemic risk is the heart.
The wider context sits on neighbouring pages. The framework for classifying a short child is skeletal dysplasias; the spinal deformity of metatropic dysplasia, and the scoliosis that emerges during thoracic expansion, are managed on the principles of early-onset scoliosis and congenital scoliosis, with cervical narrowing assessed as in cervical instability. The extra digits of Ellis-van Creveld are addressed under polydactyly and, in the foot, polydactyly of the foot.
What Thoracic Expansion Actually Buys, and What It Costs
Recommending expansion thoracoplasty without its numbers understates both the benefit and the burden.
The series. O'Brien and colleagues treated 24 children with Jeune syndrome by VEPTR dynamic posterolateral expansion thoracoplasty, at a mean age at first implant of 23 months and with a mean follow-up of 8.4 years. Survival was 68 percent, set against a reported 70 to 80 percent mortality without treatment. That is a real and substantial gain, and the strongest argument for offering the operation.
- Result
- 68 percent, versus 70 to 80 percent mortality untreated
- Interpretation
- The central justification for operating
- Result
- 121 to 168 mm (p less than 0.001)
- Interpretation
- The thorax does enlarge
- Result
- 35 to 24 breaths per minute (p less than 0.05)
- Interpretation
- Less work of breathing
- Result
- 34 percent predicted falling to 27 percent
- Interpretation
- Measured lung function still declined
- Result
- 41 percent before surgery; the remainder developed it during treatment
- Interpretation
- Expect it, and plan for further implants
- Result
- Cradle or sling migration in 12, deep infection 4, superficial 5, dehiscence 5; infection 4.6 percent per procedure
- Interpretation
- Frequent, and repeated procedures compound the risk
What to promise. The thorax enlarges, CT lung volumes rose and survival improves, but forced vital capacity fell from 34 to 27 percent predicted across follow-up. The operation buys survival and reduced ventilator dependence rather than normal lung function, and complications are frequent: migration in half the patients and an infection rate of 4.6 percent per procedure, across many procedures.
How far the numbers travel. This is a retrospective single-institution series of 24 patients using one device. The figures describe that programme rather than a general standard.
Mnemonics & Memory Aids
THORAX
Hook:THORAX: Thoracic insufficiency (Jeune), Heart disease (EvC), Organs (renal-Jeune), Ribs/polydactyly, Appendage (metatropic tail), eXtreme kyphoscoliosis.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A neonate has a very narrow, bell-shaped chest with short ribs and respiratory distress. What dysplasia is this, what threatens life, and what related syndromes do you consider?”
Jeune (asphyxiating thoracic / SRTD)
- Narrow bell-shaped thorax, short ribs, short limbs (+/- polydactyly)
- Thoracic insufficiency (life-threatening in infancy); in 9 cases: mild 4, moderate 2, severe/lethal 3
- Progressive renal (and hepatic) disease; C1 stenosis and scoliosis also common
Ellis-van Creveld (chondroectodermal)
- Autosomal recessive (EVC/EVC2)
- Postaxial polydactyly + short (acromesomelic) limbs + ectodermal (nails/teeth) defects
- Congenital heart disease (single atrium/ASD)
Metatropic dysplasia
- 'Changing pattern': short-limbed becoming short-trunked
- Coccygeal 'tail', platyspondyly, dumbbell long bones
- Severe progressive kyphoscoliosis; cervical instability risk
Management
- Jeune: respiratory support + thoracic-expansion surgery (68 percent survival vs 70-80 percent mortality untreated; FVC still fell, complications frequent); renal monitoring
- Ellis-van Creveld: cardiac repair; polydactyly/dental/limb care
- Metatropic: spinal deformity management + respiratory care; all MDT + genetics
Evidence & Key Studies
Phenotypic heterogeneity in short-rib thoracic dysplasia (Jeune/Ellis-van Creveld spectrum)
- Retrospective review of 9 individuals from 8 families across three tertiary genetic centres in England, with DYNC2H1-related short-rib thoracic dysplasia. Eight presented antenatally (gestation 14 to 36 weeks) and one postnatally at 6 weeks.
- All nine had a narrow thorax and eight had shortened long bones, but polydactyly was present in only four - a minority feature. Severity was mild in 4, moderate requiring respiratory support in 2, and severe or lethal in 3.
- Earlier antenatal presentation and more significant femoral shortening and bowing predicted a poorer postnatal prognosis, and there were no clear genotype-phenotype correlations - a finding made within DYNC2H1 rather than across the whole SRTD spectrum. Seven novel variants were reported. With nine patients, the severity proportions are indicative rather than precise.
Management of thoracic insufficiency syndrome in patients with Jeune syndrome using the 70 mm radius vertical expandable prosthetic titanium rib
- 24 Jeune patients treated by VEPTR dynamic posterolateral expansion thoracoplasty at one institution; 17 with a minimum 2-year follow-up were reviewed in detail. Mean age at first implant was 23 months (7 to 62) with an average 8.4 years of follow-up (2.3 to 15.6).
- Survival was 68 percent of the 22 followed, against a reported 70 to 80 percent mortality without treatment. Chest width rose from 121 to 168 mm and CT lung volumes increased (both p less than 0.001), and respiratory rate fell from 35 to 24 breaths per minute. However, forced vital capacity fell from 34 percent predicted at first test to 27 percent at last follow-up, and early demise after surgery was common in those with multisystem disease.
- Complications were frequent: cradle or sling migration in 12 patients, superficial infection in 5, deep infection in 4 and wound dehiscence in 5, with an infection rate of 4.6 percent per procedure. Scoliosis was present preoperatively in 7 of 17 (41 percent) and the remainder developed it during treatment, 8 needing additional implants. Both C1 stenosis and scoliosis are noted as common in Jeune syndrome. This is a retrospective single-institution series using one device.
The nature of Jeune syndrome as a short-rib thoracic dysplasia (narrow thorax, short ribs/long bones, +/- polydactyly), its overlap with the Ellis-van Creveld spectrum, its highly variable severity (mild to lethal, with respiratory support needed in moderate cases), and the antenatal prognostic indicators come from the cited Pattani study. The renal/hepatic associations of Jeune, the postaxial polydactyly/ectodermal/cardiac features of Ellis-van Creveld, the metatropic dysplasia hallmarks (coccygeal tail, platyspondyly, dumbbell bones, severe progressive kyphoscoliosis), and the complication-directed management (thoracic expansion, cardiac repair, spinal deformity care) are standard, well-established teaching. The severity proportions, the antenatal predictors, the polydactyly frequency and the absence of genotype-phenotype correlation come from the Pattani series of nine DYNC2H1 patients in England, which is too small to give precise proportions and does not speak to other SRTD genes. The survival, chest-width, lung-function, scoliosis and complication figures come from the O'Brien VEPTR series - retrospective, single-institution, one device - and the 70 to 80 percent untreated mortality it cites is a historical comparison rather than a concurrent control. No trial compares thoracic expansion with supportive care, no threshold defines when to implant, no outcome data exist for Ellis-van Creveld or metatropic dysplasia specifically, and no surveillance interval for the renal or cervical complications has been validated - so none is quoted here.