Bilateral absent radii | Thumbs present | Neonatal thrombocytopenia | RBM8A | Knee disease
- TAR is bilateral absent radii WITH thumbs present plus thrombocytopenia from birth; the present thumb is the examination clue.
- The thrombocytopenia is the early danger: bleeding risk, including intracranial haemorrhage, dominates infancy and must be controlled before any procedure.
- Platelet counts usually rise after the first year or two, so elective limb reconstruction is generally safer once the bleeding tendency has settled.
- Cow's milk intolerance can trigger thrombocytopenic crises, so feeding history is part of the haematology assessment.
- TAR is more than the forearm: lower-limb anomalies, especially knee dysplasia and genu varum, are common and can dominate adult function.
- TAR is autosomal recessive, usually a 1q21.1 microdeletion on one allele plus a low-expression RBM8A variant on the other, which matters for genetic counselling.
- “Thumbs present + absent radii + low platelets = TAR until proven otherwise.
- “Check the platelet count before you touch the patient; never plan surgery around the X-ray alone.
- “Fanconi anaemia and Holt-Oram usually affect the thumb; TAR characteristically spares it.
- “The bleeding settles with age; the knees often do not.
- “Ask about cow's milk: it can precipitate a platelet crisis.
- “TAR is recessive (RBM8A), unlike autosomal dominant Holt-Oram (TBX5).
Overview/Epidemiology
Thrombocytopenia-Absent Radius (TAR) syndrome is a rare congenital malformation syndrome. Its two defining features are bilateral absence of the radii and a low platelet count present from birth.
The thumb. In most conditions that destroy the radius the thumb is also deficient or absent, because the radius and thumb share the same radial (preaxial) developmental column. TAR breaks that rule: the radii are gone but the thumbs remain. A child with bilateral absent radii and two present thumbs has TAR until proven otherwise.
How rare. One case report quotes a frequency of about 0.42 per 100,000 live births, a useful order-of-magnitude figure rather than a precise population rate (DOI). Shaw and Oliver first described the condition in 1959, and Hall and colleagues reported the first major patient series in 1969; most later reports have been single cases or small series (DOI).
Two phases. Infancy is dominated by the blood. The platelet count is typically at its lowest, and bleeding, including intracranial haemorrhage, is the main cause of early death.
Later childhood and adulthood are dominated by the skeleton. The platelet count usually improves, but the limb deformities, particularly of the knees, persist and can become the main determinant of quality of life (DOI).
Why it is examined. TAR forces correct sequencing: the visible deformity invites talk of wrist reconstruction, but the safe answer always starts with the platelet count. It also tests a clean differential, because the thumb tells you whether you are dealing with TAR, Fanconi anaemia, Holt-Oram syndrome or a VACTERL pattern, each of which carries a very different systemic risk.
TARWhat Defines the Syndrome
Hook:TAR spells the diagnosis: low platelets, no radii, but the thumbs stay.
Pathophysiology and Genetics
TAR is a disorder of both the megakaryocyte lineage and limb patterning, and the genetics explains why the two travel together.
Two hits. Affected individuals typically carry a microdeletion of chromosome 1q21.1 on one allele and a low-expression (hypomorphic) noncoding variant of the RBM8A gene on the other. The microdeletion alone is not sufficient to cause TAR, which is why both hits are needed and why the inheritance behaves in a recessive, compound-heterozygous way (DOI).
- Typical lesion
- Microdeletion of chromosome 1q21.1 spanning RBM8A (a null allele).
- Consequence
- Loss of one functional copy; not sufficient alone to cause TAR.
- Typical lesion
- Low-expression noncoding RBM8A variant (commonly in the 5'UTR or intron 1).
- Consequence
- Reduces expression of the remaining copy below a critical threshold.
- Typical lesion
- Both hits together lower functional Y14 protein.
- Consequence
- Megakaryocyte and radial-limb development are impaired, producing the TAR phenotype.
What the gene does. RBM8A encodes Y14, a core protein of the exon junction complex, which is involved in messenger RNA maturation. Reduced functional Y14 is thought to disturb the development of megakaryocytes, producing the thrombocytopenia, and of the radial limb structures. The precise mechanism that spares the thumb is not fully understood (DOI).
The platelets. The thrombocytopenia is hypomegakaryocytic: the marrow has reduced or immature megakaryocytes, so platelet production is low. The count is usually lowest in infancy and tends to recover during childhood.
Platelet crises. Episodes of worsening thrombocytopenia can be precipitated by stress, infection and notably by cow's milk intolerance, which is why a feeding history is part of the haematological assessment (DOI).
Classification and Differential Diagnosis
There is no single grading scale for TAR itself. In practice, classification means placing TAR correctly within the radial-ray differential and describing the severity of each affected region.
The radial-ray differential. Each of the radial-ray syndromes carries a different systemic risk, and the thumb is the most useful discriminator between them.
- Radius / thumb pattern
- Bilateral absent radii WITH thumbs present.
- Inheritance / gene
- Autosomal recessive; RBM8A (1q21.1).
- Key systemic clue
- Neonatal thrombocytopenia that improves with age; cow's milk intolerance.
- Radius / thumb pattern
- Radial ray and thumb hypoplasia or aplasia; short stature.
- Inheritance / gene
- Mostly autosomal recessive; FANC genes.
- Key systemic clue
- Progressive marrow failure (may be normal at birth); cancer risk.
- Radius / thumb pattern
- Radial ray with thumb anomaly (triphalangeal or absent thumb).
- Inheritance / gene
- Autosomal dominant; TBX5.
- Key systemic clue
- Congenital heart disease and conduction defects.
- Radius / thumb pattern
- Radial defect as one component; thumb may be involved.
- Inheritance / gene
- Sporadic; non-Mendelian.
- Key systemic clue
- Vertebral, anal, cardiac, tracheo-oesophageal, renal anomalies.
A common trap is to lump TAR with Holt-Oram. They are opposites in two ways: TAR keeps the thumb and is autosomal recessive; Holt-Oram involves the thumb, has heart and conduction disease, and is autosomal dominant. The inheritance changes family counselling.
Describing severity by region. Rather than a single grade, describe what each region looks like:
- Upper limb - both radii absent; ulnae present but short and often bowed; hands radially deviated; thumbs present but sometimes with reduced function. In severe cases the humerus and elbow may also be involved, and phocomelia-like patterns are described.
- Lower limb - knee dysplasia is common, with genu varum, ligamentous laxity or stiffness, patellar abnormalities and described cruciate ligament deficiency; hip and foot anomalies also occur.
- Haematology - the current platelet count and the bleeding history, because these dictate timing more than any skeletal grade.
Associated anomalies. In a clinical series of 34 patients, all had documented thrombocytopenia and bilateral radial aplasia. Lower-limb anomalies were present in 47%, cow's milk intolerance in 47%, renal anomalies in 23% and cardiac anomalies in 15%, and additional features such as scoliosis and sensorineural hearing loss were also recorded (DOI).
Clinical Presentation
- Typical findings
- Bilateral short forearms with radially deviated hands and present thumbs; low platelets on first blood count.
- Clinical meaning
- Recognise the TAR pattern and treat the bleeding risk as the priority.
- Typical findings
- Bruising, petechiae, gastrointestinal bleeding or intracranial haemorrhage.
- Clinical meaning
- Thrombocytopenia is the main early cause of morbidity and death.
- Typical findings
- Worsening thrombocytopenia or bleeding after cow's milk exposure.
- Clinical meaning
- Cow's milk intolerance is a recognised trigger; adjust feeds and watch counts.
- Typical findings
- Bilateral radial club hands, short forearms, variable thumb function, emerging knee deformity.
- Clinical meaning
- Platelets are usually improving; functional and skeletal issues come to the front.
- Typical findings
- Established upper-limb deformity plus genu varum, knee instability or knee osteoarthritis.
- Clinical meaning
- Lower-limb disease can dominate adult function and surgical need.
Function. Both upper limbs are involved symmetrically, so an affected child often uses adaptive grasp and compensatory shoulder and trunk movement. Because the thumbs are present, pinch potential is frequently better than in thumb-losing radial-ray conditions, and that influences how aggressively the wrist needs to be repositioned.
History and Examination
The history and examination cover the blood, the whole child and the limbs, in that order of safety.
History. Five areas, each tied to a decision:
- Bleeding - bruising, petechiae, gastrointestinal or intracranial bleeding, previous platelet transfusions. This defines the immediate risk and the safety of any procedure.
- Feeding - cow's milk exposure and any relationship to bleeding or platelet drops.
- Birth and antenatal - prenatal ultrasound findings, the neonatal course and other anomalies detected, which may reveal cardiac, renal or gastrointestinal involvement.
- Function - reach, pinch, grasp, dressing, feeding, mobility and any knee symptoms. These define the real reconstructive goals for the upper and lower limb.
- Family and genetics - consanguinity, affected relatives and prior genetic testing; TAR is recessive, so recurrence risk differs from the dominant syndromes.
Examination. Work from the general to the specific:
- General - bruising, petechiae, pallor, cardiac signs, abdominal findings, growth and dysmorphism, for bleeding risk and systemic involvement.
- Upper limb - symmetric short forearms, radial deviation, elbow motion, ulnar length and especially thumb presence and function, which confirm the TAR pattern and the pinch potential.
- Thumb - size, opposition, web space and stability. Present thumbs change the reconstructive plan compared with thumb-absent disease.
- Knees - alignment (genu varum), stability, range, patellar tracking and effusions. Knee dysplasia is common and may need long-term management.
- Other joints - hips, feet and spine, where anomalies are described that affect overall function.
It is easy to spend the whole examination on the forearms. In TAR the knees often determine adult mobility, and they may need more surgery over a lifetime than the forearms, so assess them deliberately.
Investigations
Blood first. The single most important investigation is the platelet count, with a full blood count and a clear bleeding history. Serial counts matter, because the trend (usually improving with age) guides the safe timing of surgery.
Radiographs. Image both forearms, wrists and hands, and the knees and any symptomatic joints:
- Forearm - confirm bilateral absent radii, assess ulnar length and bowing, and document carpal and metacarpal anatomy
- Thumb - confirm that it is present and assess its bony anatomy and stability
- Knee - look for the dysplastic features described in TAR: genu varum, a concave distal femur, a convex medial tibial plateau, patellar abnormalities and signs of ligamentous (including cruciate) deficiency (DOI)
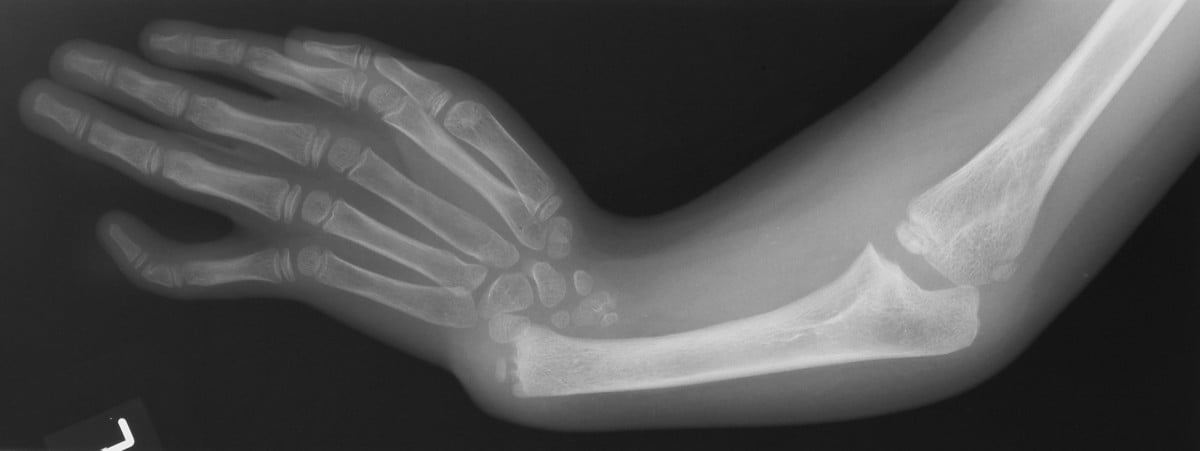
Screening the whole child. An echocardiogram and a renal ultrasound look for the cardiac and renal anomalies, which bear on anaesthetic safety and overall medical care.
Genetic testing. Molecular confirmation requires detecting both the 1q21.1 deletion and the low-expression RBM8A variant, which historically needed several techniques. Next-generation sequencing can now detect the copy-number change and the point variant in a single workflow, making confirmation more efficient (DOI). Genetic confirmation supports accurate counselling about recessive inheritance and recurrence risk (DOI).
The two-hit model is usually taught as "1q21.1 deletion plus one of two known low-expression RBM8A variants" — the 5'UTR rs139428292 and the intronic rs201779890. In the largest characterised cohort, only half of 26 molecularly confirmed patients carried one of those two variants. The other half carried four novel noncoding variants in the 5'UTR, the 3'UTR and introns, each shown in vitro to reduce expression or alter splicing (DOI).
So the assay matters, not just the request. A panel that genotypes the two familiar positions will miss roughly half of cases; one that sequences the whole RBM8A regulatory region will not. If the clinical picture is bilateral absent radii with present thumbs and neonatal thrombocytopenia, a negative targeted result should prompt a question about what the laboratory actually looked for, not a change of diagnosis.
This is also the honest framing for counselling: a confirmed deletion on one allele with no identified second hit is an incomplete result, not a refutation.
Antenatal Diagnosis and Delivery Planning
TAR is frequently a prenatal diagnosis, and getting the delivery right is part of protecting the thrombocytopenic newborn.
The scan. On second-trimester ultrasound the recognisable pattern is bilateral shortening of the forearms with the hands radially deviated but present, and with them the thumbs. That raises TAR alongside the other radial-ray syndromes. The scan cannot confirm the platelet count or the genetics, so the findings prompt referral for definitive testing rather than a firm label on imaging alone.
Molecular confirmation. Testing before birth uses the same two-hit detection as after it: a chromosomal microarray or copy-number assay for the 1q21.1 deletion on one allele, and testing for a low-expression RBM8A variant on the other, with the same caveat about what the assay covers. Next-generation sequencing can capture both the copy-number change and the noncoding variant in one workflow, which is as useful antenatally as postnatally (DOI). Where a previous child is affected and both parental alleles are known, testing can be directed and recurrence risk quoted precisely, because the inheritance is biallelic and recessive (DOI).
Delivery. This is the real management decision. A fetus suspected of having TAR should be delivered where paediatric haematology and neonatal care are available, with platelets on standby, because the newborn may be profoundly thrombocytopenic from the first hours of life and intracranial haemorrhage is the leading early cause of death (DOI). Traumatic instrumental delivery, and by the same logic any early invasive procedure, is best avoided until the platelet count and bleeding risk are known.
Management
Management is multidisciplinary and staged. The bleeding disorder governs the timing of everything skeletal, and both the upper and lower limbs need a plan.
The dramatic absent-radii deformity is not the immediate threat in a TAR infant. The threat is bleeding, including intracranial haemorrhage. Surgery, regional blocks, vigorous physiotherapy and even some splinting decisions must wait until the haematology is understood and controlled. Treating TAR as a pure hand problem is the classic mistake.
- Priority
- Control thrombocytopenia and bleeding risk.
- Action
- Haematology-led platelet support, avoid trauma, manage cow's milk intolerance, treat crises.
- Priority
- Identify cardiac, renal and other anomalies.
- Action
- Echocardiogram, renal ultrasound, paediatric and genetics review.
- Priority
- Protect skin and positioning, build adaptive use.
- Action
- Splinting, stretching and hand therapy; family education.
- Priority
- Improve hand position and function once safe.
- Action
- Wrist and hand procedures planned after the bleeding tendency settles.
- Priority
- Address knee deformity over the long term.
- Action
- Surveillance, bracing, osteotomy or arthroplasty in selected cases.
Haematology. The first job is to make the child safe. A haematology team manages severe thrombocytopenia with platelet support as required, careful avoidance of trauma and unnecessary procedures, and attention to triggers such as infection and cow's milk intolerance. Because counts usually improve with age, the same team advises when the bleeding tendency has settled enough for elective surgery. Patient and family support networks are increasingly recognised as part of long-term care (DOI).
Upper limb. Early splinting, gentle stretching and hand therapy protect skin and positioning. With the thumbs present, the emphasis is on improving hand position and grasp rather than creating a thumb. Selected children undergo wrist repositioning and hand reconstruction, but only once the bleeding disorder is controlled, and with realistic expectations about recurrence given the absent radial support and continued growth.
Lower limb. Knee disease is a long-term problem. Children may need bracing and surveillance, and selected patients undergo realignment or other procedures, yet the literature notes that management strategies have not reliably halted its natural progression. In an adult with TAR and knee osteoarthritis, total knee arthroplasty has been reported as safe and effective in a single case, with well-fixed components and improved knee and general health scores at three years (DOI).
The whole child. Cardiac, renal and gastrointestinal anomalies are managed alongside the orthopaedic problems. Any planned surgery requires a combined haematology and anaesthetic assessment, and procedures are sequenced so the child is never left without usable function during recovery.
Perioperative Haematological Management
Timing against the natural history. The thrombocytopenia is at its most dangerous in the first year of life, when severe counts and intracranial haemorrhage account for most of the early mortality. It then tends to improve through childhood, so many older children and adults have a much less severe bleeding tendency (DOI). This is why elective reconstruction is pushed beyond infancy: you are waiting for the child to grow and also for the safest haematological window (DOI).
Quantify, do not assume. The bleeding risk must be quantified and corrected around any procedure rather than assumed to have resolved. Even in an adult, platelet status is confirmed and haematology is involved before major elective surgery; in the reported adult knee arthroplasty this perioperative bleeding assessment was part of a safe outcome (DOI).
The checklist. Once elective surgery has been deferred past the high-risk infant year, into the phase where counts have recovered:
- Confirm a current platelet count and bleeding history; the count guides transfusion cover and the safety of the procedure
- Transfuse platelets to cover surgery and to treat active bleeding, to a level judged safe for the specific procedure, giving intra-operative and post-operative haemostatic cover
- Avoid antiplatelet drugs, including NSAIDs
- Look for and treat the triggers that can drop the count acutely, infection and cow's milk intolerance, because operating into an unrecognised platelet crisis is unsafe
- Plan jointly with haematology and anaesthesia, because the anaesthetic and bleeding risks must be managed together
Complications
- Problems
- Bleeding, including intracranial haemorrhage; platelet crises triggered by infection or cow's milk.
- Clinical lesson
- Bleeding is the leading early cause of death; control it before anything else.
- Problems
- Congenital heart disease (including reported associations such as Tetralogy of Fallot).
- Clinical lesson
- Screen the heart; it affects anaesthetic safety and survival.
- Problems
- Persistent radial deviation, limited reach, recurrence after wrist reconstruction.
- Clinical lesson
- Counsel families that absent radii and growth make recurrence likely.
- Problems
- Progressive knee dysplasia, genu varum, instability and later osteoarthritis.
- Clinical lesson
- Knee disease can dominate adult function and may need arthroplasty.
- Problems
- Renal anomalies, gastrointestinal problems, scoliosis and described hearing loss.
- Clinical lesson
- TAR is a whole-body syndrome requiring multidisciplinary follow-up.
What kills early. Intracranial haemorrhage and cardiac disorders are described as common and important causes of death in TAR, which is why early management is dominated by the blood and the heart rather than the limbs (DOI). The orthopaedic deformity is rarely the acute problem.
Clinical Relevance and Counselling
Counselling should be honest about the two-phase natural history. In infancy the message is bleeding precautions, feeding and avoiding unnecessary procedures; as the child grows it shifts to a lifelong musculoskeletal plan, dominated by the hands in childhood and the knees, which will need watching for years, into adulthood.
- Useful answer
- Usually the count is worst in infancy and improves as the child grows, but the early bleeding risk is real and serious.
- Why this is honest
- Reflects the typical natural history without minimising the danger.
- Useful answer
- We first make the blood safe and screen the heart and kidneys; elective hand surgery is safer once the bleeding tendency settles.
- Why this is honest
- Explains why timing is led by haematology.
- Useful answer
- Because the thumbs are present, useful pinch is often possible, and therapy plus selected surgery can improve hand position and grasp.
- Why this is honest
- Sets realistic, function-based expectations.
- Useful answer
- TAR is autosomal recessive, so recurrence risk is different from dominant syndromes; genetic counselling can give specific figures.
- Why this is honest
- Directs families to accurate, gene-based advice.
Guidelines, Registries & Global Practice
TAR is rare, so there is no large registry or single international guideline; practice is built from case series, cohort studies and specialist genetic reviews, and is consistent worldwide because the biology is the same everywhere.
- Consensus position
- Bilateral absent radii with present thumbs plus neonatal thrombocytopenia; confirm with RBM8A / 1q21.1 testing.
- Evidence basis
- Specialist reviews and molecular cohorts.
- Consensus position
- Haematology-led bleeding control takes priority over elective limb surgery in infancy.
- Evidence basis
- Phenotype series and case reports emphasising haemorrhagic and cardiac risk.
- Consensus position
- Elective reconstruction is generally undertaken once thrombocytopenia improves with age.
- Evidence basis
- Natural-history descriptions across series.
- Consensus position
- Lifelong knee surveillance; arthroplasty is an option for adult end-stage disease.
- Evidence basis
- Phenotype cohort and an adult arthroplasty case report.
- Consensus position
- Counsel as an autosomal recessive, multisystem, lifelong condition.
- Evidence basis
- Genetic studies confirming biallelic RBM8A inheritance.
The most useful global lesson is sequencing: wherever a child with TAR is treated, safe care means controlling the blood and screening the whole child before elective skeletal surgery, then planning lifelong upper- and lower-limb follow-up.
Related pages: Radial Longitudinal Deficiency is the parent classification for the absent radius and carries the Bayne grading, centralisation and radialisation decisions in full - the crucial point being that TAR sits apart from every other radial ray anomaly because the thumbs are present, which is the single fastest bedside discriminator; Thumb Hypoplasia for the spectrum that is absent here and present in Holt-Oram, Fanconi anaemia and VACTERL, and for the Blauth grading a preserved TAR thumb should be measured against; Congenital Hand Overview for where radial deficiency sits among the limb-formation failures; Ulnar Club Hand for the mirror deformity on the postaxial border; Congenital Knee Dislocation and Congenital Lower Limb Deficiency Overview for the lower-limb involvement present in 47 percent of the Greenhalgh cohort, which is the reason this is an orthopaedic rather than purely a hand topic; Haemophilia for the parallel problem of operating on a child with a bleeding diathesis, including the principle that the haematological plan precedes the surgical one; Skeletal Dysplasias for the wider differential of a short, deformed limb with systemic features; and Syndactyly for the other congenital hand difference most often coexisting with a syndromic diagnosis.
Viva Scenarios
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“A newborn has bilateral short forearms with radially deviated hands, but both thumbs are present. What is your immediate priority and your leading diagnosis?”
“The parents of a child with confirmed TAR ask when the hands can be operated on. How do you decide on timing?”
“An adult with known TAR presents with painful knee osteoarthritis and genu varum. How do you approach this?”
Define it in one line
- Bilateral absent radii + thrombocytopenia from birth + thumbs PRESENT.
- Autosomal recessive; RBM8A on chromosome 1q21.1 (two-hit model).
- Approximate frequency around 0.4 per 100,000 live births.
The discriminator
- Thumbs present = TAR (vs Fanconi and Holt-Oram, which involve the thumb).
- Holt-Oram: dominant, TBX5, heart and conduction disease.
- Fanconi: marrow failure (may be normal at birth), cancer risk, breakage testing.
Timing and safety
- Platelet count first; bleeding (intracranial haemorrhage) is the early killer.
- Cow's milk intolerance can trigger platelet crises.
- Counts usually improve with age; do elective surgery once safe.
Beyond the forearm
- Knee dysplasia and genu varum are common and progress.
- Cardiac (e.g. associations such as Tetralogy of Fallot) and renal anomalies.
- Total knee arthroplasty reported as effective in adult TAR knees.
One-line viva opener
- "Absent radii with present thumbs is TAR until proven otherwise; I would check the platelet count and bleeding risk before anything else."
Evidence Base
TAR is a multisystem syndrome, not just absent radii
- In 34 patients, all had documented thrombocytopenia and bilateral radial aplasia.
- Lower-limb anomalies were present in 47%, cow's milk intolerance in 47%, renal anomalies in 23% and cardiac anomalies in 15%.
- Additional features included scoliosis and sensorineural hearing loss, broadening the recognised phenotype beyond the forearm.