The Deforming Force of the Bunion
- Two heads: an OBLIQUE head from the bases of the second to fourth metatarsals and the peroneus longus sheath, and a TRANSVERSE head from the plantar plates of the third to fifth metatarsophalangeal joints and the deep transverse metatarsal ligament.
- Both heads insert into the plantar-lateral base of the hallux proximal phalanx and the LATERAL (fibular) sesamoid, blending with the lateral head of flexor hallucis brevis to form the CONJOINED TENDON.
- Innervated by the DEEP branch of the lateral plantar nerve (S2, S3) - it runs in the fourth layer with the deep plantar arch, deep to the muscle it supplies.
- In hallux valgus the sesamoid complex stays tethered to the lesser metatarsals by the deep transverse metatarsal ligament, so the metatarsal head slides medially OFF the sesamoids - the sesamoids do not subluxate, the metatarsal does.
- The modified McBride is a lateral release of the adductor conjoined tendon, the lateral capsule and the lateral metatarsosesamoid (suspensory) ligament - WITHOUT excising the fibular sesamoid, which is what caused hallux varus in the original operation.
- “The adductor is the only intrinsic that crosses the first web space obliquely - it is therefore the only muscle that can actively lateralise the hallux.
- “The transverse head is functionally part of the deep transverse metatarsal ligament complex; it is a transverse tie-beam, not a toe mover.
- “Its insertion is plantar-lateral to the metatarsophalangeal axis, so it flexes as well as adducts - divide it and the hallux loses a small amount of plantarflexion power.
- “Adductor tenotomy through the first web space puts the dorsal digital branches of the deep peroneal nerve and the first dorsal metatarsal artery at risk within a few millimetres of the skin incision.
Overview
The adductor hallucis is a two-headed intrinsic muscle of the third plantar layer, the layer of the short muscles of the two border toes with the adductor bridging between them. Its oblique head sweeps forward and medially across the sole from the lesser metatarsal bases; its transverse head runs across the forefoot immediately behind the lesser metatarsophalangeal joints. Both converge on the plantar-lateral base of the hallux proximal phalanx and the fibular sesamoid.
Why it matters. Functionally it is a modest muscle. Surgically it is one of the most important structures in the forefoot, because it is the only muscle capable of actively adducting and pronating the hallux, and therefore the only muscle that can convert a first-ray alignment problem into a fixed, progressive bunion. Every lateral soft-tissue release described for hallux valgus is fundamentally an adductor operation, and a release taken too far produces hallux varus.
Attachments and the Conjoined Tendon
Oblique head. The larger, deeper, longitudinal head arises from the plantar aspect of the bases of the second, third and fourth metatarsals, from the sheath of the peroneus longus tendon as it crosses the sole in the fourth layer, and from adjacent fibres of the lateral band of the plantar aponeurosis and the long plantar ligament. It runs obliquely forward and medially in the third layer, deep to the flexor tendons and the lumbricals and superficial to the interossei and the peroneus longus tendon.
Transverse head. The smaller, superficial, transverse head arises from the plantar metatarsophalangeal (plantar plate) ligaments of the third, fourth and fifth toes and from the deep transverse metatarsal ligaments joining those plantar plates. It runs transversely across the forefoot immediately proximal to the lesser metatarsophalangeal joints, in the plane of the deep transverse metatarsal ligament.
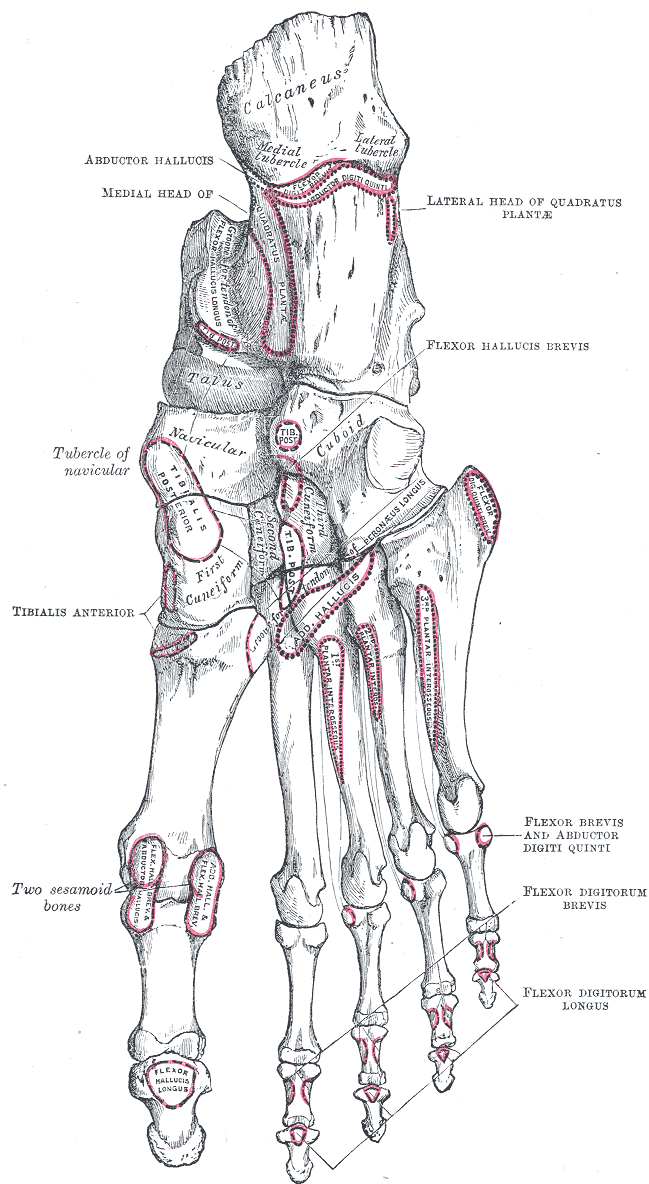
Insertion. Both heads insert into the plantar-lateral aspect of the base of the proximal phalanx of the hallux, the lateral (fibular) sesamoid and the lateral aspect of the plantar plate, with fibres also reaching the lateral joint capsule of the first metatarsophalangeal joint. Over the last 1 to 1.5 cm before insertion the tendon fuses with that of the lateral head of flexor hallucis brevis to form the conjoined tendon, the single most important structure to identify at lateral release.
The conjoined tendon. The two tendons cannot be reliably separated at operation and should be thought of as one plantar-lateral tendon unit. That is why an adductor tenotomy inevitably weakens the lateral head of flexor hallucis brevis, and why the fibular sesamoid loses much of its dynamic control after release. The unit inserts plantar to the metatarsophalangeal joint axis, so it is a weak plantarflexor of the hallux in addition to an adductor.
Innervation
Nerve supply. The deep branch of the lateral plantar nerve (S2, S3). The tibial nerve (L4 to S3) divides in the tarsal tunnel into the medial and lateral plantar nerves, usually at or just distal to the level of the medial malleolus. The lateral plantar nerve (S1 to S3, functionally S2 and S3 for the intrinsics) passes deep to flexor digitorum brevis and quadratus plantae, then divides at about the level of the fifth metatarsal base into a superficial and a deep branch.
The deep branch. It turns medially with the deep plantar arch in the fourth layer, deep to the oblique head of adductor hallucis, and supplies:
- Adductor hallucis, both heads
- The second, third and fourth lumbricals
- All the interossei except those of the fourth interosseous space
Motor entry point. The deep branch enters the deep surface of the oblique head as it crosses the sole. The nerve is therefore deep to the muscle it supplies, which is why a superficial release of the tendon distally does not denervate it, whereas a dissection through the muscle belly proximally may. It is the same nerve that runs with the deep plantar arch, so a plantar approach to the mid-metatarsal region must respect both together.
Lesions. A proximal tibial or lateral plantar nerve lesion (tarsal tunnel, high tibial nerve injury) denervates adductor hallucis along with the interossei, producing the intrinsic-minus forefoot with claw toes described under clinical relevance. Because the adductor is a lateral plantar nerve muscle and abductor hallucis is a medial plantar nerve muscle, a selective lateral plantar nerve lesion spares the abductor and produces a subtle hallux varus tendency, whereas the far commoner combined lesion produces global intrinsic wasting.
Blood Supply
Arterial supply. The deep plantar arch, the continuation of the lateral plantar artery completed medially by the deep plantar artery from the dorsalis pedis through the first intermetatarsal space, lies immediately deep to the oblique head with the deep branch of the lateral plantar nerve. Plantar metatarsal arteries arising from the arch supply the transverse head segmentally, and the first plantar metatarsal artery and the medial plantar artery contribute at the insertion.
The pedicle. The dominant pedicle enters the deep (dorsal) surface of the oblique head, in the plane of the deep plantar arch, roughly at the junction of the middle and proximal thirds of the muscle. Because of this deep, segmental supply the oblique head can be raised as a small local muscle flap for plantar forefoot coverage, most usefully for a plantar first metatarsophalangeal or first web space defect, or to fill dead space after debridement of a neuropathic ulcer or a septic first metatarsophalangeal joint.
Limits of the flap. The arc of rotation is short: only the distal third reaches the plantar-medial hallux reliably. The flap is rarely appropriate in the ischaemic or heavily neuropathic foot, where the same arch supply is compromised.
Orientation of a plantar incision. The arch and its nerve run transversely across the sole at the level of the metatarsal bases, so a longitudinal plantar incision crosses them at right angles and is the most dangerous orientation. Any plantar dissection proximal to the mid-metatarsal level should be transverse.
Relations
The four plantar layers. Where the adductor sits among its neighbours:
- Contents
- Abductor hallucis, flexor digitorum brevis, abductor digiti minimi
- Contents
- Quadratus plantae, lumbricals, flexor digitorum longus and flexor hallucis longus tendons
- Contents
- Flexor hallucis brevis (two heads, each containing a sesamoid), adductor hallucis (oblique and transverse heads), flexor digiti minimi brevis (fifth metatarsal base to fifth proximal phalanx)
- Contents
- Plantar and dorsal interossei, tibialis posterior and peroneus longus tendons
Superficial (plantar). The flexor digitorum longus and flexor digitorum brevis tendons with the lumbricals, the second layer; the flexor hallucis longus tendon running medially between the two heads of flexor hallucis brevis; and the superficial branch of the lateral plantar nerve with its digital branches.
Deep (dorsal). The deep plantar arch and the deep branch of the lateral plantar nerve, the structures at greatest risk in a deep plantar dissection; the peroneus longus tendon crossing the sole obliquely in its groove in the cuboid to the base of the first metatarsal and medial cuneiform; and the interossei and the metatarsal shafts.
Medial. The lateral head of flexor hallucis brevis, with which it conjoins, the fibular sesamoid and the lateral capsule of the first metatarsophalangeal joint. Further medially lie the flexor hallucis longus tendon in the intersesamoid groove, then the tibial sesamoid, the medial head of flexor hallucis brevis and abductor hallucis.
Lateral. The transverse head continues laterally to the fifth plantar plate; the flexor digiti minimi brevis and the abductor digiti minimi lie beyond.
Action and Biomechanics
Actions. What the muscle does, in the transverse plane and beyond:
- Adduction of the hallux in the transverse plane, towards the second toe. This is the only muscle that performs it.
- Pronation of the hallux about its long axis, because the conjoined insertion is plantar-lateral and the pull is oblique. This is the mechanism of the pronated nail plate seen in established hallux valgus.
- Plantarflexion of the first metatarsophalangeal joint, weakly.
- Transverse stabilisation of the forefoot by the transverse head.
- Support of the transverse and medial longitudinal arches as part of the intrinsic muscle sling, together with the plantar aponeurosis and the interossei.
The transverse head as a tie-beam. The transverse head is not really a toe mover. Its fibres run in the same plane as the deep transverse metatarsal ligaments, so it behaves as a dynamic transverse tie across the metatarsal parabola, resisting forefoot splay under load in late stance. Loss or attenuation of this restraint contributes to metatarsus primus varus and forefoot splay, the "splay foot" that accompanies long-standing hallux valgus, and it is why the transverse head is a genuine deforming structure that must be released, not merely bypassed, when the intermetatarsal angle is being corrected.
The force couple. In a normally aligned foot the adductor's line of pull is only a few degrees lateral to the long axis of the hallux, so its adduction moment is small and is balanced by abductor hallucis medially. The medial, correcting side of the couple is abductor hallucis, the medial capsule with the medial metatarsosesamoid ligament, and the medial head of flexor hallucis brevis acting through the tibial sesamoid. The lateral, deforming side is adductor hallucis with both heads, the lateral head of flexor hallucis brevis acting through the fibular sesamoid, the lateral capsule and lateral metatarsosesamoid ligament, and the deep transverse metatarsal ligament tethering the sesamoid complex laterally.
Why the deformity accelerates. As the hallux valgus angle increases, the adductor's line of pull moves further lateral to the joint centre and its moment arm lengthens, while abductor hallucis migrates plantarward around the metatarsal head, is lost early in the sequence, and loses almost all of its varus moment; the medial capsule and medial metatarsosesamoid ligament attenuate and fail. Extensor hallucis longus and flexor hallucis longus, both in the midline in a normal foot, are carried laterally with the phalanx and become secondary lateral deforming forces, bowstringing lateral to the joint axis. The transverse-plane force couple is lost, and once it is unbalanced the deformity is mechanically committed to progression: the more valgus, the greater the lateral moment arm of the adductor, and the greater the lateral pull.
What follows for treatment. This is why hallux valgus does not spontaneously improve, and why a bony osteotomy without a lateral release frequently recurs. Correction requires the lateral, deforming column to be released and the medial column to be re-tensioned, which is exactly what the modified McBride does; neither alone corrects a structural intermetatarsal angle, which needs an osteotomy.
Surgical division. After a lateral release the hallux loses active adduction, which is functionally irrelevant, and a small component of plantarflexion power at the first metatarsophalangeal joint. Patients do not complain of weakness. What they complain of is the consequence of over-release, hallux varus.
Contracture. An adaptively shortened adductor and lateral capsule in long-standing hallux valgus resists intraoperative correction, and is the reason correction of a severe deformity feels "tight" until the release is complete.
Synergists and antagonists.
- Muscle
- Adductor hallucis
- Nerve
- Deep branch lateral plantar (S2, S3)
- Comment
- No substitute exists
- Muscle
- Abductor hallucis
- Nerve
- Medial plantar (S1, S2)
- Comment
- Migrates plantarward in hallux valgus and is functionally lost
- Muscle
- Flexor hallucis brevis (both heads)
- Nerve
- Medial plantar (S1, S2)
- Comment
- Lateral head is conjoined with adductor
- Muscle
- Deep transverse metatarsal ligaments, plantar interossei
- Nerve
- Passive / lateral plantar
- Comment
- Together resist forefoot splay
- Muscle
- EHL and FHL
- Nerve
- Deep peroneal / tibial
- Comment
- Bowstring laterally once the phalanx deviates
Surface Anatomy and Examination
Palpation. The adductor cannot be palpated selectively. Its transverse head can be appreciated indirectly as a firm transverse band deep in the sole immediately proximal to the lesser metatarsophalangeal joints, with the toes passively dorsiflexed to slacken the flexors. The insertion and the fibular sesamoid are palpable from the plantar-lateral aspect of the first metatarsophalangeal joint with the hallux held in slight plantarflexion and varus; tenderness here in an athlete suggests fibular sesamoid or conjoined tendon pathology rather than a bunion. In an established bunion the conjoined tendon is felt as the taut cord limiting passive varus correction of the hallux.
Passive correctability. There is no isolated strength test for the adductor: it has no substitute and no antagonist that can be selectively loaded. What matters clinically is whether the lateral soft tissues are contracted, and that is assessed passively.
- How to perform
- Stabilise the first metatarsal between thumb and index finger; grasp the hallux, derotate the pronation and translate the proximal phalanx medially
- Positive finding
- Hallux cannot be brought passively to neutral, or corrects only against a firm end-point with residual pronation
- What it means
- Fixed contracture of the conjoined tendon, lateral capsule and lateral metatarsosesamoid ligament - a formal lateral release will be required
- False positives / pitfalls
- Pain-related guarding; a coexisting hallux rigidus limits the arc and mimics a soft-tissue block
- How to perform
- Plantarflex the ankle to slacken flexor and extensor hallucis longus, then repeat the correction
- Positive finding
- Tightness persists despite slackened long tendons
- What it means
- The block is intrinsic (adductor, capsule, suspensory ligament) rather than bowstringing long tendons
- False positives / pitfalls
- Failure to fully slacken the long tendons; the patient actively resisting
- How to perform
- Take the joint through a full flexion-extension arc feeling for a dorsal osteophyte and crepitus
- Positive finding
- Painful terminal dorsiflexion with a palpable dorsal ridge
- What it means
- Concomitant hallux rigidus - changes the operation from realignment to cheilectomy or fusion
- False positives / pitfalls
- Mistaking a large medial eminence for a dorsal osteophyte
- How to perform
- Assess valgus at the interphalangeal joint with the metatarsophalangeal joint held corrected
- Positive finding
- Residual distal valgus with a corrected metatarsophalangeal joint
- What it means
- Hallux valgus interphalangeus - needs an Akin osteotomy, not more lateral release
- False positives / pitfalls
- Attributing the whole deformity to the metatarsophalangeal joint
- How to perform
- Palpate the fibular sesamoid from the plantar-lateral aspect with the hallux slightly plantarflexed
- Positive finding
- Focal tenderness over the fibular sesamoid, worse on resisted push-off
- What it means
- Fibular sesamoid pathology or conjoined tendon insertional injury rather than bunion pain
- False positives / pitfalls
- Generalised forefoot tenderness in the inflamed bunion; interdigital neuroma referral
Sesamoid position. On a weight-bearing dorsoplantar radiograph, grade the position of the tibial sesamoid relative to the longitudinal axis of the first metatarsal on the Hardy and Clapham seven-point scale; a sesamoid axial (tangential) view shows the eroded crista and the degree of metatarsal head pronation. Failure of the sesamoid position to normalise on the postoperative radiograph after an apparently good bony correction is the radiographic signature of an inadequate lateral release, and correlates with recurrence.
Radiographic parameters to quote.
- Normal
- Less than 15 degrees
- Relevance to the adductor
- Directly reflects the lengthening adductor moment arm
- Normal
- Less than 9 degrees
- Relevance to the adductor
- Reflects loss of transverse restraint; not correctable by soft-tissue release alone in structural deformity
- Normal
- Less than 10 degrees
- Relevance to the adductor
- An incongruent joint needs realignment; a congruent joint with a high DMAA needs a distal closing osteotomy, not a bigger release
- Normal
- Grades 1 to 3
- Relevance to the adductor
- Grade 4 or more indicates the sesamoid tether has been overwhelmed and the metatarsal head has translated medially off the sesamoid complex
- Normal
- Less than 10 degrees
- Relevance to the adductor
- Hallux valgus interphalangeus needs an Akin osteotomy, not more lateral release
Complications
The complications, their mechanism, and how each is avoided:
- Mechanism
- Over-release plus fibular sesamoidectomy plus excessive medial eminence resection plus tight medial reefing
- Avoidance
- Preserve the fibular sesamoid; resect the eminence only to the sagittal sulcus; test correction intraoperatively before reefing
- Mechanism
- Incomplete release - typically the lateral metatarsosesamoid ligament left intact, or an uncorrected intermetatarsal angle or DMAA
- Avoidance
- Confirm the sesamoids reduce intraoperatively and on the postoperative radiograph; match the osteotomy to the deformity
- Mechanism
- Sharp dissection in the dorsal first web space
- Avoidance
- Skin-only incision, blunt spreading, retract with the fat pad
- Mechanism
- Stripping the plantar-lateral capsular pedicle at the neck, particularly with a concurrent distal osteotomy
- Avoidance
- Keep the release on the capsule and tendon; avoid circumferential neck stripping
- Mechanism
- Blind deep plantar dissection proximal to the mid-metatarsal level
- Avoidance
- Stay distal and superficial; use transverse plantar incisions when depth is needed
- Mechanism
- Dissection through the oblique head belly
- Avoidance
- Release the tendon distally rather than dividing the muscle proximally
- Mechanism
- Division of the conjoined tendon weakens the lateral head of FHB
- Avoidance
- Accept it - clinically silent; but do not compound it with a tibial sesamoidectomy
- Mechanism
- Overzealous transverse head and plantar plate release
- Avoidance
- Release the transverse head from the hallux side, not by detaching lesser plantar plates
- Mechanism
- Shortening or dorsal elevation of the first metatarsal after the combined osteotomy, not from the release itself
- Avoidance
- Preserve first ray length and plantar position
Clinical Relevance
Hallux valgus. The adductor is the engine of the deformity. The sesamoid complex (the tibial and fibular sesamoids, the intersesamoid ligament, the two heads of flexor hallucis brevis, the adductor and abductor insertions and the plantar plate) is anchored laterally to the second metatarsal by the deep transverse metatarsal ligament and the transverse head of adductor hallucis. That tether is far stronger than the metatarsosesamoid ligaments that hold the sesamoids under the first metatarsal head, so when the first metatarsal drifts into varus the sesamoids stay put and the metatarsal head slides medially off them. Say it precisely: the sesamoids do not subluxate laterally; the first metatarsal head subluxates medially off a tethered sesamoid complex.
The sequence. The clinical sequence to be able to recite:
- Predisposition: a long first metatarsal, an oblique or rounded first metatarsocuneiform joint, ligamentous laxity, family history and constricting footwear.
- Metatarsus primus varus develops, and the metatarsal head begins to translate medially while the sesamoid complex remains tethered laterally.
- The medial capsule and medial metatarsosesamoid ligament attenuate; the crista, the median ridge on the plantar metatarsal head separating the sesamoid grooves, erodes; the metatarsal head pronates.
- The force couple fails: abductor hallucis migrates plantarward and loses its correcting moment, and the adductor moment arm lengthens.
- Extensor and flexor hallucis longus bowstring laterally; the hallux pronates and the nail faces medially.
- Progression becomes obligatory, with transfer of load to the second metatarsal (second metatarsalgia, plantar plate attenuation, second-toe deformity) and eventually a crossover second toe.
What a release can and cannot do. A lateral release corrects the position of the hallux, not the intermetatarsal angle. Any structural increase in the 1-2 intermetatarsal angle requires a bony osteotomy; soft-tissue surgery alone reliably fails in anything other than a mild, congruent, laxity-driven deformity.
Fibular sesamoid pathology. Because the conjoined tendon inserts into it, the fibular sesamoid is loaded in push-off with the hallux dorsiflexed. Localised plantar-lateral first metatarsophalangeal pain, worse in terminal stance, suggests fibular sesamoiditis, stress fracture or osteonecrosis. Image with weight-bearing dorsoplantar and lateral radiographs plus an axial sesamoid view, and MRI for marrow oedema, fragmentation or osteonecrosis (low T1, high T2 signal, later collapse and fragmentation).
The divided fibular sesamoid. The fibular sesamoid is far less commonly bipartite than the tibial sesamoid, so a divided fibular sesamoid on a radiograph should raise suspicion of a genuine fracture. Fibular sesamoidectomy is a recognised salvage, but it removes the plantar-lateral anchor of the conjoined tendon and can precipitate hallux varus, particularly if the tibial sesamoid or the lateral capsule is also compromised.
Intrinsic-minus forefoot. Denervation of the deep branch of the lateral plantar nerve, as part of a tibial or lateral plantar nerve lesion, removes adductor hallucis together with the interossei and the lateral lumbricals. The result is claw toes from unopposed long extensor pull at the metatarsophalangeal joints and long flexor pull at the interphalangeal joints, forefoot splay from loss of the transverse tie, and plantar prominence of the metatarsal heads with callus or ulceration. Common contexts are Charcot-Marie-Tooth disease, diabetic distal symmetrical polyneuropathy, spinal dysraphism, post-polio, and the sequelae of compartment syndrome of the foot.
Compartment syndrome of the foot. The adductor lies within the interosseous and central compartment territory, depending on the compartment model used; the calcaneal compartment containing quadratus plantae is the one classically implicated in calcaneal fracture crush injuries. Missed foot compartment syndrome, after a calcaneal fracture, Lisfranc crush or forefoot crush, produces intrinsic contracture, and the adductor is one of the muscles whose fibrosis fixes the hallux in adduction and pronation.
Forefoot sepsis. The plane deep to the oblique head, containing the deep plantar arch, is a route by which plantar forefoot sepsis tracks proximally. A diabetic plantar forefoot abscess that has entered this plane requires formal decompression rather than a bedside incision.
Surgical Relevance
The lateral release. A complete distal soft-tissue release divides three structures, and naming all three is the exam answer. Releasing only the adductor tendon and leaving the lateral metatarsosesamoid (suspensory) ligament intact is the commonest technical error.
- Why it must be released
- It is the active deforming force and the primary lateral tether of the phalanx
- Consequence if omitted
- Persistent lateral pull, early recurrence of the hallux valgus angle
- Why it must be released
- It is contracted and prevents passive correction
- Consequence if omitted
- A tight end-point on correction; incomplete reduction
- Why it must be released
- It holds the sesamoid complex laterally under the second metatarsal territory
- Consequence if omitted
- The sesamoids will not reduce beneath the metatarsal head - the classic cause of persistent sesamoid malposition and recurrence
- Why it must be released
- NOT part of a modified McBride
- Consequence if omitted
- If excised, loss of the plantar-lateral anchor and a markedly increased risk of hallux varus
Original versus modified McBride. McBride's original operation combined adductor tenotomy and transfer, lateral capsulotomy, medial eminence resection and medial capsulorrhaphy with routine excision of the fibular sesamoid. Excision devascularises and destabilises the conjoined tendon: once the sesamoid is gone the tendon has no plantar-lateral anchor and the medial pull of abductor hallucis is unopposed, and the sesamoidectomy produced unacceptable rates of hallux varus, which fell once it was abandoned. The modified McBride, the distal soft-tissue procedure, releases the conjoined tendon, the lateral capsule and the lateral metatarsosesamoid ligament, resects the medial eminence and reefs the medial capsule, and preserves the fibular sesamoid: that preservation is the modification, and the single most examinable point.
Combining it with an osteotomy. The release is the standard soft-tissue component and is almost always combined with a metatarsal osteotomy, a proximal crescentic or proximal chevron for the moderate to severe deformity with a large intermetatarsal angle. Isolated release without a bony procedure is reserved for the mild, congruent, laxity-driven deformity with a near-normal intermetatarsal angle; otherwise recurrence is high.
Transarticular approach. The release is performed through the standard medial (or dorsomedial) approach to the first metatarsophalangeal joint, working across the joint from medial to lateral with the joint distracted and the hallux held in varus:
- Distract the joint and identify the taut conjoined tendon at the plantar-lateral base of the proximal phalanx
- Release it sharply off the phalanx and the fibular sesamoid
- Divide the lateral capsule
- Divide the lateral metatarsosesamoid ligament, feeling the sesamoid complex reduce
It needs one incision, no dorsal first web space wound, and avoids the dorsal digital nerves entirely. The price is working blind next to the plantar-lateral neck of the metatarsal, which carries the capsular vascular pedicle to the head; sharp dissection here can also injure the first dorsal metatarsal artery and its perforating branch between the first and second metatarsal bases. Multiple small transverse capsular incisions ("pie-crusting") over the lateral capsule with the hallux held corrected are a controlled alternative to a single long capsulotomy and reduce the risk of over-release.
The first metatarsal head is supplied largely from a plantar-lateral capsular pedicle in the same territory as the release. Concern about avascular necrosis when a distal chevron is combined with an extensive lateral release is long-standing; contemporary series report low rates, but keep the release to the capsule and tendon, do not strip the plantar-lateral neck periosteum, and preserve the pedicle where it enters the plantar-lateral capsule at the metatarsal neck.
Dorsal first web space approach. A 2 to 3 cm longitudinal incision in the dorsal first web space, centred over the first intermetatarsal space, spreading down between the first and second metatarsals to reach the adductor. The structures are met in order:
- Skin and subcutaneous tissue containing the dorsal digital branches of the deep peroneal nerve
- The interval between the first and second metatarsals, with the first dorsal metatarsal artery and the perforating branch to the deep plantar arch
- The transverse head of adductor hallucis, the first part of the muscle the scalpel meets as it passes plantarward
- The conjoined tendon and the lateral capsule
It gives direct vision of the transverse head and the suspensory ligament and is better for a severe, stiff deformity. Against that are a second wound, the risk of dorsal digital nerve injury with web space numbness or a neuroma, and the possibility of a symptomatic scar in a shoe. Blunt spreading with a small self-retainer rather than sharp sweeping is what protects the nerve and the perforating vessel.
Adductor transfer. After release the tendon may be transferred rather than simply discarded: the described options suture the released conjoined tendon into the lateral capsule at the first metatarsal neck or into the periosteum of the lateral first metatarsal, converting a deforming lateral pull on the phalanx into a corrective pull on the metatarsal. The biological rationale is sound and the technique is described in the original operation. Evidence that transfer improves outcome over simple release is limited, and most contemporary practice performs a release without formal transfer.
Distances and safe zones.
- Dorsal digital branches of the deep peroneal nerve: subcutaneous in the dorsal first web space, within about 3 to 5 mm of the skin. There is no safe plane above the fascia; incise skin only, then spread.
- Conjoined tendon insertion: on the plantar-lateral base of the proximal phalanx, within about 5 mm distal to the joint line. Releasing distal to this is releasing nothing; releasing proximal to it enters the sesamoid complex.
- Lateral metatarsosesamoid (suspensory) ligament: from the plantar-lateral first metatarsal neck to the fibular sesamoid, roughly 1 cm proximal to the joint line in the plantar-lateral corner. This is the structure that must be reached for the sesamoids to reduce.
- Perforating (communicating) branch between the dorsalis pedis and the deep plantar arch: in the proximal first intermetatarsal space, at the level of the metatarsal bases, and the reason a dorsal web space release should not be extended proximally.
Learn these as a triad and quote them whenever hallux varus comes up:
- Excision of the fibular sesamoid, as in the original McBride.
- Over-resection of the medial eminence beyond the sagittal sulcus, which removes the medial buttress of the metatarsal head and lets the phalanx fall into varus.
- Excessive medial capsular plication combined with an over-generous lateral release, an unbalanced soft-tissue envelope.
Two further contributors: over-correction of the intermetatarsal angle (a negative postoperative intermetatarsal angle) and prolonged postoperative dressing of the hallux in varus.
Reconstruction for iatrogenic hallux varus. Assess first: is the deformity flexible or fixed, is the metatarsophalangeal joint congruent or arthritic, has the fibular sesamoid been excised, and how much medial eminence was removed? The answers choose the operation:
- Flexible, joint preserved: medial capsular release, lateral capsular reefing and a dynamic lateral tether. The classic options are a split or whole extensor hallucis longus transfer routed beneath the deep transverse metatarsal ligament to the lateral proximal phalanx, an extensor hallucis brevis transfer, an abductor hallucis release and transfer, or a suture-button lateral tether; the released adductor, if still available, can also serve as the tether.
- Fixed with interphalangeal compensation: add a reverse Akin or a corrective proximal phalangeal osteotomy.
- Fixed, arthritic or failed reconstruction: first metatarsophalangeal arthrodesis is the reliable salvage, and the answer to give for the stiff, painful, recurrent varus.
Other operations that involve the adductor.
- Weil or distal metatarsal osteotomy of the lesser rays: the transverse head arises from the lesser plantar plates, so extensive plantar plate work alters its origin.
- Forefoot reconstruction in rheumatoid disease: the adductor is routinely released as part of the correction of severe hallux valgus with dislocated lesser metatarsophalangeal joints.
- First metatarsophalangeal arthrodesis: a lateral release is not needed to achieve correction, because the deformity is corrected at the fusion site; a release is still often useful to allow the hallux to be positioned without tension.
- Foot fasciotomy: the interosseous compartments are decompressed from the dorsum through the second and fourth intermetatarsal spaces; the medial, central and calcaneal compartments require a medial plantar incision, and the deep plantar neurovascular structures alongside the adductor are the reason that incision is placed and developed carefully.
Guidelines, Registries & Global Practice
Anatomical Variation Across Populations
- The two-headed pattern is essentially constant, but the size of the transverse head varies considerably, and a distinct third slip to the second toe plantar plate is described in a minority of dissections.
- Accessory slips of the oblique head to the fifth metatarsal base, and fusion of the transverse head with the flexor digiti minimi brevis, are recognised variants of no clinical consequence.
- Fibular sesamoid morphology varies markedly, and a bipartite fibular sesamoid is distinctly uncommon compared with the tibial sesamoid - relevant when interpreting a divided fibular sesamoid in an athlete.
- Hallux valgus prevalence rises with age and is consistently reported to be higher in women (30% versus 13% in the carded meta-analysis). Older comparative surveys report higher prevalence in habitually shod than habitually barefoot populations, and that comparison is widely quoted - but it rests on heterogeneous historical surveys rather than on the pooled data carded here, so treat footwear as permissive rather than causal on a background of inherited first-ray morphology. The carded Coughlin and Jones series puts the weighting well: 83% had a positive family history while only 34% implicated shoes or occupation.
How Different Sources Describe the Release
- Emphasis on the lateral release
- The distal soft-tissue procedure described as a defined three-structure release, most often through a transarticular approach, combined with an osteotomy selected by intermetatarsal angle and joint congruency.
- Emphasis on the lateral release
- Similar three-structure release; greater use of pie-crusting of the lateral capsule and reluctance to use a separate dorsal web space incision because of dorsal digital nerve morbidity.
- Emphasis on the lateral release
- Emphasises preservation of the plantar-lateral capsular blood supply to the metatarsal head and stepwise release with intraoperative assessment of correction.
- Emphasis on the lateral release
- Lateral release performed percutaneously or omitted altogether when a large translational correction of the metatarsal is achieved, on the argument that the sesamoids reduce with the metatarsal; this remains an area of genuine debate.
Areas of Genuine Uncertainty
- Is a lateral release always necessary? Advocates of large-translation minimally invasive and third-generation percutaneous osteotomies argue that adequate metatarsal translation reduces the sesamoids without a formal release. Others hold that the contracted lateral structures must be divided or the correction is not durable. High-quality comparative data are limited.
- Transarticular versus dorsal web space approach: both achieve release; the choice is largely a trade-off between blind dissection near the metatarsal head vascular pedicle and a second wound near the dorsal digital nerves.
- Adductor tendon transfer versus simple release: biologically appealing, but not shown to improve outcomes over release alone.
- Extent of capsular release: stepwise pie-crusting versus formal capsulotomy, with the recognised trade-off of incomplete correction against iatrogenic hallux varus.
High- versus Limited-Resource Practice
- Well-resourced settings: weight-bearing radiographs, increasing use of weight-bearing CT for sesamoid position and rotational assessment, a wide range of osteotomies and fixation, and access to revision reconstruction for hallux varus.
- Limited-resource settings: the modified McBride with a simple distal or proximal osteotomy fixed with a single screw or Kirschner wire remains an entirely appropriate operation. First metatarsophalangeal arthrodesis is a reliable, implant-light solution for the severe or arthritic deformity, and requires no lateral release for its correction.
- Everywhere: footwear advice, avoidance of constricting toe boxes, and clear counselling that a bunion is a mechanical deformity that will not regress with exercise.
Related pages: Hallux Valgus is the deformity this muscle drives once the first metatarsal has escaped medially, and the page where the correction is planned; Juvenile Hallux Valgus is the adolescent form in which the inherited first-ray morphology described here declares itself early. Sesamoid Disorders covers the fibular sesamoid this muscle inserts into, including the bipartite variant that must not be called a fracture. Flexor Hallucis Brevis and Flexor Hallucis Longus make up the rest of the sesamoid complex whose medial half is the antagonist to this muscle. Hallux Rigidus is the other first-ray diagnosis and the one that excludes several of the operations discussed here. Plantar Plate Insufficiency and Lesser Toe Deformities concern the structures the transverse head arises from, Metatarsalgia is what transfer of load away from the first ray produces, and Bunionette Deformity is the fifth-ray mirror image of the same mechanics.
MCQ Practice Points
Q: What is the nerve supply of adductor hallucis and its root value? A: The DEEP branch of the lateral plantar nerve, S2 and S3. Contrast with abductor hallucis and flexor hallucis brevis, which are supplied by the medial plantar nerve (S1, S2).
Q: From where does the transverse head of adductor hallucis arise? A: The plantar metatarsophalangeal (plantar plate) ligaments of the third, fourth and fifth toes and the deep transverse metatarsal ligaments. It is a transverse tie-beam across the metatarsal parabola, not a toe mover.
Q: Which two tendons form the conjoined tendon at the plantar-lateral first metatarsophalangeal joint? A: Adductor hallucis and the LATERAL head of flexor hallucis brevis, inserting into the plantar-lateral base of the hallux proximal phalanx and the fibular sesamoid.
Q: In hallux valgus, do the sesamoids subluxate laterally? A: No. The sesamoid complex is tethered to the second metatarsal by the deep transverse metatarsal ligament; the first metatarsal head slides medially off the sesamoids.
Q: In which plantar layer does adductor hallucis lie, and in which layer does its nerve run? A: The muscle is in the THIRD layer; the deep branch of the lateral plantar nerve that supplies it runs in the FOURTH layer with the deep plantar arch, deep to the oblique head.
Q: What is the modification in the modified McBride procedure? A: The fibular (lateral) sesamoid is PRESERVED. Routine excision in the original operation caused unacceptable rates of hallux varus.
Q: Which structure, if left intact, prevents the sesamoids from reducing after a lateral release? A: The lateral metatarsosesamoid (suspensory) ligament, running from the plantar-lateral metatarsal neck to the fibular sesamoid roughly 1 cm proximal to the joint line.
Q: Which hallux sesamoid is more commonly bipartite? A: The tibial (medial) sesamoid, by a wide margin. A divided fibular sesamoid should raise suspicion of a true fracture.
Q: What lies within a few millimetres of the skin in a dorsal first web space incision? A: Dorsal digital branches of the deep peroneal nerve. Deeper, at the level of the metatarsal bases, lies the perforating branch between the dorsalis pedis and the deep plantar arch.
Q: A high tibial nerve lesion denervates adductor hallucis. What forefoot deformity results and why? A: Claw toes and forefoot splay (the intrinsic-minus forefoot). The foot interossei and adductor insert only onto the proximal phalangeal bases and have no extensor expansion, so their loss leaves unopposed long extensor pull at the metatarsophalangeal joints and long flexor pull at the interphalangeal joints.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 46-year-old woman has a symptomatic hallux valgus with a hallux valgus angle of 34 degrees and an intermetatarsal angle of 15 degrees. She asks whether it will get worse if left alone. Explain the pathomechanics, referring to the adductor hallucis.”
“You are asked to describe the distal soft-tissue procedure. What exactly do you release, what do you deliberately NOT do, and why is the operation called modified?”
“Six months after a bunion correction performed elsewhere, a 52-year-old woman presents with the hallux deviated into 18 degrees of varus, unable to wear a closed shoe. The joint is passively correctable and radiographs show a normal joint space, an intermetatarsal angle of 2 degrees, an absent fibular sesamoid and a flush medial metatarsal head contour. Discuss.”
Anatomy
- Layer 3 of the sole (with FHB, FDMB)
- Oblique head: bases of MT 2-4, peroneus longus sheath
- Transverse head: plantar plates MTP 3-5 plus deep transverse MT ligament
- Insertion: plantar-lateral base hallux P1 plus FIBULAR sesamoid
- Conjoined tendon equals adductor plus LATERAL head FHB
Neurovascular
- Nerve: DEEP branch lateral plantar nerve (S2, S3)
- Nerve and deep plantar arch run DEEP to oblique head (layer 4)
- Artery: deep plantar arch, plantar metatarsal arteries
- Pedicle enters deep surface of oblique head - small local flap option
Hallux Valgus
- Metatarsal head slides MEDIALLY off tethered sesamoids
- Deep transverse MT ligament is the lateral tether
- Abductor hallucis migrates plantarward and is lost
- Adductor moment arm lengthens - progressive deformity
- Crista erodes; head pronates; EHL and FHL bowstring
Lateral Release (3 structures)
- 1. Conjoined tendon off P1 and fibular sesamoid
- 2. Lateral MTP joint capsule
- 3. Lateral metatarsosesamoid (suspensory) ligament, 1 cm proximal to joint
- NOT the fibular sesamoid - that is the modification
- Combine with osteotomy for a structural intermetatarsal angle
Hallux Varus Triad
- Fibular sesamoidectomy
- Medial eminence over-resection past the sagittal sulcus
- Excessive medial reefing plus over-generous lateral release
- Contributors: negative postoperative IMA, prolonged varus dressing
- Salvage: EHL or EHB transfer if flexible; arthrodesis if stiff or arthritic
Structures at Risk
- Dorsal digital branches deep peroneal nerve - 3 to 5 mm deep in web space
- Perforating branch to deep plantar arch - proximal 1st intermetatarsal space
- Plantar-lateral capsular pedicle to MT head at the neck (AVN risk)
- Deep plantar arch and deep branch LPN - transverse, at MT bases
Evidence Base
Observations on Hallux Valgus, Based on a Controlled Series
- NOTE - no abstract is indexed for this 1951 paper; the following is bounded by its title and by conventional attribution rather than by an abstract
- A controlled series of hallux valgus, comparing affected feet with controls
- The seven-point grading of tibial sesamoid position relative to the longitudinal axis of the first metatarsal is conventionally attributed to this paper
- It is also conventionally credited with establishing the relationship between the hallux valgus angle and the intermetatarsal angle
Hallux Valgus - Etiology, Anatomy, Treatment and Surgical Considerations
- Discussed the aetiology of hallux valgus, the method of patient selection, the technique of carrying out a MODIFIED McBRIDE procedure, and the surgical pitfalls associated with it
- Stressed the results of the procedure and the limitations the authors believed should be placed upon it
- Concluded that the modified McBride procedure is biomechanically sound and offers a satisfactory correction of the deformity
- Reported a very low incidence of postoperative complications, and noted that where a complication arises the surgeon has several good alternatives available to correct it
Hallux Valgus - Demographics, Etiology and Radiographic Assessment
- 103 of 108 patients (122 feet) with moderate or severe hallux valgus assessed prospectively with a standardised questionnaire, examination and radiographs
- 83% had a positive family history and 84% had bilateral bunions; onset peaked in the third decade, and 23% of feet developed the deformity at 20 years of age or younger
- The magnitude of the deformity was NOT associated with Achilles or gastrocnemius tightness, increased first ray mobility, bilaterality or pes planus
- Only 11% had evidence of an Achilles or gastrocnemius contracture, and 15% had moderate or severe pes planus
- Common findings were a family history, bilateral involvement, female sex, a LONG FIRST METATARSAL, and an oval or curved metatarsophalangeal articular surface
- Increased first ray mobility and plantar gapping of the first metatarsocuneiform joint were more common in patients with greater deformity
The Simple Bunion - Anatomy at the Metatarsophalangeal Joint of the Great Toe
- Located the pathomechanics of hallux valgus at the first metatarsophalangeal joint - specifically at the SESAMOID COMPLEX
- Defined the sesamoid complex as comprising SEVEN MUSCLES, EIGHT LIGAMENTS and TWO SESAMOID BONES
- Described the key event as the first metatarsal ESCAPING the complex and drifting MEDIALLY while the SESAMOIDS REMAIN TWISTED IN SITU
- Noted that some of the ligaments of the complex then fail while others contract
- Proposed reduction of the metatarsus primus varus by first metatarsal osteotomy together with appropriate ligament releases and plications to restore alignment
Prevalence of Hallux Valgus in the General Population
- Systematic review and meta-analysis of 78 studies with over 490,000 participants
- Pooled prevalence approximately 23% in adults aged 18 to 65 years and 36% in those over 65
- Prevalence was higher in females (30%) than males (13%)
- Identified potential sources of bias as the sampling method, study quality and the method of diagnosing hallux valgus
Blood Supply to the First Metatarsal Head and Vessels at Risk with a Chevron Osteotomy
- Ten cadaveric lower limbs injected with India ink-latex to map the arterial supply of the first metatarsal head against the limbs of a mapped distal chevron osteotomy
- Supply comes from the first dorsal metatarsal artery (dominant in 8 of 10 specimens), the first plantar metatarsal artery and the medial plantar artery
- ALL of these vessels form a plexus at the PLANTAR-LATERAL aspect of the metatarsal neck, just proximal to the capsular attachment - precisely where the adductor hallucis conjoined tendon and lateral capsule are released
- The plantar limb of the proposed chevron cut exited THROUGH this plexus in every specimen
- Contrary to the widely held view, only MINOR branches enter the DORSAL aspect of the neck
- Reported osteonecrosis of the first metatarsal head after chevron osteotomy ranges from 0% to 20%
Distal Chevron Osteotomy with Lateral Release: Avascular Necrosis Rate
- 42 feet in 30 patients had a combined distal chevron osteotomy and lateral release; 23 feet in 17 patients were available for review at a mean of 50 months
- NO foot developed definite radiographic evidence of avascular necrosis, assessed by a musculoskeletal radiologist blinded to outcome
- Intermetatarsal angle improved from 13 to 8 degrees and hallux valgus angle from 31 to 17.5 degrees
- 91% rated good or excellent; complications were two hallux varus, one extension contracture and one infection
- Directly addressed the concern that combining the two procedures devascularises the head