The Plantarflexor of the First Ray and Architect of the Cavovarus Foot
- Origin: head and upper two-thirds of the lateral fibula, the anterior and posterior intermuscular septa and the lateral tibial condyle.
- The common peroneal nerve divides within its substance at the fibular neck - the muscle wraps the nerve at its most vulnerable point.
- It crosses the sole obliquely in the cuboid tunnel to insert on the plantar-lateral base of the first metatarsal and the medial cuneiform.
- It is the only muscle that plantarflexes the first ray, and its unopposed action against a weak tibialis anterior produces cavovarus.
- Innervated by the superficial peroneal nerve, roots L5 and S1, entering the proximal third of the muscle.
- “The os peroneum is a sesamoid within the tendon at the cuboid, ossified in a substantial minority of feet, and its proximal migration on radiograph signals a peroneus longus rupture.
- “Coleman block test: if the hindfoot varus corrects with the first ray allowed to drop, the deformity is forefoot driven - treat the first ray.
- “The superficial peroneal nerve pierces the deep fascia 10 to 12 cm above the tip of the lateral malleolus - the most frequently injured nerve in lateral ankle surgery.
- “In Charcot-Marie-Tooth disease peroneus longus stays strong while tibialis anterior and peroneus brevis weaken - the exact recipe for cavovarus.
Overview
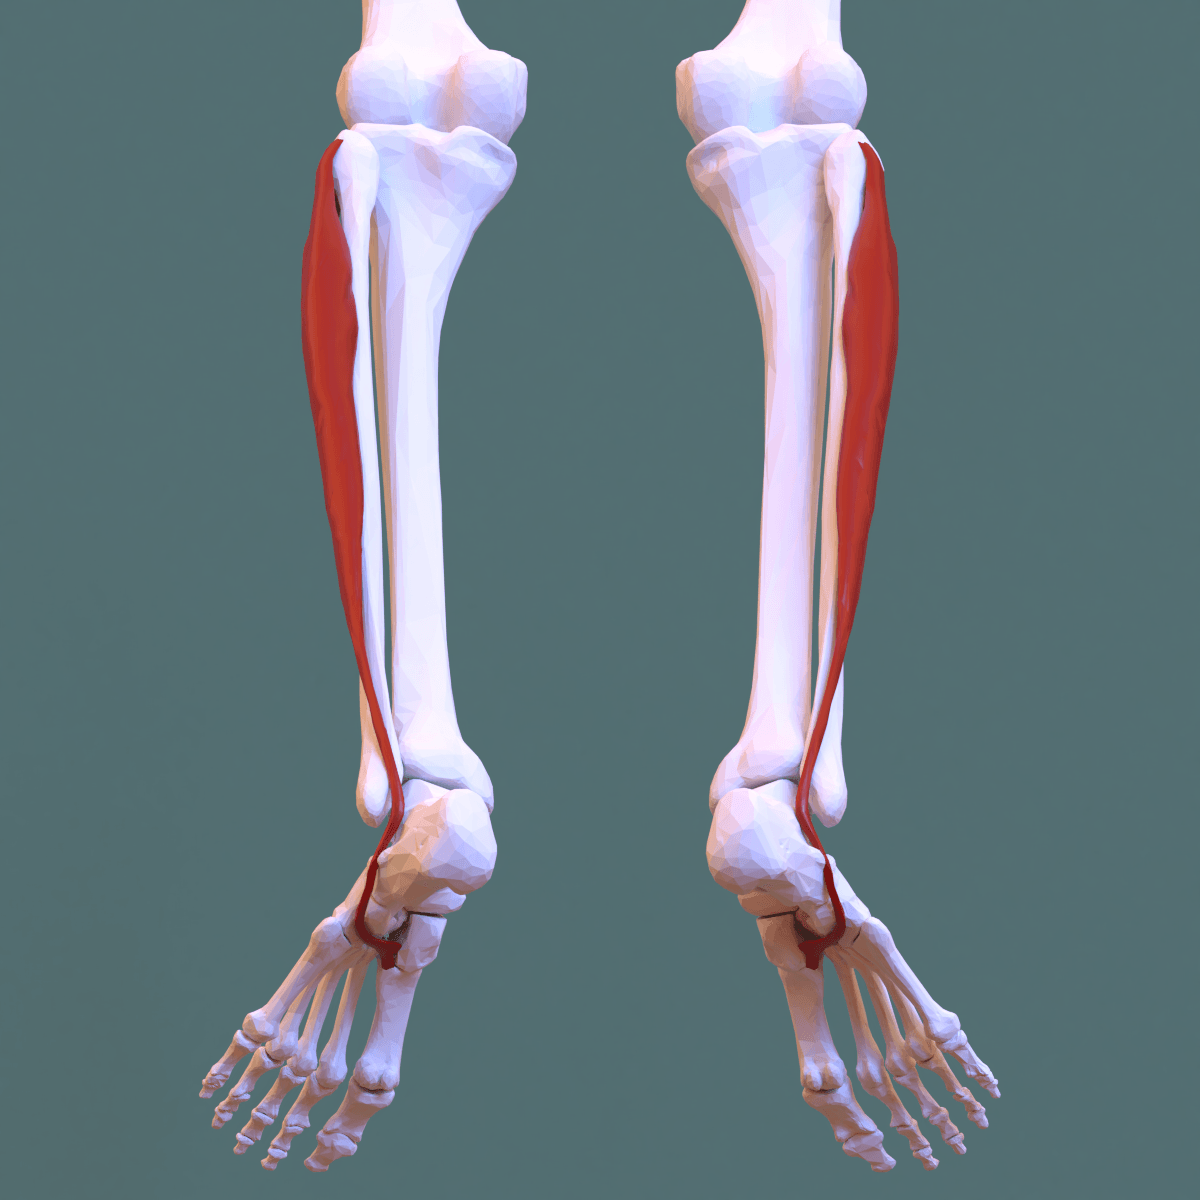
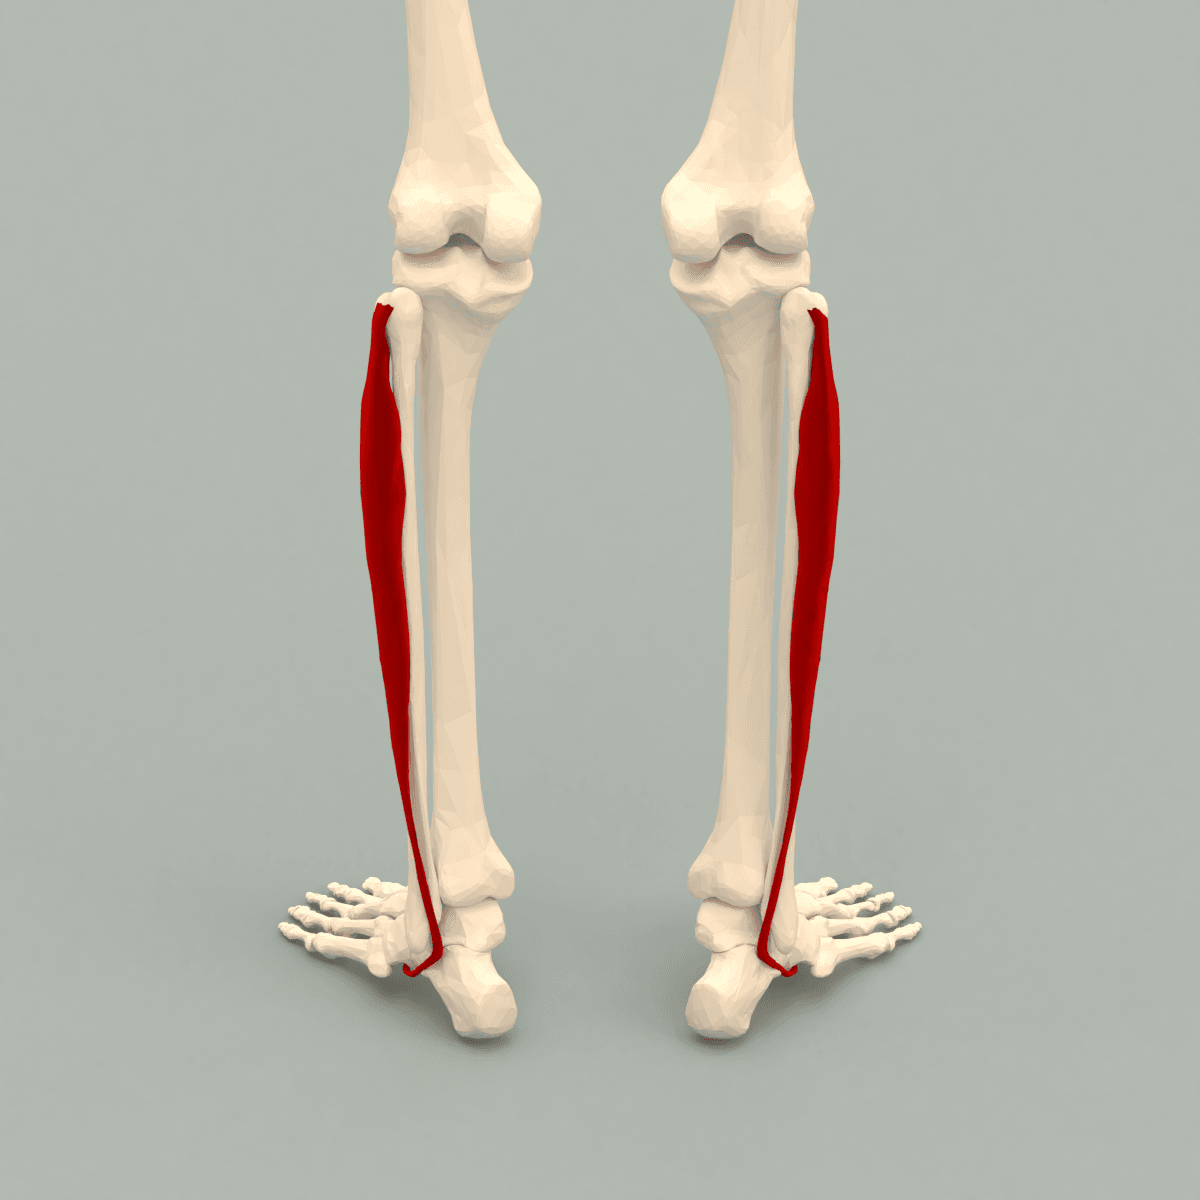
Peroneus longus (fibularis longus) is the longer, more superficial and more proximally arising of the two muscles of the lateral (peroneal) compartment. Its tendon has the longest and most convoluted course of any tendon in the lower limb, from behind the lateral malleolus, around the cuboid and across the entire sole to the base of the first metatarsal.
Two functions. That course gives it eversion at the hindfoot and plantarflexion of the first ray at the forefoot, and the second dominates its clinical importance. Peroneus longus is the only muscle that plantarflexes the first ray. When it acts unopposed, because tibialis anterior (the first ray dorsiflexor) has weakened, it drives the first metatarsal into plantarflexion and sets off the chain that ends in a cavovarus foot, which is why examiners return to this muscle so often.
In Charcot-Marie-Tooth disease and other length-dependent motor neuropathies the deformity is entirely predictable because of which muscles fail first:
- Tibialis anterior weakens early, and loses the fight to resist plantarflexion of the first ray.
- Peroneus longus stays strong, and its unopposed plantarflexion of the first ray gives forefoot cavus.
- Peroneus brevis weakens early, and loses the fight against inversion.
- Tibialis posterior stays strong, and its unopposed inversion gives hindfoot varus.
Each strong muscle overpowers its own antagonist, and the two deformities compound. The plantarflexed first ray produces a compensatory hindfoot varus (the chain is set out under Action and Biomechanics), while the unopposed tibialis posterior actively drives the hindfoot into varus as well.
Attachments, Innervation and Relations
Origin. The muscle arises from the head and upper two-thirds of the lateral surface of the fibula, a small slip from the lateral condyle of the tibia, the anterior and posterior intermuscular septa and the deep fascia of the leg. Between its two fibular attachments is a gap through which the common peroneal nerve passes, so the nerve runs through the substance of the muscle at the fibular neck and divides there into the deep and superficial peroneal nerves.
Course. The longest tendon course in the lower limb runs in five stages:
- Behind the lateral malleolus it lies superficial and posterior to peroneus brevis. The two tendons share a common synovial sheath in the retromalleolar groove, held by the superior peroneal retinaculum.
- It passes inferior to the peroneal tubercle of the calcaneus (brevis passes superior to it), beneath the inferior peroneal retinaculum, where the tendons acquire separate sheaths.
- It turns sharply plantarwards around the lateral border of the cuboid into the cuboid tunnel (the peroneal groove of the cuboid), roofed by the long plantar ligament.
- It crosses the sole obliquely from lateral to medial, deep to the plantar structures and superficial to the plantar aspect of the cuneiforms.
- It inserts on the plantar-lateral base of the first metatarsal and the plantar-lateral aspect of the medial cuneiform, with a variable slip to the base of the second metatarsal.
The os peroneum. A sesamoid lies within the tendon at the level of the cuboid. It is cartilaginous in everyone and ossified in roughly 5 to 25 per cent of feet, depending on the imaging series, and bipartite or multipartite in a minority. It acts as a pulley protecting the tendon at its point of sharpest angulation; its radiographic value is set out under Clinical Relevance.
The retinacula. The superior peroneal retinaculum runs from the posterolateral ridge of the distal fibula to the lateral calcaneus and the deep fascia, and is the primary restraint against peroneal tendon dislocation. The inferior peroneal retinaculum is continuous with the inferior extensor retinaculum and attaches to the peroneal tubercle, separating the two tendons.
The retromalleolar groove. The groove on the posterior fibula is shallow, concave or occasionally convex, and is deepened by a fibrocartilaginous ridge. A flat or convex groove predisposes to subluxation.
Its fascial exit point varies widely, and it may pierce the fascia as two separate branches. Before any lateral ankle incision, arthroscopic portal or fasciotomy, identify it by plantarflexing and inverting the foot with the fourth toe held in flexion, which tents the nerve visibly beneath the skin in most patients, and mark it. Do not rely on an average distance.
Action and Biomechanics
Eversion. Peroneus longus everts (pronates) the foot at the subtalar and transverse tarsal joints, the primary action it shares with peroneus brevis. Because the tendon passes posterior to the ankle axis with only a small moment arm, it is also a weak ankle plantarflexor.
Plantarflexion of the first ray. This action is unique to peroneus longus, and it is the one that matters clinically. By pulling the first metatarsal base plantarwards and laterally, the muscle depresses the first metatarsal head.
Arch support. It maintains the transverse and lateral longitudinal arches. Pulling the first metatarsal base toward the cuboid approximates the medial and lateral columns and stabilises the transverse arch at push-off. Acting as a plantar sling with tibialis posterior beneath the midfoot, it also stabilises the longitudinal arch.
- Peroneus longus
- Posterior and superficial
- Peroneus brevis
- Anterior and deep, against the bone
- Peroneus longus
- Passes inferior to it
- Peroneus brevis
- Passes superior to it
- Peroneus longus
- Plantar-lateral base of the first metatarsal and medial cuneiform
- Peroneus brevis
- Styloid (tuberosity) of the base of the fifth metatarsal
- Peroneus longus
- Eversion plus plantarflexion of the first ray
- Peroneus brevis
- Eversion - the stronger and more efficient evertor of the hindfoot
- Peroneus longus
- Smaller - it acts further from the subtalar axis distally
- Peroneus brevis
- Larger - a more direct evertor
- Peroneus longus
- Rupture at the cuboid or fibular groove, painful os peroneum syndrome
- Peroneus brevis
- Longitudinal split tear in the fibular groove
- Peroneus longus
- Remains strong - the deforming plantarflexor of the first ray
- Peroneus brevis
- Weakens early - loses the fight against tibialis posterior
- Peroneus longus
- Tenodesed to brevis in cavovarus; occasionally transferred
- Peroneus brevis
- Harvested for lateral ligament reconstruction (Chrisman-Snook, Evans)
The windlass. At terminal stance the great toe dorsiflexes at the metatarsophalangeal joint, tightening the plantar fascia and raising the arch. For the windlass mechanism to work the first metatarsal head must be firmly loaded against the ground, and peroneus longus supplies that load: it plantarflexes the first ray at exactly the moment the windlass engages, stabilising the medial column so that push-off occurs through a rigid tripod.
Too little. Without peroneus longus, after a rupture or a peroneus longus to brevis tenodesis, the first ray dorsiflexes under load. The resulting hypermobile first ray transfers load to the second metatarsal, causing transfer metatarsalgia and occasionally a second metatarsal stress fracture. This is a genuine and underappreciated complication of tenodesis, and one candidates should be able to name.
Too much. Unopposed peroneus longus in cavovarus drives the first ray plantarwards and sets off the chain below.
This is the single most tested biomechanical chain in cavovarus.
- Peroneus longus plantarflexes the first ray, so the first metatarsal head sits lower than the fifth.
- To get the lateral border of the foot to the ground, the whole forefoot must pronate relative to the hindfoot: a plantarflexed first ray with forefoot valgus.
- The hindfoot then supinates (goes into varus) to accommodate the pronated forefoot and keep the foot plantigrade. This is a compensatory, initially flexible hindfoot varus.
- Over time the deltoid and medial soft tissues contract, the subtalar joint stiffens, and the varus becomes fixed.
The Coleman block test interrogates step 3. Stand the patient with a 2.5 to 4 cm block under the heel and the lateral border of the foot, leaving the first ray free to drop off the edge. With the first ray allowed to plantarflex into space, the forefoot no longer needs the hindfoot to supinate.
- If the hindfoot varus corrects, it is flexible and forefoot-driven. Treat the forefoot: a dorsiflexion (closing wedge) osteotomy of the first metatarsal base and/or a peroneus longus to brevis tenodesis, with plantar fascia release as required.
- If the hindfoot varus does not correct, it is fixed. A lateralising calcaneal osteotomy (Dwyer or lateral closing wedge, or lateral translational) is required in addition, and in a rigid arthritic hindfoot a triple arthrodesis.
Surface Anatomy and Examination
Palpation. The muscle belly is palpable along the lateral leg over the upper two-thirds of the fibula. The tendon can be felt behind the lateral malleolus and traced forward below the peroneal tubercle, a small palpable prominence on the lateral wall of the calcaneus roughly 1 to 2 cm distal and anterior to the fibular tip. The insertion, deep in the sole, cannot be palpated.
Isolating peroneus longus. Stabilise the hindfoot, push up under the first metatarsal head and ask the patient to press down. Resisted first ray plantarflexion is the only clinical test that specifically loads peroneus longus rather than the evertors as a group.
- How to perform
- Stand on a block placed under the heel and lateral border, first ray hanging free
- Positive finding
- Hindfoot varus corrects to neutral or valgus
- What it means
- Flexible, forefoot-driven hindfoot varus - treat the first ray
- False positives
- A rigid hindfoot from subtalar coalition or arthritis will not correct regardless of the forefoot
- How to perform
- Stabilise the hindfoot; ask the patient to press the first metatarsal head down against the examiner thumb
- Positive finding
- Weakness or pain
- What it means
- Peroneus longus dysfunction, tear or rupture
- False positives
- Hallux rigidus or first MTP pain inhibits the effort
- How to perform
- Foot plantarflexed and everted against resistance
- Positive finding
- Weakness or pain along the peroneal tendons
- What it means
- Peroneal tendon pathology or superficial peroneal nerve lesion
- False positives
- Ankle instability, lateral ligament pain
- How to perform
- Ask for active dorsiflexion and eversion from a plantarflexed inverted position, with the examiner palpating behind the fibula
- Positive finding
- Palpable or visible snap of the tendons over the fibula
- What it means
- Peroneal tendon subluxation or dislocation with an incompetent SPR
- False positives
- Voluntary subluxation in a hypermobile patient - ask specifically
- How to perform
- Palpate the plantar-lateral midfoot at the cuboid
- Positive finding
- Focal tenderness with pain on resisted first ray plantarflexion
- What it means
- Painful os peroneum syndrome
- False positives
- Cuboid syndrome, peroneal tubercle hypertrophy, calcaneocuboid arthritis
- How to perform
- Passive dorsiflexion with knee extended then flexed, hindfoot neutral
- Positive finding
- Improvement with knee flexed
- What it means
- Gastrocnemius contracture
- False positives
- Midfoot substitution if the hindfoot is not locked
- How to perform
- Look at the standing patient from the front
- Positive finding
- The medial heel pad is visible medial to the medial border of the foot
- What it means
- Subtle hindfoot varus - an early sign of cavovarus
- False positives
- Requires a careful, unhurried look; easily missed in a rushed examination
Assessing a cavovarus foot
Never correct a cavovarus foot without answering three questions. Look first for the peek-a-boo heel from the front and at hindfoot alignment from behind.
Why is it cavovarus? A cavovarus foot in a young patient is a neurological diagnosis until proven otherwise. Around two-thirds of cases have an identifiable neurological cause, most commonly Charcot-Marie-Tooth disease. Examine the hands, the reflexes, the family and the spine: look for intrinsic wasting, clawing, areflexia and hand involvement, examine the parents, and consider nerve conduction studies and genetic testing. If the deformity is unilateral, progressive or of recent onset, obtain a spinal MRI to exclude a tethered cord, syrinx, diastematomyelia or an intraspinal tumour.
Is the hindfoot flexible? The Coleman block test decides whether the calcaneus needs an osteotomy: a flexible hindfoot needs forefoot surgery, a fixed one needs a lateralising calcaneal osteotomy added, and a rigid, arthritic hindfoot needs arthrodesis.
Is the Achilles tight? Perform the Silfverskiold test in every case. Gastrocnemius contracture is present in most cavovarus feet and must be corrected, because failing to correct it guarantees recurrence and a failed transfer.
Radiographs. Weightbearing anteroposterior and lateral foot views show:
- An increased Meary angle (talus-first metatarsal, apex dorsal)
- An increased calcaneal pitch (greater than about 30 degrees)
- A positive Hibbs angle
- A bell-shaped or hourglass sinus tarsi
- On the lateral view, overlap of the metatarsals with the first metatarsal appearing more plantar, which confirms the plantarflexed first ray
Complications
- Mechanism
- Lateral leg incision or arthroscopy portal crossing the fascial exit point 10 to 12 cm above the malleolus
- Prevention
- Mark the nerve pre-operatively by plantarflexing and inverting with the fourth toe flexed; longitudinal incisions
- Management
- Desensitisation; neuroma excision and burial in muscle if refractory
- Mechanism
- Lateral hindfoot incision or calcaneal osteotomy
- Prevention
- Full-thickness incision to bone, subperiosteal retractors, and know that the nerve lies roughly a centimetre and a half posteroinferior to the fibular tip
- Management
- Neuroma excision and burial if a painful neuroma develops
- Mechanism
- Proximal fibular surgery - the nerve divides within peroneus longus
- Prevention
- Identify and trace the nerve through the muscle before any proximal fibular osteotomy
- Management
- Explore and repair if sharply divided; AFO and later tendon transfer if permanent
- Mechanism
- Loss of first ray plantarflexion produces a dorsiflexed hypermobile first ray
- Prevention
- Anticipate it; in a non-cavus foot consider repair rather than tenodesis
- Management
- Metatarsal pad and orthosis; plantarflexion osteotomy of the first ray if severe
- Mechanism
- Retinacular repair without addressing a shallow groove or hindfoot varus
- Prevention
- Deepen the fibular groove where it is flat or convex; correct hindfoot varus
- Management
- Revision with groove deepening and, if needed, a bone block or retinacular reconstruction
- Mechanism
- Uncorrected gastrocnemius contracture, unaddressed hindfoot varus, or progressive neuropathy
- Prevention
- Silfverskiold test; intra-operative reassessment against a flat plate; counsel about progression in CMT
- Management
- Revision with the omitted procedure; arthrodesis when the deformity is rigid
- Mechanism
- Excessive lateralising calcaneal osteotomy or excessive tenodesis tension
- Prevention
- Assess intra-operatively with the foot loaded; tension the tenodesis in neutral to slight eversion
- Management
- Revision osteotomy; orthotic management
- Mechanism
- Tenodesing to a peroneus brevis that is itself torn
- Prevention
- Inspect the brevis directly - split tears are common and easy to miss
- Management
- Convert to an FDL or FHL transfer to the fifth metatarsal base, or a staged graft reconstruction
- Mechanism
- Prolonged immobilisation in a scarred sheath
- Prevention
- Early protected motion in a boot; meticulous sheath handling
- Management
- Tenolysis
- Mechanism
- Treating cavovarus as an idiopathic mechanical problem
- Prevention
- Full neurological examination, family history, nerve conduction studies, spinal MRI if unilateral or progressive
- Management
- Refer to neurology and genetics; counsel about progression before operating
Clinical Relevance
Peroneus longus tears and rupture
Where and how it presents. Tears occur at the two watershed zones, which are also the zones of high friction. The patient has lateral or plantar-lateral foot pain, weak eversion, and specifically weakness or pain on resisted first ray plantarflexion. A chronic rupture presents with a progressive dorsiflexed first ray and can precipitate a cavus-to-planus change or transfer metatarsalgia.
The radiograph. On an oblique foot radiograph, proximal migration of an ossified os peroneum is pathognomonic of a peroneus longus rupture distal to the sesamoid. Diastasis of a bipartite or multipartite os peroneum suggests a fracture or an interposed tear.
MRI and associations. Longitudinal splits appear as a C-shaped or bisected tendon on axial images, and fluid in the sheath out of proportion to the other tendon suggests tenosynovitis. A hypertrophied peroneal tubercle, present in a minority of calcanei and more prominent in cavovarus, causes attritional wear as the tendon rides over it.
Painful os peroneum syndrome (POPS)
Sobel and colleagues described a spectrum encompassing:
- Acute os peroneum fracture, or diastasis of a multipartite ossicle
- Chronic os peroneum fracture with a callus and stenosing tenosynovitis
- Attrition or partial rupture of peroneus longus proximal or distal to the ossicle
- Frank rupture with proximal ossicle migration
- A hypertrophied peroneal tubercle entrapping the tendon
It presents as plantar-lateral midfoot pain, worse on resisted first ray plantarflexion and on inversion stretch. Immobilisation and orthoses come first. Surgery involves excision of the ossicle with tendon repair or, if the tendon is irreparable, tenodesis of peroneus longus to peroneus brevis proximally.
Peroneal tendon subluxation and dislocation
Mechanism. A forceful dorsiflexion with sudden reflex contraction of the peroneals, classically a skiing injury with the ski tip catching, or a football or basketball injury. It is frequently misdiagnosed as a lateral ankle sprain.
Pathoanatomy. The superior peroneal retinaculum is avulsed or stripped from the posterolateral fibula, often lifting a periosteal sleeve with a thin rim of cortical bone. That rim is the fleck sign on an anteroposterior ankle radiograph, and it is diagnostic.
Eckert and Davis classification grades the plane of failure:
- Grade I: the retinaculum is elevated from the lateral malleolus, with the tendons lying between bone and periosteum.
- Grade II: the fibrocartilaginous ridge is elevated with the retinaculum.
- Grade III: a cortical avulsion fragment is displaced with the retinaculum (the fleck sign).
- Grade IV, added in some descriptions: the retinaculum is avulsed from its posterior attachment.
Predisposing factors. A shallow, flat or convex retromalleolar groove, a low-lying peroneus brevis muscle belly, an accessory peroneus quartus muscle (present in roughly 10 to 20 per cent of feet), retinacular laxity and hindfoot varus.
Treatment. Acute injuries in low-demand patients may be treated in a cast in slight plantarflexion and inversion for six weeks, but recurrence is common and most athletes are treated surgically. Surgery comprises superior peroneal retinaculum repair or reconstruction, combined with fibular groove deepening where the groove is shallow, and correction of hindfoot varus where present.
Peroneal tendinopathy and tenosynovitis
Overuse pain along the tendons behind and below the lateral malleolus is worse with activity on uneven ground. Always look for the underlying cause: hindfoot varus, a lateral ligament-deficient ankle, a hypertrophied peroneal tubercle, a low-lying brevis belly or a peroneus quartus. Treating the tendinopathy without correcting hindfoot varus guarantees recurrence.
Lateral compartment syndrome
It is rare compared with anterior compartment syndrome, and usually seen as part of a four-compartment leg injury. The signs are pain on passive inversion, tenderness over the lateral compartment, and numbness on the dorsum of the foot sparing the first web space (superficial peroneal territory). The release is described under Surgical Relevance.
Superficial peroneal nerve entrapment
The nerve is entrapped where it pierces the deep fascia, causing exercise-related lateral leg pain with dorsal foot paraesthesia and no motor loss. There is a recognised association with chronic exertional lateral compartment syndrome, and with a fascial defect and muscle herniation at the exit point. The diagnosis is clinical, with a Tinel sign at the exit point and reproduction on resisted dorsiflexion-eversion or passive plantarflexion-inversion; a diagnostic local anaesthetic block is confirmatory.
Surgical Relevance
Approaches and intervals
Lateral approach to the fibula and ankle. The peroneal tendons lie posterior to the fibula, with the sural nerve behind and below the fibular tip.
Posterolateral approach to the distal tibia. The interval lies between the peroneals (peroneus longus and brevis, lateral compartment) and soleus and flexor hallucis longus (posterior), reaching the posterior tibial surface. The peroneal artery lies deep in this interval.
Proximal fibular exposure and fibular head resection. Because the common peroneal nerve divides within peroneus longus, the nerve must be identified proximal to the muscle and traced through it before any osteotomy or resection. This is the highest-risk nerve exposure in the leg.
Lateral ankle arthroscopy. The anterolateral portal risks the intermediate dorsal cutaneous branch of the superficial peroneal nerve, so transilluminate and mark the nerve first.
Lateral compartment fasciotomy. Through an anterolateral incision 2 cm lateral to the tibial crest, the same incision used for the anterior compartment, identify the anterior intermuscular septum and open the lateral compartment posterior to it. The superficial peroneal nerve lies within the compartment, so direct the fasciotomy posterior and distal with care.
Peroneus longus to peroneus brevis tenodesis
This is the operation examiners ask about, and the reasoning behind it matters more than the technique. It is indicated for:
- Cavovarus reconstruction, to remove the plantarflexion force on the first ray and augment weak eversion
- An irreparable peroneus longus tear with an intact brevis
- Painful os peroneum syndrome where the tendon cannot be repaired
Technique. Through a lateral incision behind and below the fibula, expose both tendons in the common sheath. Divide peroneus longus proximal to the diseased or deforming segment and suture its proximal stump side-to-side to peroneus brevis, with the foot in neutral to slight eversion and appropriate tension, using two or three non-absorbable mattress sutures over a 2 to 3 cm overlap. Excise the distal longus segment, or leave it if it is not symptomatic.
Effect. The power of peroneus longus is redirected into eversion through the brevis insertion at the fifth metatarsal base, and its plantarflexing effect on the first ray is abolished. Correcting cavovarus means weakening the strong side and augmenting the weak, and this is why the tenodesis is a standard component of cavovarus reconstruction: it addresses both halves of the problem with one manoeuvre.
Prerequisite. The peroneus brevis must be intact and functional. If both tendons are diseased, tenodesis is not an option. A flexor digitorum longus or flexor hallucis longus transfer to the base of the fifth metatarsal restores eversion using a functioning muscle from the deep posterior compartment. Where both tendons are irreparable with substantial scarring, a staged reconstruction places a silicone rod in the peroneal sheath to create a pseudosheath, followed at three months by an allograft or hamstring autograft reconstruction.
Counselling. Loss of first ray plantarflexion leaves the hypermobile or dorsiflexed first ray and transfer metatarsalgia described under the windlass. In a foot that is not cavus this is a genuine downside; in a cavovarus foot it is the therapeutic aim.
Peroneus longus as a graft. The longus tendon is occasionally harvested as an autograft, for example in ligament reconstruction elsewhere, precisely because tenodesing the residual stump to brevis preserves eversion and losing first ray plantarflexion is generally tolerated. Counsel about the hypermobile first ray.
Cavovarus reconstruction - where peroneus longus fits
A logical order of correction:
- Plantar fascia release (Steindler) releases the tight plantar structures and allows the arch to descend. It is performed through a medial incision at the plantar-medial heel, protecting the medial calcaneal nerve and Baxter nerve (the first branch of the lateral plantar nerve).
- Peroneus longus to peroneus brevis tenodesis abolishes first ray plantarflexion and augments eversion.
- Dorsiflexion (dorsal closing wedge) osteotomy of the first metatarsal base is the bony correction of the plantarflexed first ray. It is made about 1 to 1.5 cm distal to the tarsometatarsal joint, removing a dorsal wedge and hinging on the plantar cortex.
- Recheck the Coleman block test intra-operatively by loading the foot against a flat plate. If hindfoot varus persists, add a lateralising calcaneal osteotomy (Dwyer lateral closing wedge, a lateral translational osteotomy, or a combined translation and Dwyer).
- Tibialis posterior transfer through the interosseous membrane if there is a drop foot, or a split transfer if it is the deforming muscle.
- Gastrocnemius recession or tendo-Achilles lengthening per the Silfverskiold test, almost always required.
- Claw toe correction: a Jones procedure for the hallux (extensor hallucis longus transfer to the first metatarsal neck with interphalangeal fusion), and a Hibbs procedure or flexor-to-extensor transfers for the lesser toes.
- Lateral ligament reconstruction if there is associated instability, which usually accompanies cavovarus.
- Triple arthrodesis as salvage for a rigid, arthritic hindfoot, where it realigns and stabilises the foot and tendon balancing becomes secondary.
Guidelines, Registries & Global Practice
Anatomical variation across populations
- Os peroneum ossification is reported in roughly 5 to 25 per cent of feet, with the wide range reflecting differences in imaging modality and population. It is bilateral in the majority when present, and multipartite in a minority - a fact that matters when interpreting a suspected fracture.
- Peroneus quartus is an accessory muscle present in approximately 10 to 20 per cent of feet in cadaveric series, usually arising from peroneus brevis and inserting on the retrotrochlear eminence of the calcaneus. It crowds the retromalleolar groove and is associated with brevis tears and subluxation.
- Retromalleolar groove morphology varies widely: concave in the majority, but flat or even convex in a significant minority - the anatomical substrate for peroneal tendon instability.
- Superficial peroneal nerve course is highly variable, including bifurcation proximal to the fascial exit and an anterior compartment course in a minority.
- Peroneal tubercle size varies substantially and hypertrophy is more common in cavovarus feet.
Side-by-side guidance
- Position relevant to peroneus longus
- Support a trial of orthoses and physiotherapy for peroneal tendinopathy and for symptomatic cavovarus before surgery; emphasise identifying and correcting underlying hindfoot malalignment.
- Position relevant to peroneus longus
- Emphasise a full neurological workup in any cavovarus foot, including consideration of spinal imaging in unilateral or progressive deformity, before reconstructive surgery.
- Position relevant to peroneus longus
- Highlights the superficial peroneal nerve at the fascial exit point and the sural nerve at the lateral hindfoot as the two nerves most at risk in lateral approaches.
- Position relevant to peroneus longus
- Recommend joint neurology and orthopaedic management, genetic confirmation where available, and counselling that reconstruction of a progressive neuropathic foot aims for a plantigrade braceable foot rather than a permanent correction.
- Position relevant to peroneus longus
- Favour operative repair of acute peroneal tendon dislocation in athletes because of high recurrence with non-operative management, with groove deepening where morphology is unfavourable.
Resource-dependent practice
- Well-resourced settings: MRI to characterise tendon tears and groove morphology, nerve conduction studies and genetic testing for CMT, weightbearing CT for three-dimensional deformity assessment.
- Limited-resource settings: the Coleman block test, the peek-a-boo heel sign, the Silfverskiold test and a careful neurological examination cost nothing and answer almost every question needed to plan cavovarus surgery. Weightbearing radiographs suffice for surgical planning. Plantar fascia release, peroneus longus to brevis tenodesis, first metatarsal dorsiflexion osteotomy and a Dwyer calcaneal osteotomy all require only basic instruments and are fully deliverable at district hospital level.
- Peroneal tendon surgery requires no implants beyond suture and anchors, and groove deepening can be performed with an osteotome and impactor.
Registry and outcome signals
- There is no registry for peroneal tendon or cavovarus surgery. Cohort series consistently report that failure of cavovarus reconstruction is due to under-correction, unaddressed equinus, and progression of the underlying neuropathy, rather than to failure of the tendon work itself.
- Series of peroneal tendon dislocation consistently report a high recurrence rate with non-operative treatment in athletes and reliable results with retinacular repair combined with groove deepening.
MCQ Practice Points
Q: Where does peroneus longus insert? A: The plantar-lateral base of the first metatarsal and the plantar-lateral aspect of the medial cuneiform, after crossing the sole obliquely through the cuboid tunnel.
Q: What action is unique to peroneus longus? A: Plantarflexion of the first ray. No other muscle plantarflexes the first metatarsal, which is why its unopposed action drives forefoot cavus.
Q: What is the nerve supply of the lateral compartment? A: The superficial peroneal nerve, roots L5 and S1, which arises within the substance of peroneus longus at the fibular neck.
Q: Where does the superficial peroneal nerve pierce the deep fascia? A: Approximately 10 to 12 cm proximal to the tip of the lateral malleolus, though the range is wide. Identify it by plantarflexing and inverting the foot with the fourth toe flexed.
Q: What does proximal migration of the os peroneum mean? A: Rupture of the peroneus longus tendon distal to the ossicle. It is a diagnostic radiographic sign.
Q: What does a positive Coleman block test indicate? A: The hindfoot varus is flexible and forefoot-driven. Treat the first ray with a dorsiflexion osteotomy and a peroneus longus to brevis tenodesis; a calcaneal osteotomy is not required.
Q: Which tendon passes above and which below the peroneal tubercle? A: Brevis above, longus below. Peroneus brevis is superior; peroneus longus is inferior.
Q: Which peroneal tendon lies against the fibula in the retromalleolar groove? A: Peroneus brevis (anterior and deep). Peroneus longus lies posterior and superficial. This is why brevis develops longitudinal splits.
Q: Which artery runs in the lateral compartment of the leg? A: None. The lateral compartment contains no named artery; its supply comes from perforating branches of the peroneal artery, which itself lies in the deep posterior compartment.
Q: What should you warn a patient about after a peroneus longus to brevis tenodesis? A: Loss of active first ray plantarflexion, producing a hypermobile or dorsiflexed first ray with transfer load to the second metatarsal and possible transfer metatarsalgia.
Q: Which four muscles determine the classic Charcot-Marie-Tooth cavovarus foot? A: Strong peroneus longus and tibialis posterior; weak tibialis anterior and peroneus brevis. Each strong muscle overpowers its own antagonist.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 16-year-old girl is referred with recurrent ankle sprains and a high-arched foot bilaterally. From the front you can see the medial heel pad on both sides. She has clawing of all toes and cannot heel-walk well. Her father has similar feet. Take me through your assessment and management.”
“A 28-year-old skier caught a tip and felt a sudden painful snap behind the outside of the ankle. She was diagnosed with a lateral ankle sprain. Six weeks on she has recurrent painful snapping behind the lateral malleolus when she pushes off. Radiographs taken at the time show a small flake of bone lateral to the distal fibula. What is the diagnosis and how do you manage it?”
“A 47-year-old man has three months of plantar-lateral midfoot pain after an inversion injury. He is tender over the cuboid. An oblique foot radiograph shows a small ossicle lateral to the cuboid, which the reporting radiologist has compared with a film from two years ago and noted has moved about 1.5 cm proximally. What is going on?”
Anatomy
- Origin: fibular head and upper two-thirds lateral fibula, lateral tibial condyle, intermuscular septa
- Insertion: plantar-lateral base of the first metatarsal and medial cuneiform
- Nerve: superficial peroneal, L5-S1, arising within the muscle at the fibular neck
- No named artery in the lateral compartment - supply from peroneal artery perforators
- Os peroneum within the tendon at the cuboid
Course
- Posterior and superficial to brevis in the retromalleolar groove
- Passes inferior to the peroneal tubercle (brevis superior)
- Cuboid tunnel, then obliquely across the sole
- Watershed zones at the fibula and at the cuboid
Function
- Eversion plus the only plantarflexion of the first ray
- Loads the first metatarsal head for the windlass at push-off
- Plantar sling with tibialis posterior supporting the transverse arch
- Unopposed action equals forefoot cavus
Cavovarus
- Strong: peroneus longus and tibialis posterior
- Weak: tibialis anterior and peroneus brevis
- Coleman block corrects = flexible, forefoot-driven
- Coleman block fails = add lateralising calcaneal osteotomy
- Neurological until proven otherwise - examine hands, reflexes, family, spine
Surgery
- SPN pierces fascia 10-12 cm above the lateral malleolus
- Sural nerve about 1.5 cm posteroinferior to the fibular tip
- Longus to brevis tenodesis needs an intact brevis
- Warn about transfer metatarsalgia after tenodesis
- Repair the SPR and deepen a flat groove in tendon dislocation
Evidence Base
A Simple Test for Hindfoot Flexibility in the Cavovarus Foot
- Described the lateral block test to determine whether hindfoot varus in a cavovarus foot is flexible or fixed
- The block supports the heel and lateral border while allowing the plantarflexed first ray to drop
- Correction of hindfoot varus indicates a forefoot-driven, flexible deformity
- Failure to correct indicates a fixed hindfoot requiring a calcaneal osteotomy or arthrodesis
Painful Os Peroneum Syndrome
- Coined the term and defined a five-part spectrum causing plantar-lateral foot pain
- Acute os peroneum fracture or diastasis of a multipartite ossicle causing discontinuity of the peroneus longus; chronic fracture or diastasis with callus causing stenosing tenosynovitis
- Attrition or partial rupture of the peroneus longus proximal or distal to the ossicle; and frank rupture with discontinuity
- A gigantic peroneal tubercle on the lateral calcaneus entrapping the peroneus longus or the os peroneum during tendon excursion
- Clinical diagnosis is facilitated by the single stance heel rise and the varus inversion stress test
The Dynamics of Peroneus Brevis Tendon Splits
- Investigation of the mechanism of peroneus brevis splits, with a technique of diagnosis and a proposed classification
- Concluded that splits result from a dynamic mechanical insult at the fibular groove, not from primary ischaemia
- Laxity of the superior peroneal retinaculum combined with mechanical compression by the peroneus longus causes the brevis to splay out and split over the sharp posterior edge of the fibula
- Named the contributing anatomical factors: a shallow or congenitally convex fibular groove, an anomalous low-lying peroneus brevis muscle belly, and a peroneus quartus tendon
Acute Rupture of the Peroneal Retinaculum
- 73 cases of injury to the superior peroneal retinaculum reviewed, in which three grades of injury were recognised
- Described the retinacular anatomy as a sheath distinct from a fibrous lip extending from the fibular periosteum at the lateral edge of the groove
- The grades describe the plane of failure: elevation of the retinaculum, elevation with the fibrocartilaginous ridge, and cortical avulsion
- Surgical repair was successful in all but three of the cases
Anatomical Variations in the Course of the Superficial Peroneal Nerve
- 85 legs in 44 cadavers dissected from the origin of the nerve to its terminal dorsal cutaneous branches
- In 62 legs (73%) the nerve ran wholly within the lateral compartment; in 12 (14%) it crossed into the anterior compartment; in 10 (12%) it divided in two with branches in BOTH compartments
- The nerve or its branches pierced the deep fascia anywhere from 3 to 18 cm proximal to the lateral malleolus
- The variability is wide enough that no fixed anatomical rule is safe
The Myth of Muscle Balance - Relative Strengths and Excursions of Normal Muscles About the Foot and Ankle
- Muscle fibre lengths and muscle weights below the knee were measured in the lower limbs of five cadavers to derive the relative strength and excursion of each muscle
- The plantarflexors of the ankle were found to be SIX times as strong as the dorsiflexors
- The authors discarded the concept of muscle balance in tendon transfer surgery and proposed that task appropriateness should be the guide
- Because muscle fibre length and excursion are constantly related, contracture is accompanied by decreased excursion - and tendon lengthening improves the deformity but does NOT improve the decreased active range of movement