Keasbey Tumour - Benign, Infiltrative, Recurrent, Never Metastatic
- A RARE BENIGN FIBROBLASTIC TUMOUR of children and adolescents, arising in the palmar and plantar aponeuroses and fascia of the hands, wrists, feet and ankles.
- Presents as a PAINLESS, SLOW-GROWING, FIRM, POORLY CIRCUMSCRIBED mass, typically 1 to 3 cm, fixed to fascia or tendon, only rarely limiting movement.
- The radiographic hallmark is FINE STIPPLED OR PUNCTATE CALCIFICATION within a soft-tissue mass - present in a proportion of cases, more often in older children, and effectively diagnostic when seen at this age in this site.
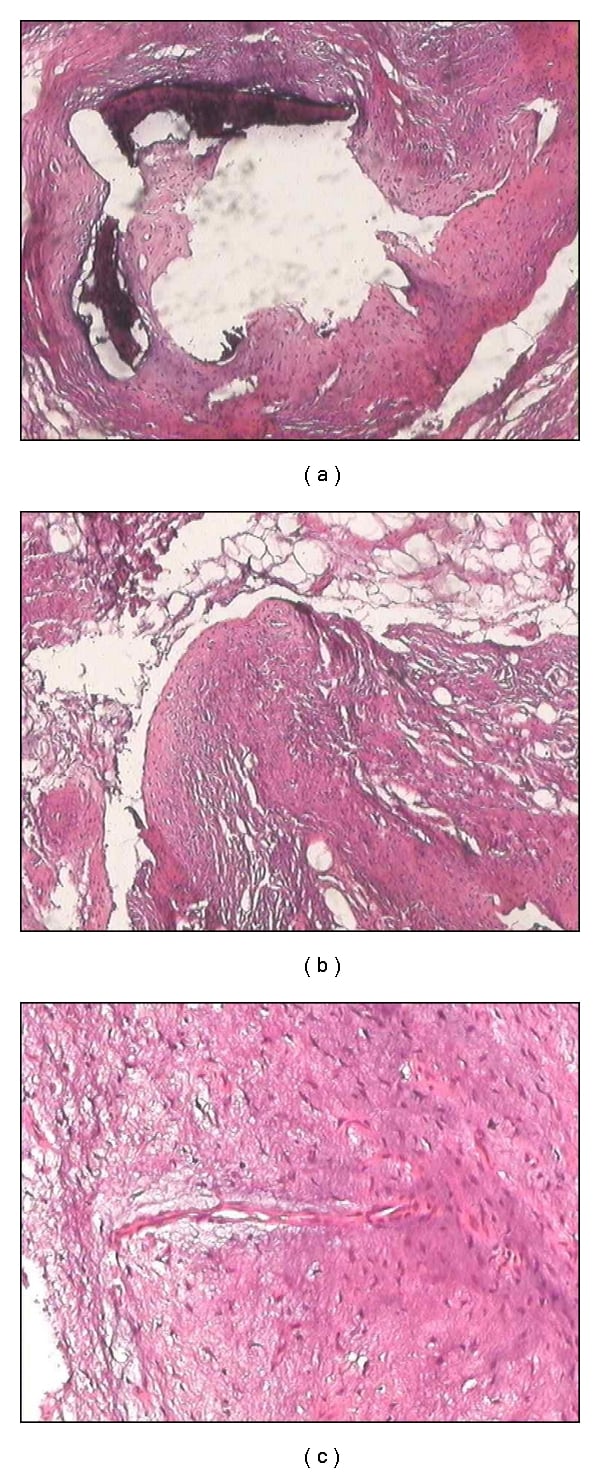
- Histology shows an INFILTRATIVE BLAND FIBROBLASTIC PROLIFERATION with characteristic CHONDROID NODULES containing central calcification and a PALISADE of rounded chondrocyte-like cells at their periphery. Recurrent FN1-EGF gene fusions have been described.
- Treatment is MARGINAL EXCISION. Local recurrence is high - commonly quoted around 50% - but there is NO METASTATIC POTENTIAL, so radical surgery, amputation and radiotherapy are NEVER justified.
- “The name tells you the diagnosis: CALCIFYING (stippled calcification), APONEUROTIC (arises in palmar and plantar fascia), FIBROMA (benign fibroblastic).
- “The younger the child, the less calcified and the more diffuse the lesion - and the more likely it is to recur.
- “Nuclear beta-catenin is NEGATIVE, which separates it from desmoid-type fibromatosis; TLE1 and an SS18 rearrangement separate synovial sarcoma.
- “Recurrence is not failure and not malignancy - counsel the family that a recurrence is re-excised, not escalated.
Overview
Calcifying aponeurotic fibroma (CAF) is a rare benign fibroblastic soft-tissue tumour arising in the aponeuroses and deep fascia of the distal extremities, characteristically in the palm, wrist, sole and ankle of children and adolescents. Keasbey described it in 1953 as juvenile aponeurotic fibroma, and it is still occasionally called Keasbey tumour.
It occupies a distinctive niche: benign histology, infiltrative growth, high local recurrence, and no metastatic potential whatsoever. The clinical challenge is therefore not oncological control but correct diagnosis and restrained surgery, because the two ways to harm a child with this lesion are to mistake it for a sarcoma and over-treat, or to mistake a sarcoma for it and under-treat.
Local aggressiveness is not malignancy. Examiners ask about this lesion precisely because it forces the candidate to separate the two, and conflating them is the commonest error. The lesion grows along fascial planes and around tendons and nerves rather than expanding as an encapsulated ball, so a "shelled out" specimen almost always leaves microscopic disease behind. That is why recurrence rates of around 50% are quoted, and why they are higher in younger children with more diffuse lesions.
Know where that number comes from before you quote it at a parent. The primary series behind it is Fetsch and Miettinen, in whom five of the ten patients with any follow-up recurred - a denominator of ten, not of the twenty-two reported - and figures across series range roughly from a third to two-thirds. "About half" is a convention that has held up across small series, not a measured rate, and the honest sentence is it comes back in roughly half of children.
It has no metastatic capacity. There are no convincing reports of metastasis. Rare reports of sarcomatous transformation exist in the literature but are anecdotal, contested, and should be treated with scepticism rather than used to justify aggressive treatment.
So the operation is a marginal excision, and a recurrence is re-excised, not escalated. Radical resection, amputation and radiotherapy have no place. Radiotherapy in particular is actively harmful in a growing child, carrying risks of growth arrest, contracture and secondary malignancy for a lesion that will never spread.
The mirror-image error is more dangerous. In an adolescent with a hand or foot mass, synovial sarcoma and epithelioid sarcoma must be excluded. Both can present as a small, slow-growing, apparently innocuous mass, and synovial sarcoma calcifies in a substantial minority. Imaging before excision, and a planned biopsy where there is any doubt, is what prevents an unplanned excision of a sarcoma.
Aetiology and Epidemiology
How rare. It is an uncommon lesion even in specialist soft-tissue tumour practice, and most orthopaedic surgeons will see very few in a career.
Age. Children and adolescents, with the great majority presenting under 20 years, in two recognised patterns. Presentation in adults is described but distinctly uncommon, and should prompt particular care over the differential diagnosis.
- Under about 5 years: lesions tend to be more diffuse and infiltrative, with sparse or absent calcification. These are the ones most often misdiagnosed, most likely to recur, and the ones to keep under closer surveillance.
- Around 8 to 15 years: lesions tend to be more nodular and better defined, with more conspicuous calcification and well-formed chondroid nodules - the classic radiographic and histological appearance.
Sex and cause. A male predominance is consistently reported, in the order of 2 to 1. There is no known inherited predisposition, no association with a syndrome, and no established environmental or traumatic cause; trauma is frequently reported by families but is almost certainly coincidental.
Maturation with age is a recognised phenomenon: the older the child, the more calcified, more nodular and better circumscribed the lesion tends to be, which is why the radiographic appearance is age-dependent.
Where It Occurs
- Frequency
- The commonest site overall
- Comment
- Arises in the palmar aponeurosis and deep fascia; may involve the flexor tendon sheaths and encase digital nerves
- Frequency
- Common
- Comment
- Small, firm, fixed nodules; can limit flexion if the tendon sheath is involved
- Frequency
- Common - the second major site
- Comment
- Arises in the plantar aponeurosis; the key differential here is plantar fibromatosis in an older patient
- Frequency
- Uncommon - described as unusual sites in dedicated series
- Comment
- Diagnosis in an unusual site is harder and depends more heavily on histology and molecular findings
What drives it. The lesion is a clonal fibroblastic neoplasm, not a reactive or post-traumatic process. Recurrent FN1-EGF gene fusions join it to a small group of tumours characterised by fibronectin (FN1) fusions, a group that also includes some cartilaginous and fibro-osseous lesions with a tendency to matrix calcification. That is a satisfying molecular explanation for the chondroid, calcifying phenotype.
The chondroid nodules are best understood as metaplastic cartilaginous differentiation within a fibroblastic proliferation, with dystrophic calcification developing centrally in those nodules and progressive ossification occasionally seen.
The infiltrative growth along fascial planes is intrinsic to the lesion and is the biological basis of its recurrence rate. It is not a consequence of inadequate surgery, although inadequate surgery makes it worse.
Histopathology and Classification
Macroscopic Appearance
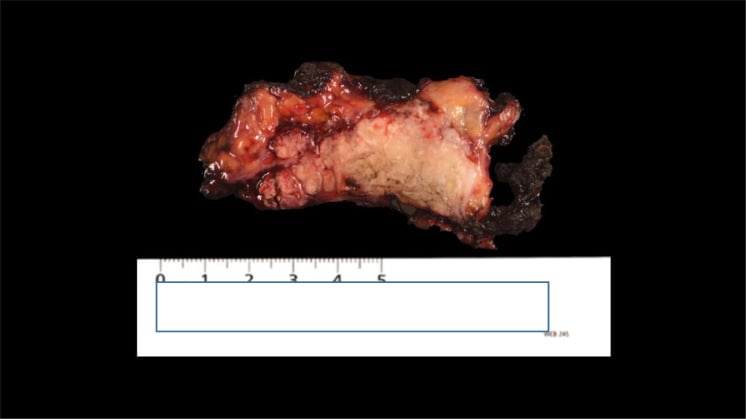
Gritty, grey-white and unencapsulated. The mass is firm to hard and poorly circumscribed, with no true capsule, blending into the surrounding fascia, fat and tendon, and gritty on cutting where calcification is present.
Microscopic Appearance - the Diagnostic Triad
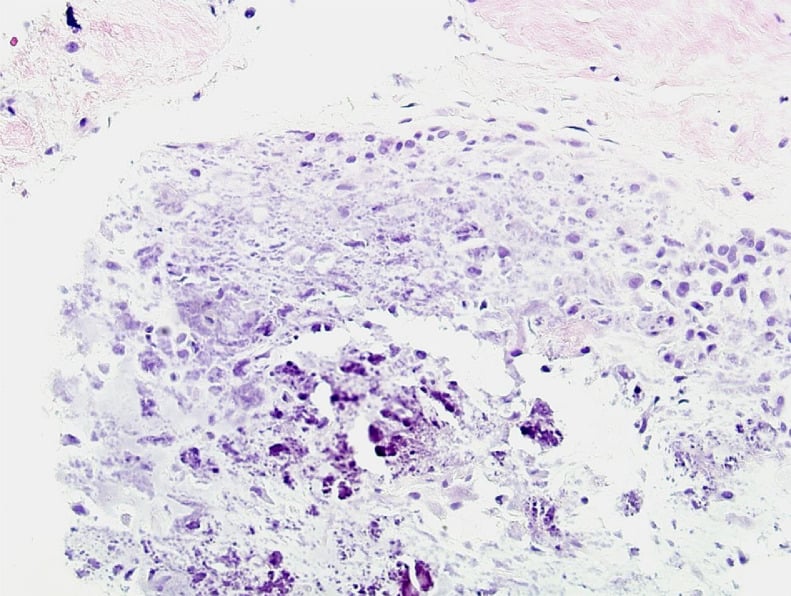
- An infiltrative, moderately cellular fibroblastic proliferation of bland spindle and stellate cells in a collagenous stroma, extending between fat lobules, along fascial septa and around tendons and nerves. The cells are cytologically bland - no significant pleomorphism, no atypia, and mitoses are rare and never atypical.
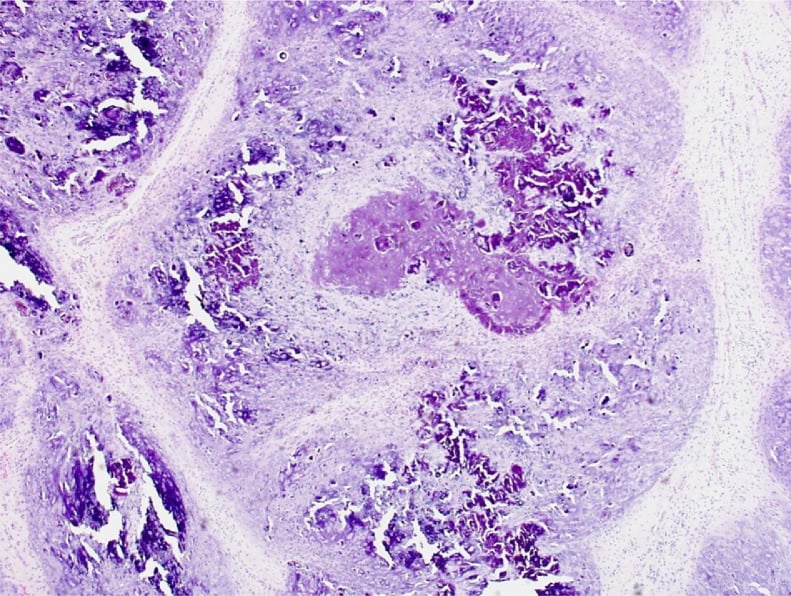
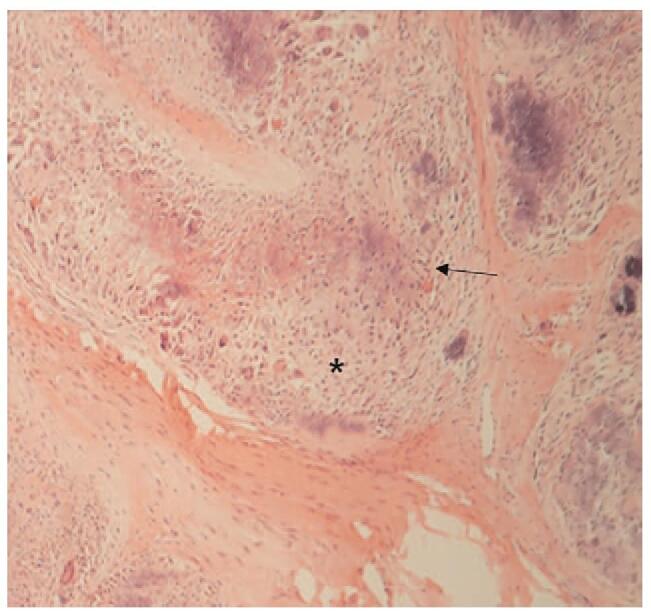
- Chondroid nodules - the diagnostic feature. Rounded nodules of cartilaginous or chondroid matrix containing central dystrophic calcification, sometimes progressing to ossification.
- Palisading of rounded, epithelioid, chondrocyte-like cells at the periphery of the calcified nodules - the cells line up radially around each nodule. This palisade is the single most characteristic microscopic feature.
Additional features. Osteoclast-like multinucleated giant cells may be scattered around the calcified foci. In very young children the lesion is often more diffuse, more cellular and less calcified, so the chondroid nodules may be few or absent - making the diagnosis considerably harder and increasing the chance of misdiagnosis as an infantile fibromatosis or fibrosarcoma.
What must not be there. No necrosis, no vascular invasion, no high-grade areas. Their presence means the diagnosis is wrong.
Immunohistochemistry
Morphology makes the diagnosis; the panel is read against the mimics.
- Smooth muscle actin (SMA): variable, often patchy positivity in the spindle cell component (myofibroblastic differentiation)
- S100: may be positive in the chondroid areas, reflecting cartilaginous differentiation - a trap if over-interpreted as a nerve sheath tumour
- Beta-catenin: no nuclear staining, which is the discriminator against desmoid-type fibromatosis, where nuclear accumulation is characteristic
- Cytokeratin, EMA and CD34: negative, helping exclude epithelioid sarcoma and some other mimics
- INI1 (SMARCB1): retained; loss is the hallmark of epithelioid sarcoma, a critical differential in the hand of an adolescent
- TLE1: negative; diffuse strong positivity supports synovial sarcoma
- Desmin and myogenin: negative, excluding rhabdomyosarcoma
Molecular Findings
- Recurrent FN1-EGF gene fusions have been described; where available, demonstration of an FN1 rearrangement supports the diagnosis in a histologically difficult or unusually sited case
- No SS18 (SYT) rearrangement - its presence indicates synovial sarcoma
- No CTNNB1 or APC alteration of the desmoid type
- No ETV6-NTRK3 fusion - its presence indicates infantile fibrosarcoma
The Differential Diagnosis
Learn it as a table. Age and site narrow it, the chondroid nodules with peripheral palisading settle it against the fibromatoses, and molecular testing rather than impression settles it against synovial sarcoma.
- Age and site
- Child or adolescent; palm, sole, wrist, ankle
- Key discriminating feature
- Chondroid nodules with central calcification and PERIPHERAL PALISADING of chondrocyte-like cells; bland infiltrative fibroblastic background
- Confirmatory test
- Histology; FN1-EGF fusion where available; beta-catenin nuclear NEGATIVE
- Age and site
- Adult, usually middle-aged or older; palm or sole
- Key discriminating feature
- Nodular myofibroblastic proliferation WITHOUT chondroid nodules or calcification; cords and contracture in the hand
- Confirmatory test
- Age and clinical pattern; histology
- Age and site
- Any age; usually deep, trunk and extremity
- Key discriminating feature
- Long sweeping fascicles of uniform fibroblasts, infiltrative, NO chondroid nodules
- Confirmatory test
- NUCLEAR BETA-CATENIN positive; CTNNB1 or APC alteration
- Age and site
- Infant, usually under 2 years; extremity
- Key discriminating feature
- Densely cellular, herringbone fascicles, brisk mitoses
- Confirmatory test
- ETV6-NTRK3 fusion
- Age and site
- Adolescent or young adult; near a joint, including the hand and foot
- Key discriminating feature
- Monophasic or biphasic spindle cell sarcoma; calcification in around a third; may look deceptively small and bland
- Confirmatory test
- TLE1 diffusely positive; SS18 (SYT) rearrangement - THE test
- Age and site
- Adolescent or young adult; HAND and forearm classically
- Key discriminating feature
- Multinodular epithelioid cells with central necrosis, mimicking a granulomatous process
- Confirmatory test
- LOSS of INI1 (SMARCB1); cytokeratin and EMA positive
- Age and site
- Infant; axilla, upper arm, trunk
- Key discriminating feature
- Triphasic - fibrous trabeculae, immature mesenchyme and mature fat; NO chondroid calcified nodules
- Confirmatory test
- Histology
- Age and site
- Adult; hands and feet
- Key discriminating feature
- Well circumscribed lobules of MATURE hyaline cartilage without a fibroblastic infiltrative component
- Confirmatory test
- Histology
- Age and site
- Any age, often a history of trauma
- Key discriminating feature
- ZONAL maturation with mature bone peripherally and immature centre - the reverse of a sarcoma
- Confirmatory test
- Radiograph pattern plus histology
- Age and site
- Any age; periarticular
- Key discriminating feature
- Amorphous calcified deposits with a foreign-body giant cell reaction, no fibroblastic tumour
- Confirmatory test
- Radiograph; calcium and phosphate metabolism
- Age and site
- Adult, occasionally adolescent; digits
- Key discriminating feature
- Mononuclear cells, osteoclast-like giant cells, haemosiderin and xanthoma cells; NO chondroid nodules
- Confirmatory test
- Histology; typical MRI low signal from haemosiderin
Classification
There is no staging and no grading system, because there is no malignant potential. The only variables that matter clinically are the age pattern set out above, the margin achieved, and whether function can be preserved.
- A marginal or wide excision makes residual microscopic disease less likely and carries the lower - though still real - recurrence risk, but never sacrifice a tendon, nerve or neurovascular bundle to obtain it
- An intralesional or piecemeal excision leaves microscopic and often macroscopic disease behind and a high recurrence risk; it is acceptable as a deliberate choice when a wider margin would cost function, and not acceptable as the result of poor planning
Clinical Presentation
The typical story. A painless, slowly enlarging, firm lump in the palm, sole, wrist or ankle of a child, often noticed incidentally by a parent or during an unrelated examination. Because it does not hurt, the duration before presentation is frequently months to years.
On examination it is firm to hard, poorly circumscribed and fixed to the underlying fascia or tendon, moving with that structure rather than independently of it, and the overlying skin is normal and freely mobile. Size at presentation is usually 1 to 3 cm; lesions larger than about 3 cm are less common and should raise the threshold for a formal diagnostic work-up.
Function is usually normal. Where the flexor tendon sheath is involved there may be mild loss of finger flexion or a sensation of tightness, but frank contracture is unusual. Multiple lesions in the same limb are described but uncommon.
Symptoms that should make you pause. Any of these shifts the emphasis toward excluding a sarcoma:
- Pain or rapid growth
- Size greater than about 5 cm
- A deep location beneath the fascia in an unusual site
- Neurological deficit
- A mass in an adolescent adjacent to a joint
Clinical Assessment
- What to do
- Duration, rate of growth, pain, prior trauma, prior surgery at the site, family history of tumours or syndromes
- What you are looking for
- A long history of painless slow growth supports a benign lesion; rapid growth or pain does not
- Pitfalls
- Families over-attribute the lump to a remembered injury; do not let that reassure you
- What to do
- Site, size in two dimensions, consistency, mobility relative to skin and to fascia, tenderness
- What you are looking for
- A firm, poorly defined mass fixed to fascia in the palm or sole of a child
- Pitfalls
- Estimating size by eye - measure and record it; a poorly defined edge is the norm here and is not itself sinister
- What to do
- Active and passive range of the adjacent joints and digits, grip and pinch in the hand, gait in the foot
- What you are looking for
- Usually normal; mild restriction if the tendon sheath is involved
- Pitfalls
- Attributing a stiff finger to the lump when there is a separate cause
- What to do
- Sensation in each digital nerve territory, capillary refill, Allen test in the hand where relevant
- What you are looking for
- Normal in almost all cases - a deficit is a red flag and also warns you the lesion may encase a nerve
- Pitfalls
- Testing sensation crudely in a young child; use two-point discrimination or a wrinkle test as appropriate
- What to do
- Palpate regional nodes; general examination for syndromic features and other masses
- What you are looking for
- Normal - this lesion does not involve nodes
- Pitfalls
- Palpable reactive nodes in a child causing unnecessary alarm
Imaging
Plain Radiograph - Always First
Start here. It is the single most useful and most available investigation, and the one that can make the diagnosis in the right clinical setting. Take two orthogonal views and include the adjacent joint.
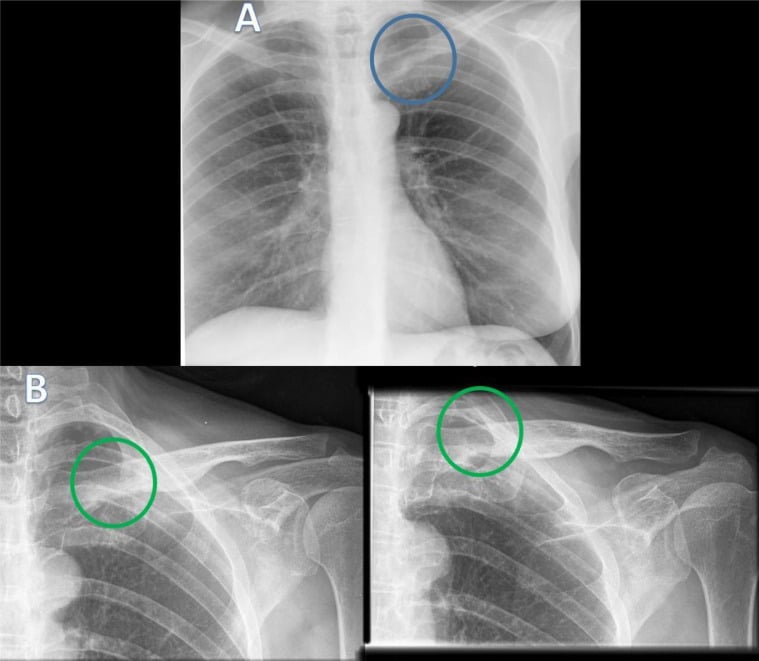
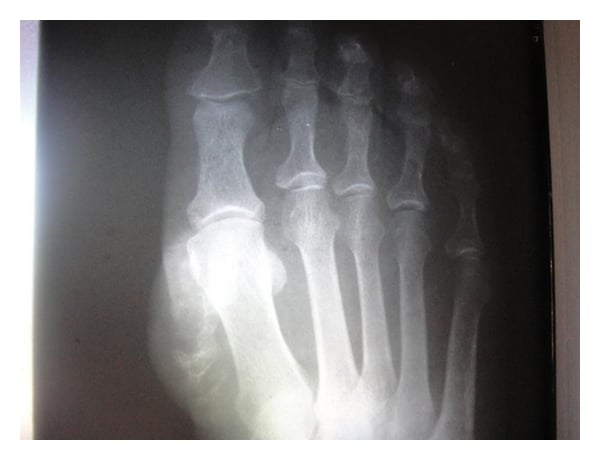
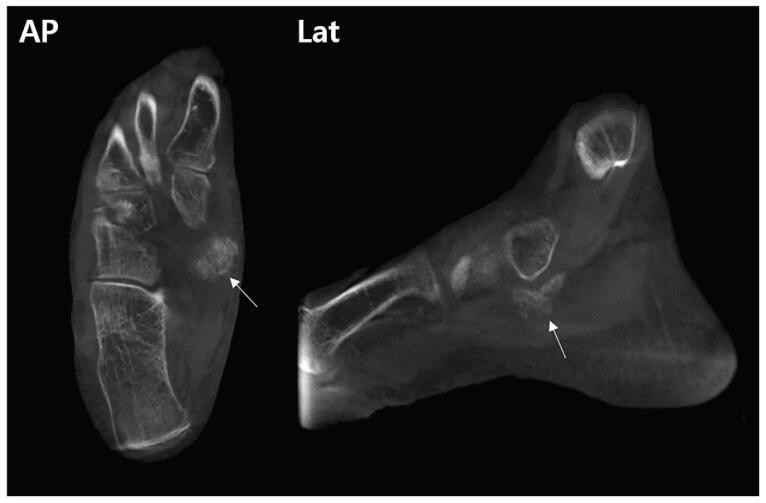
The classic finding is a soft-tissue mass containing fine, stippled or punctate calcification. The calcification is fine and granular, distributed within the lesion rather than lying as a peripheral shell.
Calcification is present in only a proportion of cases and is age-dependent - more often seen and more conspicuous in older children and adolescents, and frequently absent in children under about 5 years. Its absence therefore does not exclude the diagnosis.
Bone involvement is uncommon. Where present it is a pressure erosion or a smooth cortical indentation from an adjacent mass, not permeative destruction. Frank bone destruction should make you think of something else.
Two checks before you call the pattern characteristic. Confirm the lesion is soft tissue and not a bone lesion - an aneurysmal bone cyst, for instance - eroding outwards, and that multiple intra-articular or bursal calcified nodules are not synovial chondromatosis or another synovial disorder.
Reading the Pattern of Calcification
Age, site and the pattern of calcification separate these lesions: fine stippled calcification in the palm or sole of a child is calcifying aponeurotic fibroma, zonal peripheral maturation after trauma is myositis ossificans, and any soft-tissue mass near a joint in an adolescent must have synovial sarcoma excluded.
- Suggests
- CALCIFYING APONEUROTIC FIBROMA
- Discriminator
- Age, site and the fine granular quality of the calcification
- Suggests
- Myositis ossificans
- Discriminator
- The peripheral maturation pattern and a history of trauma; the OPPOSITE of the sarcoma pattern
- Suggests
- Tumoral calcinosis
- Discriminator
- Often abnormal calcium and phosphate metabolism; check renal function and phosphate
- Suggests
- Soft-tissue chondroma or another cartilaginous lesion
- Discriminator
- Mature cartilage matrix pattern; usually an adult
- Suggests
- SYNOVIAL SARCOMA must be excluded
- Discriminator
- Calcifies in around a third of cases; needs MRI and a planned biopsy
- Suggests
- Malignancy - not this diagnosis
- Discriminator
- Bone involvement in CAF is a pressure erosion at most
MRI - the Investigation That Defines Extent
When to request it. All but the most obviously trivial lesions, and mandatory before any excision where the diagnosis is not certain, where the lesion is larger than about 3 cm, or where it is deep to fascia.
Signal characteristics across the sequences:
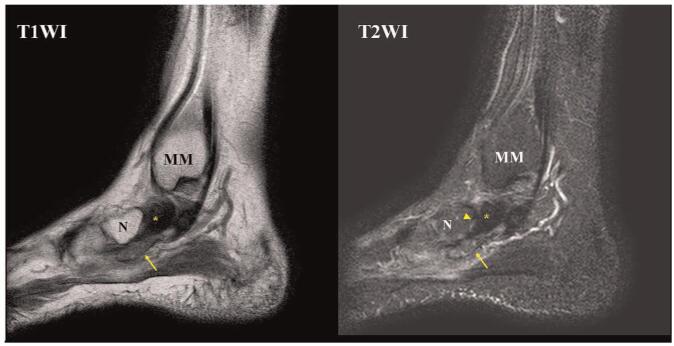
- T1: low to intermediate, similar to or slightly higher than skeletal muscle
- T2 and fluid-sensitive sequences: heterogeneous intermediate to high, with low-signal foci corresponding to the calcification and to the fibrous stroma
- Post-contrast: heterogeneous enhancement, often moderate
- Gradient-echo sequences: blooming artefact from the calcific foci, a useful confirmatory sign
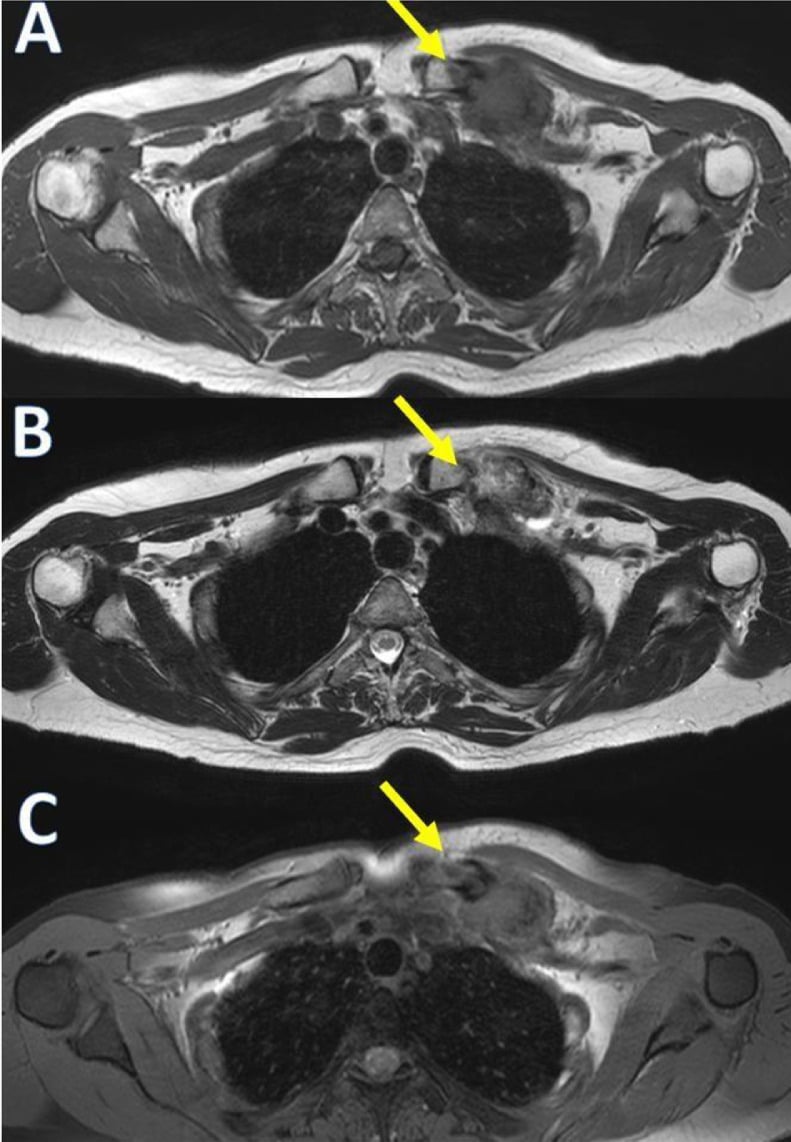
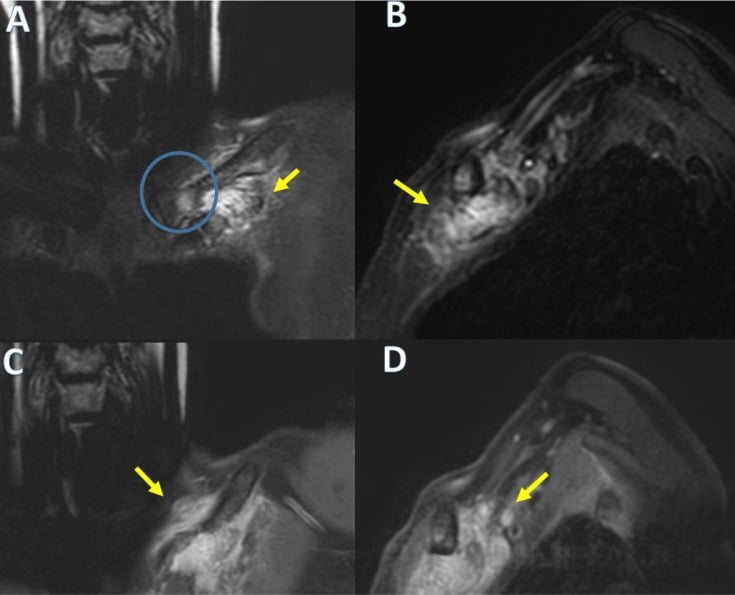
Morphology. Poorly defined, infiltrative margins, with extension along fascial planes and around tendons. This is the imaging correlate of the recurrence rate, and it is what the surgeon must know before operating.
What MRI is for. Defining the relationship to tendons, neurovascular bundles and joints, planning the incision and the extent of excision, and providing a baseline for surveillance. It cannot reliably distinguish this lesion from a sarcoma on signal alone: infiltrative margins are not evidence of malignancy here, and equally are not evidence against it, which is why histology remains the arbiter.
What each test can and cannot do. This is the honest position, and the one to state in a viva: radiograph plus age plus site can strongly suggest the diagnosis, MRI defines extent and plans surgery but does not exclude a sarcoma, and histology, supported by immunohistochemistry and molecular testing where available, is definitive. So image before you cut, and if the diagnosis is not confidently benign on age, site and radiograph, biopsy before you excise, with the incision placed so that it can be included in a definitive resection if the histology surprises you.
Ultrasound, CT and Nuclear Medicine
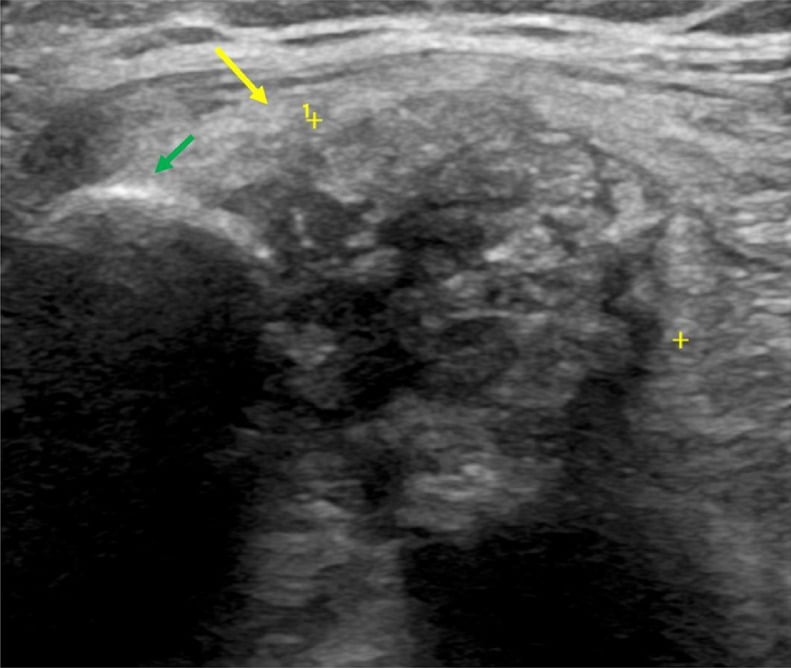
Ultrasound is useful as a first-line tool, particularly in a young child, because it avoids sedation. It shows a hypoechoic to heterogeneous mass with echogenic calcific foci and posterior acoustic shadowing, fixed to the aponeurosis, and Doppler shows modest vascularity. It is also the practical tool for follow-up in a resource-limited setting.
CT demonstrates the calcification most sensitively and shows any cortical pressure erosion. It is not usually required if radiographs and MRI are available, and it carries a radiation cost in a child. Bone scan and PET have no role in the routine assessment of this lesion.
Management
- 11. Image before you operatePlain radiographs in two planes, then MRI with contrast for any lesion that is not trivially small and obviously superficial.
- 22. Decide whether a biopsy is neededIn a child of classic age with a classic site and classic stippled calcification, a planned excisional biopsy is reasonable. Where any red flag is present, perform a planned image-guided core or open biopsy first, with the incision placed so it can be included in a definitive resection.
- 33. Marginal excisionExcise the lesion with the aponeurotic tissue it arises from, taking a marginal margin where that is achievable without functional cost.
- 44. Observation as a legitimate optionA small, asymptomatic, radiologically characteristic lesion in a young child may reasonably be observed with clinical and ultrasound surveillance, particularly where excision would require dissection around critical structures. Growth, symptoms or diagnostic uncertainty tip the balance toward excision.
- 55. Counsel the family, and document itExplain that the lesion is benign, that it can recur locally, that a recurrence is treated by simple re-excision, and that it will never spread. Documenting the conversation is what prevents alarm and inappropriate escalation when a recurrence appears.
Surgical Principles
Approach. A longitudinal incision in the palm or sole, placed along the relevant crease or a standard extensile line and oriented so that it can be extended and, if necessary, incorporated into a wider resection. Avoid transverse incisions that cross flexor creases, and avoid incisions on weight-bearing plantar surfaces where possible.
Tourniquet and magnification. Use both in the hand. The lesion infiltrates fascia and can be intimately related to digital nerves, and loupe magnification materially improves the chance of preserving them.
Extent. Excise the lesion together with the involved aponeurosis, since that is its tissue of origin. Removing a nodule and leaving the surrounding infiltrated fascia guarantees recurrence.
What to preserve at all costs. The digital nerves and their branches, the digital neurovascular bundles, the flexor tendons with their sheaths and pulleys, and the plantar digital nerves and vessels. It is entirely correct to dissect the lesion off these structures and accept a positive margin there; a functional hand with a recurrence is a better outcome than a stiff, insensate hand without one.
Frozen section has limited value here, and the diagnosis is best made on formal histology with immunohistochemistry.
Reconstruction is rarely needed. Where an extensive palmar fascial excision leaves a defect, a full-thickness graft or local flap may be required - and needing extensive reconstruction should raise the question of whether the resection was more aggressive than the diagnosis justified.
What not to do. Amputation, compartmental or radical resection, adjuvant radiotherapy, or chemotherapy: none is indicated for a benign lesion with no metastatic potential.
Management of Recurrence
Expect it. Most recurrences present within 3 years of excision, and the risk is higher after an incomplete excision.
Re-excise marginally, with the same functional priorities as the first operation. A second recurrence is managed the same way.
Reconfirm the histology on the recurrence specimen. That is not because malignant transformation is expected - it is not - but because a persistent or unusual lesion is an opportunity to make certain the original diagnosis was right.
Observation instead is reasonable for a small, asymptomatic recurrence in a functionally critical site, in a child in whom repeated dissection would cost more than the lesion does.
Multiple recurrences are not an indication to escalate. They are an indication to be sure of the diagnosis and to accept a functionally driven, deliberately conservative strategy.
Complications
- Mechanism
- The lesion encases digital nerves and their branches in the palm
- Avoidance
- Tourniquet, loupe magnification, identify nerves before dissecting; accept a positive margin at the nerve
- Mechanism
- Involvement of the tendon sheath and pulleys, or extensive dissection
- Avoidance
- Preserve the sheath and pulleys; early supervised mobilisation; do not over-resect
- Mechanism
- Extensive palmar fascial excision, prolonged immobilisation, scarring
- Avoidance
- Limit the resection to what the diagnosis justifies; early hand therapy
- Mechanism
- Incision placed across a flexor crease or on a weight-bearing plantar surface
- Avoidance
- Plan the incision along creases or standard extensile lines; avoid weight-bearing plantar skin
- Mechanism
- Misinterpreting local recurrence as malignant behaviour, and irradiating a benign lesion in a growing child
- Avoidance
- Understand that infiltration is not metastatic potential; never irradiate this lesion
- Mechanism
- Unplanned excision of what was assumed to be a benign lump but is a synovial or epithelioid sarcoma
- Avoidance
- Image before excising; planned biopsy where there is any doubt; place incisions so they can be re-excised
- Mechanism
- A recurrence appearing after inadequate counselling
- Avoidance
- Explain and document the expected recurrence rate and its benign significance at the first consultation
- Mechanism
- Long-standing untreated adjacent lesion
- Avoidance
- Uncommon; usually resolves after excision; a marker of a long-standing lesion, not of malignancy
Outcomes and Follow-Up
Prognosis
Excellent. There is no established capacity for malignant transformation, and local recurrence is the only meaningful adverse event.
Function is usually excellent provided the surgery is restrained. Where function is lost, it is far more often because of over-aggressive resection or nerve injury than because of the tumour.
Lesions may become better circumscribed and more calcified with age, and there are reports of recurrences behaving in a more nodular and more easily excised fashion in older children.
Follow-Up Strategy
Surveillance After Excision
Wound check, confirmation of the definitive histology and margin status, restoration of digital or foot function, and a documented discussion with the family about the expected recurrence rate and what to look for.
Examine and measure the site. Ultrasound is the first-line surveillance imaging - it is cheap, avoids radiation and sedation, and reliably identifies a recurrent nodule fixed to the aponeurosis. Most recurrences declare themselves in this window.
Continue annual clinical review. Reserve MRI for a suspected recurrence, a change in symptoms, or diagnostic uncertainty.
Radiograph and MRI to define extent, then repeat marginal excision with the same functional priorities. Reconfirm the histology. Do NOT escalate to radical surgery or radiotherapy.
Discharge with clear open access and written advice to return if a new lump appears. Recurrence after several disease-free years is uncommon but a patient-initiated review is always appropriate.
What to Tell the Family
The sentence that does the work is short: this is a benign lump; it can come back in the same place, and if it does we simply take it out again; it will not spread anywhere else and it will not become cancer. Add that it grows into the surrounding tissue rather than sitting in a capsule, which is why it can come back, and that we will deliberately not chase every last cell if that would mean damaging a nerve or a tendon, because the hand or foot matters more than the margin. Then teach the family and, as they grow, the patient, to report a new or enlarging lump at any point.
Guidelines, Registries & Global Practice
Global Framing and Epidemiology
- Calcifying aponeurotic fibroma is rare everywhere and no population predilection has been established. Reported series come from specialist soft-tissue pathology referral centres in Europe, North America and Asia with broadly consistent findings on age, site, sex and recurrence.
- Because it is rare, most published evidence is level 4 retrospective series and case reports. There are no randomised trials and there never will be. Practice is therefore built on consistent observations across small series: benign behaviour, high local recurrence, no metastasis.
- No registry captures this lesion specifically. National and regional sarcoma registries and multidisciplinary team datasets capture it incidentally as a benign diagnosis referred for assessment of an indeterminate soft-tissue mass, which is in fact the appropriate route for most of these lesions.
Side-by-Side Guidance
- Position relevant to this lesion
- Classifies calcifying aponeurotic fibroma as a benign fibroblastic and myofibroblastic tumour, with locally infiltrative growth and a propensity for local recurrence but no metastatic potential; recognises the FN1 rearrangement.
- Position relevant to this lesion
- Any unexplained soft-tissue mass in a child, or one that is enlarging, painful, deep to fascia, or larger than about 5 cm, should be imaged and referred to a specialist soft-tissue tumour service before excision. This is the safeguard that prevents unplanned excision of a sarcoma.
- Position relevant to this lesion
- Marginal excision is appropriate for a benign locally infiltrative lesion; function is preserved in preference to margin; unplanned excision of an undiagnosed mass is to be avoided; biopsy tracts must be placed so they can be excised with the definitive specimen.
- Position relevant to this lesion
- Radiotherapy is avoided for benign lesions in growing children because of growth disturbance, contracture and second malignancy risk; systemic therapy has no role in a lesion without metastatic potential.
Areas of Genuine Uncertainty
- The true recurrence rate. Figures ranging from roughly a third to two-thirds are reported. Series are small, margin definitions differ, and follow-up duration varies, so the commonly quoted "around 50%" is best treated as an order of magnitude.
- Whether malignant transformation genuinely occurs. A handful of reports describe sarcomatous change, but they are contested and may reflect misdiagnosis of the original lesion. The safest position is that it should not influence management.
- Optimal margin. Whether a deliberately wider excision meaningfully reduces recurrence, and whether any reduction would justify the functional cost in a hand or foot, has not been tested.
- Whether observation is an equivalent strategy for a small asymptomatic lesion or a small asymptomatic recurrence in a functionally critical site. It is widely practised and biologically defensible, but unstudied.
- The role of molecular testing in routine practice. FN1 rearrangement testing is available in specialist centres and helpful in difficult cases, but its cost-effectiveness in a lesion that is usually diagnosable on morphology is unclear.
- Optimal surveillance interval and duration. No comparative data exist; the commonly used schedule of 6-monthly review for 2 to 3 years then annually to skeletal maturity is pragmatic rather than evidence-based.
High- versus Limited-Resource Practice
- Well-resourced settings: plain radiographs and contrast-enhanced MRI, specialist soft-tissue pathology with a full immunohistochemistry panel and molecular testing, multidisciplinary team discussion before surgery, planned biopsy, hand or foot surgical expertise, and hand therapy after excision.
- Limited-resource settings: the most valuable single investigation is the one most widely available - a plain radiograph, which in a child with a firm painless palmar or plantar mass can strongly suggest the diagnosis when it shows fine stippled calcification. Ultrasound is an excellent and underused tool for both assessment and surveillance, avoids sedation, and needs no contrast. Where MRI and molecular testing are unavailable, the safeguards that matter most are clinical discipline - do not perform an unplanned excision of a mass in an adolescent, particularly near a joint; take a proper biopsy through an incision that can be re-excised; and refer or seek pathology review where the diagnosis is uncertain.
- Everywhere: the highest-value interventions are restraint and honest counselling. Do not over-resect a benign lesion; do not irradiate it; do not amputate for a recurrence; and make sure the family understands before surgery that recurrence is likely and harmless.
MCQ Practice Points
Q: Who gets calcifying aponeurotic fibroma and where? A: Children and adolescents, mostly under 20 years, with a male predominance of around 2 to 1 - in the palmar and plantar aponeuroses of the hands, wrists, feet and ankles.
Q: What is the classic radiographic appearance? A: Fine STIPPLED or PUNCTATE calcification within a soft-tissue mass. It is present in only a proportion of cases and is more conspicuous in older children - its absence does not exclude the diagnosis.
Q: What is the diagnostic histological feature? A: Chondroid nodules with central dystrophic calcification and a PALISADE of rounded chondrocyte-like cells at their periphery, set in an infiltrative but cytologically bland fibroblastic proliferation.
Q: What is the recurrence rate and the metastatic potential? A: Local recurrence around 50% (higher in younger children and after incomplete excision); metastatic potential is ZERO. Most recurrences appear within 3 years.
Q: What is the treatment of choice? A: MARGINAL EXCISION, taking the lesion with the involved aponeurosis, while preserving digital nerves, neurovascular bundles and flexor tendons - even at the cost of a positive margin. Recurrence is re-excised, not escalated.
Q: What is the role of radiotherapy? A: None. It offers no benefit for a benign non-metastasising lesion and carries risks of growth disturbance, contracture and secondary malignancy in a growing child.
Q: Which immunohistochemical stain distinguishes calcifying aponeurotic fibroma from desmoid-type fibromatosis? A: Beta-catenin. Desmoid shows nuclear beta-catenin accumulation; calcifying aponeurotic fibroma does not.
Q: Which test excludes synovial sarcoma? A: SS18 (SYT) gene rearrangement, supported by diffuse nuclear TLE1 positivity. Synovial sarcoma occurs in the hand and foot of adolescents and calcifies in around a third of cases.
Q: What is the immunohistochemical hallmark of epithelioid sarcoma, the other key hand mimic? A: LOSS of INI1 (SMARCB1), typically with cytokeratin and EMA positivity. INI1 is retained in calcifying aponeurotic fibroma.
Q: What recurrent molecular event has been described in calcifying aponeurotic fibroma? A: FN1-EGF gene fusions, confirming it is a clonal neoplasm and placing it among the FN1-rearranged, matrix-calcifying tumours.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 10-year-old boy is referred with a firm, painless lump in the ulnar side of his right palm, noticed by his mother about a year ago and slowly enlarging. It measures 2 cm, is fixed to the deeper tissues and the skin moves freely over it. Hand function and sensation are normal. How do you proceed?”
“Two years after excision of a histologically confirmed calcifying aponeurotic fibroma from the sole, an 8-year-old girl returns with a 1.5 cm firm nodule at the same site. Her parents are extremely anxious and ask whether this means it has turned into cancer, and whether she should have a wider operation or radiotherapy. How do you counsel and manage?”
“A 15-year-old girl has a 3 cm firm mass on the dorsum of her foot near the ankle, present for eight months and now mildly uncomfortable. Radiographs show a soft-tissue mass with a few scattered flecks of calcification. A colleague suggests it is probably a calcifying aponeurotic fibroma and should simply be excised in the day-case list. What is your view?”
Identity
- Benign fibroblastic tumour - Keasbey tumour (1953)
- Originally juvenile aponeurotic fibroma
- Children and adolescents, mostly under 20 years
- Male predominance around 2 to 1
- Palm, volar wrist, sole, ankle - the aponeuroses
Presentation
- PAINLESS, slow-growing, firm, poorly circumscribed
- Typically 1 to 3 cm, fixed to fascia or tendon
- Skin mobile over it; function usually normal
- Red flags: pain, rapid growth, over 5 cm, deep, adolescent near a joint
- Rarely limits movement unless the tendon sheath is involved
Imaging
- Radiograph: FINE STIPPLED or PUNCTATE calcification in a soft-tissue mass
- Calcification age-dependent - often absent under 5 years
- Bone involvement at most a pressure erosion, never permeative
- MRI: low to intermediate T1, heterogeneous T2, low-signal calcific foci, blooming on GRE, INFILTRATIVE margins
- Ultrasound: good for a young child and for surveillance
Histology
- Infiltrative BLAND fibroblastic proliferation, no atypia, rare mitoses
- CHONDROID NODULES with central calcification
- PALISADING chondrocyte-like cells at the nodule periphery
- Osteoclast-like giant cells may be present
- FN1-EGF fusion described; younger children less calcified and more diffuse
Differential
- Desmoid fibromatosis - NUCLEAR BETA-CATENIN positive
- Palmar or plantar fibromatosis - ADULT, no chondroid nodules
- SYNOVIAL SARCOMA - TLE1 positive, SS18 rearrangement, calcifies in a third
- EPITHELIOID SARCOMA - hand of a young adult, INI1 LOST
- Infantile fibrosarcoma - ETV6-NTRK3; myositis ossificans - ZONAL maturation
Management
- Image FIRST; planned biopsy if any doubt; place the incision so it can be re-excised
- MARGINAL excision including the involved aponeurosis
- Preserve digital nerves, neurovascular bundles and tendons - accept a positive margin there
- Recurrence about 50%, usually within 3 years - RE-EXCISE, never escalate
- NO radical surgery, NO amputation, NO radiotherapy, NO chemotherapy
- Follow up 6-monthly for 2 to 3 years then annually to skeletal maturity
Evidence Base
Juvenile Aponeurotic Fibroma (Calcifying Fibroma) - the Original Description
- NOTE - no abstract is indexed for this 1953 paper; the following is bounded by its title and MeSH indexing (fibroma, hand, foot, neoplasms)
- The original description of juvenile aponeurotic fibroma, also termed calcifying fibroma
- Characterised as a DISTINCTIVE TUMOUR ARISING IN THE PALMS AND SOLES OF YOUNG CHILDREN - the age and site that still define the diagnosis
- The name itself records the calcification that remains the radiographic hallmark
Juvenile Aponeurotic Fibroma
- NOTE - no abstract is indexed for this 1970 paper; the following is bounded by its title and MeSH indexing
- A clinicopathological account of juvenile aponeurotic fibroma, indexed against fibroma for classification, complications, diagnosis, pathology and surgery
- MeSH indexing also links the lesion to CALCINOSIS as a complication, consistent with the calcification that defines it
- It is conventionally cited as the series that consolidated the histological criteria and documented the tendency to local recurrence after excision
- The commonly quoted recurrence figure of around half derives from this and subsequent series rather than being verifiable from the indexed record here
Calcifying Aponeurotic Fibroma - A Clinicopathologic Study of 22 Cases Arising in Uncommon Sites
- 22 previously unpublished cases arising in UNCOMMON sites, confirming that the tumour primarily occurs in children and adolescents with a strong predilection for the distal extremities, especially the hands and feet
- 15 patients were male and 7 female - a male predominance; age range 2 to 43 years with a MEDIAN AGE OF 9, so adult presentation does occur
- Typically presented as a PAINLESS MASS, present from 2 weeks to 11 years before resection
- The uncommon sites were the back (8 cases), knee region (5), thigh (3), forearm (3), elbow (2) and arm (1)
- Lesions were often ADHERENT TO DENSE FIBROUS CONNECTIVE TISSUE such as tendon, fascia or periosteum
FN1-EGF Gene Fusions Are Recurrent in Calcifying Aponeurotic Fibroma
- The molecular basis of calcifying aponeurotic fibroma was previously unknown; this study used chromosome banding, FISH, mRNA sequencing, RT-PCR and immunohistochemistry to characterise a series of cases
- An insertion, ins(2;4)(q35;q25q?), was identified in the index case
- Fusion of the FN1 (fibronectin 1) and EGF genes, mapping to the breakpoint regions on chromosomes 2 and 4, was confirmed by RNA sequencing and RT-PCR
- FISH on five further tumours identified FN1-EGF fusions in ALL of them, establishing the fusion as RECURRENT
- Different FN1 exons (23, 27 or 42) were fused to EGF, indicating variable breakpoints within a consistent fusion partnership
Beta-catenin and LEF1 for Desmoid-Type Fibromatosis - and How Good They Actually Are
- 156 soft-tissue tumours including 35 desmoid-type fibromatoses and 121 histological mimics, stained for beta-catenin and LEF1
- Nuclear BETA-CATENIN gave sensitivity 94 per cent and specificity 88 per cent for desmoid-type fibromatosis - useful, and neither perfect nor pathognomonic
- The authors state plainly that nuclear beta-catenin is often DIFFICULT TO EVALUATE in desmoid, because nuclear expression is weak and membranous and cytoplasmic background staining is high
- LEF1 alone was 94 per cent sensitive but only 70 per cent specific, appearing in 82 per cent of nodular fasciitis, 37 per cent of soft-tissue perineurioma and 23 per cent of scars
- The two together raised specificity to 96 per cent, which is the practical use of LEF1 - as a partner stain, not a replacement
TLE1 as a Diagnostic Marker for Synovial Sarcoma - Prospective Evaluation
- PROSPECTIVE evaluation in exactly the setting that matters: incoming soft-tissue tumours where histology and clinical context made synovial sarcoma a real consideration
- Intense diffuse nuclear TLE1 staining in 35 of 35 molecularly confirmed synovial sarcomas
- Rare to absent in the 73 other soft-tissue tumours - positive in only 1 of 43 malignant peripheral nerve sheath tumours, 1 fibrosarcoma and 1 pleomorphic sarcoma
- Positive predictive value 92 per cent and negative predictive value 100 per cent in that clinical setting
- More sensitive and specific than Bcl2, epithelial membrane antigen or cytokeratins; the diagnostic standard remains demonstration of the t(X;18) SS18-SSX translocation
Loss of INI1 (SMARCB1) in Epithelioid Sarcoma - and the Tumour That Also Loses It
- 350 tumours examined: 136 epithelioid sarcomas (64 conventional distal, 64 proximal-type, 8 hybrid) against a large panel of epithelioid mimics
- Complete absence of INI1 expression in 127 of 136 (93 per cent) epithelioid sarcomas - 91 per cent of conventional, 95 per cent of proximal-type, 100 per cent of hybrid
- THE CRITICAL CAVEAT: 12 of 24 (50 per cent) EPITHELIOID MALIGNANT PERIPHERAL NERVE SHEATH TUMOURS also lost INI1, as did 2 of 22 (9 per cent) myoepithelial carcinomas and all control rhabdoid tumours
- INI1 was intact in every other tumour type tested, including metastatic carcinoma, melanoma, mesothelioma and angiosarcoma
- Conventional (distal) epithelioid sarcoma is the type arising in the hand and forearm of adolescents and young adults - the same population and site as this page's tumour