Proximal Tibial Metaphyseal Fracture | Post-Traumatic Valgus Deformity | Paediatric
- Proximal tibial metaphyseal fracture in children 3-8 years carries a high risk of post-traumatic valgus deformity (originally Cozen 1953)
- Valgus typically appears 6-12 months after the fracture has united - parents and surgeons must be warned
- The valgus deformity is usually self-correcting with continued growth over 2-3 years
- Premature corrective osteotomy carries a high rate of recurrence due to ongoing asymmetric growth - DO NOT operate early
- Indications for surgery are persistent deformity beyond skeletal maturity or functional impairment
- “Cozen fracture = proximal tibial metaphyseal fracture + later valgus
- “Counsel parents at the time of the initial injury that a valgus deformity may appear even after a perfectly healed fracture
- “Most cases spontaneously remodel - observation and serial radiographs are the mainstay of treatment
- “If surgery is needed, hemi-epiphysiodesis (guided growth) is preferred before skeletal maturity; corrective osteotomy is reserved for mature patients
Overview and Epidemiology
The phenomenon. Leonard Cozen described it in 1953: a proximal tibial metaphyseal fracture in a young child, usually unremarkable in itself, followed months later by a progressive valgus deformity of the tibia. The fracture is metaphyseal, not physeal, which is why Salter-Harris grading does not apply to it, and the valgus appears after the fracture has united, often despite a perfectly healed fracture. Distinguish it from Blount disease, from physiological genu valgum and from a true physeal bar after a proximal tibial physeal injury; the discriminators are tabulated under Investigations.
Why it matters. The Cozen phenomenon is one of the most important and frequently missed concepts in paediatric trauma, because a seemingly trivial fracture can, months later, produce a striking deformity that alarms both the parents and the treating surgeon. Understanding that the deformity improves substantially with growth is the difference between appropriate reassurance and inappropriate early surgery; recurrence after an early osteotomy is one of the most-cited pitfalls in paediatric orthopaedic textbooks.
A naming trap worth ten seconds. There are two unrelated Cozen eponyms in orthopaedics and they share nothing but a surname. This one is Leonard Cozen's 1953 description of post-traumatic tibia valga after a proximal tibial metaphyseal fracture in a child. Cozen's test is a provocative test for lateral epicondylitis - resisted wrist extension reproducing lateral elbow pain, a different Cozen, a different limb and a different decade of adult life. If a question says "Cozen", read the rest of the stem before answering.
Who. Children aged 3-8 years at peak, with most series spanning 2-10 years and some reporting cases up to age 10. There is a slight male predominance (1.2-1.5:1) that reflects exposure to play and sport; either side is affected without strong predominance, and bilateral cases are exceedingly rare. The proximal tibial physis is highly active in this age group, and that activity contributes to the asymmetric growth that follows.
How common. Proximal tibial metaphyseal fractures are among the most common paediatric lower-limb fractures and are reported worldwide; the mechanism varies by environment, with traffic injuries in low- and middle-income countries and sport in high-income ones. A substantial proportion of these children go on to valgus, but the exact figure is not established, and the numbers that circulate are examined under Outcomes and Prognosis.
Mechanism of injury. The classic mechanism, described by Cozen, is a valgus force on an extended knee. The others are a fall from a height onto a planted foot with the knee extended, a twisting or abduction force from a bicycle or scooter, a valgus blow in football, skiing or a playground fall, and a dashboard-type injury to an older child travelling as a passenger. The mechanism predicts the pattern, and the pattern predicts the late valgus risk, so document it clearly: it is part of the medicolegal record.
- Typical Pattern
- Greenstick of medial cortex (tension failure) or lateral compression
- Notes
- Classic Cozen mechanism
- Counselling
- Highest late valgus risk
- Typical Pattern
- Comminuted metaphyseal fracture, possible fibular fracture
- Notes
- Often more displacement
- Counselling
- Lower valgus risk if anatomically reduced
- Typical Pattern
- Spiral or oblique component to the metaphyseal line
- Notes
- Less typical for Cozen
- Counselling
- Lower valgus risk
Pathophysiology
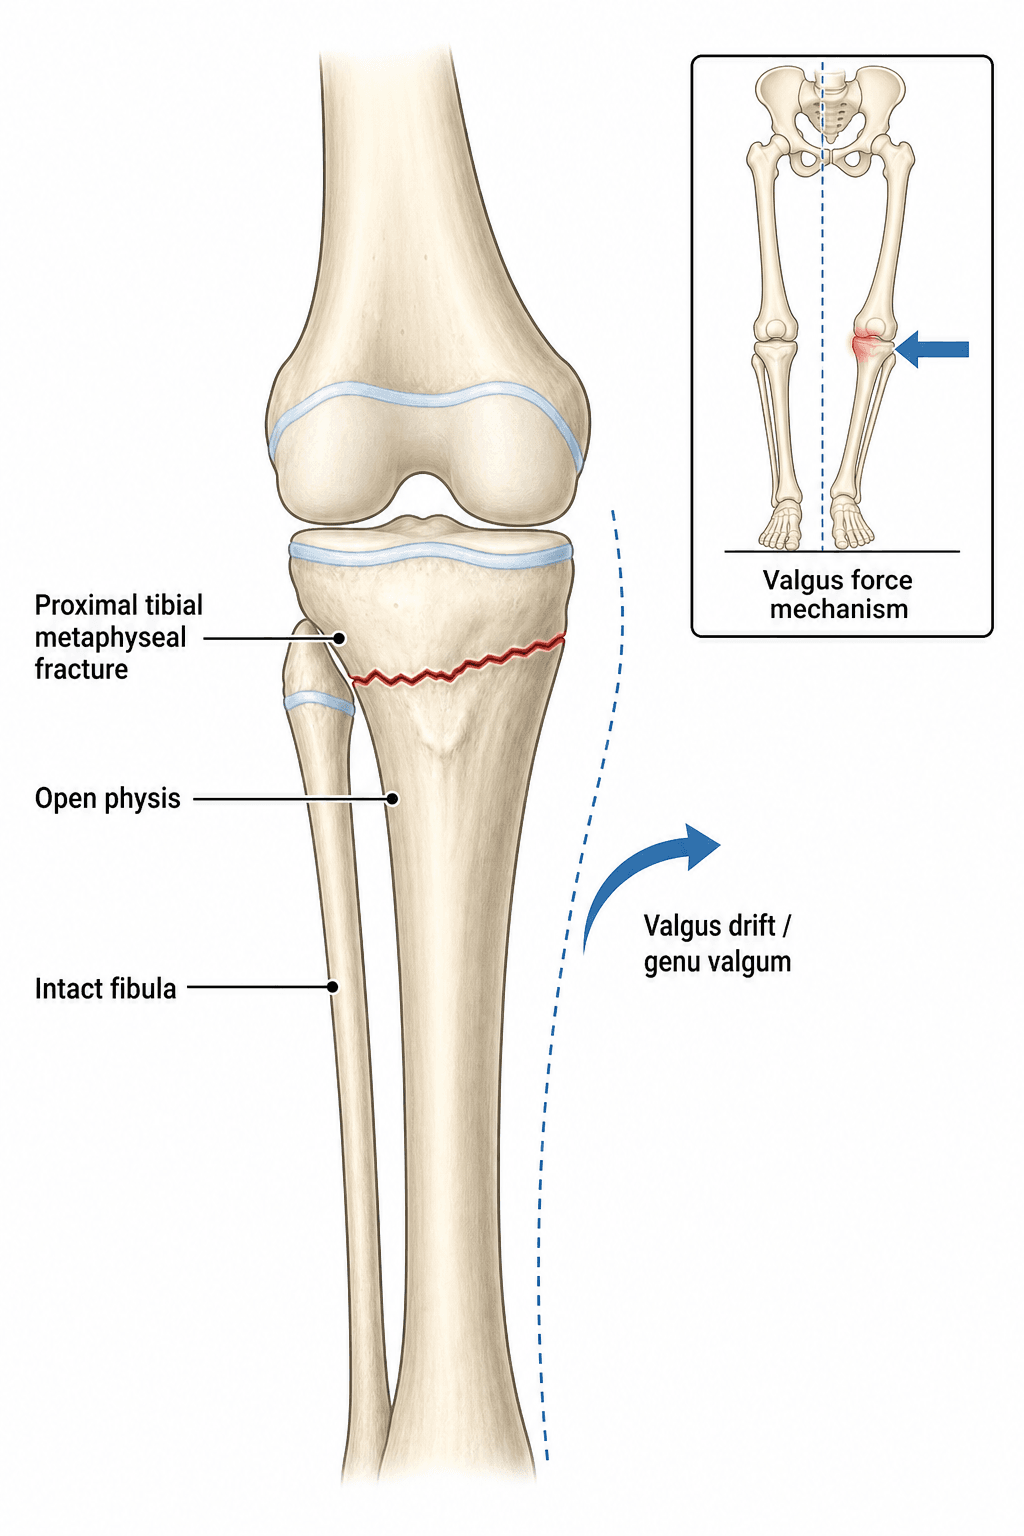
No single mechanism explains it. More than one is likely operative in any given child, and the most-cited theories are four. What they share is the implication that the growth disturbance may persist for years, which is the critical reason to defer a corrective osteotomy.
Asymmetric growth stimulation (Cozen, 1953). The hyperaemia of fracture healing stimulates the medial proximal tibial physis and produces relative medial overgrowth. The support is Cozen's original clinical series and the consistent timing of the valgus after union, and the cleanest mechanistic evidence is Green's 1983 case report, in which growth arrest lines in the proximal tibial metaphysis showed that the valgus after a nondisplaced fracture healed in normal position came from overgrowth of the medial physis, not from lateral arrest or malunion.
Tibial tubercle apophysis overgrowth (Ogden). The tibial tubercle is a continuation of the proximal tibial physis, and overgrowth of the lateral tibial tubercle apophysis contributes a valgus moment generated distal to the physis. The support is anatomic and radiographic study of the apophysis.
Soft-tissue interposition (Skak, 1982). Interposed periosteum or pes anserinus tendon on the medial side, with an intact fibula acting as a strut. Skak's seven children had primary valgus angulation with medial cortical diastasis, six with radiological signs of soft tissue interposed medially in the fracture gap, and he concluded that routine surgery to remove the interposed tissue is not justified. Lateral tethering by the fibula or the pes anserinus is a different proposed mechanism and should not be cited to his paper.
Occult crush of the lateral physis (Salter-Harris V). A sub-radiographic crush injury to the lateral physis slows lateral growth, so the valgus emerges with growth from an injury that was undetected at presentation. MRI studies show lateral physeal signal change in some cases.
Why the deformity is often transient. The valgus usually appears 6-12 months after injury, peaks around 9-18 months and then remodels, most within 2-3 years and without intervention. As long as the proximal physis is open and the child has significant growth remaining, the asymmetric growth can re-equilibrate; skeletal immaturity is the best friend of the patient with Cozen valgus.
Why early osteotomy fails. The growth disturbance that produced the valgus persists for years, so an osteotomy performed while it is still active invites recurrence. A rate of up to 50 percent is conventionally quoted, though that figure is not established in the primary literature; what the largest published series records is that corrective osteotomy has been abandoned because of frequent complications including recurrent valgus. A child with a recurrence may end up with both an osteotomy scar and a worse deformity than the original, and each osteotomy adds scar, infection risk and stiffness to a problem that nature was correcting.
Classification and Types
The acute fracture. Four patterns, and the late valgus risk runs paradoxically the wrong way: it is higher in the greenstick and less-displaced variants than in a displaced fracture that is anatomically reduced, and valgus can follow even an undisplaced injury. This is a recurring exam point.
- Description
- Compression of medial or lateral metaphyseal cortex
- Risk of Late Valgus
- Low
- Initial Treatment
- Cast 4-6 weeks, observe
- Description
- Medial cortex fails in tension, lateral cortex and periosteum intact, angulated into valgus
- Risk of Late Valgus
- Moderate-high
- Initial Treatment
- Closed reduction in slight varus, cast
- Description
- Both cortices disrupted, often fibula intact or also fractured
- Risk of Late Valgus
- Moderate
- Initial Treatment
- Anatomic reduction, cast
- Description
- Translation, overlap, or rotation
- Risk of Late Valgus
- Lower if anatomically reduced
- Initial Treatment
- Closed or open reduction, possible internal fixation
The evolving deformity. The clinical course is a dynamic remodelling process, not a one-off surgical decision, and it is staged by time from injury.
- Timing
- 0-3 months
- Findings
- Fracture united, normal alignment
- Management
- Routine follow-up only
- Timing
- 3-9 months
- Findings
- Tibio-femoral angle becomes positive, mechanical axis shifts lateral to the centre of the knee
- Management
- Observe, counsel, document
- Timing
- 9-18 months
- Findings
- Maximum deformity, often 10-15 degrees or more
- Management
- Continue observation if skeletally immature
- Timing
- 18 months - 3-4 years
- Findings
- Valgus gradually corrects with growth
- Management
- Monitor until resolution or skeletal maturity
- Timing
- Beyond skeletal maturity
- Findings
- Deformity remains after physeal closure
- Management
- Corrective osteotomy (no growth left to guide)
Clinical Assessment
History. Establish the mechanism, whether a valgus force, an axial load or a twist, and the energy: a low-energy playground fall or a high-energy fall or vehicle collision. Inability to bear weight is usually present acutely, and knee pain and swelling may dominate the presenting complaint. Always document pre-injury alignment if it is known, and any prior injury or deformity.
Examination. Inspect for bruising, swelling, angular deformity and an open wound; the tenderness is localised to the metaphysis, not the joint line. Document distal pulses, capillary refill, sensation and motor function, the peroneal nerve especially, and review the compartments serially for the first 24-48 hours, particularly after casting. Knee ligaments are difficult to assess acutely; examine under anaesthesia if a reduction is required.
Proximal tibial fractures in children can produce a tibial compartment syndrome that is easily missed in a distressed, non-cooperating child. Always:
- Re-examine at 12-24 hours after cast application
- Split the cast if there is any concern about swelling
- Admit for observation after a high-energy mechanism
- Treat the three As - Analgesia escalation, Anxiety, Agitation (the 3 As of missed compartment syndrome in children) - as a red flag
Measuring the alignment. Four measurements track the deformity, from the goniometer in clinic to the long-leg film, and the mechanical axis is the most reliable of them.
- How to Perform
- Patient standing, knees extended, goniometer over patella to tibial tubercle
- Normal Value
- Mild valgus (5-7 degrees) under age 7 is physiological
- Significance
- Valgus greater than 10 degrees or asymmetric warrants concern
- How to Perform
- Standing with knees / ankles touching
- Normal Value
- Age-dependent: 0-2 cm under age 8
- Significance
- Tracks valgus progression and resolution
- How to Perform
- Plumb line from anterosuperior iliac spine on AP long-leg film
- Normal Value
- Should pass through centre of knee
- Significance
- Most reliable measure of deformity
- How to Perform
- Measure on AP long-leg film
- Normal Value
- LDFA ~87, MPTA ~87
- Significance
- Localises deformity to femur or tibia
Compare with the other side. Children have a wide range of physiological valgus, up to 7 degrees between ages 3 and 6, so the most useful finding is asymmetry between the injured and uninjured sides. A 10 degree valgus on the injured side with a 5 degree valgus on the other is more significant than a 7 degree valgus bilaterally.
Investigations
Radiographs. The diagnosis of the Cozen phenomenon is clinical-radiographic, not MRI-dependent, and plain films are the cornerstone. Acutely, AP and lateral views of the tibia including the knee and ankle confirm the fracture and show displacement, angulation and fibular involvement, with an AP pelvis-to-ankle long-leg film added in older children for deformity assessment. At follow-up the films are for measurement: tibio-femoral angle, mechanical axis, MPTA and LDFA.
At union. Radiographs at cast removal, repeated at 6 weeks if pain persists, confirm union, document any early deformity and provide the baseline for the 6-month review. Look for early tibial asymmetry, physeal widening and tubercle overgrowth.
When valgus develops. A standing long-leg film is the gold standard for measuring the mechanical axis and tracking the deformity in the growing child: it documents the deformity quantitatively and gives the mechanical axis deviation. Repeat it every 6 months until the deformity resolves or reaches a clear plateau.
MRI of the proximal tibial physis. Reserved for the deformity that is severe or progressive, or that fails to remodel, to look for an occult lateral physeal bar or a Salter-Harris V injury. The sequences are coronal T1 and gradient echo or PD fat-saturated through the physis, and young children often need sedation.
CT with 3D reconstruction. For pre-operative planning of complex or recurrent deformity. It defines the bony anatomy for osteotomy design, whether closing wedge, opening wedge or dome.
The differential. A tibial deformity after a fracture has a short list of alternatives, and the discriminators are the history of a preceding fracture and the symmetry of the finding.
- Onset
- 6-12 months after proximal metaphyseal fracture
- Discriminating Feature
- History of preceding fracture, asymmetric valgus
- Key Test / Imaging
- Long-leg standing film, MRI if severe
- Onset
- Insidious onset, no preceding fracture
- Discriminating Feature
- Progressive varus; characteristic medial tibial epiphyseal changes
- Key Test / Imaging
- Langenskiold staging on AP knee film
- Onset
- Symmetric, peaks at 3-4 years, then resolves
- Discriminating Feature
- No preceding trauma, no asymmetric findings
- Key Test / Imaging
- Observation, no imaging required unless asymmetric
- Onset
- Months to years after physeal injury
- Discriminating Feature
- Progressive deformity, may be multiplanar
- Key Test / Imaging
- MRI confirms bar; maps location and size
- Onset
- Gradual deformity without preceding trauma
- Discriminating Feature
- Palpable mass, characteristic imaging appearance
- Key Test / Imaging
- Radiographs, MRI for soft-tissue variants
- Onset
- Bilateral, gradual, other signs of metabolic disease
- Discriminating Feature
- Widened physis, cupped metaphyses, low phosphate / low vitamin D
- Key Test / Imaging
- Bone profile, wrist and knee films, endocrinology workup
Management Algorithm
- Typical Management
- Above-knee cast 4-6 weeks, then observe
- Key Pearl
- Warn parents about late valgus
- Pitfall
- Discharging without counselling
- Typical Management
- Closed reduction in slight varus, cast
- Key Pearl
- Slight over-correction may reduce late valgus
- Pitfall
- Leaving in valgus and accepting the result
- Typical Management
- Observe with serial clinical and radiographic review
- Key Pearl
- Most remodel within 2-3 years
- Pitfall
- Listing for corrective osteotomy too early
- Typical Management
- Guided growth - temporary medial hemi-epiphysiodesis (largest series: correction in all but one of 19)
- Key Pearl
- Needs reliable follow-up; the tether must come out or the leg OVERCORRECTS
- Pitfall
- Reaching for osteotomy instead - it has been abandoned for recurrent valgus
- Typical Management
- Corrective tibial osteotomy (no growth left to guide)
- Key Pearl
- Also measure limb length - the injured tibia overgrows in these children
- Pitfall
- Offering guided growth when the physes have closed
The acute fracture. The goal is union in acceptable alignment and a family who understand the natural history.
Acute Treatment Protocol
Clinical examination, neurovascular status and pain control, with two-view radiographs of the tibia including the knee and ankle. Tetanus and antibiotic prophylaxis if the fracture is open. The counselling described below happens now, at the first visit.
Above-knee cast with the knee in slight flexion and the ankle at neutral, moulded to hold the fracture. A greenstick in valgus is reduced as described below. If there is any concern about swelling, split the cast and reapply it after the swelling settles.
Remove the cast when clinical and radiographic union is achieved, typically 4-6 weeks in this age group; the review radiographs confirm union, document alignment and provide the baseline for future comparison. Encourage weight-bearing and a gradual return to activity.
Clinical review at 3, 6 and 12 months, then annually until any deformity resolves, with a standing long-leg film at 6 and 12 months or sooner if a deformity becomes obvious. Note any emerging valgus, and counsel that it usually remodels.
Reducing the greenstick in valgus. Many paediatric orthopaedic surgeons complete the fracture, reversing the intact cortex, and reduce the tibia in slight varus. This is thought to lower the rate of post-traumatic valgus by allowing more uniform physeal stimulation, and slight over-correction may reduce the late valgus. Document the reduction manoeuvre clearly.
Counselling at the first visit. This is the most important single conversation of the episode. Tell the family that a knock-knee appearance may develop on the injured side months after the fracture has healed, even after perfect healing; that it is likely to self-correct with growth; that the appropriate response is observation and review, not surgery; and that follow-up continues until remodelling is complete.
Document it. Write a brief clinic note that the family was counselled about the Cozen phenomenon, the natural history and the rationale for observation. The note is medicolegally essential, it pre-empts complaints, and it protects the surgeon, the family and the child; skip the conversation and you will be the surgeon asked to "fix" a valgus that was always going to correct, and may end up doing an osteotomy that then recurs.
When valgus appears. From 6-12 months the goal is to avoid premature surgery: document, reassure and monitor. A deformity that is getting worse at the 6-month review is the natural course rather than a failure - in Skak's series the valgus progressed through the first year despite clinical healing and slowly regressed from one to two years after injury - so the default for an immature child with emerging Cozen valgus is observation, and surgery is the exception, not the rule.
Observation Protocol
The intermalleolar separation becomes visible, and the parent may notice the child tripping or looking knock-kneed; the tibio-femoral angle is increased and the mechanical axis has shifted lateral to the centre of the knee. Document, re-counsel the parents, and schedule the next review at 3-4 months.
The valgus is at its most visible, often 10-15 degrees or more, and the child may be in a normal activity pattern despite the appearance; the MPTA is increased and the mechanical axis deviation is measured. Reassure that most cases peak and then improve, and do not list for surgery.
Gradual straightening over 2-3 years, with the mechanical axis returning toward the centre of the knee. Continue observation; if the deformity plateaus, document it and decide on the next step.
- Continue Observation
- Significant growth remaining (open physes, younger child)
- Consider Surgery
- Approaching / at skeletal maturity
- Continue Observation
- Improving mechanical axis on successive films
- Consider Surgery
- Plateau or worsening despite growth
- Continue Observation
- Asymptomatic, normal function, no pain
- Consider Surgery
- Pain, instability, gait abnormality, or functional limitation
- Continue Observation
- Mild to moderate (under 15 degrees tibio-femoral)
- Consider Surgery
- Greater than 15-20 degrees, or progressive
The single decision that must not be missed: the post-fracture valgus you are observing is either benign Cozen tibia valga, which remodels, or a partial physeal arrest or bar, which progresses and will not remodel, and the management is opposite. Assemble the discriminators on serial standing long-leg films rather than treating them as separate complications.
- Benign Cozen: the valgus appears after union, peaks, and then the mechanical axis steadily improves with growth; the proximal tibial physis looks open and symmetric; the deformity is purely valgus, in the coronal plane.
- Physeal arrest (bar): the deformity is progressive and fails to remodel, or worsens, over successive films, often with a multiplanar or shortening component, convergent or tethered Harris growth-arrest lines, and physeal narrowing or bridging, typically after a higher-grade (Salter-Harris III-V) injury.
If the axis is improving or plateauing with growth, keep observing. If it is progressive or not remodelling, get an MRI or CT to map the physis for a bar, its size and location, then treat the arrest specifically: bar resection if the bar is small, commonly under about half the physis, with substantial growth remaining; otherwise completion epiphysiodesis with or without guided growth or osteotomy, and contralateral epiphysiodesis for any limb-length discrepancy. Do not just keep waiting.
Surgical options. Surgery is reserved for persistent deformity: valgus that persists or progresses beyond skeletal maturity, severe functional impairment, or pain. In a still-growing child the trigger is persistent, symptomatic valgus that is not remodelling, by the thresholds in the table above, and the operation is chosen by the growth remaining: guided growth while the physes are open, osteotomy at or near maturity.
Guided growth (hemi-epiphysiodesis). A tension-band plate (8-Plate) or staple across the medial proximal tibial physis slows medial growth and lets the lateral side catch up. It is for the skeletally immature child with persistent valgus and at least 1-2 years of growth remaining, estimated from skeletal age and remaining-growth charts or the multiplier; with too little growth left it will not correct in time, and osteotomy at maturity is the answer. The attractions are a small incision, a day-case procedure, no osteotomy, and reversibility, the plate being removed after correction; the costs are the need for residual growth, implant-related irritation and rebound.
Why it beats osteotomy in the growing child. It works with the remaining growth rather than against a persisting growth asymmetry, so it does not carry the recurrence problem of osteotomy before maturity. It is not free of recurrence, though: in the largest series, correction of the mechanical axis and MPTA was achieved in all but one of 19 patients, there were five recurrences in four patients, four of which corrected with repeat tethering, and two patients overcorrected because the family did not return for timely follow-up.
Rebound and the timing of removal. Once the plate is removed with the limb straight, the previously restrained physis can resume asymmetric growth and the valgus can recur; removing the plate too early is the classic cause of recurrence. Monitor after removal, and in a young child consider slight overcorrection before removal or simply leave the implant until closer to maturity. The tether must come out in the end, though, or the leg overcorrects, which is why the operation needs a family who will attend follow-up.
Corrective tibial osteotomy. A closing-wedge or opening-wedge osteotomy of the proximal tibia, sometimes with a fibular osteotomy, realigns the mechanical axis. It is for the skeletally mature patient, or one approaching maturity with severe deformity, and should only be performed when the growth plates are nearly closed or the family accepts the risk of recurrence. The risks are recurrence, especially if performed too early, compartment syndrome, neurovascular injury, non-union and hardware irritation. Measure limb length at the same time, for the reason given under Outcomes and Prognosis.
Combined and salvage procedures. For recurrent valgus after osteotomy, multiplanar deformity or an associated limb-length discrepancy, the options are multi-level osteotomies, gradual correction with an external fixator (Taylor Spatial Frame), or hemi-epiphysiodesis followed by osteotomy in staged fashion. Each additional procedure adds scarring, stiffness and infection risk; avoid accumulating operations on a child.
Complications
The valgus deformity heads the list; its prevention is the counselling and surveillance described under Management.
- Incidence
- A substantial proportion; the exact figure is not established (variable severity)
- Risk Factors
- Younger age (3-8), greenstick in valgus, undisplaced fracture
- Management
- Observe; surgical correction only if persistent beyond maturity
- Incidence
- Conventionally quoted as up to 50 percent if osteotomy done before skeletal maturity (figure not established)
- Risk Factors
- Premature surgery with persistent growth asymmetry
- Management
- Re-osteotomy after maturity, hemi-epiphysiodesis if growth remains
- Incidence
- Less than 1 percent, but catastrophic if missed
- Risk Factors
- High-energy mechanism, tight circumferential cast, delayed presentation
- Management
- Split cast, urgent fasciotomy if suspected
- Incidence
- Rare, usually neurapraxia
- Risk Factors
- High-energy injury, displaced fracture, surgical exploration
- Management
- Observation, foot splint, nerve conduction studies if persistent
- Incidence
- Uncommon, often subclinical initially
- Risk Factors
- Salter-Harris III-V injury, missed at initial presentation
- Management
- MRI for diagnosis, bar excision if under about half of the physis and significant growth remains
- Incidence
- Mild, rarely clinically significant
- Risk Factors
- Asymmetric growth stimulation, physeal injury
- Management
- Observe; epiphysiodesis of the contralateral side if clinically significant at maturity
- Incidence
- Rare in this age group
- Risk Factors
- High-energy mechanism, knee dislocation equivalent
- Management
- Examine under anaesthesia, MRI if any suspicion
Outcomes and Prognosis
- When Used
- Skeletally immature, asymptomatic valgus
- Expected Outcome
- Spontaneous correction over 2-3 years in most; the proportion is not established
- Long-term Function
- Excellent: normal knee, normal gait
- When Used
- Immature child with persistent valgus, growth remaining
- Expected Outcome
- Gradual correction over 12-18 months, plate removed at neutral
- Long-term Function
- Good; mild rebound possible if removed early
- When Used
- Mature patient with persistent valgus
- Expected Outcome
- Reliable correction, low recurrence if growth complete
- Long-term Function
- Good; risk of stiffness, hardware irritation
- When Used
- Inappropriate but historically common
- Expected Outcome
- Recurrence conventionally quoted as up to 50 percent, sometimes worse than original
- Long-term Function
- Variable; multiple surgeries often needed
Patience is the right conclusion, but the usual wording overstates it in two ways that matter at the follow-up clinic and in the viva.
Improvement is not normalisation. In the definitive long-term study, seven children followed a mean of 15 years, every patient's angles improved, but every patient still had a mechanical axis lateral to the centre of the knee (mean deviation 15 mm, range 3-24), and every patient had a longer tibia on the injured side (mean 9 mm, range 3-18) (PMID 10391545). The injured leg overgrows, so the sequela to warn about is not only the transient knock-knee but a small permanent limb-length difference, assessed by the principles in limb-length discrepancy and epiphysiodesis. Say to a parent that the appearance will improve greatly, not that the leg will end up identical.
Correction is real but not predictable. The largest published series states it in exactly those terms: "while spontaneous remodelling has been reported, this is not predictable" (PMID 29549568). That is why the answer is watchful follow-up rather than discharge; you are waiting to find out which child this is, not confirming a foregone conclusion. Where the deformity does persist and growth remains, the modern answer is guided growth.
The numbers you may see quoted. Figures such as "50-90% remodel" and "recurrence up to 50% after early osteotomy" circulate widely, and the same 50-90% is sometimes used in one place for the proportion who remodel and in another for the proportion who develop valgus, two quite different quantities. None of the primary sources cited here supports a specific percentage: the long-term series has seven patients and the largest series calls remodelling unpredictable. Quote the direction and the mechanism, and say the precise proportion is not established.
The prognosis is set by the growth remaining and by the trend on serial films. Favouring spontaneous correction:
- Younger age with substantial growth remaining
- Mild to moderate initial valgus (under 10 degrees tibio-femoral angle)
- Improving mechanical axis on serial films
- Asymptomatic child with normal function
Against it:
- Age greater than 10 years at injury (less remodelling potential)
- Persistent or progressive valgus on serial films
- Symptomatic deformity (pain, gait abnormality)
- Skeletal maturity reached without correction
Guidelines, Registries & Global Practice
- Paediatric tibial fractures are among the most common lower-limb fractures in children worldwide, with peak incidence in the 3-10 year age group
- Proximal metaphyseal involvement is reported from every region where paediatric imaging is available
- Mechanism varies by setting: low-energy falls and sport in HICs, higher-energy traffic-related and fall-from-height mechanisms in LMICs
- The Cozen phenomenon is described in North American, European, Asian, African, and Australasian series - it is a universal paediatric orthopaedic entity
- High-resource settings: routine long-leg standing films at follow-up, MRI available for atypical cases, 8-Plate and external fixator systems for guided growth
- Limited-resource settings: clinical measurement of intermalleolar / intercondylar distance, plain radiographs alone, conventional staples or screw hemi-epiphysiodesis
- Universal principle: the appropriate response is observation and counselling regardless of resource - the biology is the same in every setting
- Surgery: corrective osteotomy is concentrated in tertiary paediatric centres; outcome data is more abundant from these centres
- Diagnosis emphasis
- Clinical-radiographic; long-leg standing film is the gold standard for measuring mechanical axis
- Acute treatment
- Cast immobilisation 4-6 weeks; counsel family about Cozen phenomenon at presentation
- Surgery / reconstruction
- Hemi-epiphysiodesis in the immature child with persistent deformity; osteotomy only at maturity
- Diagnosis emphasis
- Clinical; AP and lateral of tibia acutely, long-leg film at follow-up
- Acute treatment
- Cast, ensure anatomic or slight-varus reduction in greenstick fractures
- Surgery / reconstruction
- Reserved for symptomatic persistent deformity at or near maturity
- Diagnosis emphasis
- Distinguish Cozen from Blount, physiological valgus, and physeal bar
- Acute treatment
- Standard cast; emphasise parental counselling and serial review
- Surgery / reconstruction
- Guided growth preferred over osteotomy in skeletally immature children
- Diagnosis emphasis
- Resource-adapted: clinical and plain radiographic assessment in most settings
- Acute treatment
- Cast immobilisation, follow-up at 3, 6, and 12 months
- Surgery / reconstruction
- Hemi-epiphysiodesis (8-Plate, staples) or osteotomy depending on maturity and resources
There is no dedicated fracture or deformity registry for the Cozen phenomenon specifically. Evidence comes from case series published by individual paediatric centres (Cozen, Skak, Ogden, Green, Tuten, Robert) and from textbook synthesis (Tachdjian, Lovell and Winter, Rockwood and Wilkins). The consistency of the message across decades and continents is striking: observe, counsel, and avoid premature osteotomy. Where uncertainty exists, it is in the relative contribution of the four competing mechanisms - not in the management principle.
Record in every proximal tibial metaphyseal fracture seen acutely:
- Mechanism of injury and energy
- Initial tibio-femoral angle or mechanical axis if measurable
- Cast type, moulding, and any reduction manoeuvre
- Family counselled about the Cozen phenomenon and the natural history of late valgus
- Follow-up plan at 3, 6, and 12 months (and beyond if valgus appears)
A missed Cozen discussion is a recurring source of complaints and medicolegal claims in paediatric orthopaedic practice worldwide. The cost of ten minutes of counselling is a fraction of the cost of an unnecessary osteotomy.
Controversies & Areas of Uncertainty
Four theories (Cozen, Ogden, Skak, Salter-Harris V) are all supported by some evidence. It is likely that more than one mechanism operates in any given child. The relative contribution of each remains undetermined and may explain why no single preventive measure (over-reduction, fibular osteotomy, pes release) has consistently eliminated the valgus.
Some surgeons advocate completing greenstick fractures and reducing in slight varus to lower the late valgus rate. Evidence is mixed; the manoeuvre is not universally practised, and anatomic or near-anatomic reduction is also acceptable. The principle is sound but the magnitude of effect is uncertain.
There is no absolute degree of valgus that mandates surgery. The decision integrates magnitude, trend on serial films, skeletal maturity, and functional impact. Some surgeons offer hemi-epiphysiodesis at 10 degrees of valgus in a 10-year-old with 2 years of growth remaining; others watch a similar deformity in a 7-year-old and expect remodelling.
Most cases resolve. Whether a small subset of patients with persistent valgus into adulthood develop premature lateral compartment osteoarthritis is plausible but not well-quantified. Adult deformity correction is sometimes offered for this reason, but the natural history beyond skeletal maturity is not rigorously documented.
MCQ Practice Points
Q: What is a Cozen fracture? A: A proximal tibial metaphyseal fracture in a young child (typically 3-8 years) that is followed by progressive valgus deformity of the tibia 6-12 months after the fracture has united. The fracture itself is often unremarkable, but the late valgus can be striking.
Q: What is the most likely mechanism of the post-traumatic valgus? A: It is probably multifactorial. The leading theories are (1) asymmetric stimulation of the proximal tibial physis by fracture hyperaemia (Cozen), (2) overgrowth of the lateral tibial tubercle apophysis (Ogden), (3) soft-tissue tethering on the medial side by pes anserinus, periosteum, or an intact fibula (Skak), and (4) sub-radiographic Salter-Harris V crush of the lateral physis. In practice, more than one mechanism is likely operative.
Q: What is the appropriate management of post-traumatic tibia valga in a 5-year-old? A: Observation with serial clinical and radiographic review. Most cases spontaneously remodel over 2-3 years. Corrective osteotomy is reserved for persistent deformity at or near skeletal maturity because early osteotomy carries a recurrence rate of up to 50 percent.
Q: How do you distinguish Cozen phenomenon from Blount disease? A: Cozen follows a proximal tibial metaphyseal fracture and appears 6-12 months later; Blount is insidious, with no preceding fracture, and shows characteristic changes in the medial proximal tibial epiphysis and metaphysis (Langenskiold staging). Physiological valgus is symmetric, peaks at 3-4 years, and resolves by age 7.
Q: When is corrective surgery indicated for Cozen valgus? A: When the deformity persists beyond skeletal maturity, is symptomatic (pain, gait abnormality, functional limitation), or is severe and progressive (greater than 15-20 degrees of tibio-femoral valgus). In a skeletally immature child, hemi-epiphysiodesis (guided growth) is the preferred temporising measure; definitive osteotomy is deferred.
Q: What is the most important complication of premature corrective osteotomy for Cozen valgus? A: Recurrence of the valgus deformity — conventionally quoted as up to 50 percent, though that precise figure is not established in the primary literature; what the largest series states is that corrective osteotomy has been abandoned because of frequent complications including recurrent valgus (PMID 29549568). The reason is that the underlying growth disturbance persists until skeletal maturity. This can produce a worse deformity than the original, with the additional burden of surgical scarring, stiffness, and infection risk from the unnecessary operation.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 5-year-old boy sustained a minimally displaced proximal tibial metaphyseal fracture 8 months ago after a fall from a slide. The fracture united uneventfully, but his mother brings him back concerned about a progressive knock-knee deformity on the injured side. Examination shows 12 degrees of valgus on the injured side and 5 degrees on the contralateral side. The child is asymptomatic and active. What is your diagnosis, and how would you manage this?”
“A 4-year-old girl has an undisplaced buckle fracture of the proximal tibial metaphyseal region after a low-energy fall. You are about to apply an above-knee cast in the emergency department. The mother is anxious and asks whether her daughter will be 'normal again'. Outline what you would say, what consent you would obtain, and what your follow-up plan would be.”
Definition & Scope
- Cozen fracture = proximal tibial metaphyseal fracture in a child (peak age 3-8) followed by late valgus deformity
- Originally described by L. Cozen in 1953
- Late valgus appears 6-12 months after union, often despite a well-reduced fracture
- Affects a substantial proportion of children in this age group, with variable severity - the exact figure is not established
Mechanism Theories
- Cozen - asymmetric physeal stimulation from fracture hyperaemia (medial overgrowth)
- Ogden - lateral tibial tubercle apophysis overgrowth contributes to valgus moment
- Skak - soft-tissue tethering (pes anserinus, periosteum, intact fibula) on the medial side
- Salter-Harris V - sub-radiographic crush of the lateral physis slows lateral growth
Diagnosis & Imaging
- Acute diagnosis is clinical and radiographic - AP and lateral tibia including knee and ankle
- Long-leg standing film is the gold standard for measuring mechanical axis and tracking deformity
- MRI reserved for atypical or progressive cases to assess the physis for a bar
- Differential: Blount disease, physiological valgus, physeal bar, rickets, osteochondroma
Acute Management
- Cast immobilisation 4-6 weeks; moulded to hold the fracture
- Consider completing greenstick fractures and reducing in slight varus
- Split the cast if there is any concern about swelling - watch for compartment syndrome
- Counselling at presentation is the single most important intervention
Late Valgus Management
- Observation is the default in the skeletally immature child
- Document and counsel the family; serial clinical and radiographic review every 6 months
- Most cases spontaneously remodel over 2-3 years, but the proportion is not established and correction is not predictable
- Hemi-epiphysiodesis if growth remains and deformity persists; osteotomy only at maturity
Pitfalls & Pearls
- Do NOT offer a corrective osteotomy in the immature child - osteotomy has been ABANDONED for recurrent valgus ('up to 50%' is conventionally quoted but not established)
- Improvement is not normalisation: at 15 years the mechanical axis stayed lateral in EVERY patient (mean 15 mm) and the injured tibia OVERGREW (mean 9 mm)
- Document the counselling about Cozen phenomenon at the first visit
- Compare the injured and uninjured sides; asymmetry is more significant than absolute valgus
- Re-examine at 12-24 hours for compartment syndrome - the three As (Analgesia, Anxiety, Agitation) are red flags in children
Evidence Base and Key Trials
Fracture of the proximal portion of the tibia in children followed by valgus deformity
- Original description of post-traumatic valgus deformity following proximal tibial metaphyseal fracture in children
- Cozen proposed asymmetric physeal stimulation from fracture hyperaemia as the mechanism
- Documented a series of children in whom valgus appeared 6-12 months after the fracture
- Cautioned against premature corrective osteotomy, recognising the natural remodelling potential
Valgus deformity following proximal tibial metaphyseal fracture in children
- Seven children with proximal tibial metaphyseal fractures showing primary valgus angulation and MEDIAL cortical diastasis, followed 18 months to 11 years, all treated non-operatively in plaster
- Six had radiological signs of soft-tissue interposition MEDIALLY IN THE FRACTURE GAP - note the direction: medial interposition blocking reduction, not lateral tethering
- In those six the valgus angulation PROGRESSED during the first year DESPITE clinical healing - progression after union is expected, not a sign of mismanagement
- From 1 to 2 years after injury the deformity slowly regressed through corrective longitudinal growth
- Concluded that ROUTINE SURGERY TO REMOVE THE INTERPOSED SOFT TISSUE IS NOT JUSTIFIED
Posttraumatic tibia valga in children. A long-term follow-up note
- SEVEN patients, re-evaluated radiographically an average of 15 years 3 months after injury (range 10 to nearly 20 years) - the definitive long-term follow-up, and the same seven reported by the institution in 1986
- EVERY patient had spontaneous improvement of the metaphyseal-diaphyseal and mechanical tibiofemoral angles, and most of the correction occurred at the proximal tibia
- ⚠️ BUT improvement was not normalisation: the mechanical axis remained LATERAL to the centre of the knee in EVERY patient, mean deviation 15 mm (range 3 to 24 mm)
- ⚠️ The affected tibia was LONGER than the contralateral side in EVERY patient, mean limb-length discrepancy 9 mm (range 3 to 18 mm) - the injured leg OVERGROWS
- Knee and ankle function were assessed formally (Cincinnati and AOFAS rating systems) rather than by radiograph alone
- ⚠️ The functional results are the part most often left out: the knee score was excellent in only FIVE of the seven and FAIR in two, and ONE OF THE SEVEN UNDERWENT A TIBIAL OSTEOTOMY AT THE AGE OF SIXTEEN for lateral knee pain attributed to the malalignment
- Ankle scores were excellent in three and good in four - no ankle was rated fair or poor
Tibia valga caused by asymmetrical overgrowth following a nondisplaced fracture of the proximal tibial metaphysis
- ⚠️ This is a SINGLE CASE REPORT, not a series - one child who developed tibia valga after a NONDISPLACED fracture that healed in a normal position
- Its contribution is mechanistic and elegant: GROWTH ARREST LINES in the proximal tibial metaphysis were used to demonstrate where the growth actually came from
- Those lines showed the valgus was caused by OVERGROWTH OF THE MEDIAL portion of the proximal tibial physis - not by lateral growth arrest or by malunion
- Confirms the clinical paradox that a fracture healed in perfect position can still produce a striking late deformity
Cozen's deformity: resolved by guided growth
- 19 patients and effectively 24 Cozen's phenomena - the authors state this is the LARGEST SERIES REPORTED IN THE LITERATURE - treated by guided growth tethering the proximal MEDIAL physis; mean follow-up from injury 7.3 years, ages 2 to 13.6 at intervention
- ⚠️ States plainly that corrective osteotomy HAS BEEN ABANDONED because of frequent complications including recurrent valgus
- ⚠️⚠️ And that while spontaneous remodelling has been reported, IT IS NOT PREDICTABLE - the single most important qualifier to the 'just wait, it always corrects' teaching
- Correction of the mechanical axis and medial proximal tibial angle was achieved in ALL BUT ONE patient
- Guided growth is not free of recurrence: FIVE recurrences in FOUR patients, four of which corrected with repeat tethering
- TWO patients OVERCORRECTED because the family did not return for timely follow-up, and both needed lateral tethering to bring them back to neutral
- Limb-length inequality at follow-up 0.1 to 1.5 cm (mean 0.5 cm); ten patients reached skeletal maturity needing no further treatment