The commonest surface osteosarcoma — low grade, chemotherapy-sparing, but unforgiving of a marginal excision
- A painless, slowly enlarging, hard mass fixed to the back of the distal femur in an adult, sometimes limiting knee flexion, is parosteal osteosarcoma until proven otherwise.
- Ossification is MOST mature centrally and least mature peripherally — the reverse of myositis ossificans, which matures at its periphery.
- The lucent cleavage plane (string sign) between mass and cortex is characteristic but neither universal nor pathognomonic.
- MRI is mandatory before surgery: it defines medullary invasion (present in up to a quarter) and identifies non-ossified soft-tissue nodules that flag dedifferentiation and dictate the biopsy target.
- MDM2 and CDK4 amplification (FISH or immunohistochemistry) distinguishes parosteal osteosarcoma from myositis ossificans, osteochondroma and fibrous dysplasia when histology looks deceptively bland.
- Treatment of pure low-grade disease is wide en-bloc resection alone; chemotherapy adds nothing. Never shell the lesion out — intralesional or marginal excision leads to local recurrence and progressive dedifferentiation.
- “Osteochondroma has cortical AND medullary continuity with the host bone; parosteal osteosarcoma does not — it sits on the cortex.
- “The lesion may wrap circumferentially around the metaphysis over time; assess the neurovascular bundle and the whole cortical circumference on axial imaging.
- “Grade 2 histology or medullary invasion alone does not mandate chemotherapy; a discrete high-grade (grade 3) component does.
- “Hemicortical resection with allograft or vascularised fibula is appropriate only when the medullary canal is free and margins can be guaranteed.
- “Late recurrence 10 to 20 years after inadequate excision is well described — surveillance must be long.
Definition, Epidemiology and Biology
Parosteal osteosarcoma is a low-grade osteosarcoma arising from the outer fibrous layer of the periosteum, growing outward onto the cortical surface rather than from the medullary cavity. It is the commonest of the surface osteosarcomas and accounts for roughly 4 to 6 per cent of all osteosarcomas.
Who gets it. Incidence peaks in the third and fourth decades, a decade or two older than conventional intramedullary osteosarcoma, which peaks in adolescence. Most published series show a slight female predominance. It is reported from the second to the seventh decade, and a paediatric case should prompt careful review of grade.
Where. Sites in approximate order of frequency:
- Approximate share
- About two thirds
- Comment
- The classic location; mass sits in the popliteal fossa
- Approximate share
- Roughly 10%
- Comment
- Posteromedial surface
- Approximate share
- Roughly 10%
- Comment
- Beware axillary neurovascular relations
- Approximate share
- Remainder
- Comment
- Rare and easily mistaken
Biology. Supernumerary ring chromosomes derived from 12q13-15 carry amplification of MDM2 and CDK4. The same amplicon underlies low-grade central osteosarcoma and well-differentiated/dedifferentiated liposarcoma, a shared low-grade osteosarcoma family.
Biopsy and Pathology
Biopsy follows staging. Biopsy is performed after complete staging imaging, never before: the biopsy tract distorts MRI, and the tract must be planned to lie within the eventual resection field. It is done in, or under the direct governance of, the unit that will perform the definitive resection, and the case is discussed at the sarcoma MDT.
Where to put the needle. Parosteal osteosarcoma is heterogeneous. A core through the dense ossified centre or base returns bland spindle cells and well-formed trabeculae, and risks a false reassurance of low grade; the dedifferentiated focus sits in the unossified soft-tissue nodule, the commonest site of high-grade change. Target the non-mineralised, MRI-bright, enhancing component, and sample generously, including any radiolucent or soft-tissue-rich zone.
Technique. Image-guided core needle biopsy is standard, and a trephine may be needed for the ossified portion. If cores are non-diagnostic, open biopsy goes through a longitudinal incision in line with the definitive approach. Send fresh tissue for cytogenetics/FISH if the diagnosis is uncertain.
Macroscopic. A hard, lobulated, greyish-white mass with a broad cortical base; the cut surface shows dense bone with fibrous septa. Any soft, fleshy, tan or haemorrhagic area is suspicious for dedifferentiation and must be sampled separately and labelled. The entire specimen must be sampled, as dedifferentiation may only be found on whole-specimen pathology after resection.
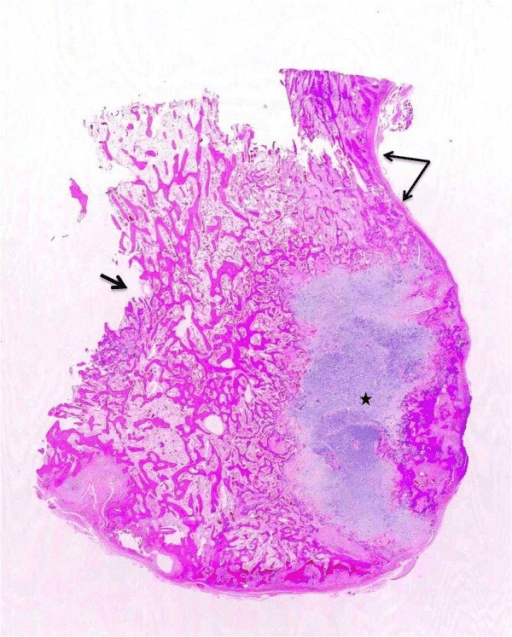
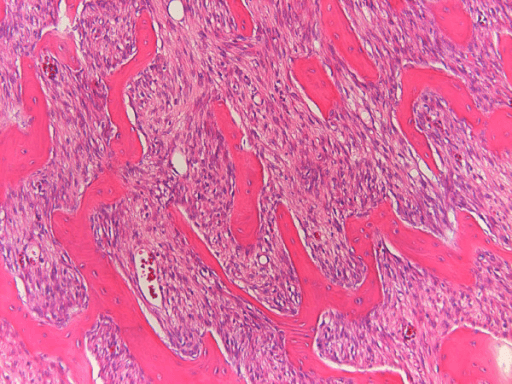
Microscopic. Well-formed, parallel, often anastomosing woven bone trabeculae lie in a hypocellular, bland spindle cell fibrous stroma, and the "streamer" or "picket-fence" pattern of parallel trabeculae is characteristic. Unhelpfully, the trabeculae may show osteoblastic rimming and may mimic normal bone or fibrous dysplasia.
Grade. Minimal cytological atypia and rare mitoses make the tumour grade 1, occasionally grade 2 with increased cellularity and atypia. Dedifferentiated areas show a high-grade sarcoma, whether conventional high-grade osteosarcoma, fibrosarcoma-like or undifferentiated pleomorphic sarcoma-like, with marked pleomorphism and mitotic activity.
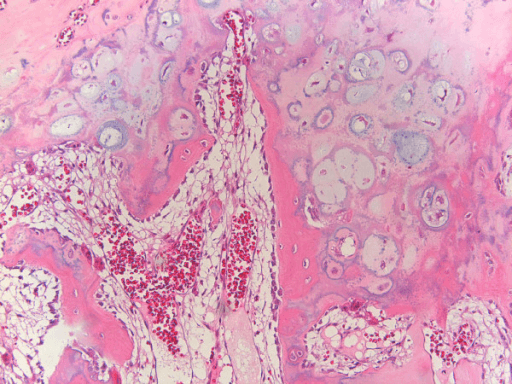
The cartilage trap. A cartilaginous cap is present in a minority and does not equal osteochondroma: the cap is disorganised and lacks the underlying medullary continuity.
Ancillary tests. MDM2 amplification by FISH is the most reliable discriminator, positive in the large majority of parosteal osteosarcomas. MDM2 and CDK4 immunohistochemistry is highly supportive when both show nuclear positivity, but its sensitivity is lower than FISH, so a negative immunostain does not exclude the diagnosis. Reactive lesions (myositis ossificans, fracture callus), osteochondroma and fibrous dysplasia are negative, which is how testing resolves the bland-histology dilemma.
MDM2 and CDK4 Immunohistochemistry in the Differential Diagnosis of Low-Grade Osteosarcoma
- 72 low-grade osteosarcomas (parosteal and low-grade central) against 107 fibrous or fibro-osseous lesions of bone or paraosseous soft tissue
- MDM2 and/or CDK4 immunoreactivity was present in 89 per cent of low-grade osteosarcomas
- ALL 107 benign fibrous and fibro-osseous lesions were negative
- The 23-case high-grade control group - 20 CONVENTIONAL high-grade osteosarcomas plus three other sarcomas - was ALSO negative
- Immunohistochemistry results were consistent with MDM2/CDK4 amplification measured by CGH array, FISH and quantitative PCR
Parosteal Osteogenic Sarcoma
- 79 patients: MORE FEMALES than males, most in the second to fourth decades
- 68 per cent involved the POSTERIOR aspect of the lower femoral shaft - the origin of the classic teaching
- SEVEN of the 79 (9 per cent) had foci of high-grade osteosarcoma within an otherwise typical parosteal tumour
- Six of the 79 showed medullary cavity involvement at surgery
- Of 31 patients treated by EXCISION, only four needed no further therapy; 3 of 10 treated by resection recurred; 4 of 27 amputees developed pulmonary metastasis
- Histologically 'active' tumour and medullary involvement both worsened prognosis
Staging and Grading
Surgical staging. Enneking (MSTS) staging is used for surgical decision-making. Low grade is stage I, intracompartmental IA and extracompartmental IB, and most parosteal osteosarcomas are stage IB because a surface tumour with a soft-tissue mass is by definition extracompartmental. A grade 3 focus defines dedifferentiation, and dedifferentiated disease is stage II. AJCC staging incorporates size, grade and metastasis, and low-grade non-metastatic disease sits in stage I.
Work-up. The staging studies are:
- Local MRI of the whole bone
- CT of the primary
- CT chest, which is required: pulmonary metastasis at presentation is rare in pure low-grade disease but is the pattern of spread when it occurs, and a baseline is needed
- Whole-body imaging considered if the grade is uncertain
Clinical Presentation and Examination
History. The complaint is a painless or minimally painful hard swelling, present for months to years before presentation. Long symptom duration is typical and is itself a clue to low-grade biology. A trauma history is often reported but is usually incidental; do not let it anchor you to myositis ossificans.
Mechanical symptoms. A posterior distal femoral mass physically blocks the last arc of flexion. Patients describe an inability to squat or kneel rather than pain.
What should change your thinking. Pain, if present and recent, or a sudden change in growth rate, raises the question of dedifferentiation. Systemic upset, night pain and weight loss are absent, and their presence should prompt reconsideration.
Inspection. With the patient prone, knees extended and then flexed to 90 degrees, look for popliteal fullness and asymmetry of the posterior thigh contour. The skin is normal: in low-grade disease there is no erythema and there are no dilated veins.
Palpation. Stand on the side of the lesion, with the patient prone and the hamstrings relaxed, and palpate deep to the hamstrings onto the posterior femoral shaft. The mass is bony hard, non-tender, immobile and fixed to bone; it does not move independently of the femur. Define its longitudinal and circumferential extent by rolling the fingers around the shaft, since circumferential wrap changes the operation.
Range of motion. With the patient supine and the hip flexed to 90 degrees, passively flex the knee, record the flexion arc and compare with the opposite side. A hard, abrupt bony block, at 100 degrees for example, with no springy end-feel and no effusion, points to an extrinsic posterior mass rather than intra-articular pathology.
Neurovascular assessment. Test tibial and common peroneal nerve motor and sensory function, and the distal pulses. Direct nerve involvement is unusual in low-grade disease (the tumour displaces rather than invades), but a fixed neurological deficit suggests dedifferentiation or a different diagnosis.
Regional nodes. Palpate the popliteal and inguinal basins. Nodal disease is not a feature of parosteal osteosarcoma, and its presence redirects the differential.
A young adult with a hard, painless posterior distal femoral mass and a fixed bony block to terminal knee flexion, and a normal examination otherwise, is the classic viva stem. The correct first answer is orthogonal plain radiographs, not an MRI-first reflex — the film usually makes the diagnosis.
Imaging
Radiographs. Request anteroposterior and true lateral views of the distal femur, plus the whole bone.
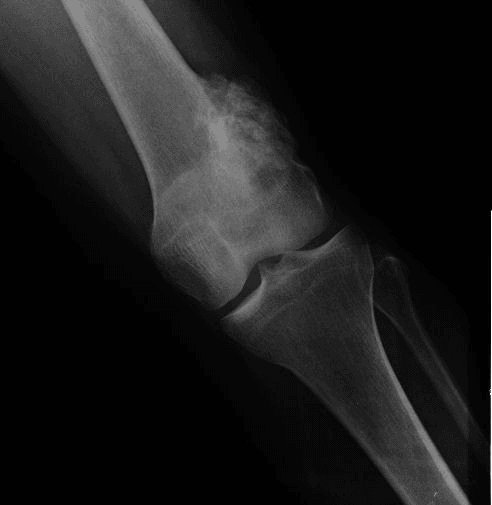
Five features make up the radiographic picture:
- Densely ossified, lobulated mass applied to the cortical surface, often described as cauliflower-like, with a broad base of attachment.
- Reverse zonation. Ossification is most dense and most mature at the centre, becoming fuzzy and immature at the periphery. Myositis ossificans does the opposite.
- The string sign. A thin radiolucent line, 1 to 3 mm wide, representing residual periosteum between the mass and the underlying cortex, best seen at the base on the tangential (lateral) view. It is seen in a minority to about half of cases and is often incomplete. It is suggestive but not pathognomonic, and it is typically lost as the lesion matures and fuses to cortex.
- Intact underlying cortex in early disease, with cortical thickening and later frank medullary permeation as the lesion advances.
- No aggressive periosteal reaction: no Codman triangle and no sunburst spiculation in pure low-grade disease. Their appearance suggests high-grade surface osteosarcoma or dedifferentiation.
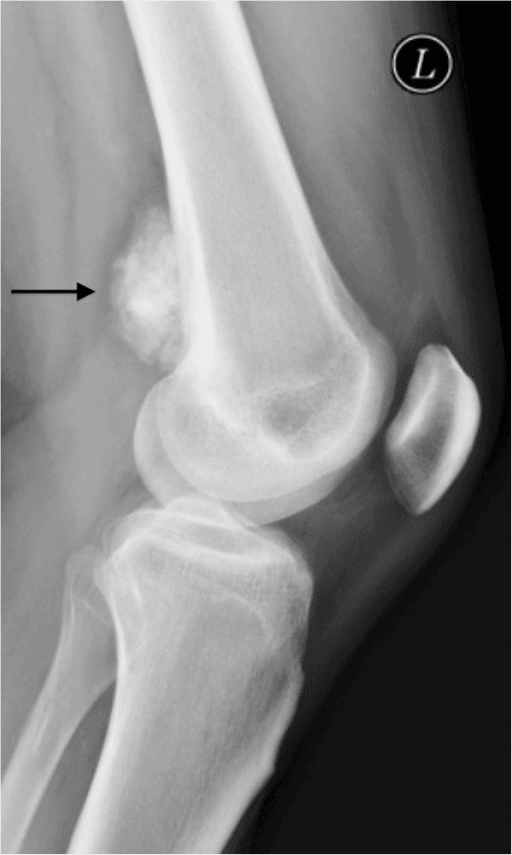
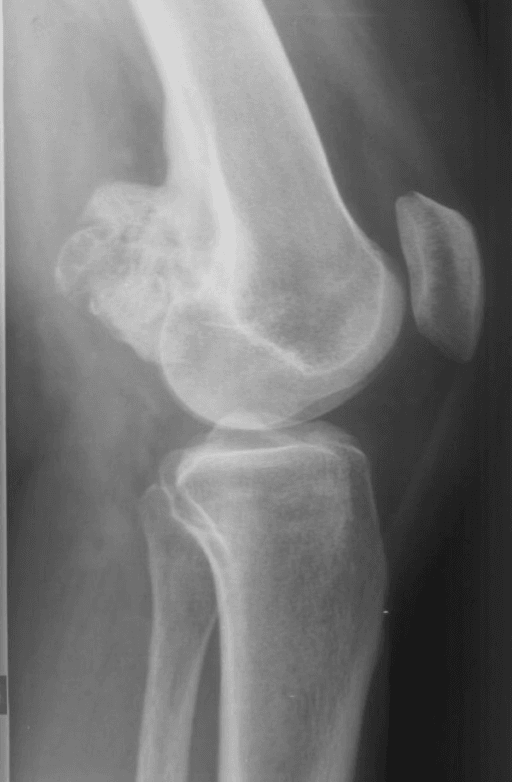
CT. CT best demonstrates the pattern and gradient of mineralisation and the broad cortical base. It confirms the absence of corticomedullary continuity, excluding osteochondroma, and this single axial observation settles that differential. It also defines circumferential wrap around the metaphysis for surgical planning and, where relevant, cortical breach.
MRI is mandatory. Plain films and CT define the ossified mass; only MRI shows medullary invasion and non-ossified nodules. Without it, the surgeon plans a hemicortical resection through tumour, and the pathologist finds a high-grade component that was never biopsied. Image the whole involved bone with axial, coronal and sagittal T1, fluid-sensitive (T2 fat-saturated or STIR) and post-gadolinium fat-saturated T1 sequences, and read them against these questions:
- Sequence
- Axial and sagittal T1
- Finding and consequence
- Replacement of normal fatty marrow signal by intermediate signal tumour. Present in up to a quarter of cases. Excludes hemicortical resection; mandates segmental or extra-articular resection
- Sequence
- T2 fat-saturated, post-contrast T1
- Finding and consequence
- A discrete high-signal, avidly enhancing unmineralised nodule within or beyond the ossified mass suggests dedifferentiation. This is the biopsy target
- Sequence
- Coronal T1 whole bone
- Finding and consequence
- Defines resection level; look for skip lesions (rare here)
- Sequence
- Axial T2 and post-contrast
- Finding and consequence
- Popliteal vessels, tibial and peroneal nerves; fat plane preserved or effaced
- Sequence
- Sagittal
- Finding and consequence
- Rare; extension into the knee mandates extra-articular resection
Marrow is not grade. Marrow involvement in parosteal osteosarcoma reflects local advance, not necessarily dedifferentiation. What it does and does not change is set out under Management.
Nuclear medicine. Bone scintigraphy shows intense uptake but adds little diagnostically, because a densely ossifying benign lesion is also hot. FDG-PET is not required routinely. Where it is used, marked focal hypermetabolism disproportionate to the bland ossified mass may direct biopsy toward a dedifferentiated focus.
Differential Diagnosis
Two of the ways parosteal osteosarcoma is mishandled start here. Calling it myositis ossificans leads to observation of a sarcoma. Calling it osteochondroma gets it shelled out, and a marginal "excision of exostosis" leaves tumour behind.
- Key imaging discriminator
- Broad-based ossified mass on intact cortex; mature centre, immature rim; string sign; no medullary continuity
- Age / history
- 3rd to 4th decade; painless mass over years, block to flexion
- Consequence of getting it wrong
- Marginal excision leads to recurrence and dedifferentiation
- Key imaging discriminator
- Cortical AND medullary continuity with host bone; cartilage cap on MRI
- Age / history
- Adolescent to young adult; often incidental
- Consequence of getting it wrong
- Over-treatment of a benign lesion, or under-treatment of sarcoma
- Key imaging discriminator
- Peripheral mature ossified rim, immature centre; separates from cortex over time; rapid early evolution then stabilises
- Age / history
- Trauma or intramuscular injection; painful early, settles
- Consequence of getting it wrong
- Unnecessary radical surgery if biopsied early and misread as sarcoma
- Key imaging discriminator
- Diaphyseal; cortical saucerisation, perpendicular spiculation, chondroid matrix; less dense ossification
- Age / history
- Adolescent to young adult
- Consequence of getting it wrong
- Missing an intermediate-grade tumour that may warrant chemotherapy
- Key imaging discriminator
- Surface mass with large unmineralised soft-tissue component, aggressive periosteal reaction
- Age / history
- Any age; shorter history, painful
- Consequence of getting it wrong
- Omitting chemotherapy from a high-grade tumour
- Key imaging discriminator
- Classic parosteal mass PLUS discrete non-ossified enhancing nodule or cortical destruction
- Age / history
- Often long-standing lesion, recent change or recurrence
- Consequence of getting it wrong
- Under-treatment: needs full high-grade protocol
- Key imaging discriminator
- Small hands and feet lesions; cartilage cap, no cortical destruction
- Age / history
- Young adults, digits
- Consequence of getting it wrong
- Radical surgery for a benign process
Myositis ossificans matures from outside in; parosteal osteosarcoma matures from inside out. Combine with the cortical relationship: myositis ossificans drifts away from cortex, osteochondroma is continuous with cortex and marrow, parosteal osteosarcoma is stuck onto intact cortex.
Management
Establish grade and marrow status BEFORE the first cut. Pure low-grade disease is cured by an adequate wide en-bloc resection alone; a dedifferentiated component converts the case to a conventional high-grade osteosarcoma pathway with neoadjuvant chemotherapy. Every management error in this disease traces back to a lesion excised without staging or without a representative biopsy.
Grade decides the chemotherapy; marrow decides the operation. A dedifferentiated (grade 3) component is the only firm indication for chemotherapy in parosteal disease, and chemotherapy has no established role in pure low-grade parosteal osteosarcoma. Whether marrow invasion should also bring chemotherapy is argued under Controversies.
Staging first. Unplanned excision of an unstaged lesion is the commonest management error in this disease.
Matching the operation to the findings. Read the axial sequences for circumferential wrap and marrow signal change, then match the scenario:
- Systemic therapy
- None
- Operation
- Hemicortical / sagittal resection with reconstruction (allograft, vascularised fibula, or bone transport) where a wide margin is achievable
- Systemic therapy
- None
- Operation
- Segmental (intercalary) or joint-sacrificing resection with endoprosthetic or biological reconstruction
- Systemic therapy
- None if low grade
- Operation
- Extra-articular resection
- Systemic therapy
- Full neoadjuvant plus adjuvant high-grade osteosarcoma chemotherapy (methotrexate, doxorubicin, cisplatin backbone)
- Operation
- Wide resection, margins as above
- Systemic therapy
- Per grade
- Operation
- Amputation as the reliable oncological option
- Systemic therapy
- Per grade
- Operation
- Metastasectomy where complete resection is achievable
It is oncologically acceptable only when the medullary canal is uninvolved on MRI, the tumour occupies less than the full circumference, and the planned cut delivers a genuine cuff of normal cortex on every surface. If any of these is in doubt, do a segmental resection.
Dedifferentiated disease. The wide resection is done between the cycles of neoadjuvant and adjuvant chemotherapy. Margins are planned exactly as for low-grade disease: chemotherapy does not license a narrower margin.
Margins. A positive margin on definitive histology mandates early re-resection, not surveillance and not radiotherapy. Re-resection to negative margins restores much of the survival advantage.
Radiotherapy has no established role. Osteosarcoma is relatively radioresistant, and the low-grade variant is curable surgically. Radiotherapy is reserved for genuinely unresectable disease, positive margins where re-resection is impossible, or palliation; it is of limited efficacy and should be framed to patients as such.
Operative Technique: Posterior Distal Femoral Lesion
The sequence below is for a wide en-bloc resection of the classic lesion.
Prone on a radiolucent table, with a tourniquet high on the thigh (often not inflated for a posterior approach, given vessel proximity). Prepare the whole limb and ipsilateral hemipelvis, with the foot in a drape bag so the knee can be flexed and extended intraoperatively. If a vascularised fibula is planned, the contralateral limb is available, with a separate team and set-up for the harvest.
Staging MRI and CT displayed, and an image intensifier. Oscillating and reciprocating saws and osteotomes, with a bone-cutting jig, navigation or patient-specific instrumentation if hemicortical resection is planned. Vascular instruments, vessel loops and slings. Allograft thawed and available, or an endoprosthesis in the full range of sizes with a plan B, and frozen-section pathology available.
Mark the biopsy tract for en-bloc excision with the specimen. Define the proximal and distal osteotomy levels from MRI with a defined margin, commonly 2 cm or more beyond marrow signal change, measured against a fixed landmark such as the joint line and confirmed intraoperatively with the image intensifier. Decide the reconstruction, and its salvage, in advance.
A longitudinal posterior midline incision incorporating the biopsy tract. Identify and protect the posterior cutaneous nerve of the thigh, then develop the interval between the hamstrings, retracting biceps femoris laterally and semitendinosus and semimembranosus medially, to reach the popliteal fossa.
The tibial nerve is identified most superficially in the fossa, then the common peroneal nerve along the medial border of biceps femoris; sling both. Deep to the tibial nerve lies the popliteal vein, and deepest the popliteal artery on the posterior capsule. Mobilise the neurovascular bundle off the tumour pseudocapsule sharply, staying on the tumour side of the fat plane, and ligate geniculate branches deliberately. Never dissect into the tumour to save a millimetre of vessel adventitia: if the artery is encased, plan resection and interposition graft, or amputation.
Detach the medial and lateral heads of gastrocnemius from the femoral condyles as needed, and osteotomise at the predetermined levels. For a hemicortical resection, use the planned jig or navigation to cut a sagittal or coronal window of cortex carrying the tumour with a normal cortical margin all round. Deliver the specimen untouched and unopened, oriented and marked for the pathologist, with the biopsy tract attached, and send the marrow margin for frozen section.
The popliteal artery and vein, tibial nerve, common peroneal nerve (most vulnerable where it crosses the fibular neck if the dissection extends distally), medial and lateral sural cutaneous nerves, superior geniculate vessels, and the physis in the rare skeletally immature patient.
A hemicortical defect takes a structural allograft, vascularised fibula or bone transport, fixed with a plate spanning the defect and neutralising torsion. An intercalary defect takes an allograft-plate composite, a vascularised fibula (alone or intercalated within allograft) or bone transport; a joint-sacrificing resection takes a distal femoral endoprosthesis. Protect every construct with a plate long enough to bridge stress risers by a minimum of two cortical diameters.
Layered closure over suction drainage, avoiding tension across the popliteal fossa, and a hinged knee brace. After an endoprosthesis, mobilise early and weight-bear as the construct allows. After a biological reconstruction, protect weight-bearing for 3 to 6 months, with radiographs at 6-weekly intervals until union. Chemoprophylaxis for venous thromboembolism per unit policy.
The pitfalls are excising through the pseudocapsule, failing to excise the biopsy tract, underestimating circumferential wrap on axial imaging, and an inadequate proximal marrow margin. Salvage for a positive margin on definitive histology is early re-resection, as set out under Management.
Dedifferentiation
How often. Dedifferentiation occurs in roughly 15 to 25 per cent of cases, but be clear which denominator you are quoting, because the two commonly cited figures count different things. Synchronous dedifferentiation, present in the resection specimen at diagnosis, was 7 of 79 (9 per cent) in the original Mayo series. The higher 15 to 25 per cent range counts tumours that harbour or later develop a high-grade component, so it includes metachronous dedifferentiation emerging in a recurrence, classically after inadequate primary excision. An examiner asking "what proportion dedifferentiate?" is usually asking the second question; an examiner asking "what will the pathologist find?" is asking the first.
What it is. Dedifferentiation is defined by a discrete high-grade sarcomatous component juxtaposed against the low-grade parosteal tumour, and the transition is typically abrupt. The high-grade component retains MDM2 amplification, confirming its clonal origin from the low-grade lesion. In practice, amplification identifies the low-grade lineage of a dedifferentiated tumour whose high-grade component looks like any conventional osteosarcoma.
Recognising it. The red flags, with how each is caught and acted on:
- Domain
- Clinical
- Mechanism
- High-grade clone outgrowing the indolent ossified lesion
- Prevent or detect by
- Serial clinical review of any parosteal lesion under surveillance
- Action if present
- Restage with MRI and chest CT; biopsy the suspicious zone
- Domain
- Clinical
- Mechanism
- Emergence of a discrete high-grade sarcomatous component (15 to 25 per cent of cases)
- Prevent or detect by
- Documented size at each review rather than impression
- Action if present
- Re-image and re-biopsy targeting the growing area
- Domain
- Imaging
- Mechanism
- Dedifferentiated tissue does not ossify, so it appears as non-ossified enhancing tumour against the dense stalk
- Prevent or detect by
- Contrast-enhanced MRI, not radiographs alone
- Action if present
- Targeted biopsy of the enhancing nodule, not the ossified mass
- Domain
- Imaging
- Mechanism
- High-grade component invades cortex and medulla, unlike the surface-based low-grade lesion
- Prevent or detect by
- MRI assessment of marrow and cortex in every case at diagnosis
- Action if present
- Treat as high-grade until biopsy proves otherwise
- Domain
- Pathological
- Mechanism
- A single low-grade core from a heterogeneous tumour misses the abrupt high-grade transition
- Prevent or detect by
- Image-directed multi-site sampling; generous specimen review; MDM2 amplification retained in both components
- Action if present
- Rebiopsy or extensive resection specimen sampling before committing to surgery alone
- Domain
- Pathological and clinical
- Mechanism
- Metachronous dedifferentiation classically follows intralesional or marginal primary excision
- Prevent or detect by
- Wide negative-margin resection at the index operation, in a sarcoma unit
- Action if present
- Restage, biopsy, and treat on a conventional high-grade osteosarcoma protocol with neoadjuvant and adjuvant chemotherapy plus wide resection
Prognosis falls substantially, approaching that of conventional high-grade osteosarcoma, with metastatic risk concentrated in the lungs. Treatment follows the conventional high-grade osteosarcoma protocol set out under Management.
Low Grade Parosteal Osteosarcoma: Clinical and Oncological Outcomes
- 22 patients with low-grade parosteal osteosarcoma treated by limb salvage and reconstructed with bone allograft, 1980 to 2010
- Mean age 32 years (range 10-59); mean follow-up 93 months (range 8-237)
- Ten-year OVERALL SURVIVAL 91 per cent (95% CI 79-100)
- Four patients developed local recurrence - TWO of them reclassified as DEDIFFERENTIATED on the resection specimen
- Two developed distant recurrence, lung the only site
- Ten-year survival of the RECONSTRUCTION was only 65 per cent (95% CI 44-86)
Outcomes, Surveillance and Complications
Oncological outcome. Long-term survival by grade, margin and marrow status:
- Long-term survival
- Greater than 90%
- Comment
- Excellent; deaths are rare and usually follow recurrence with dedifferentiation
- Long-term survival
- Substantially reduced
- Comment
- High local recurrence; each recurrence risks higher grade
- Long-term survival
- Modestly reduced in some series
- Comment
- Not an indication for chemotherapy; is an indication for a bigger resection
- Long-term survival
- Comparable to conventional high-grade osteosarcoma
- Comment
- Lung metastases dominate
Surveillance. Local site imaging (radiograph, with MRI or CT as indicated by reconstruction) and CT chest at intervals of about 3 to 6 months for the first 2 to 3 years, then 6 to 12 monthly. Because recurrence 10 to 20 years after surgery is documented, follow-up should extend well beyond the 5-year point conventional for high-grade sarcoma, and patients must be told to report any new mass or pain at any time.
Complications. The table gives approximate frequency, prevention and management for each.
- Approximate frequency
- Low (single figures in specialist series)
- Prevention
- Adequate margin, biopsy tract excision, orientated specimen
- Management
- Re-staging, re-resection; reassess grade — recurrence is often higher grade
- Approximate frequency
- High
- Prevention
- Do not shell the lesion out
- Management
- Wide re-resection; consider amputation for repeated failure
- Approximate frequency
- Variable
- Prevention
- Frozen-section marrow margin, preoperative planning
- Management
- Early re-resection to negative margins
- Approximate frequency
- Roughly 10 to 30% for biological reconstructions
- Prevention
- Rigid long-plate fixation, vascularised augmentation, avoid gaps
- Management
- Bone grafting, revision fixation, vascularised fibula
- Approximate frequency
- Roughly 10 to 20%
- Prevention
- Long-plate protection, protected weight-bearing
- Management
- Revision fixation or graft exchange
- Approximate frequency
- Roughly 5 to 15%, higher with endoprosthesis and prior chemotherapy
- Prevention
- Prophylaxis, meticulous soft-tissue handling, avoid tension closure
- Management
- Debridement and antibiotics; two-stage revision or amputation for chronic infection
- Approximate frequency
- Uncommon with disciplined dissection
- Prevention
- Identify and sling nerves first; vascular team on standby
- Management
- Immediate repair or graft; orthosis for foot drop, later tendon transfer
- Approximate frequency
- Increases with time and youth
- Prevention
- Appropriate stem fixation, activity counselling
- Management
- Revision arthroplasty
- Approximate frequency
- Common after posterior approach
- Prevention
- Early graded physiotherapy
- Management
- Physiotherapy; manipulation or arthrolysis if persistent
Guidelines, Registries & Global Practice
Global epidemiology. Osteosarcoma incidence is broadly similar worldwide at approximately 3 per million per year, with parosteal variants a consistent 4 to 6 per cent of that total across North American, European, Asian and Latin American series. Presentation stage, however, is not uniform: in settings with limited access to cross-sectional imaging and specialist pathology, parosteal osteosarcoma is more often excised as a presumed exostosis and presents to the sarcoma service as a recurrence.
Society guidance — where it genuinely addresses this topic
- What it says that matters here
- Bone sarcomas should be managed in reference centres by a multidisciplinary team; biopsy performed by or with the treating surgical team; low-grade osteosarcoma (including parosteal) treated by surgery alone, with chemotherapy reserved for high-grade or dedifferentiated disease
- What it says that matters here
- Explicitly separates low-grade (parosteal, low-grade central) osteosarcoma — wide excision alone, with chemotherapy only if high-grade elements are identified in the specimen — from high-grade disease treated with neoadjuvant and adjuvant chemotherapy
- What it says that matters here
- Suspected bone sarcoma referred to a specialist bone sarcoma centre before biopsy; imaging pathway of radiograph first, then MRI of the whole bone
- What it says that matters here
- Unplanned excision of a bone tumour is a recognised avoidable harm; radiograph interpretation with a low threshold for referral is the responsibility of the first clinician
- What it says that matters here
- Defines parosteal osteosarcoma as a low-grade surface osteosarcoma with MDM2/CDK4 amplification and recognises the dedifferentiated subtype
Registries. There is no implant registry directly relevant here, but national bone tumour registries (Rizzoli, Mayo, the Scandinavian Sarcoma Group registry, the Cooperative Osteosarcoma Study Group database) supply the outcome data that underpin the surgery-alone approach. National joint registries do contribute indirectly: AOANJRR, NJR and AJRR report the survivorship of tumour endoprostheses used for reconstruction, informing the counselling of a young adult about revision risk over decades.
Practice variation by resource setting
- High-resource settings: routine MRI whole bone, MDM2 FISH, navigation or patient-specific guides for hemicortical resection, vascularised fibula reconstruction.
- Middle-resource settings: MRI usually available but molecular testing may require referral; hemicortical resection performed on conventional planning; allograft supply may be limited, favouring endoprosthesis or bone transport.
- Limited-resource settings: radiograph and CT-led diagnosis; molecular confirmation unavailable; the priority is avoiding unplanned excision and achieving an oncologically clean operation, in which a well-executed amputation or a segmental resection with a simple reconstruction serves the patient better than an ambitious limb salvage without margin control.
Controversies & Areas of Uncertainty
The argument for. Some series associate marrow involvement with higher recurrence and a greater likelihood of finding high-grade foci on whole-specimen review.
The argument against. Multivariable analyses in the larger series identify grade, not marrow status, as the driver of metastasis and death, and reported outcome data suggest that medullary invasion in an otherwise low-grade tumour does not independently mandate chemotherapy. Chemotherapy has never been shown to benefit grade 1 disease.
Pragmatic position. Medullary invasion changes the operation (no hemicortical resection) and mandates exhaustive sampling of the resection specimen. It does not by itself trigger chemotherapy.
MCQ Practice Points
Q: Which imaging feature most reliably separates parosteal osteosarcoma from myositis ossificans?
A: The DIRECTION of zonation. Parosteal osteosarcoma ossifies most densely at its centre with an immature periphery; myositis ossificans has a mature ossified peripheral rim around an immature centre, and separates from the cortex as it matures. The string sign is supportive but is present in only a proportion of parosteal tumours.
Q: A densely ossified surface lesion of the distal femur shows continuity of the host medullary cavity with the lesion on axial CT. Diagnosis?
A: Osteochondroma. Corticomedullary continuity is the defining feature and effectively excludes parosteal osteosarcoma, which sits on an intact cortex. Assess the cartilage cap thickness on MRI for secondary chondrosarcoma if there is pain or growth after skeletal maturity.
Q: What is the role of chemotherapy in a grade 1 parosteal osteosarcoma with 1 cm of medullary invasion?
A: None. Grade determines systemic therapy and this tumour is grade 1. Medullary invasion determines the EXTENT OF RESECTION instead - it excludes hemicortical resection and mandates a segmental resection with an adequate marrow margin, confirmed by frozen section. Two different questions answered by two different variables; conflating them is the trap.
Q: Which molecular abnormality supports the diagnosis and is shared with well-differentiated liposarcoma?
A: Amplification of the 12q13-15 region carrying MDM2 and CDK4, present as supernumerary ring chromosomes. Demonstrated by FISH for MDM2 amplification or by MDM2/CDK4 immunohistochemistry. Reactive ossifying lesions and osteochondroma are negative - and so, importantly, is CONVENTIONAL high-grade osteosarcoma, which is what makes the stain useful for proving the low-grade lineage of a dedifferentiated tumour. Sensitivity of immunohistochemistry is about 89 per cent, so a negative stain does not exclude the diagnosis.
Q: What proportion of parosteal osteosarcomas contain or develop a high-grade component, and what does it change?
A: Roughly 15 to 25 per cent - but say which denominator you mean. That range counts tumours that harbour OR LATER DEVELOP a high-grade focus, so it includes metachronous dedifferentiation in a recurrence. Dedifferentiation present in the specimen AT DIAGNOSIS was 7 of 79, about 9 per cent, in the original Mayo series. Either way it converts management to a conventional high-grade osteosarcoma protocol - neoadjuvant and adjuvant chemotherapy plus wide resection - and substantially worsens prognosis.
Q: A patient had a posterior distal femoral 'exostosis' shelled out 8 months ago; histology was reported as low-grade osteosarcoma. What next?
A: Restage completely (MRI whole bone, CT chest), review the original histology and pathology specimen at the sarcoma centre with MDM2 testing, and plan wide re-resection of the tumour bed including the previous scar and drain sites. Surveillance alone is inadequate: recurrence after intralesional excision is frequent and is often higher grade than the index tumour. In the original Mayo series only 4 of 31 patients treated by simple excision needed no further therapy.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 32-year-old teacher presents with an 18-month history of a painless, slowly enlarging firm lump behind the right knee. She cannot kneel. Examination shows a hard, immobile mass deep to the hamstrings, fixed to the femur, with a bony block to knee flexion at 105 degrees, no effusion and normal neurovascular status. Take me through your approach.”
“The same patient's MRI shows a classic ossified posterior mass but also a 3 cm unmineralised, avidly enhancing nodule at its lateral margin, with high T2 signal and effacement of the fat plane against the popliteal vessels. There is 2 cm of marrow signal change in the distal femur. How does this change your plan?”
“A 40-year-old man is referred 10 months after a district general hospital excised a 'posterior distal femoral exostosis' through a limited posterior incision. Histology, reviewed late, reads low-grade osteosarcoma. He now has a firm, slightly tender fullness at the scar. What do you do?”
“A 28-year-old woman has a biopsy-proven grade 1 parosteal osteosarcoma of the posteromedial proximal tibia. MRI shows no marrow involvement and the tumour occupies about 40 per cent of the circumference over 7 cm. Would you perform a hemicortical resection, and how?”
Identity
- Commonest surface osteosarcoma; 4 to 6% of all osteosarcomas
- Low grade (grade 1, sometimes 2); arises from outer fibrous periosteum
- Third to fourth decade, slight female excess
- Posterior distal femoral metaphysis in about two thirds; then proximal tibia and proximal humerus
- MDM2 and CDK4 amplification from ring chromosomes of 12q13-15
Clinical
- Painless, slowly enlarging, bony hard mass fixed to bone over months to years
- Bony block to terminal knee flexion, no effusion, normal neurovascular examination
- New pain or accelerated growth suggests dedifferentiation
- Prone examination: define longitudinal and circumferential extent
Imaging signatures
- Densely ossified lobulated mass on a broad cortical base
- Reverse zonation — mature centre, immature periphery (opposite of myositis ossificans)
- String sign: thin lucent periosteal cleavage plane; suggestive, not universal
- No corticomedullary continuity (excludes osteochondroma)
- No Codman triangle or sunburst in pure low-grade disease
- MRI mandatory: medullary invasion in up to a quarter; non-ossified enhancing nodule equals dedifferentiation
Differential
- Osteochondroma — cortical and medullary continuity
- Myositis ossificans — peripheral maturation, separates from cortex, trauma history
- Periosteal osteosarcoma — diaphyseal, chondroblastic, intermediate grade, saucerised cortex
- High-grade surface osteosarcoma — grade 3, large soft-tissue component
- Dedifferentiated parosteal — low-grade tumour plus discrete high-grade focus
Pathology
- Parallel woven bone trabeculae in bland hypocellular fibrous spindle stroma
- Minimal atypia, rare mitoses; cartilage cap in a minority
- MDM2 FISH is the most reliable discriminator; MDM2/CDK4 immunohistochemistry supportive
- Sample the entire specimen — dedifferentiation may be focal
Treatment
- Pure low grade: wide en-bloc resection ALONE; no chemotherapy, no radiotherapy
- Hemicortical resection only if marrow free, less than circumferential, margin guaranteed
- Medullary invasion or circumferential disease: segmental or joint-sacrificing resection
- Dedifferentiated: full high-grade osteosarcoma chemotherapy protocol plus wide resection
- Never shell the lesion out; always excise the biopsy tract in continuity
- Positive margin on final histology: early re-resection, not surveillance
Outcome and surveillance
- Greater than 90% long-term survival for pure low-grade disease with clear margins
- Dedifferentiation in 15 to 25% and the strongest adverse prognostic factor
- Recurrence after inadequate excision is common and often higher grade
- Metastases are pulmonary; CT chest at staging and in follow-up
- Late recurrence 10 to 20 years out — extend surveillance well beyond 5 years
One-line traps
- Reverse zonation is the myositis ossificans discriminator
- Medullary invasion changes the operation, not the chemotherapy decision
- A grade 3 focus is the only firm chemotherapy trigger
- Biopsy the soft nodule, not the dense bone
- Refer before biopsy; the index operation is the treatment