Flexor-Tendon Imbalance Phenomena
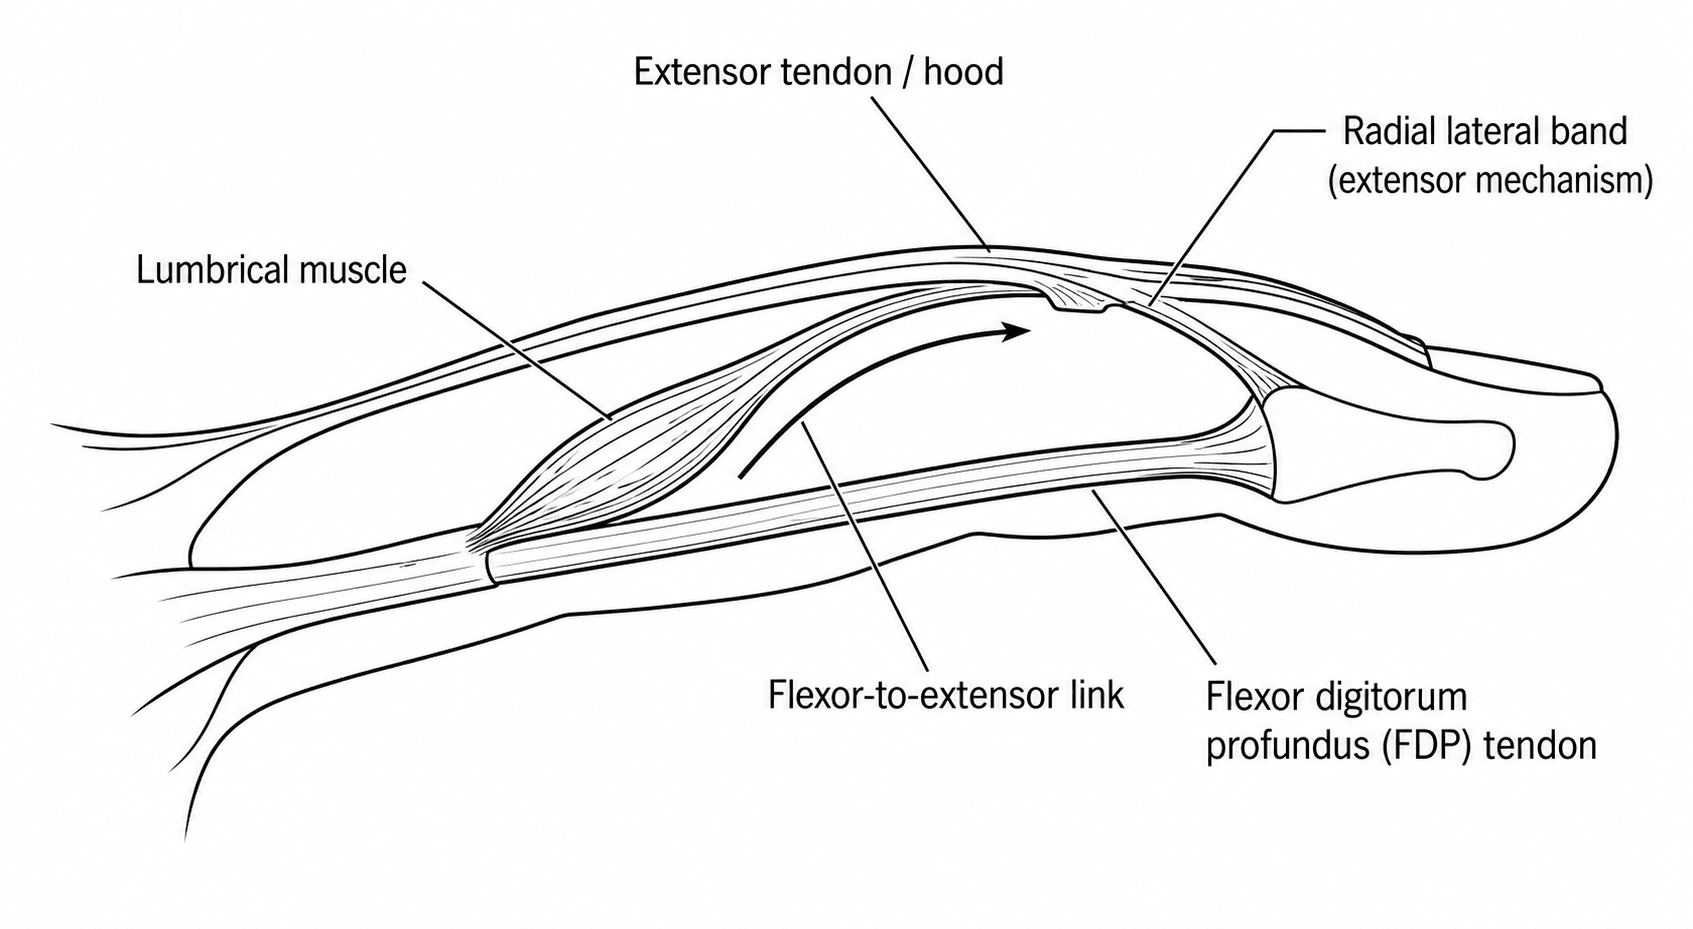
- One piece of anatomy explains both: the FDP tendons to the fingers arise from a SINGLE COMMON MUSCLE BELLY, and the LUMBRICALS arise from the FDP tendons and insert into the radial lateral band, bridging a flexor to an extensor.
- QUADRIGA: one FDP functionally too SHORT (over-advanced, over-tightened, tethered by adhesion, or sutured too proximally to an amputation stump) uses up the shared excursion, so the OTHER fingers cannot complete the fist - flexion lag and weak grip.
- LUMBRICAL-PLUS: an FDP that has lost effective distal pull while the lumbrical stays attached (division distal to the lumbrical origin, an over-LONG graft, a distal-finger amputation) diverts flexion effort through the lumbrical, so the IP joints PARADOXICALLY EXTEND.
- PREVENTION is the key clinical message: correct tension at repair and advancement, correct graft length at grafting, and at amputation no FDP sutured under tension to the stump.
- TREATMENT: release the over-tight or tethered FDP for quadriga; LUMBRICAL RELEASE or a flexor graft of appropriate length for lumbrical-plus.
- “Shared anatomy: FDP = one common muscle belly; lumbricals run FROM the FDP tendon TO the extensor lateral band. This explains BOTH phenomena.
- “QUADRIGA = an FDP too SHORT/tight/over-advanced/amputated-proximal → the OTHER fingers can't fully flex (weak grip, flexion lag). Named after the 4-horse chariot.
- “LUMBRICAL-PLUS = an FDP too LONG/slack/divided distal to lumbrical origin/over-long graft → PARADOXICAL IP EXTENSION on attempted flexion. Treat with lumbrical release or correct graft length.
The Shared Anatomy
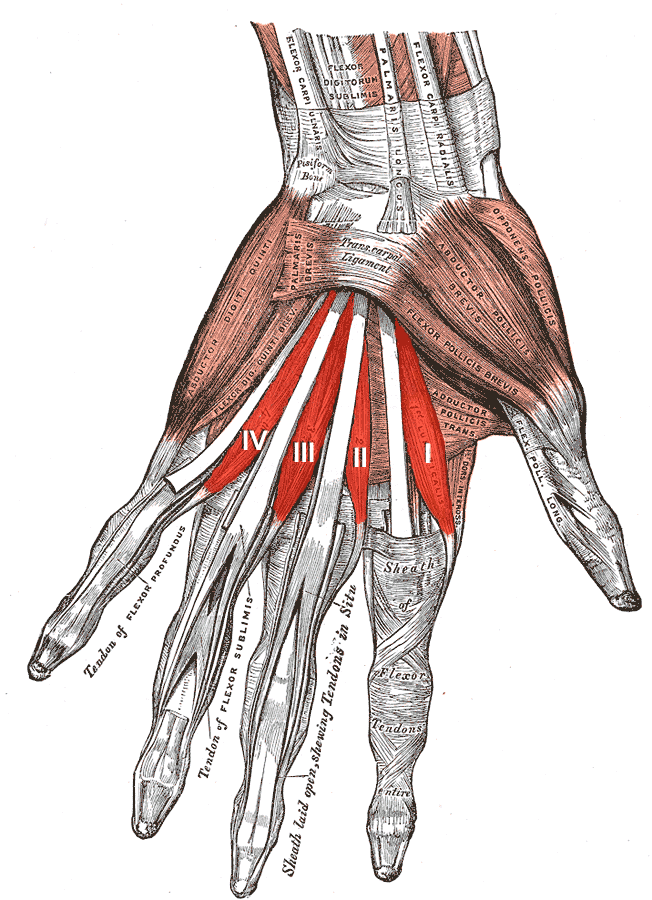
One common belly. The flexor digitorum profundus (FDP) tendons to the index, middle, ring and little fingers arise from a single common muscle belly, the index often the most independent. Their excursion is largely shared, so one finger's deep flexor cannot move fully independently of the others.
A muscle that bridges flexor to extensor. There are four lumbricals, and uniquely they have no bony origin. Each arises from the FDP tendons in the palm and inserts into the radial lateral band of the extensor mechanism, running from a flexor tendon to an extensor, which is precisely why force can be rerouted from FDP to extensor.
- The radial two, to the index and middle fingers, are unipennate and arise from a single FDP tendon
- The ulnar two, to the ring and little fingers, are bipennate and arise from two adjacent FDP tendons; by linking adjacent tendons they also reinforce the shared-excursion mechanics behind the quadriga
These two facts, shared FDP excursion and the flexor-to-extensor lumbrical, are the entire basis of the quadriga effect and the lumbrical-plus finger.
Quadriga Effect
What it is. The quadriga effect is loss of full active flexion and grip in the other fingers when one FDP is functionally too short. Because the tendons share a common belly, the over-tight tendon uses up its excursion, and the neighbouring fingers cannot complete the fist: a flexion lag and weak grip. The name comes from the Roman four-horse chariot, the quadriga, whose reins move together, so restraining one restrains all.
How the FDP is made too short.
- Over-advanced or over-tightened at repair
- Tethered by adhesion
- Sutured too proximally, or under tension, to the stump after amputation
Treatment. Release the over-tight or tethered tendon, by tenolysis or by revising an over-advanced repair or the amputation tension, to restore the excursion of the common belly.
Lumbrical-Plus Finger
What it is. The lumbrical-plus finger, the paradoxical extension described by Parkes, is extension of the interphalangeal joints when the patient tries to flex the finger. It occurs when the FDP loses effective distal pull while the lumbrical stays attached, classically after:
- FDP division distal to the lumbrical origin
- An over-long flexor graft
- A distal-finger amputation
Mechanism. Contraction intended to flex the digit instead slackens or pulls the FDP proximally. The force is transmitted through the lumbrical to the extensor mechanism, and the IP joints extend.
Why the level of division matters. Lumbrical-plus needs the lumbrical to stay attached to an FDP that has lost its distal anchor. A division distal to the lumbrical origin leaves the lumbrical pulling on a now slack, free tendon; a division proximal to the lumbrical origin removes the lumbrical's drive and does not cause it. The broader intrinsic-plus and intrinsic-minus syndromes are developed in Intrinsic-Minus and Intrinsic-Plus Hand; what matters here is the lumbrical origin and the level of division.
Treatment. Lumbrical release, dividing the offending lumbrical, or revising an over-long flexor graft to the correct length. Conservative techniques have also been described, but lumbrical release or an appropriately tensioned FDP graft are the standard surgical solutions.
The Two Side by Side
In a sense the two are opposite tension errors of the same system, both produced by getting flexor tendon length or tension wrong. Quadriga is an FDP that is too short or tight, limiting the others. Lumbrical-plus is an FDP that is too long or slack, or has lost its distal insertion, so its force is rerouted through the lumbrical.
- Quadriga effect
- FDP too SHORT / over-tight / tethered
- Lumbrical-plus finger
- FDP too LONG / slack / lost distal anchor
- Quadriga effect
- Over-advanced repair, adhesion, amputation stump sutured too proximal
- Lumbrical-plus finger
- FDP divided distal to lumbrical origin, over-long graft, distal amputation
- Quadriga effect
- OTHER fingers cannot fully flex (weak grip, flexion lag)
- Lumbrical-plus finger
- Affected finger's IP joints EXTEND on attempted flexion
- Quadriga effect
- Shared common muscle belly - excursion 'used up'
- Lumbrical-plus finger
- Force rerouted FDP → lumbrical → extensor mechanism
- Quadriga effect
- Release/tenolyse the over-tight/tethered FDP; correct tension
- Lumbrical-plus finger
- Lumbrical release or correct flexor graft length
How to Demonstrate Each One at the Bedside
Both are diagnosed by watching an active movement rather than by imaging, and each has a specific manoeuvre. Recognise them early by testing active flexion of every finger.
Quadriga: examine the fingers that are not complaining. Ask for a full fist. The involved digit flexes normally, or is stiff for its own reasons, while the neighbouring, uninvolved fingers stop short with a flexion lag at the PIP and DIP joints, and grip strength is measurably reduced. Quantify it as the distance from each fingertip to the distal palmar crease on maximal active flexion, compared with the other hand.
Tendon or joint. A persistent gap in the uninvolved fingers with full passive flexion is the finding, because the deficit is active only. If the fingers cannot be passively flexed either, the problem is the joints, not the tendon. Passively extending the involved finger slackens the common belly and improves the others' flexion, whereas flexing it worsens them, which makes a useful demonstration.
Lumbrical-plus: watch the finger while the patient tries to make a fist. The IP joints extend, with the MCP flexing, as flexion is attempted; the patient often describes the finger "going the wrong way" or being knocked straight. The movement is paradoxical and unmistakable once seen, and active flexion effort exaggerates it.
The MCP-block manoeuvre. Blocking or holding the MCP joint prevents MCP flexion and slackens the lumbrical. This abolishes the paradoxical extension and confirms the lumbrical as the culprit. Otherwise confirmation is anatomical rather than radiological: the history contains an FDP that has lost its distal anchor.
Imaging. Neither needs imaging to diagnose. Imaging is for defining the tendon anatomy before revision surgery. General hand examination is covered in Hand Examination and Clinical Localisation; the manoeuvres above are the phenomenon-specific ones.
In quadriga the OTHER fingers under-flex and the involved finger may look normal; in lumbrical-plus the SAME finger paradoxically extends on attempted flexion.
Preventing Them: the Numbers and the Rules That Are Actually Followed
"Set the correct tension" is the right principle and useless as an instruction. Specific rules do the work, and each corresponds to one of the operations that causes these problems.
- The rule
- Do NOT advance the tendon more than about 1 cm
- What happens if it is broken
- Over-advancement shortens the FDP, producing QUADRIGA in the other fingers and a DIP flexion contracture in this one
- The rule
- Accept a graft or staged reconstruction rather than advancing beyond that limit
- What happens if it is broken
- The same shortening - the temptation to close the gap by pulling harder is exactly how quadriga is created
- The rule
- Do NOT tenodese the flexor across the gap or suture FDP to the extensor over the stump
- What happens if it is broken
- Tethering the flexor at a fixed short length restrains the common belly - QUADRIGA in the remaining fingers
- The rule
- Set the graft to the correct length rather than erring long
- What happens if it is broken
- An over-long, slack graft leaves the FDP without effective distal pull - LUMBRICAL-PLUS
Grafting cuts both ways. A graft set too short risks quadriga, the opposite error to the over-long graft in the last row.
Amputation. The amputation rule and the graft rule pull in opposite directions, which is why the two phenomena are so often confused. Fixing the flexor too short causes quadriga; leaving it with no effective distal anchor causes lumbrical-plus. After a distal amputation both are possible: tenodese the flexor and the other fingers suffer, leave the profundus with nothing to pull on and this finger paradoxically extends. That is the reason the flexor is simply allowed to retract rather than being anchored under tension, and many surgeons avoid tenodesing FDP to FDS under tension. Be aware that a distal amputation can create a lumbrical-plus imbalance.
Where the rules come from. The 1 cm limit and the reason for it come from Flexor Tendon Repair Techniques; the amputation rule from Ray Amputation of the Hand and Foot; and the advancement-versus-graft decision in the avulsion setting from Jersey Finger.
Mnemonics & Memory Aids
SHORT vs LONG
Hook:SHORT FDP → quadriga (the others can't flex); LONG/divided FDP → lumbrical-Plus (paradoxical extension).
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“After a finger amputation, a patient cannot fully make a fist with the neighbouring fingers. What has happened and why?”
“A patient with an over-long flexor tendon graft notices that when he tries to bend the finger, the tip straightens instead. Explain this.”
Shared anatomy
- FDP tendons arise from ONE common muscle belly (shared excursion)
- Lumbricals originate from FDP tendons, insert on the radial lateral band
- Both phenomena follow from this anatomy
Quadriga effect
- One FDP too SHORT/tight (over-advanced, tethered, amputated proximal)
- The OTHER fingers cannot fully flex - weak grip, flexion lag
- Treat: release/tenolyse the over-tight tendon; correct amputation tension
Lumbrical-plus finger
- FDP too LONG/slack/divided distal to lumbrical / over-long graft / distal amputation
- Paradoxical IP EXTENSION on attempted flexion (often middle finger; Parkes)
- Treat: lumbrical release or correct flexor graft length
Prevention
- Repair/advancement: correct tension (avoid over-tight = quadriga)
- Grafting: correct graft length (avoid over-long = lumbrical-plus)
- Amputation: do not suture FDP under tension to the stump
Evidence & Key Studies
Pathomechanics of lumbrical and FDP muscle tears (the quadriga effect) - a cadaveric model
- Lumbrical muscles originate on the FDP tendons; injuries occur when a shear force acts between origins on adjacent FDP tendons as they glide, and other structures of the deep flexor complex are affected via the so-called quadriga effect.
- In a cadaveric loading model of isolated 5th-finger FDP loading, rupture occurred with lumbrical detachment from the 4th FDP and changes in the FDP tendons at the distal forearm, demonstrating the shared deep-flexor mechanics underlying the quadriga effect.
- The study confirms that loading one finger's FDP transmits effects to adjacent fingers through the shared deep-flexor complex.
Lumbrical-plus (paradoxical extension) finger - description and management
- Paradoxical extension, termed the 'lumbrical-plus' finger by Parkes in 1970, is characterised by extension of the interphalangeal joints when the patient flexes the fingers, and is most common in the middle finger.
- Standard treatment involves lumbrical muscle release or a flexor digitorum profundus graft of an appropriate length.
- A conservative technique for the lumbrical-plus deformity was also described, as reports of conservative management were lacking.
The shared deep-flexor mechanics underlying the quadriga effect (lumbricals arising from the FDP tendons, effects transmitted between fingers through the common deep-flexor complex) come from the cited Carnicero cadaveric study, and the definition and treatment of the lumbrical-plus (paradoxical extension) finger - lumbrical release or an appropriately-lengthened FDP graft - from the cited Gangatharam report. The common FDP muscle-belly anatomy, the 'quadriga' analogy, and the causative tension/length errors in repair, grafting and amputation are standard, well-established teaching. The 1 cm limit on FDP advancement, and the DIP flexion contracture that accompanies over-advancement, are taken from Flexor Tendon Repair Techniques; the rule against tenodesing the flexor across an amputation gap from Ray Amputation of the Hand and Foot; and the advancement-versus-graft decision in tendon avulsion from Jersey Finger - so the four pages give the same operative instruction. (See also Flexor Tendon Lacerations and Flexor Tendon Rehabilitation.)