Intra-articular Hindfoot Injuries with a Precarious Blood Supply
- A talar body fracture is intra-articular and, unlike a neck fracture, disrupts both the tibiotalar and the subtalar (posterior facet) surfaces, so anatomic articular reduction is the priority and arthritis of both joints is common
- No muscular attachments, a largely cartilage-covered surface and a largely retrograde supply: displaced body fractures carry a high risk of avascular necrosis
- CT is mandatory - plain radiographs underestimate these fractures
- Displaced fractures need anatomic reduction and rigid fixation, usually through a malleolar osteotomy that preserves the deltoid; a truly non-displaced fracture may be treated in a non-weight-bearing cast with close surveillance
- A dislocated, extruded or open talus is an emergency because of the skin and the posterior tibial neurovascular bundle; definitive fixation of a closed fracture can be staged until the soft tissues settle
- Arthritis, not osteonecrosis, is the commoner outcome - counsel that arthritis and chronic pain are expected even after anatomic reduction
- “Body fracture = both tibiotalar and subtalar surfaces, Sneppen classification; neck fracture = Hawkins classification
- “Artery of the tarsal canal (from the posterior tibial) is the dominant supply to the body
- “Hawkins sign (subchondral lucency ~6-8 wks) present = revascularising; absent = concerning but not diagnostic, confirm with MRI
- “Protect the deltoid and its branches during a medial malleolar osteotomy - they are one of the few remaining sources of blood to the body
Overview: Body Versus Neck
A talar body fracture is an intra-articular fracture of the body of the talus. Unlike a talar neck fracture, it disrupts both the tibiotalar (ankle) and the subtalar (posterior facet) articular surfaces, so anatomic reduction of the joint surfaces is the priority and post-traumatic arthritis of both joints is common.
Body versus neck. The neck fracture is extra-articular to the ankle, although it involves the subtalar joint. It is classified by Hawkins, and its AVN risk rises with displacement and dislocation (see Talus Fractures). The body fracture is classified by Sneppen.
Mechanism. Talar body fractures follow high-energy mechanisms: falls from height, motor-vehicle crashes and axial loading. They are frequently part of a polytrauma or associated with other hindfoot and malleolar injuries.
Anatomy, Blood Supply & Why AVN Happens
A bone without muscle. About 60% of the talus is covered by articular cartilage and it has no muscular or tendinous attachments, so blood can only enter through the limited non-articular surfaces.
The supply. The dominant supply to the body is the artery of the tarsal canal, a branch of the posterior tibial artery. It is supplemented by deltoid branches medially and by the artery of the sinus tarsi, from the dorsalis pedis and peroneal arteries. Much of this flow runs retrograde, distal to proximal, into the body.
Why AVN happens. A displaced body fracture readily strips that supply and causes avascular necrosis. This is the anatomical reason talar body and neck fractures behave so differently from most other fractures.
Classification
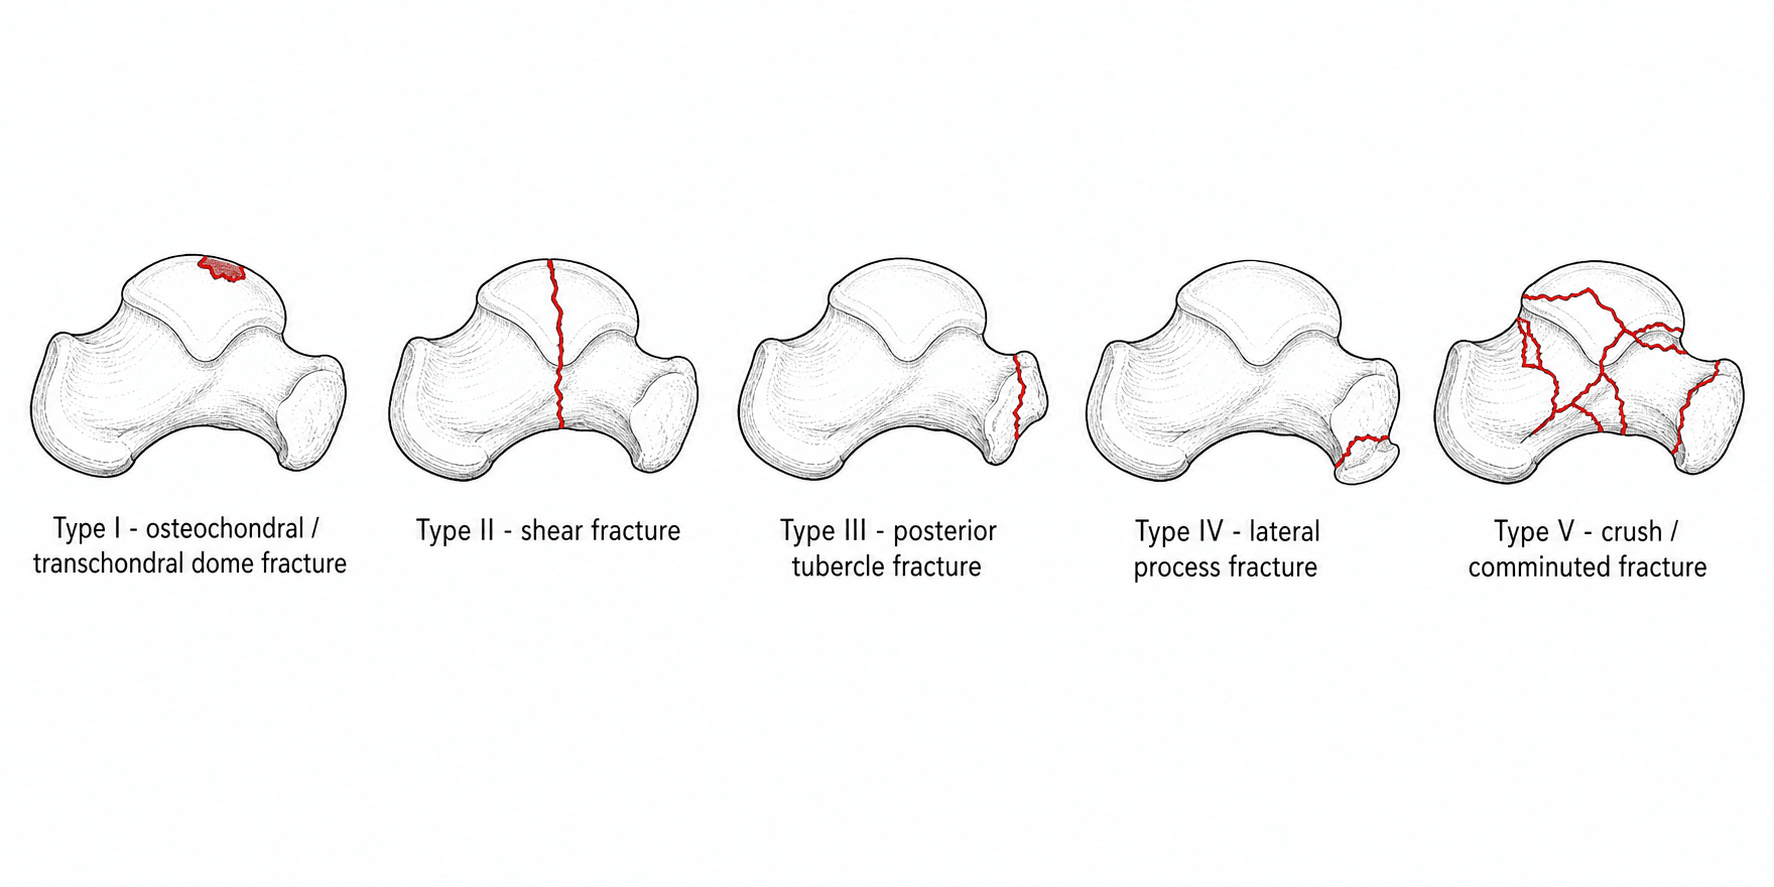
Sneppen classifies talar body fractures into five types. The shear (II) and crush (V) patterns are the principal body fractures and carry the highest rates of AVN and post-traumatic arthritis; three of the others have their own topics.
- Pattern
- Osteochondral or transchondral fracture of the talar dome
- Notes
- See Osteochondral Lesion of the Talus
- Pattern
- Coronal, sagittal or horizontal shear fracture of the body
- Notes
- The principal body fracture; splits the tibiotalar and subtalar surfaces
- Pattern
- Posterior tubercle fracture
- Notes
- See Posterior Process Talus Fractures
- Pattern
- Lateral process fracture ("snowboarder's ankle")
- Notes
- See Lateral Process Talus Fractures
- Pattern
- Crush or comminuted fracture of the body
- Notes
- Worst prognosis for AVN and arthritis
Assessment & Imaging
Assessment. The mechanism is high-energy, so a careful soft-tissue and neurovascular assessment is essential.
Look for the partners. A talar body fracture is frequently accompanied by other injuries, so image the whole foot and ankle and survey the patient:
- An ipsilateral medial malleolar fracture, as in the cited Moger case
- A lateral or posterior process fracture
- A calcaneal or navicular fracture
- Subtalar or total talar dislocation
- Ipsilateral lower-limb and spine fractures, as a high-energy axial injury
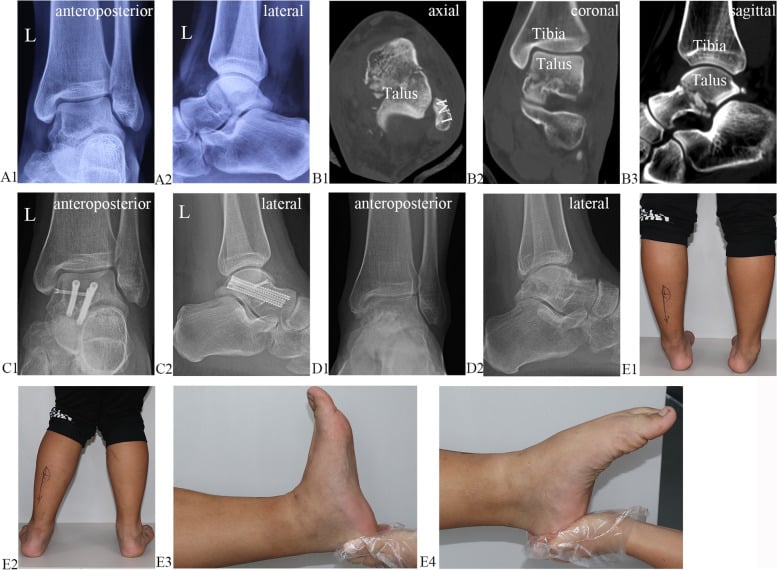
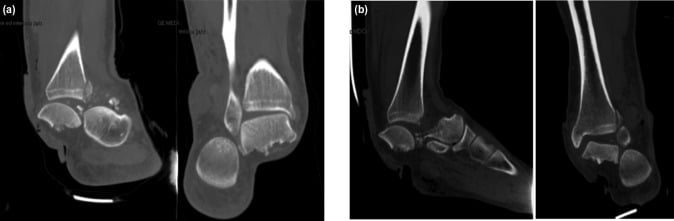
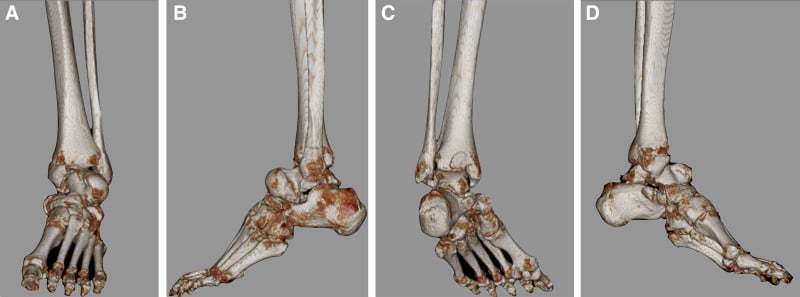
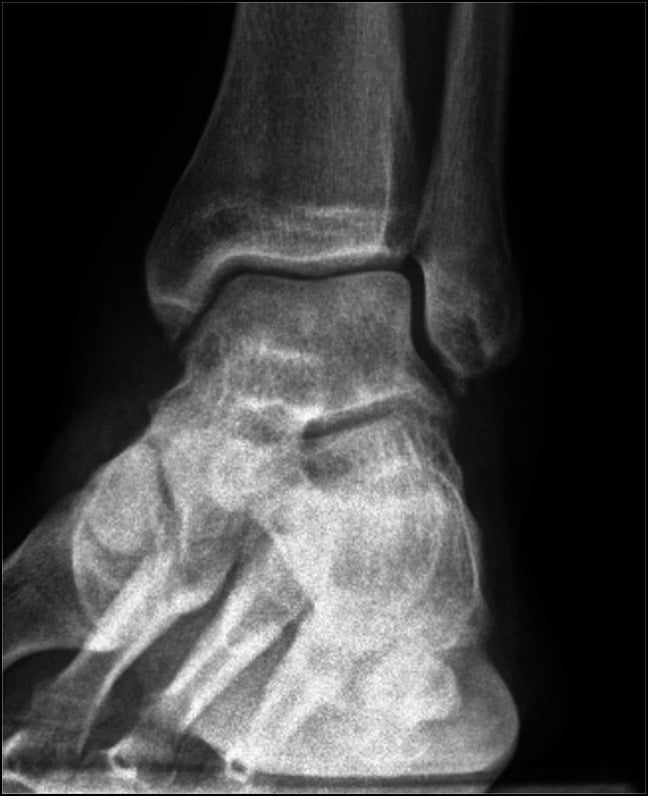
CT is mandatory. Plain AP, lateral and mortise radiographs underestimate these fractures. CT defines the fracture planes, the degree of articular comminution and displacement, and any associated lateral or posterior process or malleolar fractures, which together determine the surgical approach and fixation strategy.
Management
Urgency belongs to the dislocation, not the fixation. The instinct that every hour of delay to definitive fixation worsens osteonecrosis does not survive the data. In 26 displaced fractures isolated to the talus, neck and body, treated by open reduction and stable fixation and followed for a mean of 74 months, a delay in surgical fixation did not appear to affect outcome, union or the prevalence of osteonecrosis. All closed displaced fractures healed regardless of the time to surgery, and the overall union rate was 88%.
That splits the word "urgent" into two different things:
- Timing
- EMERGENCY reduction
- Why
- The threat is to the skin and the posterior tibial neurovascular bundle, not to a clock running on osteonecrosis
- Timing
- STAGE the definitive fixation
- Why
- Delay did not affect union, outcome or osteonecrosis - whereas operating through compromised skin causes wound failure
- Timing
- Definitive ORIF on a planned list
- Why
- Anatomic articular reduction, done well, matters more than done fast
Two errors in opposite directions. Leaving a dislocated talus unreduced overnight risks the skin and the neurovascular bundle. Rushing a swollen, blistered ankle to definitive fixation risks a wound catastrophe in an injury that would have tolerated waiting. Soft-tissue swelling and fracture blisters often dictate the timing, and definitive fixation may be staged after temporary stabilisation; an open fracture or an irreducible dislocation demands emergency treatment.
The extruded body. A displaced body fragment can extrude posteromedially, where it tents or breaches the skin and threatens the posterior tibial neurovascular bundle behind the medial malleolus. It needs urgent reduction to relieve the pressure on the skin and the bundle, and an irreducible or open extrusion goes straight to theatre.
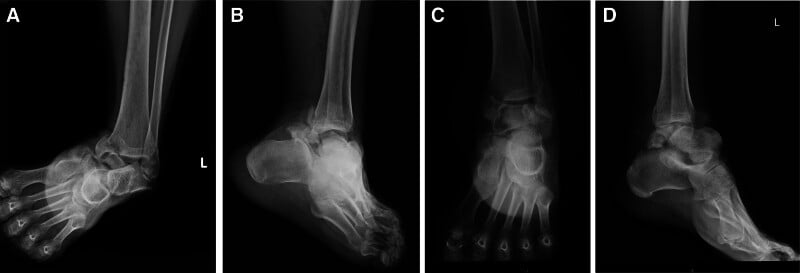
The totally extruded talus. Complete extrusion of the talus, the "missing" talus, is a devastating open injury. Current practice favours thorough debridement and reimplantation of the talus, even when fully extruded, with antibiotics, rather than primary excision. The high risk of AVN and infection is accepted because primary talectomy leaves a very poor hindfoot, though some grossly contaminated cases still require excision and later reconstruction or arthrodesis.
Open fractures. These follow the usual urgent debridement, antibiotic and (often staged) fixation principles, with soft-tissue cover as needed. See Subtalar Dislocations and Total Talar Dislocation.
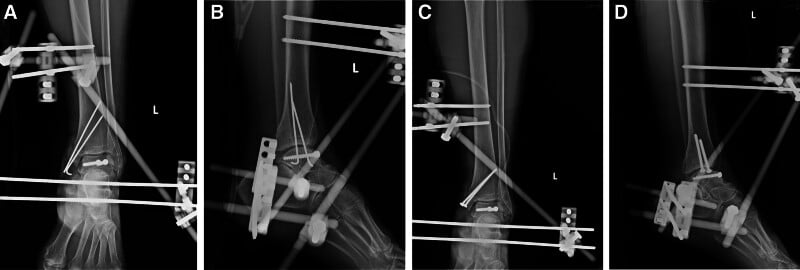
Non-displaced fractures. A truly non-displaced fracture, confirmed on CT, can be managed non-operatively in a non-weight-bearing cast or boot with close radiographic surveillance, because even minimally displaced intra-articular fractures may need fixation. The cited Kopp series went further and advocated osteosynthesis even for non-displaced patterns.
Displaced fractures. These require anatomic reduction of the articular surfaces and rigid internal fixation with lag screws, often supplemented by mini-fragment plates for comminution. Buried or headless screws are used where they would otherwise be prominent in the articular surface.
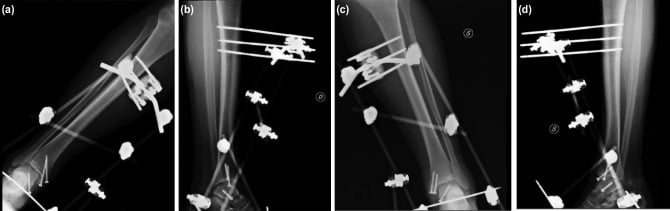
Exposure. The body of the talus is deep and largely articular, so adequate visualisation usually requires a medial or lateral malleolar osteotomy, and the osteotomy is then fixed. A medial malleolar osteotomy is reflected on the deltoid ligament, and the deltoid and its branches must be protected: stripping them removes one of the few remaining sources of blood to the body and worsens the risk of AVN.
Severe comminution (Sneppen V). Anatomic reconstruction may be impossible. The options are limited fixation or primary or delayed arthrodesis (tibiotalar or tibiotalocalcaneal), with the patient counselled about stiffness and AVN.
Where to treat. Complex hindfoot injuries are best managed at, or referred to, a foot-and-ankle or trauma centre.
Complications & Outcomes
Avascular necrosis is the feared complication of displaced body fractures and dominates discussion of this injury, but it is not the one most patients get.
Arthritis is the commoner outcome. In the 26-fracture Lindvall series, post-traumatic subtalar arthritis was the most common finding and was present in every patient, 16 with more than one joint involved, while osteonecrosis occurred in 13 of the 26. A separate series of 42 surgically treated talar neck and body fractures (Kopp) found the same ordering: arthritis 23.8% against osteonecrosis 14.3%. Arthritis of the tibiotalar and/or subtalar joints is common after these double-articular injuries and is the main long-term outcome determinant.
Counselling. A patient with a displaced talar fracture should be told that post-traumatic arthritis and chronic pain are expected even after anatomic reduction and stable fixation. This is especially true after an open injury: osteonecrosis followed 6 of 7 open fractures in the Lindvall series. Lead with arthritis, which every patient in that series developed, rather than osteonecrosis, which affected half.
Other complications. Malunion alters hindfoot mechanics, and non-union, wound problems or infection, and stiffness also occur. Overall functional outcome correlates with the severity of the original fracture and the quality of the articular reduction.
Diagnosing & Managing Avascular Necrosis
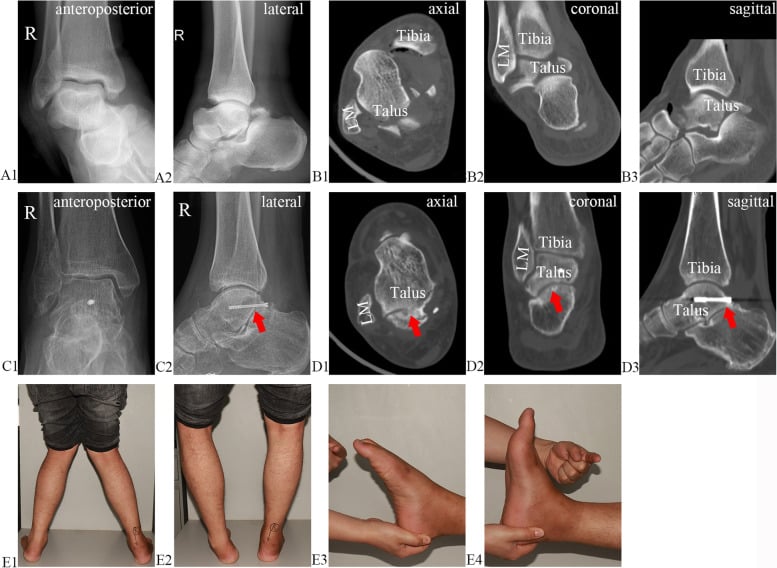
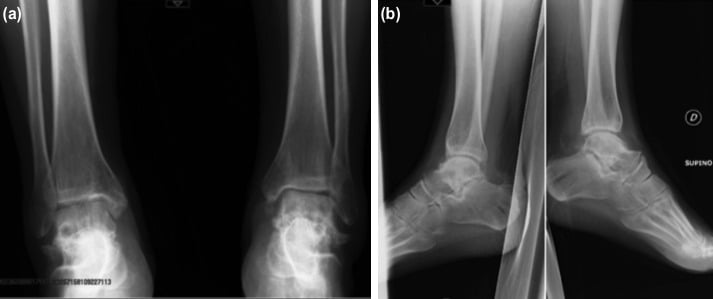
The Hawkins sign. A thin subchondral lucency in the talar dome on a mortise radiograph at about 6 to 8 weeks. It is produced by subchondral bone resorption (disuse osteopenia), which can only occur if the bone is vascularised, so a positive sign means the talus is perfused and AVN is unlikely. Its absence is concerning but not diagnostic, because a still-immobilised, non-weight-bearing limb may not resorb.
Confirming AVN. Where the Hawkins sign is absent or equivocal, MRI is the definitive test for the presence and extent of necrosis, while CT shows established collapse. Follow with serial imaging.
Weight-bearing. Whether prolonged non-weight-bearing protects a necrotic talus from collapse is debated. The historical practice of strict offloading until revascularisation has weak evidence that it prevents collapse, and many now allow protected weight-bearing once the fracture has united, individualised to the patient.
The salvage ladder. Non-collapsed AVN can remain functional and is observed. Once there is dome collapse or post-traumatic arthritis, salvage is by arthrodesis of the affected joint or joints (tibiotalar, subtalar or tibiotalocalcaneal), sometimes with bone graft to restore height. Talar AVN with extensive collapse is a difficult problem and may need a combined fusion. Hip and shoulder osteonecrosis are developed elsewhere; the hindfoot fusions are in Ankle Arthrodesis and Subtalar Arthrodesis.
Mnemonics & Memory Aids
DSPLC
Hook:Sneppen I-V = Dome, Shear, Posterior tubercle, Lateral process, Crush.
TALUS
Hook:TALUS body fracture = two joints, AVN, lag screws, urgent reduction of a dislocation, Sneppen + CT.
Clinical Decision Scenarios
Practise clinical reasoning and management decisions out loud
“How does a talar body fracture differ from a talar neck fracture, how are body fractures classified, and why are they prone to avascular necrosis?”
“A young man falls from a height and CT shows a displaced shear (Sneppen II) fracture of the talar body with intact skin. How would you manage him and what complications would you counsel him about?”
Definition & classification
- Intra-articular body fracture - disrupts tibiotalar AND subtalar surfaces
- Sneppen: I dome, II shear, III posterior tubercle, IV lateral process, V crush
- Lateral process / posterior process / OCD have dedicated topics
Blood supply & AVN
- No muscle attachments; ~60% cartilage; retrograde supply
- Artery of tarsal canal (post. tibial) dominant + deltoid + sinus tarsi (DP/peroneal)
- Hawkins sign (subchondral lucency ~6-8 wks) present = revascularising; absent = AVN
Imaging & management
- CT mandatory (plain films underestimate)
- Non-displaced: NWB cast + surveillance | Displaced: anatomic ORIF
- Exposure usually via malleolar osteotomy (protect deltoid); lag/headless screws +/- plate
Timing - two different urgencies
- EMERGENCY: dislocated, extruded or open talus (threatens skin + posterior tibial bundle)
- STAGE definitive ORIF if swollen/blistered - delay did NOT affect union, outcome or osteonecrosis
- 26 displaced talar fractures, 74-month follow-up: union 88%, all closed ones healed despite delay
Complications
- Post-traumatic SUBTALAR arthritis is the commonest - every patient in the cited series
- Osteonecrosis 13 of 26 overall; 6 of 7 OPEN fractures
- A separate 42-patient series: arthritis 23.8% vs osteonecrosis 14.3%
- Counsel that arthritis and chronic pain are EXPECTED even after anatomic reduction
- Malunion, non-union, wound problems, stiffness; salvage = arthrodesis
Evidence & Key Studies
Surgical management of talus fractures: mid-term functional and radiographic outcomes
- In a prospective series of 42 surgically treated talar neck and body fractures, 28.5% were ISOLATED talar BODY fractures (a further 21.5% combined neck-and-body), classified by Hawkins, Sneppen and Marti.
- Avascular necrosis affected the talar body in 14.3% (three requiring secondary arthrodesis) and arthritis developed in 23.8%; AVN incidence without dome collapse did not necessarily cause functional impairment.
- Functional/radiographic outcome correlated with fracture severity; osteosynthesis was advocated even for non-displaced patterns, with staged treatment for dislocated/open injuries and referral of complex injuries to foot-surgery centres.
Combined talus fracture with medial malleolar fracture: a case report with review of literature
- Describes a Sneppen type II talar body fracture with an ipsilateral medial malleolar fracture - illustrating the association of body fractures with malleolar injury and the value of the Sneppen classification.
- Treatment was open anatomic reduction of the talar body with a Herbert (headless) screw and cannulated-screw fixation of the medial malleolus.
- Emphasises early diagnosis and fixation to optimise outcome, while noting the unpredictable risks of AVN, wound complications and post-traumatic ankle arthritis.
Open reduction and stable fixation of isolated, displaced talar neck and body fractures
- Twenty-five patients with 26 displaced fractures isolated to the talus (neck and/or body) treated by open reduction and stable internal fixation, followed for a minimum of 48 and a mean of 74 months; overall union rate 88%.
- A delay in surgical fixation did not appear to affect outcome, union or the prevalence of osteonecrosis, and all closed displaced fractures healed regardless of the delay to surgery.
- Post-traumatic subtalar arthritis was the most common finding and occurred in every patient, 16 with more than one joint involved, while osteonecrosis was seen after 13 of the 26 fractures and after 6 of the 7 open fractures - so patients should be counselled that arthritis and chronic pain are expected even after anatomic reduction and stable fixation.
The proportion of body fractures and the osteonecrosis and arthritis rates of 14.3% and 23.8% come from the cited Kopp series of 42 surgically treated talar neck and body fractures, and the Sneppen-type-II body-with-malleolar example and fixation principles from the cited Moger case report, which is a single case.
The finding that delay to definitive fixation did not affect outcome, union or osteonecrosis, the 88% union rate, and the ordering of complications - subtalar arthritis in every patient against osteonecrosis in 13 of 26, and 6 of 7 open fractures - are the cited Lindvall series, which pooled displaced neck and body fractures rather than reporting body fractures separately, and is retrospective with 26 fractures. The same paper is the source of the counselling line that arthritis and chronic pain are expected outcomes even after anatomic reduction. Separating the emergency reduction of a dislocated or extruded talus from the schedulable definitive fixation of a closed one is the reading that follows from those findings placed beside the soft-tissue principle, rather than a distinction the paper draws in those words.
The Sneppen classification, the retrograde talar blood supply and the Hawkins sign are standard, well-established teaching. (See also Talus Fractures, Lateral Process Talus Fractures, Posterior Process Talus Fractures and Osteochondral Lesion of the Talus.)