Calcification within hyaline or fibrocartilage — a radiographic sign, not a diagnosis
- Chondrocalcinosis means calcification of cartilage; it is most often calcium pyrophosphate dihydrate (CPPD) crystal deposition.
- Chondrocalcinosis is not the same as calcific tendinopathy (hydroxyapatite in tendon) or vascular calcification — define the tissue involved before you commit.
- Under age 55, or if florid and polyarticular, chondrocalcinosis is a metabolic disease until proven otherwise: screen for haemochromatosis, hyperparathyroidism, hypomagnesaemia and hypophosphatasia.
- The classic CPPD arthropathy pattern is radiocarpal and second and third metacarpophalangeal joint disease with hook-like osteophytes, and patellofemoral-predominant knee degeneration.
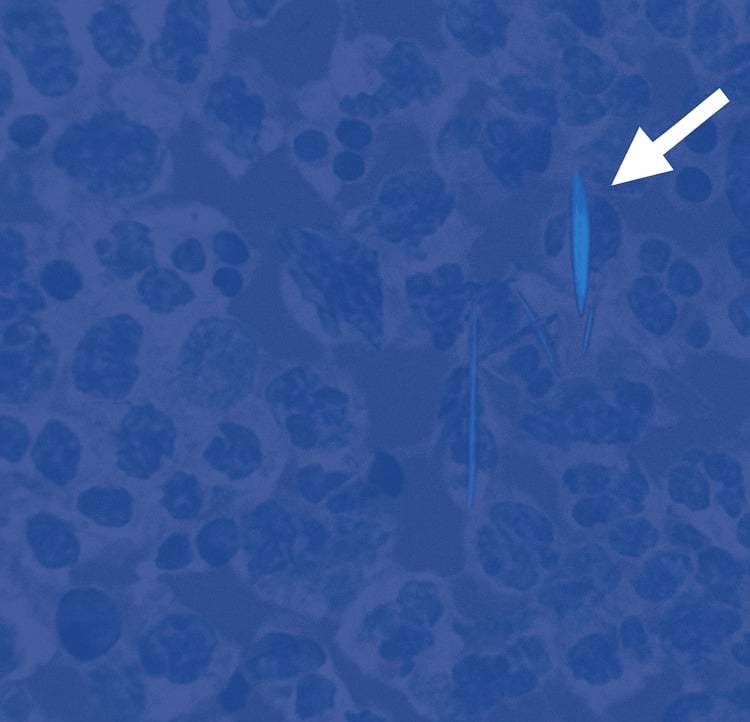
- Definitive diagnosis of CPPD is positively birefringent rhomboid crystals on polarised light microscopy of aspirate, not the radiograph.
- Acute pseudogout in a prosthetic or native joint is clinically indistinguishable from septic arthritis — aspirate, send for Gram stain and culture as well as crystals.
- “Say the tissue, the site and the distribution: 'linear calcification paralleling the subchondral bone of the femoral condyles, in keeping with hyaline cartilage calcification'.
- “Wrist chondrocalcinosis plus scapholunate widening with proximal capitate migration equals scapholunate advanced collapse secondary to CPPD.
- “Isolated symphysis pubis chondrocalcinosis in a young man should prompt a ferritin and transferrin saturation.
- “Severe destructive shoulder disease with intra-articular debris and rotator cuff loss is Milwaukee shoulder — basic calcium phosphate, not CPPD.
Recognising the Pattern
Definition. Chondrocalcinosis is radiographically visible calcification within cartilage: hyaline articular cartilage, or a fibrocartilaginous structure such as the meniscus, triangular fibrocartilage complex, symphysis pubis, acetabular labrum, glenoid labrum or annulus fibrosus. It is a radiographic sign; calcium pyrophosphate dihydrate (CPPD) crystal deposition is its commonest cause, not its synonym.
Hyaline cartilage. A thin, dense, linear band running parallel to the subchondral bone and separated from it by the uncalcified cartilage layer. It is best seen at the femoral condyles, humeral head and radial head.
Fibrocartilage. Thicker, shaggier, more amorphous or punctate calcification within the substance of the structure. The classic examples are the triangular density in the meniscus on an anteroposterior knee film, and the dense wedge between the ulnar head and triquetrum at the TFCC.
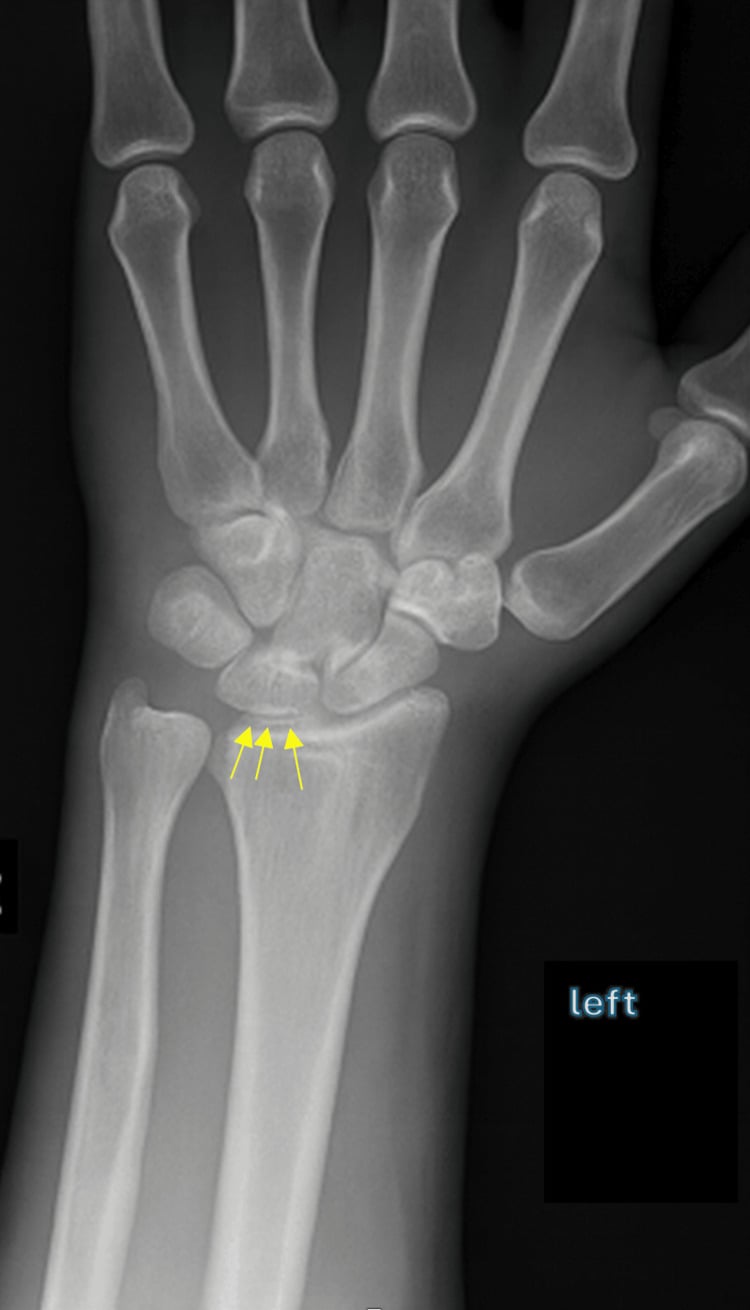
Confirming it is genuinely present. Three checks:
- The density is intra-articular and conforms to the shape of a cartilage structure, rather than following a tendon, capsule or vessel.
- It is present at more than one site. Screening films of the knees (anteroposterior), wrists (posteroanterior) and pelvis (symphysis pubis) form the standard "chondrocalcinosis series", and establish whether deposition is monoarticular or systemic.
- Ultrasound agrees, if the radiograph leaves doubt. What it shows is in Next Investigation.
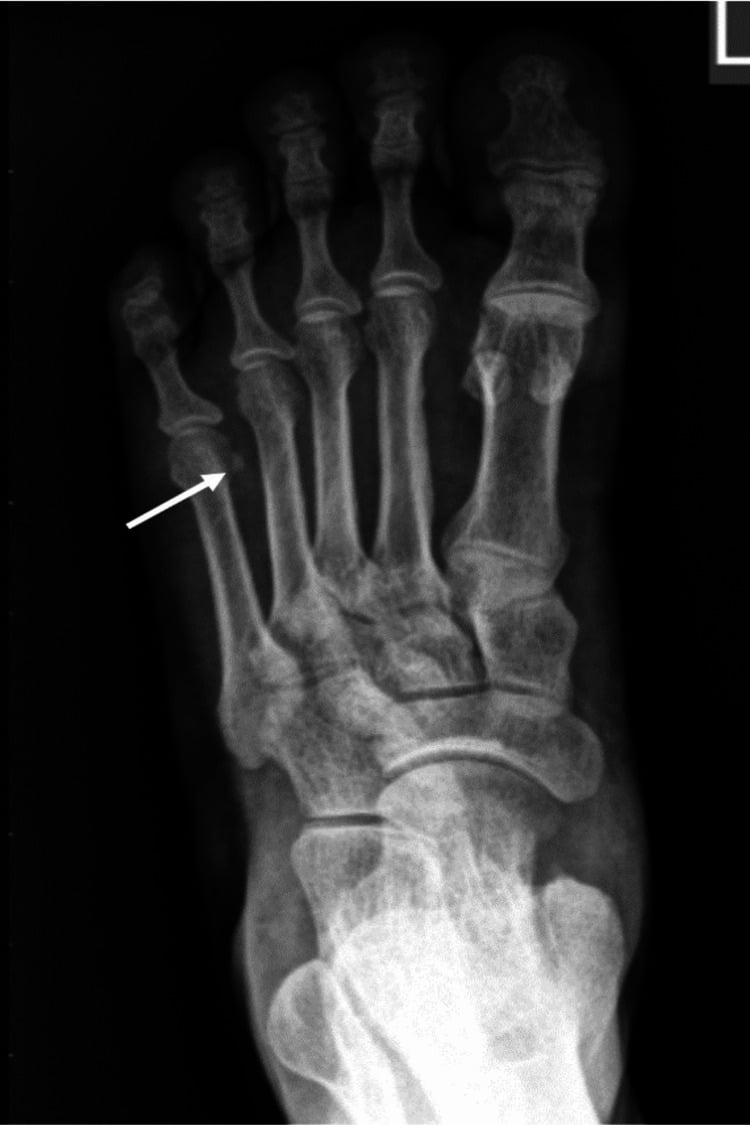
Saying it out loud. "There is linear calcification paralleling the subchondral bone of both femoral condyles and amorphous calcification within the body of the medial meniscus. This is chondrocalcinosis involving both hyaline and fibrocartilage. There is patellofemoral joint space narrowing with subchondral sclerosis. The pattern favours calcium pyrophosphate deposition disease. I would examine the wrists and symphysis pubis for further deposition, and given the patient's age I would screen for haemochromatosis and hyperparathyroidism."
Mimics. Calcification within the capsule, synovium, ligaments or tendons is not chondrocalcinosis, and shifts the differential toward hydroxyapatite deposition or gout. The false positives, and what gives each away:
- Calcific tendinopathy (hydroxyapatite deposition) - globular, homogeneous, and located in the supraspinatus tendon, gluteus medius insertion or longus colli, outside the joint line
- Synovial osteochondromatosis - multiple discrete rounded bodies of equal size with ring-and-arc chondroid mineralisation, distending the capsule rather than confined to a cartilage layer
- Vascular calcification - tram-track parallel lines following a known vessel course, popliteal or femoral
- Meniscal ossification - a true ossicle with cortex and trabeculae, not amorphous density
- Gouty tophus - soft tissue density with eccentric erosions and overhanging edges; usually only mineralised in chronic renal disease
- Pellegrini–Stieda - post-traumatic calcification at the medial femoral condyle along the medial collateral ligament, extra-articular
Next Investigation
The screening radiograph series is first-line in every case and is described above.
The metabolic screen. Serum calcium, phosphate, PTH, ferritin with transferrin saturation, magnesium, alkaline phosphatase, and thyroid function. It is mandatory under age 55, in polyarticular disease, or if any systemic feature is present. A low alkaline phosphatase is the specific clue to hypophosphatasia and is easily overlooked as a normal-range result.
Joint aspiration with polarised light microscopy. The only test that positively confirms CPPD, and it simultaneously excludes sepsis and urate. It is mandatory in any acutely inflamed joint and useful electively when the diagnosis is uncertain. A cell count above 50,000 per cubic millimetre with neutrophil predominance is treated as infection until cultures return.
Ultrasound. Hyperechoic deposits within the substance of the hyaline cartilage layer, which do not produce the posterior acoustic shadow typical of hydroxyapatite and do not disappear at differing insonation angles the way the surface double contour sign of urate does. It is more sensitive than radiography at the knee and wrist and useful for guiding aspiration, so its place is the equivocal radiograph or the technically difficult aspiration.
Dual-energy CT. Colour-codes monosodium urate, separating gout from CPPD in the selected cases where clinical and radiographic features overlap. It does not replace aspiration where infection is a consideration.
CT of the cervical spine. For acute neck pain with pyrexia and raised inflammatory markers in a patient with known chondrocalcinosis. It demonstrates the calcification around the odontoid peg and prevents an unnecessary infection or malignancy workup.
When to stop. An asymptomatic incidental meniscal calcification in a patient over 70 with normal bloods and no systemic features needs no follow-up imaging and no treatment. Say this explicitly; recognising when to stop is a mark-scoring answer.
The crystal differential. CPPD, urate and basic calcium phosphate part on tissue, appearance, microscopy and site. Gout travels with CPPD as an associated crystal disease, and mixed deposition occurs.
- CPPD (calcium pyrophosphate)
- Hyaline and fibrocartilage
- Gout (monosodium urate)
- Synovium, soft tissue tophi, periarticular
- Hydroxyapatite (basic calcium phosphate)
- Tendon, bursa, capsule
- CPPD (calcium pyrophosphate)
- Linear or punctate calcification within cartilage
- Gout (monosodium urate)
- Usually radiolucent; erosions with overhanging edges and preserved joint space
- Hydroxyapatite (basic calcium phosphate)
- Globular homogeneous amorphous density outside the joint line
- CPPD (calcium pyrophosphate)
- Rhomboid, weakly positively birefringent
- Gout (monosodium urate)
- Needle-shaped, strongly negatively birefringent
- Hydroxyapatite (basic calcium phosphate)
- Not visible on polarised light; alizarin red stain required
- CPPD (calcium pyrophosphate)
- Knee, wrist TFCC, symphysis pubis
- Gout (monosodium urate)
- First metatarsophalangeal joint, midfoot, olecranon bursa
- Hydroxyapatite (basic calcium phosphate)
- Supraspinatus tendon, gluteus medius, longus colli
- CPPD (calcium pyrophosphate)
- Pseudo-osteoarthritis with large subchondral cysts; crowned dens syndrome
- Gout (monosodium urate)
- Chronic tophaceous gout with punched-out para-articular erosions
- Hydroxyapatite (basic calcium phosphate)
- Milwaukee shoulder with cuff loss and humeral head collapse
The Differential
The shape of the list. Idiopathic, age-related CPPD is overwhelmingly the commonest cause, commoner than all the metabolic causes combined, and its prevalence rises with each decade. It is a finding of ageing cartilage, usually asymptomatic, and does not by itself explain a painful knee. The rest of the table exists to stop you missing the treatable minority.
The must-not-miss. Haemochromatosis, because chondrocalcinosis may precede cirrhosis and diabetes by years and the arthropathy can be the presenting feature. What discriminates it is the metacarpophalangeal arthropathy in the table, not the chondrocalcinosis: isolated cartilage calcification is non-specific.
The counterintuitive one. Hypophosphatasia is the reason alkaline phosphatase is on the panel. A persistently low value dismissed as a laboratory artefact is the classic miss, and bisphosphonates are contraindicated because they worsen the disease.
The reversible one. Hypomagnesaemia is the most easily reversible cause on the list and the one most often left off the request form. Think of long-term proton pump inhibitors, thiazides, short bowel, alcohol excess, or Gitelman syndrome in a young patient.
- Typical age / setting
- Men aged 40-60; fatigue, skin pigmentation, diabetes, hepatomegaly
- Discriminating feature
- Degenerative change with hook-like osteophytes on the radial side of the second and third metacarpal heads, with squared metacarpal heads — arthropathy often precedes systemic disease
- What confirms it
- Transferrin saturation over 45 per cent with raised ferritin; HFE gene testing; liver MRI showing iron
- Typical age / setting
- Women over 50; renal stones, fatigue, constipation, bone pain
- Discriminating feature
- Chondrocalcinosis with subperiosteal resorption of the radial border of the middle phalanges, acro-osteolysis and a pepper-pot skull
- What confirms it
- Raised calcium with an inappropriately raised or normal PTH; sestamibi scan for adenoma
- Typical age / setting
- Children and young adults; premature loss of deciduous teeth, metatarsal stress fractures, atypical femoral fractures
- Discriminating feature
- Chondrocalcinosis in a young patient with a persistently LOW alkaline phosphatase — the only cause where a low ALP is the clue
- What confirms it
- Low serum alkaline phosphatase, raised urinary phosphoethanolamine, ALPL gene mutation
- Typical age / setting
- Any age; hot swollen joint, fever, raised inflammatory markers
- Discriminating feature
- Chondrocalcinosis on the film does not exclude sepsis; the synovial white cell count and differential are the discriminator
- What confirms it
- Synovial fluid Gram stain and culture; crystals may be present simultaneously
- Typical age / setting
- Over age 65; incidental or intermittent knee and wrist pain
- Discriminating feature
- Increasing prevalence with each decade; knee-predominant, often asymptomatic, no systemic features and a normal metabolic screen
- What confirms it
- Positively birefringent rhomboid crystals on aspiration; normal calcium, PTH, ferritin, magnesium, ALP
- Typical age / setting
- Elderly inpatient, often after surgery, trauma or acute medical illness
- Discriminating feature
- Abrupt monoarticular hot knee or wrist over 12-24 hours in a patient with pre-existing chondrocalcinosis; self-limiting over days
- What confirms it
- Aspiration showing weakly positively birefringent rhomboid crystals with an inflammatory cell count
- Typical age / setting
- Age 60-80; progressive joint pain in unusual joints
- Discriminating feature
- Degeneration at joints osteoarthritis spares — radiocarpal, elbow, glenohumeral, ankle — with prominent subchondral cysts disproportionate to the joint space loss
- What confirms it
- Radiographic distribution plus chondrocalcinosis; exclude secondary causes by blood screen
- Typical age / setting
- Any age; single joint with prior injury or surgery
- Discriminating feature
- Strictly monoarticular and confined to the operated or injured joint, with no deposition at the wrist or symphysis
- What confirms it
- History plus normal screening films of the contralateral knee, wrists and pelvis
- Typical age / setting
- Over age 60; typical medial compartment knee disease
- Discriminating feature
- Chondrocalcinosis confined to the degenerate compartment, tracking the disease rather than preceding it
- What confirms it
- Distribution matches classic osteoarthritis; metabolic screen normal
- Typical age / setting
- Young adults with tetany, or elderly on long-term diuretics
- Discriminating feature
- Polyarticular chondrocalcinosis at an unexpectedly young age with hypokalaemic metabolic alkalosis
- What confirms it
- Low serum and urinary magnesium; renal tubular studies; SLC12A3 mutation in Gitelman
- Typical age / setting
- Onset in the twenties to forties; strong family history, multiple affected relatives
- Discriminating feature
- Early-onset florid polyarticular deposition including the spine, with an entirely normal metabolic screen
- What confirms it
- Family pedigree; ANKH gene testing
- Typical age / setting
- Age 15-40; tremor, dysarthria, Kayser–Fleischer rings, hepatic disease
- Discriminating feature
- Chondrocalcinosis with subchondral fragmentation and irregular ossification, plus osteopenia and rickets-like changes
- What confirms it
- Low serum caeruloplasmin, raised urinary copper, slit-lamp examination
- Typical age / setting
- Age 30-50; dark urine on standing, blue-black ear and scleral pigmentation
- Discriminating feature
- Dense multilevel intervertebral disc calcification with disc space narrowing and vacuum phenomena — spine dominates over peripheral joints
- What confirms it
- Urinary homogentisic acid; HGD gene mutation
- Typical age / setting
- Age 30-50; coarse features, large hands, carpal tunnel syndrome
- Discriminating feature
- Chondrocalcinosis on a background of WIDENED joint spaces from cartilage hypertrophy, with tufted terminal phalanges and increased heel pad thickness
- What confirms it
- Raised IGF-1, failure of growth hormone suppression on oral glucose tolerance test, pituitary MRI
Arthritis and chondrocalcinosis in haemochromatosis — why a young or florid case needs a ferritin
- The metacarpophalangeal joints and wrists were the commonest sites of haemochromatosis arthropathy, with chondrocalcinosis present in 9 of 25 subjects - the pattern the page flags as the must-not-miss systemic cause.
- Arthropathy was largely confined to probands (clinically diagnosed) rather than asymptomatic discovered homozygotes, and was age-related - so an iron-overload arthropathy can be the presenting feature, not a late one.
- Case series of 25 subjects: it documents the association and the joint pattern, not the frequency in an unselected population.
The 2023 ACR/EULAR Classification Criteria for Calcium Pyrophosphate Deposition Disease
- The first validated classification criteria for symptomatic CPPD disease, developed jointly by the American College of Rheumatology and EULAR
- TWO FINDINGS ARE SUFFICIENT ON THEIR OWN, once joint pain or swelling is present and no alternative disease explains it: crowned dens syndrome, or calcium pyrophosphate crystals in synovial fluid
- Otherwise a weighted score above 56 points, combining clinical features, associated metabolic disorders and laboratory and imaging findings
- Derivation cohort (190 CPPD cases, 148 mimickers): sensitivity 92.2 per cent, specificity 87.9 per cent
- Independent validation cohort (251 cases, 162 mimickers): sensitivity 99.2 per cent, specificity 92.5 per cent
Prevalence of Chondrocalcinosis in the Elderly and its Association with Knee Osteoarthritis - the Framingham Study
- A large population-based study of the elderly, designed specifically to escape the small size and biased selection of previous work on this association
- After controlling for age, radiographic knee osteoarthritis was modestly more common in those with chondrocalcinosis - relative risk 1.52 (95 per cent CI 1.22 to 1.90), the same figure for severe radiographic osteoarthritis
- Chondrocalcinosis was associated with BOTH symptomatic and asymptomatic radiographic osteoarthritis
- THE NUMBER THAT MATTERS FOR TEACHING: only 4.4 per cent of radiographic osteoarthritis is potentially attributable to chondrocalcinosis
- The authors' conclusion is that chondrocalcinosis and osteoarthritis are genuinely associated but increase INDEPENDENTLY with age
Relative Risk of Knee Chondrocalcinosis in Siblings of Index Cases with Pyrophosphate Arthropathy
- Radiographic sibling study: 80 index cases with pyrophosphate arthropathy listed for knee replacement, 122 of their siblings aged 40 or over, and 1729 community participants from knee pain surveys
- Knee chondrocalcinosis in 13 per cent of siblings against 6.9 per cent of the community - adjusted odds ratio 1.2 (95 per cent CI 0.6 to 2.3), NOT significant
- Pyrophosphate arthropathy in 7 per cent of siblings against 3.4 per cent of the community - adjusted odds ratio 1.1 (95 per cent CI 0.4 to 2.7), also not significant
- The main risk factors for both were age, knee pain and knee osteoarthritis - not family history
- Community prevalence figures worth knowing: knee chondrocalcinosis 6.9 per cent, and an age, sex and knee-pain standardised pyrophosphate arthropathy prevalence of 2.40 per cent in those aged 40 and over
Narrowing It Down
The questions, in the order the viva asks them.
Is it truly cartilage calcification? Decide which structure the density lies in before anything else: parallel to subchondral bone, or within a meniscus, TFCC, labrum or symphyseal disc. Globular and in a tendon means hydroxyapatite deposition; a rounded ossicle with a cortex is a loose body or meniscal ossification. This step alone eliminates half the mimics, and it is the step most often skipped.
How old is the patient? Take the age before ordering anything; it is the single most important branch point. Over 65 with knee-limited deposition and no systemic features, idiopathic age-related CPPD is overwhelmingly likely and a blood screen may be all that is needed. Under 55, chondrocalcinosis is a metabolic disease until proven otherwise, and reciting "degenerative" without the screen is the single commonest viva failure.
One joint or many? Screen the knees, wrists and pelvis rather than imaging only the symptomatic joint, and ask specifically about previous injury or surgery to that joint. Monoarticular deposition in a previously injured or operated joint is post-traumatic or degenerative and needs no systemic workup. Polyarticular deposition, particularly including the symphysis pubis and both wrists, substantially raises the probability of a metabolic driver or familial disease and triggers blood testing.
What are the joints themselves doing? Look past the calcification, especially at the second and third metacarpophalangeal joints and the radiocarpal joint. Degenerative change at joints osteoarthritis spares (radiocarpal, elbow, glenohumeral, ankle, second and third metacarpophalangeal) is the flag for CPPD or haemochromatosis, not primary osteoarthritis. The metacarpal-head and joint-space patterns of haemochromatosis and acromegaly are in the table; the CPPD patterns are these:
- Isolated radiocarpal and scapholunate disease with proximal capitate migration is CPPD-driven scapholunate advanced collapse
- Patellofemoral-predominant wear with large subchondral cysts is CPPD
- Normal joint spaces with pure deposition is early or asymptomatic disease
Is the spine involved? Review any available spinal imaging for disc calcification, ligamentum flavum calcification and the region of the odontoid peg. Fused sacroiliac joints alongside multilevel disc calcification suggests ochronosis. Calcification of the transverse ligament of the atlas is crowned dens syndrome, which can present as acute neck pain with pyrexia mimicking meningitis, and which the 2023 ACR/EULAR criteria treat as sufficient on its own to classify CPPD disease.
Are there systemic clues? Examine the skin and liver, ask about renal stones, childhood dental loss and tremor, and take a drug history for proton pump inhibitors and thiazides. Each answer maps onto the setting column of the table.
Is the joint acutely inflamed? If the joint is hot, swollen and painful, stop and aspirate before starting antibiotics, sending fluid for cell count, Gram stain, culture and polarised microscopy. The pathway is now a suspected septic arthritis pathway, and chondrocalcinosis on the radiograph does not change that: crystals in the fluid do not exclude coexisting infection. Never attribute an acutely hot joint to pseudogout on the basis of the radiograph alone.
MCQ Practice Points
Q: Which crystal appearance confirms calcium pyrophosphate deposition on polarised light microscopy?
A: Rhomboid or rod-shaped crystals showing weak POSITIVE birefringence. Urate crystals are needle-shaped with strong NEGATIVE birefringence. Basic calcium phosphate crystals are too small to be seen on light microscopy and require alizarin red staining or electron microscopy.
Q: Which radiographic feature most strongly suggests haemochromatosis rather than idiopathic CPPD?
A: Hook-like osteophytes arising from the radial aspect of the second and third metacarpal heads, with squaring of the metacarpal heads and uniform joint space narrowing. Isolated chondrocalcinosis is non-specific; it is the metacarpophalangeal arthropathy that discriminates.
Q: A 22-year-old with polyarticular chondrocalcinosis has an alkaline phosphatase of 22 units per litre. What is the diagnosis?
A: Hypophosphatasia. It is the only cause of chondrocalcinosis characterised by a persistently LOW alkaline phosphatase. Additional clues are premature deciduous tooth loss, recurrent metatarsal stress fractures and atypical subtrochanteric femoral fractures. Bisphosphonates are contraindicated.
Q: Which three joints form the standard radiographic screening series for chondrocalcinosis?
A: Knees (anteroposterior), wrists (posteroanterior for the triangular fibrocartilage complex) and pelvis (for the symphysis pubis). Involvement of all three establishes systemic deposition and mandates a metabolic screen.
Q: What distinguishes Milwaukee shoulder from CPPD arthropathy of the shoulder?
A: Milwaukee shoulder is basic calcium phosphate (hydroxyapatite) deposition, producing a rapidly destructive glenohumeral arthropathy with massive rotator cuff deficiency, superior humeral head migration and large blood-stained effusions containing little cellular inflammation. CPPD arthropathy causes cartilage-based linear calcification and a more conventional degenerative pattern.
Q: An elderly patient presents with acute severe neck pain, fever and a C-reactive protein of 120. CT shows calcification surrounding the odontoid peg. What is the diagnosis?
A: Crowned dens syndrome — CPPD deposition in the transverse ligament of the atlas. It mimics meningitis, giant cell arteritis and epidural abscess. Recognition prevents an unnecessary infection workup; it responds to colchicine or corticosteroid. In the 2023 ACR/EULAR classification criteria it is one of only two findings SUFFICIENT on its own to classify CPPD disease.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are shown an anteroposterior radiograph of the knee in a 44-year-old man attending with mechanical knee pain after a football injury. There is dense triangular calcification within both menisci and a linear band paralleling the subchondral bone of both femoral condyles. Joint spaces are preserved. Describe the findings and outline your approach.”
“You are shown a radiograph of an 81-year-old woman on day three after a hemiarthroplasty for a hip fracture, who has developed an acutely hot, swollen, exquisitely painful contralateral knee overnight. C-reactive protein is 190 and she is pyrexial at 38.2 degrees. The radiograph shows meniscal and hyaline chondrocalcinosis with moderate patellofemoral narrowing.”
“You are shown a posteroanterior wrist radiograph in a 63-year-old woman with a two-year history of radial-sided wrist pain and reduced grip. There is dense calcification in the triangular fibrocartilage complex, widening of the scapholunate interval to 5 millimetres, radioscaphoid joint space narrowing with sclerosis, and proximal migration of the capitate. There is no history of trauma.”
Define before you differentiate
- Hyaline cartilage: thin linear band parallel to subchondral bone
- Fibrocartilage: amorphous density within meniscus, TFCC, symphysis, labrum, annulus
- Not chondrocalcinosis: tendon (hydroxyapatite), capsule, vessels, loose bodies, meniscal ossicle
Screening series
- Anteroposterior knees
- Posteroanterior wrists (TFCC)
- Anteroposterior pelvis (symphysis pubis)
Bloods that change management
- Calcium, phosphate, PTH — hyperparathyroidism
- Ferritin and transferrin saturation — haemochromatosis
- Magnesium — hypomagnesaemia, Gitelman, chronic proton pump inhibitor use
- Alkaline phosphatase — a LOW value means hypophosphatasia
- Thyroid function; caeruloplasmin and urinary copper if Wilson suspected
Age thresholds
- Under 55: full metabolic screen mandatory
- Over 65 with knee-limited deposition: usually idiopathic age-related
- Under 40 with polyarticular disease: consider familial ANKH mutation and hypophosphatasia
CPPD arthropathy pattern
- Radiocarpal and second and third metacarpophalangeal disease with hook osteophytes
- Patellofemoral-predominant knee degeneration
- Involvement of joints osteoarthritis spares: elbow, glenohumeral, ankle
- Large subchondral cysts disproportionate to joint space loss
- Scapholunate advanced collapse without trauma
Red flags
- Hot joint: aspirate before antibiotics; crystals do not exclude sepsis
- Acute neck pain with fever: consider crowned dens syndrome on CT
- Rapidly destructive shoulder with cuff loss: Milwaukee shoulder, not CPPD
- Young patient with low alkaline phosphatase: avoid bisphosphonates
When to do nothing
- Asymptomatic incidental meniscal calcification over age 70
- Normal metabolic screen and no systemic features
- No follow-up imaging and no treatment indicated