Biological restoration of femoral bone stock in revision hip arthroplasty using morsellised allograft, layered retrograde impaction and a cemented polished double-taper stem
- Impaction grafting is the only revision femoral technique that RESTORES bone stock rather than bypassing it — its principal indication is the young patient with cavitary bone loss who will likely need further revision.
- The construct works only with a force-closed, polished, collarless, double-tapered stem (Exeter philosophy): controlled subsidence at the stem-cement interface generates radial compressive (hoop) load that stimulates graft incorporation; the graft-cement composite itself must be rigidly stable.
- Graft: fresh-frozen morsellised femoral head allograft, cleared of soft tissue and cartilage; larger chips distally for axial stability, finer proximally; vigorous layered retrograde impaction over a guidewire with sized tamps/phantoms builds a neomedullary canal.
- Segmental (uncontained) defects must be converted to contained defects with metal mesh and cerclage before impaction; an incompetent tube cannot resist hoop stress.
- Prophylactic cerclage wiring of thin or ectatic cortex before vigorous impaction is the key manoeuvre to prevent intraoperative fracture (reported up to 10-15 percent).
- Incorporation is real but PARTIAL and slow, and should be described that way. Tagil's human biopsies 1.5 years after impaction grafting still showed large areas unremodelled and sometimes unrevascularised, with necrotic graft trabeculae in fibrous tissue - a radiograph showing trabecular remodelling is not evidence the graft has become host bone throughout.
- “Distinguish acceptable stem subsidence WITHIN the cement mantle (design feature of a polished taper, usually 1-2 mm) from catastrophic subsidence of the cement-graft construct (technical failure from inadequate impaction).
- “Never use a composite-beam (shape-closed, roughened or collared) stem with impaction grafting — subsidence at a bonded stem-cement interface is failure, not function.
- “If the femoral tube cannot be reconstructed to a stable contained cylinder even with mesh, abandon impaction grafting for a distally fixed tapered fluted stem or proximal femoral replacement.
Rationale and Patient Selection
Femoral impaction bone grafting (IBG) was popularised in Exeter (Gie, Ling) and Nijmegen (Slooff, Schreurs) in the late 1980s to early 1990s. It addresses the central problem of femoral revision in the young patient: every alternative strategy consumes or bypasses bone, whereas IBG rebuilds it.
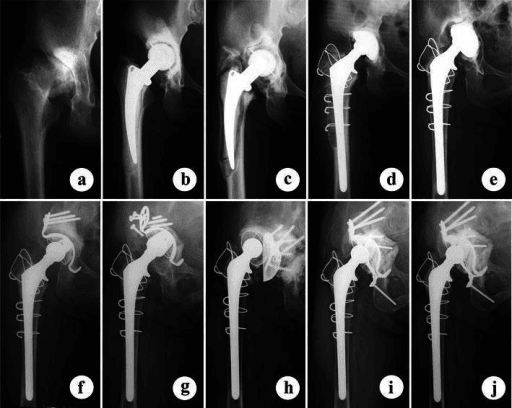
How the strategies differ. The strategy in a deficient femur is chosen by whether bone stock must be rebuilt, bypassed or substituted. Impaction grafting with a cemented polished taper rebuilds it; a distally fixed stem bypasses the proximal femur and accepts proximal stress-shielding and a harder re-revision; a proximal femoral replacement or allograft-prosthesis composite substitutes for it, which is salvage rather than restoration.
- Fixation principle
- Force-closed taper in cement on compacted allograft
- Effect on bone stock
- Restores — graft remodels to host bone
- Best-suited patient
- Young patient, cavitary loss, containable tube
- Fixation principle
- Distal press-fit in diaphysis
- Effect on bone stock
- Bypasses proximal femur; proximal stress-shielding
- Best-suited patient
- Most Paprosky III defects; workhorse in many units
- Fixation principle
- Distal scratch-fit, needs 4-5 cm isthmus
- Effect on bone stock
- Bypasses; risk of stress-shielding and difficult re-revision
- Best-suited patient
- Type II-IIIA with adequate isthmus
- Fixation principle
- Megaprosthesis or allograft-prosthesis composite
- Effect on bone stock
- Sacrifices or substitutes proximal femur
- Best-suited patient
- Elderly, low demand, non-reconstructable Type IV
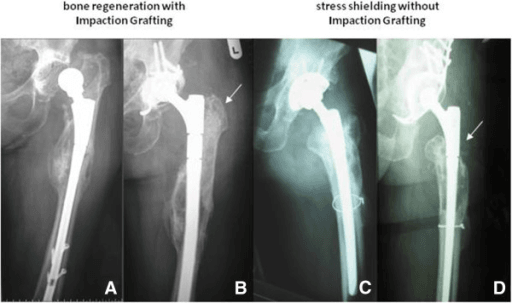
Who it is for. The decision turns on infection status, the Paprosky defect type, whether the cortical tube is contained or can be made so, and what the patient will demand of the reconstruction. The younger, higher-demand patient in whom re-revision is anticipated is the one in whom restoring bone stock is strategically valuable; the elderly, low-demand patient favours a quicker construct, because IBG is technically demanding and time-consuming.
Indications. The defect must be contained or containable, and the patient must stand to gain from the bone:
- Paprosky type II and IIIA cavitary or ectatic defects with an intact cortical tube, the classic indication
- Paprosky IIIB and selected IV, and Vancouver B3 periprosthetic fractures, provided the tube can be reconstituted with mesh, cerclage and/or strut allograft to contain the graft
- Wide, capacious "stove-pipe" canals where a cemented stem alone would have an excessive mantle and an uncemented stem cannot obtain fit
Contraindications. Do not graft into infection, and do not graft into a defect you cannot close:
- Active infection: staged reconstruction only after eradication
- Segmental loss that cannot be converted to a contained defect
- Inability to source adequate allograft, typically 2 to 4 fresh-frozen femoral heads
- Very elderly or low-demand patients, where a quicker distally fixed stem or proximal femoral replacement is more pragmatic
"Impaction grafting is chosen when the priority is to leave the femur with more bone than you found — a biological reconstruction for the patient who will outlive this revision."
Biology of Graft Incorporation
Morsellised, impacted fresh-frozen allograft behaves quite differently from structural bulk allograft, which remains largely a dead scaffold with only superficial creeping substitution. Incorporation is real, but it is partial and slow, and it should be described that way.
The impacted graft is initially a dead, mechanically stable particulate scaffold. Host haematoma infiltrates it, and inflammatory cells and vascular buds begin to invade from the endosteal surface and from any point of contact with bleeding host bone.
Osteoclasts resorb dead trabecular fragments while osteoblasts lay new woven bone on graft surfaces: classical creeping substitution, far more complete than in bulk graft because the particulate structure is fully permeable to vascular ingrowth. Rigid mechanical stability from impaction and compressive load from the taper-slip stem are prerequisites; micromotion produces fibrous encapsulation instead.
Woven bone remodels to lamellar trabecular bone orientated along load lines, and radiographs show trabecular remodelling and cortical repair or thickening. Do not over-read this: the reconstructed segment is a composite of living host bone and residual dead graft, human biopsy material shows areas that remain unremodelled years later, and the radiographic appearance runs ahead of the histology.
Progressive corticalisation around the cement mantle; the reconstructed segment approaches normal bone architecture, which brings any future revision technically closer to a primary procedure.
What incorporation needs. A contained defect, a viable vascular host bed, rigid mechanical stability of the graft mass, compressive rather than shear loading, absence of infection, and graft of adequate quality, free of fat and soft tissue.
Graft Preparation
Source. Fresh-frozen femoral head allograft from a licensed bone bank, typically 2 to 4 heads for a femur. All cartilage, cortical shell remnants and soft tissue are stripped before milling.
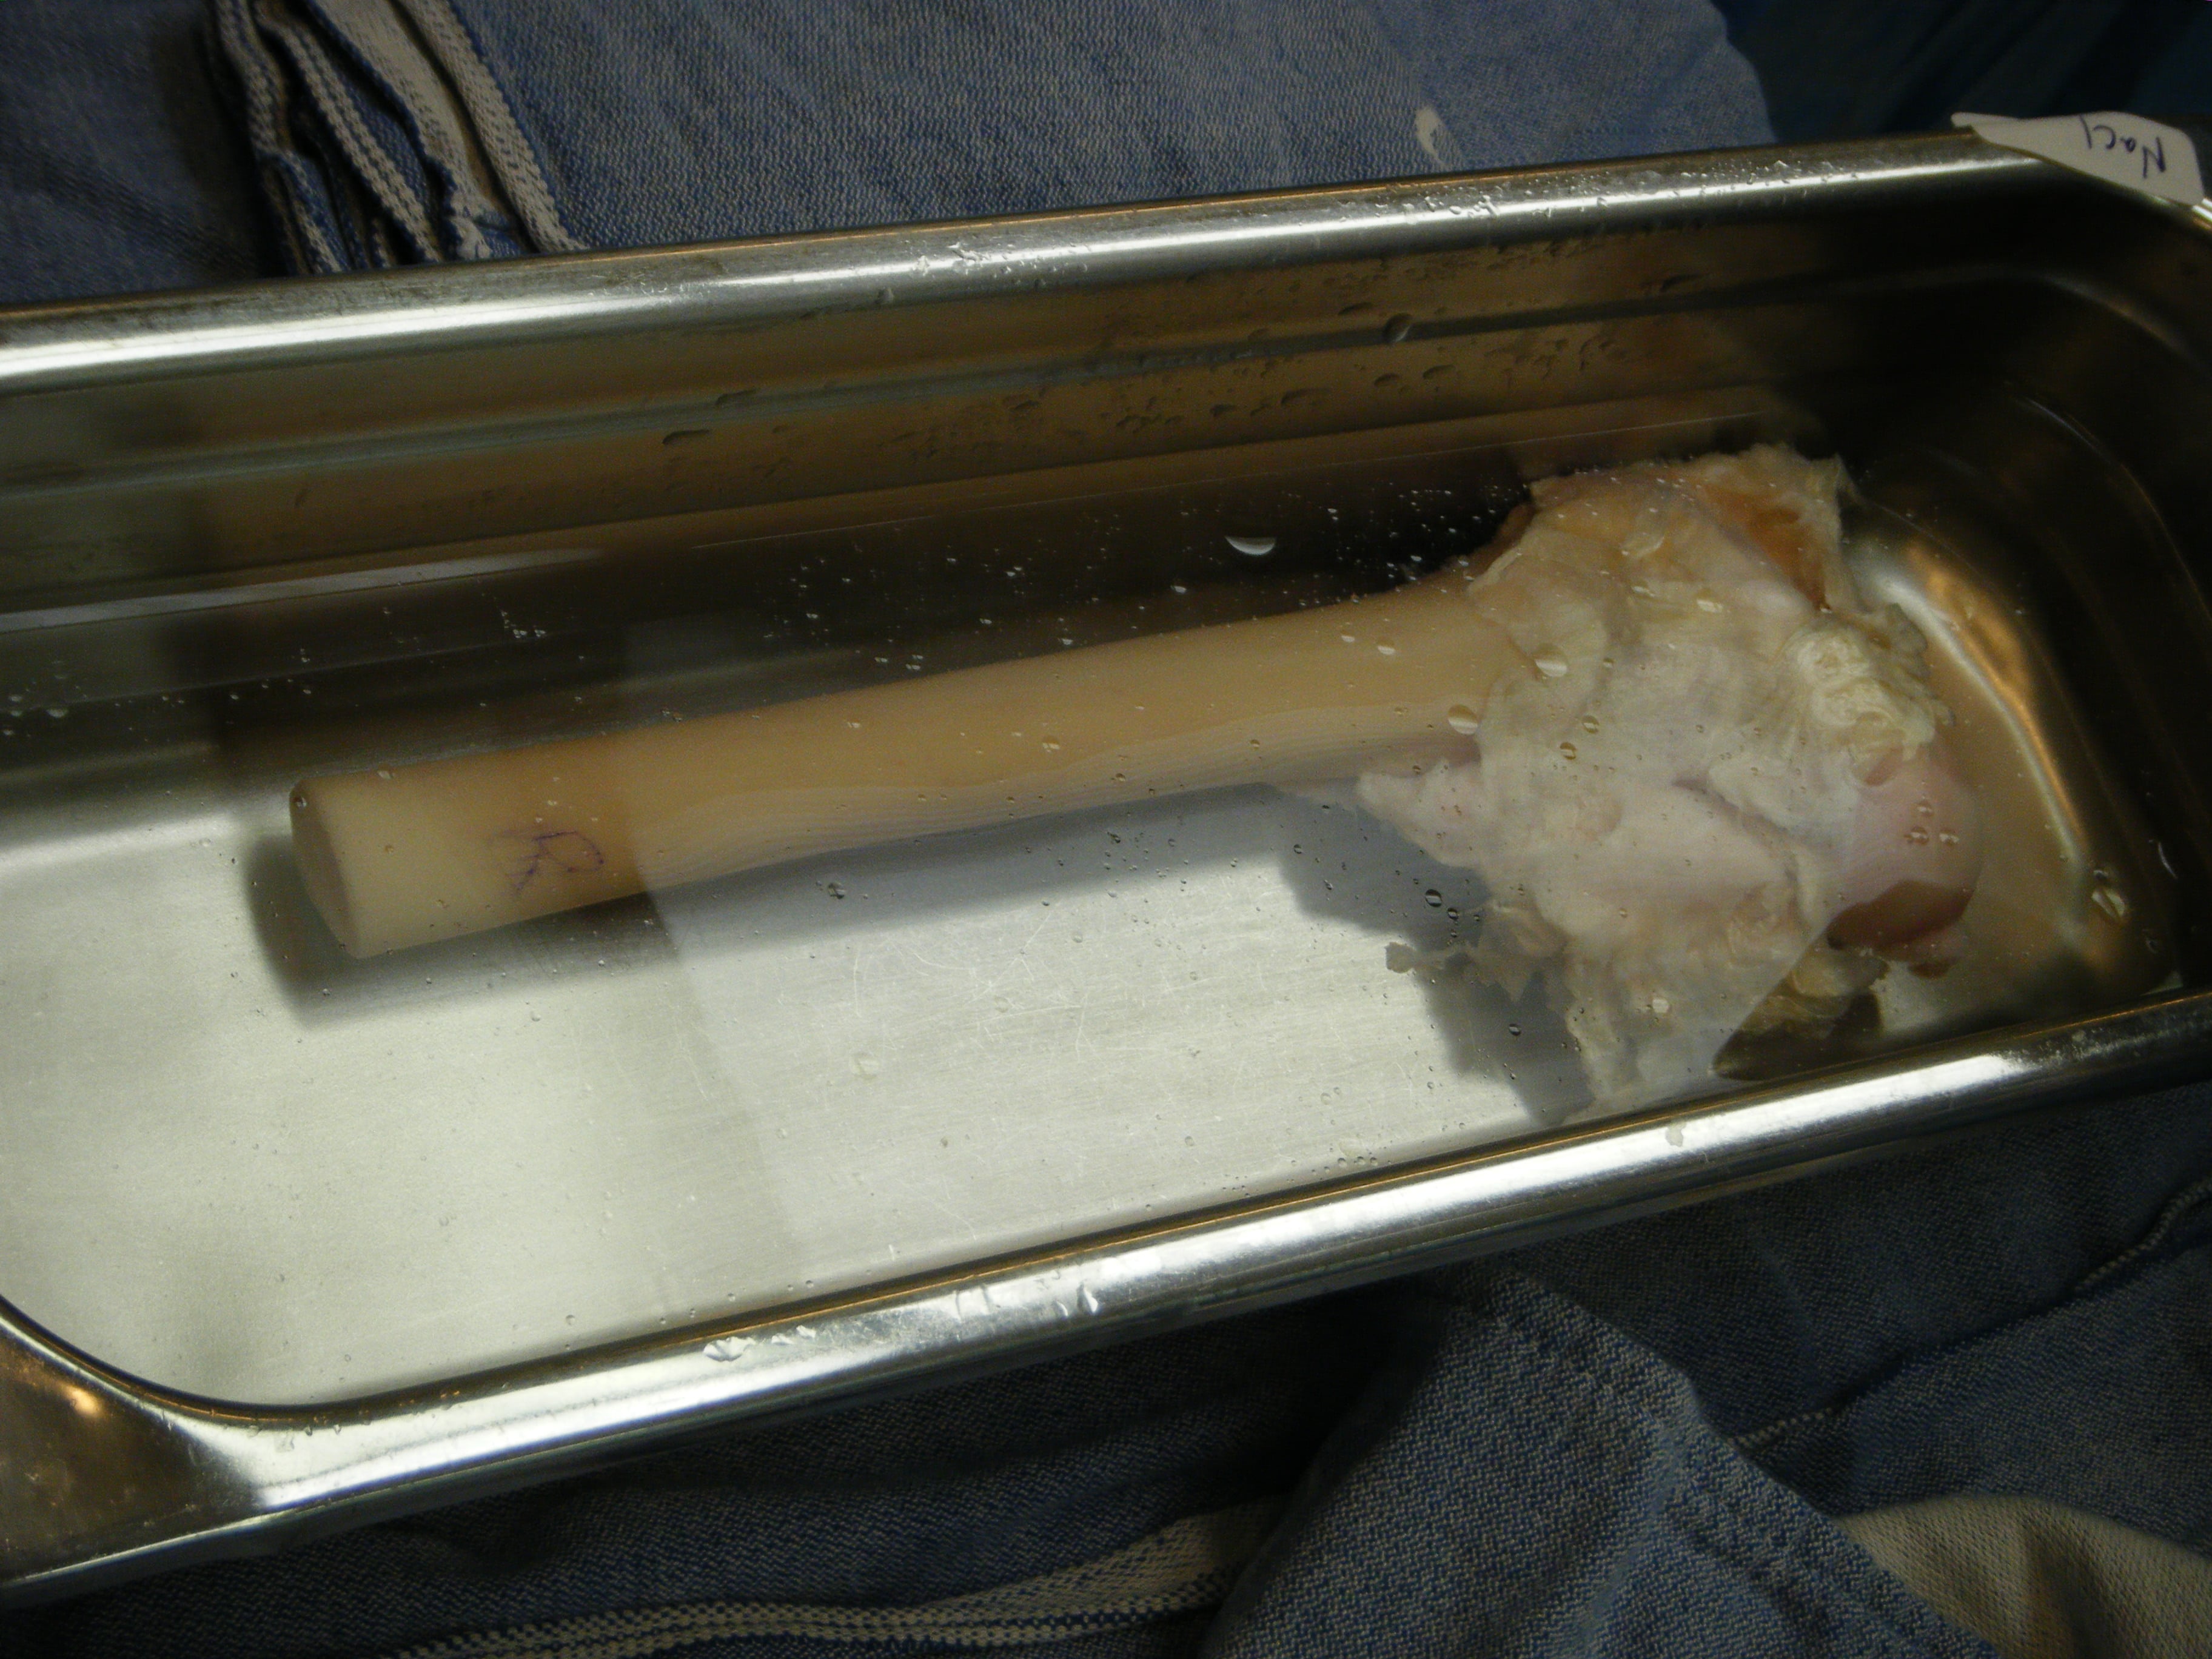
Chip size by zone. The distal canal takes 8 to 10 mm chips, milled with a bone mill or rongeurs. Large chips interlock and resist axial and shear load where distal stability is most critical; chips milled too fine distally lose interlock and allow subsidence. The last proximal layers use finer chips of roughly 3 to 5 mm, which pack around the tamps into metaphyseal irregularities and fill the proximal cavity densely. The proximal pitfall is over-milling to a slurry or paste, which has no mechanical interlock at all.
Washing. Washed graft is now preferred: warmed saline pulsed lavage over a sieve, drained, and impacted slightly damp. Washing removes marrow fat, blood and immunogenic cellular debris; fat acts as a lubricant, so washed graft achieves higher shear strength and impaction density in bench testing, and washing may reduce immunogenic load and fat embolisation. Chip size is set at milling and is unchanged by washing. Two pitfalls: impacting sodden rather than damp graft, and leaving fat in situ and blaming the tamps for poor density.
The case for unwashed graft. The classic Exeter series milled and impacted the graft directly, and the results carded below were obtained with unwashed graft. Unwashed graft retains marrow elements and theoretically osteoinductive proteins, and its published results are historically excellent; against it, fat lubrication limits the achievable impaction density, and that mechanical argument now dominates in most units. The case for washing rests on laboratory and practice-based reasoning, not on a clinical comparison.
Antibiotic in the graft. Some surgeons add antibiotic powder, for example vancomycin, to the graft in higher-risk cases for local elution at the graft bed. The evidence is limited; elution data are supportive, but this is adjunctive and no substitute for debridement and systemic cover.
Operative Technique (Exeter / X-change)
Position and approach. Lateral decubitus on a supported table. The posterior approach is most common because it is extensile and allows an extended trochanteric osteotomy if needed; an anterolateral approach is acceptable according to surgeon preference.
Imaging and equipment. Full-length femoral radiographs are templated for a stem that bypasses distal defects by at least two cortical diameters where possible, and an image intensifier is available for guidewire and plug position and for fracture surveillance. The dedicated X-change (or equivalent) instrumentation comprises:
- Intramedullary plug and central guidewire
- Cannulated distal impactors
- Modular proximal tamps and phantom stems, sized one size up from the definitive stem to create the cement mantle space
- Slap hammer
- Mesh and cable or cerclage set
- Cement gun with long revision nozzles
Preparation and clearance. Infection is excluded preoperatively with inflammatory markers and aspiration where indicated, and multiple deep tissue samples are taken at surgery. Remove the failed stem, then meticulously clear all cement, membrane and fibrous tissue from the endosteum back to bleeding host bone, because retained membrane blocks graft incorporation. Culture the membrane.
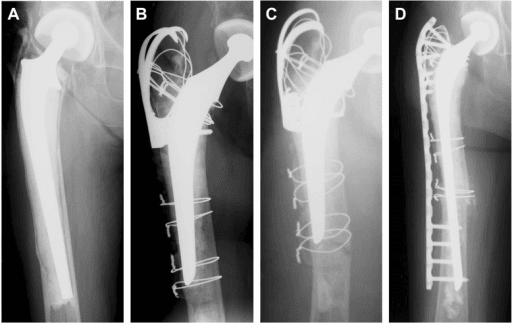
Assess the tube and contain it. Probe for occult perforations and thin segments; old cement-removal tracks are notorious. A segmental defect is converted to a contained one by applying stainless-steel mesh over the calcar or diaphyseal deficiency, secured with cerclage wires or cables, recreating a cylindrical tube; strut allograft with cables may reinforce a grossly deficient diaphysis. Place prophylactic cerclage around thin or ectatic segments before any impaction begins.
Distal plug and guidewire. Insert the intramedullary restrictor, a threaded plug with a guidewire eyelet in the X-change system, approximately 2 cm distal to the planned stem tip, and confirm the level on the image intensifier. The plug defines the cement mantle length and gives the distal graft column something to impact against. Pass the central guidewire through it: every cannulated impactor and phantom runs over this wire, which keeps the neomedullary canal centred and prevents varus malposition.
Distal layered impaction. Deliver the 8 to 10 mm chips and impact them retrogradely in layers with cannulated distal impactors of decreasing then appropriate diameter, striking firmly; this is deliberately vigorous. Build a dense distal column above the plug.
Vigorous impaction and long-column cement pressurisation both embolise fat and marrow contents. Communicate with the anaesthetic team before these steps, especially in patients with cardiopulmonary comorbidity — hypotension and desaturation events are well described, analogous to bone cement implantation syndrome.
Proximal impaction with phantoms. Switch to the modular proximal tamps and phantom stems, oversized replicas of the stem. Add the finer chips and impact around and with the phantom, working proximally layer by layer and packing graft into metaphyseal cavities and against the mesh.
The stability test. The final phantom must sit at the templated level and be absolutely stable to axial push and rotational torque; any movement means further impaction. This single step determines whether the reconstruction succeeds. The product is a neomedullary canal, a tube of densely compacted allograft sized to accept the definitive stem plus a circumferential cement mantle of roughly 2 mm.
Cementation. Remove the phantom and guidewire without disturbing the graft. Do not pulse-lavage the neomedullary canal, which would wash out graft; pack and dry it gently. Gun-inject standard-viscosity antibiotic-loaded cement retrogradely in a slightly earlier, doughier phase than for a primary, then pressurise with a proximal seal. Cement interdigitates into the graft to form a cement-graft composite, and some penetration into the graft is expected and desirable.
The stem. Insert the polished, collarless, double-tapered stem (Exeter) slowly to templated depth in correct version, with a centraliser, and hold until cure. The centraliser maintains the distal mantle and accommodates taper subsidence.
At risk. The sciatic nerve behind a posterior approach; a thin cortex, which fractures or perforates during impaction; and the circulation, during both impaction and pressurisation.
Closure and aftercare. Check stability, repair the capsule and short external rotators, and close in layers. Weight-bearing is traditionally protected, touch to partial, for 6 to 12 weeks, progressing with radiographic evidence of a stable construct; earlier weight-bearing protocols exist, but the graft-cement composite is most vulnerable early. Serial radiographs at 6 weeks, 3, 6 and 12 months monitor subsidence and remodelling.
C-PIG-CSSequence of Femoral Impaction Grafting
Hook:Contain the pig before you cement the stem — you cannot impact into an open field.
Complications: Rates, Prevention, Management
What actually fails. Impaction grafting essentially does not fail by loosening. In Halliday's 226 hips, survivorship at 10 to 11 years was 99.1% with reoperation for symptomatic aseptic loosening as the endpoint and 90.5% with any further femoral operation as the endpoint, and ten of the twelve aseptic reoperations were for femoral fracture. The gap is fracture, and containment, cerclage and a stem long enough to bypass compromised bone are the technical answers to it.
Not only the tamp. In Te Stroet's long-stem series, intraoperative fractures or fissures occurred in 24% of patients but none occurred during impaction of the graft, which puts the exposure and the extraction, rather than the impactor alone, under suspicion.
- Mechanism
- Vigorous impaction and cement pressurisation against a thin, ectatic cortex; stress riser at old screw holes or window edges
- Approximate rate
- Up to 10 to 15 percent in reported series
- Prevention
- Prophylactic cerclage of thin cortex before impaction; mesh over uncontained defects; long stem bypassing defects by two cortical diameters; controlled impaction under fluoroscopic surveillance
- Salvage
- Intraoperative: cerclage cables, longer stem, strut allograft. Postoperative: treat as periprosthetic fracture — fix if construct stable, revise to a long distally fixed stem if unstable
- Mechanism
- Under-impaction leaves a compressible graft bed; the whole construct migrates rather than the stem settling within cement
- Approximate rate
- Technique-dependent; the signature failure of under-impaction
- Prevention
- Vigorous layered impaction from distal to proximal; phantom must be axially and rotationally rock-stable before cementing; adequate chip size distally; washed graft for better interlock
- Salvage
- Minor and stabilising: observe with serial radiographs. Progressive with symptoms or instability: revision, usually to a distally fixed tapered fluted stem
- Mechanism
- A shape-closed or uncemented design cannot subside minutely within cement to load the graft; taper-slip cemented stems are the intended partner for impaction grafting
- Approximate rate
- Avoidable by design selection
- Prevention
- Select a polished collarless tapered stem; cement into the impacted graft bed; do not substitute an uncemented stem into a graft mantle
- Salvage
- Recognise early; revision to the correct stem philosophy or to a distally fixed stem if the graft bed is already compromised
- Mechanism
- Uncontained cortical defect or a calcar deficiency allows chips to escape during impaction, so pressure is never generated
- Approximate rate
- Related to defect grade and containment technique
- Prevention
- Convert every uncontained defect to a contained one with metal mesh and cerclage before impacting; check containment at each level
- Salvage
- Re-contain and re-impact at the same sitting; if containment cannot be restored, abandon impaction grafting for a distally fixed stem
- Mechanism
- Large dead allograft volume revascularises slowly; poor host bed, chip size or infection blocks creeping substitution
- Approximate rate
- Radiographic incorporation is usually progressive but incomplete in part of the mantle
- Prevention
- Washed, appropriately sized fresh-frozen chips; vigorous impaction to maximise chip-to-host contact; exclude infection preoperatively; avoid immediate unprotected full weight-bearing
- Salvage
- Observe if the construct is stable; revision to a distally fixed tapered fluted stem if progressive migration or pain supervenes
- Mechanism
- A large volume of avascular allograft with no blood supply is an ideal substrate; any residual organism colonises the whole mantle
- Approximate rate
- Comparable to other complex revisions, broadly 2 to 5 percent
- Prevention
- Exclude infection preoperatively; antibiotic-loaded cement; consider antibiotic-supplemented graft; meticulous asepsis given the large allograft volumes
- Salvage
- Standard periprosthetic joint infection principles — usually two-stage exchange; the infected graft must be removed in its entirety
- Mechanism
- Revision soft-tissue envelope, abductor deficiency and version error at stem insertion into a cement mantle
- Approximate rate
- Elevated versus primary hip arthroplasty, as for all revisions
- Prevention
- Careful version control during stem insertion, soft-tissue repair, larger head or dual mobility in high-risk patients
- Salvage
- Closed reduction and address the cause; revise for recurrent instability
- Mechanism
- Impaction and cement pressurisation drive marrow contents into the venous sinusoids
- Approximate rate
- Uncommon but recognised
- Prevention
- Washed graft carries less fat; staged communication with the anaesthetist before each pressurisation; vigilance in cardiac patients
- Salvage
- Pause impaction and pressurisation; supportive resuscitation
Guidelines, Registries & Global Practice
- Global variation: IBG is most established in the United Kingdom, the Netherlands and Scandinavia, reflecting the Exeter and Nijmegen heritage and strong bone-banking infrastructure. In North America, distally fixed uncemented tapered fluted stems dominate femoral revision; IBG is a niche technique in selected young patients.
- Registry evidence: revision-of-revision data from the National Joint Registry (UK), Swedish Hip Arthroplasty Register and Dutch (LROI) registries confirm cemented revision with impaction grafting as a durable option in appropriate defects, while also documenting the worldwide shift toward uncemented modular and monoblock tapered fluted stems for most femoral revisions. Registries consistently show revision outcomes are unit- and volume-dependent — IBG in particular is a technique with a documented learning curve.
- Society guidance: no society mandates a single femoral revision strategy. BOA/BHS revision hip networks in the UK recommend complex femoral bone loss be managed in specialist revision units with access to bone banking and the full range of implants. EFORT and AAOS revision instructional material present IBG as the bone-stock-restoring option for contained defects in younger patients.
- Resource considerations: IBG requires a licensed bone bank, fresh-frozen allograft supply, dedicated instrumentation and considerable theatre time. In settings without bone banking, alternatives include distally fixed stems, or (with caution) processed/irradiated allograft with inferior mechanical and biological properties. Cost of allograft versus modular revision implants varies by region and can favour either strategy.
Biomechanics: Why the Polished Taper Is Essential
Force-closed, or taper-slip. The polished Exeter-type stem is not bonded to cement. Under load it subsides minutely within the cement mantle, wedging as a taper, and that converts axial load into radial compressive hoop stress transmitted through cement into the impacted graft and out to host cortex. Compressive loading of graft is osteogenic, Wolff's law applied to allograft incorporation, and Tagil's loaded grafts remodelled faster than unloaded ones; shear loading causes resorption and fibrous tissue.
Why a shape-closed stem cannot do it. A composite-beam stem, whether matt, roughened or collared, is bonded to its cement. Any subsidence at a bonded interface represents interface failure, and the load it transfers to the graft is predominantly shear, which resorbs graft and produces early massive subsidence. Choosing the wrong stem is a design-stage error, and an avoidable one.
Two interfaces, two meanings of subsidence. Expected behaviour is early subsidence of the stem at the stem-cement interface of the order of 1 to 2 mm, then stabilisation: a design feature, mirrored in RSA studies of primary Exeter stems, seen on the radiograph as the centraliser space closing with no migration of the cement mantle and no lucency at the cement-graft or graft-host levels. Pathological behaviour is subsidence at the cement-graft or graft-host interface, the whole composite migrating, which indicates inadequate impaction or an uncontained defect and predicts failure.
Controversies & Areas of Uncertainty
- Washing the graft: mechanically superior and now majority practice, but the historic Exeter results were achieved unwashed; whether washing removes clinically meaningful osteoinductive signal remains debated.
- IBG versus tapered fluted stems in Paprosky III: fluted stems are faster, forgiving and reliable but stress-shield the proximal femur; IBG restores bone but is slower with higher fracture risk. Most units reserve IBG for the young; direct comparative data are limited and largely observational.
- Weight-bearing protocols: traditional protected weight-bearing for 6 to 12 weeks versus earlier loading to stimulate graft — no high-level evidence; practice varies.
- Graft substitutes and extenders: mixing allograft with tricalcium phosphate/hydroxyapatite granules or bioactive glass to economise allograft shows promising series but long-term equivalence to pure allograft is unproven.
- Vancouver B3 fractures: IBG with a long stem and mesh is described with good results in specialist hands, but most surgeons prefer distal fixation in the fracture setting.
- Chip size and vibration/standardised impaction devices: optimal particle size distribution and force-controlled impaction systems remain research topics; current practice is craft-based.
MCQ Practice Points
Q: Which stem design is mandatory for femoral impaction grafting? A: A force-closed (taper-slip) design — polished, collarless, double-tapered (Exeter type). Controlled subsidence within the cement mantle generates radial compression of the graft; shape-closed stems load the graft in shear and fail.
Q: What graft chip sizes are used and where? A: Larger chips of 8-10 mm distally for interlock and axial stability; finer chips of roughly 3-5 mm proximally to pack metaphyseal cavities. Graft must be cleared of cartilage, fat and soft tissue.
Q: Where is the intramedullary restrictor placed? A: Approximately 2 cm distal to the planned stem tip, with a central guidewire through it to keep cannulated impactors and phantoms centred and prevent varus malposition.
Q: What is the signature intraoperative complication and its prevention? A: Femoral fracture, reported in up to 10-15 percent — prevented by prophylactic cerclage of thin or ectatic cortex, mesh over defects, and controlled impaction with fluoroscopic surveillance.
Q: Why wash the morsellised allograft? A: Pulsed-lavage washing removes marrow fat (a lubricant), substantially increasing impacted graft shear strength and stability (Dunlop and colleagues), and reduces embolic and immunogenic load.
Q: What distinguishes impaction grafting from all other femoral revision strategies? A: It restores bone stock — biopsy and retrieval studies show revascularisation and remodelling of impacted allograft to viable trabecular bone — making any future revision easier; alternatives bypass or sacrifice bone.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 52-year-old with a loose cemented femoral stem 15 years after arthroplasty for developmental dysplasia. Radiographs show a widened, thin-walled proximal femur with cavitary loss extending into the diaphysis but an intact cortical tube — Paprosky IIIA. Infection has been excluded. How will you reconstruct the femur and why?”
“Eighteen months after femoral impaction grafting with an Exeter stem, radiographs show the stem has subsided 2 mm relative to the cement since the immediate postoperative film. The patient is asymptomatic. The registrar is worried. Interpret and advise.”
“During vigorous distal impaction in a Paprosky IIIA femur, you feel a sudden give and the impactor advances. Fluoroscopy shows a spiral fracture of the diaphysis at the level of a previously thinned cortical segment. Walk me through your management.”
“A 58-year-old undergoing femoral revision has a loose stem with a 5 cm segmental defect of the medial calcar and proximal medial cortex, but a good diaphyseal tube distally. You wish to preserve bone stock. Can impaction grafting still be used, and how?”
Indications & Selection
- Young/high-demand patient where restoring bone stock matters
- Paprosky II-IIIA cavitary loss with intact cortical tube — classic case
- IIIB/IV and Vancouver B3 only if containable with mesh and cerclage
- Contraindications: active infection, uncontainable defect, no allograft supply
Graft
- Fresh-frozen morsellised femoral head allograft, 2-4 heads
- Strip cartilage, fat, soft tissue; wash with pulsed lavage (better shear strength)
- Chips 8-10 mm distally, 3-5 mm proximally — no slurry
Technique Sequence
- Explant, remove all cement and membrane, culture, assess tube
- Mesh plus cerclage for segmental defects; prophylactic wires on thin cortex
- Plug 2 cm below planned stem tip; central guidewire
- Layered retrograde impaction; phantom must be rock stable axially and rotationally
- Standard-viscosity cement, retrograde, pressurised; polished collarless double-taper stem
Biomechanics & Biology
- Force-closed taper-slip: axial load to radial compression to graft osteogenesis
- 1-2 mm stem-within-cement subsidence is design; construct migration is failure
- Graft incorporates: revascularisation, creeping substitution, remodelling to viable trabecular bone (Linder; Ullmark)
Complications
- Femoral fracture up to 10-15 percent — prophylactic cerclage prevents
- Massive subsidence = under-impaction or lost containment; salvage with distally fixed fluted stem
- Infection ~2-5 percent; fat embolisation during impaction/pressurisation — warn anaesthetist
Evidence
- Gie/Ling 1993 JBJS Br — technique description
- Exeter and Nijmegen (Schreurs/Slooff) long-term series — durable survivorship beyond 10-15 years
- Dunlop 2003 JBJS Am — washing improves graft mechanics
- Histology confirms true biological restoration of bone stock
Evidence Base
Impacted Cancellous Allografts and Cement for Revision Total Hip Arthroplasty
- The founding Exeter-Nijmegen description: impacted morsellised cancellous allograft with cement for femoral fixation where bone stock has been lost.
- 56 hips reviewed at 18 to 49 months, with few complications and a majority of satisfactory results.
- Radiographic evidence of incorporation of the graft.
- The authors' own conclusion is markedly more tentative than the technique's later reputation: 'Further study and review are necessary, but the use of the method appears to be justified.'
Femoral Impaction Grafting with Cement in Revision THR - Evolution of the Technique and Results
- 226 hips in 207 patients from one centre, all operated more than five years previously - and performed by THIRTY-TWO different surgeons, not a single expert.
- TWO SURVIVORSHIP FIGURES FROM THE SAME COHORT, AND THE GAP BETWEEN THEM IS THE WHOLE MESSAGE: 90.5 per cent (CI 82 to 98) with ANY further femoral operation as the endpoint, against 99.1 per cent (CI 96 to 100) for reoperation for symptomatic aseptic loosening, at 10 to 11 years.
- Of the 12 stems needing further surgery for aseptic failure, TEN were for femoral FRACTURE and only two for loosening.
- Early post-operative infection in 2 hips (1 per cent). No deaths attributable to the revision.
- The series changed the technique: increased use of LONGER stems, indicated where host bone around a short stem tip is compromised, in major bone loss, or when a femoral fracture occurs.
The Use of a Long Stem Cemented Femoral Component in Revision THR - Five to 16 Years
- 37 consecutive patients, mean age 76, mean follow-up 9 years (5 to 16), using a cemented Exeter stem of at least 205 mm for extensive femoral defects. Impaction bone grafting was used in 24 (65 per cent).
- Intra-operative fractures or fissures occurred in 9 patients (24 per cent) - BUT NONE OCCURRED DURING IMPACTION OF THE BONE GRAFT.
- Post-operative periprosthetic fracture in 2 patients (5 per cent), both plated.
- Nine-year survival: 96.3 per cent with all-cause re-revision as the endpoint, and 80.7 per cent including re-operation for any reason.
- THERE WERE NO RE-REVISIONS FOR ASEPTIC LOOSENING. The single reconstruction failure was for recurrent dislocation, converted to excision arthroplasty.
The Morselized and Impacted Bone Graft - Animal Experiments on Proteins, Impaction and Load
- A thesis testing why the technique works, against three hypotheses: osteoinduction from released proteins, osteoconduction improved by impaction, and mechanical load.
- PROTEINS MATTER: deproteinised graft admitted less bone ingrowth than untreated graft.
- IMPACTION IMPAIRS EARLY INGROWTH - the opposite of the intuitive hypothesis. Raising bone volume fraction from 35 to 65 per cent REDUCED new bone ingrowth at six weeks.
- That reduction had disappeared by 12 weeks - a catch-up phenomenon - and exogenous osteogenic protein-1 restored six-week ingrowth into impacted graft.
- LOAD ACCELERATES REMODELLING: in a rabbit knee model, grafts loaded through a complete prosthesis showed increased new bone formation AND increased resorption compared with unloaded grafts.
- IN HUMANS: biopsies from four patients 1.5 years after impaction grafting of vertebral bodies showed LARGE AREAS STILL UNREMODELLED AND SOMETIMES UNREVASCULARISED, with necrotic graft trabeculae embedded in fibrous tissue.