The Central Muscle Beneath the Plantar Fascia
- It is the CENTRAL muscle of the FIRST plantar layer, lying immediately deep to the central band of the plantar aponeurosis - not the second layer, which is quadratus plantae, the lumbricals and the long flexor tendons.
- Origin from the MEDIAL PROCESS OF THE CALCANEAL TUBEROSITY and the deep surface of the plantar aponeurosis - it shares its origin with the plantar fascia, which is why the two diseases overlap.
- Four tendons insert into the sides of the MIDDLE phalanges of toes 2 to 5, each splitting to allow the flexor digitorum longus tendon to pass through - the TENDON CHIASMA (chiasma tendinum).
- Innervated by the MEDIAL plantar nerve (S1, S2), which runs along its deep-medial surface between it and abductor hallucis.
- The BAXTER NERVE (first branch of the lateral plantar nerve) passes between the deep fascia of abductor hallucis and the medial margin of quadratus plantae, then runs laterally along the DEEP SURFACE of flexor digitorum brevis to abductor digiti minimi - two entrapment points, and the reason up to around a fifth of recalcitrant heel pain is neural rather than fascial.
- “The muscle shares a footprint with the plantar fascia on the medial calcaneal tuberosity, so an enthesopathy affects both - the reason a partial fasciotomy inevitably encounters the FDB origin.
- “Release only the MEDIAL third to half of the plantar fascia; a complete release causes longitudinal arch collapse and lateral column pain.
- “The FDB tendon splits round the FDL tendon in the foot; in the hand the FDS tendon splits round the FDP. Same architecture, opposite naming logic to remember.
- “The Baxter nerve is a PURE MOTOR problem clinically - it produces heel pain and abductor digiti minimi weakness with NO sensory loss, which is why it is missed.
Overview
Flexor digitorum brevis is the central muscle of the first plantar layer of the sole. It arises from the medial process of the calcaneal tuberosity and the deep surface of the plantar aponeurosis, and divides into four tendons which insert into the sides of the middle phalanges of the second to fifth toes.
Its surgical importance has almost nothing to do with toe flexion. It matters because of where it sits: it shares an origin with the plantar aponeurosis on the medial calcaneal tuberosity, it forms the floor of the plane in which the plantar fascia is released, and its deep fascia forms one wall of the tunnel carrying the first branch of the lateral plantar nerve, the Baxter nerve. Almost every question about this muscle is really a question about plantar heel pain.
Flexor digitorum brevis is frequently mislabelled as a second-layer muscle. It is not. The three muscles of the first layer all arise from the calcaneal tuberosity and all lie immediately deep to the plantar aponeurosis, with flexor digitorum brevis in the centre.
- Layer 1, the most superficial, immediately deep to the plantar aponeurosis: abductor hallucis medially, flexor digitorum brevis centrally, abductor digiti minimi laterally
- Layer 2: quadratus plantae, the four lumbricals, and the tendons of flexor digitorum longus and flexor hallucis longus, all lying immediately deep to flexor digitorum brevis
- Layer 3: flexor hallucis brevis, adductor hallucis, flexor digiti minimi brevis
- Layer 4: plantar and dorsal interossei, plus the tendons of tibialis posterior and peroneus longus
The plane between layer 1 and layer 2 is the plane the Baxter nerve travels in, the plane an endoscopic fascia release instrument passes through, and the plane a plantar abscess spreads along. Place the muscle in the wrong layer and you will place the nerve in the wrong plane.
The truss. The foot behaves as a truss: the calcaneus, midfoot and metatarsals form the arch, and the plantar aponeurosis is the tie-beam on its tension side. The intrinsic muscles, flexor digitorum brevis among them, are the dynamic tie-beam working in parallel with it. Flexor digitorum brevis and abductor hallucis actively support the arch, which is why strengthening them (the short-foot exercise) is a legitimate part of treatment, and why sacrificing the entire aponeurosis is so damaging: it transfers the whole tie-beam load onto muscles that cannot carry it.
The windlass. In terminal stance, dorsiflexion of the metatarsophalangeal joints winds the plantar aponeurosis around the metatarsal heads like a cable round a drum. The arch rises, the hindfoot supinates, the transverse tarsal joint locks, and the foot converts from a compliant shock absorber into a rigid lever for push-off. That is Hicks' windlass mechanism, and every cycle of it loads the shared enthesis of the aponeurosis and flexor digitorum brevis on the medial calcaneal tuberosity; repetitive traction at that footprint is the mechanical basis of plantar fasciopathy.
Two clinical corollaries. Passive dorsiflexion of the toes tensions the enthesis and reproduces the pain of plantar fasciopathy, which is the basis of the windlass test. And a tight posterior chain forces earlier and greater forefoot loading, so gastrocnemius or Achilles tightness increases the load, which is why calf stretching and, in refractory cases, gastrocnemius recession work.
Attachments and the Tendon Chiasma
Origin. The muscle arises from the medial process of the calcaneal tuberosity, the same bony footprint from which the plantar aponeurosis arises: the aponeurosis is superficial, the muscle immediately deep to it, and the two share fibres. It takes further origin from the deep (superior) surface of the central band of the aponeurosis throughout the proximal sole, and from the intermuscular septa on either side that separate it from abductor hallucis medially and abductor digiti minimi laterally.
Why the shared enthesis matters. "Plantar fasciitis" is in reality an enthesopathy of the aponeurosis and the underlying flexor digitorum brevis origin, and MRI often shows oedema in the proximal muscle as well as thickening of the fascia. It is also the reason a partial fasciotomy inevitably encounters the muscle origin.
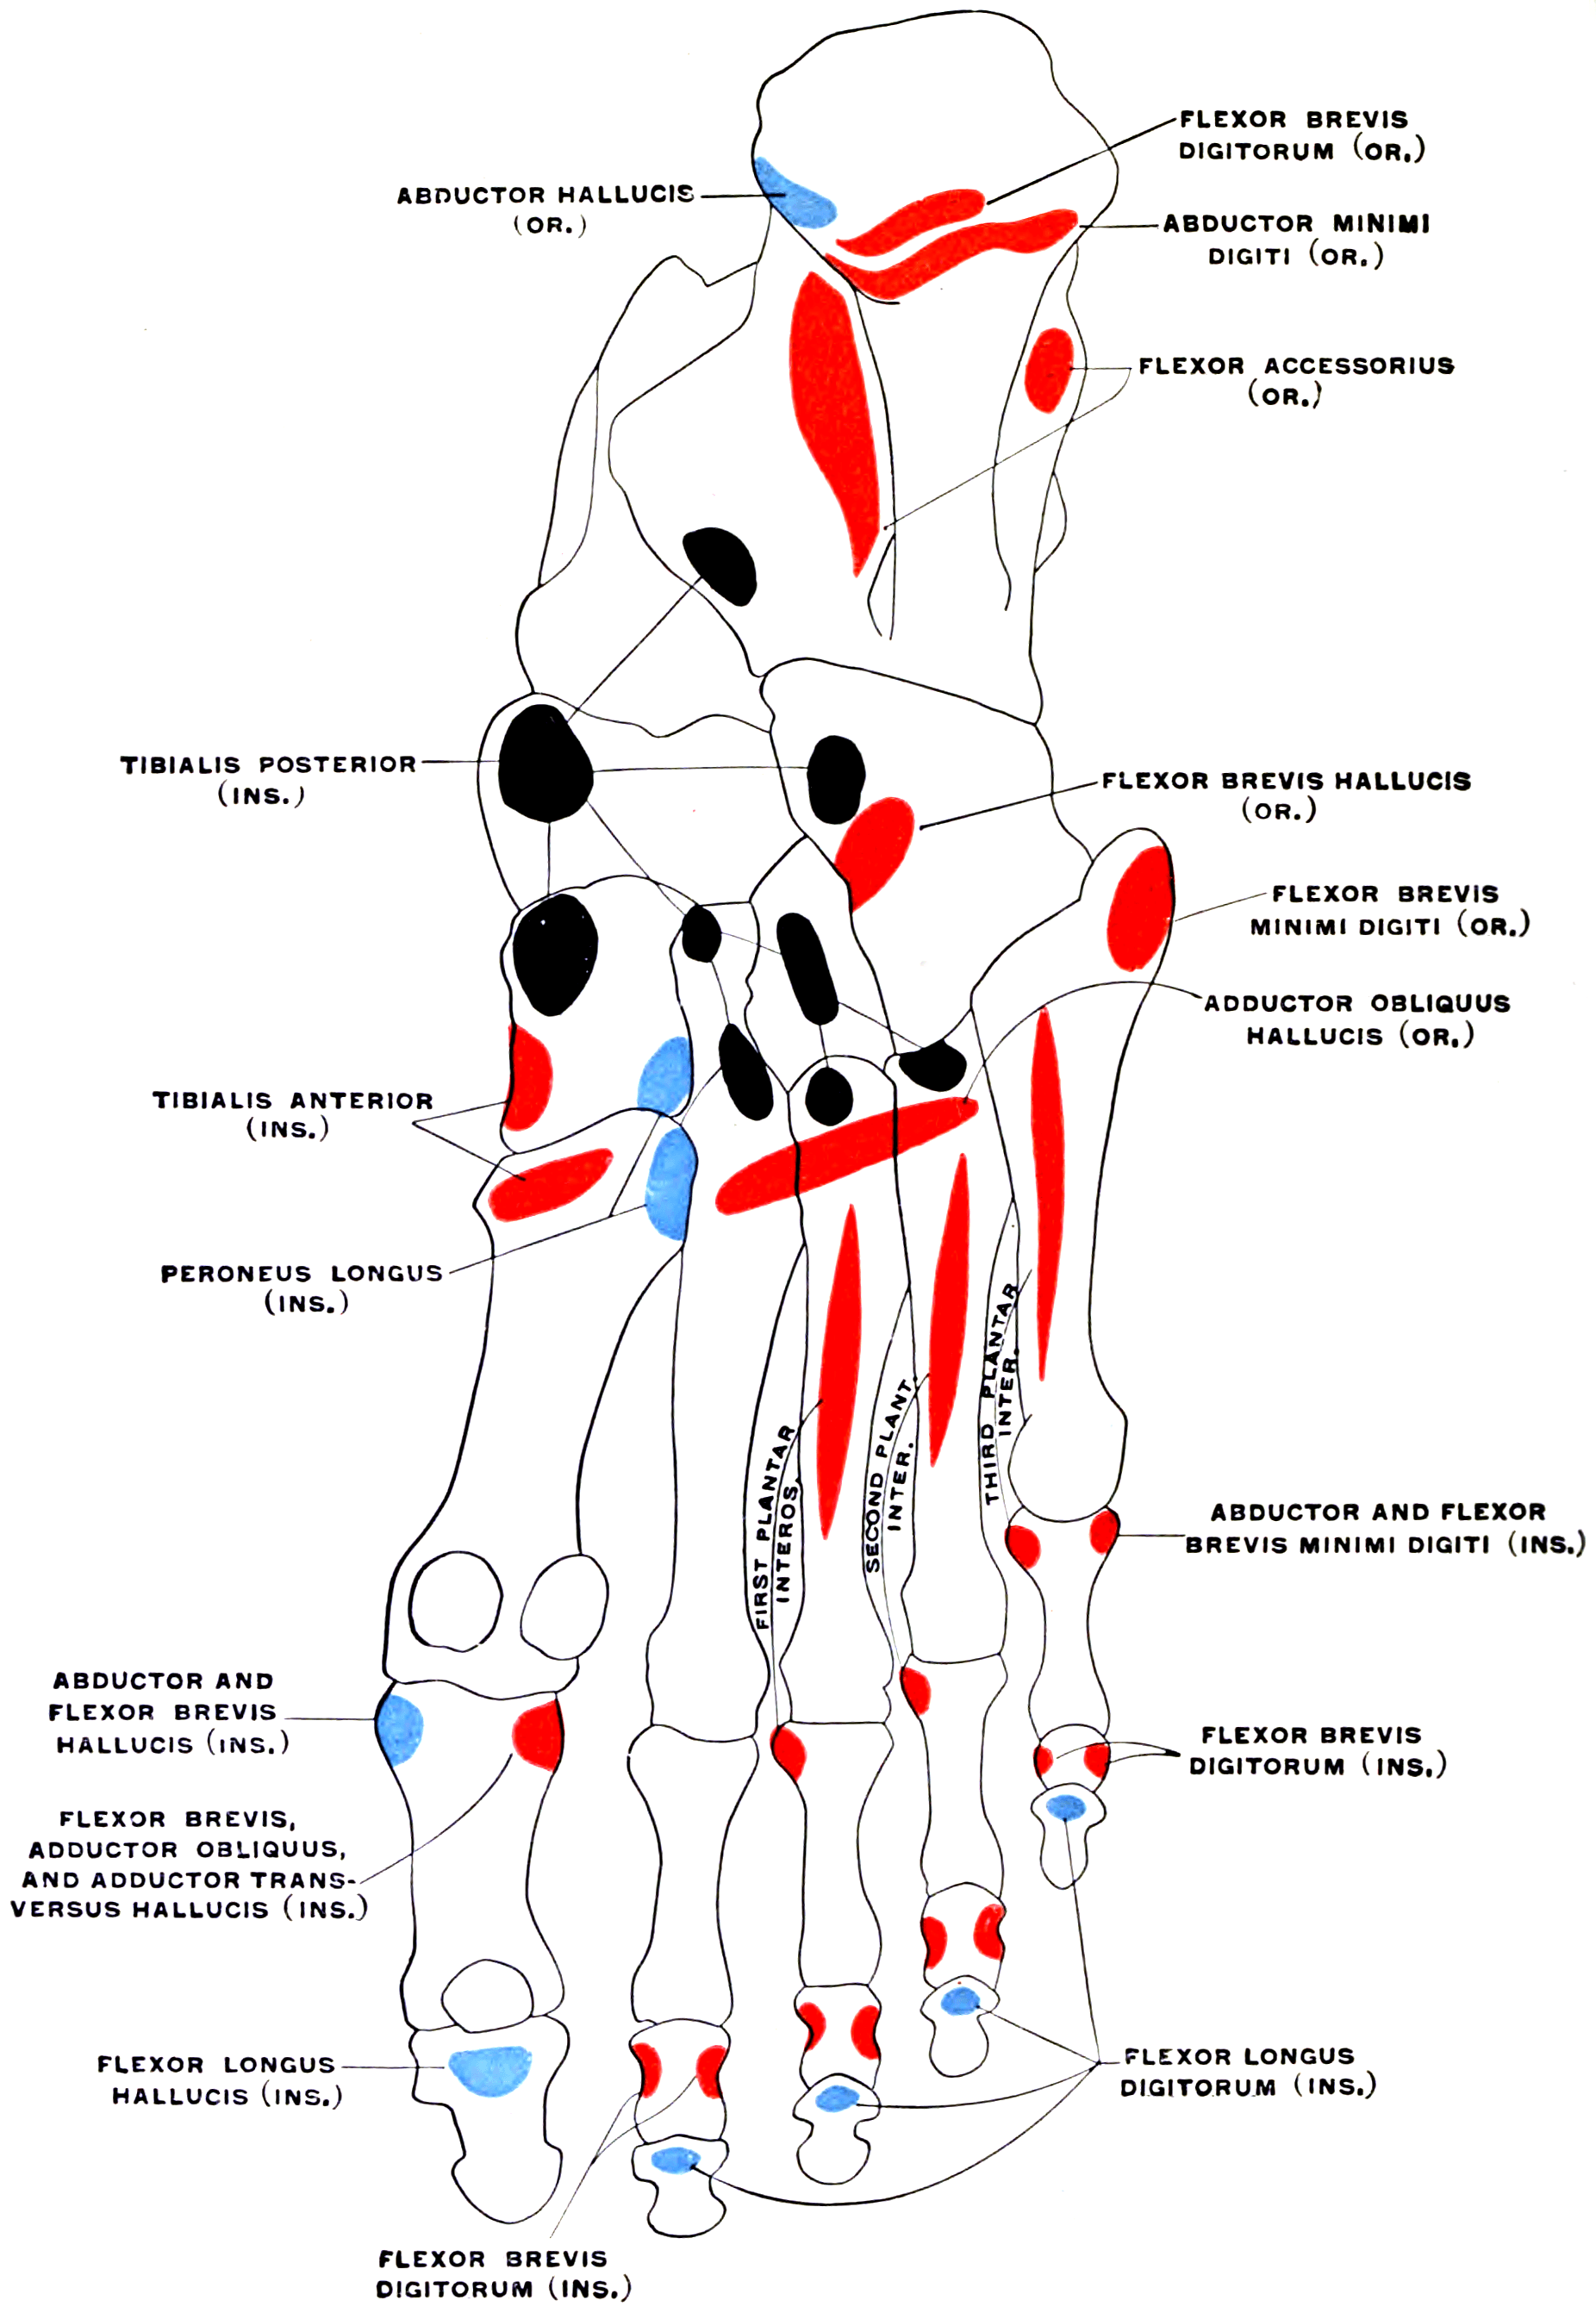
Course and division. The belly runs forward in the central compartment and narrows into four tendons at about the level of the mid-metatarsals. Each enters the corresponding digital flexor sheath, lying superficial (plantar) to the flexor digitorum longus tendon at first.
The chiasma. Within the sheath, at about the level of the proximal phalanx, each tendon splits into two slips so that the flexor digitorum longus tendon can pass through it and continue distally. This is the chiasma tendinum, the plantar equivalent of Camper's chiasma in the hand, where flexor digitorum superficialis splits round profundus in the same way. The two slips then partly reunite deep to the long tendon before dividing again to insert.
Insertion. The slips insert into the sides of the plantar surface of the base and shaft of the middle phalanx of each of toes 2 to 5. The muscle therefore crosses and acts on the metatarsophalangeal and proximal interphalangeal joints but not the distal interphalangeal joint, which is the anatomical basis of the isolation test described under Examination.
Variation. The tendon to the fifth toe is absent or vestigial in a substantial minority of feet, widely reported in the region of one in five to one in four, with variation between series. This is not a pathology, and it is a favourite examination point; accessory slips from the long flexor tendons or quadratus plantae to the fifth toe frequently substitute. Accessory bellies arising from the flexor digitorum longus tendon or quadratus plantae are also described, occasionally passing to the fifth toe on the medial rather than the plantar aspect.
Innervation
Medial plantar nerve (S1, S2). The tibial nerve (L4 to S3) divides in the tarsal tunnel, deep to the flexor retinaculum, into the medial and lateral plantar nerves, usually at or just distal to the level of the medial malleolus. The medial plantar nerve passes deep to abductor hallucis and then forward between abductor hallucis and flexor digitorum brevis, giving muscular branches as it goes. It supplies only four muscles: flexor digitorum brevis, abductor hallucis, flexor hallucis brevis and the first lumbrical. Everything else in the sole is lateral plantar nerve.
Motor entry point. Branches enter the deep and medial surface of the muscle in its proximal third, close to the origin, so a dissection that strips the deep-medial surface of the proximal muscle risks denervating it. The first branch of the lateral plantar nerve also gives twigs to flexor digitorum brevis and to the periosteum of the medial calcaneal tuberosity as it passes, so the muscle has a small dual contribution.
When the nerve fails. A medial plantar nerve palsy, from a tarsal tunnel or a high tibial nerve lesion, weakens proximal interphalangeal flexion of toes 2 to 5 together with abductor hallucis and flexor hallucis brevis, removes the muscle's dynamic arch support, and produces medial plantar sensory loss.
The nerves around the muscle. Four nerves run in or beside flexor digitorum brevis, and each has its own syndrome.
- Course relative to FDB
- Runs forward between abductor hallucis and the deep-medial surface of FDB
- Clinical syndrome
- Jogger's foot - entrapment at the knot of Henry or beneath the abductor hallucis fascia, with SENSORY symptoms in the medial sole and medial three and a half toes
- Course relative to FDB
- Runs obliquely across the sole DEEP to FDB, superficial to quadratus plantae
- Clinical syndrome
- Component of tarsal tunnel syndrome; sensory loss over the lateral sole and lateral one and a half toes
- Course relative to FDB
- Passes between abductor hallucis deep fascia and quadratus plantae, then laterally along the DEEP surface of FDB to abductor digiti minimi
- Clinical syndrome
- Baxter neuropathy - chronic plantar heel pain with NO sensory loss; abductor digiti minimi wasting
- Course relative to FDB
- Arise proximally, pierce the flexor retinaculum and run superficial to the FDB origin to the heel pad skin
- Clinical syndrome
- Painful heel scar or neuroma after a medial or transverse heel incision; a cause of persistent post-fasciotomy pain
Blood Supply
Arteries. The medial plantar artery, the smaller terminal branch of the posterior tibial artery, supplies the medial part of the muscle and travels with the medial plantar nerve. The lateral plantar artery, the larger terminal branch, crosses the sole deep to flexor digitorum brevis, supplying it segmentally from its deep surface before continuing as the deep plantar arch. Calcaneal branches of the posterior tibial artery supply the origin.
Pedicle position. The dominant pedicles enter the deep surface of the muscle: proximally from the calcaneal and medial plantar branches, more distally from the lateral plantar artery as it crosses. Those proximal pedicles are what allow the muscle to be raised as a local flap for the heel, described under Surgical Relevance. The lateral plantar artery crossing the deep surface is also the reason a proximal transverse plantar incision, the historic approach for heel spur excision, is a bloody and unforgiving exposure.
Relations and Compartments
Superficial. Plantar to the muscle lie the central band of the plantar aponeurosis, adherent to it and sharing its calcaneal footprint, then the plantar fat pad with its fibrous septae and the plantar skin. The medial calcaneal sensory branches of the tibial nerve run superficial to the origin toward the heel pad.
Deep. The second layer lies dorsal to the muscle: the flexor digitorum longus tendon with the four lumbricals arising from it, the flexor hallucis longus tendon medially and the knot of Henry where the two long flexors cross, and quadratus plantae, arising from the calcaneus and inserting into the lateral margin of the flexor digitorum longus tendon. In the plane between flexor digitorum brevis and quadratus plantae the lateral plantar nerve and artery cross obliquely, and the Baxter nerve runs laterally along the deep surface of the muscle.
Medial and lateral. Medially lie abductor hallucis and its deep fascia, then the medial plantar nerve and artery, and further medially the contents of the tarsal tunnel. Laterally lies abductor digiti minimi, the target muscle of the Baxter nerve.
Compartments. Flexor digitorum brevis occupies the central (superficial) compartment of the sole. Immediately deep and proximal to it, the calcaneal compartment contains quadratus plantae. The remaining compartments:
- Medial: abductor hallucis and flexor hallucis brevis
- Lateral: flexor digiti minimi brevis and abductor digiti minimi
- Interosseous compartments: the interossei
The first branch of the lateral plantar nerve (the inferior calcaneal nerve, or Baxter nerve) arises from the lateral plantar nerve within about a centimetre of the tibial nerve bifurcation, then takes a right-angled course with a compression point on each limb.
- Vertical (descending) segment. It passes downward and laterally between the deep fascia of abductor hallucis medially and the medial caudal margin of quadratus plantae laterally, an interval lying roughly 1 cm distal and 1 cm medial to the medial calcaneal tuberosity. This narrow fibro-muscular interval is the first and commonest site of compression, aggravated by a hypertrophied abductor hallucis, an accessory muscle, or the oedema of a chronic enthesopathy.
- Horizontal (transverse) segment. It then turns laterally and runs along the deep surface of flexor digitorum brevis, immediately anterior to the medial calcaneal tuberosity, to reach abductor digiti minimi. Here it can be compressed against the tuberosity by an inferior heel spur, a thickened plantar fascia origin, or a hypertrophic flexor digitorum brevis. This is the second site.
On the way it supplies the periosteum of the medial calcaneal tuberosity (hence deep, poorly localised heel pain), the long plantar ligament and the calcaneal periosteum, twigs to flexor digitorum brevis, and motor fibres to abductor digiti minimi, the only muscle it exclusively supplies. Its origin is not constant: it may come off the tibial nerve directly or as more than one branch, and in the Unlu cadaveric series it arose from the medial calcaneal nerve in three feet in ten, so a decompression releases the whole interval rather than seeking a single nerve.
Why it is missed. Its cutaneous contribution is negligible, so there is no sensory loss. It presents as chronic medial plantar heel pain, maximal just distal and medial to the medial calcaneal tuberosity rather than at the fascial origin itself, often with pain radiating laterally across the heel, sometimes with night pain, and on MRI or electrodiagnostics with selective wasting or denervation of abductor digiti minimi. A pure motor nerve producing a purely painful syndrome is the paradox, and the paradox is why the diagnosis is overlooked.
Action and Biomechanics
Actions. Its primary and defining action is flexion of the proximal interphalangeal joints of toes 2 to 5, with flexion of the metatarsophalangeal joints secondarily; it does not flex the distal interphalangeal joints, which is flexor digitorum longus alone. Beyond the toes it gives dynamic support to the medial longitudinal arch in parallel with the aponeurosis, and in terminal stance it stabilises the toes against the ground, keeping the toe pulps loaded and lengthening the effective foot lever.
The four-way balance. Flexor digitorum brevis and flexor digitorum longus both flex the toe, but at different joints, and their balance against the extensors and the intrinsics determines lesser toe posture. The correct model is a four-way balance: the long extensor extends the metatarsophalangeal joint through the extensor sling, the long flexor flexes the distal interphalangeal joint, the short flexor flexes the proximal interphalangeal joint, and the intrinsics, interossei and lumbricals, flex the metatarsophalangeal joint and are the only intrinsic counterweight to the long extensor.
Why the foot claws and the hand does not. In the foot, unlike the hand, the interossei have no extensor expansion into the dorsal hood, so they cannot extend the interphalangeal joints. Losing them produces claw toe: hyperextension at the metatarsophalangeal joint from unopposed long extensor pull, with flexion at both interphalangeal joints from unopposed long and short flexor pull. In the intrinsic-minus foot of diabetic or hereditary neuropathy, where interossei and lumbricals are denervated together, the claw toes are accompanied by plantar prominence of the metatarsal heads with callus and ulceration beneath them.
The deformity map. Which joint is flexed names the deformity and points to the responsible tendon:
- Claw toe: metatarsophalangeal extension with PIP and DIP flexion; intrinsic-minus, so classically neuropathic (Charcot-Marie-Tooth, diabetes, cavus)
- Hammer toe: PIP flexion with a neutral or extended metatarsophalangeal joint and a neutral or extended DIP; a flexor digitorum brevis-dominant deformity
- Mallet toe: isolated DIP flexion; a flexor digitorum longus deformity
- Curly toe: a flexion, adduction and varus rotation deformity of a lesser toe in childhood, attributed to a tight or abnormally inserted long and short flexor complex
These distinctions matter because they dictate which tendon is addressed, set out under Clinical Relevance. The muscles in the balance, with their nerves and the joints they act on:
- Muscle
- Flexor digitorum brevis
- Nerve
- Medial plantar (S1, S2)
- Joint acted on
- MTP and PIP only
- Muscle
- Flexor digitorum longus
- Nerve
- Tibial (L5, S1, S2)
- Joint acted on
- MTP, PIP and DIP
- Muscle
- Quadratus plantae
- Nerve
- Lateral plantar (S2, S3)
- Joint acted on
- Corrects the oblique pull of FDL
- Muscle
- Interossei and lumbricals
- Nerve
- Lateral plantar (mostly)
- Joint acted on
- MTP - no extensor expansion in the foot
- Muscle
- Extensor digitorum longus and brevis
- Nerve
- Deep peroneal (L5, S1)
- Joint acted on
- Extends MTP through the extensor sling
- Muscle
- Plantar aponeurosis
- Nerve
- Not applicable
- Joint acted on
- The structure FDB works alongside and cannot replace
Surface Anatomy and Examination
Palpation. The muscle belly is not selectively palpable, lying deep to the tough plantar aponeurosis, but its tendons can be felt in the sole beneath the metatarsal heads with the toes passively extended. Landmark the medial calcaneal tuberosity with the ankle in neutral by palpating along the plantar-medial heel until the tender bony prominence at the anteromedial corner of the calcaneal tuberosity is found; this is the shared enthesis of the plantar aponeurosis and flexor digitorum brevis.
Localise the pain. The critical clinical skill in a painful heel is finding the site of maximal tenderness, because the site changes the diagnosis. The differential table under Clinical Relevance pairs each site with the finding that confirms it.
Isolating brevis from longus. The logic is identical to the FDS/FDP test in the hand: block the distal joint to take the long flexor out of the equation, then test the proximal joint. The manoeuvres, with their pitfalls:
- How to perform
- Hold the DISTAL interphalangeal joint of the toe in extension to neutralise flexor digitorum longus, then ask for active flexion of the PIP joint against resistance
- Positive finding
- Weak or absent resisted PIP flexion with the DIP blocked
- What it means
- Flexor digitorum brevis weakness - medial plantar nerve lesion, or after harvest or division of the tendon
- False positives / pitfalls
- Failing to block the DIP allows FDL to substitute; a stiff PIP joint mimics weakness; a congenitally absent fifth toe tendon
- How to perform
- Stabilise the middle phalanx and ask for active DIP flexion only
- Positive finding
- Weak or absent DIP flexion
- What it means
- Flexor digitorum longus lesion, or a proximal tibial nerve problem
- False positives / pitfalls
- Tenodesis effect from ankle position; mallet toe contracture
- How to perform
- Passively dorsiflex the metatarsophalangeal joints (ideally with the patient standing on a step with the toes over the edge) while palpating the medial calcaneal tuberosity
- Positive finding
- Reproduction of sharp pain at the medial calcaneal tuberosity
- What it means
- Plantar fasciopathy - the test tensions the shared enthesis of the aponeurosis and FDB
- False positives / pitfalls
- Low sensitivity when performed non-weight-bearing; a stiff first metatarsophalangeal joint prevents adequate tensioning
- How to perform
- Press deeply in the interval between abductor hallucis and quadratus plantae, roughly 1 cm distal and 1 cm medial to the tuberosity
- Positive finding
- Deep, well-localised tenderness with pain radiating laterally across the heel, sometimes reproduced on eversion and dorsiflexion
- What it means
- Baxter (first branch of lateral plantar nerve) entrapment
- False positives / pitfalls
- Overlaps with the fascial origin; there is NO sensory loss to confirm it - correlate with abductor digiti minimi wasting
- How to perform
- Ask the patient to abduct the fifth toe, and inspect and palpate the muscle bulk along the lateral border of the foot, comparing sides
- Positive finding
- Weakness or visible wasting of abductor digiti minimi
- What it means
- Denervation from Baxter nerve entrapment - the only muscle exclusively supplied by that nerve
- False positives / pitfalls
- Many normal people cannot voluntarily abduct the fifth toe - compare with the other side and rely on bulk and MRI
- How to perform
- Compress the calcaneal body between thumb and fingers from medial and lateral
- Positive finding
- Pain on medial-lateral compression away from the plantar enthesis
- What it means
- Calcaneal stress fracture rather than a soft-tissue heel problem
- False positives / pitfalls
- A very tender heel pad may hurt with any pressure - compare with the plantar-specific tests
- How to perform
- Assess ankle dorsiflexion with the knee extended and then flexed to 90 degrees
- Positive finding
- Dorsiflexion markedly improves with the knee flexed
- What it means
- Isolated gastrocnemius tightness - a treatable contributor to plantar heel pain, and the indication for gastrocnemius recession in refractory cases
- False positives / pitfalls
- Subtalar or midfoot motion mistaken for ankle dorsiflexion - lock the hindfoot in neutral
Radiographs and ultrasound. Weight-bearing radiographs exclude bony pathology, show a plantar calcaneal spur, which is of limited significance as a cause of pain but is a mechanical relation of the Baxter nerve, and assess hindfoot alignment and cavus. Ultrasound is the workhorse for the plantar fascia: thickness greater than 4 mm at the enthesis, loss of the normal fibrillar pattern, hypoechogenicity and a peritendinous fluid collection. It is dynamic and cheap, and it allows guided injection.
MRI and electrodiagnostics. MRI is reserved for diagnostic uncertainty and recalcitrant pain. It shows fascial thickening and perifascial oedema, oedema in the proximal flexor digitorum brevis, calcaneal marrow oedema (a stress fracture or a florid enthesopathy) and, critically, selective fatty atrophy of abductor digiti minimi in Baxter neuropathy. Electrodiagnostics can support Baxter neuropathy or tarsal tunnel syndrome, but they are technically demanding for a short distal motor branch and a negative study does not exclude the diagnosis.
Complications
- Mechanism
- Complete rather than partial plantar fasciotomy
- Avoidance
- Release the medial third to half only, measured and under direct vision
- Mechanism
- Instrument or blade passing laterally in the plane deep to the fascia and superficial to FDB
- Avoidance
- Stay medial; open decompression rather than endoscopic release when neural symptoms are present
- Mechanism
- Division of medial calcaneal sensory branches
- Avoidance
- Identify and preserve them; place the incision dorsal to weight-bearing skin; avoid transverse plantar heel incisions
- Mechanism
- Superficial or repeated corticosteroid injection
- Avoidance
- Inject deep to the fascia from a medial approach; limit the number of injections; counsel explicitly
- Mechanism
- Repeated corticosteroid injection, or an inadvertently complete release
- Avoidance
- Limit injections; document counselling; consider shockwave therapy instead
- Mechanism
- The diagnosis was never fascial - most often unrecognised Baxter neuropathy, fat pad atrophy, a stress fracture or inflammatory enthesitis
- Avoidance
- Re-examine and re-image before operating; localise tenderness precisely
- Mechanism
- Stripping the deep-medial surface of the proximal muscle where the medial plantar nerve branches enter
- Avoidance
- Work superficial to the muscle; do not dissect its deep-medial surface unnecessarily
- Mechanism
- Dissection in the plane deep to FDB, particularly through a proximal transverse plantar incision
- Avoidance
- Use a medial approach; expect the vessel crossing obliquely deep to the muscle
- Mechanism
- Harvest of FDB as a heel flap, or division of the tendons
- Avoidance
- Usually well tolerated; counsel about reduced toe purchase
- Mechanism
- Operating on a plantar surface with poor perfusion or protective sensation
- Avoidance
- Assess perfusion first; offload rigorously; prefer percutaneous techniques such as flexor tenotomy where they will do
Clinical Relevance
Plantar fasciopathy
What it is. The commonest cause of plantar heel pain is a degenerative enthesopathy, not primarily inflammatory, hence the preferred term fasciopathy. It presents as sharp medial plantar heel pain, worst on the first steps in the morning and after periods of rest, easing with walking then worsening with prolonged standing, with tenderness at the medial calcaneal tuberosity reproduced by the windlass test.
Risk factors. The recognised ones are a raised body mass index, a prolonged weight-bearing occupation, a sudden increase in running load, reduced ankle dorsiflexion or gastrocnemius tightness, pes planus and pes cavus, and reduced first metatarsophalangeal dorsiflexion.
Natural history. The great majority resolve within 6 to 12 months with non-operative care, and that fact is the whole basis of management. The pathway below exists to hold the line while time does its work.
- 1Stage 1 - first 6 weeksExplanation and reassurance about the natural history, activity and load modification, weight management, cushioned or supportive footwear, an off-the-shelf heel cushion or arch support, plantar-fascia-specific stretching and calf stretching, and simple analgesia.
- 2Stage 2 - 6 weeks to 6 monthsSupervised plantar-fascia-specific stretching, progressive high-load plantar fascia and intrinsic strengthening (heel raises with the toes dorsiflexed, short-foot exercises), a custom or prefabricated orthosis, taping, and consideration of a night splint holding the ankle at neutral.
- 3Stage 3 - 6 to 12 monthsExtracorporeal shockwave therapy where available. Consider a single ultrasound-guided corticosteroid injection deep to the fascia from a MEDIAL approach, with explicit counselling about fascia rupture and fat pad atrophy. Re-examine specifically for Baxter neuropathy, fat pad atrophy, stress fracture and inflammatory disease.
- 4Stage 4 - beyond 12 months, refractoryRe-confirm the diagnosis with imaging. Gastrocnemius recession if the Silfverskiold test is positive. Partial plantar fasciotomy releasing only the MEDIAL third to half, open or endoscopic, with decompression of the first branch of the lateral plantar nerve where neural symptoms are present.
Corticosteroid injection. Two specific harms follow it. Plantar fascia rupture is reported after repeated injection, producing acute arch collapse and a palpable defect; plantar fat pad atrophy is a permanent, disabling loss of heel cushioning, worse with superficial injection. Inject deep to the fascia from a medial approach, aiming away from the fat pad, limit the number of injections, and warn the patient about both.
Surgery. The operation is a partial plantar fasciotomy, whose safe extent and technique are under Surgical Relevance. In the patient with a positive Silfverskiold test a gastrocnemius recession is a legitimate alternative or adjunct, and avoids sacrificing any of the aponeurosis. Heel spur excision is not therapeutic in itself: the spur is not the cause of pain, and is relevant only as a structure that can compress the Baxter nerve.
Baxter neuropathy
How common. Entrapment of the first branch of the lateral plantar nerve accounts for a meaningful minority of chronic plantar heel pain, commonly quoted as up to around 20% of recalcitrant cases. The two compression points are the ones described in the tunnel box above.
Telling it from fasciopathy. The pain is frequently burning. The pointers away from a fascial diagnosis are the site of maximal tenderness, the absence of the classic first-step-in-the-morning pattern in some cases, pain that persists despite adequate fascial treatment, provocation by deep palpation in the abductor hallucis-quadratus plantae interval, weakness or wasting of abductor digiti minimi when present, and MRI evidence of its selective atrophy.
Management. Non-operative treatment comes first: offloading, orthoses to reduce heel valgus and fascial tension, neuropathic analgesia, and treatment of any coexisting fasciopathy. Surgical decompression releases the deep fascia of abductor hallucis and the medial caudal margin of the quadratus plantae fascia, divides the medial third of the plantar fascia, and excises a prominent heel spur if it is compressing the nerve; the approach is described under Surgical Relevance.
The rest of the differential
Heel pain that has not responded to a year of good fascial treatment is usually on this list somewhere other than the first row.
- Discriminating feature
- First-step morning pain; tender at the medial calcaneal tuberosity; positive windlass test
- Confirmatory finding
- Fascia thicker than 4 mm with loss of fibrillar pattern on ultrasound
- Discriminating feature
- Tender 1 cm distal and medial to the tuberosity; pain radiates laterally; NO sensory loss
- Confirmatory finding
- Selective fatty atrophy of abductor digiti minimi on MRI
- Discriminating feature
- Diffuse central heel pain, worse barefoot on hard floors; thin, non-resilient heel pad
- Confirmatory finding
- Clinical; reduced pad thickness on ultrasound; often a history of repeated steroid injection
- Discriminating feature
- Positive medial-lateral squeeze test; night pain; a history of load increase or a fragility context
- Confirmatory finding
- Calcaneal marrow oedema on MRI, later a sclerotic line on radiograph
- Discriminating feature
- SENSORY symptoms across the sole, positive Tinel behind the medial malleolus
- Confirmatory finding
- Nerve conduction studies; a space-occupying lesion on MRI
- Discriminating feature
- Sensory symptoms in the medial sole and medial three and a half toes, at the knot of Henry
- Confirmatory finding
- Clinical, supported by MRI or diagnostic injection
- Discriminating feature
- Bilateral heel pain in a younger patient, other enthesitis, inflammatory back pain
- Confirmatory finding
- Raised inflammatory markers, HLA-B27, sacroiliitis on imaging
- Discriminating feature
- Skeletally immature, POSTERIOR heel pain at the apophysis, not plantar
- Confirmatory finding
- Age and site; radiographs to exclude other pathology
- Discriminating feature
- A palpable nodule in the fascia, mid-arch rather than at the enthesis
- Confirmatory finding
- Nodular thickening of the fascia on ultrasound or MRI
- Discriminating feature
- Acute pop with immediate pain and bruising, often after repeated steroid injection; a palpable defect
- Confirmatory finding
- Discontinuity of the fascia on ultrasound or MRI
Two further causes belong on the list: a bone lesion of the calcaneus, a tumour or cyst, rare but not to be missed on the radiograph, and tarsal coalition.
Lesser toe deformity and tendon surgery
Hammer toe is the deformity most attributable to flexor digitorum brevis. A flexible hammer toe can be treated with a flexor-to-extensor (Girdlestone-Taylor) transfer, using the split flexor digitorum longus rather than brevis; a fixed hammer toe needs proximal interphalangeal resection arthroplasty or arthrodesis. The same choice, transfer or proximal interphalangeal arthroplasty or arthrodesis, applies to the claw toe.
Mallet toe, a flexor digitorum longus problem, is treated by flexor tenotomy or distal interphalangeal fusion. Curly toe in childhood involves both long and short flexors: open flexor tenotomy of both tendons is the classical treatment, and comparative evidence shows it performs as well as the more extensive flexor-to-extensor transfer. A diabetic claw toe with an apical ulcer is very effectively treated by a simple percutaneous flexor tenotomy, which offloads the toe tip and lets the ulcer heal.
Compartment syndrome, sepsis and the deep plane
Calcaneal compartment syndrome, from the haematoma of a calcaneal fracture or a crush injury, involves quadratus plantae in the calcaneal compartment immediately deep and proximal to flexor digitorum brevis. Untreated it produces fibrosis of quadratus plantae and the deep muscles, fixed claw toes and chronic neuropathic pain.
Plantar space infection tracks in the plane between flexor digitorum brevis and the second layer, and can reach the calcaneal compartment and the tarsal tunnel proximally. Drainage requires a formal medial or plantar-central incision, with awareness of the lateral plantar neurovascular bundle crossing deep to the muscle.
Surgical Relevance
The medial approach for fasciotomy and nerve decompression
The workhorse exposure, and the one that allows both a partial fasciotomy and a Baxter nerve decompression through the same incision. The incision is oblique or longitudinal on the medial heel, roughly 3 to 4 cm long, centred about 2 cm distal and 1 cm plantar to the tip of the medial malleolus and running toward the plantar-medial heel, deliberately dorsal to the weight-bearing plantar skin.
The layers in order. Six structures are met in turn:
- Skin and subcutaneous fat containing the medial calcaneal sensory branches of the tibial nerve. Identify and preserve them: a divided branch produces a painful heel scar and is a common cause of persistent post-operative pain.
- The superficial fascia of abductor hallucis, then the muscle, retracted plantarward or dorsally.
- The deep fascia of abductor hallucis, the first compression point of the Baxter nerve. Release it longitudinally.
- The medial caudal margin of quadratus plantae and its fascia. Release it to complete the vertical decompression.
- The medial edge of the plantar aponeurosis and the underlying flexor digitorum brevis origin. Release the medial third to half of the aponeurosis only, under direct vision.
- An inferior heel spur, excised only if it is compressing the nerve at the tuberosity; otherwise leave it.
Close without tension and mobilise early; a stiff, painful heel scar is as disabling as the original problem.
Endoscopic plantar fascia release
The corridor. Two small portals, medial and lateral, at the level of the fascial origin, with a cannula passed superficial to flexor digitorum brevis and deep to the plantar aponeurosis, which is exactly the corridor of the Baxter nerve's horizontal segment. The advantages are small wounds, less scar sensitivity and quicker recovery. The risks are that the release is harder to limit accurately, and that the lateral portal and any lateral extension of the cut place the Baxter nerve at direct risk; iatrogenic injury, a recognised complication of endoscopic and percutaneous release, converts a treatable fascial problem into an intractable neuropathic one.
The rules. Stay medial, keep the working cannula medial to the midline of the heel and superficial to muscle, cut only the medial third to half, and keep the fascia in view throughout. The further lateral the instrument travels, the closer it is to the nerve. Do not use this technique when a neural component is suspected: those patients need an open decompression.
Lesser toe tendon procedures
Percutaneous flexor tenotomy for the diabetic claw toe with an apical ulcer is a small plantar stab at the level of the proximal or middle phalanx, dividing the long and short flexor tendons under tension with the toe held extended. It is simple and done under local anaesthetic. Open flexor tenotomy for the childhood curly toe divides both the long and short flexor tendons through a small plantar transverse incision at the base of the toe, with less morbidity than a transfer.
Flexor-to-extensor (Girdlestone-Taylor) transfer for a flexible claw or hammer toe harvests the flexor digitorum longus tendon, not brevis, splits it, and passes the two limbs dorsally on either side of the proximal phalanx to be sutured over the extensor hood, converting the long flexor into a metatarsophalangeal flexor to substitute for the absent intrinsics. The transfer uses longus because it is the tendon that continues to the distal phalanx and can be delivered proximally; the chiasma is where the brevis tendon splits around it, and the longus must be released distal to the chiasma to be withdrawn.
Flexor digitorum brevis as a heel flap
Indication and technique. Small plantar heel defects with exposed calcaneus, or a small central heel ulcer, most often after debridement of calcaneal osteomyelitis or a chronic pressure ulcer. The muscle is raised distally, dividing the four tendons, and turned proximally on its proximal pedicles from the calcaneal and medial plantar branches, then covered with a skin graft.
Limitations. The flap is thin, its arc of rotation is short, it is unreliable in the ischaemic or heavily neuropathic foot, where the indication most often arises, and harvesting it sacrifices lesser toe proximal interphalangeal flexion, which is usually well tolerated but weakens toe purchase. The medial plantar artery (instep) fasciocutaneous flap, giving durable, sensate, like-for-like cover of the weight-bearing heel, and the abductor hallucis muscle flap for a small medial defect are generally preferred; free tissue transfer is used for larger defects.
Distances and safe zones
- Medial calcaneal sensory branches of the tibial nerve arise above the tarsal tunnel and pierce the flexor retinaculum, running superficial to the abductor hallucis fascia into the heel pad, typically crossing the medial heel within about 1 to 2 cm proximal to the medial calcaneal tuberosity. There is no safe subcutaneous plane in the medial heel; identify and preserve them.
- Extent of fasciotomy: measure it; do not estimate it after the fascia has retracted.
- Lateral plantar artery and nerve cross the sole obliquely deep to flexor digitorum brevis, in the plane between layers 1 and 2, at about the level of the mid-hindfoot to proximal midfoot. Any dissection in that plane lateral to the midline must expect them.
The recognised consequences of a complete plantar fasciotomy are progressive longitudinal arch collapse, dorsolateral midfoot and lateral column pain, transfer metatarsalgia, metatarsal and midfoot stress fracture, and an irreversibly altered gait. There is no reliable reconstruction.
Release the medial third to half only. Before releasing anything, satisfy yourself that:
- The patient has had a genuine and prolonged non-operative programme, usually at least a year.
- The diagnosis really is fascial: re-examine for Baxter neuropathy, fat pad atrophy, calcaneal stress fracture and inflammatory enthesitis.
- A positive Silfverskiold test has been addressed; a gastrocnemius recession may achieve the same relief without sacrificing any fascia.
Guidelines, Registries & Global Practice
Anatomical Variation Across Populations
- Absence of the tendon to the fifth toe is the single most important variation, reported across dissection series in a substantial minority of feet (commonly cited in the region of one in five to one in four, with considerable variation depending on definition and population). Accessory slips from flexor digitorum longus or quadratus plantae frequently substitute.
- Accessory bellies arising from the long flexor tendon or from quadratus plantae are described, occasionally reaching the fifth toe on the medial rather than the plantar aspect - a recognised cause of a small mass in the sole.
- The first branch of the lateral plantar nerve varies in its origin (from the lateral plantar nerve, from the tibial nerve directly, or as multiple branches) in a meaningful proportion of feet. A decompression must therefore release the whole interval rather than seek a single nerve.
- Plantar heel pain is one of the commonest musculoskeletal presentations worldwide, and its prevalence tracks obesity, occupational standing and running participation rather than ethnicity.
Side-by-Side Guidance and Practice Differences
- Position on plantar heel pain and fasciotomy
- Strong emphasis on the favourable natural history; plantar-fascia-specific stretching first line; shockwave therapy for refractory cases; partial fasciotomy limited to the medial third to half after prolonged failure of non-operative care.
- Position on plantar heel pain and fasciotomy
- Similar stepwise approach with a generally higher threshold for surgery, caution about corticosteroid injection because of fascial rupture and fat pad atrophy, and growing use of gastrocnemius recession where the Silfverskiold test is positive.
- Position on plantar heel pain and fasciotomy
- Emphasise the anatomy of the medial calcaneal sensory branches and the first branch of the lateral plantar nerve, and the importance of a limited, measured fascial release.
- Position on plantar heel pain and fasciotomy
- Increasing emphasis on progressive high-load plantar fascia and intrinsic strengthening (including short-foot exercises) rather than stretching alone, and on load management in runners.
Areas of Genuine Uncertainty
- Corticosteroid injection: provides short-term relief but with a real risk of fascial rupture and permanent fat pad atrophy, and no demonstrated long-term benefit. The number of injections that is acceptable is not agreed.
- Extracorporeal shockwave therapy: supported by trial evidence in refractory cases but with heterogeneous protocols, variable effect sizes and inconsistent availability and funding.
- Endoscopic versus open partial fasciotomy: endoscopic release offers quicker recovery but a higher theoretical and reported risk of Baxter nerve injury and a less controllable extent of release.
- Gastrocnemius recession for plantar fasciopathy: attractive because it sacrifices no fascia, but the evidence base and the correct patient selection criteria are still developing.
- How much fascia is too much: the medial third to half is widely taught, but the exact threshold at which arch collapse becomes likely has not been defined prospectively.
- Prevalence of Baxter neuropathy: commonly quoted as up to a fifth of recalcitrant heel pain, but the figure derives from surgical series and depends heavily on how the diagnosis is made.
High- versus Limited-Resource Practice
- Well-resourced settings: ultrasound and MRI for diagnostic clarification, custom orthoses, shockwave therapy, guided injection, and access to endoscopic release and gastrocnemius recession.
- Limited-resource settings: the diagnosis is clinical, and the treatment that does most of the work costs almost nothing - explanation of the natural history, load and weight management, calf and plantar-fascia-specific stretching, a simple heel cushion or an insole cut from firm foam, and a supportive shoe. A percutaneous flexor tenotomy for a diabetic apical toe ulcer is a high-value, minimal-equipment operation available anywhere.
- Everywhere: resist the temptation to operate on a heel that has not had a genuine year of good non-operative treatment, and never release the whole fascia.
MCQ Practice Points
Q: In which plantar layer does flexor digitorum brevis lie? A: The FIRST layer, centrally, immediately deep to the plantar aponeurosis, with abductor hallucis medially and abductor digiti minimi laterally. Layer 2 is quadratus plantae, the lumbricals and the long flexor tendons.
Q: Where does flexor digitorum brevis insert? A: The sides of the plantar surface of the MIDDLE phalanges of toes 2 to 5. It flexes the metatarsophalangeal and proximal interphalangeal joints, never the distal interphalangeal joint.
Q: What is the nerve supply of flexor digitorum brevis? A: The MEDIAL plantar nerve (S1, S2) - one of only four muscles it supplies, along with abductor hallucis, flexor hallucis brevis and the first lumbrical.
Q: Between which two structures does the first branch of the lateral plantar nerve become entrapped? A: The deep fascia of abductor hallucis and the medial caudal margin of quadratus plantae. It then runs laterally along the deep surface of flexor digitorum brevis to abductor digiti minimi.
Q: What sensory deficit does Baxter neuropathy produce? A: None. It is effectively a pure motor nerve, which is why it is so often misdiagnosed as plantar fasciitis. Look for abductor digiti minimi wasting on MRI.
Q: How much of the plantar fascia may be safely released? A: The medial third to half of the central band. Complete release causes longitudinal arch collapse, lateral column pain, metatarsalgia and stress fracture.
Q: What is the chiasma tendinum in the foot? A: The split in each flexor digitorum brevis tendon that allows the flexor digitorum longus tendon to pass through it within the digital sheath, before the two slips insert on the middle phalanx.
Q: Which tendon of flexor digitorum brevis is commonly absent? A: The tendon to the fifth toe, absent or vestigial in a substantial minority of feet. Accessory slips from the long flexor or quadratus plantae may substitute.
Q: Which deformity is attributable to flexor digitorum brevis dominance? A: Hammer toe - PIP flexion with the metatarsophalangeal joint neutral or extended. Mallet toe (isolated DIP flexion) is FDL; claw toe (MTP extension with both IP joints flexed) is intrinsic-minus.
Q: What plantar fascia thickness on ultrasound supports a diagnosis of plantar fasciopathy? A: Greater than 4 mm at the enthesis, with loss of the normal fibrillar pattern and hypoechogenicity.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 48-year-old teacher has had medial plantar heel pain for 18 months. She has had a full physiotherapy programme, orthoses, two corticosteroid injections and shockwave therapy. She now describes burning pain that is worst in the evening, and the point of maximal tenderness is about a centimetre distal and medial to the medial calcaneal tuberosity, with pain radiating across the heel. What is going on and what do you do?”
“A 44-year-old man had a plantar fascia release for refractory heel pain nine months ago. His heel pain has resolved, but he now has dorsolateral midfoot pain and describes his arch as having dropped. On examination the medial arch is lower than on the other side and there is tenderness over the lateral column. Explain what has happened and what you would do.”
“You are shown a dissected sole with the plantar aponeurosis reflected. The examiner points to the central muscle and asks you to name it, place it in the correct layer, describe its tendon architecture, and explain why the foot interossei produce a claw toe when the hand interossei do not.”
Anatomy
- LAYER 1 - central, immediately deep to the plantar aponeurosis
- Origin: medial process of calcaneal tuberosity plus deep surface of the aponeurosis
- Four tendons to toes 2 to 5, inserting on the MIDDLE phalanges
- Chiasma tendinum - FDB splits around the FDL tendon
- Fifth toe tendon absent or vestigial in a substantial minority
Neurovascular
- Nerve: MEDIAL plantar nerve (S1, S2)
- Medial plantar muscles: FDB, abductor hallucis, FHB, 1st lumbrical
- Lateral plantar artery and nerve cross obliquely DEEP to FDB
- Medial calcaneal sensory branches run SUPERFICIAL to the origin
- Pedicles enter the deep surface - a thin local heel flap option
Baxter Nerve
- First branch of the lateral plantar nerve (inferior calcaneal nerve)
- Arises within 1 cm of the tibial nerve bifurcation
- Point 1: abductor hallucis deep fascia versus quadratus plantae margin
- Point 2: against medial calcaneal tuberosity, deep to FDB origin
- Motor to abductor digiti minimi - NO sensory loss; MRI shows ADM atrophy
Plantar Fasciopathy
- First-step morning pain; tender at medial calcaneal tuberosity; positive windlass test
- Ultrasound: fascia thicker than 4 mm, loss of fibrillar pattern
- Most resolve within 6 to 12 months
- Plantar-fascia-specific stretching first line (DiGiovanni)
- Release the MEDIAL THIRD TO HALF only - never the whole fascia
Windlass Mechanism
- Aponeurosis is the tie-beam of the foot truss (Hicks)
- MTP dorsiflexion winds the fascia round the metatarsal heads
- Arch rises, hindfoot supinates, transverse tarsal joint locks
- Gastrocnemius tightness increases the load - Silfverskiold test
- Complete release equals arch collapse and lateral column pain
Lesser Toe Deformity
- Hammer toe - PIP flexion, FDB dominant
- Mallet toe - DIP flexion, FDL
- Claw toe - MTP extension plus both IP flexed, intrinsic-minus
- Foot interossei have NO extensor expansion - hence claw
- Girdlestone-Taylor transfer uses FDL, not FDB
Evidence Base
Treatment of Chronic Heel Pain by Surgical Release of the First Branch of the Lateral Plantar Nerve
- 69 heels in 53 patients with chronic heel pain underwent surgical release of the first branch of the lateral plantar nerve
- Mean duration of symptoms was 23 months (range 6 months to 8 years); no patient had less than 6 months of conservative treatment first, and the mean was 14 months
- Before surgery, 83% had taken non-steroidal anti-inflammatory drugs, 91% of heels had used heel cups or orthoses, and 86% had received one or more steroid injections
- 34 heels had developed pain initially during a sports activity
- Postoperatively 61 heels (89%) had an excellent or good result and 57 heels (83%) had complete resolution of pain
Heel Pain - Operative Results
- 34 operative cases in 26 patients with recalcitrant heel pain over 6 years
- The procedure was an ISOLATED NEUROLYSIS of the mixed nerve supplying the abductor digiti quinti as it passes beneath the abductor hallucis muscle and beneath the medial ridge of the calcaneus
- The DEEP FASCIA OF ABDUCTOR HALLUCIS was released routinely
- An impinging heel spur or a tight plantar fascia was partially removed or released ONLY IF it was causing entrapment of the nerve
- Described the biomechanical pathogenesis of heel pain in relation to pes planus and pes cavus predisposing to an entrapment neuropathy, and clarified the anatomy of the heel in relation to the nerve
Tissue-Specific Plantar Fascia Stretching Enhances Outcomes in Chronic Heel Pain
- 101 patients with chronic proximal plantar fasciitis of at least 10 months duration randomised to a plantar-fascia-specific stretching programme or a standard Achilles tendon stretching programme; 82 returned for follow-up
- All patients also received prefabricated soft insoles, a three-week course of celecoxib and an educational video, so the stretching protocol was the only variable
- At 8 weeks the plantar-fascia-stretching group had significantly better Foot Function Index pain scores for worst pain (p = 0.02) and for pain with the FIRST STEPS IN THE MORNING (p = 0.006)
- Response rates also favoured that group for pain, activity limitations and patient satisfaction
- Concluded that a NON-WEIGHT-BEARING stretch specific to the plantar fascia is superior to the standard weight-bearing Achilles tendon stretch
Plantar Fascia-Specific Stretching Exercise Improves Outcomes in Chronic Plantar Fasciitis - Two-Year Follow-Up
- Two-year follow-up of the 82 patients from the original randomised trial, with complete data from 66
- At the 8-week point ALL patients were instructed in the plantar-fascia-stretching protocol, and both groups then improved markedly - especially those crossing over from the Achilles protocol
- Consequently, in contrast to the 8-week results, there were NO significant between-group differences at two years for worst pain or pain with first steps
- 92% (61 of 66) reported total satisfaction or satisfaction with minor reservations, and 77% (51) reported no limitation in recreational activities
- Supported the tissue-specific plantar fascia stretch as the KEY COMPONENT of treatment for chronic plantar fasciitis
The Mechanics of the Foot. II. The Plantar Aponeurosis and the Arch
- NOTE - no abstract is indexed for this 1954 paper; the following is bounded by its title and by the conventional attribution of the windlass concept to this series
- The second in Hicks' series on the mechanics of the foot, addressing the plantar aponeurosis and the arch
- The description of the aponeurosis as a tie-beam whose tensioning by toe dorsiflexion raises the longitudinal arch is conventionally attributed to this work
- It is the origin of the term windlass mechanism as applied to the foot
Surgery for Curly Toe Deformity - a Double-Blind Randomised Prospective Trial
- NOTE - no abstract is indexed for this paper; the following is bounded by its title and MeSH indexing (toes - abnormalities, surgery) plus conventional attribution
- A double-blind, randomised, prospective trial of surgery for curly toe deformity - a high level of evidence for a paediatric forefoot procedure
- It is conventionally cited as showing that simple flexor tenotomy is as effective as the more extensive flexor-to-extensor transfer
- That equivalence conclusion is the widely quoted result but is not verifiable from the indexed record alone
Innervation of Three Weight-Bearing Areas of the Foot - an Anatomic Study and Clinical Implications
- Ten feet from five male cadavers, dissected under the microscope, with distances measured against a defined axis from the centre of the medial malleolus to the centre of the calcaneus.
- The lateral plantar nerve courses BENEATH THE ABDUCTOR HALLUCIS AND FLEXOR DIGITORUM BREVIS MUSCLES and supplies the fat pad over the fifth metatarsal head - this page's muscle is one of its two roofs.
- THE INFERIOR CALCANEAL NERVE (BAXTER'S) DOES NOT ALWAYS ARISE WHERE THE EPONYM SUGGESTS: it originated from the LATERAL PLANTAR nerve in 70 per cent and from the MEDIAL CALCANEAL nerve in 30 per cent, 10.66 mm proximal to the axis.
- The tibial nerve divided into medial and lateral plantar nerves 23.45 mm proximal to the axis; the medial calcaneal nerve arose 41.89 mm proximal and divided into two or three branches.
- Heel sensation comes from the medial calcaneal and inferior calcaneal nerves; the weight-bearing pads under the first and fifth metatarsal heads had previously been neglected.