The Donor Tendon of the Flatfoot and the Engine of the Claw Toe
- Origin: posterior surface of the tibia below the soleal line, medial to tibialis posterior - it is the only deep flexor arising solely from the tibia.
- It crosses superficial to tibialis posterior at the ankle and deep to flexor hallucis longus at the knot of Henry, then divides into four tendons for the lateral four toes.
- It lies immediately posterior to tibialis posterior and immediately anterior to the neurovascular bundle in the tarsal tunnel - the D of Tom Dick And Very Nervous Harry.
- Quadratus plantae inserts into the FDL tendon in the sole to correct its oblique line of pull; the four lumbricals arise from the FDL tendons.
- Innervated by the tibial nerve, roots S1 and S2, with motor branches in the proximal third.
- “FDL is roughly one-third the strength of tibialis posterior but has two to three times its excursion - it works as a tenodesis and checkrein, not as a strength substitute.
- “Divide FDL PROXIMAL to the FHL interconnection you have actually identified, not at a memorised level - the slip lies a mean 9 to 11 mm distal to the knot in about half of feet, so 'just distal to the knot' takes it away with the graft in those feet.
- “Harvest is not free: simulated FDL harvest costs about 23% of lesser-toe push-off force, and about one foot in seven has no FHL-to-FDL interconnection at all.
- “Quadratus plantae, uniquely, has no attachment to any phalanx - it inserts entirely into the FDL tendon.
- “In a claw toe the FDL is the deforming force at the interphalangeal joints once the intrinsics have failed.
Overview
Flexor digitorum longus (FDL) is the most medial of the three muscles of the deep posterior compartment. It arises from the posterior surface of the tibia below the soleal line, the only one of the three deep flexors to arise solely from the tibia, and its tendon runs behind the medial malleolus, crosses the sole and divides into four slips for the lateral four toes.
Why it matters to a surgeon. Two features dominate. The first is that FDL is relatively expendable: its tendinous interconnections with flexor hallucis longus at the knot of Henry mean that after harvest the lesser toes usually retain active flexion, driven onward by FHL through the interconnection. That underpins its role as the standard donor for FDL transfer in stage II posterior tibial tendon dysfunction, one of the highest-yield operations in foot and ankle surgery. Relatively is the load-bearing word, and the anatomy section below puts a number on it: the interconnection preserves movement rather than strength, and it is not guaranteed to be present in the foot in front of you.
The second is that FDL is a deforming force. Once the intrinsic muscles of the foot fail, in neuropathy, in cavovarus, after a compartment syndrome, in the diabetic foot, the unopposed long flexors and long extensors produce the claw toe, and FDL is the muscle pulling the interphalangeal joints into flexion.
Attachments, Innervation and Relations
Origin. The posterior surface of the tibia below the soleal line and medial to the vertical ridge, from just below the soleal line to within a few centimetres of the distal tibia, with some fibres from the fascia covering tibialis posterior. It is the only deep posterior compartment muscle arising solely from the tibia: tibialis posterior arises from tibia, fibula and interosseous membrane, and flexor hallucis longus principally from the fibula.
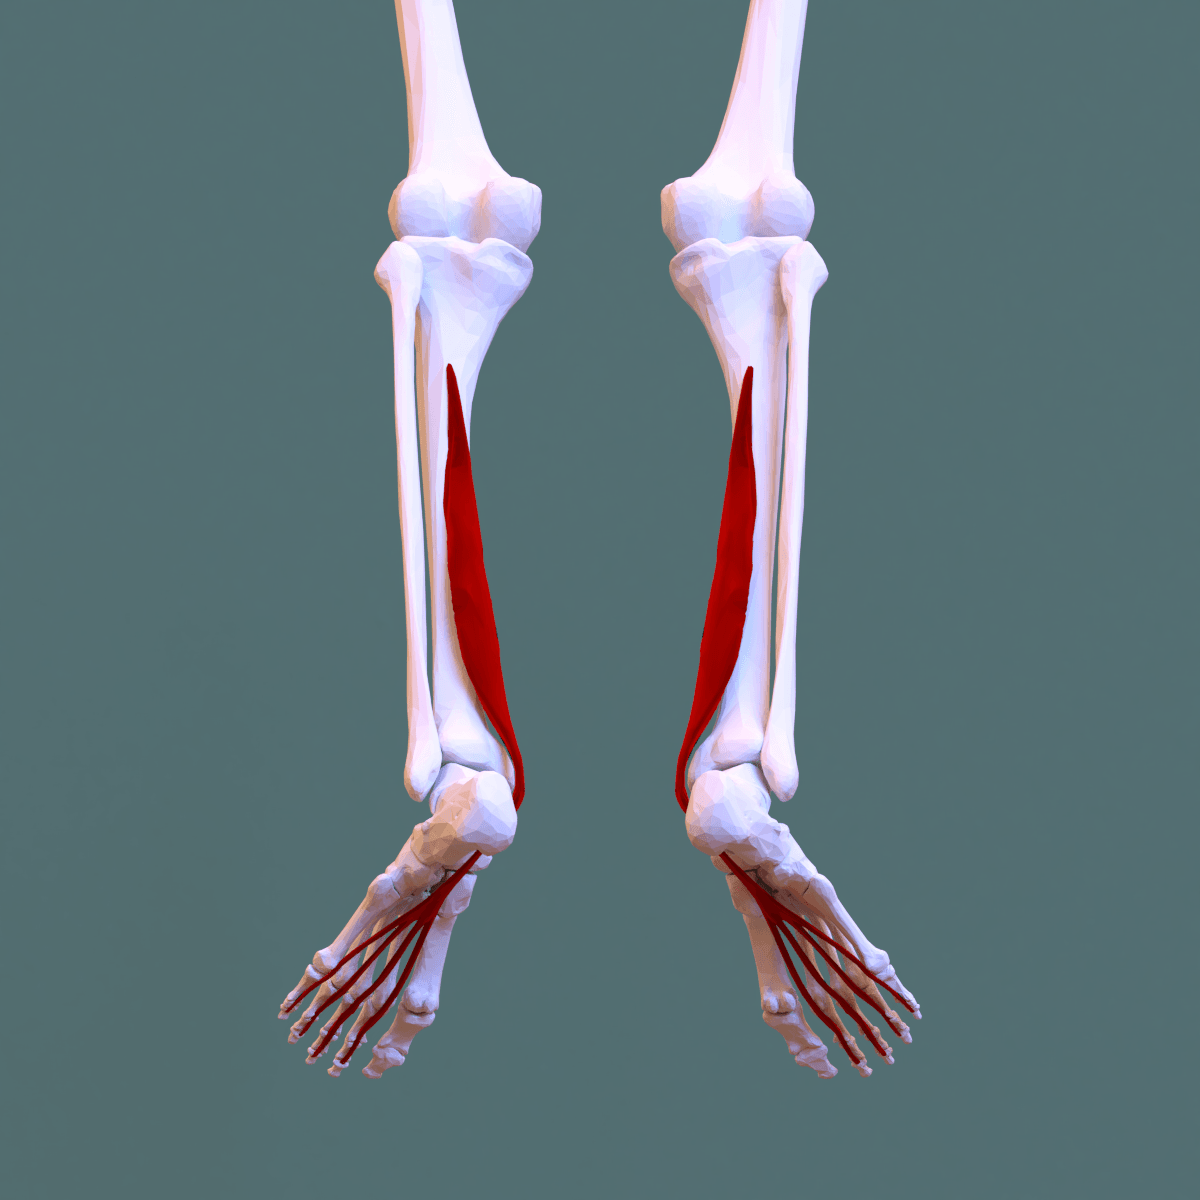
Course at the ankle. The tendon forms in the distal third of the leg and crosses superficial (posterior) to the tibialis posterior tendon at about the level of the medial malleolus, so that in the tarsal tunnel FDL lies immediately posterior to tibialis posterior. It passes behind the malleolus in its own groove and synovial sheath beneath the flexor retinaculum, then turns forward beneath the sustentaculum tali, still superficial to tibialis posterior.
Course in the sole. It runs forward and laterally, crossing deep (dorsal) to flexor hallucis longus at the knot of Henry beneath the navicular and medial cuneiform, where the two tendons exchange slips. It receives the insertion of quadratus plantae (flexor accessorius) on its lateral border, divides into four tendons for the second to fifth toes, and gives origin to the four lumbricals: the first from the medial side of the second tendon (unipennate), the second to fourth from the adjacent sides of the tendons (bipennate).
Insertion. Each tendon passes through the split in the corresponding flexor digitorum brevis tendon, the same relationship as flexor digitorum profundus and superficialis in the hand, and inserts on the plantar base of the distal phalanx of the second to fifth toes. Brevis stops at the middle phalanx, so FDL is the only flexor of the distal interphalangeal joints of the lesser toes.
At the knot of Henry (master knot of Henry), plantar to the navicular and medial cuneiform, the flexor hallucis longus tendon crosses plantar (superficial) to the flexor digitorum longus tendon, and the two are bound together by a fibrous sling and exchange tendinous slips.
- The commonest arrangement transmits drive from FHL to FDL: a single slip from the great toe flexor joining the tendons of the lesser toes, found in 83% of 166 legs in the largest series.
- It is not always there. In a cadaveric series of 36 feet there was no communication at all in 14.7%, roughly one foot in seven with no safety net.
- It is usually not at the knot. In those 166 legs the interconnection lay proximal to, at, or distal to the knot, and the commonest position was distal to it in 52%, by a mean of about 9 to 11 mm.
The level that matters. The lesser toes are driven through the slip, so what counts is not the knot but where the slip joins FDL. Divide FDL proximal to that junction and the slip carries FHL drive onward into the distal tendon, so the toes keep working; divide distal to it and the toe slips are cut off from the slip as well as from FDL, and nothing drives them at all. This is O'Sullivan's conclusion from 16 dissections: transection proximal to the knot of Henry retains hallux and lesser-toe function in the majority of feet.
How expendable is "expendable"? Not completely. In a cadaveric loading study with pressure mapping, simulated FDL harvest still reduced lesser-toe push-off force by 23% and total forefoot force by 9%, and the crossover pattern did not predict who lost most. The interconnection preserves movement, not strength. Consent for reduced toe purchase; do not promise none.
The reciprocal point. The same interconnection means that a distal FHL harvest at or beyond the knot of Henry risks the lesser toes as well as the hallux, which is one of the arguments for a proximal FHL harvest in Achilles reconstruction. FHL harvest is the costlier of the two: it cut great toe pressure by 31% in the same study.
The nerve at the knot. The medial plantar nerve and artery lie immediately adjacent, on the plantar-medial side. They are the structures at risk in any distal harvest, and the reason a plantar-medial incision must be made under direct vision rather than by pulling blindly on a tendon.
It is stated confidently in many sources, but it assumes the interconnection sits at the knot, and it usually does not. A cut placed just distal to the knot therefore lands proximal to the slip in some feet and distal to it in others, which is close to a coin toss for whether the lesser toes keep their drive.
Do this instead: expose the interconnection, apply traction to FHL and watch which toes move, then divide FDL proximal to the junction you have actually seen. If there is no interconnection, tenodese the distal FDL stump to FHL rather than leaving the lesser toes with no motor.
Innervation. The tibial nerve, root values S1 and S2, with an L5 contribution described in some sources. Motor branches arise in the proximal third of the leg and enter the deep surface of the muscle. The tibial nerve reaches the deep compartment beneath the tendinous soleal arch, so a lesion there denervates FDL along with tibialis posterior and flexor hallucis longus.
The lumbricals and quadratus plantae are supplied differently. Quadratus plantae takes the lateral plantar nerve (S2, S3). The first lumbrical takes the medial plantar nerve and the second to fourth the lateral plantar nerve, directly analogous to the hand. A lateral plantar nerve lesion therefore denervates quadratus plantae and three of the four lumbricals, removing the vector correction described below and unbalancing the toes, which contributes to lesser toe deviation and clawing. It is one of the mechanisms by which a tarsal tunnel syndrome or a distal tibial nerve lesion produces lesser toe deformity.
Root value logic. S1 is tested by plantarflexion, eversion and the ankle jerk; S2 contributes to toe flexion and the intrinsics. Weak lesser toe flexion with weak inversion localises to the tibial nerve or the deep posterior compartment. Weak lesser toe extension localises to L5 and the deep peroneal nerve, a different problem entirely.
Blood supply. Muscular branches of the posterior tibial artery, with a contribution from the peroneal artery proximally. The tendon is fed through a mesotendon and vincular system from the posterior tibial artery and distally from the medial and lateral plantar arteries. FDL is a well-vascularised, robust tendon, which is part of why it makes a good transfer donor, and it has no equivalent of the notorious watershed segment that afflicts the tibialis posterior tendon just distal to the medial malleolus. It is never used as a muscle flap: it is deep, functionally significant, and supplied by unnamed segmental branches, and deep posterior compartment muscle is not sacrificed for soft tissue cover.
Relations in the leg. FDL is the most medial of the deep posterior compartment muscles, lying on the posterior surface of the tibia. Tibialis posterior lies lateral and deep to it, flexor hallucis longus lateral on the fibula, and the deep transverse fascia and beyond it the soleus behind. The posterior tibial artery and tibial nerve lie on the posterior surface of tibialis posterior and FDL, between them and the deep transverse fascia.
At the ankle: the tarsal tunnel. Anterior to posterior beneath the flexor retinaculum the order is tibialis posterior, flexor digitorum longus, posterior tibial artery and veins, tibial nerve, flexor hallucis longus. FDL lies immediately posterior to tibialis posterior and immediately anterior to the neurovascular bundle, and that relationship defines the safe plane for harvest: between the two tendons and strictly anterior to the bundle. The tibial nerve divides into medial and lateral plantar nerves within or just distal to the tunnel, and the first branch of the lateral plantar nerve (Baxter nerve) arises here.
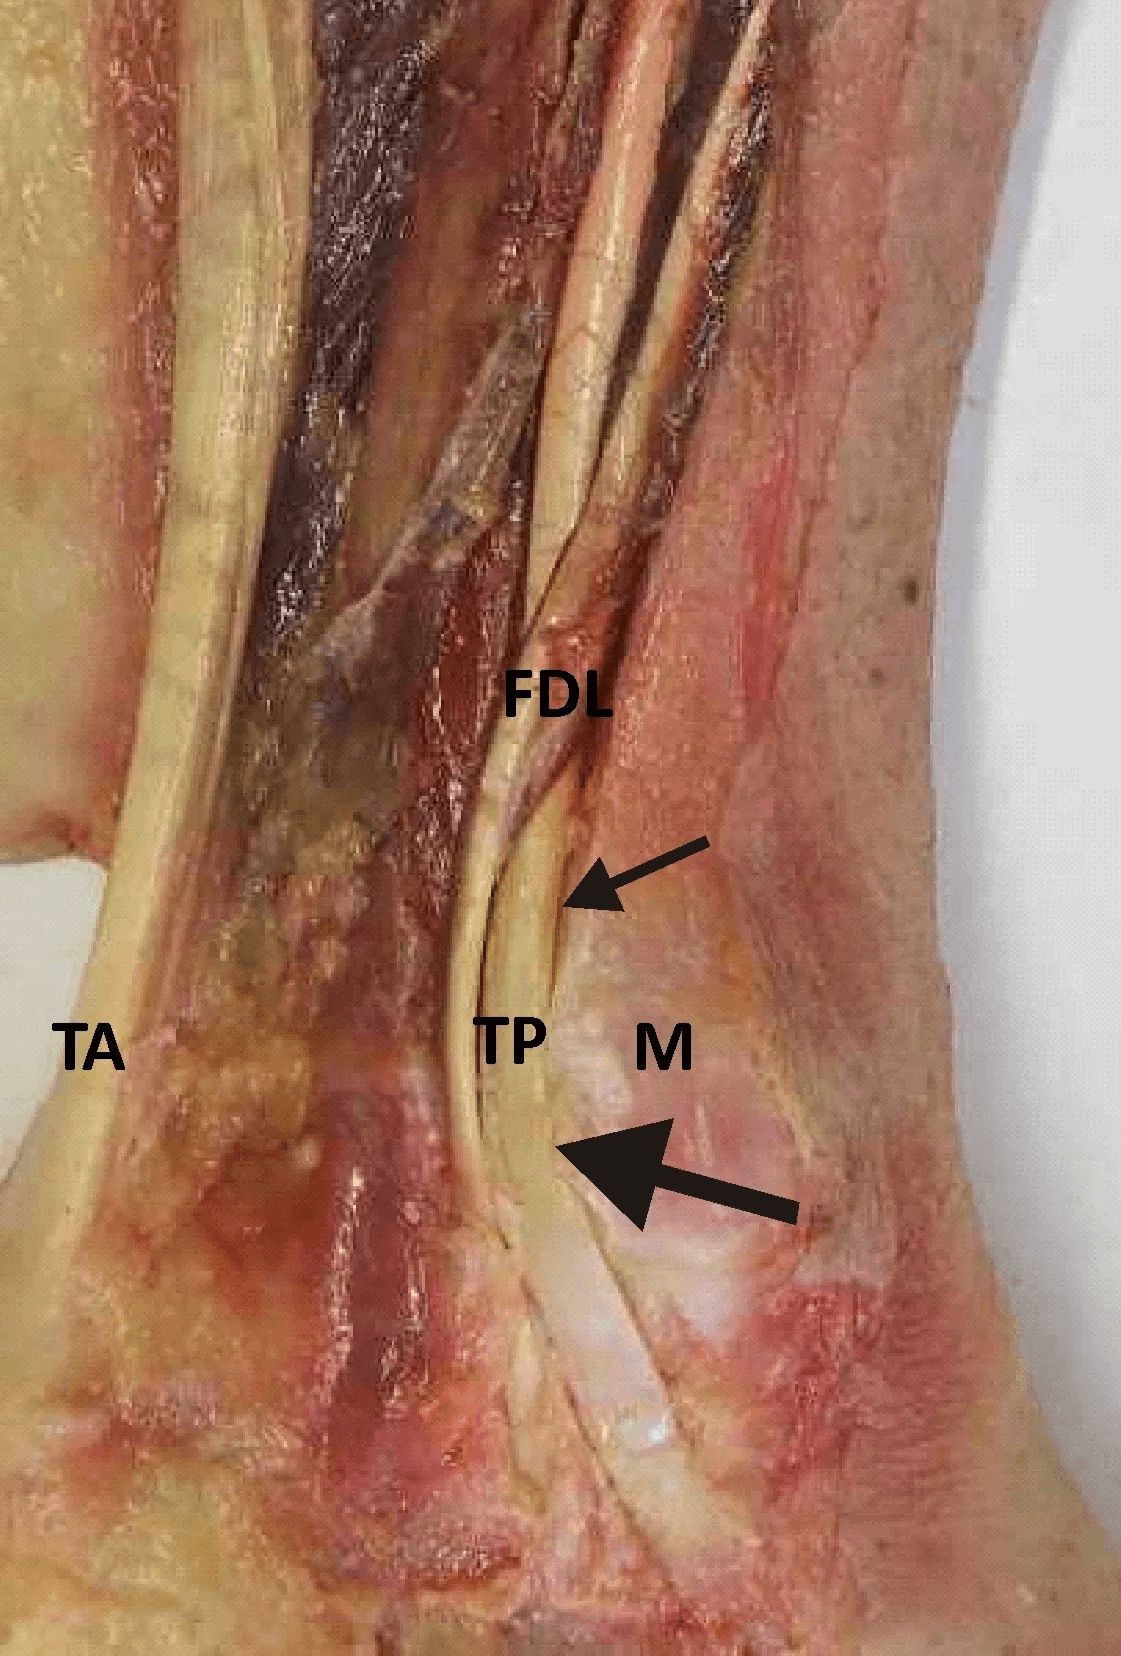
Tom Dick And Very Nervous HarryTarsal Tunnel - Anterior to Posterior
Hook:FDL sits between tibialis posterior in front and the neurovascular bundle behind - the whole safety logic of the medial hindfoot approach is contained in that single sentence.
In the sole. FDL runs deep to the plantar aponeurosis and flexor digitorum brevis (first layer), forming part of the second layer of the sole with FHL, quadratus plantae and the lumbricals. The lateral plantar nerve and artery run laterally across the sole between the first and second layers, immediately superficial to quadratus plantae. Distally each tendon passes through the split in the corresponding brevis tendon within the fibro-osseous flexor sheath of the toe.
In the medial hindfoot the tibialis posterior and flexor digitorum longus tendons look alike, lie in adjacent sheaths, and are easily confused, and in a flatfoot reconstruction the tibialis posterior is usually diseased and therefore even less distinctive. The discriminators are absolute: tibialis posterior is anterior, thicker, and inserts on the navicular tuberosity as a single broad tendon; flexor digitorum longus is posterior, thinner, and divides into four slips distally.
Trace each tendon distally before dividing anything. Harvesting the tibialis posterior by mistake converts a reconstructable stage II deformity into a disaster with no donor left.
Action and Biomechanics
Actions. The first is the one no other muscle can perform:
- Flexion of the distal interphalangeal joints of the second to fifth toes, its unique and irreplaceable action, since flexor digitorum brevis reaches only the middle phalanges
- Flexion of the proximal interphalangeal and metatarsophalangeal joints of the lesser toes, assisted by brevis and the intrinsics
- Plantarflexion of the ankle, weak, with a small moment arm
- Inversion of the hindfoot and dynamic support of the medial longitudinal arch, because it passes beneath the sustentaculum tali and along the medial column, synergistic with tibialis posterior
In gait. FDL is active from mid-stance to terminal stance, peaking around heel rise. It presses the toes to the floor during push-off, which broadens the weightbearing base of the forefoot, stabilises the toes against the ground and increases the effective lever arm of the foot. Toe purchase matters: a foot in which the toes do not touch the ground at push-off loads the metatarsal heads more heavily, which is one mechanism of metatarsalgia in a claw toe foot. FDL is in phase with tibialis posterior, which is why it can be transferred to substitute for it without any need for phase re-education.
Flexor digitorum longus enters the sole from the medial side, running obliquely from posteromedial to anterolateral. If it acted alone, contracting it would flex the toes and pull them medially, so the lesser toes would deviate toward the great toe with every push-off.
Quadratus plantae (flexor accessorius) solves this. It arises by two heads from the medial and lateral borders of the plantar surface of the calcaneus and inserts into the lateral border of the FDL tendon in the sole. Its pull is directly posterior, along the long axis of the foot, so vectorially it cancels the medial deviating component of the FDL pull and the resultant is straight-line flexion of the toes. It also lets the toes be flexed with the ankle in any position, partially uncoupling toe flexion from ankle position.
The exam point. Quadratus plantae, uniquely, has no attachment to any phalanx: it inserts entirely into a tendon.
Strength and excursion. These are the numbers that drive transfer surgery, and the comparison with tibialis posterior is the one an examiner wants:
- Tibialis posterior
- Substantially stronger - roughly three times FDL
- Flexor digitorum longus
- Roughly one-third of tibialis posterior
- Consequence for transfer
- FDL cannot restore native inversion power
- Tibialis posterior
- Short - about 1 to 1.5 cm
- Flexor digitorum longus
- Longer - about 2 to 3 cm
- Consequence for transfer
- Excursion is adequate; strength is not
- Tibialis posterior
- Early to mid stance
- Flexor digitorum longus
- Mid to terminal stance
- Consequence for transfer
- In phase - no re-education required
- Tibialis posterior
- Beneath the sustentaculum to the navicular
- Flexor digitorum longus
- Beneath the sustentaculum, adjacent course
- Consequence for transfer
- Almost identical vector - a direct anatomical substitute
- Tibialis posterior
- Not expendable - loss causes flatfoot
- Flexor digitorum longus
- Relatively expendable - FHL drives the toes through the interconnection, at a cost of about 23% of lesser-toe push-off
- Consequence for transfer
- This is why FDL is the donor and not the recipient
When FDL fails. In isolation the loss is active distal interphalangeal flexion of the lesser toes, detectable on examination but rarely a functional complaint, and loss of toe purchase at push-off, which transfers load to the metatarsal heads. In combination with intrinsic failure the picture is very different: FDL becomes a deforming force, and clawing results.
Surface Anatomy and Examination
Palpation. The tendon can be felt immediately posterior to the tibialis posterior tendon behind the medial malleolus, with the toes actively flexed and relaxed.
Isolating the long flexor. Stabilise the middle phalanx of a lesser toe and ask the patient to flex the distal interphalangeal joint. Flexor digitorum brevis inserts on the middle phalanx and cannot flex the DIP joint, so DIP flexion is FDL alone, directly analogous to isolating flexor digitorum profundus in the hand. Absent or weak DIP flexion means FDL laceration, rupture, denervation or a completed transfer, allowing for pain inhibition and a stiff DIP joint as false positives.
Isolating the short flexor. Hold all the other toes in extension, which tenodeses the common FDL muscle belly, and ask for PIP flexion of the tested toe.
Named tests and signs. The tests that matter around this tendon:
- How to perform
- Push the metatarsal head dorsally from the plantar surface, simulating weightbearing
- Positive finding
- The toe deformity corrects
- What it means
- The deformity is flexible and a soft-tissue procedure will suffice; if the toe does not straighten, a bony procedure is required
- False positives
- A rigid joint will not correct
- How to perform
- Passively straighten the toe with the ankle in neutral and then plantarflexed
- Positive finding
- Deformity corrects more with the ankle plantarflexed
- What it means
- Tethering of the long flexors proximally, or a tenodesis effect
- False positives
- Fixed capsular contracture will not change
- How to perform
- Observe the standing patient from behind
- Positive finding
- More toes visible lateral to the leg
- What it means
- Hindfoot valgus with forefoot abduction - the setting in which FDL transfer is used
- False positives
- External tibial torsion; always compare sides
- How to perform
- Rise onto the toes on one leg
- Positive finding
- Cannot rise, or rises without the heel inverting
- What it means
- Tibialis posterior insufficiency - the indication for FDL transfer
- False positives
- Balance, calf weakness, pain inhibition
- How to perform
- Passive dorsiflexion with the knee extended and then flexed, hindfoot held neutral
- Positive finding
- Improvement with the knee flexed
- What it means
- Isolated gastrocnemius contracture - must be corrected during flatfoot reconstruction
- False positives
- Midfoot substitution if the hindfoot is not locked
- How to perform
- Test light touch in the medial and lateral plantar territories
- Positive finding
- Loss of protective sensation
- What it means
- Neuropathy - the setting for diabetic claw toe and tip ulceration
- False positives
- Callus; test with a 10 g monofilament at defined sites
The vocabulary of lesser toe deformity. Examiners test it, and the joint positions are what separate the three:
- Claw toe: metatarsophalangeal joint extended, proximal interphalangeal flexed, distal interphalangeal flexed. Usually multiple toes, and usually neurological, from intrinsic failure with unopposed long flexors and extensors
- Hammer toe: metatarsophalangeal joint neutral or extended, proximal interphalangeal flexed, distal interphalangeal neutral or extended. Usually a single toe, often the second, and usually mechanical: footwear, a long second ray, or hallux valgus crowding
- Mallet toe: distal interphalangeal flexed alone, with the MTP and PIP normal. This is specifically an FDL problem, and it is the deformity most reliably corrected by a simple flexor tenotomy
Always look for the cause. Flexibility is settled by the push-up test in the table above. A claw toe pattern in multiple toes then demands a neurological examination: diabetes, Charcot-Marie-Tooth disease, a previous compartment syndrome, a spinal lesion. Treating the toes without diagnosing the neuropathy is a missed diagnosis.
Complications
- Mechanism
- The two tendons are adjacent and look alike, and the tibialis posterior is diseased and atypical
- Prevention
- Trace both tendons distally before dividing
- Management
- Salvage is very difficult - consider FHL transfer or convert to arthrodesis
- Mechanism
- Distal harvest at the knot of Henry
- Prevention
- Work under direct vision through an adequate incision; do not pull the tendon blindly
- Management
- Neurolysis if entrapped; a plantar neuroma is very difficult to treat
- Mechanism
- Dissecting posterior to FDL in the tarsal tunnel
- Prevention
- Stay anterior to the bundle throughout; FDL is the posterior limit of safe dissection
- Management
- Immediate repair with microsurgical support
- Mechanism
- The nerve crosses the lateral hindfoot posteroinferior to the fibular tip
- Prevention
- Full-thickness incision to bone, subperiosteal retractors
- Management
- Neuroma excision and burial if refractory
- Mechanism
- Excessive translation tents the bundle over the medial calcaneal wall
- Prevention
- Keep to the standard translation; protect the medial cortex from the saw
- Management
- Reduce the translation or release the tarsal tunnel
- Mechanism
- Dividing FDL distal to the FHL interconnection, which takes the slip with the graft and leaves the toe tendons with no motor - or harvesting a foot that has no interconnection at all
- Prevention
- Identify the slip, pull FHL and watch the toes, then divide proximal to the junction; tenodese the distal stump to FHL when no interconnection is found
- Management
- Usually well tolerated even when it occurs, though push-off is measurably reduced; flexor tenodesis if a symptomatic deformity develops
- Mechanism
- Omitting the lateral column lengthening, Cotton osteotomy or gastrocnemius recession
- Prevention
- Full deformity assessment: Silfverskiold, forefoot plane, talonavicular uncoverage, weightbearing ankle view
- Management
- Revision with the omitted procedure; arthrodesis if now fixed
- Mechanism
- Excessive tension producing a stiff, inverted foot
- Prevention
- Tension in inversion and plantarflexion, and check the foot sits plantigrade against a flat plate
- Management
- Release and retension - difficult once healed
- Mechanism
- Loss of active flexion of the treated toe
- Prevention
- Counsel in advance - it is expected and trivial in a neuropathic foot
- Management
- Reassurance; no treatment needed in the neuropathic patient
- Mechanism
- Rigid rather than flexible deformity, or inadequate perfusion
- Prevention
- Confirm flexibility with the push-up test and confirm perfusion before tenotomy
- Management
- Bony procedure, revascularisation, or amputation of the toe if perfusion cannot be restored
- Mechanism
- Operating on a fixed deformity, or not addressing the MTP joint
- Prevention
- Push-up test in every case; address the MTP with release, extensor lengthening and a Weil osteotomy where needed
- Management
- Revision with the appropriate bony procedure
- Mechanism
- Ischaemic fibrosis of FDL, FHL and tibialis posterior
- Prevention
- Deliberately divide the deep transverse fascia at fasciotomy
- Management
- Tendon lengthening or release, sometimes arthrodesis - results are far worse than timely fasciotomy
Clinical Relevance
FDL transfer for stage II posterior tibial tendon dysfunction is the operation this anatomy exists to serve, and the tabs below take it from indication to the structures that can be damaged.
The setting. Stage II posterior tibial tendon dysfunction (progressive collapsing foot deformity): the tendon is elongated, degenerate or torn, there is a planovalgus deformity with forefoot abduction, and crucially the hindfoot corrects passively to neutral. A fixed deformity is stage III and requires arthrodesis.
Why FDL is chosen. It is relatively expendable through the knot of Henry interconnection, it is in phase with tibialis posterior so no re-education is needed, it is adjacent in the same surgical field through the same medial incision, its line of pull beneath the sustentaculum tali to the medial midfoot is almost identical, and its excursion is adequate. The numbers behind each of those are in the strength and excursion table above.
What it cannot do. At about one-third the strength of tibialis posterior it cannot restore native inversion power, and any candidate who claims otherwise will be corrected. The transfer works as a dynamic checkrein, a tenodesis and a proprioceptive restraint that holds a correction produced by bone, which is why it must be combined with a medial displacement calcaneal osteotomy. The osteotomy moves the tuberosity medially, bringing the Achilles vector medial to the subtalar axis so that it becomes an invertor again rather than a deforming evertor, and shifts the weightbearing axis. A tendon transfer alone will stretch out against a deformed, malaligned hindfoot: the bone does the work, and the tendon holds it.
Lesser toe deformity and flexor surgery. The intrinsic muscles, the interossei and lumbricals, flex the metatarsophalangeal joints and extend the interphalangeal joints. When they fail, in neuropathy, cavovarus or a previous compartment syndrome, the long extensors extend the MTP unopposed and the long flexors flex the interphalangeal joints unopposed, and the result is the claw toe.
The MTP joint is the key. Once the MTP hyperextends, the plantar plate is drawn distally, the metatarsal head is driven plantarwards, the fat pad migrates distally and no longer cushions the head, and metatarsalgia and plantar keratosis follow. Correcting the toe alone without addressing the MTP joint will not relieve the metatarsalgia.
A flexible deformity (positive push-up test) is treated with soft tissue:
- Flexor tenotomy: simple division of the flexor tendon, percutaneous or open
- Flexor-to-extensor transfer (Girdlestone-Taylor): the FDL tendon is split longitudinally and both limbs are passed dorsally either side of the proximal phalanx and sutured to the extensor hood, converting the deforming flexor into an MTP flexor and IP extensor and reproducing the lost intrinsic function. It requires a flexible deformity and is combined with an MTP release where the joint is contracted
A fixed deformity (negative push-up test) needs bone, and soft-tissue procedures alone will recur:
- PIP resection arthroplasty or arthrodesis for the interphalangeal component
- MTP release, extensor lengthening and a shortening metatarsal osteotomy (Weil) for the MTP component
Percutaneous flexor tenotomy in the diabetic foot. The indication is a neuropathic ulcer at the tip of a clawed or hammered toe in a patient with adequate perfusion. The deformity drives the tip of the distal phalanx into the ground, and no dressing or offloading device will heal an ulcer that is being re-traumatised at every step.
The procedure is a percutaneous division of the flexor tendon at the plantar aspect of the toe through a needle or a small blade stab incision, usually under local anaesthetic in the clinic, taking seconds per toe. The tendon lies immediately deep to the plantar skin at the level of the proximal or middle phalanx, with the digital neurovascular bundles at the plantar-medial and plantar-lateral corners, so aim strictly midline plantar and pass the blade transversely against the bone. The toe straightens, the tip lifts off the ground, and the ulcer offloads; reported healing rates are high and recurrence rates low, with a very low complication rate, which makes it a genuinely high-value, low-cost, low-risk intervention.
Prerequisites and counselling. Adequate arterial perfusion, no active spreading infection or osteomyelitis requiring other treatment, and a flexible deformity, since a rigidly fixed toe needs a bony procedure. The toe will float slightly and lose active flexion; in a neuropathic foot this is a trivial price for ulcer healing, and patients should be told it will happen.
Tenosynovitis of the FDL occurs alongside tibialis posterior tenosynovitis in the medial hindfoot, and can contribute to tarsal tunnel symptoms by crowding the tunnel.
Laceration of the FDL in the sole or behind the medial malleolus is uncommon and, in isolation, well tolerated. It should be looked for specifically in any medial ankle or plantar laceration, alongside the tibial nerve.
Flexor digitorum accessorius longus is an accessory muscle arising in the deep posterior compartment and inserting into the FDL or quadratus plantae. It is present in a minority of feet and is a recognised cause of tarsal tunnel syndrome by occupying space in the tunnel; it is also a recognised incidental MRI finding that should not be mistaken for a mass.
Deep posterior compartment syndrome infarcts FDL along with FHL and tibialis posterior. The late sequel is fixed clawing of the toes with plantar sensory loss and a cavovarus foot.
Surgical Relevance
Other operations involving FDL. The tendon is met, moved or endangered in other operations too:
- Posteromedial approach to the tibia: the FDL is elevated from the posterior tibia, with the neurovascular bundle retracted, giving access to the posterior tibial cortex for plating a posterior malleolar fragment or grafting a nonunion
- Posteromedial fasciotomy: the incision lies 1 to 2 cm posterior to the posteromedial tibial border. The superficial posterior compartment is opened first, then the deep transverse fascia must be deliberately divided to release the deep compartment containing FDL. Failing to do so is the classic incomplete fasciotomy, and its late sequel is a clawed, insensate foot
- Tarsal tunnel release: the FDL sheath is opened as part of the release, and an accessory flexor digitorum accessorius longus is excised if present
- FDL transfer to the fifth metatarsal base: used to restore eversion when both peroneal tendons are irreparable
- FDL transfer for Achilles reconstruction: an alternative to FHL, weaker but preserving hallux function; occasionally preferred in a dancer or sprinter
- Calcaneal fracture fixation: a screw directed from lateral to medial into the sustentacular fragment can transfix the FDL and the neurovascular bundle if it over-penetrates the medial cortex
FDL as a donor. Flexor digitorum longus is the textbook example of a good transfer donor, and the reasons generalise to any tendon transfer:
- Expendable: its function is duplicated or compensated, here by the FHL interconnection at the knot of Henry
- Adequate excursion for the intended job
- In phase with the recipient, so no re-education is needed
- A straight line of pull through a smooth gliding bed, without an acute turn
- Adequate power, though here the power is inadequate to substitute fully, which is why the transfer is combined with a bony procedure. That candid limitation is precisely the point examiners want acknowledged
- A supple, passively correctable recipient joint: stage II, not stage III
Guidelines, Registries & Global Practice
Anatomical variation across populations
- Knot of Henry interconnections are consistently present but variable in pattern. The commonest arrangement transmits drive from FHL to FDL, but reciprocal slips and more complex patterns occur, and the slips vary in number and thickness. The functional consequence of a harvest therefore cannot be assumed to be identical in every foot, and the surgeon should inspect the interconnection directly.
- Quadratus plantae varies in the presence and size of its two heads; the lateral head is absent in a minority of feet, which theoretically alters the vector correction.
- Flexor digitorum accessorius longus is an accessory muscle present in a minority of feet, arising in the deep posterior compartment and inserting into the FDL or quadratus plantae. It is a recognised cause of tarsal tunnel syndrome and an incidental MRI finding that should not be mistaken for a mass.
- Lumbrical number and configuration occasionally varies, with absence of the fourth lumbrical described.
Side-by-side guidance
- Position relevant to flexor digitorum longus
- Support a substantial trial of orthoses, immobilisation and eccentric strengthening before reconstruction in stage I and early stage II PTTD, then stage-directed surgery with FDL transfer plus bony realignment for flexible stage II.
- Position relevant to flexor digitorum longus
- Emphasise deformity-specific reconstruction combining tendon transfer with bony realignment and correction of gastrocnemius contracture; arthrodesis reserved for rigid deformity.
- Position relevant to flexor digitorum longus
- Recommends describing the deformity by its components - hindfoot valgus, forefoot abduction, forefoot varus, peritalar subluxation, ankle instability - rather than a single linear stage, and highlights the spring ligament as central to the pathoanatomy.
- Position relevant to flexor digitorum longus
- Supports surgical offloading, including flexor tenotomy, for a non-healing neuropathic ulcer related to a toe deformity in an adequately perfused foot, alongside offloading, infection control and structured surveillance.
- Position relevant to flexor digitorum longus
- In posteromedial fasciotomy, emphasises deliberate division of the deep transverse fascia to release the deep posterior compartment; in medial hindfoot surgery, emphasises the fixed order of the tarsal tunnel structures.
Resource-dependent practice
- Well-resourced settings: weightbearing CT, MRI, interference screw fixation, spring ligament internal bracing, arthroereisis implants.
- Limited-resource settings: the diagnosis of stage II posterior tibial tendon dysfunction is entirely clinical - too-many-toes, single heel raise, passive correctability - and weightbearing radiographs suffice for planning. The FDL transfer with medial displacement calcaneal osteotomy requires only a saw, two screws, suture and basic instruments, and is fully deliverable at district hospital level. A well-executed triple arthrodesis remains a reliable operation for a rigid deformity where implants are limited.
- Percutaneous flexor tenotomy is one of the highest-value interventions in global diabetic foot care: it requires a blade, local anaesthetic and a few minutes, and it converts a chronically non-healing tip ulcer into a healing one. In settings where amputation is the default endpoint for a chronic toe ulcer, its availability changes outcomes substantially.
Registry and outcome signals
- There is no dedicated registry for flatfoot reconstruction or lesser toe surgery. Institutional cohorts consistently show durable improvement after combined FDL transfer and bony realignment for flexible stage II deformity, with the main causes of failure being under-correction, an unaddressed gastrocnemius contracture, and unrecognised fixed forefoot varus.
- Diabetic foot series consistently report high ulcer healing rates and low recurrence at the treated toe after percutaneous flexor tenotomy, with the principal caveats being adequate perfusion and a flexible deformity.
- Major trauma and open fracture audits consistently link delayed or incomplete fasciotomy - most often failure to release the deep posterior compartment - to poor functional outcomes including fixed toe clawing.
MCQ Practice Points
Q: What is distinctive about the origin of flexor digitorum longus? A: It arises solely from the posterior surface of the tibia below the soleal line, medial to the vertical ridge - the only deep posterior compartment muscle to arise from the tibia alone.
Q: Where does FDL insert? A: The plantar base of the distal phalanges of the second to fifth toes, after passing through the split in the corresponding flexor digitorum brevis tendon.
Q: What lies immediately anterior and immediately posterior to FDL in the tarsal tunnel? A: Tibialis posterior anteriorly and the posterior tibial artery and veins posteriorly, then the tibial nerve, then FHL - Tom Dick And Very Nervous Harry.
Q: Where exactly is FDL divided during a transfer, and why is "just distal to the knot of Henry" the wrong answer?
A: Divide PROXIMAL to the point where the flexor hallucis longus slip joins FDL, so that the slip continues to drive the distal tendon and the lesser toes keep flexing. The familiar rule fails because the interconnection is not at the knot: in the largest series (166 legs) it lay a mean 9 to 11 mm distal to the knot in 52% of feet, so a cut "just distal to the knot" takes the slip away with the graft in about half of cases. Identify the slip, pull FHL, watch the toes, then cut proximal to what you have seen - and in the roughly 15% with no interconnection at all, tenodese the stump to FHL.
Q: What is the function of quadratus plantae and what is unique about it? A: It corrects the oblique line of pull of FDL so that toe flexion is straight rather than medially deviated. It is the only muscle in the body with no attachment to a phalanx - it inserts entirely into the FDL tendon.
Q: Where do the lumbricals of the foot arise, and what is their nerve supply? A: From the flexor digitorum longus tendons. The first is supplied by the medial plantar nerve and the second to fourth by the lateral plantar nerve - exactly as in the hand.
Q: How does FDL compare with tibialis posterior? A: Roughly one-third the strength but two to three times the excursion. The transfer works as a tenodesis and checkrein, not as a strength substitute.
Q: How do you test FDL specifically? A: Stabilise the middle phalanx and resist flexion of the distal interphalangeal joint. Flexor digitorum brevis inserts on the middle phalanx and cannot flex the DIP joint.
Q: Define the three lesser toe deformities. A: Claw - MTP extended, PIP flexed, DIP flexed, usually multiple and neurological. Hammer - MTP neutral or extended, PIP flexed, DIP neutral or extended, usually single and mechanical. Mallet - DIP flexed alone, an FDL problem correctable by tenotomy.
Q: What does the Kelikian push-up test tell you? A: Whether the lesser toe deformity is flexible. Pushing the metatarsal head dorsally simulates weightbearing; if the toe straightens, a soft-tissue procedure will suffice.
Q: What is a flexor-to-extensor transfer? A: The FDL tendon is split longitudinally and both limbs passed dorsally either side of the proximal phalanx to the extensor hood, converting the deforming flexor into an MTP flexor and IP extensor, reproducing lost intrinsic function. It requires a flexible deformity.
Q: How far is the calcaneal tuberosity translated in an MDCO, and why? A: 8 to 12 mm medially, to bring the Achilles insertion medial to the subtalar joint axis so that it acts as an invertor rather than an evertor. Beyond about 10 mm the tibial nerve is progressively tented on the medial calcaneal wall.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are about to perform a flexor digitorum longus transfer and medial displacement calcaneal osteotomy for a 52-year-old woman with stage II posterior tibial tendon dysfunction. Talk me through the medial dissection, exactly where you divide the tendon, and why.”
“A 63-year-old man with type 2 diabetes and peripheral neuropathy has a 6 mm ulcer at the tip of his clawed second toe. It has been present for three months despite dressings and a total contact cast. His pedal pulses are palpable. The toe straightens when you push up under the metatarsal head. How would you treat him?”
“A 29-year-old man is eight months after intramedullary nailing of a closed tibial shaft fracture. The fracture has united. He complains that all his toes curl under and the sole of his foot feels numb. On examination all five toes are clawed and the deformity does not change with ankle position. He has reduced sensation over the whole sole. What has happened and what will you do?”
Anatomy
- Origin: posterior TIBIA below the soleal line - the only deep flexor from tibia alone
- Insertion: plantar base of the distal phalanges of toes 2 to 5
- Passes through the split in flexor digitorum brevis - like FDP and FDS in the hand
- Nerve: tibial, S1-S2, motor branches in the proximal third
- Crosses superficial to tibialis posterior at the ankle, deep to FHL at the knot of Henry
The Sole
- Quadratus plantae inserts into the FDL tendon - corrects the oblique vector
- Quadratus plantae has no phalangeal attachment - unique
- The four lumbricals arise from the FDL tendons
- First lumbrical medial plantar nerve; second to fourth lateral plantar nerve
- Quadratus plantae is lateral plantar nerve
Tarsal Tunnel
- Tom Dick And Very Nervous Harry
- FDL is the D - behind tibialis posterior, in front of the bundle
- Safe harvest plane is between TP and FDL, anterior to the bundle
- Confirm FDL by its four distal slips
FDL Transfer
- Stage II PTTD - flexible planovalgus that corrects passively
- One-third the strength of TP but 2-3 cm excursion, and in phase
- Divide PROXIMAL to the FHL slip you have identified - not at a fixed level relative to the knot
- Medial plantar nerve is immediately adjacent at the knot
- Always combine with MDCO 8-12 mm plus gastrocnemius recession
- Add Evans for abduction, Cotton for fixed forefoot varus
Lesser Toes
- Claw = MTP extended, PIP and DIP flexed, multiple, neurological
- Hammer = PIP flexed, single, mechanical
- Mallet = DIP flexed alone - pure FDL
- Kelikian push-up test determines flexibility
- Percutaneous flexor tenotomy heals diabetic tip ulcers - confirm perfusion first
Evidence Base
Anatomy of the Sural Nerve with Emphasis on the Incision for Medial Displacement Calcaneal Osteotomy
- 20 cadaveric specimens dissected specifically to map the sural nerve within the operative field of a medial displacement calcaneal osteotomy
- Distances were expressed as RATIOS between fixed bony landmarks rather than as absolute centimetre measurements, because absolute distances scale with foot size
- Median ratio of the nerve position from the lateral malleolar tip toward the posteroinferior calcaneal margin was 0.26 (range 0.19 to 0.32) along the diagonal
- Concluded it is relatively safe to make the oblique incision through a point no less than one third of the distance from the tip of the lateral malleolus to the posteroinferior margin of the calcaneus
Treatment of Stage II Posterior Tibial Tendon Deficiency with FDL Transfer and Calcaneal Osteotomy
- Retrospective review of 129 patients operated between 1990 and 1997 for stage II posterior tibial tendon deficiency
- All had a painful flexible flatfoot without fixed forefoot supination deformity
- Treated with medial translational calcaneal osteotomy plus flexor digitorum longus transfer to the navicular
- At a mean of 5.2 years the mean AOFAS hindfoot score was 79 of 100 (range 54 to 93) - a good result, not a normal foot, and the best score in the series was 93
- 125 patients (97%) had pain relief and 108 (84%) could wear ordinary shoes without an orthotic, but SUBTALAR MOTION WAS REDUCED IN 73 OF 129 (56%) and isokinetic inversion or plantarflexion was weak in 26 (20%); there were seven significant complications in six patients
Tibialis Posterior Tendon Dysfunction - Staging and Treatment
- Established that dysfunction of the tibialis posterior tendon evolves through a series of stages, each with characteristic pain, clinical signs and radiographic changes
- The staging system permits clarification and individualisation of the dysfunction, the expected pathological changes, and the surgical treatment
- The three stages are tenosynovitis with a tendon of normal length, tendon elongation with a flexible deformity, and fixed hindfoot deformity
- Restored attention to the importance of the tibialis posterior tendon in normal hindfoot function
Interconnections Between Flexor Digitorum Longus and Flexor Hallucis Longus at the Knot of Henry
- Cadaveric study of the anatomical variations in the tendinous interconnection between FDL and FHL at the knot of Henry
- In over two-thirds of specimens, tension applied to the FHL tendon ALONE produced flexion of all the digits as well as the hallux
- Framed explicitly around deciding which of the two tendons should be transected proximal to the knot of Henry in tibialis posterior dysfunction surgery
- The pattern is variable, so the functional consequence of a harvest cannot be assumed identical in every foot
The Myth of Muscle Balance - Relative Strengths and Excursions of Normal Muscles About the Foot and Ankle
- Muscle fibre lengths and muscle weights below the knee were measured in the lower limbs of five cadavers to derive the relative strength and excursion of each muscle
- The plantarflexors of the ankle were found to be SIX times as strong as the dorsiflexors
- The authors discarded the concept of muscle balance in tendon transfer surgery and proposed that task appropriateness should be the guide
- Because muscle fibre length and excursion are constantly related, contracture is accompanied by decreased excursion - and tendon lengthening improves the deformity but does NOT improve the decreased active range of movement
Anatomical Reconstruction of the Spring Ligament Using Peroneus Longus Tendon Graft
- Posterior tibial tendon insufficiency is often accompanied by FAILURE OF THE SPRING LIGAMENT, and the authors set out to test whether repairing that ligament alone can correct the deformity without bony realignment
- A flatfoot model of 5 to 15 degrees of talonavicular abduction was created in 10 cadaver foot-ankle specimens and loaded to 357 N, and three different peroneus longus reconstructions were compared
- A superomedial and plantar passage of the graft through the calcaneus and navicular outperformed the other two routes, taking the talonavicular joint from 9.1 +/- 8.1 degrees abducted to 1.0 +/- 6.8 degrees adducted
- The subtalar joint moved from 3.1 +/- 3.3 degrees everted to 0.4 +/- 4.2 degrees inverted, so the correction acted at both joints
Percutaneous Flexor Tenotomy for Diabetic Toe Ulcers
- 38 patients and 65 toes over 4 years; percutaneous tenotomy of BOTH the superficial and deep flexor tendons through a small transverse plantar stab incision just proximal to the web level
- 25 of 27 ulcerated toes (93%) healed, in a median of 21 days (range 7 to 224 days), with only 3 recurrences
- No infection of any incision and no toe amputations; no complications in the neuro-ischaemic ulcers
- No toe treated with preventive tenotomy went on to ulcerate, though 33 further ulcers occurred elsewhere in 18 patients (47%) over a median 31-month follow-up
Isolated Gastrocnemius Tightness
- Prospective case-control study: 34 consecutive patients with metatarsalgia or related midfoot and forefoot symptoms against 34 age, weight and sex-matched asymptomatic controls, measured with a purpose-built electrogoniometer
- Knee EXTENDED, mean maximal ankle dorsiflexion was 4.5 degrees in patients versus 13.1 degrees in controls (p less than 0.001); knee FLEXED to 90 degrees it was 17.9 versus 22.3 degrees (p = 0.09, not significant) - the difference vanishes once the gastrocnemius is relaxed, which is the entire logic of the Silfverskiold test
- The prevalence depends entirely on where the threshold is set: at dorsiflexion of 5 degrees or less, contracture was present in 65% of patients and 24% of controls; at 10 degrees or less it was present in 88% of patients but ALSO in 44% of controls
- Combined gastrocnemius-soleus contracture, defined as 10 degrees or less with the knee flexed, was found in 29% of patients and 15% of controls
Knot of Henry Variation and the Effect on Plantar Flexion Strength
- Cadaveric specimens were loaded through the Achilles, FHL and FDL while push-off force was measured on a pressure mapping system; each tendon was then unloaded in turn to simulate its harvest, and the specimens were dissected afterwards to classify the crossover pattern
- Simulated FDL harvest reduced LESSER TOE push-off force by an average of 23% and total forefoot force by 9% - so the interconnection preserves toe flexion but does NOT preserve toe strength
- Simulated FHL harvest cost more: great toe pressure fell 31% and total forefoot pressure 22%, which is why hallux weakness is a recognised complaint after FHL transfer
- There were NO statistical differences in force reduction between the different knot of Henry crossover patterns - the variation that anatomy papers classify did not predict who lost strength
Communications Between the Tendons of Flexor Hallucis Longus and Flexor Digitorum Longus - a Cadaveric Study
- Observational cadaveric study of 36 formalin-fixed cadavers, mapping the pattern of communication between FHL and FDL and the position of the master knot of Henry
- Type I (a single slip running from FHL to FDL, the pattern that protects the lesser toes after an FDL harvest) was the commonest at 61.76%
- Type IV - NO COMMUNICATION AT ALL between the two tendons - was the second commonest pattern at 14.70%, so roughly one foot in seven has no interconnection to fall back on
- In type I the communication can be divided at the FDL end to lengthen the graft, which is the anatomical basis for gaining tendon length when the harvest is short
Type and Location of FHL Musculotendinous Junctions and Its Tendinous Interconnections with FDL - Pertinent Data for Tendon Harvesting and Transfer
- The largest series of its kind - 166 legs from 52 embalmed and 31 soft cadavers - mapping the interconnection between FHL and FDL and its position relative to the master knot of Henry
- The interconnection was NOT reliably at the knot: it lay proximal to it, at it, or distal to it, and the commonest position was DISTAL to the knot in 51.67% of legs, by a mean of about 9 to 11 mm
- A single slip running FHL to FDL (type I) accounted for 82.93%, and a previously undescribed type was found in 8.53% where part of the FHL tendon fused with FDL while the remainder continued to the hallux
- A low-lying lateral FHL muscle belly was present in 66.13% of legs, extending a mean 13.10 mm beyond the level at which the tendon crosses the distal tibia