The Vector Corrector of the Sole
- Two heads from the plantar calcaneus: a larger MEDIAL head from the medial concave surface of the calcaneus below the groove for flexor hallucis longus, and a flatter LATERAL head from the lateral border of the plantar calcaneal surface just anterior to the lateral process of the tuberosity and from the long plantar ligament.
- It inserts into the POSTEROLATERAL MARGIN of the flexor digitorum longus tendon in the second layer - it has no bony distal attachment and no attachment to any toe.
- Its function is VECTOR CORRECTION: flexor digitorum longus enters the sole obliquely from postero-medial around the sustentaculum tali, so its unaided pull would flex the lesser toes with medial deviation. Quadratus plantae pulls the tendon laterally and aligns the pull with the toe axes.
- Innervated by the LATERAL plantar nerve (S2, S3), typically by a branch given off proximally, deep in the tarsal tunnel region - which is why a proximal lateral plantar nerve lesion denervates it early.
- Its medial caudal margin, with the deep fascia of abductor hallucis, forms the fibro-muscular tunnel through which the FIRST BRANCH OF THE LATERAL PLANTAR NERVE (Baxter nerve) descends - the commonest compression point in Baxter neuropathy.
- “The only muscle in the body whose sole insertion is into another muscle's tendon.
- “It is also an ANKLE-INDEPENDENT flexor: because it arises from the calcaneus rather than the leg, it can flex the toes when flexor digitorum longus is slackened by ankle plantarflexion.
- “It lies in the CALCANEAL COMPARTMENT - the compartment implicated in compartment syndrome after calcaneal fracture, and the reason a missed calcaneal compartment syndrome ends in fixed claw toes.
- “Any operation that decompresses the Baxter nerve MUST release the medial caudal margin of the quadratus plantae fascia, not just the abductor hallucis fascia.
Overview
Quadratus plantae, also called flexor accessorius, is a flat quadrilateral muscle of the second plantar layer. That is the layer of the long flexor tendons, flexor digitorum longus and flexor hallucis longus, and of the muscles that hang off them: quadratus plantae behind and the lumbricals in front.
Its unique insertion. It arises by two heads from the plantar surface of the calcaneus and inserts into the tendon of another muscle, the posterolateral margin of flexor digitorum longus. No other muscle in the body inserts solely into another muscle's tendon in this way.
What it is for. It has no bony distal attachment, no attachment to any toe and no independent action on any joint. It exists to redirect the line of pull of flexor digitorum longus and to give the long flexor a second, ankle-independent motor, an anatomical correction for a design compromise in the way the long flexor enters the foot. How far that account has actually been measured is taken up under Action and Biomechanics.
Attachments, Innervation and Relations
Origin: Two Heads
Medial head. The larger, thicker and more muscular head arises from the medial concave surface of the calcaneus, immediately plantar to the groove for the flexor hallucis longus tendon and below the sustentaculum tali. It lies deep in the hindfoot close to the medial calcaneal wall, intimately related to the tarsal tunnel contents above it.
Lateral head. Flatter and more tendinous, it arises from the lateral border of the plantar surface of the calcaneus, immediately anterior to the lateral process of the calcaneal tuberosity, and from the long plantar ligament, whose fibres blend with the origin. The long plantar ligament separates the two heads proximally, and they converge distally into a flat quadrilateral belly.
Insertion
The muscle inserts into the posterolateral margin and deep surface of the flexor digitorum longus tendon in the mid-sole, at about the level where that tendon divides into its four digital slips. Some fibres extend onto the individual slips, most consistently to the second, third and fourth toe tendons; contributions to the fifth are inconstant.
No bony insertion. There is no attachment to any bone, phalanx or joint capsule. This is unique and highly examinable.
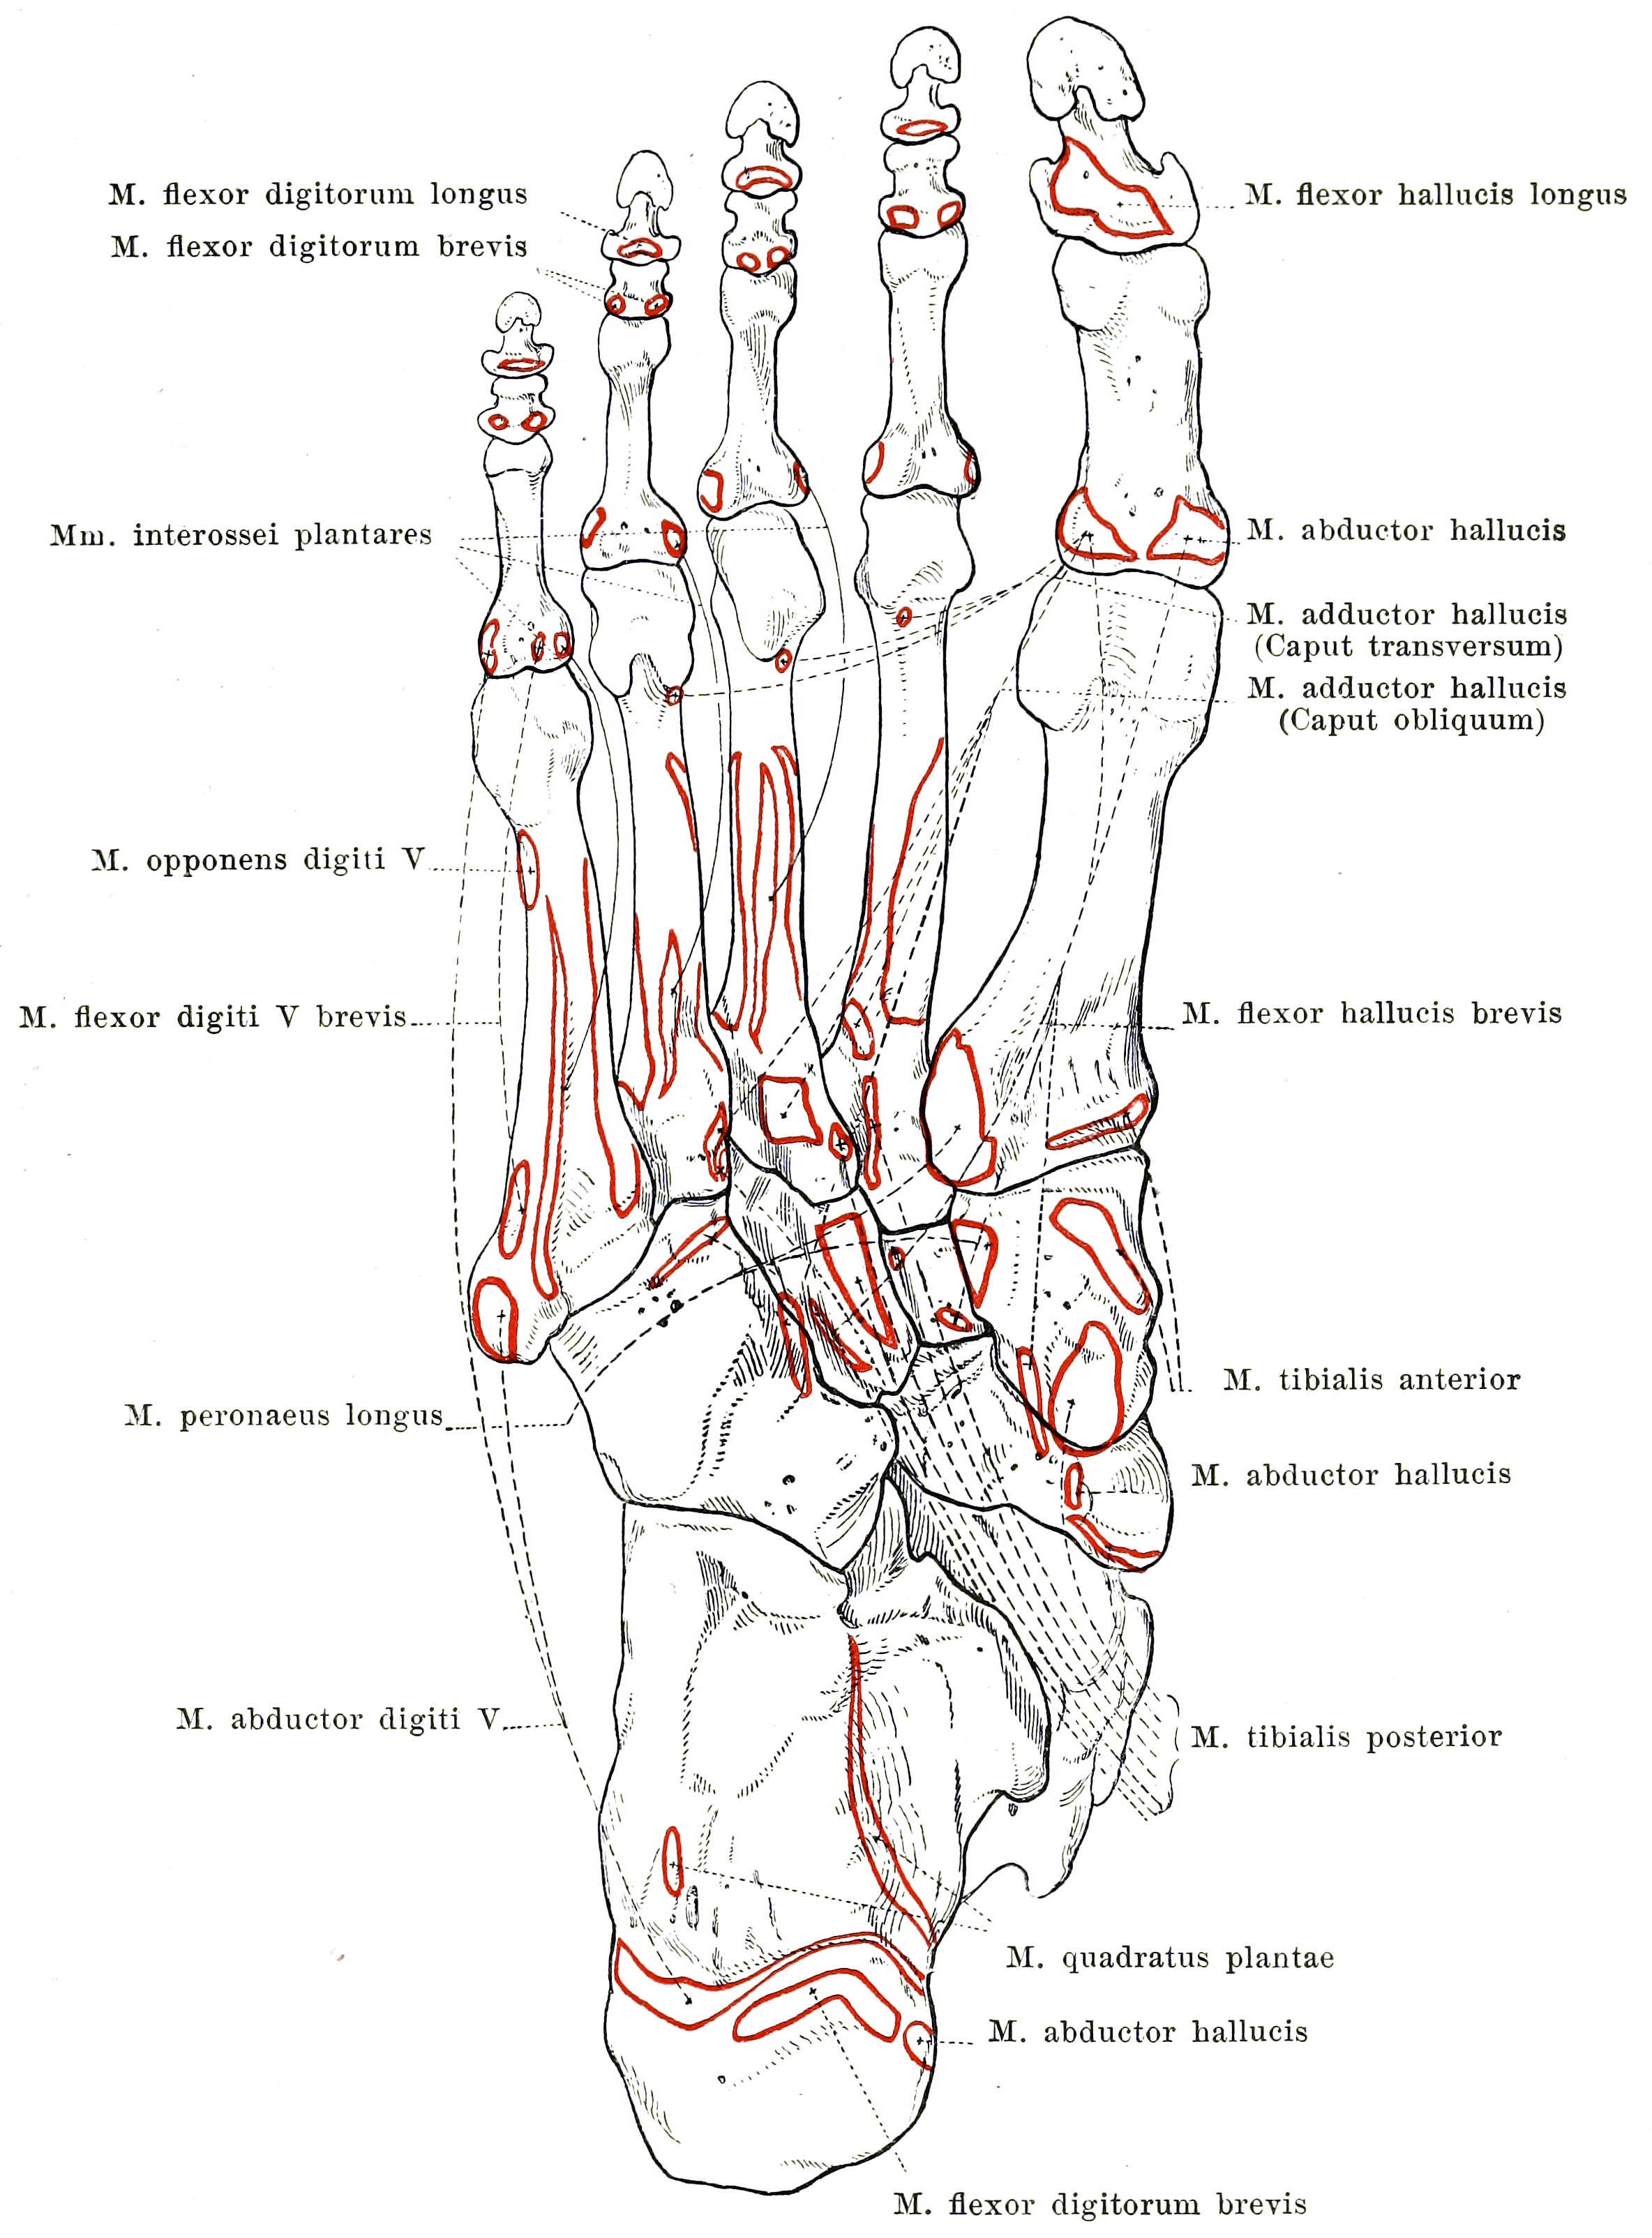
Variations
- Absence of the lateral head is the commonest variation, described in a meaningful minority of feet.
- Complete absence of the muscle is reported but rare. Where it occurs, the digital slips of flexor digitorum longus tend to be more directly aligned, and accessory slips from flexor hallucis longus at the knot of Henry are more prominent.
- Additional slips to the fifth toe tendon, or fusion with the flexor digitorum brevis origin, are recognised.
- Accessory muscles in the same region, most notably an accessory flexor digitorum longus, can occupy the calcaneal compartment; what they cause is set out under Clinical Relevance.
Action and Biomechanics
Why the Muscle Exists
This is the concept the whole page hangs on, and the one an examiner will ask.
The oblique pull. Flexor digitorum longus arises in the deep posterior compartment of the leg and enters the foot behind the medial malleolus, curving forward around the sustentaculum tali to reach the sole. It therefore approaches the lesser toes from postero-medial, running obliquely across the sole from medial-posterior to lateral-anterior. Unaided, its contraction would flex the lesser toes with a component of medial deviation, curling them toward the hallux rather than flexing them straight down.
The correction. Quadratus plantae arises from the calcaneus laterally and posteriorly and inserts on the lateral margin of the long flexor tendon, so its pull is posterolateral. Contracting synchronously with the long flexor, it rotates the resultant vector laterally into alignment with the axes of the toes, its principal and defining action. Flexor digitorum longus supplies the force; quadratus plantae supplies the direction. Without it, toe flexion becomes toe curling with adduction.
Ankle independence. Flexor digitorum longus is a two-joint, in fact multi-joint, muscle crossing the ankle. As the ankle plantarflexes in terminal stance its muscle-tendon unit shortens passively, moving down its length-tension curve and losing active force, at precisely the point in the gait cycle where toe purchase matters most. Quadratus plantae arises from the calcaneus, distal to the ankle, so it is unaffected by ankle position and can continue to load the long flexor tendon.
Hence flexor accessorius. The old name describes exactly that: an accessory motor for the long flexor tendon, allowing effective toe purchase in terminal stance while the ankle is plantarflexing. It is the answer to give when asked why a muscle would insert into another muscle's tendon, because it converts a leg muscle into a foot muscle for the part of the cycle when the leg muscle is least effective.
During the windlass. A subtler role: as the metatarsophalangeal joints dorsiflex in terminal stance and the plantar aponeurosis winds around the metatarsal heads, quadratus plantae helps keep the long flexor tendon aligned in its distal course rather than bowstringing medially.
At the joints. It has no direct action on any joint. It assists flexion of the lesser toes at the metatarsophalangeal, proximal interphalangeal and distal interphalangeal joints only through the flexor digitorum longus tendon, and it contributes indirectly to the intrinsic sling supporting the longitudinal arch by keeping the long flexor efficient throughout terminal stance.
A rope-tensioner. The hand solves the oblique-pull problem for flexor digitorum profundus largely through the fibrous digital sheaths and the lumbricals. The foot adds a dedicated proximal vector-correcting muscle, its answer to the lumbricals of the hand plus a rerouting pulley. Where a synergist would work in parallel on the same bone, quadratus plantae is a rope-tensioner working on the rope itself.
How settled this is. The vector-correction account is derived from the muscle's geometry and from its old name; it has never been measured directly. Sooriakumaran's review asks whether the muscle is simply an accessory flexor that brings the line of pull into the long axis, as its name would suggest, and answers that the electromyographic evidence points elsewhere: quadratus plantae behaves as a primary toe flexor, preferentially recruited ahead of flexor digitorum longus in voluntary flexion, and it appears to resist extension of the toes during stance, which stabilises the foot.
Two anatomical facts cut the same way. The lateral head is absent in about a third of feet (31 of 100 in Pretterklieber's series) and the whole muscle is single-headed in 34 per cent, which is hard to reconcile with an indispensable vector-correcting role. In vivo, the two heads act on different toes, the medial on the second toe alone and the lateral on all four. Teach the vector explanation as the anatomical rationale it is, and say plainly that the recorded behaviour is that of an accessory flexor and a stance-phase stabiliser.
When It Fails
- Effect on quadratus plantae
- Denervated early (the branch arises proximally), with loss of the lateral vector-correcting pull
- Consequence
- Lesser toes flex with medial deviation, contributing to curling and adduction and, with global intrinsic loss, to claw toes; a proximal tibial or tarsal tunnel lesion adds global intrinsic loss and sensory change
- Effect on quadratus plantae
- May be spared
- Consequence
- Interossei and lateral intrinsics affected while vector correction is preserved
- Effect on quadratus plantae
- NOT denervated - it is the compressing wall, not the victim
- Consequence
- Heel pain and abductor digiti minimi wasting with no sensory loss
- Effect on quadratus plantae
- Ischaemic necrosis, then fibrosis and contracture within a tight compartment
- Consequence
- FIXED claw toes with a rigid, contracted sole, chronic neuropathic pain, and an insensate sole from associated nerve ischaemia
- Effect on quadratus plantae
- Anatomical variation
- Consequence
- Usually asymptomatic; the digital slips of FDL tend to be more directly aligned
- Effect on quadratus plantae
- Loses its distal attachment and becomes functionless
- Consequence
- A reason to harvest FDL distally
- Effect on quadratus plantae
- Denervated with all the lateral plantar nerve intrinsics
- Consequence
- Claw toes from unopposed long extensor and long flexor pull; metatarsal head plantar prominence, callus, ulceration
Lesser Toe Balance and Why the Foot Claws
The lesser toe is governed by a four-way balance, and quadratus plantae is the vector regulator within it.
- Extensor digitorum longus extends the metatarsophalangeal joint through the extensor sling.
- Flexor digitorum longus flexes the distal interphalangeal joint and, with quadratus plantae correcting its direction, contributes to axial flexion at all three joints.
- Flexor digitorum brevis flexes the proximal interphalangeal joint.
- Interossei and lumbricals flex the metatarsophalangeal joint, and are the only intrinsic counterweight to the long extensor, because in the foot, unlike the hand, they have no extensor expansion into the dorsal hood.
How the balance fails. Loss of the intrinsics gives a claw toe: metatarsophalangeal hyperextension from unopposed extensor digitorum longus, with flexion at both interphalangeal joints from the unopposed long and short flexors. Loss of the vector correction superimposes medial deviation and curling, which is part of why the neuropathic foot shows adducted, overriding lesser toes rather than simple sagittal clawing.
Why the foot ulcerates. Once the metatarsophalangeal joint hyperextends, the plantar fat pad migrates distally and the metatarsal head becomes prominent plantarward. The neuropathic foot then ulcerates under the metatarsal head and at the toe tip.
- Mallet toe - isolated DIP flexion, a flexor digitorum longus problem
- Claw toe - MTP extension with both IP joints flexed, from unopposed long extensor and long flexor after intrinsic loss
- Medial deviation and curling - loss of the quadratus plantae vector correction
- Hammer toe - PIP flexion with a neutral or extended MTP, flexor digitorum brevis dominant
- Crossover toe - plantar plate attenuation with intrinsic imbalance at a single ray
- Curly toe of childhood - tight long AND short flexors, treated by flexor tenotomy
Synergists and Antagonists
- Structure
- Flexor digitorum longus
- Nerve
- Tibial (L5, S1, S2)
- Comment
- Supplies the force; quadratus plantae supplies the direction
- Structure
- The four lumbricals
- Nerve
- First from medial plantar, remainder lateral plantar
- Comment
- Arise from the FDL digital slips just distal to the QP insertion
- Structure
- Flexor digitorum brevis
- Nerve
- Medial plantar (S1, S2)
- Comment
- First layer, superficial to quadratus plantae
- Structure
- Extensor digitorum longus and brevis
- Nerve
- Deep peroneal (L5, S1)
- Comment
- Unopposed at the MTP joint after intrinsic loss - the claw toe mechanism
- Structure
- None
- Nerve
- Not applicable
- Comment
- No other muscle corrects the FDL vector - which is why its loss is not compensated
Surface Anatomy and Examination
Not palpable. Quadratus plantae lies in the calcaneal compartment, deep to flexor digitorum brevis, the plantar aponeurosis and the heel pad, and cannot be felt. What can be localised is the interval it forms with abductor hallucis. Deep tenderness there, with the ankle in neutral and in the absence of tenderness on the tuberosity itself, is the physical sign of Baxter nerve entrapment.
Beside the medial head. The medial head origin lies immediately plantar to the sustentaculum tali, with the flexor hallucis longus tendon in its groove above it. Pain and crepitus on hallux motion behind the medial malleolus localise to that tendon rather than to the muscle.
There is no isolated test. With no bony insertion and no independent joint action, no manoeuvre can isolate the muscle: nothing changes at any joint when quadratus plantae alone contracts, only the direction in which the long flexor moves the toes. Saying that clearly is a better answer than inventing a test. What can be assessed is the consequence of losing it, the direction of lesser toe flexion, and the conditions in which it is implicated.
- How to perform
- With the ankle in neutral and the foot unloaded, ask the patient to curl the lesser toes and observe the plane of movement, comparing sides
- Positive finding
- Toes flex with medial deviation and adduction rather than straight plantarward
- What it means
- Loss of the quadratus plantae vector correction - suggests a proximal lateral plantar or tibial nerve lesion, in the context of other intrinsic signs
- False positives / pitfalls
- Established fixed deformity, prior surgery or a curly toe deformity gives the same appearance without denervation; many people flex the toes poorly
- How to perform
- Press deeply about 1 cm distal and 1 cm medial to the medial calcaneal tuberosity
- Positive finding
- Well-localised deep tenderness, often with pain radiating laterally across the heel
- What it means
- Baxter nerve entrapment in the tunnel whose lateral wall is the quadratus plantae fascia
- False positives / pitfalls
- Overlaps with the fascial origin; there is NO sensory loss to confirm it - correlate with abductor digiti minimi bulk
- How to perform
- Inspect and palpate the muscle along the lateral border of the foot and ask for fifth toe abduction, comparing sides
- Positive finding
- Wasting or weakness
- What it means
- Denervation from Baxter nerve compression - the only muscle that nerve exclusively supplies
- False positives / pitfalls
- Many normal people cannot voluntarily abduct the fifth toe; rely on comparative bulk and MRI
- How to perform
- Assess for a tense swollen sole, pain out of proportion to injury, and pain on PASSIVE toe extension; measure compartment pressures if suspected
- Positive finding
- Severe pain on passive toe extension with a tense sole after a calcaneal or crush injury
- What it means
- Compartment syndrome involving the calcaneal compartment containing quadratus plantae - a surgical emergency
- False positives / pitfalls
- Analgesia and regional block mask the pain; an insensate neuropathic foot removes the key symptom; pulses and capillary refill are preserved until very late
- How to perform
- Look for claw toes, plantar callus under the metatarsal heads, hollowing of the intermetatarsal spaces, and inability to hold a sheet of paper under the toes
- Positive finding
- Clawing, wasting, callus and loss of paper grip
- What it means
- Global intrinsic denervation - diabetic or hereditary neuropathy; quadratus plantae is denervated as part of the pattern
- False positives / pitfalls
- Age-related intrinsic weakness; footwear-related toe deformity without neuropathy
- How to perform
- Stand the patient with the lateral border of the foot on a block and the first ray hanging free
- Positive finding
- Hindfoot varus corrects on the block
- What it means
- A flexible, forefoot-driven cavus - relevant because the intrinsic-minus foot of Charcot-Marie-Tooth is the classic setting of quadratus plantae denervation
- False positives / pitfalls
- A rigid hindfoot will not correct and needs a calcaneal osteotomy - do not misread a fixed deformity as flexible
Imaging
- Radiographs are of limited direct use for the muscle, but are needed for the calcaneus, hindfoot alignment and cavus assessment.
- MRI is the investigation that shows the muscle. Look for fatty atrophy of quadratus plantae in chronic proximal tibial or lateral plantar nerve lesions, denervation oedema in acute lesions, and selective fatty atrophy of abductor digiti minimi in Baxter neuropathy. It also shows accessory muscles occupying the calcaneal compartment and any space-occupying lesion in the tarsal tunnel.
- Ultrasound can demonstrate the interval between abductor hallucis and quadratus plantae and guide a diagnostic injection into it, a useful confirmatory step in suspected Baxter neuropathy.
- Electrodiagnostics may support a proximal tibial or lateral plantar nerve lesion, but they are technically difficult for short distal motor branches and a negative study does not exclude the diagnosis.
Complications
- Mechanism
- Release of the abductor hallucis fascia only, leaving the quadratus plantae fascial margin intact
- Avoidance
- Release BOTH walls of the tunnel and follow the nerve through both its vertical and horizontal segments
- Mechanism
- Missed calcaneal compartment syndrome with fibrosis of quadratus plantae and the deep intrinsics
- Avoidance
- Clinical vigilance, passive toe extension pain, compartment pressures, urgent medial fasciotomy
- Mechanism
- Division of the medial calcaneal sensory branches
- Avoidance
- Identify and preserve them; place the incision dorsal to weight-bearing skin; avoid transverse plantar heel incisions
- Mechanism
- Dissection in the plane superficial to quadratus plantae, particularly through a plantar incision
- Avoidance
- Use a medial approach; develop the plane under direct vision; expect the bundle crossing obliquely
- Mechanism
- Injury to the proximally arising branch during deep tarsal tunnel dissection
- Avoidance
- Identify the lateral plantar nerve early and preserve its proximal branches
- Mechanism
- FDL divided in the mid-sole proximal to the quadratus plantae insertion
- Avoidance
- Harvest FDL distally at the toe, beyond the chiasma
- Mechanism
- Medial hindfoot dissection at the level of the sustentaculum
- Avoidance
- Subperiosteal dissection with the tendon identified; avoid blind retractor placement
- Mechanism
- Failure to address the metatarsophalangeal joint, plantar plate or a long metatarsal
- Avoidance
- Assess and treat the whole ray, including plantar plate insufficiency and metatarsal length
- Mechanism
- Operating on weight-bearing plantar skin, particularly in the neuropathic or ischaemic foot
- Avoidance
- Medial and dorsal approaches; assess perfusion; rigorous offloading; percutaneous techniques where they suffice
- Mechanism
- The diagnosis was neural, not fascial
- Avoidance
- Localise tenderness precisely before operating; look for abductor digiti minimi atrophy on MRI
Clinical Relevance
Baxter Neuropathy: Quadratus Plantae as the Compressing Wall
The first compression point. The first branch of the lateral plantar nerve (inferior calcaneal nerve, Baxter nerve) arises from the lateral plantar nerve within about 1 cm of the tibial nerve bifurcation. Its descending, vertical segment runs between the deep fascia of abductor hallucis medially and the medial caudal margin of quadratus plantae laterally, the first and commonest compression point.
The second compression point. The nerve then turns laterally, running superficial to quadratus plantae and along the deep surface of flexor digitorum brevis, immediately anterior to the medial calcaneal tuberosity, to reach abductor digiti minimi. Here a heel spur or a thickened plantar fascial origin can compress it.
What it supplies. It supplies the periosteum of the medial calcaneal tuberosity, the long plantar ligament, twigs to flexor digitorum brevis, and motor supply to abductor digiti minimi. Its cutaneous contribution is negligible, which is why the neuropathy produces no sensory loss.
Presentation. Chronic plantar heel pain, maximal just distal and medial to the tuberosity rather than on it, is often burning and sometimes radiates laterally across the heel; there is sometimes wasting or weakness of abductor digiti minimi. It accounts for a meaningful minority of chronic recalcitrant plantar heel pain, commonly quoted as up to around a fifth.
The surgical point. A decompression that releases only the abductor hallucis deep fascia leaves the lateral wall of the tunnel, the quadratus plantae fascial margin, intact and the nerve still tethered. Both walls must be released.
Lesser Toe Deformity and Flexor Surgery
Quadratus plantae is not usually the cause of a lesser toe deformity, but it is central to understanding the tendon balance and to executing the operations.
Curly toe. In childhood this is a flexion, adduction and varus rotation deformity of a lesser toe, most often the third, fourth or fifth, attributed to a tight or abnormally inserting long and short flexor complex. It illustrates the adducting effect of an uncorrected oblique long-flexor pull. The recognised treatment is open flexor tenotomy of both the long and short flexors; Hamer's double-blind randomised trial is conventionally cited as showing that it performs as well as the more extensive flexor-to-extensor transfer, a result quoted from convention rather than from an indexed abstract.
Flexible claw and hammer toe. These are treated by a flexor-to-extensor (Girdlestone-Taylor) transfer of flexor digitorum longus. The technique, and the one point in it that involves quadratus plantae, are under Surgical Relevance.
Diabetic claw toe with an apical ulcer. A simple percutaneous flexor tenotomy treats it very effectively, offloading the toe tip and letting the ulcer heal without any bony surgery.
Fixed hammer or claw toe. This needs a proximal interphalangeal resection arthroplasty or arthrodesis, with metatarsophalangeal release and sometimes a shortening metatarsal osteotomy.
The Intrinsic-Minus Foot
Charcot-Marie-Tooth disease. Hereditary motor and sensory neuropathy is the classic setting: intrinsic wasting, claw toes, a plantarflexed first ray, forefoot-driven cavus and hindfoot varus. Quadratus plantae is denervated with the other lateral plantar nerve intrinsics, and the medial deviation of the lesser toes reflects loss of vector correction as well as clawing.
Diabetic neuropathy. Distal symmetrical polyneuropathy produces the same intrinsic-minus pattern. Fatty atrophy of the intrinsic foot muscles on MRI is one of the earliest structural markers of diabetic neuropathy, appearing before deformity becomes clinically obvious. The harm is mechanical, through the hyperextension and fat pad migration set out under Action and Biomechanics.
Management is protective. It comprises neuropathy screening, footwear and total-contact insoles, callus care, flexor tenotomy for apical ulcers, and reconstruction for fixed deformity.
Calcaneal Compartment Syndrome
The compartment. The calcaneal compartment contains quadratus plantae, together with the lateral plantar neurovascular bundle, and communicates with the deep posterior compartment of the leg. Its relatively poor collateral supply and tight fascial envelope contribute to its vulnerability in compartment syndrome.
The compartments of the foot. The common teaching model groups them as follows.
- Medial: abductor hallucis, flexor hallucis brevis
- Central: flexor digitorum brevis, the flexor digitorum longus tendons, the lumbricals, adductor hallucis
- Lateral: abductor digiti minimi, flexor digiti minimi brevis
- Interosseous: the interossei, in four separate spaces
- Calcaneal: quadratus plantae
Manoli and Weber's cadaveric study described nine compartments: medial, superficial, lateral, adductor, four separate interossei and calcaneal.
When to suspect it. After a calcaneal fracture, a Lisfranc or forefoot crush, or another high-energy foot injury, and after prolonged pressure or reperfusion.
Diagnosis. It is clinical: a tense, swollen sole, pain out of proportion, and pain on passive toe extension, with pulses and capillary refill preserved until very late. Compartment pressures confirm it, and the calcaneal compartment must be measured specifically, as it can be elevated when others are not.
Treatment. Urgent decompression through the medial (Henry) approach, which decompresses the medial, central (superficial and deep) and calcaneal compartments through one incision, with dorsal incisions for the interosseous compartments if required. The technique is under Surgical Relevance.
If it is missed. The sequel is fibrosis of quadratus plantae and the deep intrinsics with fixed claw toes, a rigid contracted sole, chronic neuropathic pain and an insensate plantar surface. It is one of the most disabling outcomes in foot trauma and there is no good reconstruction.
Other Conditions in the Region
- Tarsal tunnel syndrome. The branch to quadratus plantae and the whole lateral plantar nerve are in the territory; look on MRI for a space-occupying lesion (ganglion, varicosity, accessory muscle, tumour).
- Accessory muscles in the calcaneal compartment, most notably an accessory flexor digitorum longus, can compress the tarsal tunnel contents or the Baxter nerve and present as heel or medial ankle pain with a soft mass.
- Plantar space infection tracks along the plane superficial to quadratus plantae and can reach the calcaneal compartment and the tarsal tunnel. Drainage requires a formal medial approach with awareness of the lateral plantar bundle.
- Flexor hallucis longus tenosynovitis occurs in the groove beneath the sustentaculum, immediately above the medial head origin, and is a differential for deep medial hindfoot pain.
Surgical Relevance
Medial Approach for Baxter Nerve Decompression
Indication. Chronic recalcitrant plantar heel pain with clinical and imaging features of first branch entrapment, after failure of a genuine non-operative programme.
Incision. An oblique medial heel incision of roughly 3 to 4 cm, running from about 2 cm distal and plantar to the tip of the medial malleolus toward the plantar-medial heel, deliberately dorsal to weight-bearing plantar skin.
- Identify and preserve the medial calcaneal sensory branches of the tibial nerve in the subcutaneous fat, typically crossing within 1 to 2 cm proximal to the medial calcaneal tuberosity. There is no safe subcutaneous plane, and a divided branch is a common cause of persistent postoperative heel pain.
- Incise the superficial fascia of abductor hallucis and retract the muscle.
- Release the deep fascia of abductor hallucis, the medial wall of the tunnel and the classic compression point.
- Release the medial caudal margin of the quadratus plantae fascia, the lateral wall. Do not omit this step; it is the commonest reason for an incomplete decompression.
- Release the medial third of the plantar aponeurosis if there is a coexisting fasciopathy, keeping strictly to the medial third to half.
- Excise an inferior heel spur only if it is demonstrably compressing the nerve at the tuberosity.
- Confirm the nerve runs free from its origin through both segments.
Afterwards. Close without tension and mobilise early. Warn the patient that neuropathic pain resolves slowly and may take months.
1. Never decompress the Baxter nerve without releasing the quadratus plantae fascial margin. Releasing only the medial wall is the commonest reason a decompression fails and the patient returns with unchanged pain.
2. Never miss a calcaneal compartment syndrome. Regional anaesthesia and a neuropathic foot both remove the warning symptom, so maintain a low threshold for measuring pressures.
Guidelines, Registries & Global Practice
Anatomical Variation Across Populations
- Absence of the lateral head is the commonest variation, described across dissection series in a meaningful minority of feet, with the medial head essentially always present.
- Complete absence of the muscle is reported but rare. Where it occurs, the digital slips of flexor digitorum longus tend to run more directly and accessory interconnections at the knot of Henry are more prominent.
- Accessory slips to the fifth toe tendon, and fusion of the origin with flexor digitorum brevis, are recognised.
- Accessory muscles in the same compartment, particularly an accessory flexor digitorum longus, are found in a small percentage of feet and are a recognised cause of tarsal tunnel or Baxter nerve compression and of a soft mass in the medial hindfoot.
- The origin of the first branch of the lateral plantar nerve varies - from the lateral plantar nerve, directly from the tibial nerve, or as multiple branches - in a meaningful proportion of feet. This variability is exactly why a decompression should release the whole interval rather than seek a single named nerve.
- Prevalence of the conditions that make this muscle relevant is driven by diabetes, hereditary neuropathy and high-energy trauma, not by population anatomy.
Side-by-Side Guidance and Practice Differences
- Position on the relevant conditions
- Foot compartment syndrome recognised as a clinical diagnosis warranting urgent medial-approach fasciotomy; Baxter neuropathy accepted as a distinct entity in recalcitrant heel pain with decompression of both tunnel walls.
- Position on the relevant conditions
- Similar approach to compartment syndrome; a generally higher threshold for operating on heel pain and greater emphasis on prolonged non-operative treatment and on gastrocnemius recession where indicated.
- Position on the relevant conditions
- Emphasises the medial (Henry) approach for decompression of the medial, central and calcaneal compartments, and awareness of the lateral plantar neurovascular bundle crossing superficial to quadratus plantae.
- Position on the relevant conditions
- Strong support for annual neuropathy screening, protective footwear and total-contact insoles, and for percutaneous flexor tenotomy as a simple effective treatment for apical toe ulceration in the intrinsic-minus foot.
Areas of Genuine Uncertainty
- Compartment pressure thresholds in the foot are less well established than in the leg, and the number and boundaries of the compartments are still debated between anatomical models. The clinical diagnosis therefore carries more weight than the number.
- Whether prophylactic fasciotomy is warranted in high-energy calcaneal or Lisfranc crush injuries with borderline findings.
- Reported prevalence of Baxter neuropathy among recalcitrant heel pain varies widely because it depends on how the diagnosis is made, and there is no accepted diagnostic gold standard.
- Whether quadratus plantae denervation contributes measurably to lesser toe deformity independently of global intrinsic loss has not been isolated experimentally in humans.
- Optimal treatment of established post-compartment-syndrome intrinsic contracture - the balance between soft-tissue release, tenotomy, arthrodesis and accommodation - has no evidence base beyond small series.
High- versus Limited-Resource Practice
- Well-resourced settings: MRI to demonstrate intrinsic and abductor digiti minimi atrophy and to exclude tarsal tunnel lesions, ultrasound-guided diagnostic injection into the abductor hallucis-quadratus plantae interval, compartment pressure monitoring, and access to negative pressure dressings after fasciotomy.
- Limited-resource settings: the two things that matter most cost nothing. Foot compartment syndrome is diagnosed by examination, and a medial Henry fasciotomy needs only a scalpel and knowledge of the anatomy. Likewise, percutaneous flexor tenotomy for a diabetic apical toe ulcer is a local-anaesthetic, minimal-equipment procedure with a high yield, and protective footwear plus callus care prevents far more disability than any operation.
- Everywhere: in the neuropathic foot, the absence of pain removes the warning sign for both compartment syndrome and ulceration, so structured examination and offloading substitute for symptoms.
MCQ Practice Points
Q: Where does quadratus plantae insert? A: Into the posterolateral margin of the tendon of FLEXOR DIGITORUM LONGUS. It has no bony distal attachment and no attachment to any toe - the only muscle whose sole insertion is into another muscle's tendon.
Q: What is the principal function of quadratus plantae? A: Correction of the oblique line of pull of flexor digitorum longus. FDL enters the sole obliquely around the sustentaculum tali, so unaided it would flex the lesser toes with medial deviation; quadratus plantae rotates the vector laterally into line with the toe axes.
Q: Why is quadratus plantae also called flexor accessorius? A: Because it arises from the CALCANEUS, distal to the ankle, so it can generate toe flexion force independent of ankle position - including when ankle plantarflexion slackens flexor digitorum longus in terminal stance.
Q: What is the nerve supply of quadratus plantae? A: The LATERAL plantar nerve (S2, S3), by a branch given off proximally near the tarsal tunnel - which is why a proximal lesion denervates it early while a distal lateral plantar nerve lesion may spare it.
Q: In which plantar layer does quadratus plantae lie? A: The SECOND layer, with the lumbricals and the tendons of flexor digitorum longus and flexor hallucis longus - deep to flexor digitorum brevis.
Q: What forms the lateral wall of the tunnel in which the first branch of the lateral plantar nerve is entrapped? A: The medial caudal margin of QUADRATUS PLANTAE and its fascia. The medial wall is the deep fascia of abductor hallucis. Both must be released at decompression.
Q: In which compartment of the foot does quadratus plantae lie? A: The CALCANEAL compartment, which also contains the lateral plantar neurovascular bundle and communicates with the deep posterior compartment of the leg.
Q: Describe the two origins of quadratus plantae. A: A larger, thicker MEDIAL head from the medial concave surface of the calcaneus just plantar to the groove for flexor hallucis longus, and a flatter LATERAL head from the lateral border of the plantar calcaneal surface just anterior to the lateral process of the tuberosity, and from the long plantar ligament.
Q: What is the commonest anatomical variation of quadratus plantae? A: Absence of the lateral head, described in a meaningful minority of feet. Complete absence of the muscle is reported but rare.
Q: Why must flexor digitorum longus be harvested distally for a Girdlestone-Taylor transfer? A: Because dividing it in the mid-sole proximal to the quadratus plantae insertion leaves quadratus plantae without a distal attachment and functionless. Harvest distal to the chiasma at the toe.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are shown a dissection of the second layer of the sole. The examiner points at quadratus plantae and asks: what is it, where does it attach, and why would a muscle insert into another muscle's tendon?”
“A 51-year-old woman had a plantar fascia release and a decompression of the first branch of the lateral plantar nerve nine months ago for chronic heel pain. Her pain is completely unchanged. The operation note records release of the abductor hallucis fascia and division of the medial half of the plantar fascia. What has probably happened?”
“A 33-year-old man had a pallet dropped on his foot six hours ago. Radiographs show an undisplaced calcaneal fracture. The sole is tense and swollen, he is requiring escalating opioid analgesia, and passive extension of the toes is exquisitely painful. Pedal pulses are palpable and capillary refill is normal. What is your diagnosis and what do you do?”
Anatomy
- LAYER 2 (with lumbricals and the long flexor tendons)
- Medial head: medial concave calcaneus, plantar to the FHL groove
- Lateral head: lateral plantar calcaneus anterior to the lateral process, plus long plantar ligament
- Insertion: POSTEROLATERAL margin of the FDL tendon - no bony insertion
- Commonest variation: absence of the lateral head
Function
- Corrects the OBLIQUE pull of flexor digitorum longus
- FDL supplies the force, quadratus plantae supplies the direction
- Without it, lesser toes flex with MEDIAL deviation
- Flexor accessorius: ankle-INDEPENDENT toe flexion (origin on the calcaneus)
- No isolated clinical test - no independent joint action
Neurovascular
- Nerve: LATERAL plantar nerve (S2, S3)
- Branch given off PROXIMALLY near the tarsal tunnel
- Lateral plantar nerve and artery cross SUPERFICIAL to the muscle
- Deep to flexor digitorum brevis - the plane of the Baxter nerve
- Not used as a flap - use instep or abductor hallucis flaps for the heel
Baxter Nerve
- First branch of the lateral plantar nerve; arises within 1 cm of the bifurcation
- Tunnel: abductor hallucis DEEP fascia medially, QUADRATUS PLANTAE margin laterally
- Then laterally, superficial to QP and deep to FDB, to abductor digiti minimi
- NO sensory loss; MRI shows selective abductor digiti minimi atrophy
- Decompression MUST release both tunnel walls
Calcaneal Compartment
- Contains quadratus plantae plus the lateral plantar bundle
- Communicates with the deep posterior compartment of the leg
- Clinical: tense sole, pain out of proportion, pain on PASSIVE toe extension
- Pulses normal until very late - do not be reassured
- Medial Henry approach decompresses medial, central and calcaneal
Lesser Toe Balance
- Mallet toe - DIP, flexor digitorum longus
- Hammer toe - PIP, flexor digitorum brevis
- Claw toe - MTP extension plus both IP flexed, intrinsic-minus
- Foot interossei have NO extensor expansion - hence claw
- Girdlestone-Taylor uses FDL harvested DISTAL to the QP insertion
Evidence Base
Treatment of Chronic Heel Pain by Surgical Release of the First Branch of the Lateral Plantar Nerve
- 69 heels in 53 patients with chronic heel pain underwent surgical release of the first branch of the lateral plantar nerve
- Mean duration of symptoms was 23 months (range 6 months to 8 years); no patient had less than 6 months of conservative treatment first, and the mean was 14 months
- Before surgery, 83% had taken non-steroidal anti-inflammatory drugs, 91% of heels had used heel cups or orthoses, and 86% had received one or more steroid injections
- 34 heels had developed pain initially during a sports activity
- Postoperatively 61 heels (89%) had an excellent or good result and 57 heels (83%) had complete resolution of pain
Heel Pain - Operative Results
- 34 operative cases in 26 patients with recalcitrant heel pain over 6 years
- The procedure was an ISOLATED NEUROLYSIS of the mixed nerve supplying the abductor digiti quinti as it passes beneath the abductor hallucis muscle and beneath the medial ridge of the calcaneus
- The DEEP FASCIA OF ABDUCTOR HALLUCIS was released routinely
- An impinging heel spur or a tight plantar fascia was partially removed or released ONLY IF it was causing entrapment of the nerve
- Described the biomechanical pathogenesis of heel pain in relation to pes planus and pes cavus predisposing to an entrapment neuropathy, and clarified the anatomy of the heel in relation to the nerve
Surgery for Curly Toe Deformity - a Double-Blind Randomised Prospective Trial
- NOTE - no abstract is indexed for this paper; the following is bounded by its title and MeSH indexing (toes - abnormalities, surgery) plus conventional attribution
- A double-blind, randomised, prospective trial of surgery for curly toe deformity - a high level of evidence for a paediatric forefoot procedure
- It is conventionally cited as showing that simple flexor tenotomy is as effective as the more extensive flexor-to-extensor transfer
- That equivalence conclusion is the widely quoted result but is not verifiable from the indexed record alone
Intrinsic Muscle Atrophy and Toe Deformity in the Diabetic Neuropathic Foot
- MRI of the metatarsal region in 8 patients with diabetic polyneuropathy and 8 age- and sex-matched non-diabetic controls, with toe joint angles measured by three-dimensional digitiser
- Remarkable atrophy of ALL the intrinsic muscles in the neuropathic subjects, with a 73% decrease in muscle cross-sectional area distally
- Muscle comprised only 8.3% of total foot cross-sectional area in neuropathic subjects versus 30.8% in controls
- IMPORTANT NEGATIVE - there were NO significant differences between groups in the metatarsophalangeal or interphalangeal joint angles of the second ray, and clawing or hammering was present in only 2 of the 8 neuropathic subjects
- The authors concluded that intrinsic muscle atrophy does NOT necessarily imply toe deformity, and that the consequences of MOTOR neuropathy in the diabetic foot are profound and under-emphasised beside sensory neuropathy
Fasciotomy of the Foot - An Anatomical Study with Special Reference to Release of the Calcaneal Compartment
- Prompted by three patients who developed clawing of the lesser toes as a LATE SEQUELA of calcaneal fracture, hypothesised to follow contracture after an occult compartment syndrome of the foot
- 17 unembalmed adult lower limb specimens had their compartments injected with dyed gelatin, were frozen, then sectioned transversely or sagittally to map the distribution
- NINE compartments were identified: medial, superficial, lateral, ADDUCTOR, FOUR SEPARATE INTEROSSEI, and CALCANEAL
- The calcaneal compartment was established as a discrete compartment containing quadratus plantae
- The contents and boundaries of each compartment were mapped, providing the anatomical basis for selective decompression
Why Does Man Have a Quadratus Plantae? A Review of Its Comparative Anatomy
- Poses the question this page's name assumes the answer to: is quadratus plantae 'simply an accessory flexor that brings the line of pull of flexor digitorum longus in line with the long axis of the foot, as its name would suggest?'
- Cites electromyographic evidence that it instead acts as a PRIMARY TOE FLEXOR in voluntary movements, being PREFERENTIALLY RECRUITED OVER flexor digitorum longus
- Electromyography also suggests it functions to RESIST EXTENSION of the toes during the stance phase, increasing the stability of the foot
- Comparative anatomy suggests it is also an intrinsic EVERTOR of the foot - a proposition the authors state human electromyography has yet to confirm
- Phylogenetically the muscle is getting BULKIER in man, implying increasing rather than vestigial significance in human locomotion
- Notes its clinical relevance in heel pain, claw toe deformity and diabetic polyneuropathy
Morphological Characteristics and Variations of the Human Quadratus Plantae Muscle
- Both feet of 50 formalin-fixed donors (25 men, 25 women) - 100 feet - dissected specifically to settle the muscle's origin and insertion, which the author notes had never been precisely specified
- The muscle had ONE head in 34 per cent, TWO in 57 per cent and THREE in 9 per cent; the three-headed form occurred only in men
- THE LATERAL HEAD WAS ABSENT IN 31 OF 100 FEET; the medial head was absent in only one
- The medial head arose from the medial calcaneal surface in 100 per cent, the long plantar ligament in 93 per cent and the plantar calcaneocuboid ligament in 80 per cent; the lateral head from the long plantar ligament in 90 per cent and the lateral calcaneal tuberosity in 64 per cent
- Insertion was ALWAYS a mixture of at least two of muscular (84 per cent), tendinous (89 per cent) and aponeurotic (45 per cent) - so no single insertion description is correct
- Flexor digitorum accessorius longus and peroneocalcaneus internus were present in 12 per cent of individuals and 20 per cent of men
- The author concludes the muscle can be classified by head number but that NO classification is possible for its origins or its insertion
Activities of the Medial and Lateral Heads of Quadratus Plantae in Toe Flexion, Measured by Real-Time Tissue Elastography
- Thirteen healthy subjects performed maximal voluntary flexion of each lesser toe against a hand-held dynamometer with external belt fixation, with muscle stiffness measured by ultrasound real-time tissue elastography
- The MEDIAL head stiffened significantly only for SECOND-toe flexion (strain ratio 0.10 plus or minus 0.11 against 0.34 plus or minus 0.33 at rest)
- The LATERAL head stiffened significantly for flexion of the second, third, fourth AND fifth toes
- The authors conclude the medial head assists second-toe flexion while the lateral head assists all four lesser toes - two heads, two roles
- This is a direct in-vivo measurement of the muscle in action, not an inference from its attachments
Fiber Type Composition of the Human Quadratus Plantae Muscle: A Comparison of the Lateral and Medial Heads
- Immunohistochemical fibre typing of both heads in eleven formalin-embalmed specimens, mean age 84 plus or minus 9 years
- WITHIN an individual the two heads were strikingly similar - a mean difference in Type I content of only 4.1 per cent
- BETWEEN individuals the composition was extraordinarily variable: Type I fibres ranged from 19.1 to 91.6 per cent in the lateral head and 20.4 to 97.0 per cent in the medial head
- The authors conclude that matched composition within a person supports a SINGLE shared function for the two heads
- They note surveys showing one or other head is absent in about 20 per cent of the population, which would matter if the heads did different jobs