Tendon to Tendon — The Hand's Proprioceptive Governor
- The lumbricals are the only muscles in the body with both origin and insertion on tendon — origin from flexor digitorum profundus, insertion into the radial lateral band of the extensor hood.
- They have no bony attachment at all, which is why they are the pure interphalangeal extensors and why they can slacken their own origin.
- Radial two (index and middle) are median-innervated; ulnar two (ring and little) are supplied by the deep motor branch of the ulnar nerve.
- The radial two are unipennate from a single profundus tendon; the ulnar two are bipennate from two adjacent profundus tendons.
- They pass VOLAR to the deep transverse metacarpal ligament, whereas the interossei pass dorsal to it.
- “Lumbrical-plus finger: divide the FDP distal to the lumbrical origin and the profundus stump retracts, pulling the lumbrical proximally, so attempted finger flexion produces paradoxical PIP extension.
- “Quadriga: the profundus tendons share a common muscle belly, so tethering or over-advancing one tendon limits excursion in all the others.
- “The lumbrical canal runs from the midpalmar space distally to the web space, and is the route by which deep palmar infection reaches the digit.
- “The lumbrical is the only muscle that can relax its own origin — the anatomical basis for its proposed proprioceptive role.
Overview
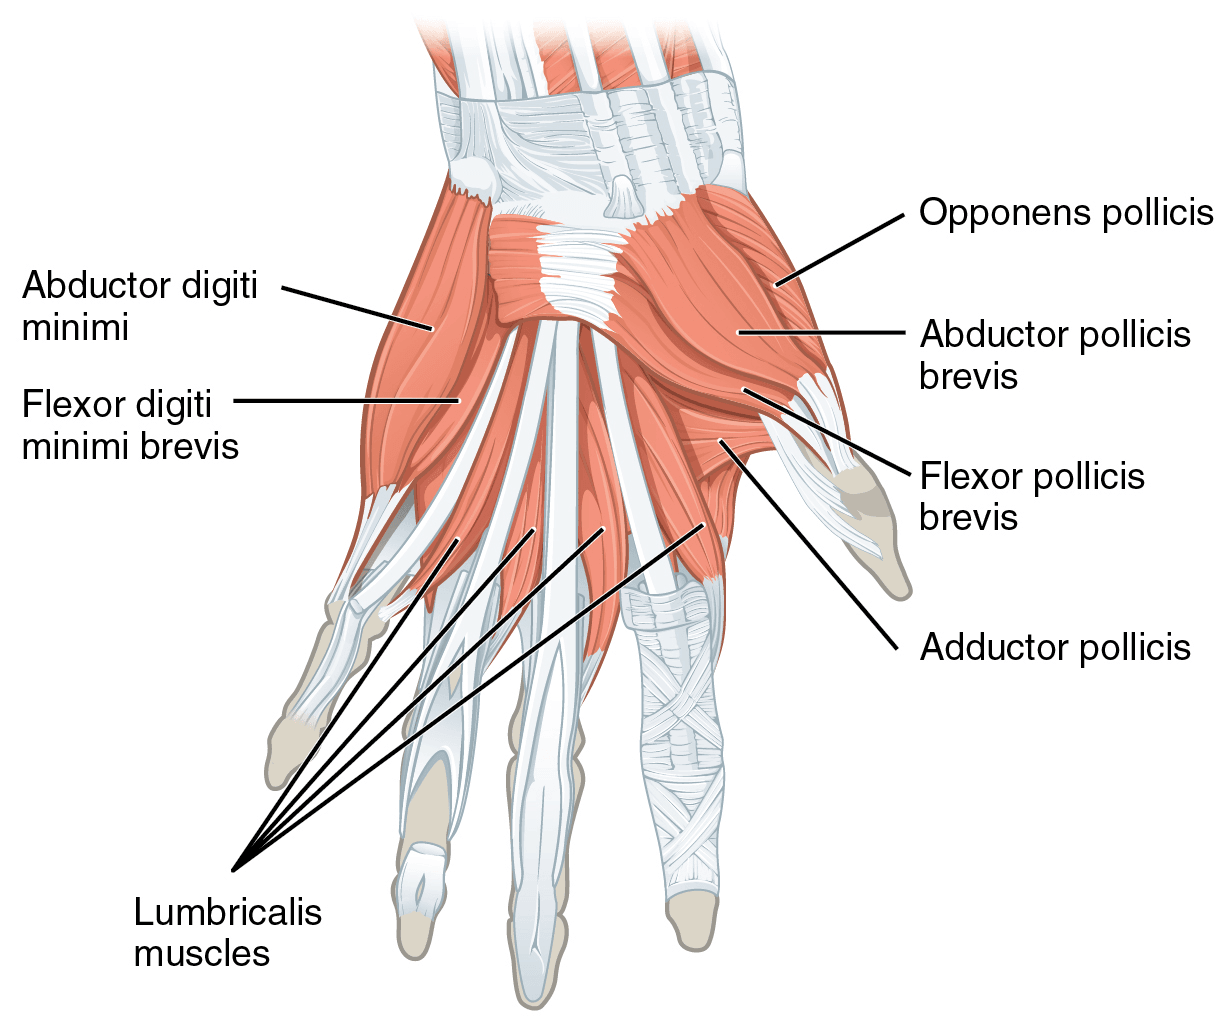
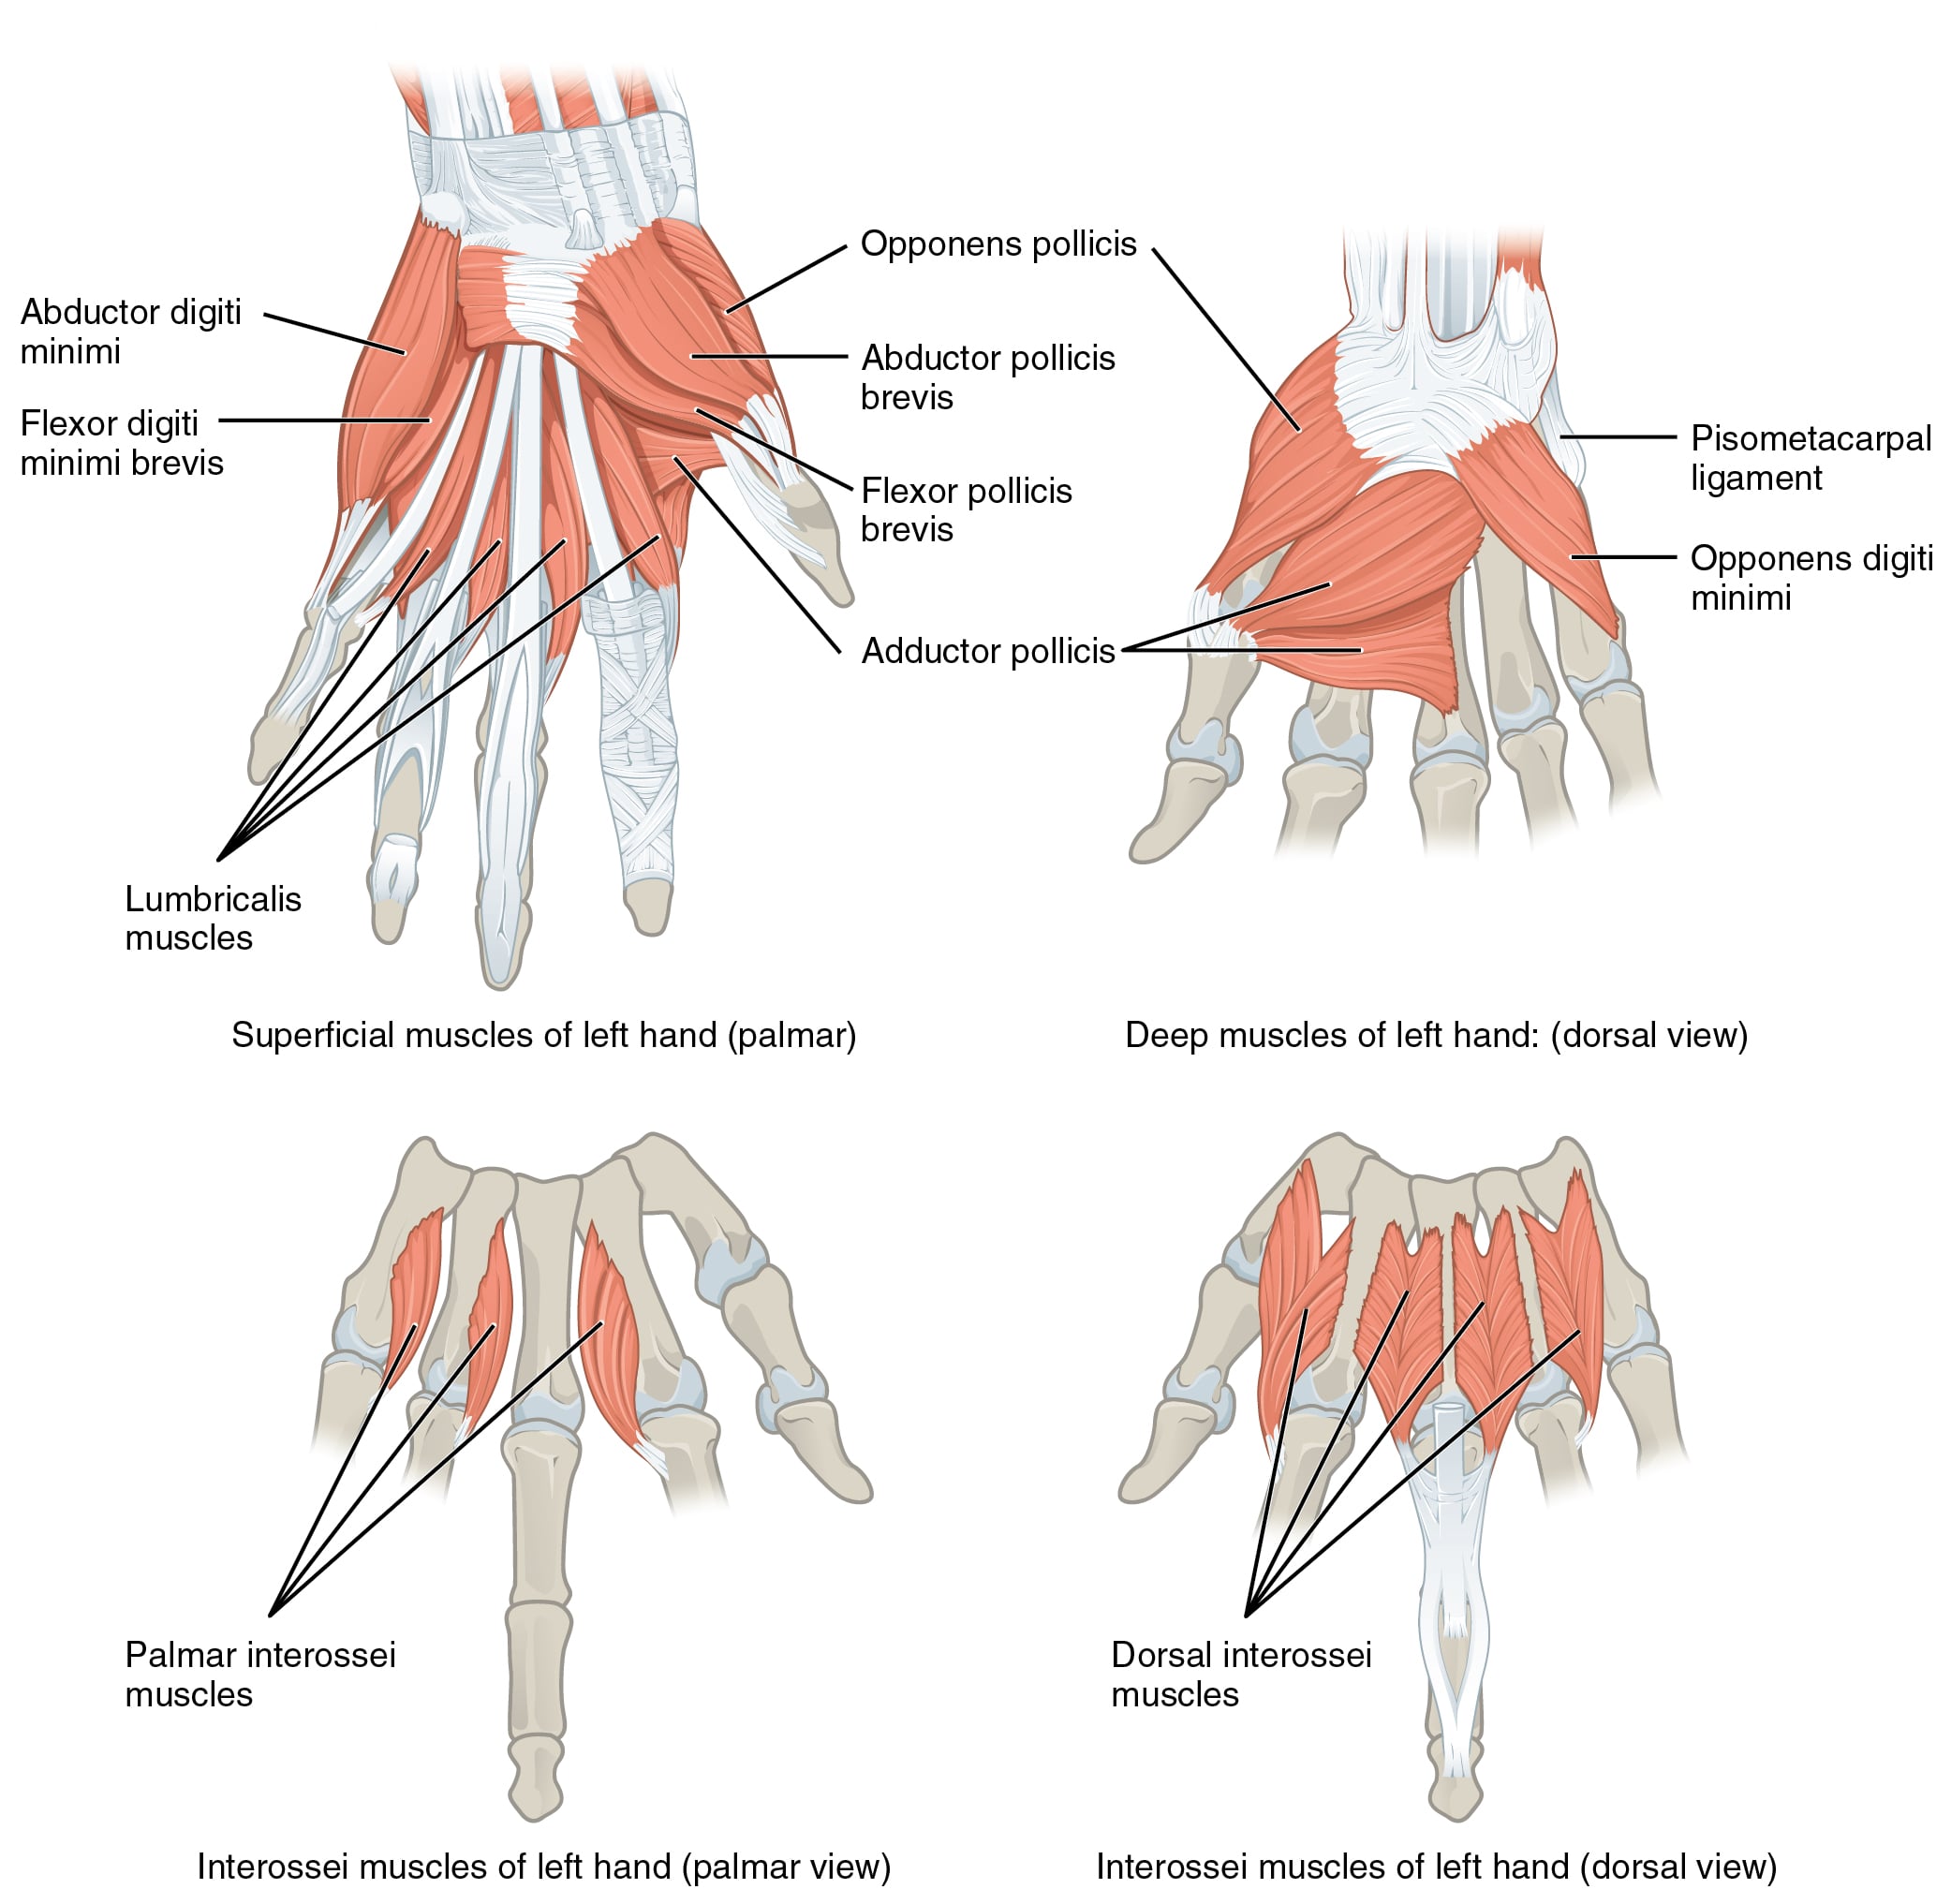
The lumbricals ("earthworms", from the Latin lumbricus) are four slender, cylindrical muscles arising in the palm from the flexor digitorum profundus (FDP) tendons and inserting into the radial lateral bands of the extensor hoods of the index, middle, ring and little fingers. They are the smallest muscles in the hand and they generate very little force.
Why they are examined. Every other muscle in the body pulls a mobile bone toward a fixed one. The lumbricals are the only muscles with origin and insertion both on tendon, and that single fact explains a set of clinical phenomena, the lumbrical-plus finger, quadriga and paradoxical extension, that appear in every hand viva. It is why a muscle this small is examined more often than almost any other structure.
Attachments, Innervation and Relations
Origin. Each lumbrical arises from the flexor digitorum profundus tendons in the palm, distal to the distal edge of the transverse carpal ligament, at approximately the level of the mid-palm to the distal palmar crease depending on the position of the digits. Because the origin sits on a moving tendon it migrates roughly 2-3 cm proximally and distally with finger flexion and extension, which is why it can enter the carpal tunnel in full flexion.
- Origin
- Radial side and palmar surface of the index FDP tendon
- Architecture
- Unipennate
- Digit served
- Index
- Origin
- Radial side and palmar surface of the middle FDP tendon
- Architecture
- Unipennate
- Digit served
- Middle
- Origin
- Adjacent sides of the middle and ring FDP tendons
- Architecture
- Bipennate
- Digit served
- Ring
- Origin
- Adjacent sides of the ring and little FDP tendons
- Architecture
- Bipennate
- Digit served
- Little
Insertion. Each lumbrical runs distally along the radial side of its digit, passes volar to the deep transverse metacarpal ligament, then turns dorsally around the radial side of the MCP joint. It inserts into the radial lateral band of the extensor hood at the level of the proximal phalanx, joining the interosseous contribution to form the conjoined lateral band and thence the terminal tendon. There is no bony insertion at all: that is the defining feature, and the reason the lumbrical is the purest interphalangeal extensor.
Compared with the interossei. The two intrinsic groups are built for opposite jobs.
- Lumbricals
- Flexor digitorum profundus TENDON — mobile
- Interossei
- Metacarpal BONE — fixed
- Lumbricals
- Radial lateral band ONLY
- Interossei
- Base of proximal phalanx AND lateral band
- Lumbricals
- VOLAR
- Interossei
- DORSAL
- Lumbricals
- Radial two median, ulnar two ulnar
- Interossei
- All ulnar (deep motor branch)
- Lumbricals
- Interphalangeal extension
- Interossei
- MCP flexion, abduction or adduction, and IP extension
- Lumbricals
- Very small
- Interossei
- Large — the first dorsal interosseous rivals an extrinsic muscle
- Lumbricals
- Exceptionally high — proprioceptive role
- Interossei
- Conventional
Variations. Absence of the fourth lumbrical is reported in a minority of hands, and the third and fourth may be fused. Insertion into the ulnar rather than the radial lateral band, or into both, is described, particularly at the little finger. In some individuals the muscle belly itself lies within the carpal tunnel in flexion; hypertrophy of the muscle or an unusually proximal origin is a recognised cause of dynamic carpal tunnel syndrome, covered under Clinical Relevance.
Action and Biomechanics
Interphalangeal extension. The lumbrical inserts into the radial lateral band, dorsal to the interphalangeal axes, so extension of the PIP and DIP joints is its dominant and near-exclusive action. Loss of that action contributes to the claw; excess of it produces the lumbrical-plus finger.
MCP flexion. The line of pull is volar to the MCP axis, so the lumbrical flexes the MCP joint, but weakly. With no bony insertion and little force it cannot substitute for interosseous MCP flexion, and it has almost no independent MCP flexion contribution beyond that volar line of pull.
Slackening its own origin. Both attachments move: the origin is the profundus tendon, which moves distally when the profundus relaxes and proximally when it contracts, and the insertion belongs to the extensor system. When the lumbrical contracts it pulls the profundus tendon distally, slackening the flexor, while pulling the lateral band proximally, tightening the extensor. It is the only muscle that can relax its own origin, a reciprocal switch that shifts the finger from flexion toward extension in a single action.
Proprioception. Lumbricals have an exceptionally high density of muscle spindles relative to their small mass. Because both attachments move, the muscle acts as a length transducer between the flexor and extensor systems, sensing their relative positions; this is why it is often described as the "governor" of the finger, coordinating the two systems rather than generating power, and why it is proposed to be a proprioceptive organ. It also explains the loss of fine coordination out of proportion to strength loss.
Force and architecture. The lumbricals are the smallest and weakest intrinsic muscles, with tiny physiological cross-sectional areas, yet their excursion is relatively large for their size, and larger than the interossei, because their origin moves. The lumbrical is a control element, not a power element. No tendon transfer can restore lumbrical function as such; anti-claw surgery restores the geometric effect, MCP flexion with IP extension, rather than the muscle.
The lumbrical-plus finger. This is the single most examined lumbrical concept. Cut the profundus distal to the lumbrical origin and the origin becomes a free, retracting tendon end; the lumbrical is stretched and pulls the lateral band, producing extension when the patient tries to flex. The sequence:
- The FDP tendon is divided or lost distal to the lumbrical origin
- The profundus stump retracts proximally, but it is still attached to the lumbrical origin
- When the patient attempts to flex the finger, the profundus muscle contracts and pulls the stump proximally; because the stump has no distal attachment, all that force is transmitted through the lumbrical, which is stretched and tensioned
- The lumbrical pulls on the radial lateral band, and the lateral band extends the PIP and DIP joints
- The result is paradoxical extension of the interphalangeal joints on attempted flexion: the harder the patient tries to make a fist, the straighter the finger becomes
The causes are the ways a profundus can be divided or effectively lengthened while its lumbrical origin is retained:
- Distal amputation through the middle phalanx or distal to it, the commonest cause
- Zone 1 or 2 FDP laceration left unrepaired
- FDP avulsion (jersey finger) where the tendon retracts
- An excessively long flexor tendon graft, which effectively behaves like a divided tendon
- Rupture of an FDP repair
The quadriga effect. This is the other half of the same story. The flexor digitorum profundus tendons to the middle, ring and little fingers share a common muscle belly in the forearm; the index profundus is more independent, which is why the index has the most independent DIP flexion and is comparatively protected from quadriga. Because they share a belly, excursion is common to all: if one tendon is tethered, over-advanced, sutured too tightly, or fixed at a shorter length than the others, the profundus belly cannot excurse fully when the other digits try to flex, and the other fingers cannot fully flex. The patient presents with an incomplete fist and weak grip in fingers that were never injured.
The name, and a correction. It comes from the Roman four-horse chariot: the driver holds four reins as one, so if one horse is short-reined the others cannot run. Schreuders' review of the phenomenon adds a correction to the usual teaching: the profundus tendons are markedly interconnected and cannot move independently in the way the superficialis tendons can, and the cross-connections between the tendons matter more than the shared belly, which is why the effect persists even where bellies are separate.
Both complications arise from the same well-meant but wrong manoeuvre: suturing the flexor and extensor tendons over the end of an amputated digit in the belief that it "balances" the stump. Suture the profundus to anything and fix its length, and the shared profundus belly cannot excurse: quadriga, the other fingers cannot make a fist. Leave the profundus divided but the lumbrical origin intact, and attempted flexion tensions the lumbrical: lumbrical-plus, the affected finger extends when the patient tries to flex. The correct technique at digital amputation is to divide the flexor and extensor tendons cleanly, let them retract, and not suture them to each other or to bone.
Synergists and antagonists. The interossei are the synergists: they share the lateral band insertion and add the MCP flexion power the lumbrical lacks. The antagonists are extensor digitorum communis at the MCP joint, and flexor digitorum superficialis and profundus at the IP joints.
Surface Anatomy and Examination
Landmarks. The lumbricals lie in the distal half of the palm, radial to each FDP tendon and deep to the palmar aponeurosis; they are not palpable. The distal palmar crease overlies approximately the level of the A1 pulleys and the MCP joints, and the lumbricals lie just proximal and radial to it. Kaplan's cardinal line, drawn from the apex of the first web space parallel to the proximal palmar crease toward the hook of hamate, approximates the level of the superficial palmar arch, which lies at or just proximal to it, and the level at which the common digital nerves arise from the median and ulnar nerves to run alongside the lumbricals and supply the radial two.
Testing. There is no clean isolated lumbrical test. The lumbrical action, MCP flexion with IP extension, is shared with the interossei, and the interossei dominate. The nearest approximation is the "lumbrical position" or intrinsic-plus test: the patient holds the MCP joints flexed to about 80-90 degrees with the IP joints fully straight, and resists, which tests the intrinsic system as a whole. Isolated DIP flexion of the index tests the independence of the index FDP and is the relevant test when quadriga is suspected in the index.
Testing for the two syndromes. Six tests, with what a positive result means and what else can produce it.
- How to perform
- Ask the patient to make a full fist and watch the affected digit
- Positive finding
- The PIP and DIP joints EXTEND as the patient tries to flex
- What it means
- Lumbrical-plus finger — FDP divided distal to the lumbrical origin
- False positives
- A fixed PIP extension contracture looks similar at rest but does not change with effort
- How to perform
- Ask the patient to make a full fist; measure the distance from each fingertip to the distal palmar crease
- Positive finding
- The uninjured fingers cannot reach the palm, with a fixed shortfall
- What it means
- Quadriga — one profundus is tethered or over-advanced, limiting the shared belly
- False positives
- Joint stiffness or flexor adhesion in the individual digits; test each digit passively
- How to perform
- Block the PIP joint in extension and ask the patient to flex the DIP
- Positive finding
- Absent DIP flexion
- What it means
- FDP division or avulsion
- False positives
- DIP joint stiffness or a mallet deformity
- How to perform
- Hold all other fingers in full extension and ask the patient to flex the test finger at the PIP
- Positive finding
- Absent PIP flexion
- What it means
- FDS division
- False positives
- An absent or conjoined little finger FDS (see the caveat below)
- How to perform
- Passively block MCP hyperextension and ask for active PIP extension
- Positive finding
- PIP joints extend fully
- What it means
- Correctable claw — extensor mechanism intact
- False positives
- Fixed PIP contracture makes it uninterpretable
- How to perform
- Compare passive PIP flexion with the MCP extended versus flexed
- Positive finding
- Worse with the MCP extended
- What it means
- Intrinsic tightness
- False positives
- Equal restriction in both positions indicates a joint contracture
The little finger FDS caveat. Testing the flexor digitorum superficialis of the little finger by holding the other three fingers extended fails in a substantial minority of people, because the little finger superficialis is absent, vestigial or conjoined with the ring finger superficialis. Test the little finger FDS by holding only the index and middle extended, allowing the ring to flex with it. This is a favourite examination trap and has direct surgical relevance when planning an FDS transfer.
Complications
- Mechanism
- FDP divided or effectively lengthened distal to the lumbrical origin
- Prevention
- At amputation, divide tendons and let them retract; do not leave an over-long tendon graft
- Salvage
- Lumbrical tendon release, or excision of the retracted profundus stump
- Mechanism
- Fixed length of one profundus tendon in the shared belly, from tenodesis, over-advancement or adhesion
- Prevention
- Never tenodese the FDP over an amputation stump; do not advance an FDP more than about 1 cm
- Salvage
- Divide the tethering tendon or perform tenolysis
- Mechanism
- The radial proper digital nerve lies immediately volar to the lumbrical tendon
- Prevention
- Identify the bundle before dividing anything; use a mid-lateral or Bruner approach with adequate exposure
- Salvage
- Direct repair; a digital nerve should always be repaired
- Mechanism
- A spiral cord displaces the bundle superficially, proximally and toward the midline
- Prevention
- Identify the bundle proximally in normal tissue and follow it distally
- Salvage
- Direct repair under magnification
- Mechanism
- Transverse incision across the web
- Prevention
- Never cross the web transversely; use longitudinal or oblique palmar plus dorsal incisions
- Salvage
- Z-plasty or four-flap Z-plasty release
- Mechanism
- Infection tracks proximally along the lumbrical canal
- Prevention
- Examine for loss of the palmar concavity and pain on passive digital extension; drain the deep space when involved
- Salvage
- Deep space drainage, repeat washout, prolonged antibiotics
- Mechanism
- Digital nerve left at the level of the scar or a pressure point
- Prevention
- Draw the nerve distally, divide sharply and allow it to retract into soft tissue
- Salvage
- Neuroma excision with transposition into muscle or bone
- Mechanism
- A proximal lumbrical muscle belly entering the pulley region
- Prevention
- Recognise the muscle belly rather than a nodule at operation
- Salvage
- Debulking or partial lumbrical excision rather than further pulley division
- Mechanism
- Lumbrical incursion into the tunnel only with sustained grip
- Prevention
- Consider the diagnosis when standard studies are normal but symptoms are grip-related
- Salvage
- Carpal tunnel release once other causes are excluded
Clinical Relevance
Recognition. Ask the patient to make a fist and watch the affected digit: it extends at the PIP while the others flex. Ask about a previous amputation, flexor tendon injury, jersey finger or tendon graft, because the history usually gives the diagnosis. Then establish whether the FDP is divided distal to the lumbrical origin (laceration, avulsion, amputation) or effectively lengthened (an over-long tendon graft, a ruptured repair), because the mechanism determines the fix.
The mimics. A fixed PIP extension contracture, a swan-neck deformity and intrinsic tightness all produce an extended PIP. Only the lumbrical-plus finger extends more when the patient tries to flex, so watch the finger during active effort.
Treatment. Division of the lumbrical tendon at its insertion into the lateral band is the definitive treatment, and it is simple and reliable. It removes the abnormal linkage between the retracting profundus stump and the extensor mechanism; the finger loses a small amount of interphalangeal extension power, which the interossei amply compensate, and the paradoxical extension abolishes immediately. Division or excision of the retracted profundus stump is an alternative, and where the finger is otherwise reconstructable, tightening or revising an over-long graft addresses the cause.
The trap. Do not treat a lumbrical-plus finger by tightening or repairing the profundus unless you can restore a functioning distal insertion. In an amputation stump there is nothing distal to attach it to, so the only options are lumbrical release or excision of the stump.
Surgical Relevance
Distances and safe zones. The arches, the deep motor branch and the A1 pulley are located by distance from the transverse carpal ligament and the palmar creases.
- Superficial palmar arch: approximately 1 cm distal to the distal edge of the transverse carpal ligament. The deep arch lies about 1 cm proximal to the superficial arch.
- Deep motor branch of the ulnar nerve: crosses the palm roughly 1-2 cm distal to the distal edge of the transverse carpal ligament, on the palmar surface of the interossei, deep to the flexor tendons and the lumbricals. The lumbricals are therefore volar to the nerve, a plane that separates safe from dangerous in palmar dissection.
- A1 pulley: overlies the MCP joint at approximately the level of the distal palmar crease for the ring and little, and the proximal palmar crease for the index. Release must be strictly midline and longitudinal; the radial digital nerve to the index and the ulnar digital nerve to the little finger cross obliquely and are the ones at risk in percutaneous release.
Digital amputation. Tendon management at amputation is where both lumbrical complications are made or avoided.
- 1Step 1 — Identify the tendons
Identify the flexor digitorum profundus and superficialis and the extensor tendon at the level of the amputation.
Know what you are dividing
- 2Step 2 — Divide cleanly and let them retract
Draw each tendon distally, divide it sharply, and allow it to retract proximally.
This is the correct technique
- 3Step 3 — Do NOT tenodese
Do not suture the profundus to the extensor over the bone end, and do not suture either tendon to bone or to periosteum. It feels tidy and it causes quadriga and a lumbrical-plus finger.
The single most important step
- 4Step 4 — Shorten bone appropriately
Trim the bone end and round the condyles so the soft tissue closes without tension.
Avoids a tender, prominent stump
- 5Step 5 — Manage the digital nerves
Draw each digital nerve distally, divide it sharply and allow it to retract into soft tissue away from the scar and away from pressure points.
Prevents a painful stump neuroma
- 6Step 6 — Consider ray amputation
For an index or little finger amputation at or proximal to the MCP joint, a ray amputation gives a better appearance and often better function than a short stump, at the cost of measurable grip strength.
Discuss with the patient in advance
- 7Step 7 — Mobilise early
Early motion of the remaining digits prevents adhesion and the secondary quadriga of scar tethering.
Therapy from the first week
Lumbrical release. The indication is an established lumbrical-plus finger. Approach through a mid-lateral or volar zig-zag (Bruner) incision over the proximal phalanx on the radial side, where the lumbrical joins the lateral band. Identify the lumbrical tendon as it passes volar to the deep transverse metacarpal ligament and turns dorsally to the radial lateral band, and divide it distal to the intermetacarpal ligament, at or just proximal to its junction with the lateral band.
What to protect, and the alternative. The radial proper digital nerve and artery lie immediately volar to the tendon being divided. The alternative operation is excision of the retracted profundus stump through a palmar incision, which removes the proximal driver. Lumbrical release abolishes the paradoxical extension at once, with negligible functional cost.
Flexor tendon surgery. Set graft tension against the normal digital cascade with the wrist in neutral: the fingers should lie in progressively greater flexion from index to little. In two-stage flexor reconstruction the lumbrical origin is a landmark for the proximal junction, and the muscle should be preserved where possible.
Guidelines, Registries & Global Practice
Anatomical variation across populations
- Absence or fusion of the fourth lumbrical is reported in a minority of hands across cadaveric series worldwide, with no functional consequence.
- Dual (median and ulnar) innervation of the third lumbrical is a well-recognised variant; the fourth is consistently ulnar. Series differ in reported prevalence largely by how the contribution is defined.
- Absent or conjoined flexor digitorum superficialis of the little finger is present in a substantial minority of hands across all populations. This has direct clinical relevance to examination technique (test the little finger superficialis with only the index and middle held extended) and to donor planning for tendon transfer.
- The Riche-Cannieu and Martin-Gruber anastomoses (the latter in roughly 15-20% of limbs) shift lumbrical innervation in individual patients and are the standard explanation for a clinical picture that does not match the level of a documented nerve injury.
Differences in described practice
- Tendon management at digital amputation: every major source — AO, AAOS instructional material, BOA/BSSH and European hand surgery texts — agrees that flexor and extensor tendons should be divided and allowed to retract, and that tenodesis over the bone end is wrong. It nonetheless remains one of the most frequently encountered avoidable errors in revision hand surgery, which is why examiners keep asking about it.
- Flexor tendon advancement: the approximately 1 cm threshold is a long-standing teaching point rather than a figure derived from randomised evidence. Practice is consistent internationally in avoiding significant advancement in favour of grafting.
- Hand infection drainage: the principle of dual palmar and dorsal drainage for a collar-stud web abscess and the prohibition on transverse web incisions are universal. Antibiotic choice varies with local MRSA prevalence, and guidance from national bodies should be followed.
- Wide-awake local anaesthesia no tourniquet (WALANT) surgery has changed practice for tenolysis and tendon transfer in many centres, because it allows intra-operative confirmation of active motion. Adoption varies widely by health system and by anaesthetic practice, and it is particularly valuable in resource-limited settings because it removes the need for general anaesthesia.
Global context
- Hand infection remains a major cause of disability worldwide and is disproportionately concentrated in manual workers, people with diabetes and settings with delayed presentation. The lumbrical canal anatomy on this page determines the drainage plan and requires no imaging.
- Digital amputation is among the commonest hand operations performed globally, frequently by non-specialists. The single instruction that prevents both lumbrical-plus finger and quadriga — divide the tendons and let them retract — is the highest-value teaching point in this topic.
- Resource considerations: every procedure described here requires only a scalpel, sutures and a splint. Access to hand therapy is the limiting factor for outcome after tenolysis, and where therapy is unavailable the threshold for tenolysis should be higher, because adhesions reform without supervised mobilisation.
MCQ Practice Points
Q: What is anatomically unique about the lumbricals? A: They are the only muscles with both origin and insertion on tendon — from the flexor digitorum profundus to the radial lateral band.
Q: What is the innervation of the four lumbricals? A: Radial two (index, middle) median via the common digital nerves; ulnar two (ring, little) deep motor branch of the ulnar nerve.
Q: Which lumbricals are bipennate? A: The third and fourth, arising from the adjacent sides of two profundus tendons. The first and second are unipennate.
Q: Do the lumbricals pass volar or dorsal to the deep transverse metacarpal ligament? A: Volar. The interossei pass dorsal. Anti-claw transfers must follow the lumbrical, volar.
Q: A finger extends at the PIP when the patient tries to make a fist. Diagnosis and treatment? A: Lumbrical-plus finger; divide the lumbrical tendon (or excise the retracted profundus stump).
Q: Which fingers are at risk of quadriga and why is the index relatively spared? A: Middle, ring and little, because they share a profundus muscle belly. The index profundus has a relatively independent belly.
Q: How much can an FDP be advanced before quadriga becomes a real risk? A: Approximately 1 cm is the classically quoted threshold; beyond that, use a graft.
Q: Where do the lumbricals insert? A: The radial lateral band of the extensor hood only — there is no bony insertion.
Q: Are the lumbricals lost in an isolated recurrent motor branch injury? A: No. The radial two lumbricals are supplied by branches of the common digital nerves, distal to the recurrent branch takeoff.
Q: What is the clinical importance of the lumbrical canal? A: It is the route by which infection tracks between the web space and the midpalmar or thenar space in either direction.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 45-year-old had a ring finger amputation through the middle phalanx eight months ago. He now complains that when he tries to grip, the stump straightens out and pushes objects away. What is happening?”
“A 29-year-old had a zone 2 flexor tendon repair of the ring finger a year ago. The ring finger moves well. But he says his hand is weak and he cannot make a full fist — the middle and little fingers do not reach the palm. Passive flexion of those fingers is full. Explain and manage.”
“A 52-year-old diabetic has a painful, swollen hand. The middle and ring fingers are held apart. There is fullness on the dorsum between the third and fourth metacarpals and tenderness in the palm. He is febrile. Manage him.”
Anatomy
- Origin: flexor digitorum profundus tendons in the palm
- Insertion: radial lateral band only — no bony insertion
- The only muscles with origin AND insertion on tendon
- Radial two unipennate; ulnar two bipennate
Nerve
- First and second: median, via the common digital nerves
- Third and fourth: deep motor branch of the ulnar nerve
- Spared in an isolated recurrent motor branch injury
- Third lumbrical may be dually innervated
Mechanics
- Volar to the deep transverse metacarpal ligament
- Pure interphalangeal extensor; weak MCP flexor
- The only muscle that can slacken its own origin
- High spindle density — a proprioceptive governor
Clinical
- Lumbrical-plus: paradoxical IP extension on attempted flexion
- Quadriga: uninjured fingers cannot make a fist
- At amputation, divide the tendons and let them retract
- Lumbrical canal carries infection between web and deep palmar space
Evidence Base
The Anatomy of the Dorsal Aponeurosis of the Human Finger and Its Functional Significance
- The anatomical description on which the whole functional account of the lumbrical rests: the dorsal aponeurosis of the finger and the way the intrinsic tendons enter it
- The lumbrical is a muscle attached to TENDON AT BOTH ENDS, linking the flexor and extensor systems - unique among skeletal muscles
- It passes VOLAR to the metacarpophalangeal axis and inserts DORSAL to the interphalangeal axes via the radial lateral band, which is the geometry that produces metacarpophalangeal flexion with interphalangeal extension
- Lumbrical contraction therefore slackens the profundus while tightening the extensor assembly - the mechanical basis of paradoxical extension
The Lumbrical Plus Finger
- Original description of the lumbrical plus finger: paradoxical interphalangeal extension on attempted flexion
- Occurs when the flexor digitorum profundus is divided, lost or effectively lengthened distal to the lumbrical origin
- The retracting profundus stump transmits flexor force through the lumbrical into the radial lateral band, which extends the interphalangeal joints
- Recognised causes in subsequent practice include distal amputation, unrepaired zone 1 and 2 profundus laceration, profundus avulsion and an over-long tendon graft
- Division of the lumbrical tendon abolishes the deformity
Architectural Design of the Human Intrinsic Hand Muscles - What the Lumbrical Is Built For
- The architectural counterpart to the spindle argument: lumbricals had an EXTREMELY HIGH fibre length to muscle length ratio, implying a design toward high EXCURSION rather than high force
- The interossei showed the opposite pattern - relatively high physiological cross-sectional area with a low fibre length ratio, indicating high force and low excursion
- So within one hand two intrinsic groups are built for opposite jobs, and the lumbrical is the excursion element
Lumbrical Muscle Incursion into the Carpal Tunnel During Finger Flexion
- Five cadaver upper limbs studied radiographically with radiopaque markers on the flexor retinaculum and the lumbrical origins, in four finger positions
- In FULL EXTENSION the lumbrical origins sat an average of 7.8 mm DISTAL to the carpal tunnel - outside it
- They moved an average of 14 mm into the tunnel at 50 per cent finger flexion, 25.5 mm at 75 per cent, and 30 mm at FULL flexion
- The authors' conclusion is the important one: incursion of normal lumbricals into the carpal tunnel during finger flexion is a NORMAL occurrence, not an anomaly
- They propose it as a mechanism by which sustained gripping - a repetitive workplace task - could raise carpal tunnel pressure
The Quadriga Phenomenon - A Review and Clinical Relevance
- The flexor digitorum profundus tendons are markedly interconnected and cannot move independently in the way the superficialis tendons can
- IMPORTANT CORRECTION TO THE USUAL TEACHING: the effect is often attributed to the common profundus muscle belly, but the author argues the CROSS-CONNECTIONS BETWEEN THE TENDONS matter more
- The phenomenon affects strength testing, assessment of tendon excursion, and the choice of exercises taught after tendon injury
- Clinically relevant wherever one profundus is tethered, over-advanced or tenodesed - classically over an amputation stump
Deep Space and Web Space Infections of the Hand
- Web space (collar-stud) abscesses have connected palmar and dorsal components and require drainage of both
- Infection tracks along the LUMBRICAL CANAL between the web space and the midpalmar or thenar space - the anatomical reason this page carries an infection card at all
- Adjacent fingers held abducted by web swelling is a characteristic clinical sign
- Transverse incisions across the web produce contracture and must be avoided