The Pelvic Half of the Iliopsoas, and the Compartment That Traps the Femoral Nerve
- Iliacus arises from the upper two-thirds of the iliac fossa, the inner lip of the iliac crest, the anterior sacroiliac and iliolumbar ligaments and the upper lateral sacrum, and inserts onto the lateral side of the psoas tendon and directly onto the femur just distal to the lesser trochanter.
- It is supplied by the femoral nerve (L2, L3), with the branches arising WITHIN THE ABDOMEN in the iliac fossa - proximal to the inguinal ligament.
- The iliac fascia forms a tight, unyielding compartment over the muscle; bleeding within it compresses the femoral nerve, and the same plane is the target of the fascia iliaca compartment block.
- Beneath the inguinal ligament the iliopectineal arch divides the space into the lacuna musculorum laterally (iliopsoas, femoral nerve, lateral femoral cutaneous nerve) and the lacuna vasorum medially (femoral artery, vein, lymphatics and the femoral canal).
- Iliocapsularis, arising from the anterior inferior iliac spine and the anterior hip capsule, hypertrophies in the dysplastic hip and is a recognised imaging marker of instability.
- “A femoral nerve lesion in the thigh spares iliacus and therefore spares hip flexion, whereas a lesion in the pelvis paralyses both iliacus and quadriceps - the way to localise a femoral neuropathy at the bedside.
- “The classical iliacus haematoma presents in an anticoagulated or haemophiliac patient with a painful hip held flexed, quadriceps weakness, an absent knee jerk and numbness over the anterior thigh and medial leg.
- “In iliac crest graft harvest, the superior cluneal nerves cross the crest around 8 cm lateral to the posterior superior iliac spine, and the lateral femoral cutaneous nerve lies within a few centimetres of the anterior superior iliac spine - the two distances that keep the harvest safe.
- “In open reduction of the dysplastic hip the iliopsoas tendon crossing the capsule creates the hourglass constriction; releasing it is part of the operation, not an optional extra.
Overview
Iliacus is a broad, flat, triangular muscle that fills the iliac fossa on the inner surface of the ilium, converges downward and medially, and joins the psoas major tendon to form iliopsoas, the principal flexor of the hip. Unlike psoas it has no attachment to the vertebral column: it is a purely pelvic muscle acting only on the hip.
Why it matters. Four things follow from where it lies, and they are largely independent of one another. The iliac fascia turns the iliac fossa into a closed compartment with the femoral nerve inside it; every operation on the inner table of the ilium begins by elevating the muscle; its femoral nerve branches leave within the abdomen, which localises a femoral neuropathy at the bedside; and its neighbour iliocapsularis is an imaging marker of the unstable dysplastic hip. Each is taken in turn below.
Attachments, Innervation and Relations
Origin. The muscle arises from the inner surface of the ilium and the structures at its margins:
- The upper two-thirds of the concavity of the iliac fossa, the broad, smooth inner surface of the ilium
- The inner lip of the iliac crest
- The anterior sacroiliac and iliolumbar ligaments and the upper lateral part of the sacrum (the ala)
- A few fibres from the anterior inferior iliac spine and the upper part of the hip capsule, which blend with iliocapsularis
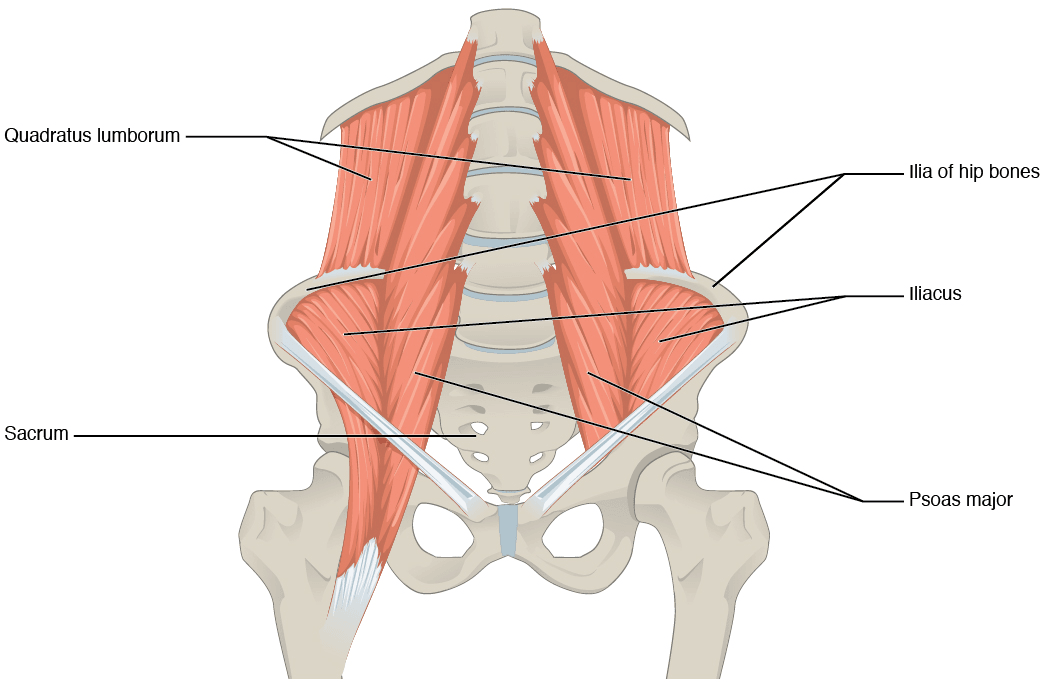
Insertion. The fibres converge inferomedially onto the lateral side of the tendon of psoas major, forming the composite iliopsoas tendon, and some continue past the tendon to insert directly onto the femur just distal to the lesser trochanter, along the spiral line. The psoas tendon is the central cord that reaches the lesser trochanter; iliacus is a muscular sleeve on its lateral aspect, so the unit is a tendon with muscle wrapped around it and the tendinous proportion increases distally, approximately 40 per cent tendon at the level of the hip joint and predominantly tendon at the lesser trochanter.
That gradient is why the level of an iliopsoas release is a real clinical decision rather than a matter of preference. Releasing the unit at the level of the joint divides the tendon while leaving the iliacus fibres intact, and so preserves more hip flexion power than a release at the lesser trochanter; a tendon-only release at the joint does not abolish the muscle's action.
Course. The unit passes over the anterior hip capsule and the iliopectineal eminence, beneath the inguinal ligament in the lacuna musculorum, and turns posteriorly around the front of the hip to reach the lesser trochanter on the posteromedial femur.
Iliocapsularis (iliacus minor). A distinct and constant muscle in most individuals, though frequently overlooked. It arises from the anterior inferior iliac spine and the anterior aspect of the hip joint capsule, to which it is intimately adherent, and inserts on the femur just distal to the lesser trochanter along with the medial fibres of iliacus. Because its origin is the capsule itself, contracting it tensions the anterior capsule, and it acts as a dynamic anterior stabiliser of the hip, particularly where bony coverage is deficient.
The iliac fascia converts the iliac fossa into a closed osteofascial compartment with the femoral nerve inside it. Two clinical consequences follow, and they are opposite sides of the same fact: blood collecting in the space cannot decompress and crushes the nerve against the ilium, which is the iliacus haematoma with femoral nerve palsy; and local anaesthetic deposited deep to the fascia spreads through the same space to the nerves it contains, which is the fascia iliaca compartment block. If you understand why the block works, you understand why the haematoma causes a palsy.
Action and Biomechanics
Actions. Iliacus acts only on the hip, and what it does depends on which end is fixed:
- Action
- Hip flexion; together with psoas the strongest hip flexor
- Mechanism
- Broad origin across the iliac fossa converging on the lesser trochanter
- Loss Produces
- Weakness climbing stairs, rising from a low chair, getting into a car; not on level walking
- Action
- Dominant flexor as rectus femoris loses moment arm
- Mechanism
- Retained flexion moment arm at high flexion angles
- Loss Produces
- The deficit is greatest in deep flexion
- Action
- Anterior pelvic tilt and trunk flexion on the pelvis
- Mechanism
- Reverse origin-insertion action
- Loss Produces
- Weak sit-up; altered standing pelvic tilt
- Action
- Weak external rotation of the hip in some positions
- Mechanism
- Tendon wraps the femoral neck before reaching the lesser trochanter
- Loss Produces
- Minor in isolation
- Action
- Tensions the anterior capsule; dynamic anterior stabiliser
- Mechanism
- Direct capsular origin
- Loss Produces
- Anterior instability in the undercovered hip
The difference from psoas. Psoas comes from the lumbar spine (the bodies, discs and transverse processes of T12 to L5) and iliacus from the pelvis, so only psoas crosses the lumbar spine and only psoas contributes to lumbar segmental control and to the hip-spine interaction. Iliacus contributes nothing to lumbar segmental control and does not produce the lumbar hyperlordosis of a psoas contracture. Its origin is broad and its excursion relatively short compared with psoas, so it provides the bulk and power of the unit while psoas provides the long lever and the spinal link.
Contracture of the combined unit produces a fixed flexion deformity at the hip with compensatory anterior pelvic tilt, quantified by the Thomas test.
Iliocapsularis and the dysplastic hip. In a normal hip the bony acetabulum provides the coverage and iliocapsularis is a small, unremarkable muscle. In a dysplastic hip the anterior and superior coverage is deficient, the anterior capsule is loaded and the head tends to subluxate anteriorly; because iliocapsularis originates directly from that capsule it responds by hypertrophying, tightening the capsule and resisting the anterior translation the bone cannot resist. In an over-covered pincer hip with femoroacetabular impingement the muscle is normal or thin, because the bone is doing the work.
Surface Anatomy and Examination
Landmarks. The iliac crest, the anterior superior iliac spine and the posterior superior iliac spine are the bony landmarks that define every approach to the muscle. Iliacus itself is not palpable, lying on the inner surface of the ilium behind the abdominal wall, but the combined iliopsoas tendon can be felt in the femoral triangle lateral to the femoral artery with the hip flexed and externally rotated.
The fascia iliaca block landmark. On a line from the anterior superior iliac spine to the pubic tubercle, the needle enters 1 cm below the junction of the lateral and middle thirds and is advanced perpendicular; two distinct pops are felt as it crosses the fascia lata and then the fascia iliaca.
Localising a femoral neuropathy. This is the single most useful bedside distinction. Test hip flexion power (supine resisted straight leg raise and seated resisted flexion) and knee extension power, elicit the knee jerk, and map sensation over the anterior thigh and the medial leg. A lesion in the pelvis weakens hip flexion because the iliacus branches are involved, which points to a retroperitoneal cause and demands imaging.
- Lesion in the Pelvis (above the inguinal ligament)
- Denervated - hip flexion weak
- Lesion in the Thigh (below the ligament)
- Spared - hip flexion preserved
- Lesion in the Pelvis (above the inguinal ligament)
- Weak, knee extension lost
- Lesion in the Thigh (below the ligament)
- Weak, knee extension lost
- Lesion in the Pelvis (above the inguinal ligament)
- Absent
- Lesion in the Thigh (below the ligament)
- Absent
- Lesion in the Pelvis (above the inguinal ligament)
- Lost
- Lesion in the Thigh (below the ligament)
- Lost
- Lesion in the Pelvis (above the inguinal ligament)
- Iliacus or retroperitoneal haematoma, pelvic mass, transpsoas or anterior spinal surgery, anterior acetabular retractor
- Lesion in the Thigh (below the ligament)
- Groin haematoma, femoral catheterisation, penetrating injury, hip surgery in the femoral triangle
- Lesion in the Pelvis (above the inguinal ligament)
- Urgent CT of the abdomen and pelvis
- Lesion in the Thigh (below the ligament)
- Ultrasound of the groin, then CT if unclear
The Thomas test. With the patient supine, the opposite hip is pulled into full flexion to flatten the lumbar lordosis while the tested thigh is observed. If it lifts from the couch the test is positive and the angle is recorded as the flexion contracture. The modified test, with the leg hanging over the end of the couch, separates iliopsoas from rectus femoris and tensor fasciae latae.
The instability screen in the borderline hip. Where iliocapsularis becomes relevant, assess for apprehension in extension and external rotation, an abductor lurch and the prone instability signs, and measure the lateral centre-edge angle and acetabular index on radiographs. Apprehension with anterior loading, a lateral centre-edge angle in the borderline range and a hypertrophied iliocapsularis on cross-sectional imaging together mean the hip is relying on soft tissue for stability.
Pitfalls. Do not rely on the knee jerk alone: it is absent in many older patients and can be diminished by pain or positioning. Do not assume that anterior thigh numbness after hip surgery is a femoral nerve problem, because the lateral femoral cutaneous nerve is far more commonly involved, is purely sensory, and produces numbness over the anterolateral thigh with normal power. And in a patient on anticoagulation with new hip pain and a limp, image before attributing it to a musculoskeletal strain; a missed iliacus haematoma with an evolving femoral palsy is a preventable disaster.
Complications
Femoral nerve injury. In the pelvis the nerve is compressed by an iliacus or retroperitoneal haematoma, by retractors in the ilioinguinal middle window, in periacetabular osteotomy and in the anterior hip approaches, or injured directly during pelvic or anterior spinal surgery. The consequence is quadriceps paralysis with loss of knee extension and an unstable knee in stance, plus saphenous sensory loss, with hip flexion weak but not abolished. Avoidance rests on retractors placed on bone with blunt broad tips and released periodically, correction of coagulopathy before elective surgery, and prompt imaging of any new post-operative quadriceps weakness.
Lateral femoral cutaneous nerve injury. Very common after the direct anterior hip approach, periacetabular osteotomy and anterior iliac crest harvest, it produces meralgia paraesthetica: numbness, tingling or burning over the anterolateral thigh with normal power. Warn every patient, because it is common enough that an unwarned patient reasonably feels misled.
Superior cluneal nerve injury and donor-site pain. Harvesting the posterior crest beyond the cluneal safe zone injures the superior cluneal nerves and produces buttock numbness and a painful neuroma. Persistent donor-site pain occurs in a meaningful proportion of iliac crest harvests from either site, is the commonest complication overall, and should be part of the consent.
Haemorrhage. Superior gluteal artery injury from posterior crest dissection toward the greater sciatic notch retracts into the pelvis and may require angiographic embolisation or a separate intrapelvic approach. The deep circumflex iliac branches bleed during anterior harvest, the corona mortis when avulsed in the medial windows, and the iliac fossa diffusely after elevating iliacus; the last is controlled with packing, bone wax and a drain.
Iliac wing and ASIS fracture. Harvesting too close to the anterior superior iliac spine weakens it and can produce an avulsion fracture through the sartorius and inguinal ligament attachment, a painful, slow-healing and entirely avoidable complication. Over-harvesting the crest can also cause a hernia through the iliac fossa defect if the inner table and fascia are not restored.
Complications of iliacus haematoma management. Delayed diagnosis, with an established and incompletely recovering femoral palsy, is the main problem. Re-bleeding follows surgical decompression in a patient whose coagulopathy has not been corrected, and quadriceps weakness may persist despite decompression where the deficit was longstanding.
Clinical Relevance
The condition. Bleeding into the closed iliac fascia compartment compresses the femoral nerve against the iliac fossa. It is the classical compartment-type neuropathy of the pelvis.
Causes. The recognised settings are:
- Anticoagulation, with warfarin and the direct oral anticoagulants, the commonest current cause
- Haemophilia and other bleeding disorders, a classical presentation in haemophilia A and B and one of the recognised muscle bleeds along with the calf and forearm
- Blunt trauma and hyperextension injuries of the hip, including sporting injuries in young athletes
- After retroperitoneal or vascular procedures, femoral artery catheterisation and pelvic surgery
- Spontaneous, particularly in the elderly and in renal failure
Presentation. Pain in the groin, iliac fossa or back, with the hip held in flexion and slight external rotation and resisting passive extension, together with abdominal or iliac fossa tenderness. The femoral nerve deficit is progressive: quadriceps weakness, an absent knee jerk, and numbness over the anterior thigh and the medial leg and foot in the saphenous distribution. A falling haemoglobin and, in a large bleed, haemodynamic compromise complete the picture.
Symptoms may evolve over hours to days, and the neurological deficit typically follows the pain. Check the coagulation and image urgently.
Investigation. Urgent contrast-enhanced CT of the abdomen and pelvis demonstrates the haematoma, its size and any active extravasation; ultrasound can confirm a collection quickly at the bedside but is less complete. Send a full coagulation screen, factor assays where a bleeding disorder is suspected, and a group and save.
Management. Treatment proceeds as follows:
- Correct the coagulopathy immediately: vitamin K and prothrombin complex concentrate for warfarin, the appropriate reversal agent for a direct oral anticoagulant, and factor replacement in haemophilia, which is the mainstay and is often sufficient by itself
- Resuscitate and monitor serially, with documented neurological examinations
- Conservative management is appropriate for most patients whose deficit is stable or improving after correction of the coagulopathy; recovery of the nerve is usual, though it may take months
- Surgical or radiological intervention for a progressive neurological deficit, an expanding haematoma, haemodynamic instability, or failure of correction: angiographic embolisation of an identified bleeding vessel, or surgical decompression and evacuation with release of the iliac fascia through a retroperitoneal approach
- Decompression is controversial in haemophilia, where factor replacement alone usually suffices and surgery risks further bleeding; decisions there are made jointly with haematology
Surgical Relevance
Principle. The ilioinguinal approach (Letournel) exposes the anterior column and the quadrilateral surface through three windows created between the structures crossing the pelvic brim. Iliacus defines the first of them.
Lateral window. Created by subperiosteal elevation of iliacus from the internal iliac fossa, from the iliac crest down to the pelvic brim, it gives access to the internal iliac fossa, the anterior sacroiliac joint, the upper anterior column and the iliac wing; the same elevation gives access for the Bernese periacetabular osteotomy, the Salter innominate osteotomy and pelvic tumour resection. Its medial boundary is the iliopsoas with the femoral nerve, retracted medially. Strip strictly subperiosteally with a broad elevator, do not damage the iliac apophysis in an adolescent, and pack the fossa to control the diffuse bleeding from the muscle and the iliolumbar branches while the other parts of the exposure are developed.
Middle window. This lies between the iliopsoas with the femoral nerve laterally and the external iliac vessels medially, and is created by dividing the iliopectineal fascia, which separates the muscular from the vascular compartment and runs from the inguinal ligament to the iliopectineal eminence. It gives access to the pelvic brim, the quadrilateral surface, the superior pubic ramus and the anterior column. At risk are the femoral nerve, retracted with the iliopsoas; the external iliac vessels, which must be slung and handled gently; and the lymphatics, whose disruption causes a persistent lymphocele.
Medial window. Medial to the external iliac vessels and containing the spermatic cord or round ligament, it gives access to the superior pubic ramus and the pubic symphysis. The corona mortis crossing the superior pubic ramus must be identified and ligated before it is avulsed.
The modern alternative. The anterior intrapelvic (modified Stoppa) approach, often combined with the lateral window, works medial to the iliopsoas from a midline or Pfannenstiel incision and gives excellent access to the quadrilateral surface without the middle window dissection around the femoral nerve and the external iliac vessels. It has largely replaced the classical three-window ilioinguinal approach in many units.
Fascia iliaca compartment block. Local anaesthetic deposited deep to the fascia iliaca spreads within the compartment to reach the femoral nerve and the lateral femoral cutaneous nerve, and, less reliably, the obturator. The landmark technique uses the surface point and the two fascial pops described above. The supra-inguinal ultrasound-guided approach enters above the inguinal ligament and deposits the local anaesthetic deep to the fascia iliaca over the iliacus, giving more reliable cephalad spread and better femoral and lateral femoral cutaneous coverage.
Its uses are analgesia for hip and femoral fractures, where it reduces opioid requirement and is recommended in many national hip fracture pathways, and supplementary analgesia for hip and thigh surgery. It requires no nerve identification, carries a low risk of intraneural or intravascular injection, and is easily learned. The cautions are local anaesthetic systemic toxicity with the large volumes used, and the masking of an evolving compartment or nerve problem, so document the neurological examination before the block.
Guidelines, Registries & Global Practice
Anatomical variation
- Iliocapsularis is present in essentially all hips but varies widely in size, and that variation is itself the clinical signal - its bulk tracks with the degree to which the hip relies on soft-tissue stability.
- The lateral femoral cutaneous nerve has a notoriously variable course near the anterior superior iliac spine: it may pass over, through or medial to the inguinal ligament, may divide into multiple branches proximally, and may cross the crest itself. There is no distance that is universally safe, which is why the nerve should be identified where the exposure allows and the patient warned in every case.
- The corona mortis is present in a substantial proportion of pelves and may be arterial, venous or both.
- Accessory iliacus slips and variations in the composition of the distal iliopsoas tendon, including a bifid tendon, are described and are a recognised cause of persistent symptoms after an incomplete release.
- Superior cluneal nerve course varies, and an entrapment of the nerve where it crosses the iliac crest under a fascial tunnel is an under-recognised cause of low back and buttock pain in its own right.
Practice framing across bodies
- Position Relevant to Iliacus and the Iliac Fossa
- The lateral window is created by subperiosteal elevation of iliacus; the anterior intrapelvic approach is increasingly favoured over the classical middle window dissection around the femoral nerve.
- Position Relevant to Iliacus and the Iliac Fossa
- Fascia iliaca compartment block is recommended as part of multimodal analgesia for hip fracture, reducing opioid requirement.
- Position Relevant to Iliacus and the Iliac Fossa
- Borderline dysplasia should be assessed for instability before arthroscopy; capsular management must be conservative and the capsule repaired.
- Position Relevant to Iliacus and the Iliac Fossa
- Bone graft substitutes and local autograft are increasingly used in place of iliac crest harvest, driven largely by donor-site morbidity.
- Position Relevant to Iliacus and the Iliac Fossa
- Muscle bleeds in haemophilia, including iliacus, are treated primarily with factor replacement; surgical decompression is reserved for progressive neurological deficit.
Resource-dependent practice
- Well-resourced settings: ultrasound-guided supra-inguinal fascia iliaca blocks, cross-sectional measurement of iliocapsularis for borderline dysplasia, angiographic embolisation for an expanding iliacus haematoma, and bone graft substitutes reducing the need for crest harvest.
- Limited-resource settings: the landmark fascia iliaca block requires nothing but a needle and knowledge of two fascial pops and is one of the highest-value analgesic techniques available for hip fracture anywhere. Iliacus haematoma is diagnosable clinically and by ultrasound and is managed primarily by correcting the coagulopathy. Iliac crest autograft remains the standard graft in most of the world, and the nerve landmarks - posterior to the ASIS, within 8 cm of the PSIS - are the whole of the safety technique.
Global framing
- Iliac crest bone graft remains the biological benchmark against which substitutes are measured, and persistent donor-site pain is its dominant and consistently reported morbidity across international series.
- Fascia iliaca block has been adopted into hip fracture care pathways in many countries as a means of reducing opioid use and delirium in older patients, and it is one of the few interventions in this territory supported by consistent comparative evidence.
- Periacetabular osteotomy is concentrated in specialist centres internationally, and the recognition that borderline dysplasia is a distinct and dangerous group to treat arthroscopically has been one of the significant shifts in hip preservation practice.
MCQ Practice Points
Q: From where does iliacus arise? A: The upper two-thirds of the iliac fossa, the inner lip of the iliac crest, the anterior sacroiliac and iliolumbar ligaments, and the upper lateral sacrum.
Q: What supplies iliacus, and where do the branches arise? A: The femoral nerve (L2, L3), with the branches arising WITHIN THE ABDOMEN in the iliac fossa, proximal to the inguinal ligament.
Q: How do you distinguish a femoral nerve lesion in the pelvis from one in the thigh? A: By hip flexion. A pelvic lesion weakens iliacus and therefore hip flexion; a thigh lesion spares iliacus. Neither abolishes hip flexion, because psoas has its own supply.
Q: How exactly does iliacus insert? A: Onto the lateral side of the psoas tendon, with some fibres continuing directly onto the femur just distal to the lesser trochanter.
Q: What divides the space beneath the inguinal ligament, and what is in each part? A: The iliopectineal arch. Laterally, the lacuna musculorum contains iliopsoas, the femoral nerve and the lateral femoral cutaneous nerve; medially, the lacuna vasorum contains the femoral artery, vein, lymphatics and the femoral canal.
Q: Is the femoral nerve inside the femoral sheath? A: No. It lies lateral to the sheath, in the muscular compartment - which is why it is spared in a femoral hernia.
Q: Where does iliocapsularis arise, and what does its hypertrophy indicate? A: From the anterior inferior iliac spine and the anterior hip capsule. Hypertrophy indicates a dysplastic, unstable hip relying on soft tissue for stability; it is normal or thin in an over-covered pincer hip.
Q: How far lateral to the posterior superior iliac spine can you safely harvest bone? A: Within about 8 cm - beyond that the superior cluneal nerves cross the crest.
Q: Why start an anterior iliac crest harvest at least 2 to 3 cm posterior to the ASIS? A: To protect the lateral femoral cutaneous nerve and to avoid an avulsion fracture of the anterior superior iliac spine through the weakened bone.
Q: How is the lateral window of the ilioinguinal approach created? A: By subperiosteal elevation of iliacus from the internal iliac fossa, giving access to the iliac wing, internal iliac fossa, anterior sacroiliac joint and upper anterior column.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 74-year-old woman on warfarin for atrial fibrillation presents with two days of right groin and iliac fossa pain. She holds the hip flexed, cannot straighten the knee against gravity, and the knee jerk is absent. What is the diagnosis and what do you do?”
“A 24-year-old woman has two years of anterior hip pain and a sense of the hip giving way. The lateral centre-edge angle is 22 degrees and MRI shows an anterosuperior labral tear. A colleague has offered her hip arthroscopy. What is your view, and what does iliocapsularis have to do with it?”
“You are exposing an anterior column acetabular fracture through an ilioinguinal approach. Describe the windows, what iliacus contributes, and everything you must protect.”
Anatomy
- Origin: upper two-thirds of the iliac fossa, inner lip of the crest, SI and iliolumbar ligaments, lateral sacrum
- Insertion: lateral side of the psoas tendon and the femur just distal to the lesser trochanter
- Nerve: femoral nerve (L2, L3), branches arising WITHIN the abdomen
- No spinal attachment - a purely pelvic hip flexor
Compartment
- Iliac fascia forms a closed compartment over the muscle
- Contains iliacus, psoas, femoral nerve and lateral femoral cutaneous nerve
- Iliacus haematoma compresses the femoral nerve - correct coagulopathy first
- Fascia iliaca block targets the same plane; two pops - fascia lata then fascia iliaca
Under the Inguinal Ligament
- Iliopectineal arch divides the space
- Lacuna musculorum (lateral): iliopsoas, femoral nerve, LFCN
- Lacuna vasorum (medial): femoral artery, vein, lymphatics, femoral canal
- Femoral nerve is OUTSIDE the femoral sheath
Surgical
- Lateral window of the ilioinguinal approach = iliacus elevated from the inner table
- Anterior crest harvest: start 2-3 cm posterior to the ASIS (LFCN, avulsion)
- Posterior crest harvest: stay within 8 cm of the PSIS (cluneal nerves); avoid the sciatic notch
- Iliocapsularis hypertrophy on MRI marks the dysplastic, unstable hip
Evidence Base
The Iliocapsularis Muscle - An Important Stabilizer in the Dysplastic Hip
- MR arthrography used to compare 45 hips with deficient acetabular coverage against 40 hips with excessive coverage
- Thickness, width, circumference, cross-sectional area and partial volume of iliocapsularis were all increased in the dysplastic group
- Dysplastic hips also had a LOWER prevalence of fatty infiltration of the muscle than over-covered hips
- The findings support the muscle acting to stabilise the femoral head in a deficient acetabulum
- The authors note it serves as an anatomic landmark during periacetabular osteotomy and that preoperative assessment of it aids decision-making in borderline dysplasia versus impingement
Acetabulum Fractures - Classification and Management
- Twenty-two years of experience leading the authors to conclude that perfect open reduction is the method of choice for displaced acetabular fractures
- A satisfactory outcome can be expected if the fracture reduction is perfect, and the converse also applies
- The type of fracture dictates the choice of surgical approach
- The indication for operation and the result both turn on the degree of congruence achieved between acetabulum and femoral head, classified as total, partial or apparent incongruence
- With partial incongruence a very good clinical result cannot be expected in more than 55 per cent of hips left unoperated
Subacute Femoral Compressive Neuropathy from Iliacus Compartment Haematoma
- Case report of traumatic retroperitoneal haematoma in the iliacus muscle causing delayed femoral compression neuropathy
- The authors emphasise the anatomical substrate - the iliacus compartment - as the basis for compression of the femoral nerve
- A subacute compartment syndrome, with progressive oedema, swelling and ischaemia within the iliacus compartment, is proposed as the underlying mechanism
- Early fasciotomy, with or without evacuation of the haematoma, is recommended to provide rapid decompression
- The stated aim of early decompression is to minimise the chance of permanent nerve injury
Complications of Iliac Crest Bone Graft Harvesting
- Retrospective review of 414 consecutive iliac crest bone graft procedures performed over ten years
- 41 minor complications (10 per cent) and 24 major complications (5.8 per cent) were identified
- Minor complications were superficial infection, superficial seroma and minor haematoma
- Major complications included herniation of abdominal contents through massive donor sites, vascular injury, deep infection, NEUROLOGIC INJURY, deep haematoma requiring surgery and iliac wing fracture
- The authors concluded harvesting can carry significant morbidity, reducible by preoperative planning and proper technique
Comparison of the Fascia Iliaca Compartment Block with the 3-in-1 Block in Children
- Description and prospective evaluation of a single-injection fascia iliaca compartment block in 60 paediatric patients, compared with 60 given a 3-in-1 block
- Local anaesthetic is injected immediately behind the fascia iliaca at the union of the lateral with the two medial thirds of the inguinal ligament, then forced upward by finger compression
- Adequate analgesia was obtained in more than 90 per cent of fascia iliaca blocks versus only 20 per cent of 3-in-1 blocks
- The high 3-in-1 failure rate was not due to needle misplacement, since a femoral nerve block developed in all of those patients
- The authors attribute the success to the fascia iliaca circumscribing a potential space in which the femoral, lateral cutaneous and obturator nerves run for much of their course
Prevention of Nerve Injury after Periacetabular Osteotomy
- 1760 periacetabular osteotomies performed between 1991 and 2008 at five institutions were reviewed for major sciatic or femoral nerve injury
- 36 patients (2.1 per cent) developed a major nerve deficit - a lower incidence than previously reported
- No patient or surgical risk factor was identified as associated with nerve injury
- Only 17 of the 36 recovered completely, more commonly with femoral than sciatic injuries; median time to recovery or plateau was 5.5 months (range 2 days to 24 months)
- The authors suggest exploration may be warranted if direct nerve injury is suspected