Punctate calcification within unossified epiphyseal and periarticular cartilage in infancy — a shared radiographic endpoint of peroxisomal, teratogenic, endocrine and storage disease
- Stippling is calcification within cartilage that has not yet ossified — a transient sign, typically gone by 2 to 3 years of age, so a normal radiograph at age 4 never excludes it.
- The single most useful branch point is symmetric rhizomelic shortening (peroxisomal) versus asymmetric shortening (Conradi–Hünermann, X-linked dominant). Do NOT label the rhizomelic form simply 'lethal'.
- Absent or minimal limb shortening with a flat nasal bridge and short distal phalanges points away from primary skeletal dysplasia and towards a teratogen or maternal autoimmune cause.
- Coronal clefts of the vertebral bodies on the lateral radiograph are near-specific for rhizomelic chondrodysplasia punctata type 1 in this setting.
- Congenital hypothyroidism produces epiphyseal dysgenesis, which mimics stippling but appears in ossified centres, not in unossified cartilage.
- Cervical spine stenosis, hypoplastic odontoid and atlantoaxial instability occur in CDPX1 (brachytelephalangic) and dictate anaesthetic and sporting precautions. Image them regardless of the genetic result: a negative ARSE test does not exclude the phenotype or its risks.
- A drug and pregnancy history — vitamin K antagonists, phenytoin, alcohol, hyperemesis with vitamin K deficiency — is as diagnostic as any laboratory test. For vitamin K antagonists, calibrate the story: the risk depends on how long exposure continued.
- Ask about the MOTHER'S health, not only her medication: maternal autoimmune disease with anti-Ro and anti-La antibodies reproduces the same phenotype. Send a maternal antibody screen and a neonatal ECG.
- “Say the words: 'multiple punctate calcific densities within the unossified cartilage of the epiphyses and periarticular soft tissues'.
- “Look at the lateral spine and the hands before you commit — coronal clefts and short distal phalanges do most of the discriminating.
- “Cataracts plus ichthyosis plus asymmetric shortening in a girl equals Conradi–Hünermann until disproven.
- “Stippling in an infant with hypotonia, seizures, large fontanelle and hepatomegaly is Zellweger spectrum, not a dysplasia.
- “Any child with stippled epiphyses needs a maternal history, an eye examination and a peroxisomal screen before the orthopaedic plan.
Recognising the Pattern
Definition. Stippled epiphyses describes multiple small, round or irregular punctate calcific densities lying within cartilage that has not yet ossified: the epiphyseal anlage, the carpus and tarsus, the periarticular soft tissues, the vertebral end plates, the tracheal and laryngeal cartilage, and the pubic and ischial cartilage. Stippled epiphyses is the sign; chondrodysplasia punctata is the correct radiological term for the condition group.
Confirming the sign is genuine. Satisfy yourself on each of these before naming a cause.
- The densities lie within cartilage, not within an ossification centre. In a neonate's distal femoral epiphysis, stippling sits where the secondary centre should be, as a cloud of dots rather than a single homogeneous centre.
- They are present at several sites. An isolated finding at one joint is far more likely to be artefact or normal irregular ossification; genuine chondrodysplasia punctata affects several regions, typically the hips, knees, shoulders, carpus, tarsus, spine and larynx.
- The child is the right age. Stippling is a neonatal and infantile sign, most florid at birth, fading over the first two to three years as the cartilage ossifies and sometimes leaving a permanently irregular or flattened epiphysis. A normal later film therefore proves nothing: a four-year-old with unexplained asymmetric limb shortening, cataracts and ichthyosis still has Conradi–Hünermann, so go back and find the neonatal films.
- The lateral spine agrees. Coronal clefts (a vertical lucent line splitting the vertebral body in the coronal plane) and stippling of the vertebral end plates strongly support a true dysplasia.
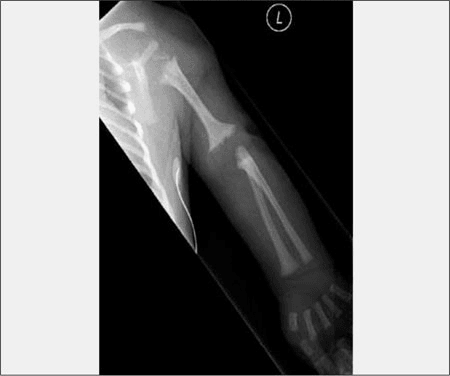
How to say it out loud. "This is an anteroposterior radiograph of the pelvis and lower limbs of a neonate. There are multiple punctate calcific densities within the unossified cartilage of the proximal femoral, distal femoral and proximal tibial epiphyses, and within the periarticular soft tissues around the hips. The appearances are those of stippled epiphyses, or chondrodysplasia punctata. I would like to review the lateral spine for coronal clefts, the hands for distal phalangeal shortening, and the humeri and femora to determine whether limb shortening is present and whether it is symmetric."
What mimics the pattern. Each of these produces irregular or calcified densities that are not stippling.
- Normal irregular ossification. The distal femoral epiphysis in particular ossifies irregularly in some normal infants. The fragments are larger, confined to the ossification centre, and unaccompanied by soft tissue or vertebral stippling.
- Multiple epiphyseal dysplasia. Irregular, fragmented, delayed epiphyses, but presenting at 3 to 10 years with gait pain, not in the neonate, and with no soft tissue calcification.
- Congenital hypothyroidism (epiphyseal dysgenesis). Fragmented, moth-eaten ossification within centres that have already ossified, whereas stippling lies in cartilage that has not and is present at or shortly after birth. Where the calcification sits is the distinction; get it wrong and you order genetics instead of thyroid function.
- Meconium or dystrophic soft tissue calcification, and calcified cephalhaematoma or intrauterine infection foci. These are extra-articular and do not respect cartilage anatomy.
- Chondrocalcinosis in an older child. Calcification of formed hyaline cartilage or meniscus: a different tissue and a different age group.
Next Investigation
The Orthopaedic Burden
The cervical spine. Brachytelephalangic chondrodysplasia punctata and warfarin embryopathy cause cervical canal stenosis, hypoplastic odontoid and atlantoaxial instability. Image the cervical spine in every brachytelephalangic or vitamin-K-antagonist-exposed child before any anaesthetic.
Cord injury on intubation or from minor trauma is the real-world catastrophe hidden behind an apparently benign hand radiograph.
Do not wait for the genetics. The cervical imaging is not contingent on a molecular diagnosis. Only 58 per cent of males with the brachytelephalangic phenotype have a detectable ARSE mutation, and around 40 per cent have neither that nor any identified maternal cause; the stenosis and hypoplastic odontoid are present regardless.
Surveillance before reconstruction. Document scoliosis, coxa vara, limb length discrepancy, contractures and cataract status. In infants likely to survive, and most now do, the orthopaedic plan is surveillance of the spine and limb lengths rather than early reconstruction.
The Differential
Each cause is listed with the feature that separates it and the test that confirms it.
- Typical age / setting
- Neonate; autosomal recessive
- Discriminating feature
- Symmetric, severe rhizomelic shortening of humeri and femora with coronal vertebral clefts, bilateral cataracts, profound developmental delay and contractures
- What confirms it
- Plasma phytanic acid raised, erythrocyte plasmalogens reduced; PEX7 sequencing
- Typical age / setting
- Neonate; hypotonia, seizures, large anterior fontanelle, hepatomegaly
- Discriminating feature
- Stippling concentrated in patella and acetabulum with dysmorphic high forehead and flat orbital ridges — the neurological picture dominates, not the limbs
- What confirms it
- Very-long-chain fatty acids raised; renal cortical cysts on ultrasound; PEX gene panel
- Typical age / setting
- Neonate; maternal anticoagulation in weeks 6 to 12 of gestation
- Discriminating feature
- Nasal and midface hypoplasia with a depressed bridge and choanal narrowing plus short distal phalanges; limbs relatively preserved
- What confirms it
- Maternal drug history is diagnostic; cervical spine imaging for stenosis
- Typical age / setting
- Male neonate; X-linked recessive
- Discriminating feature
- Strikingly short distal phalanges with nasomaxillary hypoplasia and cervical canal stenosis or hypoplastic odontoid; stature usually near normal
- What confirms it
- Plasma arylsulfatase E activity, ARSE sequencing; flexion-extension cervical views and MRI
- Typical age / setting
- Female neonate to infant; X-linked dominant, male-lethal
- Discriminating feature
- Asymmetric limb shortening with ichthyosiform erythroderma following Blaschko lines, patchy cicatricial alopecia and sectorial or asymmetric cataracts
- What confirms it
- Raised 8-dehydrocholesterol and 8(9)-cholestenol; EBP sequencing; skin biopsy
- Typical age / setting
- Infant; missed or untreated newborn screening; endemic iodine deficiency
- Discriminating feature
- Fragmented ossification within a formed centre with markedly delayed bone age, large fontanelles including the posterior, and wormian bones
- What confirms it
- TSH raised with low free T4; response to levothyroxine
- Typical age / setting
- Neonate of a mother with known or occult connective tissue disease
- Discriminating feature
- Stippling with nasal hypoplasia in an infant who may also have congenital heart block or neonatal lupus rash; skeletal features mild and resolve
- What confirms it
- Maternal anti-Ro and anti-La antibodies; neonatal ECG
- Typical age / setting
- Neonate; documented first-trimester exposure
- Discriminating feature
- Short palpebral fissures, smooth philtrum, thin upper lip and microcephaly accompany mild stippling; distal phalangeal and nail hypoplasia with phenytoin
- What confirms it
- Exposure history plus the facial phenotype; no peroxisomal biochemical abnormality
- Typical age / setting
- Neonate; mother with prolonged vomiting or bowel disease in the first trimester
- Discriminating feature
- Warfarin-embryopathy phenotype with no anticoagulant exposure; nasal hypoplasia and stippling in an otherwise well infant
- What confirms it
- Maternal nutritional and obstetric history; prolonged maternal prothrombin time if tested during pregnancy
- Typical age / setting
- Neonate with recognised aneuploidy phenotype
- Discriminating feature
- Stippling is incidental and mild; overshadowed by clenched hands with overlapping digits and rocker-bottom feet (18) or by hypotonia, 11 ribs and iliac flaring (21)
- What confirms it
- Karyotype or microarray
- Typical age / setting
- Neonate; autosomal recessive cholesterol synthesis defect
- Discriminating feature
- Two-three toe syndactyly, postaxial polydactyly, microcephaly, cleft palate and genital ambiguity in a 46,XY infant, with only mild stippling
- What confirms it
- Raised serum 7-dehydrocholesterol; DHCR7 sequencing
- Typical age / setting
- Neonate to early infancy; storage phenotype
- Discriminating feature
- Coarse facies, gingival hypertrophy, hepatosplenomegaly with periosteal cloaking and dysostosis multiplex accompanying the stippling
- What confirms it
- Enzyme assay (beta-galactosidase; GlcNAc-phosphotransferase) and raised plasma lysosomal enzymes in I-cell
- Typical age / setting
- Female infant; X-linked dominant
- Discriminating feature
- Strictly unilateral ichthyosiform naevus and ipsilateral limb hypoplasia or absence with a sharp midline demarcation — stippling on the affected side only
- What confirms it
- NSDHL sequencing; skin biopsy of the naevus
- Typical age / setting
- Neonate; small for gestational age with hepatosplenomegaly, or an isolated benign form
- Discriminating feature
- Rubella gives longitudinal metaphyseal celery-stalk striations rather than true cartilaginous stippling; Sheffield type shows stippling limited to the calcaneus and tarsus with a normal outcome
- What confirms it
- TORCH serology and urine CMV PCR; in Sheffield type, resolution on follow-up radiographs with normal biochemistry
Counsel rhizomelic disease with the real figures. Older texts call rhizomelic chondrodysplasia punctata type 1 lethal in infancy. It is serious but not reliably fatal: in the largest natural history series 90 per cent reached one year and 50 per cent reached six, with death most often from a respiratory cause, so the conversation with parents is not a terminal one.
Narrowing It Down
- 11. Is the stippling real and multifocal?
Confirm punctate densities within UNOSSIFIED cartilage at more than one site, and obtain a lateral spine, hands and lower limb views.
A single irregular ossification centre with no soft tissue or vertebral involvement is normal variation and needs no work-up. Genuine multifocal stippling in a neonate always earns a metabolic and maternal history.
- 22. Is there limb shortening, and is it symmetric?
Compare humeri and femora against forearms and legs, and look at the lateral spine for coronal clefts.
Symmetric severe rhizomelic shortening points to rhizomelic chondrodysplasia punctata type 1, and coronal clefts make it near-specific. Asymmetric shortening, often with hemivertebrae and scoliosis, points to Conradi–Hünermann. Little or no shortening shifts the differential towards teratogens, maternal autoimmune disease and aneuploidy.
- 33. What do the hands and midface show?
Look specifically at the distal phalanges and the nasal bridge before anything else.
Short distal phalanges (brachytelephalangy) with nasomaxillary hypoplasia and a depressed nasal bridge define the brachytelephalangic group: CDPX1, vitamin K antagonist embryopathy, maternal vitamin K deficiency and maternal anti-Ro disease. This one look separates a large, survivable subgroup from the rhizomelic disorders.
- 44. What is the maternal and drug history — and how long did the exposure last?
Ask about vitamin K antagonists and record the exact GESTATIONAL WEEK they were stopped, plus anticonvulsants, alcohol, severe hyperemesis or malabsorption, and any maternal rash, arthralgia, sicca symptoms or known connective tissue disease.
Warfarin embryopathy and maternal vitamin K deficiency reproduce the CDPX1 radiograph almost exactly, so a missed history loses the diagnosis and misdirects genetic counselling for the next pregnancy. For vitamin K antagonists the classic window is weeks 6 to 12, but duration is the variable, not exposure itself: in 408 first-trimester exposures there was NO typical embryopathy, stopping by five completed weeks left the malformation rate indistinguishable from background (2.4 versus 2.3 per cent), and beyond seven weeks it rose fivefold. A positive maternal antibody screen converts a genetic work-up into a different conversation, and the mother may not yet know she has lupus or Sjögren.
- 55. Are there skin, eye or neurological findings?
Examine the skin in daylight for Blaschko-line changes, arrange formal ophthalmology, and assess tone, fontanelle and liver.
Ichthyosis along Blaschko lines with patchy alopecia equals CDPX2; a strictly unilateral naevus with ipsilateral limb hypoplasia equals CHILD syndrome. Cataracts occur in both CDPX2 and rhizomelic disease and were present in EVERY infant in the largest rhizomelic series, so ophthalmology is not optional. Hypotonia, seizures, hepatomegaly and a large fontanelle indicate Zellweger spectrum; coarse facies with organomegaly indicates a storage disorder.
- 66. Is there a systemic explanation outside the skeleton?
Check the newborn thyroid screen, send a karyotype or microarray if dysmorphic, and consider congenital infection in a growth-restricted infant with hepatosplenomegaly.
Confirmed congenital hypothyroidism is treated, not genotyped, and the radiographic abnormality resolves with levothyroxine.
MCQ Practice Points
Q: Parents of a neonate with rhizomelic chondrodysplasia punctata type 1 ask how long their child will live. What do you tell them?
A: Not what the older textbooks say. In the largest natural history series — 35 systematically studied individuals plus 62 literature cases — 90 per cent reached one year and 50 per cent reached six, with death most often from a respiratory cause; the authors state explicitly that survival is greater than previously reported. That changes the whole conversation: respiratory care determines survival, every infant needs ophthalmology because bilateral cataracts were universal, and the orthopaedic remit becomes long-term surveillance of contractures rather than palliation. Caveat worth stating: the cohort was recruited through support organisations, which under-samples neonatal deaths and biases survival upwards.
Q: During which gestational window does vitamin K antagonist exposure produce chondrodysplasia punctata, and how large is the risk?
A: Classically the sixth to twelfth weeks — but the modern number reframes it. In a prospective cohort of 408 first-trimester vitamin K antagonist pregnancies against 1,642 controls, NOT ONE typical embryopathy occurred. Major malformations overall were increased (7.4 versus 2.3 per cent, OR 2.14), and the effect was almost entirely a function of duration: stopping by five completed gestational weeks gave 2.4 versus 2.3 per cent (OR 1.07 — no excess at all), while continuing beyond seven weeks gave 10.8 per cent (OR 5.18). Spontaneous abortion rose from 17.5 to 38 per cent. So the intervention is early pregnancy recognition and immediate conversion to heparin, and the classic phenotype is rarer than its textbook prominence suggests. Caveat: the drug studied was phenprocoumon, and women who stopped early differ in disease severity from those who could not.
Q: A boy has brachytelephalangic chondrodysplasia punctata. ARSE sequencing is negative. What now?
A: Continue to manage the phenotype. In a prospective series of 29 male probands, ARSE mutations were found in only 58 per cent, and around 40 per cent had neither a detectable mutation nor any identified maternal cause — so the older assumption that unexplained cases are all maternal phenocopies (vitamin K deficiency, autoimmune disease) is not supported. The cervical canal stenosis, hypoplastic odontoid and airway risk are present whatever the genotype, so cervical imaging before anaesthesia and sporting advice proceed unchanged. Note the era caveat: sequencing in 2008–2010 would have missed deep intronic and large-deletion alleles that current methods detect.
Q: An infant has stippling with nasal hypoplasia, no limb shortening and no drug exposure. What maternal investigation is indicated?
A: A maternal autoimmune screen — anti-Ro and anti-La antibodies, looking for lupus or Sjögren syndrome, which reproduce the brachytelephalangic phenotype and in which the mother is sometimes still undiagnosed. Also check maternal vitamin K status and take a malabsorption and hyperemesis history. Add a neonatal ECG for congenital heart block. The association is established from case reports only, so it has no quantified risk — but the tests are cheap and the maternal diagnosis matters in its own right.
Q: A neonate has symmetric rhizomelic shortening, stippled epiphyses and coronal vertebral clefts. Which investigation is most likely to confirm the diagnosis?
A: Plasma phytanic acid and erythrocyte plasmalogens. This combination indicates rhizomelic chondrodysplasia punctata type 1, a peroxisomal disorder of PEX7 — phytanic acid raised, plasmalogens reduced. A sterol profile would be the answer for Conradi–Hünermann, and thyroid function for epiphyseal dysgenesis. Classify by pathway and the test follows.
Q: Which single radiographic feature best separates the brachytelephalangic group from rhizomelic chondrodysplasia punctata?
A: Short distal phalanges with relatively preserved long bone lengths. Rhizomelic disease shortens the humeri and femora severely and symmetrically; the brachytelephalangic phenotypes (CDPX1, vitamin K antagonist embryopathy, maternal vitamin K deficiency, maternal anti-Ro disease) shorten the distal phalanges and hypoplase the midface while stature remains near normal.
Q: A female infant has asymmetric limb shortening, stippling, hemivertebrae and whorled ichthyosis. What is the inheritance pattern?
A: X-linked dominant with male lethality (Conradi–Hünermann–Happle, EBP). The asymmetry of skeletal and cutaneous involvement reflects random X-inactivation. Surviving affected males are usually mosaic or have an additional X chromosome.
Q: A four-year-old is referred with limb length discrepancy and cataracts. Radiographs show no stippling. Does this exclude chondrodysplasia punctata?
A: No. Stippling is a transient sign that resolves as the cartilage ossifies, typically within the first two to three years, sometimes leaving flattened or irregular epiphyses. The neonatal radiographs must be retrieved, and biochemical or genetic testing pursued on clinical grounds.
CHILD-ZCauses of Stippled Epiphyses
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are shown this radiograph of a neonate: there are dense punctate calcifications throughout the proximal femoral, distal femoral and humeral epiphyseal cartilage, with markedly short and broad humeri and femora. The lateral spine shows vertical lucencies splitting the vertebral bodies. Describe and give your differential.”
“You are shown this hand radiograph of a male neonate showing conspicuously short distal phalanges, alongside a lateral skull and facial view demonstrating nasal hypoplasia with a depressed bridge. There is punctate calcification in the carpal and tarsal cartilage. Limb lengths are near normal. What is your approach?”
“You are shown radiographs of a female infant with stippled epiphyses. The right femur is appreciably shorter than the left, there are two hemivertebrae in the thoracic spine, and the mother reports scaly whorled skin lesions that followed streaky lines on the trunk and have now faded to areas of hair loss. What is the diagnosis and what is the orthopaedic plan?”
The Sign
- Punctate calcification within unossified cartilage: epiphyses, carpus, tarsus, larynx, vertebral end plates, periarticular soft tissue
- Neonatal and infantile; resolves by roughly 2 to 3 years leaving flattened or irregular epiphyses
- Must be multifocal — a single irregular ossification centre is normal variation
- Viva phrase: 'multiple punctate calcific densities within unossified epiphyseal cartilage — chondrodysplasia punctata'
The Three Branch Points
- Symmetric rhizomelic shortening plus coronal clefts equals rhizomelic CDP type 1 (peroxisomal, poor prognosis)
- Asymmetric shortening plus Blaschko-line ichthyosis equals Conradi–Hünermann, CDPX2 (X-linked dominant, survivable)
- Brachytelephalangy plus nasomaxillary hypoplasia equals CDPX1, warfarin, maternal vitamin K deficiency or maternal anti-Ro
Non-Skeletal Causes Not to Miss
- Congenital hypothyroidism — the only fully treatable cause; check newborn screening
- Zellweger spectrum — hypotonia, seizures, hepatomegaly, large fontanelle, renal cortical cysts
- Trisomy 18 and 21, Smith–Lemli–Opitz — stippling incidental to the dysmorphic phenotype
- GM1 gangliosidosis and I-cell disease — coarse facies, organomegaly, dysostosis multiplex
Investigations
- Skeletal survey including lateral spine and both hands first
- Peroxisomal screen: very-long-chain fatty acids, phytanic acid, plasmalogens
- Sterol profile: 8-dehydrocholesterol (CDPX2), 7-dehydrocholesterol (Smith–Lemli–Opitz)
- Thyroid function; maternal anti-Ro and anti-La with neonatal ECG
- Cervical spine flexion-extension views plus MRI in brachytelephalangic phenotypes
Orthopaedic Consequences
- Cervical stenosis and atlantoaxial instability in CDPX1 and warfarin embryopathy — pre-anaesthetic imaging mandatory
- Congenital scoliosis from hemivertebrae in CDPX2 — serial surveillance, never treat as idiopathic
- Limb length discrepancy from asymmetric physeal damage — scanograms and timed epiphysiodesis or lengthening
- Cataracts require early ophthalmology referral to prevent deprivation amblyopia
- Tracheal and laryngeal cartilage calcification may cause airway compromise
Counselling Points
- Rhizomelic CDP type 1: autosomal recessive, one-in-four recurrence, prenatal diagnosis available
- CDPX2: X-linked dominant, male-lethal, high variability between affected females
- CDPX1: X-linked recessive, affected males, carrier mothers
- Warfarin embryopathy: no genetic recurrence risk — convert to low molecular weight heparin before conception
Evidence Base
Natural History of Rhizomelic Chondrodysplasia Punctata
- 35 previously unreported affected individuals studied systematically, plus review of 62 literature cases for survival and cause of death
- SURVIVAL IS SUBSTANTIALLY BETTER THAN PREVIOUSLY REPORTED: 90 PER CENT REACHED ONE YEAR and 50 PER CENT REACHED SIX YEARS
- Death was most often from a respiratory cause
- The phenotype is uniform in its core features: ALL infants had joint contractures, bilateral cataracts, and severe growth and psychomotor delay
- The authors set out health supervision recommendations and explicit guidance for parental counselling
Pregnancy Outcome of First Trimester Exposure to the Vitamin K Antagonist Phenprocoumon Depends on Duration of Treatment
- Prospective observational cohort from a national teratology information service: 408 first-trimester vitamin K antagonist exposures against 1,642 unexposed pregnancies
- THERE WAS NO TYPICAL WARFARIN EMBRYOPATHY IN THE ENTIRE EXPOSED COHORT OF 408
- Major birth defects overall were increased - 7.4 per cent against 2.3 per cent (adjusted odds ratio 2.14, 95 per cent CI 1.4 to 3.4)
- THE RISK IS EXQUISITELY TIME-DEPENDENT: stopping by five completed gestational weeks gave 2.4 per cent against 2.3 per cent (OR 1.07, CI 0.2 to 3.6) - NO EXCESS AT ALL. Continuing beyond seven weeks gave 10.8 per cent (OR 5.18, CI 2.0 to 11.6)
- Spontaneous abortion 38.0 per cent against 17.5 per cent (adjusted hazard ratio 2.9), rising 1.12-fold per additional exposure week
A Prospective Study of Brachytelephalangic Chondrodysplasia Punctata: Identification of Arylsulfatase E Mutations and Determination of Potential Phenocopies
- Prospective testing programme 2008-2010; 29 male probands with brachytelephalangic chondrodysplasia punctata, with functional analysis of every novel allele in COS cells
- ARSE mutations were found in 17 of 29 (58 PER CENT) - better than the historical 50 per cent but still leaving a large unexplained group
- All mutant alleles had negligible arylsulfatase E activity, confirming CDPX1 is a loss-of-function disorder
- AROUND 40 PER CENT OF MALES HAD NEITHER A DETECTABLE ARSE MUTATION NOR ANY KNOWN MATERNAL CAUSE - maternal aetiologies were not reported in most patients
- There were no obvious genotype-phenotype correlations among those with mutations
Fetal Chondrodysplasia Punctata Associated with Maternal Autoimmune Diseases: A Review
- Review from a paediatric clinical genetics and prenatal diagnosis programme collating every case reported in English to date
- Frames chondrodysplasia punctata as an aetiologically HETEROGENEOUS endpoint rather than a diagnosis
- Fetal causes listed: chromosome abnormalities, peroxisomal disorders, lysosomal storage disorders, cholesterol synthesis defects and abnormal vitamin K metabolism
- Maternal causes listed: severe malabsorption, teratogen exposure, and autoimmune disease
- The maternal autoimmune association was first reported by Curry and by Costa in 1993 and expanded by Chitayat in 2010
Chondrodysplasia Punctata: A Clinical Diagnostic and Radiological Review
- Review by clinical genetics and paediatric radiology authors covering the full range of disorders producing this radiographic pattern
- Groups the causes as inborn errors of metabolism involving PEROXISOMAL and CHOLESTEROL pathways, embryopathy, and chromosomal abnormality
- Notes that earlier classifications were morphological and that elucidation of the biochemical and molecular basis produced a NEW AETIOLOGICAL classification
- Provides the clinical and radiographic findings for each type alongside the aetiological grouping
- Sets out an investigative guideline for reaching an exact diagnosis in a new case