Limb-sparing pelvic resection: zone dictates reconstruction; complications dominate outcome
- Internal hemipelvectomy preserves the limb; external (hindquarter) amputation removes it — the choice hinges on neurovascular involvement and soft-tissue coverage, not tumour size alone
- Biopsy must be along a tract resectable en bloc with the specimen, placed by or after discussion with the resecting surgeon
- Zone I and III resections often need no skeletal reconstruction; zone II demands a decision between biological, endoprosthetic and pseudarthrosis solutions
- Deep infection 20 to 40 percent is the dominant complication and the most common reason endoprosthetic reconstructions fail
- Margins trump reconstruction sophistication: an elegant custom implant after a contaminated margin is an oncological failure
- “Hip transposition (Friedel) gives surprisingly good MSTS scores (often 60 to 70 percent) with the lowest implant-related complication burden — never dismiss it as a 'lesser' option
- “Saddle prosthesis is essentially historic: high rates of migration, infection and poor function
- “Zone III resections threaten the bladder, urethra, spermatic cord/round ligament and obturator neurovascular bundle — catheterise and consider ureteric stents
- “Sciatic nerve encasement plus femoral vessel involvement flips the plan to external hemipelvectomy
Definitions, Indications and Patient Selection
What the operation is. Internal hemipelvectomy is en bloc resection of part or all of the innominate bone with the lower limb preserved. External hemipelvectomy (hindquarter amputation) removes limb and hemipelvis together and is covered in the hindquarter amputation topic. The choice between them hinges on neurovascular involvement and soft-tissue coverage, and the resection is planned by zone, not by tumour size alone.
Who is a candidate. The principal indications:
- Primary bone sarcoma of the pelvis: chondrosarcoma (the most common pelvic primary in adults, chemo- and radio-resistant, so the surgical margin is everything), Ewing sarcoma after neoadjuvant chemotherapy, and osteosarcoma
- Selected soft-tissue sarcomas invading the pelvis
- Carefully selected solitary metastases or locally aggressive benign lesions (giant cell tumour) where curettage is inadequate
- Occasionally infection or a failed prior reconstruction, as a salvage setting
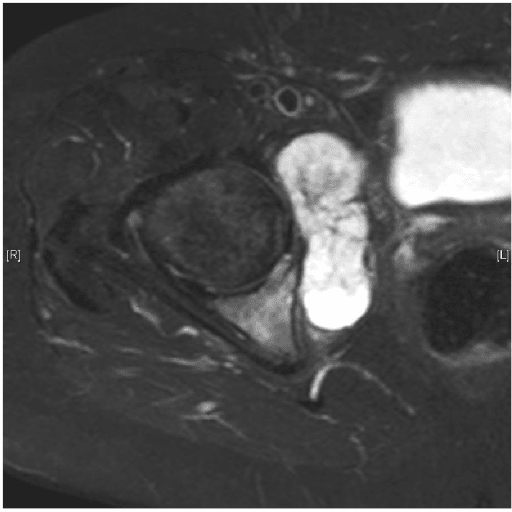
The margin comes first. Margin quality drives outcome, particularly in chondrosarcoma, where adjuvant therapy will not rescue a contaminated margin. The resection planes are planned on cross-sectional imaging, including whether the sacrum, femoral head or adjacent viscera must be included, and if no wide margin is possible with the limb in situ the operation is an external hemipelvectomy.
What limb salvage requires. All of the following must be satisfied:
- An achievable oncological margin (wide for sarcoma) with the limb retained
- A preservable femoral neurovascular bundle and at least one major nerve to the limb: classically the sciatic. Loss of the femoral nerve alone is compatible with useful function with a knee-stabilising brace
- A soft-tissue envelope adequate for closure, with or without pedicled or free flaps; involve plastic surgery early and map prior incisions and biopsy tracts
- Physiology that tolerates a long, high-blood-loss procedure, judged by anaesthetic and critical care assessment, with cell salvage and major transfusion planning
- A motivated patient who understands the complication rates and the prolonged rehabilitation
When salvage is the wrong answer. A salvaged limb that is insensate, ischaemic and painful is worse than a well-rehabilitated amputation, and marginal physiology or an unmotivated patient shifts the balance towards amputation. When the limb is taken, posterior or anterior flap coverage is planned according to which vessels remain uninvolved, and prosthetic and wheelchair rehabilitation is planned from the outset.
Sciatic nerve encasement combined with femoral vessel or nerve involvement, fungating or infected tumour, prior contaminating surgery/biopsy through all flap options, or tumour progression through chemoradiotherapy with unreconstructable soft tissues — these favour external hemipelvectomy.
Consent for both. The final decision may be intraoperative, once the resection planes and nerves are directly inspected, so the patient is consented for both internal and external hemipelvectomy preoperatively and the patient, family and rehabilitation team are briefed on either outcome. Rehabilitation, surveillance imaging and psychological support are arranged in advance; nobody wakes to an unexpected amputation.
Enneking-Dunham Zones and What Each Demands
The language. The Enneking-Dunham classification (JBJS 1978) is the universal language for pelvic resections, and zone dictates both technical difficulty and reconstruction. Combined resections are common: periacetabular chondrosarcoma frequently requires a zone I plus II resection, with the osteotomy through the ilium and the pubic root, or a zone II plus III resection. Always describe a resection by its zones in the exam.
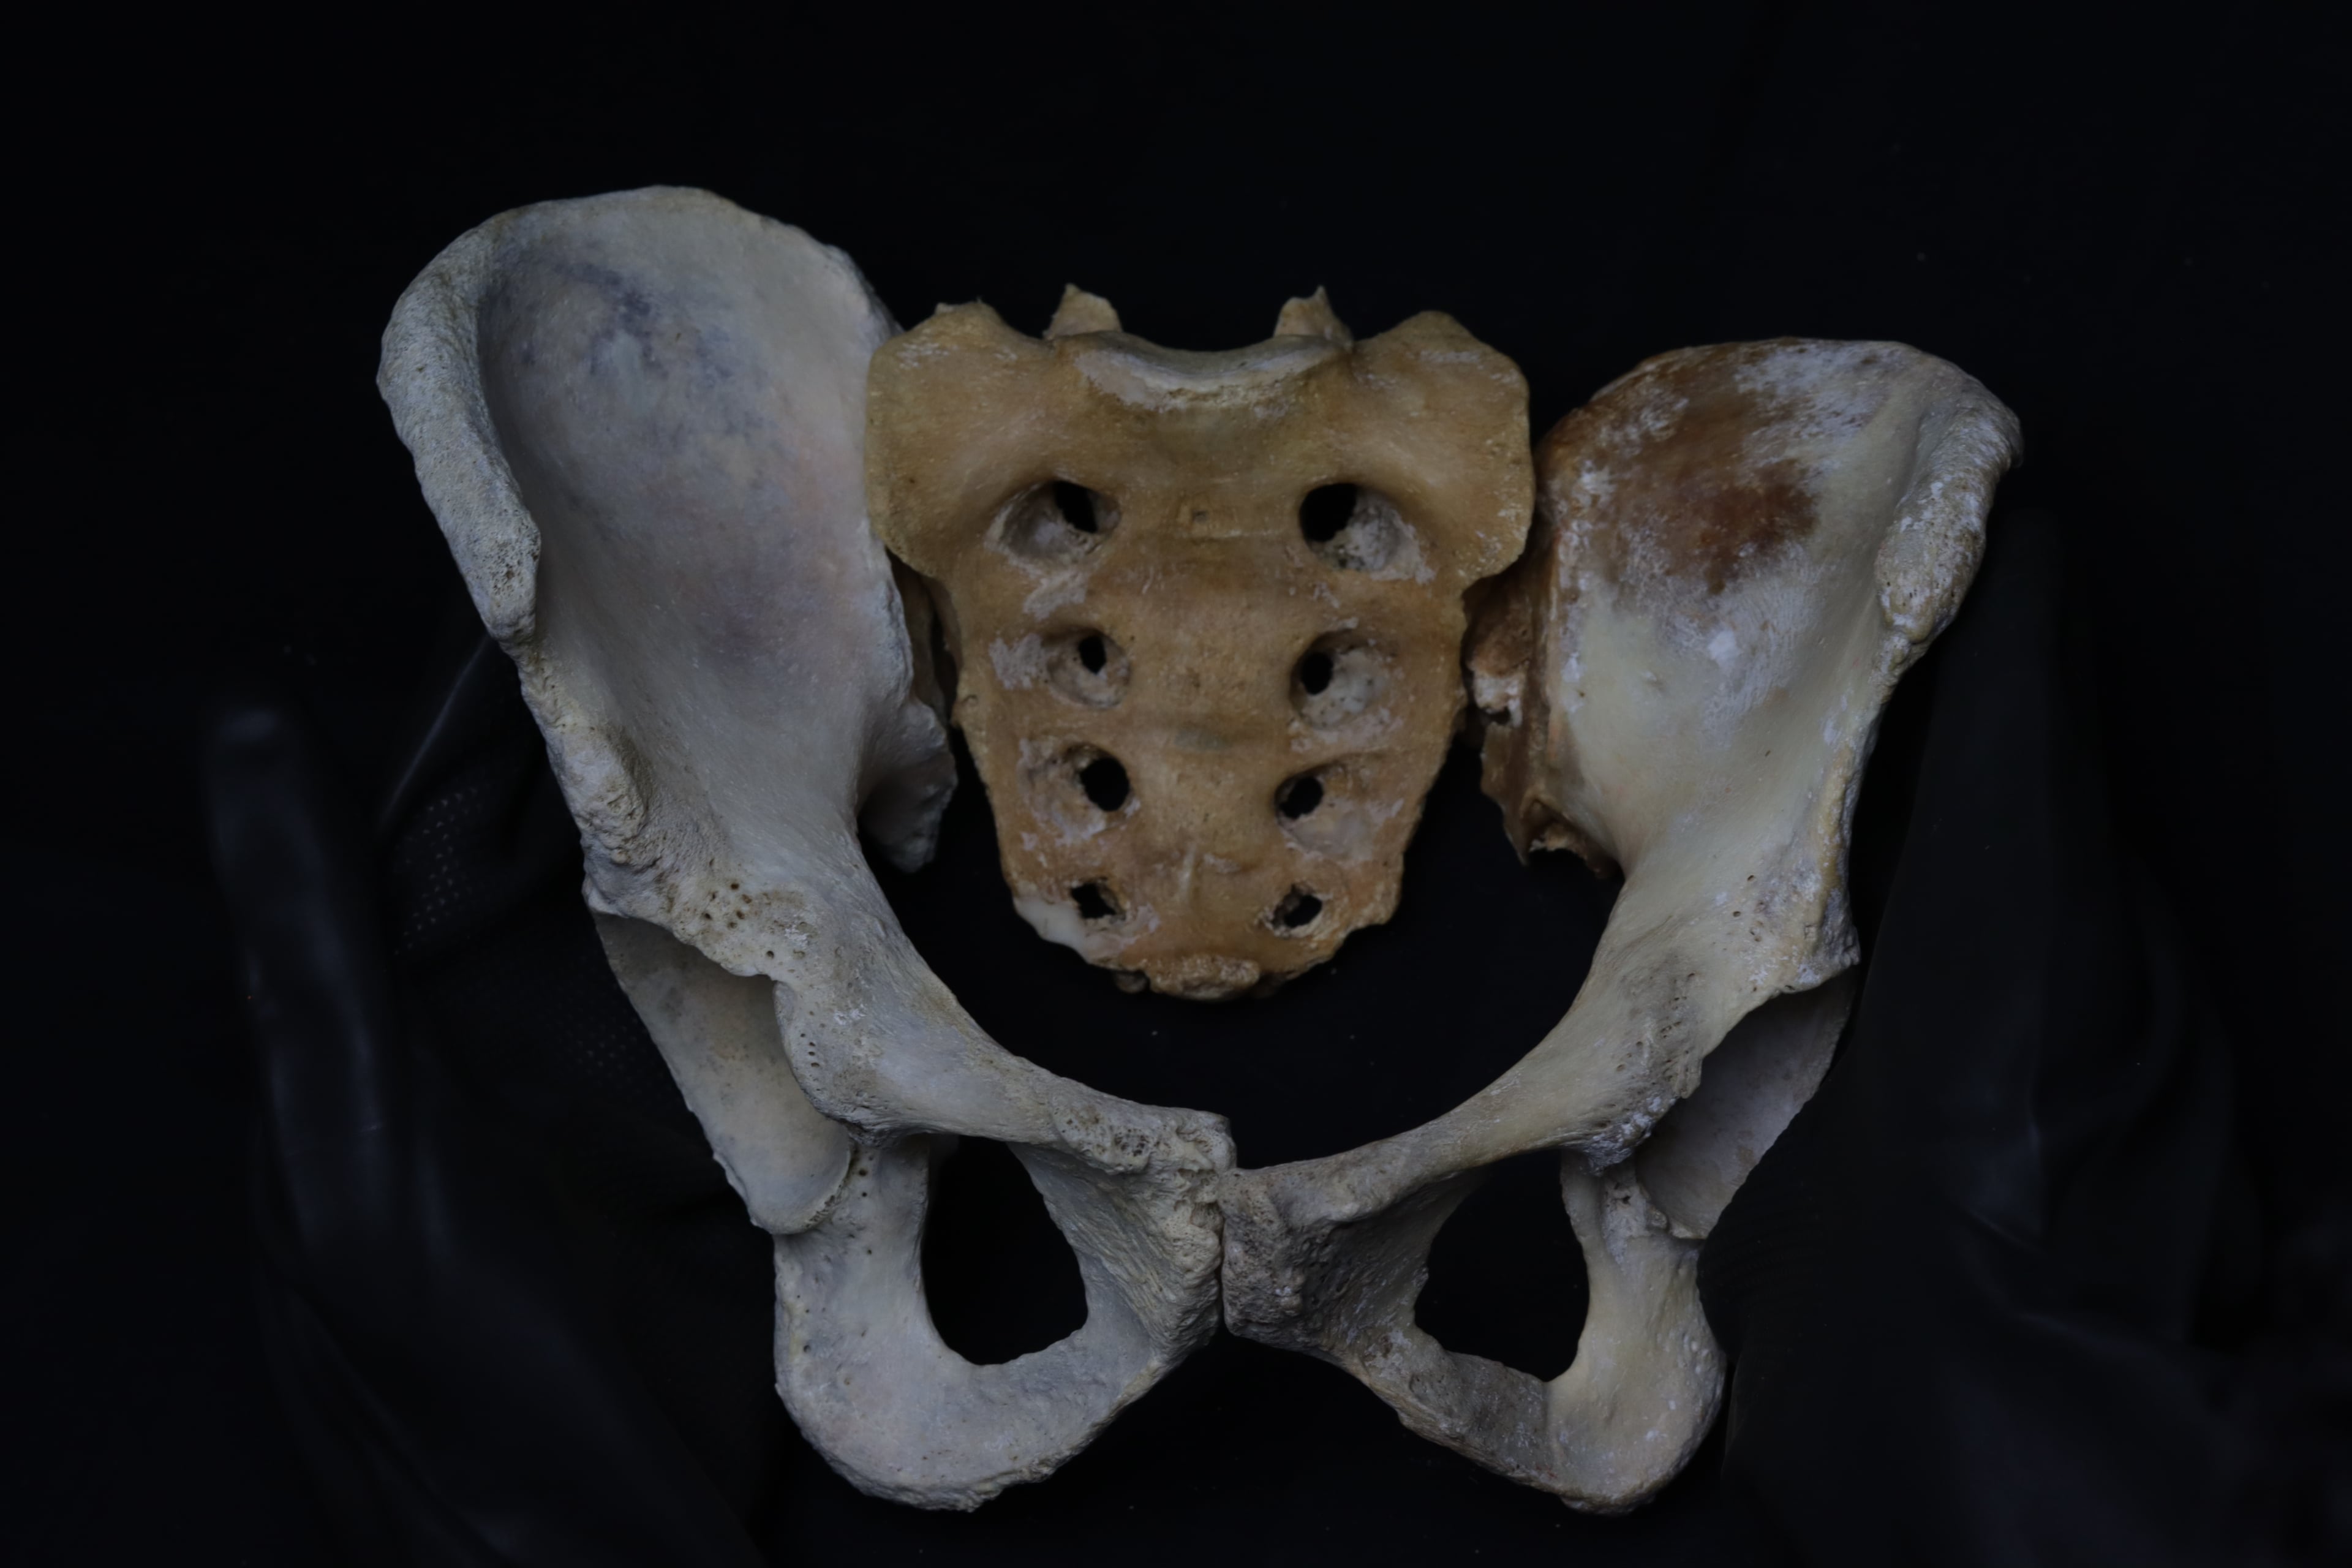
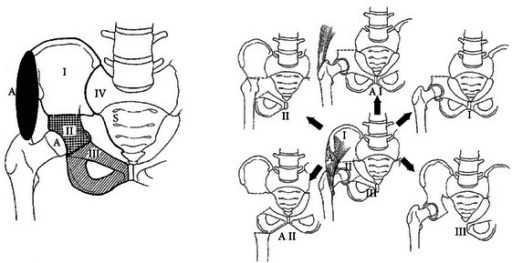
- Bone resected
- Iliac wing between the SI joint and supra-acetabular bone
- Key at-risk structures
- Superior gluteal neurovascular bundle, L5 nerve root, SI joint
- Reconstruction
- None required if a bone bridge remains; iliosacral bar or screws, with or without vascularised fibula, if the posterior ring is discontinuous
- Aftercare emphasis
- Protect the posterior ring if discontinuity was accepted; abductor rehabilitation and gait retraining
- Bone resected
- Acetabulum plus adjacent ilium, pubis and ischium
- Key at-risk structures
- Femoral neurovascular bundle, sciatic nerve, obturator bundle, hip abductors
- Reconstruction
- Mandatory for hip function: hip transposition, ice-cream-cone prosthesis, custom (patient-specific) implant, allograft or allograft-prosthetic composite, or arthrodesis
- Aftercare emphasis
- Highest complication burden — dislocation, infection and implant failure; protected weight-bearing and abductor-sparing precautions
- Bone resected
- Pubic rami and/or ischium
- Key at-risk structures
- Bladder, urethra, corona mortis, obturator bundle, spermatic cord
- Reconstruction
- No skeletal reconstruction needed — the ring stays load-bearing through the intact acetabulum; repair the pelvic floor and defect with mesh or flap
- Aftercare emphasis
- Watch for hernia through the soft-tissue defect and urogenital injury; early mobilisation is usually tolerated
- Bone resected
- Resection crosses the SI joint into the sacral ala
- Key at-risk structures
- Lumbosacral trunk, sacral roots, iliac veins
- Reconstruction
- Spinopelvic (lumbopelvic) fixation, with or without fibula strut, if the posterior column of the ring is lost
- Aftercare emphasis
- Union of the lumbopelvic construct and neurological monitoring of sacral roots (bowel, bladder, plantarflexion) drive rehabilitation
- Bone resected
- Periacetabular disease extending into the iliac wing or the pubic root
- Key at-risk structures
- Cumulative — sum of the constituent zones
- Reconstruction
- Reconstruction is dictated by the periacetabular component; osteotomies pass through the ilium and the pubic root
- Aftercare emphasis
- Describe the resection by its constituent zones
Workup and Planning
Staging. Local staging is a contrast MRI of the whole pelvis: intraosseous and extraosseous extent, the relationship to the iliac vessels, the sciatic and femoral nerves, the SI joint, the hip joint and the bladder and rectum. It is the study that defines the osteotomy planes. The rest of the staging:
- CT chest for pulmonary staging, because bone sarcomas metastasise to lung
- CT pelvis for cortical detail and matrix mineralisation, and as the dataset for navigation or 3D-printed cutting guides and custom implants
- Whole-body staging with bone scan or FDG-PET according to tumour type; PET is valuable for Ewing response assessment
- Bloods, with alkaline phosphatase and LDH where relevant, and fertility and psychology referral in young patients
Biopsy. An image-guided core needle biopsy at the treating sarcoma centre, along a tract agreed with the resecting surgeon. The tract must lie within the planned incision and be excisable en bloc with the specimen: a transgluteal or posterior biopsy of a periacetabular tumour can contaminate the flaps needed for closure and convert a limb-sparing case into an amputation, and the needle should not cross intermuscular planes or enter the joint. Mark the entry site by tattoo or photograph so that it is excised at resection.
Sequencing. Discuss at the sarcoma MDT before definitive surgery. Osteosarcoma and Ewing sarcoma receive neoadjuvant chemotherapy first; chondrosarcoma proceeds straight to surgery.
Operative planning. Virtual surgical planning on fused CT-MRI defines the osteotomies with a planned margin, commonly 5 to 10 millimetres beyond the MRI-defined tumour plus a soft-tissue cuff, and patient-specific cutting guides or computer navigation reduce intralesional resection rates. The rest of the plan:
- Preoperative angio-CT if a vessel is abutted, a vascular surgeon on standby, and consideration of ureteric stents, which make the ureters palpable, and a urinary catheter
- Bowel preparation and a defunctioning discussion if the rectum is at risk
- Cross-match substantial blood and give tranexamic acid. Cell salvage is available but contested in sarcoma: many avoid it or use leucocyte filtration
- Plastic surgery involvement for the flap coverage plan; the pedicled rectus abdominis is the workhorse
- Consent that, beyond the two operations, covers nerve deficit, infection requiring implant removal, and mortality
Operative Strategy by Zone
Indication. An iliac wing tumour sparing the acetabulum and SI joint, or taken with the SI joint as a zone I plus IV resection.
Position and approach. Floppy lateral or lateral decubitus, allowing anterior and posterior access. The utilitarian pelvic incision runs along the iliac crest, extensile ilioinguinal-type anteriorly and extending posteriorly toward the PSIS. Elevate the abductors laterally and iliacus medially off the remaining bone only, keeping the muscle cuff on the tumour.
At risk. The superior gluteal artery at the greater sciatic notch, where a retraction injury causes torrential bleeding that retracts into the pelvis; the L5 nerve root and lumbosacral trunk anterior to the ala; and the femoral nerve within iliacus.
Osteotomies. A supra-acetabular cut and a cut adjacent to, or through, the SI joint, under guide or navigation.
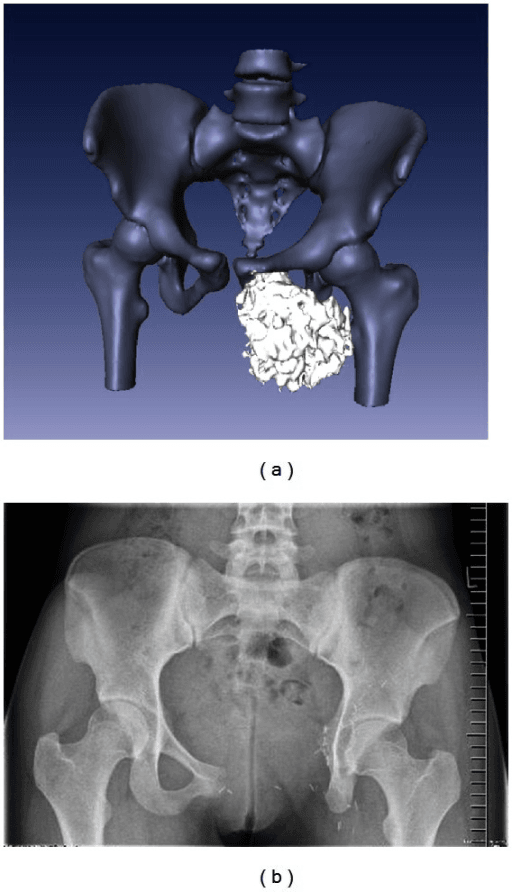
The reconstruction decision. If a supra-acetabular bone bridge remains, no reconstruction. If the ring is discontinuous between sacrum and acetabulum there are two options: accept controlled proximal migration, with modest limb shortening and often acceptable function, or restore continuity with an iliosacral bar or screw construct plus a vascularised free fibula or structural allograft to fuse the sacrum to the residual ilium. Restoring the ring is favoured in young, high-demand patients where limb length and abductor mechanics matter.
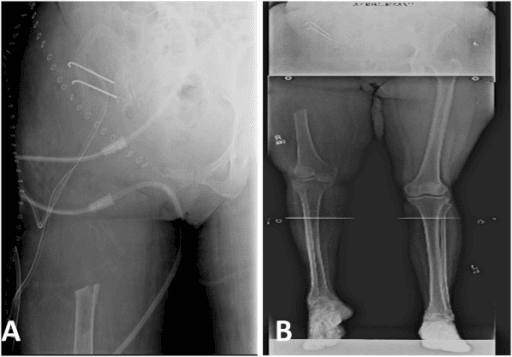
Zone II Reconstruction: Options and Selection
Choosing the reconstruction. The options form a ladder from no reconstruction at all to a patient-specific implant. Climb it only as far as bone stock, infection risk, demand and resources allow.
- 1Rung 0 — Resection without reconstruction (flail hip)Trigger: low-demand or palliative patient, or margin sacrifice leaves nothing to build on. Accepts shortening and instability; gives pain relief and mobility with aids.
- 2Rung 1 — Friedel hip transposition (iliofemoral pseudarthrosis)Trigger: poor residual bone stock for an implant, irradiated or previously infected field, resource-limited setting, or salvage after failed endoprosthesis. Femoral head displaced proximally against residual ilium or lateral sacrum, contained by capsule, mesh and abductor reattachment. No implant means no implant infection or loosening; MSTS commonly 60 to 70 percent with the lowest reoperation burden. Cost: 2 to 5 centimetres shortening (shoe raise), Trendelenburg gait, prolonged bracing.
- 3Rung 2 — Stemmed 'ice-cream-cone' acetabular prosthesis (LUMiC-type)Trigger: zone II with or without zone III resection and preserved iliac or SI-adjacent bone to accept the conical hydroxyapatite-coated stem. Off-the-shelf or modular, so no manufacturing delay after neoadjuvant chemotherapy; dual-mobility or constrained bearing restores hip centre and length. MSTS approximately 70 percent. Fails by infection (leading mode), dislocation, stem loosening or breakage, iliac stress fracture. Not an option after very high combined zone I plus II resection.
- 4Rung 3 — Massive allograft or allograft-prosthesis compositeTrigger: young patient in whom restoring bone stock matters, with a good soft-tissue envelope and access to bone banking. Cemented total hip into the allograft acetabulum. Function variable; fails by infection, host-graft nonunion, allograft fracture and resorption.
- 5Rung 4 — Custom 3D-printed hemipelvic endoprosthesisTrigger: complex combined-zone defect in a centre with the design pipeline. Patient-specific titanium implant planned on the resection CT with matching cutting guides, porous trabecular surfaces for osseointegration at sacrum and ilium, integrated acetabulum, screws aimed into best bone. MSTS approximately 70 percent with early weight bearing in many series. Cost and lead time are the limits, and the implant cannot adapt if margins change intraoperatively.
- 6Off-ladder — Arthrodesis and the saddle prosthesisIliofemoral or ischiofemoral arthrodesis: strong, stable, low late failure, but stiff hip, difficulty sitting and high nonunion — reserved for heavy manual workers or salvage. Saddle prosthesis articulating over a notch in residual ilium is historic: proximal migration, iliac fracture, dislocation, infection and poor function; largely abandoned. Know it as a cautionary exam answer, not a recommendation.
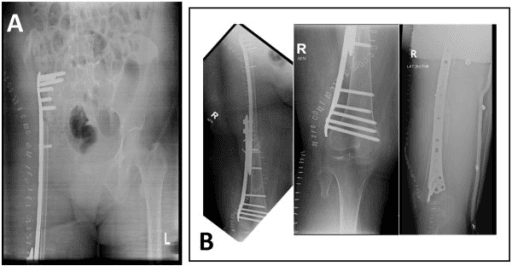
The resection is planned for the margin; the reconstruction is planned for the defect — in that order. Shaving a margin to preserve the acetabulum or fit an implant converts a curative operation into a local-recurrence machine, and local recurrence after pelvic chondrosarcoma is frequently fatal. When forced to choose, choose the margin.
Complications: Rates, Prevention, Management
Infection dominates. Deep infection complicates 20 to 40 percent of pelvic resection-reconstructions, reflecting long operating time, large dead space, proximity to the perineum, irradiated tissue and implant surface colonisation. It is the most common reason endoprosthetic reconstructions fail, and the patient is warned that it may cost the reconstruction.
Preventing and treating it. Minimise operating time, staging the most complex cases; manage dead space meticulously; cover implants with flaps; drain; use extended antibiotic prophylaxis, as many units do, and silver or antibiotic coatings where available. When infection is established, debride early and aggressively. An established endoprosthetic infection usually mandates implant removal, as do recurrent infection, loosening or an exposed implant: conversion to hip transposition or a flail hip, or rarely a secondary external hemipelvectomy for uncontrolled sepsis.
Haemorrhage. The common and external iliac vessels, the superior gluteal artery at the greater sciatic notch and the corona mortis are all at risk. Proximal vascular control of the iliac vessels before the osteotomies is a core safety step; massive haemorrhage is the intraoperative killer.
- Where
- Anterior pelvis, zone III and pubic osteotomies
- Mechanism
- Traction, laceration or avulsion during osteotomy and tumour mobilisation; massive haemorrhage
- Avoid by
- Dissect and sling the vessels early; vascular surgery on standby
- If injured
- Direct repair or interposition graft; be prepared for massive transfusion protocol and re-exploration for ongoing bleeding
- Where
- Greater sciatic notch, above piriformis
- Mechanism
- Divided or retracted into the pelvis at the notch; also the pedicle for posterior flap perfusion
- Avoid by
- Identify at the notch and ligate under direct vision rather than dividing blind; preserve perforators supplying the posterior flap
- If injured
- Retrieve and ligate securely (retraction into pelvis causes concealed bleeding); anticipate posterior flap ischaemia and plan alternative coverage
- Where
- Posteriorly at the notch, on the ischium; femoral anteriorly, lumbosacral trunk on the ala
- Mechanism
- Traction, thermal or sharp injury during posterior column and sacral osteotomy
- Avoid by
- Identify and protect the nerve early in the dissection; planned sacrifice is consented preoperatively, not discovered intraoperatively
- If injured
- Tag ends for later reconstruction if oncologically appropriate; orthosis for foot drop, protective skin care and rehabilitation
- Where
- Zone III, pubic and retropubic dissection
- Mechanism
- Direct laceration or devascularisation during periacetabular and pubic resection
- Avoid by
- Catheter decompression, preoperative ureteric stents in reoperative or bulky zone III disease, urology on standby
- If injured
- Immediate urological repair over a stent with prolonged catheter drainage; delayed diagnosis risks urinoma, fistula and secondary infection
Wound necrosis and flap failure. Long incisions, irradiated tissue and thin posterior flaps closed under tension. Preserve the perforators, plan pedicled rectus abdominis or gluteal flaps prospectively with plastic surgery, and avoid closure under tension. When a flap fails, debride early and salvage or re-cover it before implant exposure supervenes.
Dislocation and mechanical failure. Endoprosthetic dislocation reflects abductor loss and an altered hip centre, answered with dual-mobility or constrained liners, abduction bracing and careful abductor reattachment. Aseptic loosening, stem fracture and iliac stress fracture occur late, and revision options narrow with each failure, ending at transposition or amputation.
Venous thromboembolism. VTE risk is high after pelvic resection. Extended chemoprophylaxis plus mechanical prophylaxis, continued beyond discharge per unit protocol.
Local recurrence and surveillance. Local recurrence tracks with margin status and is highest after intralesional or marginal resection, so the margins are documented on the resection specimen. Surveillance is serial MRI of the pelvis for the resection bed and CT chest for the lung, the dominant site of metastasis, at intervals per sarcoma guidelines for a minimum of 5 years (10 for chondrosarcoma in many units). A recurrence in the bed goes to early salvage resection or amputation if resectable, lung disease to metastasectomy or systemic therapy referral, and external hemipelvectomy is reserved for uncontrolled sepsis or unsalvageable recurrence.
Functional Outcomes and Rehabilitation
What to expect. Function depends on nerve preservation and abductor reconstruction. Isolated zone I or III resections often score 80 percent or better on the MSTS; zone II reconstructions cluster around 60 to 70 percent regardless of method, with hip transposition performing comparably to endoprostheses at lower reoperation cost. All zone II patients have some abductor deficiency: expect a Trendelenburg gait and a walking aid in the first year, and counsel accordingly.
Drains, flap monitoring, VTE prophylaxis, bed-to-chair transfers; abduction brace after endoprosthesis in many protocols; early isometric quadriceps and ankle work.
Touch or partial weight bearing per construct — earlier full weight bearing after well-fixed custom implants; transposition and fusion constructs protected longer while stabilising. Hip precautions after endoprosthesis.
Wean brace, progress to full weight bearing, abductor and core strengthening, gait retraining; shoe raise for transposition shortening; adjuvant therapy continues in parallel for chemosensitive tumours.
Functional plateau typically 12 to 24 months, with oncological surveillance continuing throughout.
Guidelines, Registries & Global Practice
- Global epidemiology: pelvic sarcomas are rare — chondrosarcoma is the most common pelvic primary in adults, Ewing sarcoma in children and adolescents; all should be managed in designated sarcoma centres, a principle enshrined in UK NICE sarcoma service guidance, ESMO-EURACAN clinical practice guidelines and equivalent national sarcoma pathways worldwide
- ESMO-EURACAN bone sarcoma guidelines: biopsy at the treating centre along a resectable tract; neoadjuvant chemotherapy for osteosarcoma and Ewing; surgery-first for conventional chondrosarcoma; structured MDT decision-making
- NICE (UK): referral of suspected bone sarcoma to specialist centres; supports the centralisation model that pelvic resection outcomes depend on (volume-outcome relationship is well recognised for these procedures)
- Registry evidence: national arthroplasty registries (NJR, AOANJRR and others) capture little tumour endoprosthesis data; the meaningful datasets are collaborative sarcoma registries and multicentre implant cohorts (for example the European LUMiC collaboration and ISOLS-affiliated series), which consistently report infection as the leading reconstruction failure
- Practice variation by resource setting: custom 3D-printed implants and navigation concentrate in high-resource centres; hip transposition and resection without reconstruction deliver comparable oncological outcomes and respectable function where implant infrastructure, bone banking or revision capacity are limited — an important equity point: limb salvage does not require a custom implant
Controversies & Areas of Uncertainty
- Endoprosthesis versus hip transposition for zone II: no randomised data; endoprostheses restore length and early function but carry infection/dislocation/loosening; transposition avoids implant failure at the cost of shortening. Series-level MSTS scores overlap substantially
- Custom 3D-printed implants: enthusiasm and early series are favourable, but long-term fixation, cost-effectiveness and the inflexibility problem (implant fixed before final margins) remain unresolved
- Navigation and patient-specific guides: reduce intralesional resection rates in comparative series, but survival benefit is unproven
- Cell salvage in sarcoma surgery: theoretical tumour-cell reinfusion risk versus massive transfusion need; leucodepletion filters are used in some centres, avoidance in others
- Reconstruction at all for zone I discontinuity: many patients function well with an unreconstructed defect and modest shortening; when to fuse the ring remains judgement-based
- Thresholds for external hemipelvectomy: with modern flaps and vascular reconstruction, the boundary keeps moving — but survival is driven by tumour biology and margin, not by whether the limb was kept
MCQ Practice Points
Q: Which Enneking-Dunham zone poses the greatest reconstructive challenge?
A: Zone II, the periacetabular zone. Resection sacrifices the hip joint and the weight-bearing acetabulum, demanding transposition, endoprosthetic, biological or fusion reconstruction. Zones I and III often need no skeletal reconstruction at all.
Q: What is the most common major complication of pelvic resection-reconstruction?
A: Deep infection, in the region of 20 to 40 per cent — 28 per cent with the LUMiC prosthesis (Bus) and 32 per cent after hip transposition (Gebert). Note what that pair implies: the rate is essentially the same with and without an implant, so infection here is driven by operative time, blood loss, dead space, perineal proximity and irradiated tissue rather than by the construct chosen. In Bus's series greater blood loss was significantly associated with infection (2.3 versus 1.5 L, p = 0.039).
Q: A zone III resection is completed. What skeletal reconstruction is required?
A: None — the sacro-acetabular weight-bearing arch is intact. Reconstruct the pelvic floor (mesh or flap) to prevent herniation, and protect the bladder, urethra, corona mortis and obturator bundle during resection.
Q: Which reconstruction is now regarded as historic because of migration, iliac fracture and infection?
A: The saddle prosthesis — superseded by stemmed acetabular (ice-cream-cone, LUMiC-type) and custom 3D-printed implants.
Q: Which findings favour external over internal hemipelvectomy?
A: Combined sciatic nerve AND femoral neurovascular involvement, fungating or infected tumour, contamination of all flap options, and unreconstructable soft-tissue loss — a limb without vessels, nerve supply or coverage is not salvageable. Note the converse, established by Enneking and Dunham in 1978: sciatic nerve resection alone is not a contraindication to a limb-sparing procedure.
Q: Why does margin status matter more than reconstruction choice in pelvic chondrosarcoma?
A: Because chondrosarcoma is resistant to chemotherapy and radiotherapy, so surgery is the only curative modality. Enneking and Dunham found recurrence in 100 per cent of oncologically inadequate resections against 4 per cent of adequate ones, and Mochizuki's 135-patient national series identified surgical margin among only six significant prognostic factors, with 10-year survival of 65 per cent. The resection plan therefore dictates the reconstruction, never the reverse — and note where adequacy is most often lost: at a poorly planned biopsy, before the resection is even begun.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 45-year-old presents with deep groin pain. Imaging shows a 9 centimetre cartilaginous tumour centred on the acetabulum with a large extraosseous mass abutting but not encasing the external iliac vessels. Biopsy at the sarcoma centre confirms grade 2 chondrosarcoma. Walk me through your management.”
“Eight months after a zone II resection reconstructed with an ice-cream-cone prosthesis, a 30-year-old presents with a discharging sinus, raised CRP and radiographic lucency around the iliac stem. How do you proceed?”
“A 15-year-old with an iliac wing Ewing sarcoma has completed induction chemotherapy with an excellent radiological response. The tumour occupies the mid-ilium; the acetabulum and SI joint appear clear on MRI. Plan the surgery and reconstruction.”
Zones (Enneking-Dunham)
- I ilium — often no reconstruction; iliosacral bar/fibula fusion if ring discontinuity matters
- II periacetabular — the reconstructive challenge; hip sacrificed
- III ischiopubic — no skeletal reconstruction; pelvic floor repair; urogenital structures at risk
- IV sacral extension — consider spinopelvic fixation if posterior ring lost
Workup
- Contrast MRI pelvis for local staging; CT chest for lungs; CT for planning/guides
- Core biopsy at sarcoma centre along a tract excisable en bloc
- Chondrosarcoma: surgery-first; osteosarcoma/Ewing: neoadjuvant chemotherapy
- Plan resection on pre-chemotherapy tumour extent
Zone II reconstruction
- Hip Transposition — no implant, MSTS often 60 to 70 percent, lowest reoperation burden
- Ice-cream Cone (LUMiC-type) — needs residual iliac bone stock; dual mobility to cut dislocation
- Additive-manufactured Custom 3D-printed — precise but costly, cannot adapt intraoperatively
- Structural allograft/APC — biological but infection/nonunion/fracture risks
- Arthrodesis or flail hip — niche; Saddle prosthesis — historic, avoid
Complications
- Deep infection 20 to 40 percent — dominant failure; removal plus transposition salvage
- Wound necrosis/flap failure — plan pedicled rectus abdominis prospectively
- Dislocation — abductor loss; dual mobility, bracing
- Haemorrhage — proximal iliac control before osteotomy; superior gluteal artery at the notch
- Local recurrence tracks with margin status
Choose amputation instead when
- Sciatic nerve plus femoral neurovascular involvement
- Fungating or infected tumour; contaminated flap options
- Unreconstructable soft-tissue envelope
- Uncontrolled sepsis after failed reconstruction (secondary external hemipelvectomy)
Evidence Base
Resection and Reconstruction for Primary Neoplasms Involving the Innominate Bone
- Of more than 200 patients evaluated, 57 were judged candidates for a curative procedure - 25 had hemipelvectomy and 32 a non-amputative resection. Follow-up 1 to 17 years
- The three procedures described, singly or combined, are the zones still in use: iliac wing, periacetabular, and pubis
- An oncologically ADEQUATE procedure was achieved in only two-thirds of cases; the rest were compromised by poorly planned biopsies, occult microextensions and surgical errors
- Recurrence was 100 PER CENT after an inadequate procedure and 4 PER CENT after an adequate one - the single most important number in pelvic sarcoma surgery
- Function was nearly normal when the hip joint was preserved. Where the hip was removed and arthrodesis attempted, fusion was achieved in only HALF of cases; where pseudarthrosis resulted, outcomes ranged from good to poor
- Resection of the sciatic nerve was NOT a contraindication to a limb-sparing procedure
The Management of Pelvic Chondrosarcoma in Japan - Japanese Musculo-Skeletal Oncology Group
- 135 patients with pelvic chondrosarcoma across 58 Japanese institutions between 1989 and 1998 - a national rather than single-centre picture
- Limb salvage in 121 and ablative surgery in 14
- Margins were intralesional in 27, marginal in 30 and wide in 77
- Local recurrence in 33 patients, distant metastasis in 25, and postoperative infection in 25
- Cumulative 10-year survival 65 per cent; outcome was determined by six significant factors - surgical stage, tumour site, tumour size, SURGICAL MARGIN, and post-operative functional mobility and activity level
- The authors' conclusion: wide excision, or wide with partly marginal areas, plus stable reconstruction