The Roof of the Cubital Tunnel and the Wall of Guyon Canal
- Two heads: a humeral head from the medial epicondyle and an ulnar head from the olecranon and posterior ulnar border, bridged by the arcuate ligament of Osborne.
- The ulnar nerve enters the forearm BETWEEN the two heads - the ligament is the roof and the elbow capsule with the posterior band of the medial collateral ligament is the floor of the cubital tunnel.
- It is the ONLY wrist flexor supplied entirely by the ulnar nerve (C7-C8, with a T1 contribution); flexor carpi radialis and palmaris longus are median.
- The pisiform is a sesamoid within the FCU tendon; the pull continues to the hook of hamate and fifth metacarpal base through the pisohamate and pisometacarpal ligaments.
- FCU and the pisiform form the ULNAR wall of Guyon canal, with the hook of hamate as the radial wall.
- “FCU strength localises an ulnar lesion: it may be WEAK in cubital tunnel syndrome, though it is often clinically spared, and it is NORMAL in Guyon canal compression.
- “The FCU motor branches arise 1 to 4 cm distal to the medial epicondyle and are the tether that must be mobilised - not divided - during anterior transposition.
- “Failed cubital tunnel release is most often incomplete release of the DISTAL FCU aponeurosis rather than of Osborne ligament itself.
- “Acute red, hot, exquisitely tender swelling over the pisiform with amorphous calcification on radiograph is calcific tendinitis, not sepsis - it settles without surgery.
Overview
Flexor carpi ulnaris (FCU) is the ulnar-most and most powerful of the superficial wrist flexors, and it is unusual in three ways that examiners exploit repeatedly. It is the only wrist flexor supplied entirely by the ulnar nerve, so its strength is the bedside test that separates an ulnar lesion at the elbow from one at the wrist. Its two heads of origin form the roof of the cubital tunnel, with the nerve passing between them, so the muscle is both the cause of and the corridor to the commonest compressive neuropathy of the upper limb after carpal tunnel syndrome. And it inserts into a sesamoid, the pisiform, from which its force is relayed distally by ligament, a design that increases its moment arm and creates a distinct pisotriquetral pathology.
Why surgeons want to keep it. FCU is the principal ulnar deviator and the key wrist stabiliser during power grip. Power grip needs the wrist held in about 20 to 30 degrees of extension with slight ulnar deviation so that the long finger flexors work at length, and that posture is not passive. Extensor carpi radialis longus and brevis extend and radially deviate, FCU flexes and ulnar deviates, and firing together their flexion-extension components partly cancel while their deviation moments hold the wrist against the strong ulnar-deviating pull of the finger flexors. Extensor carpi ulnaris completes the picture as the dorsal ulnar stabiliser, and the FCU-ECU pair is the ulnar column couple that resists the radial drift imposed by grip.
What its loss costs. Remove FCU and the wrist loses its principal ulnar-sided flexion anchor. Grip strength falls because the wrist collapses out of the length-tension optimum for the finger flexors, which are themselves no weaker. That is the whole argument for preferring flexor carpi radialis as a transfer donor: borrowing FCR costs a modest loss of flexion power, borrowing FCU costs a destabilised wrist during grip, and this is why modern radial nerve palsy transfer sets take FCR rather than FCU.
Where the same power is the problem. In spastic cerebral palsy an overactive FCU is the dominant deforming force producing the flexed, ulnar-deviated, pronated wrist, and transferring it dorsally converts the deforming force into a corrective one. In the spastic wrist the deforming force is exactly what you want to redirect; in a normal wrist the same power should be left where it is.
Attachments, Innervation and Relations
Humeral head. From the medial epicondyle of the humerus via the common flexor origin, of which it is the most ulnar (posterior) component.
Ulnar head. From the medial margin of the olecranon and, by an aponeurosis, from the proximal two-thirds of the subcutaneous posterior border of the ulna. That aponeurotic origin is shared with flexor digitorum profundus and extensor carpi ulnaris along the same subcutaneous border, which is the plane exploited in the posterior approach to the ulna.
The arch between the heads. A tendinous arch, the arcuate ligament of Osborne (the cubital tunnel retinaculum), spans from the medial epicondyle to the olecranon and bridges the two heads. The ulnar nerve passes beneath it, between the heads, to enter the forearm.
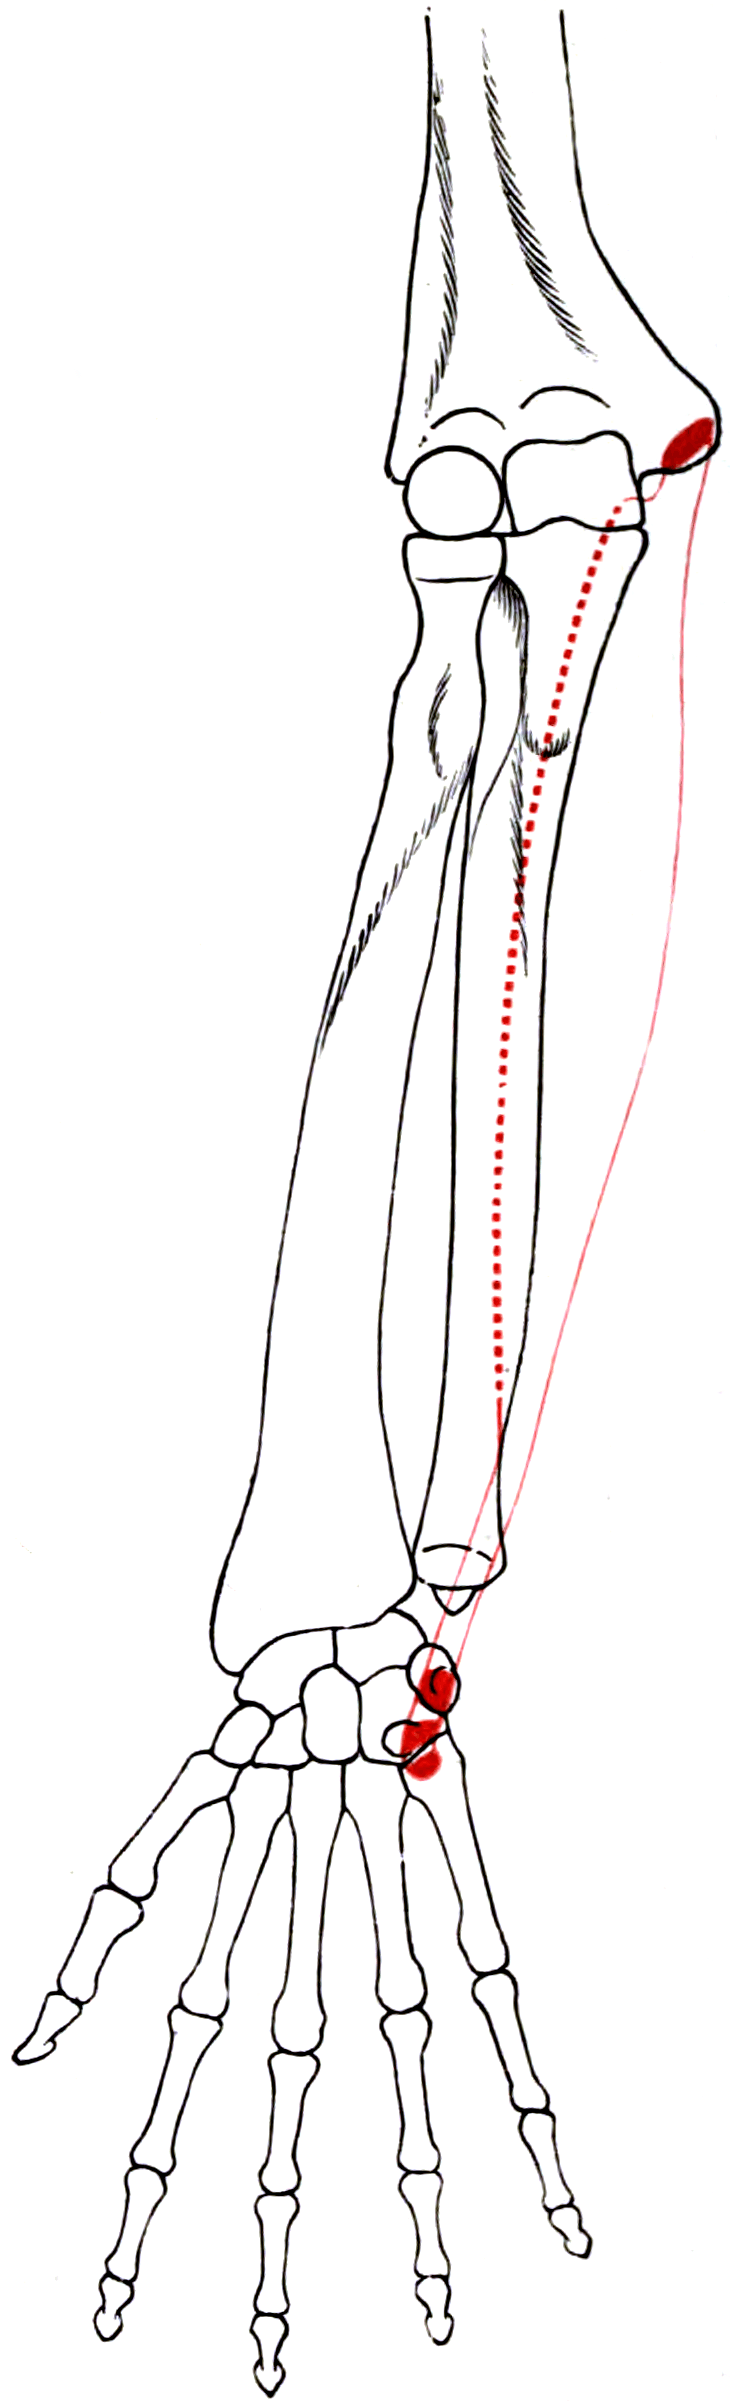
Insertion. The principal insertion is the pisiform, a sesamoid bone within the FCU tendon that articulates with the triquetrum. The pull continues through the pisohamate ligament to the hook of the hamate and the pisometacarpal ligament to the base of the fifth metacarpal, and some fibres run on into the flexor retinaculum and the origin of abductor digiti minimi. As a sesamoid the pisiform displaces the tendon volarly and increases the FCU flexion moment arm; it also means an FCU transfer must be detached from the pisiform, which changes the pull of the pisohamate complex.
The muscle belly. Unlike FCR, FCU remains muscular almost to the wrist, with fleshy fibres persisting along the tendon to within a few centimetres of the pisiform. A transfer or graft therefore carries muscle bulk with it, which makes subcutaneous routing bulkier than an FCR or palmaris longus transfer and makes pure tendon harvest impossible.
Action and Biomechanics
Primary actions. FCU flexes and ulnar deviates the wrist, stabilises it during grip and contributes a little to elbow flexion:
- Wrist flexion: the strongest of the three wrist flexors, with the largest physiological cross-sectional area of the group; FCR is second
- Ulnar deviation, acting with extensor carpi ulnaris; their flexion and extension components cancel, leaving pure ulnar deviation
- Wrist stabilisation during power grip, functionally its most important role, holding the wrist against the ulnar-deviating and flexing pull of the long finger flexors
- Weak elbow flexion through the humeral head, clinically negligible but the reason FCU activity is recorded on elbow EMG
Length-tension and transfer suitability. FCU is a high-force, short-excursion motor: a large cross-section and about 33 mm of tendon excursion, against roughly 70 mm for the finger flexors. That makes it ideal for a wrist-level transfer and poor as a finger flexor.
After FCU transfer. Ulnar-sided wrist flexion power is lost. In cerebral palsy that is the intention; in a normal wrist it produces measurable grip weakness and a tendency to radial deviation.
Surface Anatomy and Examination
Finding the tendon. The pisiform is the key landmark: palpate the hard, mobile, pea-shaped bone at the proximal edge of the hypothenar eminence, in line with the ulnar border of the forearm, and the FCU tendon runs directly into it. Ask the patient to flex and ulnar deviate the wrist against resistance and the tendon stands out as the ulnar-most cord at the volar wrist. The ulnar nerve and artery lie immediately radial to it, about 1 cm radial to the pisiform at the level of the distal wrist crease; never look for them ulnar to FCU.
At the elbow. The ulnar nerve is palpable in the groove between the medial epicondyle and the olecranon and can be rolled under the finger; the FCU arch lies just distal to it.
Isolation test. Forearm supinated, elbow flexed to 90 degrees and supported, fingers relaxed. The patient flexes and ulnar deviates the wrist against resistance applied over the hypothenar eminence while you palpate the tendon; grade the power MRC 0 to 5 and always compare sides.
Pitfalls. The long finger flexors substitute if the patient clenches the fist. Palmaris longus tenses in the midline and can be mistaken for FCU by an examiner palpating too radially, and abductor digiti minimi contraction can be misread as tendon tension, so palpate proximal to the pisiform.
Named tests around FCU and the ulnar nerve. What each test shows, and what fools it:
- How to perform
- Elbow flexed, forearm supinated, fingers relaxed; resist wrist flexion with ulnar deviation
- Positive finding
- Weakness, or pain at the pisiform
- What it means
- FCU weakness (proximal ulnar lesion) or FCU insertional tendinopathy
- False positives
- Pain from pisotriquetral arthritis loaded by the same manoeuvre
- How to perform
- Elbow maximally flexed, wrist neutral, held 60 seconds
- Positive finding
- Paraesthesiae in the ring and little fingers
- What it means
- Cubital tunnel syndrome
- False positives
- Positive in a proportion of asymptomatic people if the wrist is also extended
- How to perform
- Percuss the nerve in the groove
- Positive finding
- Radiating paraesthesiae to the ulnar digits
- What it means
- Ulnar nerve irritability at the elbow
- False positives
- Frequently positive in normal, thin individuals
- How to perform
- Palpate the nerve while flexing and extending the elbow
- Positive finding
- Nerve subluxates over or dislocates anterior to the epicondyle
- What it means
- Instability - a relative indication for transposition rather than in-situ release
- False positives
- Asymptomatic subluxation occurs in a substantial minority
- How to perform
- Pinch paper between thumb and index; examiner pulls
- Positive finding
- Thumb IP joint flexes (FPL substituting for adductor pollicis)
- What it means
- Ulnar motor weakness at any level
- False positives
- Any cause of weak key pinch, including thumb basal joint pain
- How to perform
- Grasp the pisiform and shear it across the triquetrum
- Positive finding
- Pain and crepitus
- What it means
- Pisotriquetral arthritis
- False positives
- Uncomfortable in normal wrists if done forcefully
- How to perform
- Ask the patient to adduct the extended fingers
- Positive finding
- The little finger drifts into abduction
- What it means
- Weak third palmar interosseous - ulnar intrinsic weakness
- False positives
- Present in some normal hands with lax intrinsics
Differential diagnosis of ulnar-sided wrist pain. The discriminator at the bedside, and what confirms it:
- Key Discriminator
- Tenderness on the tendon proximal to the pisiform; pain on resisted flexion-ulnar deviation
- Confirmatory Finding
- Sheath fluid and tendon thickening on ultrasound
- Key Discriminator
- Sudden onset, red hot swollen tender pisiform, disproportionate pain
- Confirmatory Finding
- Amorphous calcification just proximal to the pisiform on a supinated oblique or carpal tunnel view
- Key Discriminator
- Pain on pisiform shear and on direct pressure; pain leaning on the heel of the hand
- Confirmatory Finding
- Joint narrowing on a 30-degree supinated oblique view
- Key Discriminator
- Pain on ulnar deviation and axial load, foveal tenderness
- Confirmatory Finding
- Ulnar fovea sign, MR arthrography or arthroscopy
- Key Discriminator
- Pain on grip with ulnar deviation, positive ulnar variance
- Confirmatory Finding
- Lunate and ulnar head subchondral change on MRI
- Key Discriminator
- Tenderness over the hook, pain gripping a club or bat
- Confirmatory Finding
- Carpal tunnel view or CT
- Key Discriminator
- Intrinsic weakness with NORMAL FCU and normal dorsal ulnar sensation
- Confirmatory Finding
- Nerve conduction study localising across the wrist; ultrasound or MRI for a ganglion
Complications
Medial antebrachial cutaneous nerve neuroma. The commonest complication of cubital tunnel surgery and the leading cause of a dissatisfied patient after an otherwise successful decompression: a painful neuroma and numbness over the medial forearm. It is avoided by deliberately identifying and retracting the branches, a posteriorly placed longitudinal incision, and careful subcutaneous dissection rather than blunt spreading.
Other nerve injuries. The FCU motor branches are at risk during transposition or flap elevation, and their loss produces weak ulnar-sided wrist flexion and a destabilised grip. The deep motor branch of the ulnar nerve is at risk during pisiform excision or Guyon canal exploration as it curves around the hook of hamate, and its loss produces intrinsic paralysis with preserved sensation, a devastating and easily missed complication.
Persistent symptoms after decompression. Two causes are technical and are in the alert above: an incomplete distal release of the FCU aponeurosis, and a new compression point at an un-excised intermuscular septum after transposition. The others are perineural scarring after circumferential mobilisation, and a missed second site (double crush), most often a coexisting carpal tunnel syndrome or cervical radiculopathy.
Devascularisation. Circumferential mobilisation strips the longitudinal extraneural plexus described under Blood Supply. Preserve a soft-tissue cuff around the nerve when transposing.
After a Green transfer. Over-tensioning produces over-correction into fixed wrist extension, which is harder to live with than the original flexion posture, functionally worse than the original deformity and difficult to salvage. Under-correction follows inadequate tension, which achieves nothing, or transferring a muscle without voluntary control; transferring an FCU without voluntary control converts a flexion deformity into an extension deformity. The subcutaneously routed tendon bowstrings around the ulnar border if the tunnel is too tight or too angular, and grip strength falls with removal of the ulnar wrist stabiliser.
Valgus instability. Excessive medial epicondylectomy detaches the origin of the medial collateral ligament and produces valgus instability, which is why only a partial epicondylectomy is safe.
Clinical Relevance
The anatomy is the disease. The ulnar nerve traverses five potential constriction points around the elbow, three of which are FCU-related or FCU-adjacent:
- The arcade of Struthers, roughly 8 cm proximal to the medial epicondyle, a fascial band from the medial head of triceps to the intermuscular septum
- The medial intermuscular septum
- The medial epicondyle and retro-condylar groove itself
- The arcuate ligament of Osborne between the two heads of FCU, the roof of the tunnel proper
- The deep flexor-pronator aponeurosis distally, where the nerve passes between FCU and flexor digitorum profundus
Why flexion provokes symptoms. In elbow flexion the arcuate ligament tightens and the medial collateral ligament bulges into the floor, the tunnel cross-section falls, and intraneural pressure rises several-fold, which is why symptoms are nocturnal and flexion-provoked. Add wrist extension and shoulder abduction and the nerve is placed on maximal excursion, the basis of the elbow flexion provocative test.
Clinical pattern. Paraesthesiae in the ring and little fingers, nocturnal symptoms, clumsiness, weak grip and pinch, and later intrinsic wasting with the first dorsal interosseous the most visible. Sensory loss involves the dorsal ulnar hand. An elbow-level palsy weakens FCU and the ulnar half of flexor digitorum profundus, and the profundus weakness is why clawing of the ring and little fingers is LESS marked in a high (elbow) lesion than in a low (wrist) lesion, the ulnar paradox: the denervated profundus cannot flex the distal interphalangeal joints into a claw.
Investigation. Nerve conduction studies with inching across the elbow: a conduction velocity drop across the elbow segment supports the diagnosis, though studies may be normal in early or purely dynamic compression. Ultrasound shows nerve enlargement proximal to the compression and dynamically demonstrates subluxation over the epicondyle. Radiographs look for cubitus valgus, osteophytes, a prominent medial epicondyle or an old fracture (tardy ulnar palsy).
Surgical Relevance
In-situ decompression. A longitudinal incision of 6 to 8 cm posterior to the medial epicondyle, centred on the cubital tunnel; keeping it posterior to the epicondyle reduces the chance of a painful scar directly on the point of the elbow. Identify and protect the branches of the medial antebrachial cutaneous nerve crossing the field, then release from proximal to distal:
- Divide the deep fascia and, if tight, the medial intermuscular septum proximally
- Divide the arcuate ligament of Osborne, the roof of the tunnel between the FCU heads
- Continue distally and divide the deep flexor-pronator aponeurosis between the FCU heads and over the nerve as it passes between FCU and flexor digitorum profundus
When the release is adequate. The nerve is free for approximately 5 to 8 cm proximal and distal to the epicondyle with no residual band on passive elbow flexion. Then flex the elbow through a full arc: if the nerve now dislocates anteriorly over the epicondyle, transposition is required.
Anterior transposition. Indicated for ulnar nerve subluxation or dislocation, prior failed in-situ release, cubitus valgus or a deformed medial epicondyle, and nerve tethering by scar. Beyond the in-situ release:
- Excise the medial intermuscular septum rather than merely divide it
- Mobilise the nerve circumferentially, preserving the longitudinal vascular plexus where possible
- Mobilise the FCU motor branches by intraneural dissection so the nerve translates anteriorly without tethering
- Place the nerve anterior to the medial epicondyle and hold it there subcutaneously (a fascial sling), submuscularly (under the flexor-pronator mass, requiring a Z-lengthened or step-cut reattachment) or intramuscularly
- Confirm a smooth path with no kinking through full flexion and extension before closure
Medial epicondylectomy. An alternative that removes the fulcrum without devascularising the nerve. Only a partial epicondylectomy should be performed.
- Stopping the release at Osborne ligament. The deep flexor-pronator aponeurosis distal to the FCU heads must also be divided - incomplete distal release is the leading cause of persistent symptoms.
- Dividing rather than mobilising the FCU motor branches during transposition. You gain millimetres and lose the wrist stabiliser of power grip.
- Merely dividing the medial intermuscular septum before transposition. Excise it: a transposed nerve angulating over the cut edge creates a new, iatrogenic compression point.
Guidelines, Registries & Global Practice
Anatomical variation across populations
- Accessory heads and anomalous slips of FCU are described, including slips arising from the coronoid or from the medial intermuscular septum; these occasionally contribute to cubital tunnel compression and should be sought at surgery when no other cause is found.
- An anconeus epitrochlearis - an accessory muscle spanning from the olecranon to the medial epicondyle over the cubital tunnel, replacing the arcuate ligament - is present in a minority of elbows across cadaveric series and is a recognised cause of cubital tunnel syndrome. It must be excised rather than simply incised.
- Anomalous muscles crossing Guyon canal, including accessory abductor digiti minimi and aberrant palmaris brevis fibres, are described in a small percentage of hands and are a cause of ulnar tunnel syndrome in young patients with no other pathology.
Side-by-side guidance on cubital tunnel management
- Position on Cubital Tunnel Surgery
- Supports simple in-situ decompression as effective for idiopathic cubital tunnel syndrome, with no demonstrated superiority of transposition in the absence of instability or a structural indication.
- Position on Cubital Tunnel Surgery
- Recommend a trial of activity modification and night splinting before surgery in mild disease; in-situ decompression as the default operation with transposition reserved for instability or revision.
- Position on Cubital Tunnel Surgery
- Emphasises complete release across all five potential compression points and excision - not simple division - of the medial intermuscular septum where transposition is performed.
- Position on Cubital Tunnel Surgery
- Emphasises patient selection for FCU transfer on voluntary control, passive range and the ability to release with the wrist extended, rather than on the severity of the deformity.
Evidence position worth stating
- Multiple randomised comparisons and systematic reviews of simple in-situ decompression versus anterior transposition for idiopathic cubital tunnel syndrome have found comparable clinical outcomes, with transposition carrying a higher rate of wound complications. The defensible position is: in-situ release for the stable nerve, transposition for instability, revision surgery, or a structural abnormality of the epicondyle.
- For FCU transfer in cerebral palsy, published series consistently report reliable improvement in resting posture and appearance and satisfaction rates above 85 per cent, with functional gain in a majority but not all patients. Counsel to that evidence.
High- versus limited-resource practice
- Well-resourced settings: high-resolution ultrasound for dynamic assessment of nerve subluxation, nerve conduction studies with inching, endoscopic cubital tunnel release in some centres, and formal upper limb gait and video analysis before cerebral palsy transfers.
- Limited-resource settings: the diagnosis is clinical, the localisation rests entirely on FCU strength, profundus strength and dorsal ulnar sensation, and in-situ decompression through a short posterior incision remains a highly effective, equipment-light operation. FCU transfer requires no implants and is achievable wherever competent postoperative therapy exists - and therapy availability, not technique, is the true limiting factor.
MCQ Practice Points
Q: Which wrist flexor is entirely ulnar-innervated? A: Flexor carpi ulnaris, ulnar nerve C7-C8 with a T1 contribution. FCR and palmaris longus are median.
Q: What passes between the two heads of FCU? A: The ulnar nerve, beneath the arcuate ligament of Osborne, which is the roof of the cubital tunnel.
Q: What forms the floor of the cubital tunnel? A: The elbow joint capsule and the posterior band of the medial collateral ligament. The roof is the arcuate ligament between the FCU heads.
Q: Where does FCU insert? A: Pisiform (a sesamoid within the tendon), then onward via the pisohamate ligament to the hook of hamate and the pisometacarpal ligament to the fifth metacarpal base.
Q: What are the ulnar and radial walls of Guyon canal? A: The pisiform and FCU tendon form the ulnar wall; the hook of the hamate forms the radial wall. The roof is the volar carpal ligament and palmaris brevis; the floor is the transverse carpal and pisohamate ligaments.
Q: Where do the FCU motor branches leave the ulnar nerve? A: 1 to 4 cm distal to the medial epicondyle. They must be mobilised, not divided, during anterior transposition.
Q: What is the most common technical cause of persistent symptoms after in-situ cubital tunnel release? A: Failure to release the deep flexor-pronator aponeurosis distal to Osborne ligament, where the nerve passes between FCU and flexor digitorum profundus.
Q: Why does a high ulnar lesion claw less than a low one? A: Because the ulnar half of flexor digitorum profundus is also denervated, so the distal interphalangeal joints cannot flex into a claw.
Q: Where does the dorsal cutaneous branch of the ulnar nerve arise? A: 5 to 8 cm proximal to the ulnar styloid. Preserved dorsal ulnar hand sensation localises a lesion distal to it, at Guyon canal.
Q: Red, hot, exquisitely tender pisiform with amorphous calcification on radiograph - diagnosis? A: Calcific tendinitis of FCU at its insertion. Self-limiting; treat non-operatively and do not wash it out.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 46-year-old builder has numbness in his ring and little fingers, weak pinch and early wasting of the first dorsal interosseous. How do you determine where the ulnar nerve is compressed, at the bedside, before ordering anything?”
“A 38-year-old woman presents to the emergency department with 24 hours of severe ulnar wrist pain. The area over the pisiform is red, warm, swollen and exquisitely tender. She is afebrile. The referring team has started intravenous antibiotics for suspected septic arthritis. What do you do?”
“A 14-year-old with spastic hemiplegic cerebral palsy has a flexed, pronated, ulnar-deviated wrist. The family want it straightened. What determines whether you would perform a flexor carpi ulnaris transfer, and how would you do it?”
Anatomy
- Humeral head: medial epicondyle; ulnar head: olecranon and posterior ulnar border
- Ulnar nerve passes BETWEEN the heads under Osborne ligament
- Insert: pisiform, then pisohamate to hook of hamate and pisometacarpal to 5th MC
- Nerve: ulnar, C7-C8 (T1); the only entirely ulnar wrist flexor
- Muscular almost to the pisiform - bulky as a transfer
Cubital Tunnel
- Roof: arcuate ligament of Osborne between the FCU heads
- Floor: capsule and posterior band of the MCL
- Five compression points: Struthers arcade, septum, groove, Osborne, distal FCU fascia
- Motor branches 1 to 4 cm distal to the medial epicondyle
Guyon Canal
- Ulnar wall: pisiform and FCU tendon
- Radial wall: hook of hamate
- Roof: volar carpal ligament and palmaris brevis
- Zone 1 mixed, zone 2 motor, zone 3 sensory
Localisation
- Weak FCU = elbow; normal FCU = wrist
- Dorsal ulnar numbness = proximal to 5-8 cm above the styloid
- Ulnar paradox - high lesions claw less
- Froment and Wartenberg signs for intrinsic weakness
Surgery
- Release must extend through the distal FCU aponeurosis
- Excise the intermuscular septum before transposition
- Green transfer FCU to ECRB - needs voluntary control
- Proximally based FCU flap on the posterior ulnar recurrent artery
Evidence Base
The Anatomy of the Distal Ulnar Tunnel
- The distal ulnar tunnel is 4 to 4.5 cm long and divided into three zones by the internal topography of the nerve
- Zone 1 lies proximal to the bifurcation, zone 2 encompasses the deep motor branch and zone 3 surrounds the superficial branch
- All 39 reviewed cases of combined motor and sensory deficit arose from zone 1 lesions
- All 36 zone 2 lesions produced intrinsic paralysis, with hypothenar involvement determined by the exact level
- Zone 3 lesions produced sensory deficits only; combined loss most often followed compression from deep to the nerve
Transfer of the Flexor Carpi Ulnaris to the Radial Wrist Extensors in Cerebral Palsy
- Fourteen patients with cerebral palsy reviewed after FCU transfer to extensor carpi radialis longus and/or brevis
- Postoperative active wrist arc of motion was improved in the majority
- Grasp and release mechanism was enhanced after operation
- The procedure was judged successful in most patients
Flexor Carpi Ulnaris Tendon Transfers in Cerebral Palsy
- Sixteen children with FCU transfer to ECRL, ECRB or extensor digitorum, mean follow-up 4 years (range 1 to 9)
- General resting wrist position improved; the centre of the arc of motion averaged 9 degrees of extension and 6 degrees of pronation
- Fourteen of 16 parents reported functional improvement and all 16 reported improved appearance
- Fifteen of 16 were satisfied overall and 14 of 16 would recommend the procedure
Cubital Tunnel Syndrome Pathophysiology
- Cubital tunnel syndrome is the SECOND most common peripheral compression neuropathy.
- As the elbow flexes, the arcuate ligament elongates and canal volume falls by 55 PER CENT.
- Intraneural and extraneural pressures have been shown to exceed 200 mmHg with elbow flexion AND FLEXOR CARPI ULNARIS CONTRACTION - the muscle is not a bystander, its contraction is part of the mechanism.
- Because the nerve runs behind the axis of rotation, elbow flexion produces excursion of the nerve proximal and distal to the medial epicondyle, and the nerve ELONGATES 4.7 to 8 mm.
- The syndrome develops through repetitive elbow motion, prolonged elbow flexion or direct compression.
Hypothenar Hammer Syndrome: A Discrete Syndrome to Be Distinguished from Hand-Arm Vibration Syndrome
- Review of 52 articles on trauma to the ulnar artery as it passes over the hamate
- Repetitive hypothenar trauma produces thrombosis, arterial irregularity or aneurysm formation
- Colour and temperature change is more diffuse than in classical Raynaud phenomenon and lacks the triphasic change
- Allen test, Doppler and arteriography confirm the diagnosis
Excision of Pisiform in Pisotriquetral Arthritis
- Eight patients (nine cases) with pisotriquetral arthritis treated by excision of the pisiform after failing splints, anti-inflammatories and local steroid injection.
- PISOTRIQUETRAL ARTHRITIS TRAVELS WITH ULNAR NEURITIS: associated conditions included ulnar neuritis, rheumatoid arthritis, pisotriquetral loose bodies and an anomalous muscle.
- Seven of eight patients had prompt relief of pain after pisiform excision COMBINED WITH RELEASE OF GUYON'S CANAL.
- A palmar approach was required so that ulnar tunnel release and pisiform excision could be done simultaneously.
- The one patient with rheumatoid arthritis needed a further procedure (Darrach) before pain was eliminated.