A two-stage reconstruction for segmental bone loss — the cement spacer grows the biological chamber, and the second stage fills it
- The Masquelet induced-membrane technique, first described by Alain-Charles Masquelet in 1986, is a two-stage surgical strategy for reconstructing segmental bone defects.
- In the first stage, after radical debridement, a PMMA cement spacer is placed in the defect and the limb stabilised, and over six to eight weeks a vascularised 'induced membrane' forms around the spacer.
- In the second stage, the spacer is removed while preserving the membrane, and the cavity is filled with autologous cancellous bone graft, typically from the iliac crest or via RIA from the femoral canal.
- The induced membrane acts as a biological chamber, secreting osteoinductive and angiogenic factors (VEGF, TGF-β, BMP-2) while preventing graft resorption and fibrous ingrowth.
- The technique is indicated for critical-sized defects (generally greater than 2 to 5 cm) caused by high-energy open fractures (e.g., Gustilo-Anderson IIIB), post-traumatic osteomyelitis, infected nonunion, and tumour resection, most often in the tibia, with defects of 4–25 cm successfully reconstructed.
Overview & Epidemiology
The Masquelet induced-membrane technique is a two-stage surgical strategy for reconstructing segmental bone defects, first described by Alain-Charles Masquelet in 1986. It exploits the body's foreign-body response to a block of polymethylmethacrylate (PMMA) cement to create a biologically privileged environment for bone grafting: the first stage grows the chamber, the second fills it.
The two stages. In the first stage, following radical debridement of nonviable bone and soft tissue, a PMMA cement spacer is inserted into the defect and the limb is stabilised. Over six to eight weeks a vascularised, bioactive "induced membrane" forms around the spacer. In the second stage the spacer is carefully removed while the membrane is preserved, and the cavity is filled with autologous cancellous bone graft, most commonly harvested from the iliac crest or by reamer-irrigator-aspirator (RIA) from the femoral canal.
Who. Candidates have critical-sized bone defects that will not heal spontaneously; the thresholds that define "critical" are set out under Pathology. The most common causes are high-energy open fractures (particularly Gustilo-Anderson type IIIB injuries), post-traumatic osteomyelitis, infected nonunion and defects created by tumour resection. The population skews toward young adult males, reflecting the demographics of high-energy trauma, though the technique is also applied in paediatric patients with congenital pseudarthrosis and in military casualties with blast injuries.
Where. The tibia is the most frequent site, where a precarious soft-tissue envelope and high rates of open fracture make segmental defects common. The femur is second, followed by the humerus and forearm and, less commonly, the hand, foot and clavicle. Defects ranging from 4 to 25 cm have been successfully reconstructed.
Why it matters. The technique is a technically accessible alternative to distraction osteogenesis (Ilizarov bone transport) and free vascularised fibular transfer, both of which demand prolonged treatment times or microsurgical expertise. Its principal virtues remain its simplicity, its reproducibility and its independence from a microsurgeon. The staged design accommodates infection control, because an antibiotic-laden cement spacer delivers high local antibiotic concentrations, which makes the technique especially valuable in septic nonunion.
What it delivers. Union rates of approximately 80 to 90% are reported in most series, even in defects exceeding 10 cm, although the tibia fares less well than the femur and the best pooled figure for a tibia is 84%. Complications, among them graft resorption, refracture, persistent infection and donor-site morbidity, are not rare. Success depends on adherence to the core principles: radical debridement, stable fixation, adequate soft-tissue coverage, atraumatic membrane preservation at the second stage, and grafting within the window of peak membrane bioactivity.
Pathology & Pathophysiology
The problem. Segmental bone loss is one of the most challenging problems in orthopaedic reconstruction. It arises most commonly from high-energy open fractures, debridement of infected non-union, tumour resection and osteomyelitis. Left untreated, a critical defect progresses to atrophic non-union, deformity, chronic infection and, ultimately, limb-threatening dysfunction.
Two thresholds, often conflated. A critical-size defect, the point beyond which bone will not bridge on its own, is conventionally defined as a length over about 2 cm or loss of more than 50% of the cortical circumference; the regenerative capacity of bone is overwhelmed and the defect fills with fibrous tissue instead. That is a biological threshold, and it is convention rather than a measured cut-off. The practical threshold for choosing this operation is different and larger: most reported series reserve the induced-membrane technique for defects of roughly 2 to 5 cm and above, and the cohorts that define its results sit well beyond that, with 57% of Karger's defects exceeding 5 cm and Masquelet's original series spanning 4 to 25 cm.
What that means at the bedside. A 1.5 cm defect is critical-size but is usually managed by shortening, grafting or compression, not by a two-stage reconstruction. The workhorse role is the post-traumatic or post-infective long-bone defect, particularly of the tibia and femur, typically exceeding 4 to 5 cm, where acute shortening or conventional grafting would fail.
The membrane. The technique exploits the foreign-body reaction to the PMMA spacer. Rather than a nuisance, the fibrous capsule that forms, the induced membrane, is a biologically privileged structure that transforms a hostile defect into a favourable graft bed. It matures over 4 to 8 weeks and has three properties that matter:
- Richly vascularised, with a synovial-like epithelium on its inner surface; it behaves as a neo-periosteum, with an osteogenic surface layer facing the cement, and histologically it mimics true periosteal tissue
- Secretory, producing vascular endothelial growth factor (VEGF), transforming growth factor-beta (TGF-β1) and bone morphogenetic protein-2 (BMP-2), the osteoinductive and angiogenic factors that make it a biological chamber
- Containing, preventing graft resorption, soft-tissue interposition and fibrous ingrowth
The timing tension. The interval between stages is classically six to eight weeks, when the induced membrane is at its biological zenith. Pelissier's rabbit study is the source of all of this, and in it maximum BMP-2 production was at four weeks, at which point the membrane drove human bone marrow stromal cells toward the osteoblastic lineage; the authors themselves concluded that reconstruction "could be carried out earlier than previously thought". No human trial has settled the interval.
Relevant anatomy. Defects most frequently involve the tibia, femur and forearm, and each brings its own constraint:
- Key considerations
- Subcutaneous border; poor anteromedial soft-tissue envelope; often requires flap cover
- Key considerations
- Robust muscular envelope; favourable healing environment
- Key considerations
- Preservation of interosseous membrane and rotational axis critical
The blood supply. The periosteal and endosteal blood supply must be respected during debridement. The nutrient artery is frequently compromised, and healing then depends on periosteal and membrane-derived vascularity.
Clinical Assessment
The stories. A patient presenting for consideration of induced-membrane reconstruction usually offers one of four narratives:
- High-energy open fracture (Gustilo IIIB/IIIC), often with segmental bone loss at the time of injury or following serial debridement
- Chronic osteomyelitis requiring segmental resection of infected, sequestrated bone
- Infected non-union, frequently after multiple failed fixation attempts
- Tumour resection, occasionally, where biological reconstruction is preferred over endoprosthesis
The history. Document previous operations, antibiotic courses, smoking status, diabetes and nutritional state. All of them prejudice membrane quality and graft incorporation.
Examination. What you find depends on where the patient is in the pathway:
- Expected findings
- Deformity, shortening, sinus tracts or discharging wounds, soft-tissue scarring, adjacent joint stiffness
- Expected findings
- Stable limb with external fixator or internal fixation; wounds should be quiescent; a palpable spacer may be appreciated in subcutaneous bones
- Expected findings
- Progressive consolidation clinically and radiographically; resolution of mobility at the defect site
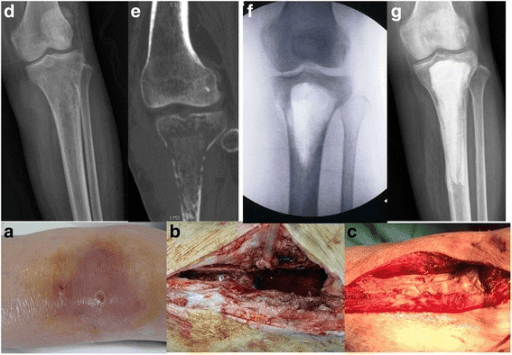
What it can be confused with. The induced membrane itself, and the clinical picture surrounding the technique, may be mistaken for several other entities:
- Periosteum, which the membrane mimics in structure and behaviour
- Infected collection or abscess: at second-stage surgery the fluid surrounding the spacer can resemble pus; culture and inspection are mandatory before proceeding to graft
- Foreign-body granuloma: histological appearances overlap, since the membrane is fundamentally a foreign-body reaction to PMMA
- Persistent non-union: slow graft incorporation on radiographs may be misread as failure; consolidation frequently requires up to a year
Investigations
Success of the second stage depends on rigorous assessment before the cement spacer is exchanged. The surgeon must be satisfied on two counts, that infection is controlled and that the membrane is biologically competent, and imaging, blood tests and tissue each answer part of that. The technique forgives many sins, but not sepsis.
Radiographs. Plain radiography remains the first-line investigation between stages. Assess:
- Position and integrity of the PMMA spacer, which should overlap the bone ends so that membrane is induced over viable cortex
- Stability of fixation, with no lucency around implants
- Evidence of persistent sequestrum, periosteal reaction or progressive osteolysis suggesting ongoing sepsis
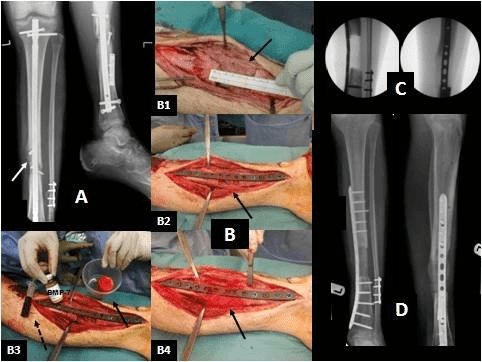
CT. CT gives superior delineation of defect geometry, occult sequestra and the quality of the bone ends. Measure defect length on orthogonal reconstructions: defects exceeding 5 cm traditionally favour induced-membrane reconstruction over acute shortening, and the upper limits at which the alternatives enter the discussion are set out under Management.
MRI. Valuable where residual osteomyelitis is suspected. It shows marrow oedema (low T1, high STIR signal), the classic penumbra sign of intraosseous abscess, a thin T1-hyperintense rim around a low-signal collection, and sinus tracts. Metal artefact reduction sequences are advisable in the presence of fixation.
Nuclear imaging. Labelled leucocyte scintigraphy or FDG-PET/CT is reserved for equivocal cases, where its high negative predictive value helps exclude persistent infection.
Blood tests. Serial inflammatory markers should be trending towards normal before second-stage grafting:
- Target prior to stage 2
- Normal or near-normal (<10 mg/L)
- Target prior to stage 2
- Falling trend; ideally normalised
- Target prior to stage 2
- Within reference range
- Target prior to stage 2
- >35 g/L (nutritional optimisation)
- Target prior to stage 2
- <8% in diabetic patients
Vitamin D deficiency should be corrected, and smoking cessation strongly encouraged, given their deleterious effect on graft incorporation.
Tissue, not serology. Definitive exclusion of infection rests on tissue sampling, and the principles mirror those established for prosthetic joint infection:
- Withhold antibiotics for at least two weeks before sampling where clinically safe
- Take a minimum of five deep tissue samples from representative sites (membrane, bone ends, medullary canal), each with clean, unused instruments
- Send specimens for extended-culture microbiology (including fungal and mycobacterial culture where indicated) and histopathology; more than five neutrophils per high-power field suggests active infection
- Sonication of removed spacers or implants improves organism yield in biofilm-associated infection
- Molecular techniques (16S rRNA PCR) may assist in culture-negative cases
Only when imaging, biochemistry and tissue diagnostics are concordant should the surgeon proceed to membrane preservation and autologous grafting.
Management & Decision-Making
Start with the defect and the limb. Measure the segmental bone loss after the planned debridement margins, and assess the soft-tissue envelope and limb perfusion; document sensation, vascularity and physiological reserve. Not every defect demands reconstruction, and conservative management or simpler measures are appropriate when:
- The defect is under 2 cm with a stable, well-vascularised envelope, where acute shortening or conventional grafting often suffices
- The limb is insensate or dysvascular, or the patient's physiological reserve is poor, where amputation may serve better
- Active, undrained infection persists, because reconstruction before source control invites failure
- The patient cannot tolerate or comply with a prolonged, staged pathway
Indications. Segmental defects of 2 to 25 cm, typically post-traumatic, post-infective (following excision of infected non-union or osteomyelitis) or post-tumour resection, and composite injuries where soft-tissue reconstruction can be staged alongside the first stage.
Choosing between reconstructions. Three options compete for the same defect, and they differ in the size they suit, how they handle infection and what they demand of surgeon and patient.
- Defect range
- 2 to 25 cm; best under 15 cm
- Infection handling
- Excellent — radical debridement plus antibiotic-loaded PMMA spacer; cultures guide timing of stage two
- Technical demand
- Moderate; two staged procedures 6 to 8 weeks apart
- Main drawbacks
- Needs large cancellous autograft volume (iliac crest or RIA, allograft dilution ideally 1:3 or less); graft resorption if membrane violated or over-compacted; union 80 to 90 percent
- Defect range
- Effectively unlimited; favoured for defects greater than 15 to 20 cm
- Infection handling
- Good — debridement plus transport through a clean bed, no bulk graft to seed
- Technical demand
- High; demands frame expertise and compliant patient
- Main drawbacks
- Prolonged frame time, pin-site infection, docking-site non-union often needing grafting, joint stiffness
- Defect range
- Typically greater than 6 cm; salvage after failed Masquelet
- Infection handling
- Good — living vascularised bone resists residual contamination
- Technical demand
- Highest; microvascular team, theatre time and monitoring
- Main drawbacks
- Donor-site morbidity, flap thrombosis risk, slow hypertrophy with protected weight-bearing for many months, stress fracture
The induced membrane is favoured by a defect of 2 to 25 cm, typically under 15 cm, with controlled infection, a healthy or flap-reconstructable soft-tissue envelope, adequate autograft supply from iliac crest or RIA, and a patient who can complete two stages 6 to 8 weeks apart. Transport or a vascularised fibula is favoured by a defect greater than 15 to 20 cm or a failed Masquelet, insufficient autograft volume for the chamber, recurrent infection despite spacer exchange, a need for concurrent limb lengthening or deformity correction, and available microvascular expertise with an acceptable donor fibula. At that size, or after a failed Masquelet, hybrid techniques sit alongside vascularised fibular transfer and bone transport as the options to consider, and beyond 10 to 15 cm those alternatives may already prompt consideration.
Read the length thresholds against the evidence. Karger, Hsu and Griffin all found that defect length does not itself predict failure to unite. In Hsu's analysis a defect of 7 cm or more and a pre-existing infected nonunion each raised post-operative infection, and infection lowered union, so length acts through infection. A 15 cm defect is not a reason to abandon the technique on length alone; it is a reason to put the whole effort into source control, and in that analysis an antibiotic-loaded spacer significantly reduced the need for revision.
Stage one. Debridement is the foundation of the operation, and everything after it depends on its being radical: inadequate debridement leaves a septic bed that dooms the reconstruction. The sequence:
- Radical debridement of all necrotic and infected bone until punctate bleeding, the "paprika sign"; send deep tissue for culture and histology
- Stabilisation with internal fixation (plate or nail) where infection is controlled, or external fixation if contamination is high
- Spacer insertion: PMMA cement, antibiotic-loaded where infection is suspected, moulded to fill the defect and overlap both bone ends, ideally by 1 to 2 cm
- Soft-tissue cover with a flap at the same sitting or within days; a healthy envelope is non-negotiable, and where the soft tissues are inadequate, flap coverage takes priority before proceeding
The interval. Over the following six weeks the membrane forms around the spacer, and the window is used to optimise the host: stop smoking, control diabetes and correct nutrition, all of them modifiable determinants of union. Positive cultures from stage one mean tailored antibiotics, delay of stage two, and consideration of repeat debridement with spacer exchange.
Stage two, typically 6 to 8 weeks later. The membrane is the biological chamber, and the operation is built around not damaging it:
- Incise the membrane longitudinally with care and preserve it
- Remove the spacer piecemeal, without damaging the membrane
- Freshen and reopen the medullary canals of both bone ends
- Fill the chamber with morcellised autologous cancellous graft from the iliac crest or RIA harvest, diluting with allograft or substitutes only if volume exceeds supply, ideally at no more than a 1:3 ratio
- Close the membrane over the graft, avoiding over-compaction, which impairs revascularisation
When to stop. If the membrane is violated, or purulence or recurrent infection is found at stage two, abandon grafting, re-debride and insert a new spacer; the maturation interval restarts before stage two is attempted again.
Complications & Outcomes
The technique carries a recognised complication profile across both stages. Reported failure rates requiring further intervention range from 10 to 50%, reflecting heterogeneity in defect aetiology, host physiology and technical execution, and failure is most often attributable to inadequate initial debridement or persistent infection rather than to graft biology. The six principal modes of failure are set out below, each with its prevention and its salvage:
- Mechanism
- Residual necrotic or septic bone; may declare only after second-stage grafting, especially post-traumatic and septic non-union
- Prevent by
- Radical debridement to bleeding bone ('paprika sign'); antibiotic-loaded cement spacer; deep multi-site tissue sampling; culture-directed systemic antibiotics; delay stage two until CRP and ESR normalise
- Salvage if encountered
- Return to first principles: repeat debridement, spacer exchange and a further induced-membrane cycle
- Mechanism
- Careless extraction strips the membrane, destroying its vascular and osteoinductive properties
- Prevent by
- Longitudinal incision of the membrane; gentle extraction, fragmenting cement in situ if needed; operate at 6 to 8 weeks when membrane biology is optimal
- Salvage if encountered
- Preserve and repair all remaining membrane over the graft; consider re-spacering and a fresh induction cycle if the sleeve is lost
- Mechanism
- Incomplete consolidation, particularly defects greater than 6 cm or where the membrane has been damaged
- Prevent by
- Avoid overpacking; cancellous autograft as the mainstay, adding limited allograft or demineralised matrix only when volume is insufficient; ensure stable fixation
- Salvage if encountered
- Revision fixation with supplementary autograft at the graft to host junction; consider bone transport or vascularised fibular graft if refractory
- Mechanism
- Immature, incompletely corticalised regenerate loaded too early; typically within the first two years
- Prevent by
- Protected weight-bearing until radiographic corticalisation; vigilance until full cortical remodelling is evident
- Salvage if encountered
- Usually heals with cast immobilisation or exchange nailing
- Mechanism
- Implant loosening or breakage during prolonged consolidation measured in months
- Prevent by
- Robust internal fixation from the outset (locked plating or intramedullary nailing); staged loading
- Salvage if encountered
- Revision fixation, commonly exchange nailing, with supplementary autograft as required
- Mechanism
- Pain, haematoma or lateral cutaneous nerve injury after iliac crest or RIA (Reamer-Irrigator-Aspirator) harvest
- Prevent by
- Meticulous harvest technique and nerve-aware exposure; RIA for large volumes; limit crest harvest volume
- Salvage if encountered
- Symptomatic management; neuropathic pain pathways for cutaneous nerve injury; evacuate significant haematoma
When salvage fails. Refractory cases may warrant conversion to bone transport, vascularised fibular grafting or, rarely in the lower limb, amputation following candid shared decision-making. In the SoFCOT series of 84, six of the eight failures required amputation, all severe leg injuries combining extensive defect, soft-tissue loss and infection; amputation remains a real endpoint in the long infected defect and must be named at consent.
Prognosis. The union rates quoted under Overview apply to appropriately selected patients, and even then 40 to 50% may require an additional procedure. Time to union is typically 6 to 12 months, though in the SoFCOT series the mean was 14.4 months from the first stage, reached after a mean of 6.11 interventions, with malalignment in 17% and delayed corrective surgery, mostly to the foot, in a further 16%. Adverse prognostic factors are smoking, diabetes mellitus, defects greater than 8 cm, prior infection and poor soft-tissue coverage, and smoking cessation should be considered near-mandatory before the second stage. Patients must be counselled that consolidation is measured in months, about the possibility of repeat grafting and donor-site morbidity, and that consent is for well over a year of treatment, not for an operation and a recovery.
Surveillance. Follow-up continues for a minimum of two years:
- Clinical review at 6-weekly intervals initially, assessing pain, wound status and weight-bearing progression, with protected weight-bearing advanced as consolidation appears
- Serial radiographs to monitor graft incorporation and corticalisation, with CT where union is equivocal
- Inflammatory markers (CRP, ESR) if infection is suspected
- Vigilance for late stress fracture until full cortical remodelling is evident
Guidelines, Registries & Global Practice
The Masquelet Induced-Membrane Technique: Global Variation in Practice
Overview
The induced-membrane technique, described by Alain-Charles Masquelet in 1986, remains a mainstay for segmental bone defect reconstruction. Its two-stage design—cement spacer insertion with membrane induction, followed by autologous grafting at six to eight weeks—is conceptually simple, yet worldwide practice is remarkably heterogeneous. The consultant should appreciate that much of what we "know" derives from case series rather than robust comparative evidence.
Variation in Practice
Practice differs at almost every decisional node:
- Spacer composition: Plain polymethylmethacrylate (PMMA) versus antibiotic-loaded cement. Most units add gentamicin or vancomycin empirically, though Masquelet's original description used plain cement, and laboratory data suggest antibiotic loading has little effect on membrane biology.
- Interval timing: The classical 6–8 week interval is honoured more in the breach; series report second stages from 4 weeks to over 6 months, particularly where infection eradication must be confirmed.
- Graft material: Iliac crest autograft remains the reference standard, but Reamer–Irrigator–Aspirator (RIA) harvest predominates in North America and much of Europe. Extenders—allograft, tricalcium phosphate, demineralised bone matrix—are commonly added when defect volume exceeds harvestable autograft, typically in ratios up to 1:3.
- Fixation: External fixation, plating, and intramedullary nailing are all reported; nail-plus-membrane constructs are increasingly favoured for femoral and tibial defects in well-resourced settings.
Resource-Setting Considerations
- High-resource settings
- RIA systems
- Resource-limited settings
- Iliac crest (open harvest)
- High-resource settings
- Commercial antibiotic cement
- Resource-limited settings
- Plain PMMA, hand-mixed antibiotics
- High-resource settings
- Locked nails/plates
- Resource-limited settings
- Monolateral or ring external fixators
- High-resource settings
- Vascularised fibula, bone transport
- Resource-limited settings
- Masquelet often preferred for its low technology burden
In low- and middle-income countries, the technique's appeal lies precisely in avoiding microsurgical expertise and specialised frames. Series from sub-Saharan Africa and South Asia report acceptable union rates despite delayed presentation and higher infection burdens, though follow-up attrition limits interpretation.
Guideline and Registry Evidence
Here candour is required: no national or international guideline mandates a specific Masquelet protocol, and no dedicated registry exists. The evidence base comprises:
- Systematic reviews (e.g. Morelli et al., 2016) pooling heterogeneous case series, reporting union rates of roughly 80–90% but with wide confidence intervals.
- The French Society of Orthopaedic Surgery (SoFCOT) symposium data, the nearest approximation to multicentre registry evidence, describing outcomes across French centres.
- No randomised trial has directly compared induced-membrane reconstruction with distraction osteogenesis; retrospective comparisons suggest broadly equivalent union with differing complication profiles.
Summary
The Masquelet technique exemplifies a procedure diffused globally ahead of its evidence. The prudent consultant adheres to sound principles—radical debridement, stable fixation, membrane preservation at second stage—while acknowledging that spacer additives, interval timing and graft augmentation remain matters of institutional custom rather than proven doctrine.
MCQ Practice Points
Q: What are the two stages of the Masquelet induced-membrane technique?
A: In stage one, after radical debridement, a PMMA cement spacer is placed in the defect and the limb is stabilised; over 6–8 weeks a vascularised induced membrane forms around the spacer. In stage two, the spacer is removed while preserving the membrane, and the cavity is filled with autologous cancellous bone graft, typically from the iliac crest or via RIA.
Q: What biological functions does the induced membrane serve?
A: The membrane acts as a biological chamber that secretes osteoinductive and angiogenic factors, including VEGF, TGF-β, and BMP-2. It also prevents graft resorption and fibrous tissue ingrowth, creating a privileged environment for bone healing.
Q: Which patients are candidates for the Masquelet technique?
A: Candidates have segmental defects large enough that spontaneous bridging will not occur — critical-size begins above about 2 cm or half the cortical circumference — but in practice the technique is reserved for defects of roughly 2 to 5 cm and above, most often after Gustilo IIIB open fractures, post-traumatic osteomyelitis, infected nonunion or tumour resection. Smaller critical-size defects are usually handled by shortening, compression or primary grafting rather than a two-stage reconstruction.
Q: Which bones are most commonly treated with this technique and why?
A: The tibia is the most frequent site because its precarious soft-tissue envelope and high rate of open fractures make segmental defects common. The femur is second, followed by the humerus, forearm, and less commonly the hand, foot, and clavicle.
Q: What range of defect sizes has been successfully reconstructed with the Masquelet technique?
A: Defects ranging from 4 to 25 centimeters have been successfully reconstructed. This makes the technique applicable across a remarkably wide range of anatomic and defect-size scenarios.
Q: Why is the Masquelet technique clinically important compared to alternatives?
A: It offers a technically accessible alternative to distraction osteogenesis (Ilizarov bone transport) and free vascularised fibular transfer, both of which require prolonged treatment. It also relies on the foreign-body response to create a favorable grafting environment rather than complex microsurgery or frame management.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 28-year-old male motorcyclist sustains a Gustilo-Anderson type IIIB open tibial fracture with a 6 cm segmental bone defect after debridement of contaminated, devitalized bone. Soft-tissue coverage is achieved with a free flap. The examiner asks: "Describe your strategy for reconstructing this bone defect using the induced-membrane technique, including the rationale, staging, and biological principles."”
“A 34-year-old motorcyclist sustains a Gustilo IIIB open tibial fracture. After serial debridements there is a 5 cm segmental diaphyseal defect with a compromised anteromedial soft-tissue envelope. The registrar asks whether the defect will heal if simply bridged with a plate. Outline your reconstructive strategy using the Masquelet technique, explaining the biological rationale, staging, and timing.”
“A 34-year-old smoker presents 8 weeks after a Gustilo IIIB open tibial fracture. Serial debridements have left a 6 cm segmental defect, managed at the index unit with an antibiotic-loaded cement spacer and external fixation. Wounds are quiescent; there are no sinuses. He is referred to you for the next stage of reconstruction. Discuss your assessment and management, including the biological rationale, timing, and intra-operative findings you might encounter at the second stage.”
Definition & Core Concept
- Two-stage surgery for segmental bone defect reconstruction; described by Masquelet, 1986
- Exploits foreign-body response to a PMMA cement spacer
- Spacer induces a vascularised, bioactive 'induced membrane' over 6–8 weeks
- Membrane = biological chamber for later bone grafting
Stage 1 vs Stage 2
- Stage 1: radical debridement → PMMA spacer in defect → limb stabilisation
- Wait 6–8 weeks for membrane formation around spacer
- Stage 2: remove spacer, preserve membrane, fill cavity with autologous cancellous graft
- Graft sources: iliac crest or RIA (reamer–irrigator–aspirator) from femoral canal
Membrane Biology
- Secretes osteoinductive & angiogenic factors
- Key factors: VEGF, TGF-β, BMP-2
- Prevents graft resorption and fibrous ingrowth
Patient Population & Indications
- Critical-sized defects (greater than 2 to 5 cm) that won't heal spontaneously
- Causes: high-energy open fractures (Gustilo IIIB), post-traumatic osteomyelitis, infected nonunion, tumour resection
- Skews young adult male (high-energy trauma demographics)
- Also used in paediatric congenital pseudarthrosis and blast injuries
Anatomic Distribution & Significance
- Most common site: tibia (poor soft-tissue envelope, frequent open fractures)
- Then femur > humerus > forearm > hand/foot/clavicle
- Defects of 4–25 cm successfully reconstructed
- Technically accessible alternative to Ilizarov bone transport and free vascularised fibula
Evidence Base
Reconstruction of the Long Bones by the Induced Membrane and Spongy Autograft
- The originating series: 35 cases of large diaphyseal defect reconstructed in two stages
- Stage one inserts a cement spacer, which is responsible for forming a pseudosynovial membrane; stage two reconstructs the defect with a large fresh autologous cancellous graft
- The membrane is described as preventing resorption of the graft and favouring its vascularity and corticalisation
- Defects reconstructed ranged from 4 to 25 cm
- In weight-bearing diaphyseal segments, normal walking was possible at a mean of 8.5 months
Induced Membranes Secrete Growth Factors Including Vascular and Osteoinductive Factors and Could Stimulate Bone Regeneration
- The biology behind the technique, studied in RABBITS with membranes harvested at 2, 4, 6 and 8 weeks after spacer implantation
- Histology showed rich vascularisation of the induced membrane
- Immunochemistry demonstrated production of growth factors VEGF and TGF-beta1 and the osteoinductive factor BMP-2
- MAXIMUM BMP-2 PRODUCTION WAS AT FOUR WEEKS - not later - and at that time the membranes favoured differentiation of human bone marrow stromal cells toward the osteoblastic lineage
- The authors' conclusion follows directly: bone reconstruction could be carried out EARLIER than previously thought