Capitellar Osteochondrosis | Self-Limiting | Boys Under 10 | Excellent Prognosis
- Osteochondrosis (avascular necrosis) of the capitellar ossification centre in young children
- Boys under 10 years, usually the dominant arm - distinct from adolescent OCD
- Whole epiphysis involved with NO loose body formation - this separates it from OCD
- Self-limiting - the capitellum reossifies and remodels with rest alone
- Excellent prognosis - surgery is essentially never required for true Panner disease
- “Age is the single best discriminator: under 10 thinks Panner, teenager thinks OCD
- “Treat with activity restriction - no throwing or weight-bearing on the elbow
- “Loose bodies or a focal unstable fragment mean OCD, not Panner disease
- “Early radiographs can be normal - MRI is the most sensitive early test
Overview and Epidemiology
Panner disease (capitellar osteochondrosis) is an osteochondrosis of the capitellum, the lateral ossification centre of the distal humerus: a disturbance of the normal endochondral ossification of an epiphyseal growth centre. It was first described by the Danish radiologist Hans Jessen Panner in the 1920s. The initiating event is traditionally described as avascular necrosis, but the cause of the osteochondroses as a group is not settled (see Pathophysiology below).
Who gets it. Panner disease is rare, and most published evidence comes from case reports and small series. It characteristically affects boys younger than 10 years, most commonly around 5 to 10 years of age, and usually involves the dominant arm.
A lateral compression injury. It is one of the two recognised lateral compression injuries of the immature elbow. The other is osteochondritis dissecans (OCD) of the capitellum, which affects an older, adolescent age group. Both are seen more often in children exposed to repetitive valgus loading of the elbow, such as throwers and gymnasts, although Panner disease can also occur with no sporting history at all.
What the examiner is testing. Panner disease is a discriminator topic. A candidate who simply says "osteochondrosis of the capitellum, treat with rest" has done well, but the examiner is really testing whether you can confidently separate it from osteochondritis dissecans of the capitellum and explain why that distinction changes management. Framing the two as a continuum of disordered endochondral ossification, separated largely by age, signals genuine understanding.
Pathophysiology and Anatomy
The capitellum. The rounded lateral part of the distal humeral articular surface, it articulates with the radial head. It develops from a secondary ossification centre that is usually the first to appear at the elbow, around age 1 to 2 years, and ossifies progressively through childhood.
The blood supply. Like other epiphyses during active ossification, the capitellum has a relatively tenuous blood supply, which leaves it vulnerable during periods of rapid growth and mechanical loading. The ossification centre is supplied by only one or two end-arteries, from the radial and interosseous recurrent vessels, which enter the capitellum posteriorly and cross the physis to reach the epiphysis. They are isolated end-arteries with little or no anastomotic collateral, a watershed, so the ossifying centre has no alternative supply if their flow is interrupted.
The load. During throwing and other valgus-loading activities the lateral side of the joint, the radiocapitellar articulation, is compressed while the medial side is under tension. This lateral compression is the mechanical stress most associated with capitellar osteochondral problems. The watershed pattern is what makes the capitellum prone to ischaemia and avascular necrosis when repetitive radiocapitellar compression disrupts perfusion during the ossification window, and it is the shared anatomical basis of both Panner disease and capitellar OCD.
The traditional mechanism. The most-cited explanation is avascular necrosis of the capitellar ossification centre: a vulnerable, immature blood supply plus repetitive lateral compressive load is thought to disrupt perfusion, producing ischaemia and necrosis of the whole epiphysis, seen radiographically as fragmentation and sclerosis. Whatever initiates it, the sequence that follows is consistent and benign. Because the entire centre is involved in a child with high growth and remodelling potential, it spontaneously revascularises, reossifies and remodels, restoring near-normal architecture, which explains the excellent natural history.
Say "traditional", not "proven". The aetiology of the osteochondroses as a group remains uncertain: genetic, hormonal, mechanical, repetitive-trauma and vascular factors have all been proposed (Achar, carded below), and no study has demonstrated the vascular insult in Panner disease directly. This matters conceptually rather than practically. It is precisely because the cause is unsettled that the field describes Panner disease and capitellar OCD as a continuum of disordered endochondral ossification rather than as two vascular events, and it is why the descriptive term osteochondrosis is preferred in current writing.
Two patterns on one continuum. The continuum view is widely held. In the younger child the whole epiphysis is involved and heals (Panner disease); in the older adolescent a focal segment of subchondral bone and overlying cartilage is affected and may become unstable or detach to form a loose body (OCD). Age at onset largely determines which pattern, and which prognosis, is seen.
Classification
Panner disease itself has no widely used formal classification. The clinically important task is to place a capitellar osteochondral lesion on the Panner-to-OCD spectrum and, if it is OCD, to judge lesion stability. The single most useful discriminator in the exam and in clinic is age at presentation, supported by whether the lesion is diffuse or focal and whether there is any loose body.
- Panner Disease
- Under 10 years (first decade)
- OCD of Capitellum
- Adolescent (second decade)
- Panner Disease
- Whole capitellar epiphysis
- OCD of Capitellum
- Focal area of capitellum
- Panner Disease
- No
- OCD of Capitellum
- Possible (if fragment detaches)
- Panner Disease
- Absent
- OCD of Capitellum
- May be present with loose body
- Panner Disease
- Excellent, self-limiting
- OCD of Capitellum
- Variable, depends on stability
- Panner Disease
- Essentially never
- OCD of Capitellum
- May be needed for unstable lesions
TENPanner vs OCD - The Age Rule
Hook:Remember TEN: the magic age is around ten - younger children get whole-epiphysis Panner disease with no loose bodies; older children get focal OCD that can detach.
Stability, once in OCD territory. If the lesion is OCD rather than Panner disease, stability of the osteochondral fragment drives management.
- Stable lesion - intact overlying cartilage, no displacement - often managed conservatively, similar in spirit to Panner disease
- Unstable lesion - cartilage breach, fragment mobility or a loose body - the group that may require surgery (fixation, debridement/microfracture, or osteochondral grafting)
The practical point for Panner disease is the converse. True Panner disease is, by definition, the stable, whole-epiphysis, no-loose-body end of the spectrum, and therefore does not need surgery.
Clinical Presentation
History. The child typically presents with an insidious, dull ache over the lateral aspect of the elbow, sometimes related to throwing or other repetitive elbow activity but frequently with no clear injury at all. Pain is usually mild and activity-related, and parents may notice the child holding the arm slightly bent or being reluctant to straighten it fully. The child is systemically well; fever or malaise should prompt consideration of infection instead.
Look and feel. There may be a small effusion or mild swelling over the lateral elbow, often subtle, and the child frequently holds the elbow in slight flexion. Tenderness over the radiocapitellar joint is the key local sign. Pain may be reproduced by activities that load the radiocapitellar joint, consistent with the lateral compression mechanism.
Movement. A mild loss of full extension, a flexion contracture of a few degrees, is characteristic, and flexion is usually preserved. Significant mechanical locking or catching is not typical of Panner disease; if present, it suggests a loose body and therefore OCD. The neurovascular examination is normal, and any deficit points away from Panner disease.
Investigations and Diagnosis
Radiographs. AP and lateral radiographs of the elbow are the first-line investigation; comparison with the unaffected side can help in a young child with immature ossification. Typical findings:
- Fragmentation and irregular ossification of the capitellar centre, which nonetheless retains its overall shape
- Sclerosis (increased density) of the affected centre
- A small joint effusion and a slightly irregular articular contour
- No loose bodies and no large focal defect; their presence suggests OCD instead
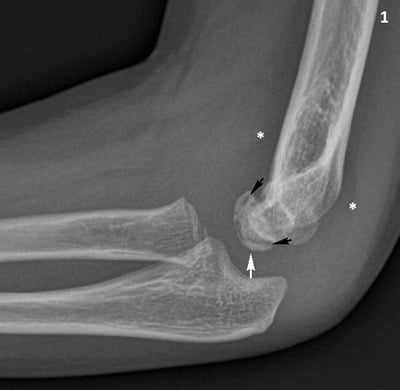
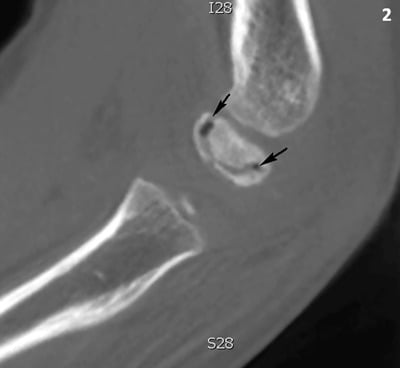
The early film can be normal. A normal radiograph in a young child with a convincing clinical picture does not exclude Panner disease, and should prompt MRI if symptoms persist.
The normal-variant trap. The capitellum normally ossifies from a single centre, but it can ossify irregularly or from multiple (multicentric) foci, giving a fragmented, notched or mottled appearance that is a normal finding in young children. That appearance can look radiographically identical to the fragmentation and sclerosis of Panner disease, so the diagnosis is clinical. Panner disease is the radiographic change plus localised radiocapitellar tenderness, a small effusion, a slight loss of extension and activity-related lateral pain; an asymptomatic irregular capitellum, found incidentally or on the pain-free contralateral side, is a normal variant, not disease, and should not be labelled Panner.
MRI. MRI is more sensitive than radiographs for early disease, showing capitellar bone marrow oedema before radiographs change. It is the investigation of choice when films are normal but symptoms persist, or when the diagnosis is unclear. Findings in Panner disease:
- Diffuse low signal on T1 of the capitellar epiphysis (marrow replacement by ischaemia/oedema)
- High signal on fat-saturated T2, reflecting bone marrow oedema of the whole epiphysis
- Preserved overall epiphyseal contour, with no separated osteochondral fragment
MRI also assesses the overlying articular cartilage and fragment stability, the key feature separating self-limiting Panner disease from an unstable OCD lesion that may need surgery.
Ultrasound. Ultrasound can detect capitellar surface irregularity, but in young children mild irregularity may simply reflect normal variation in ossification rather than disease, so its findings must be interpreted with caution.
Differential diagnosis. Five conditions matter in the child with elbow pain:
- Osteochondritis dissecans of the capitellum - the single most important differential. It occurs in adolescents, is a focal lesion, and may produce loose bodies, locking and a poorer prognosis.
- Little League elbow (medial epicondyle apophysitis/avulsion) - a medial overload problem of the throwing child, in contrast to the lateral pain of Panner disease.
- Occult fracture of the radial neck or lateral condyle after trauma - the history of injury and a fracture line distinguish it.
- Septic arthritis or osteomyelitis - the child is systemically unwell with fever and raised inflammatory markers; the effusion is tense and the joint is irritable in all directions.
- Normal ossification variant - irregular, multicentric capitellar ossification without the clinical findings of disease (above).
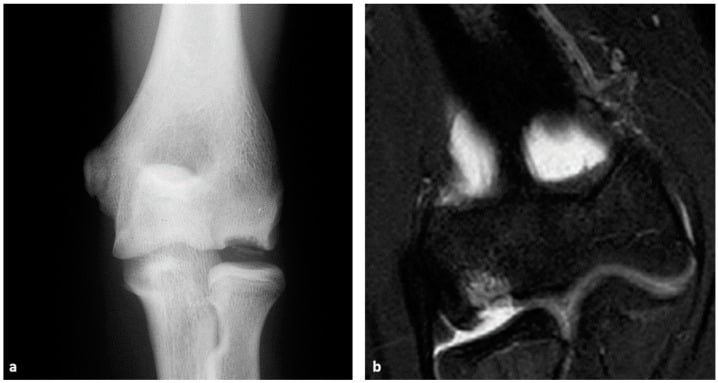
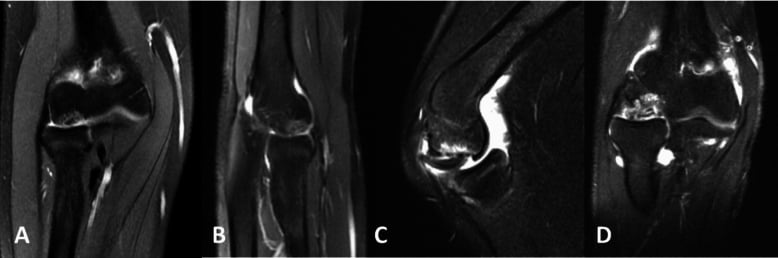
A practical pathway.
- Clinical pattern - a systemically well boy under 10 with lateral elbow pain, mild effusion and a slight loss of extension.
- Plain radiographs, of both elbows if needed - fragmentation and sclerosis of the whole capitellar centre with no loose body.
- MRI if films are normal or the picture is atypical - diffuse capitellar marrow oedema with a preserved contour supports Panner disease; a focal unstable fragment suggests OCD.
- Place it on the spectrum - young age, diffuse involvement and no loose body mean Panner disease and conservative management; an older child, a focal lesion or a loose body mean OCD, assessment of stability and consideration of surgery.
Management
The principle. True Panner disease is managed conservatively; there is no role for surgery. The aim is symptom relief and protection of the capitellum while it reossifies. Treatment starts by confirming that it is true Panner disease: a young child, diffuse capitellar involvement, no loose body and no unstable fragment on MRI.
The measures.
- Activity restriction - stop throwing, gymnastics, weight-bearing on the elbow and other elbow-loading activities. This is the single most important intervention and the mainstay of treatment.
- Relative rest and analgesia - short-term rest, ice after activity and judicious NSAIDs for comfort.
- Temporary immobilisation if painful - a sling or a short period of splinting or casting can settle an acutely painful elbow, followed by early gentle remobilisation to avoid stiffness.
- Graded return - range of motion and then loading are reintroduced only once symptoms have settled and reossification is under way; return to sport is gradual, once the child is asymptomatic with restored motion.
Follow-up and expected course. Clinical and, if needed, radiographic follow-up confirms that symptoms are settling and reossification is progressing. Symptoms typically settle over weeks to a few months, while radiographic reconstitution of a near-normal capitellum takes many months: the radiographic appearance lags behind clinical recovery.
Reconsider the diagnosis and look for osteochondritis dissecans if the child is adolescent, if there is mechanical locking or catching, or if imaging shows a focal unstable fragment or a loose body. These features take the lesion off the self-limiting Panner pathway and into the OCD pathway, where surgery may be required. Treating an unstable OCD lesion as benign Panner disease risks progressive joint damage.
Complications and Prognosis
Panner disease is fundamentally a benign, self-limiting condition, and complications attributable to the disease itself are uncommon. The main hazards are diagnostic and iatrogenic.
Natural history. With activity restriction the capitellum reossifies and remodels, and most children regain a normal, pain-free elbow with full or near-full motion. A small number may have minor radiographic flattening or a slight residual loss of terminal extension, usually without functional consequence.
Misdiagnosis as, or progression to, OCD. The most important pitfall is failing to recognise an osteochondritis dissecans lesion, especially in an older child: such a lesion can become unstable, form loose bodies, cause locking and lead to early radiocapitellar degeneration if mismanaged.
Overtreatment. Unnecessary surgery, or prolonged rigid immobilisation with resulting elbow stiffness, in a child who has true, self-limiting Panner disease are avoidable harms.
Long-term outlook. There is no recognised direct association between true Panner disease and later osteoarthritis; the long-term risk lies with unrecognised or unstable OCD lesions, not with the benign childhood entity.
Guidelines, Registries & Global Practice
Global Epidemiology
Panner disease is a rare paediatric osteochondrosis reported worldwide with a remarkably consistent profile across published series: boys younger than 10 years, the dominant arm, and a benign self-limiting course. Because it is uncommon and benign, the evidence base is built almost entirely from case reports and small series rather than registries or trials, and there is no arthroplasty, trauma or implant registry that tracks it. Reported associations with throwing and gymnastic activities reflect the lateral compression mechanism common to immature-elbow osteochondral lesions.
Guideline and Society Positions
- Position on Panner disease
- Clinical and radiographic diagnosis on the Panner-to-OCD spectrum; conservative management with activity restriction; no operative role for true Panner disease
- Position on Panner disease
- Managed conservatively within paediatric elbow and "the painful elbow in a child" pathways; image to exclude OCD and other causes, and reassure regarding natural history
- Position on Panner disease
- Same conservative consensus; MRI reserved for normal radiographs with persistent symptoms or to assess OCD stability
- Position on Panner disease
- Self-limiting osteochondrosis of the capitellum; treat the cause of lateral compression, restrict activity, and distinguish from OCD
No society publishes a dedicated Panner disease guideline because management is uncontroversial and uniformly non-operative; recommendations are extrapolated from the broader paediatric elbow and osteochondrosis literature.
High- vs Limited-Resource Practice
In well-resourced settings, radiographs confirm the diagnosis and MRI is available for normal-film cases or to assess OCD fragment stability. In limited-resource settings the diagnosis remains clinical and radiographic, and activity restriction with simple analgesia achieves the same excellent outcome without advanced imaging. The universal teaching point is identical everywhere: recognise the entity, separate it from osteochondritis dissecans, avoid unnecessary surgery, and reassure the family.
Related pages: Osteochondritis Dissecans of the Capitellum is the other half of this page - the same joint surface, the older child, the focal lesion that can detach - and the two should be read together because the whole diagnostic task here is deciding which one you are looking at. Little League Elbow is the medial-side counterpart of the same throwing load and the commonest reason a young thrower's elbow hurts on the wrong side. Lateral Elbow Pain and Systematic Approach to Elbow Imaging give the wider differential and the films, while Paediatric Elbow Radiology Assessment covers the ossification-centre sequence you must know before calling an irregular capitellum abnormal. Capitellum Fractures and Nursemaid's Elbow are the traumatic entities that present to the same clinic. Among the other osteochondroses, Kohler Disease, Freiberg Disease, Osgood-Schlatter Disease and Legg-Calve-Perthes Disease share the unresolved aetiology and the same imaging-lags-behind-symptoms behaviour. The Limping Child is the presentation-level framework, and Septic Arthritis Pathophysiology is the diagnosis that must be excluded before an irritable joint in a child is called an osteochondrosis.
Controversies and Areas of Uncertainty
- Aetiology is uncertain. The cause of osteochondrosis in general, and Panner disease specifically, remains unproven; genetic, hormonal, mechanical, repetitive-trauma and vascular factors have all been proposed and likely interact during the vulnerable ossification window.
- Panner versus OCD - one disease or two? Most authorities regard them as a continuum of disordered endochondral ossification separated mainly by age, but the exact boundary is blurred and some lesions are difficult to classify, which directly affects whether surgery is considered.
- Disease versus normal variant. Irregular, multicentric capitellar ossification can be a normal radiographic finding in young children, and minor subchondral surface irregularity on ultrasound may reflect normal development rather than disease - so imaging must always be correlated with clinical findings.
- Role and timing of MRI. MRI is the most sensitive early test and is valuable when radiographs are normal or to assess OCD stability, but it is not required for every typical case and may involve sedation in very young children.
- Naming trap. Do not conflate true childhood Panner disease with adolescent OCD - misapplying the benign label to an unstable OCD lesion risks under-treating a condition that can cause loose bodies and joint damage.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“An 8-year-old boy presents with a few weeks of dull pain over the outer aspect of his dominant elbow and a slight inability to fully straighten it. There is a small effusion and tenderness over the radiocapitellar joint. He is otherwise well. What is your diagnosis and how would you manage him?”
“A 14-year-old competitive baseball pitcher has lateral elbow pain and intermittent catching. Radiographs show a focal lucent lesion of the capitellum with a separate ossific fragment. The referring doctor has labelled this Panner disease. What are your thoughts?”
“A 7-year-old boy has three weeks of lateral elbow pain and a small loss of extension. His elbow radiographs are reported as normal. The family wants to know why he still has pain and what you will do next. How do you proceed?”
Definition
- Osteochondrosis (AVN) of the capitellum
- Lateral ossification centre of distal humerus
- A lateral compression injury of the elbow
- Whole epiphysis involved
Demographics
- Boys under 10 years (first decade)
- Usually the dominant arm
- Rare condition
- Linked to throwing and gymnastics
Clinical Features
- Dull lateral (radiocapitellar) elbow pain
- Small effusion and mild swelling
- Slight loss of full extension
- No mechanical locking, systemically well
Imaging
- Radiographs: fragmentation and sclerosis, shape kept
- NO loose bodies (key point)
- Early films may be normal
- MRI most sensitive - diffuse capitellar marrow oedema
Panner vs OCD
- Panner = under 10, whole epiphysis, no loose body
- OCD = adolescent, focal lesion, may form loose bodies
- Continuum of disordered ossification
- Age is the best discriminator
Treatment
- CONSERVATIVE ONLY
- Activity restriction from elbow loading
- Analgesia, short immobilisation if painful
- NO surgery for true Panner disease
Prognosis
- Self-limiting, excellent outcome
- Capitellum reossifies and remodels
- Radiographic healing lags symptoms
- Main risk is misdiagnosing unstable OCD
Evidence Base
Lateral Compression Injuries: Panner Disease and OCD of the Capitellum (Key Review)
- Panner disease is an osteochondrosis of the capitellum, a rare disorder usually affecting the dominant arm in children younger than 10 years
- Symptomatic management - reduction of stressful elbow activities - is usually sufficient to allow resolution
- Healing takes a prolonged period but most patients show excellent long-term results
- OCD of the capitellum occurs in adolescents and is associated with loose body formation; Panner disease and OCD likely represent a continuum of disordered endochondral ossification with presentation and prognosis depending mainly on age at onset
Apophysitis and Osteochondrosis: Common Causes of Pain in Growing Bones
- Osteochondrosis refers to degenerative changes in the epiphyseal ossification centres of growing bones, with the capitellum being the site of Panner disease
- The aetiology of osteochondrosis is uncertain, with genetic, hormonal, mechanical, repetitive-trauma and vascular factors proposed
- Radiographs may be normal initially; MRI is more sensitive to early changes
- Osteochondrosis generally resolves with relative rest, and surgery is rarely needed