Suprascapular Nerve | Suprascapular & Spinoglenoid Notch | Overhead Athletes
- Two notches, two patterns: suprascapular notch lesion weakens supraspinatus AND infraspinatus; spinoglenoid notch lesion weakens infraspinatus ONLY
- Paralabral cyst: arises from a posterosuperior labral tear acting as a one-way valve; the classic spinoglenoid notch compressor
- Isolated infraspinatus wasting in an overhead athlete is suprascapular neuropathy at the spinoglenoid notch until proven otherwise
- EMG/NCS is the diagnostic standard; MRI finds the compressive lesion and shows muscle atrophy/fatty change
- Most cases are non-operative; decompress a discrete compressive lesion or refractory symptoms
- “Supraspinatus spared = lesion is at the spinoglenoid notch (distal)
- “Cyst means look for the labral tear that feeds it
- “Painless isolated infraspinatus wasting is common and often asymptomatic in athletes
- “Routine nerve release adds nothing to rotator cuff repair (Level I evidence)
Overview and Epidemiology
Suprascapular neuropathy is compression or traction of the suprascapular nerve along its course over the scapula. It produces posterior shoulder pain and weakness of external rotation and/or abduction, and is thought to cause roughly 2% of chronic shoulder pain (Clavert and Thomazeau, DOI).
Why it matters. It is an easily missed cause of posterior shoulder pain and weakness that mimics a rotator cuff tear with normal tendons. Historically it was considered a diagnosis of exclusion and it is now recognised more often. Recognising the notch-specific weakness pattern is high-yield.
Who. It affects overhead athletes and older patients with cuff tears.
- Overhead athletes: volleyball, baseball, tennis and swimming. Isolated infraspinatus wasting is common in elite volleyball players, often in the dominant (hitting) shoulder.
- Older patients: traction from large or retracted rotator cuff tears.
Pathophysiology and Anatomy of Suprascapular Neuropathy
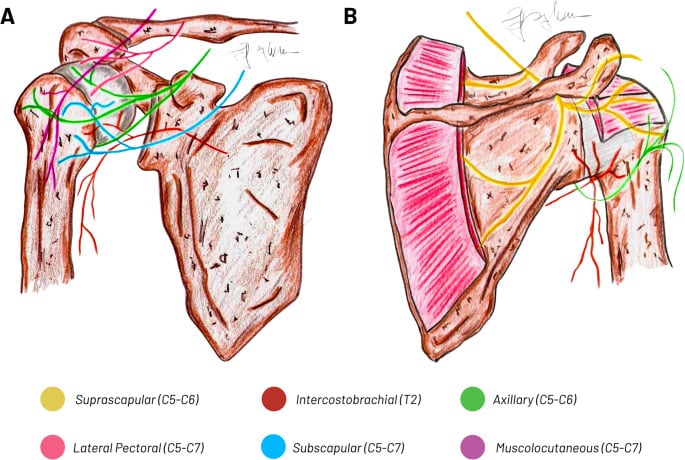
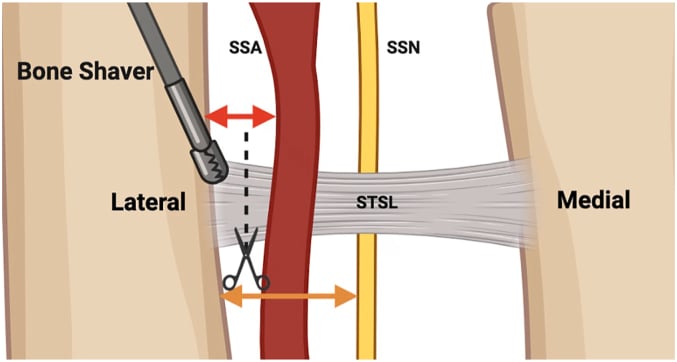
The course. The suprascapular nerve arises from the upper trunk of the brachial plexus (C5-C6) and runs across the posterior triangle of the neck to the scapula. At the suprascapular notch it passes UNDER the transverse scapular ligament while the suprascapular artery passes OVER it: "Army over Navy", artery over, nerve under. It supplies supraspinatus, then curves around the base of the scapular spine through the spinoglenoid notch to reach infraspinatus.
Why the notch determines the deficit. The motor branches to supraspinatus leave the nerve at or proximal to the suprascapular notch, and the branches to infraspinatus are given off after the nerve rounds the spinoglenoid notch. A suprascapular notch lesion therefore weakens both muscles, while a spinoglenoid notch lesion weakens infraspinatus only and spares supraspinatus.
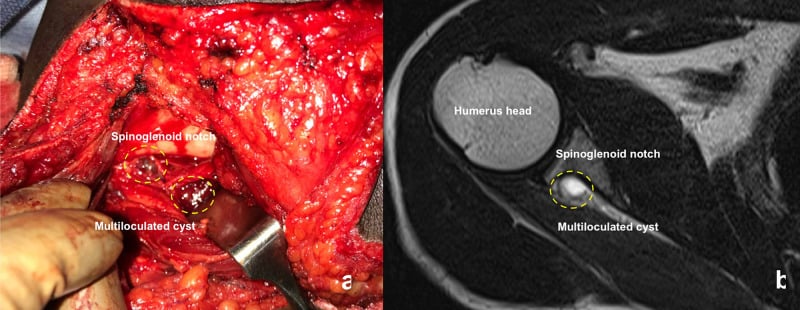
Compression. A paralabral (ganglion) cyst, an ossified or hypertrophied transverse scapular ligament, a tumour or distended veins narrow the notch, and a scapular fracture is another compressive cause. The paralabral cyst arises from a posterosuperior labral tear acting as a one-way valve and is the classic compressor at the spinoglenoid notch. When a cyst is present, always look for the labral tear beneath it.
Traction. Repetitive overhead motion stretches the nerve over a fixed point. The "sling effect" of the spinoglenoid ligament tethers the nerve during cross-body adduction and internal rotation, and a large retracted cuff tear can also pull on the nerve medially.
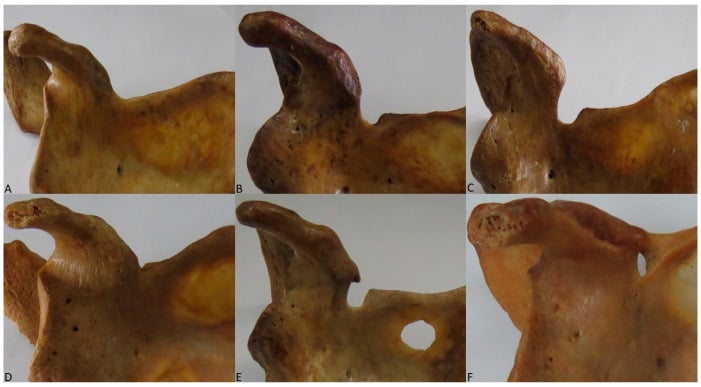
Notch shape. A deep, narrow (U-shaped) suprascapular notch crowds the nerve and is associated with a higher entrapment risk.
Why It Hurts: The Nerve's Articular Sensory Territory
A motor nerve with a large joint territory. Beyond supplying supraspinatus and infraspinatus, the suprascapular nerve provides articular (sensory) branches to roughly two-thirds to 70% of the shoulder joint: the posterosuperior glenohumeral capsule, the acromioclavicular joint, the subacromial bursa and the coracoclavicular and coracoacromial ligaments. It has no cutaneous territory.
Why the pain is deep and poorly localised. The sensory supply is deep, capsular and non-dermatomal, so entrapment produces a diffuse, aching, hard-to-point-to posterolateral shoulder pain rather than a sharp, mappable one. That is a useful contrast with C5-C6 radiculopathy, which follows a dermatome.
Why the nerve block works. A suprascapular nerve block anaesthetises that large articular territory. It is diagnostic here, since temporary relief supports the diagnosis, and it is a recognised analgesic tool for shoulder pain more broadly: adhesive capsulitis, post-operative pain and chronic degenerative or hemiplegic shoulder pain. Ultrasound- or landmark-guided blocks target the nerve in the floor of the suprascapular fossa.
Why pain can outlast decompression. Pain can persist after a technically successful decompression if the articular pain generator, the labral tear or the capsule, is not also addressed, which is why several series report residual pain.
Classification Systems
By site. The clinical pattern of weakness localises the lesion before imaging.
- Supraspinatus
- Weak
- Infraspinatus
- Weak
- Typical Cause
- Ligament ossification, cyst, traction
- Supraspinatus
- Spared
- Infraspinatus
- Weak
- Typical Cause
- Paralabral cyst, spinoglenoid ligament
- Supraspinatus
- Variable
- Infraspinatus
- Variable
- Typical Cause
- Traction injury, neuralgic amyotrophy mimic
By mechanism. The mechanism drives whether the nerve itself needs surgery.
- Example
- Paralabral cyst, tumour, ossified ligament
- Implication
- Address the lesion; good prognosis if decompressed early
- Example
- Overhead athlete, retracted cuff tear
- Implication
- Treat the underlying cause; nerve release often unnecessary
- Example
- Scapular fracture, surgical injury
- Implication
- Depends on continuity of the nerve
Clinical Assessment
History. The pain is deep and poorly localised over the posterolateral shoulder, with weakness of external rotation, and of abduction if the lesion is proximal. Ask about repetitive overhead activity and which arm is dominant. A cyst can present with pain even before weakness develops, while isolated infraspinatus wasting may be painless and found incidentally. The red flags are rapid progression and a suspected mass.
Examination. Always compare both shoulders from behind.
- Wasting of infraspinatus and/or supraspinatus in the fossa
- External rotation weakness with the arm at the side
- Abduction weakness if supraspinatus is involved (a notch lesion)
- Tenderness over the suprascapular or spinoglenoid notch
- Compensation: deltoid and trapezius overactivity, altered scapular rhythm
Differential diagnosis. Consider these before attributing the symptoms to the nerve:
- Rotator cuff tear
- C5-C6 cervical radiculopathy
- Parsonage-Turner syndrome (neuralgic amyotrophy)
- Quadrilateral space syndrome (axillary nerve)
- A posterosuperior labral tear without neuropathy
Investigations
EMG and nerve conduction studies are the diagnostic gold standard. Prolonged motor latency to supraspinatus and/or infraspinatus, with denervation potentials, confirms and localises the neuropathy and grades its severity. Pain can occur with a normal study.
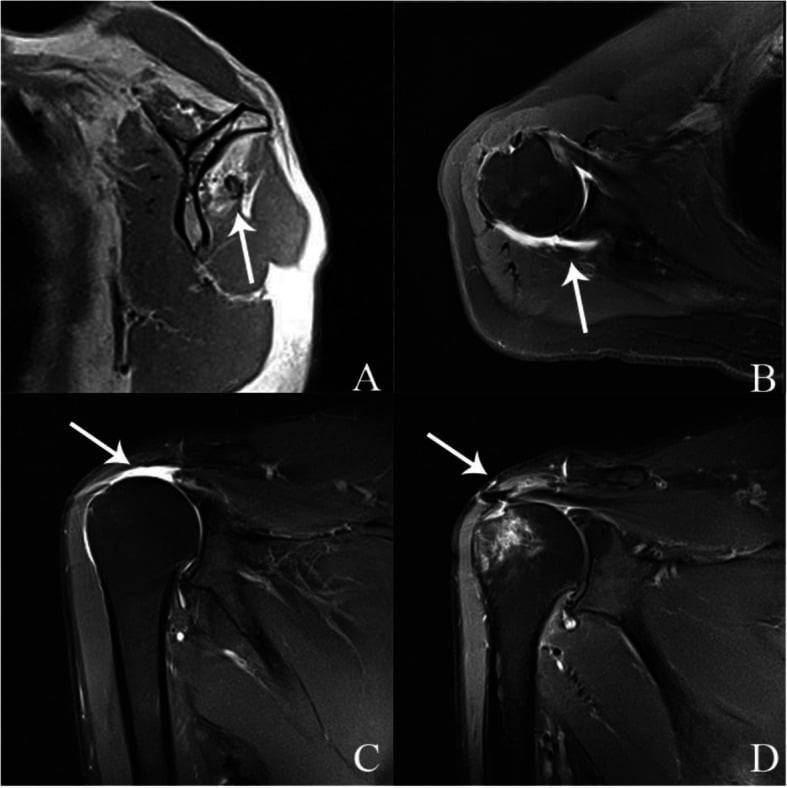
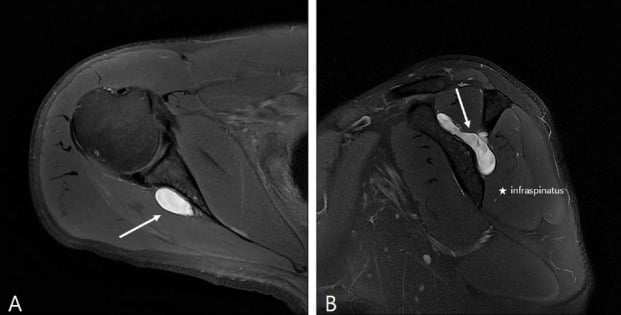
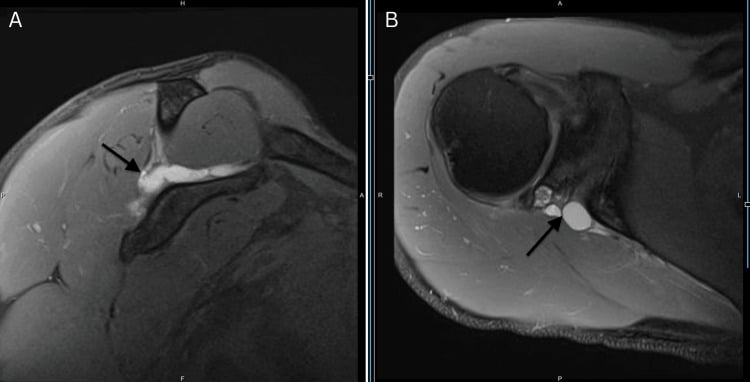
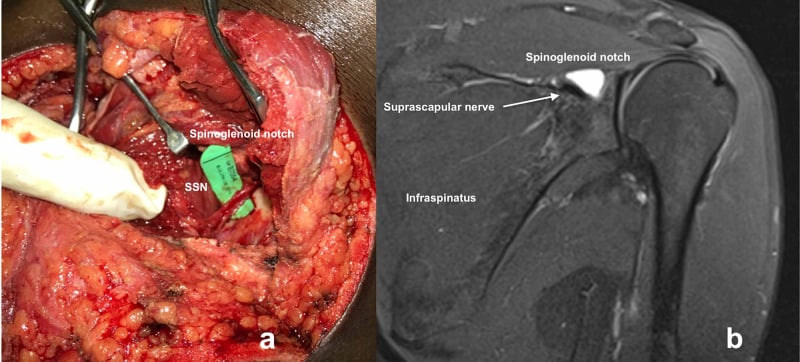
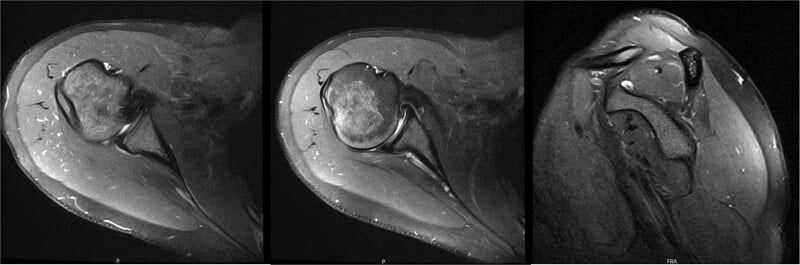
MRI is best for the compressive lesion. It shows a paralabral cyst and the labral tear feeding it, muscle oedema (acute denervation) or fatty atrophy (chronic), and excludes a mass. EMG confirms the neuropathy and MRI finds its cause, so both are usually needed.
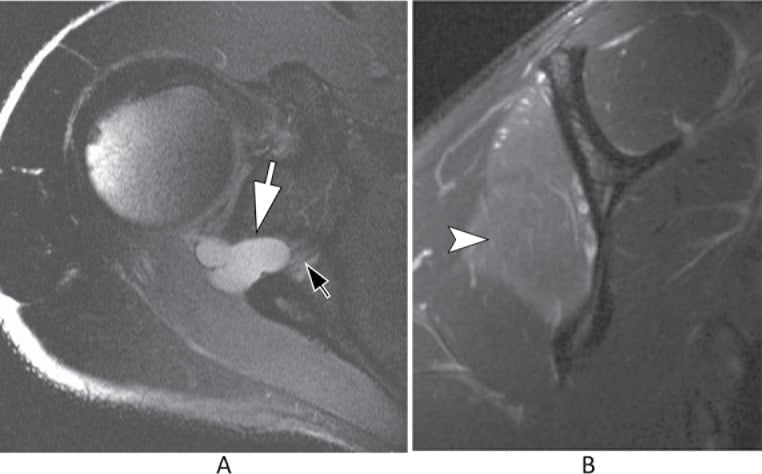
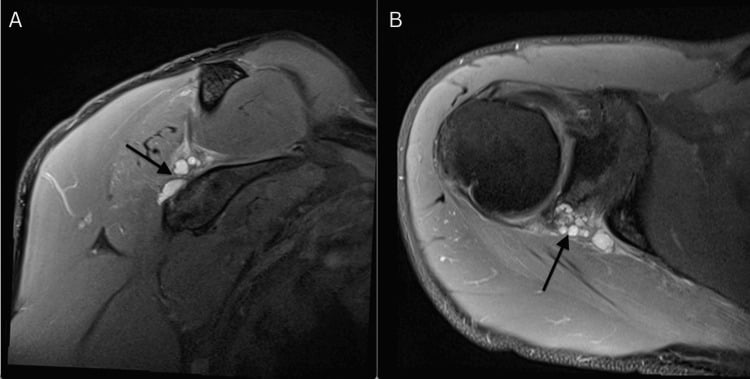
Mimics on MRI. Distended spinoglenoid notch veins can mimic a paralabral cyst on MRI and must be distinguished before percutaneous aspiration (Carroll, PMID 12589484). A haematoma can do the same.
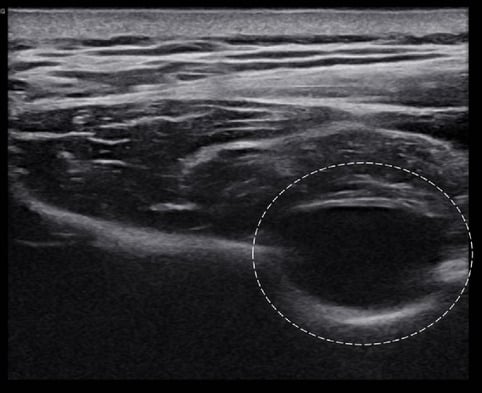
Ultrasound can show a cyst and guide aspiration. The diagnostic suprascapular nerve block is described above, with the nerve's articular territory.
Management Algorithm
Non-operative first. Most isolated neuropathies, particularly painless wasting in athletes, are managed non-operatively. In overhead athletes isolated infraspinatus wasting is often painless and well tolerated: compressive neuropathy is common in this group, yet many have no clinically relevant deficit (Strauss, PMID 32732653). High prevalence does not equal a surgical indication.
- Activity modification: reduce provocative overhead load, especially for athletes with painless wasting who are functioning well
- Physiotherapy: scapular stabilisation and cuff and periscapular strengthening, restoring scapulohumeral rhythm and recruiting compensators where infraspinatus is weak
- NSAIDs and nerve block: analgesia, and a diagnostic and therapeutic suprascapular nerve block
- Image-guided aspiration: consider it for a symptomatic paralabral cyst
Aspiration. Image-guided aspiration can relieve a spinoglenoid cyst (Wee, PMID 30283206), but it is often a temporising measure, and recurrence is common unless the feeding labral tear is repaired.
Surgical indications. Consider decompression when:
- A discrete compressive lesion is present (paralabral cyst, ossified ligament, tumour)
- Pain or progressive weakness persists despite adequate conservative treatment
- There is a functional deficit important to the patient, such as a competitive overhead athlete
Asymptomatic isolated infraspinatus wasting that is well tolerated is not a routine indication.
Nerve release during cuff repair. A double-blinded RCT (Sachinis, PMID 34156877) and a meta-analysis (Yang, PMID 35833960) show that adding suprascapular nerve release to rotator cuff repair does not improve pain, function or nerve recovery. Treat the cuff tear; routine release is not recommended.
Operative options. Match the operation to the cause and the notch involved. Arthroscopic decompression is now the dominant approach for nerve release.
- Indication
- Spinoglenoid paralabral cyst with labral tear
- Notes
- Treats the source; lower recurrence than aspiration alone
- Indication
- Suprascapular notch compression
- Notes
- Has largely replaced open release
- Indication
- Complex/revision, mass excision
- Notes
- Posterior approach to the notch
- Likely Site
- Suprascapular notch
- Key Test
- EMG/NCS + MRI
- First Step
- Non-operative; image for cyst/ligament
- Likely Site
- Spinoglenoid notch
- Key Test
- MRI for paralabral cyst
- First Step
- Activity modification; aspirate/decompress cyst if symptomatic
- Likely Site
- Traction neuropathy
- Key Test
- MRI cuff + EMG
- First Step
- Treat the cuff tear; routine nerve release not required
Surgical Technique
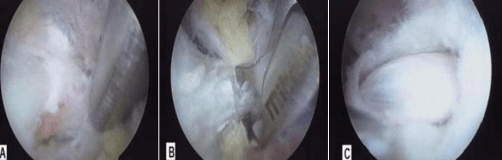
Arthroscopic suprascapular notch decompression. The steps:
- Setup: beach-chair or lateral decubitus, with standard diagnostic glenohumeral and subacromial arthroscopy first
- Approach the notch: work medial to the coracoid and anterior to the supraspinatus, developing the interval to expose the transverse scapular ligament
- Identify structures: protect the suprascapular artery (above the ligament) and the nerve (below), and confirm the nerve before any release
- Release: divide the transverse scapular ligament to decompress the nerve, addressing any bony narrowing if present
- Confirm and close: verify free nerve excursion, then standard portal closure and early range of motion
Preliminary series show normalisation of nerve latency and good pain and function outcomes after arthroscopic release.
- Relationship
- Below transverse scapular ligament
- Consequence if Injured
- Worsened deficit
- Relationship
- Above the ligament (usually)
- Consequence if Injured
- Bleeding, obscured field
- Relationship
- Overlies the working interval
- Consequence if Injured
- Iatrogenic cuff injury
Spinoglenoid cyst decompression. Decompress the cyst and repair the feeding posterosuperior labral tear. Treating only the cyst, by aspiration alone for example, risks recurrence because the labral tear keeps the one-way valve open. Arthroscopic decompression with labral repair addresses both.
Complications
- Comment
- Chronic fatty atrophy may not reverse
- Mitigation
- Treat early before irreversible atrophy
- Comment
- If labral tear left untreated
- Mitigation
- Repair labrum, not aspiration alone
- Comment
- Notch dissection is demanding
- Mitigation
- Identify and protect structures
- Comment
- Pain can persist despite decompression
- Mitigation
- Counsel on realistic expectations
Grading Fatty Atrophy and the Window for Recovery
The sequence. Denervated muscle first shows reversible oedema on MRI (acute denervation), then progresses to fatty infiltration and finally fixed atrophy. Muscle oedema without fatty infiltration is a favourable, potentially reversible picture.
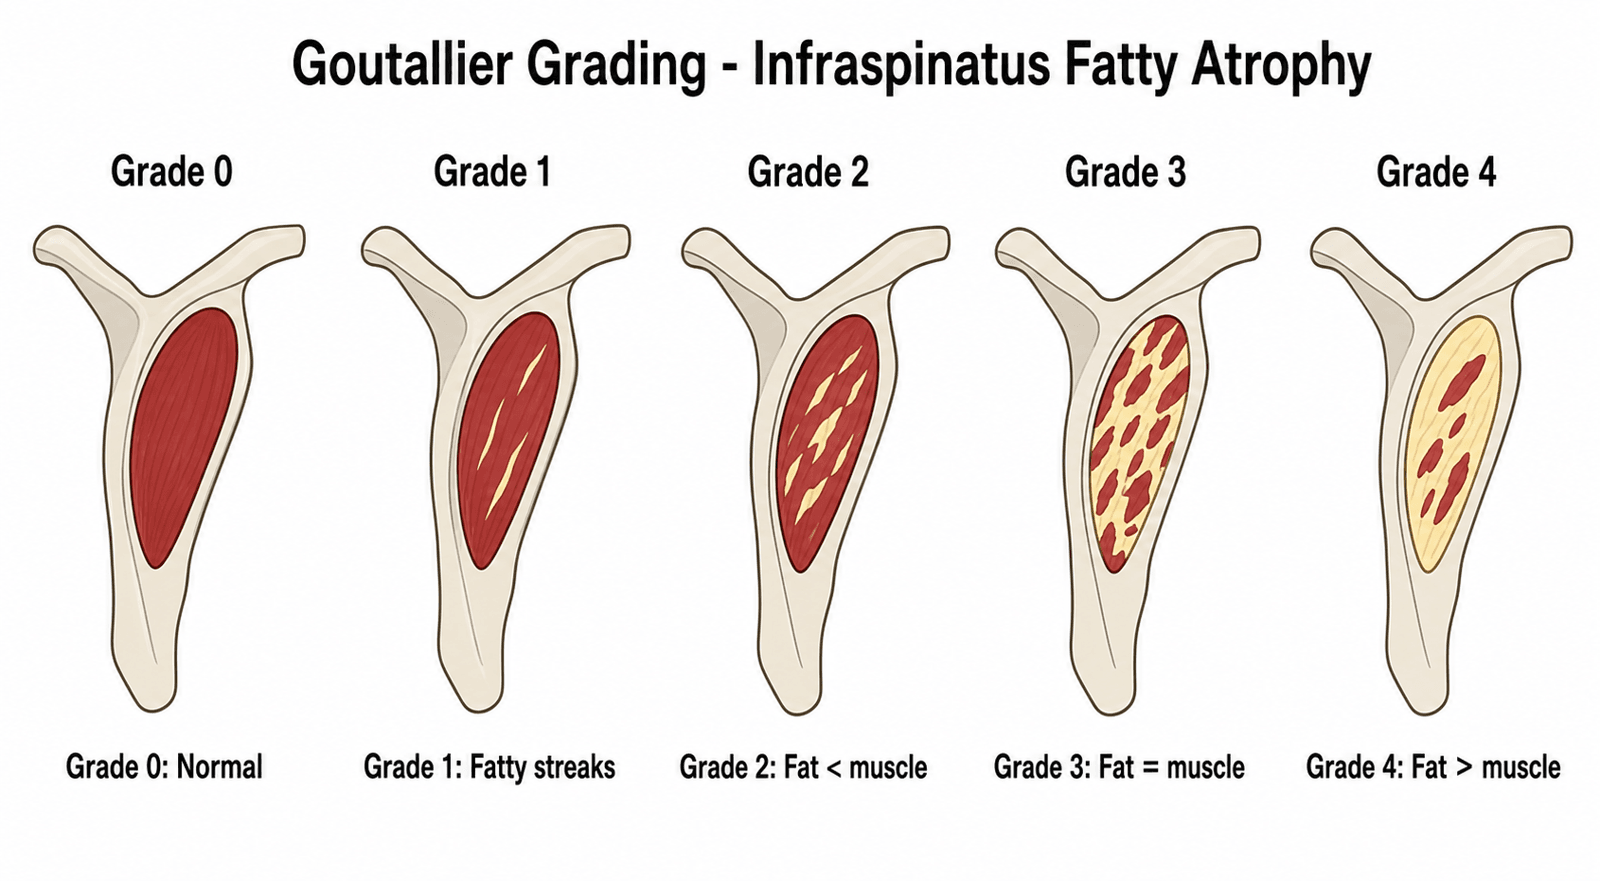
Goutallier grading was described on CT and is now applied on the sagittal-oblique "Y" MRI. Higher grades reflect irreversible replacement of the denervated infraspinatus (and/or supraspinatus) by fat.
- Grade 0: normal muscle
- Grade 1: a few fatty streaks
- Grade 2: fat present but less than muscle
- Grade 3: fat equal to muscle
- Grade 4: fat exceeding muscle
Supporting measures. The tangent sign, in which the muscle belly fails to cross a line drawn across the top of the fossa on the Y-view, indicates significant atrophy. The muscle occupation ratio quantifies the same process.
Why it governs timing. Once advanced fatty change (Goutallier grade 2-3 or higher) is established, decompression may relieve pain but strength often does not fully recover, because the muscle is no longer contractile tissue. This is the mechanistic basis for the "treat early" refrain and for confirming and localising with EMG before atrophy sets in. Established fatty atrophy predicts incomplete strength recovery and should temper the surgical promise made to the patient.
Clinical Relevance and Controversies
Open questions. Nerve release during cuff repair is covered under Management. These remain unresolved:
- Whether traction neuropathy from a retracted cuff tear needs any direct nerve treatment
- The threshold for operating on painless wasting in a high-level athlete
- The lack of a unified outcome metric across small surgical series
Guidelines, Registries & Global Practice
Global Epidemiology
- An uncommon but under-recognised cause of shoulder pain, estimated at roughly 2% of chronic shoulder pain (PMID 25454727).
- Compressive neuropathy is highly prevalent among overhead athletes, but most have no clinically relevant deficit (PMID 32732653).
- Isolated infraspinatus wasting is well described in elite volleyball and other overhead sports, frequently in the dominant arm (PMID 16035699, PMID 29364045).
Side-by-Side Guidance
- Diagnosis
- Pattern of weakness, EMG/NCS, MRI for lesion
- First-line
- Non-operative: activity modification, physiotherapy, nerve block
- Surgical default
- Arthroscopic decompression for a compressive lesion or refractory symptoms
- Diagnosis
- Electrophysiology plus MRI; ultrasound for cyst
- First-line
- Conservative; image-guided cyst aspiration
- Surgical default
- Endoscopic release has superseded open surgery (PMID 25454727)
- Diagnosis
- Confirm neuropathy; assess functional need
- First-line
- Rehabilitation; treat the athlete, not just the scan
- Surgical default
- Decompress only symptomatic, well-indicated athletes (PMID 32732653)
Across regions the convergent position is that diagnosis rests on EMG/NCS plus MRI, that most cases are managed non-operatively, and that surgery - now predominantly arthroscopic - is reserved for a discrete compressive lesion or refractory symptoms.
Registry & Outcome Notes
- No dedicated international registry exists; evidence rests on RCTs (PMID 34156877), meta-analysis (PMID 35833960), and surgical case series (PMID 33091550, PMID 17210425).
- Arthroscopic decompression series report significant functional improvement and, in the absence of major concomitant pathology, no complications or revisions at medium-term follow-up (PMID 33091550).
High- vs Limited-Resource Practice
- High-resource: routine EMG/NCS, MRI for cyst and labral tear, ultrasound-guided block/aspiration, arthroscopic decompression.
- Limited-resource: clinical pattern recognition and a diagnostic suprascapular nerve block guide management; open decompression under regional anaesthesia remains effective where arthroscopy is unavailable.
Documentation & Consent (universal)
- Record the weakness pattern (supraspinatus vs infraspinatus) and visible wasting at each visit.
- When a cyst is present, document the feeding labral tear and the plan to address it.
- Consent for decompression should include incomplete strength recovery if chronic atrophy exists, cyst recurrence if the labrum is untreated, and risk to the suprascapular nerve and artery.
Related pages: SLAP Tears is the lesion behind most paralabral cysts at the spinoglenoid notch, and the reason treating the labral tear usually decompresses the nerve without touching it; Rotator Cuff Tears and Massive Rotator Cuff Tears for the traction mechanism the Sachinis trial above tests - a retracted tear tethers the nerve, and repairing it restored full electrophysiological function in nearly ninety percent of the control arm; Throwing Biomechanics Phases for the repetitive cross-body follow-through implicated in spinoglenoid traction, and for why this is a late-cocking and deceleration problem; Parsonage-Turner Syndrome is the single most important differential - a brachial neuritis can present as isolated infraspinatus wasting after a viral illness and must not be decompressed; Cervical Radiculopathy for the C5-C6 lesion that reproduces the motor pattern from above and is excluded by examining the rest of the myotome; Quadrilateral Space Syndrome and Scapular Winging for the other posterior shoulder neuropathies, where the muscle wasted and the nerve involved are different; Axillary Nerve Anatomy and Brachial Plexus Anatomy for the upper-trunk origin that places this nerve at C5-C6 and explains the referral pattern; and Ganglion Cysts for the lesion whose aspiration the Carroll card above warns against attempting when the structure is actually a vein.
MCQ Practice Points
Q: A patient has weak external rotation with preserved abduction and isolated infraspinatus wasting. Where is the lesion? A: Spinoglenoid notch - distal to the supraspinatus motor branches, so only infraspinatus is affected.
Q: What is the relationship of the suprascapular artery and nerve at the suprascapular notch? A: Nerve passes UNDER the transverse scapular ligament; artery passes OVER it ("Army over, Navy under" / artery over, nerve under).
Q: What is the usual source of a spinoglenoid paralabral cyst? A: A posterosuperior labral tear acting as a one-way valve. Repair the labrum to prevent recurrence.
Q: What is the gold-standard diagnostic test for suprascapular neuropathy? A: EMG / nerve conduction studies. MRI identifies the compressive lesion and muscle atrophy.
Q: Does routine suprascapular nerve release improve outcomes during rotator cuff repair? A: No. A Level I RCT (Sachinis) and meta-analysis (Yang) show no added benefit.
Q: What can mimic a spinoglenoid paralabral cyst on MRI? A: Distended spinoglenoid notch veins (venous varix) - distinguish before any aspiration.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 24-year-old elite volleyball player has visible wasting of the infraspinatus fossa of the dominant shoulder, noted at a routine screen. He has mild posterior ache but performs at a high level. Abduction strength is normal; external rotation is mildly weak.”
“A 40-year-old presents with deep posterior shoulder pain and weakness of both abduction and external rotation. MRI shows no rotator cuff tear but an ossified-looking transverse scapular ligament. EMG shows prolonged latency to both supraspinatus and infraspinatus.”
“A 64-year-old has a large, retracted, reparable rotator cuff tear and EMG-confirmed suprascapular neuropathy. The patient asks whether the nerve also needs to be released at the time of repair.”
Key Anatomy
- Suprascapular nerve = C5-C6 from upper trunk
- Nerve UNDER transverse scapular ligament; artery OVER
- Suprascapular notch supplies supraspinatus first
- Spinoglenoid notch then supplies infraspinatus
Localising the Lesion
- Suprascapular notch = supraspinatus + infraspinatus weak
- Spinoglenoid notch = infraspinatus only
- Isolated infraspinatus wasting in athlete = spinoglenoid
- Confirm and localise with EMG/NCS
Causes
- Paralabral cyst from posterosuperior labral tear
- Traction: overhead sport or retracted cuff tear
- Ossified ligament, tumour, scapular fracture
- Distended notch veins (MRI mimic of cyst)
Management
- Non-operative first for most cases
- Aspirate symptomatic cyst (recurs without labral repair)
- Decompress for compressive lesion / refractory symptoms
- Arthroscopic release now dominant; treat early
Key Evidence
- Routine nerve release adds nothing to cuff repair (PMID 34156877, 35833960)
- Arthroscopic decompression: good durable outcomes (PMID 33091550)
- EMG normalises after release (PMID 17210425)
- Most athlete wasting is well tolerated (PMID 32732653)
Evidence Base
Boykin et al
- Suprascapular neuropathy is under-recognised and increasingly diagnosed
- Aetiologies: repetitive overhead activity, traction from a rotator cuff tear, and compression at the suprascapular or spinoglenoid notch
- EMG/nerve conduction studies remain the diagnostic standard; MRI shows space-occupying lesions and fatty infiltration
- Initial treatment is non-operative; decompression for extrinsic compression or progressive pain/weakness
Strauss et al
- Diagnosis combines history, examination, imaging, and electrodiagnostic studies
- Compressive neuropathy is highly prevalent in overhead athletes but most have no clinically relevant deficit
- Surgical release can improve return to play in well-indicated patients
- Surgery is not routinely recommended unless pain or strength deficits fail non-surgical care