Pain persisting beyond 6 months after an inversion injury — or arising without one
- Roughly one in five to one in three ankle sprains leaves persistent symptoms; 'it was just a sprain' is the commonest reason a fracture or OLT is missed.
- Anterolateral tenderness with a normal anterior drawer points to soft-tissue impingement, not instability.
- Deep aching, catching or giving way with effusion after activity is an osteochondral lesion until proven otherwise.
- Pain behind the fibula with swelling along the tendon sheath, worse on resisted eversion, is peroneal — split tear, tendinopathy or subluxation.
- A child or adolescent with recurrent 'sprains' and a stiff, valgus hindfoot has a tarsal coalition until excluded.
- Anterior process of calcaneus, lateral process of talus and base of the fifth metatarsal are the three fractures routinely missed on the initial film.
- Always examine the hindfoot alignment standing — a varus heel drives recurrent lateral overload and changes the operation.
- “Ottawa rules exclude fracture acutely but say nothing at 6 months — re-image the chronically painful ankle.
- “Pain that is worse walking on uneven ground and never fully settles is mechanical, not inflammatory.
- “Bilateral symptoms without trauma should trigger thought of inflammatory arthropathy or coalition, not sprain.
- “The talar dome lesion is medial and deep, or lateral and shallow — the lateral one is the traumatic one.
- “Do not offer a lateral ligament reconstruction until hindfoot varus and peroneal function have been assessed.
Recognising the Pattern
The definition. Lateral-sided ankle pain persisting beyond six months, most often following an inversion injury, with or without a sense of giving way. The task is to decide whether the pain arises from the ligament, the joint surface, the tendons, the bone or the hindfoot alignment, and the chronically painful ankle is usually a diagnosis that was never made rather than a failure of healing.
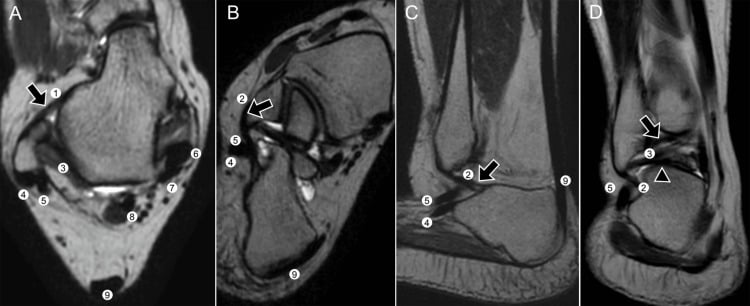
Where exactly. The point of maximal tenderness carries more diagnostic weight than any imaging. Palpate with one finger and make the patient localise to a single point rather than accepting "the outside of my ankle", then reproduce the pain deliberately with the manoeuvre that provokes that site rather than relying on the history of what hurts. Five sites cover the lateral ankle:
- Anterolateral gutter — anterior to the fibula, at the ATFL and the anterolateral capsule. Reproduced by forced dorsiflexion with eversion. Impingement or the ATFL.
- Retrofibular — behind the distal fibula along the peroneal groove. Reproduced by resisted eversion and by circumduction, looking for subluxation. Peroneal.
- Sinus tarsi — a fingerbreadth anterior and inferior to the lateral malleolar tip. Focal, deep, worse on uneven ground, with a painful passive inversion-eversion arc. The subtalar joint, sinus tarsi syndrome or an anterior process of calcaneus fracture.
- Just inferior to the fibular tip — below and slightly anterior to the tip, with pain on subtalar motion, after a dorsiflexion-inversion injury. Lateral process of talus fracture.
- Posterolateral / posterior — the os trigonum and FHL, reproduced by forced plantarflexion, not inversion. Posterior impingement.
Pain that is not at a point at all, a deep ache with swelling after activity and provoked by axial loading, comes from the joint surface: an osteochondral lesion.
What mimics the pattern. Some pain is felt laterally but does not arise there:
- Referred pain from the subtalar joint — post-traumatic subtalar arthritis after a calcaneal or talar injury feels lateral but is worse on inversion/eversion, not on drawer.
- Base of fifth metatarsal / cuboid pathology — the patient points laterally but distally; tenderness is at the metatarsal base.
- Common peroneal or superficial peroneal nerve entrapment — burning, dysaesthetic, non-mechanical; positive Tinel over the fascial exit about 10 cm above the tip of the fibula.
- Complex regional pain syndrome — pain out of proportion, allodynia, vasomotor and sudomotor change; do not operate.
- Lumbar radiculopathy (L5/S1) — pain extends above the ankle and is reproduced by straight leg raise.
Next Investigation
Weight-bearing AP, mortise and lateral, always first. They show arthritis, talar dome lesions, an os trigonum, the fifth metatarsal base, avulsion fragments and the joint space. Weight-bearing is essential, because non-weight-bearing films hide arthritis and syndesmotic widening. Normal tibiotalar, subtalar and syndesmotic alignment is established here, before subtle instability, impingement or osteochondral disease can be called.
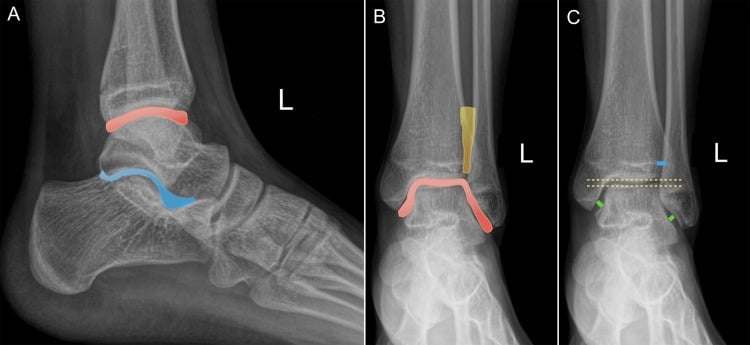
Are the films truly normal? Add a lateral oblique, then look deliberately at five sites: the talar dome corners, the anterior process of calcaneus, the lateral talar process, the fifth metatarsal base and the posterior talus. These are the occult lesions that present weeks later as persistent lateral pain having been called a sprain, and only after this search does a "normal film" justify cross-sectional imaging.
The two processes hidden by overlap. The anterior process of calcaneus and the lateral process of talus are hidden on a standard mortise view. The oblique profiles the anterior process and the anteater nose of a calcaneonavicular coalition, cheaply, and often avoids CT in the adolescent. Where tenderness is precisely localised to either process, the answer is CT rather than a repeat plain film, and for the lateral process CT rather than MRI.
Standing hindfoot alignment view (Saltzman). Quantifies varus or valgus of the heel relative to the tibial axis, and is obtained before any surgery.
MRI, the default when films are normal at 6-8 weeks. Best for osteochondral lesions, peroneal split tears, ligament attenuation, anterolateral gutter soft tissue, sinus tarsi fat obliteration and occult stress fracture. MR arthrography shows contrast traversing a full-thickness ATFL tear. Read it with the examination in hand: bone marrow oedema, mild peroneal fluid and ATFL thickening are common in asymptomatic athletes, so treat the point of maximal tenderness, not the report.
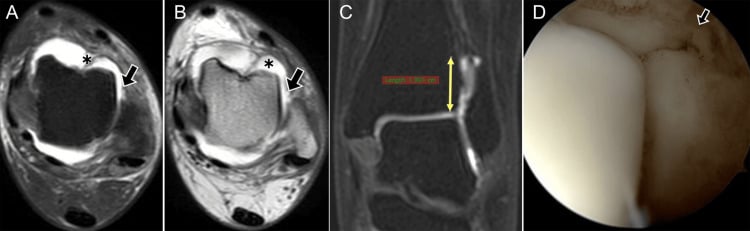
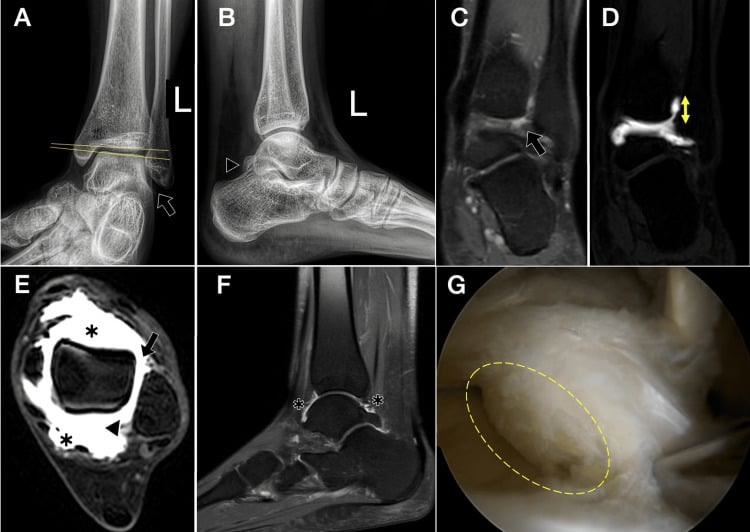
CT, for bone architecture and occult fracture. The lateral process of talus, the anterior process of calcaneus, subtalar arthritis grading, talocalcaneal coalition and the pre-operative planning of an osteochondral lesion with a large cyst. It is superior to MRI for fragment size and subchondral bone: on an osteochondral fracture CT defines the fragment while MRI maps the cartilage defect and marrow oedema, and in coalition CT confirms and defines the osseous component when operative planning needs the exact extent.
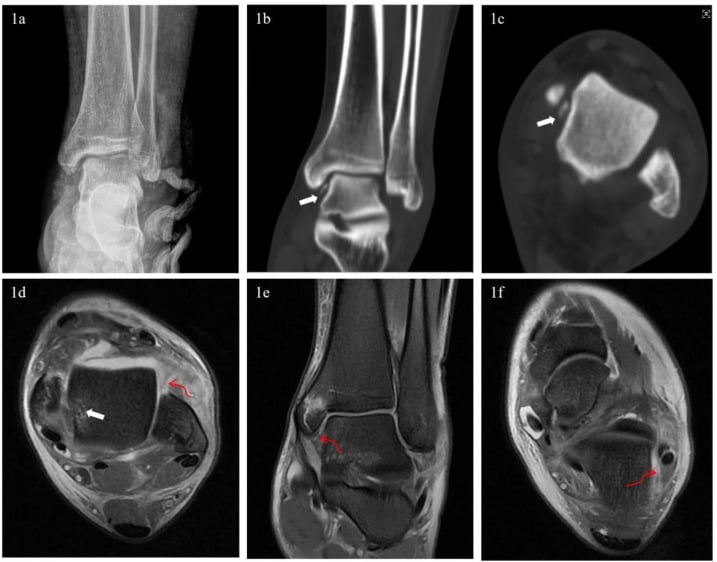
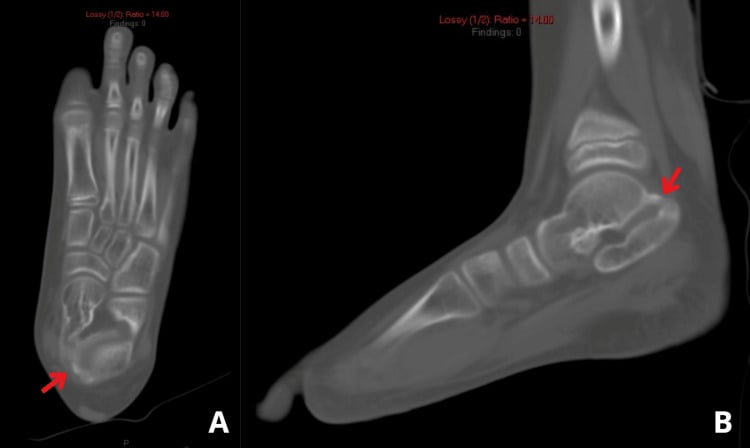
Dynamic ultrasound. The only test that demonstrates peroneal tendon subluxation in real time, and it allows a guided injection. Operator dependent.
Stress radiographs or stress fluoroscopy. Anterior drawer and talar tilt under stress. They rarely alter management, because the diagnosis of instability is clinical, but they are useful when the history and the examination disagree.
When no further imaging is needed. Classic mechanical instability with clear giving way, a normal weight-bearing series, a neutral hindfoot and no rest pain. Treat with 8-12 weeks of proprioceptive and peroneal strengthening rehabilitation first, and image only if rehabilitation fails or pain features emerge.
The Differential
The must-not-miss diagnoses head the table because each presents as the sprain it was first called.
- Typical age / setting
- 15-45, months after a sprain
- Discriminating feature
- Deep aching pain INSIDE the joint with effusion and catching — not point tenderness over a ligament
- What confirms it
- MRI (or CT for bone detail); ankle arthroscopy staging
- Typical age / setting
- Snowboarder, axial load with dorsiflexion
- Discriminating feature
- Tenderness 1 cm inferior to the fibular tip with pain on subtalar motion
- What confirms it
- CT — invisible or subtle on mortise view
- Typical age / setting
- Any age, inversion plus plantarflexion
- Discriminating feature
- Tenderness 2 cm anteroinferior to the fibular tip, at the sinus tarsi floor
- What confirms it
- Lateral oblique radiograph or CT
- Typical age / setting
- Athletes; also cavovarus feet
- Discriminating feature
- Retrofibular swelling, pain on RESISTED eversion, tendons subluxing on circumduction
- What confirms it
- MRI axial images (C-shaped or chevron brevis); dynamic ultrasound for subluxation
- Typical age / setting
- Any age; night pain, no clear injury
- Discriminating feature
- Rest and night pain, constitutional symptoms, pain unrelated to activity
- What confirms it
- Radiograph plus MRI; inflammatory markers
- Typical age / setting
- Young active adult, repeated sprains
- Discriminating feature
- GIVING WAY on uneven ground; increased anterior drawer and talar tilt versus the other side
- What confirms it
- Clinical exam; stress views or MRI showing attenuated ATFL
- Typical age / setting
- Post-sprain, 3-12 months
- Discriminating feature
- PAIN without instability, worst in forced dorsiflexion-eversion, drawer normal
- What confirms it
- MRI/MR arthrogram gutter soft tissue; diagnostic injection; arthroscopy is definitive
- Typical age / setting
- After inversion injury or in pes planovalgus
- Discriminating feature
- Focal sinus tarsi tenderness, hindfoot feels unstable but ankle drawer is normal
- What confirms it
- Response to image-guided sinus tarsi injection; MRI fat obliteration
- Typical age / setting
- Older, previous calcaneal/pilon injury
- Discriminating feature
- Stiffness and pain through the ARC of inversion-eversion, not at a point
- What confirms it
- Weight-bearing radiographs; Broden views; CT
- Typical age / setting
- 8-16 years, recurrent 'sprains'
- Discriminating feature
- STIFF hindfoot with peroneal spasm and planovalgus that does not correct on tiptoe
- What confirms it
- Oblique radiograph (anteater nose); CT/MRI for fibrous coalitions
- Typical age / setting
- Any age; may be CMT
- Discriminating feature
- Varus heel standing, peek-a-boo sign, recurrent sprains despite therapy — corrects on Coleman block
- What confirms it
- Standing hindfoot alignment view; neurological assessment for CMT
- Typical age / setting
- Dancers, footballers
- Discriminating feature
- Pain on forced PLANTARFLEXION, posterolateral not anterolateral
- What confirms it
- Lateral radiograph; MRI oedema; diagnostic injection
- Typical age / setting
- Post-sprain or post-fasciotomy
- Discriminating feature
- Burning dysaesthesia with a Tinel sign over the fascial exit in the distal leg
- What confirms it
- Nerve block relieving pain; nerve conduction studies
- Typical age / setting
- 20-45, often bilateral, no trauma
- Discriminating feature
- Morning stiffness greater than 30 minutes, enthesitis, other joints involved
- What confirms it
- Inflammatory markers, HLA-B27, MRI synovitis
The joint surface. MRI localises an osteochondral lesion on the nine-zone Raikin grid of the talar dome, and arthroscopy confirms the chondral damage and stages it.
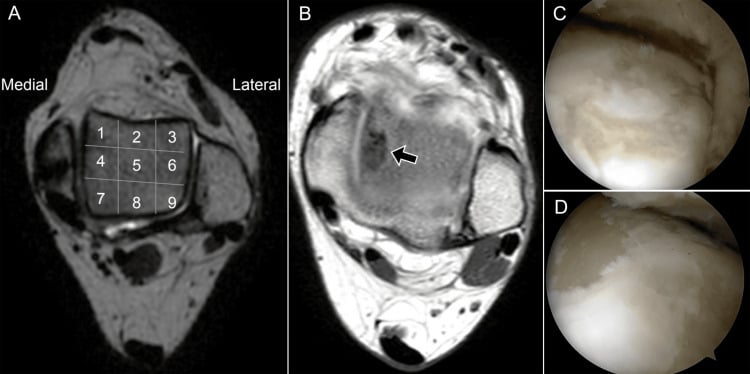
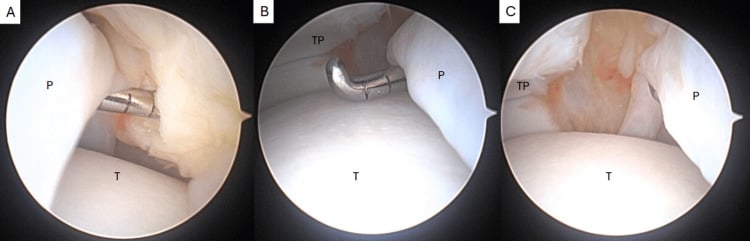
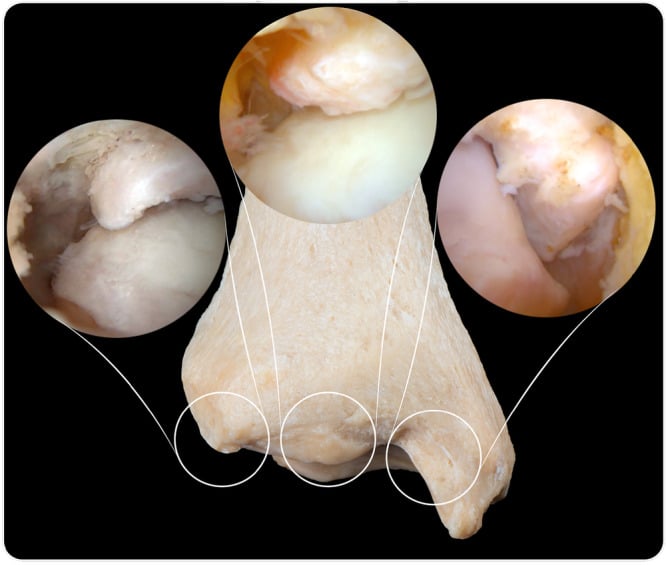
The gutter and the anterior joint. The lesion behind anterolateral pain without instability is soft tissue: a meniscoid lesion, a hypertrophied Bassett's ligament or an intra-articular plica draped across the anterior ankle. Lateral, central and medial tibial osteophytes are responsible for anterior impingement.
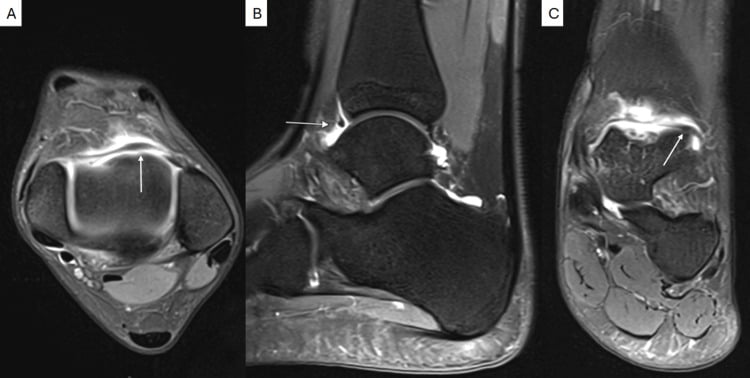
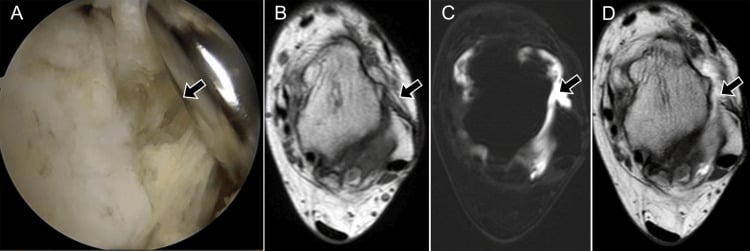
The ligament. Chronic ATFL deficiency looks like absent fibres at arthroscopy and an irregular, thickened remnant on MRI; ultrasound shows the full-thickness defect dynamically.
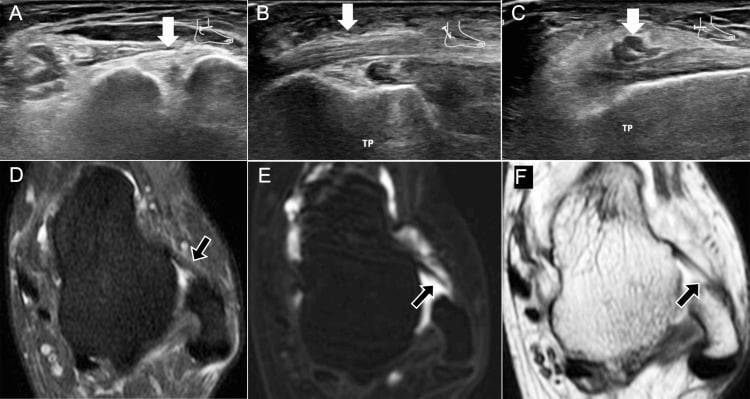
The tendons behind the fibula. The peroneal lesions are a longitudinal split of brevis, tenosynovitis, and subluxation from a deficient superior peroneal retinaculum. A split brevis wraps around longus, which is the C-shape on the axial image.
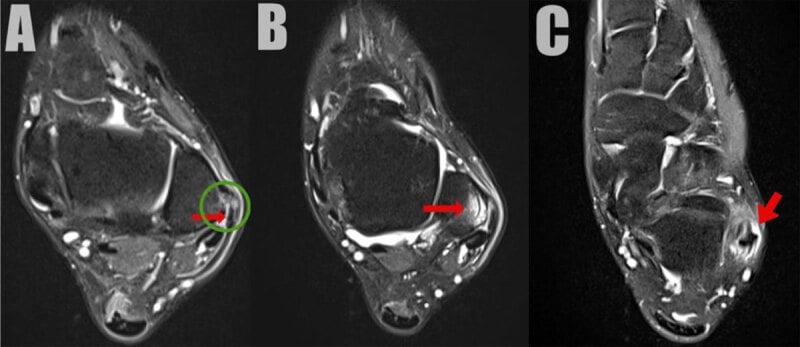
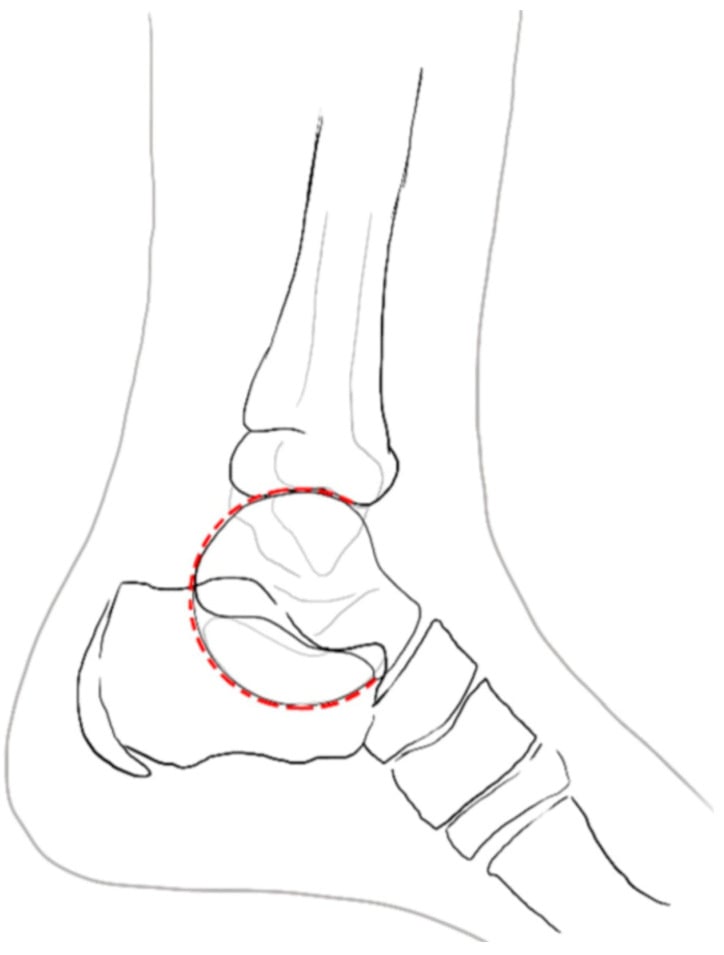
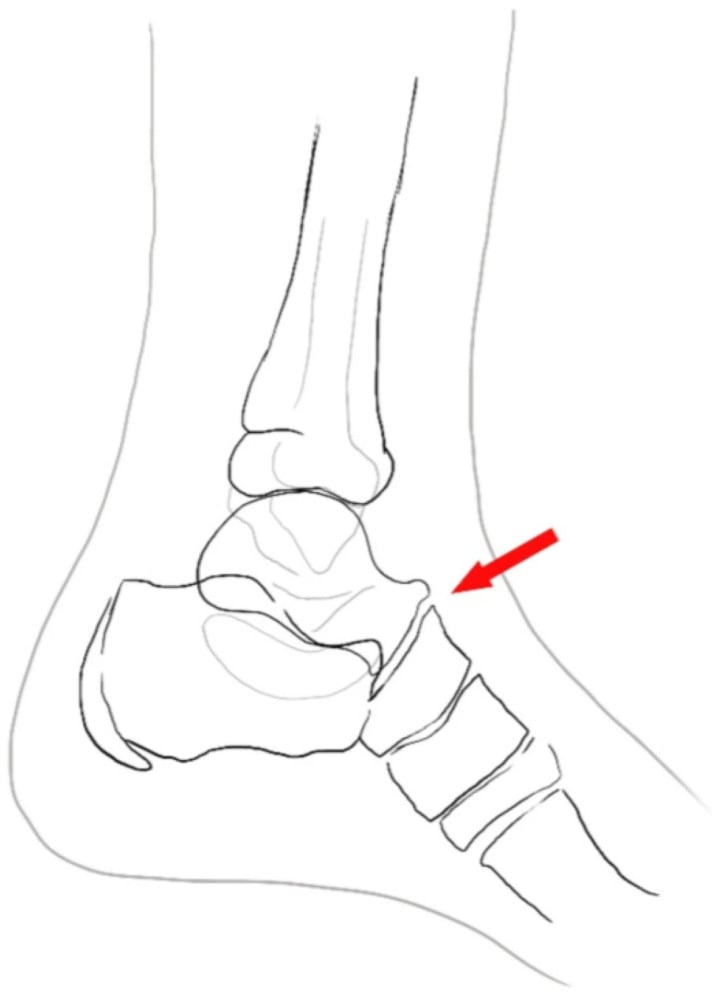
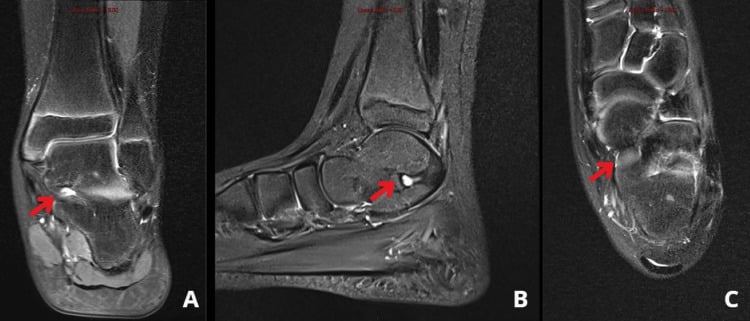
The stiff adolescent hindfoot. On the lateral radiograph a talocalcaneal coalition shows as the C-sign, a continuous curved density from the medial talar dome to the sustentaculum, and as a dorsal talar beak, which is chronic traction at the talonavicular capsule and an indirect clue to restricted hindfoot motion. When the radiographs understate the bridge, MRI shows the fibrous component of a mixed coalition and explains the pain.
Associated injuries in chronic lateral ankle instability — instability is rarely isolated
- At surgery in 61 ankles undergoing lateral ligament reconstruction, NONE had an isolated ligament injury - the direct basis for the page's warning that instability and intra-articular pathology coexist.
- Peroneal tenosynovitis (77%), anterolateral impingement (67%), attenuated peroneal retinaculum (54%) and ankle synovitis (49%) were commonest; an osteochondral lesion of the talus was present in 23% - so a stabilisation-only plan can leave the pain generator untreated.
- Retrospective operative series: it documents the frequency of co-pathology in a surgical cohort, not in the wider population of sprains, so the percentages overestimate what an unselected chronically painful ankle holds.
Occult Lesions After Ankle Injury - Why the Painful Ankle Comes Back Weeks Later
- Ankle injuries account for 21 per cent of all sports-related injuries, so the population feeding this differential is very large
- The review names the occult lesions explicitly, and they are the five sites this page's radiographic search covers: fracture of the LATERAL PROCESS OF THE TALUS, fracture of the ANTERIOR PROCESS OF THE CALCANEUS, fracture of the BASE OF THE FIFTH METATARSAL, os trigonum, and stress fractures
- The authors' central observation is the mechanism of the missed diagnosis: these lesions may be missed on initial physical examination, and the patient then presents to a sports clinic with PERSISTENT PAIN AROUND THE ANKLE
- The wider spectrum spans ligamentous injury, soft-tissue and osseous impingement, osteochondral lesions of the talus, tendon injury and fracture - the same list this page works through
Fracture of the Lateral Process of the Talus - the Snowboarder's Fracture
- Once a very rare injury, it became common with snowboarding: the largest epidemiological series (Kirkpatrick 1998) reports 2.3 per cent of ALL snowboarding injuries and 15 PER CENT OF ALL SNOWBOARDING ANKLE INJURIES
- The mechanism is dorsiflexion of the ankle with inversion of the hindfoot - the same story the patient gives for an ordinary sprain
- Many of these fractures are NOT VISIBLE on plain radiographs; CT is needed to establish size, displacement, comminution, subtalar joint involvement and associated injuries
- The clinical warning is explicit: subtle fractures requiring surgery are confused with anterior talofibular ligament sprains, and the physician should be suspicious of anterolateral ankle pain in a snowboarder
- Treatment splits on displacement: undisplaced fractures in cast, single large displaced fragments reduced and internally fixed, small or comminuted displaced fragments excised
Narrowing It Down
Was there a real injury, and how old is the patient? Establish whether a genuine inversion injury occurred, take the age, and ask directly about night and rest pain. No injury and age under 16 with a stiff hindfoot means coalition; no injury and bilateral symptoms means inflammatory arthropathy or a systemic cause; a clear inversion injury opens the post-traumatic list. Night and rest pain at any age means tumour or infection until excluded, and is not explained by instability alone.
Pain, giving way, or both? Make the patient separate the two complaints explicitly, because they will otherwise report both as "my ankle is bad". Pure giving way with minimal pain is mechanical instability, a ligament problem; pure pain with a stable ankle is impingement, an osteochondral lesion, peroneal pathology or an occult fracture. Both together means instability with an intra-articular lesion, and that changes the operation from stabilisation alone to stabilisation plus arthroscopy. Do not call it "just instability": instability and intra-articular pathology coexist, and up to a large proportion of ankles undergoing stabilisation have an associated chondral lesion, loose body or synovitis at arthroscopy.
Is the hindfoot aligned? Stand the patient and look from behind. A varus heel with a peek-a-boo sign means cavovarus, and a cavovarus foot with a plantarflexed first ray reproduces the sprain and blows out any ligament repair: uncorrected varus is the principal cause of a failed Broström. Do the Coleman block test, search for Charcot-Marie-Tooth disease, and plan a lateralising calcaneal osteotomy alongside any ligament work. Valgus with a stiff subtalar joint in an adolescent means coalition.
Does a targeted diagnostic injection settle it? Where imaging is equivocal, inject local anaesthetic under image guidance into the single structure most suspected, the sinus tarsi, the subtalar joint or the peroneal sheath, and reassess immediately. A well-placed block localises the pain generator and predicts response to surgery better than any scan. A negative block in the presence of a positive scan should stop the operation, not be explained away.
MCQ Practice Points
Q: A patient has anterolateral ankle pain worst on forced dorsiflexion with eversion, but a normal anterior drawer. What is the diagnosis?
A: Anterolateral soft-tissue impingement (meniscoid lesion or hypertrophied Bassett's ligament). The discriminator is PAIN WITHOUT INSTABILITY, provoked by dorsiflexion rather than by the drawer test. Arthroscopic debridement is highly effective.
Q: Which fracture is classically missed on the initial radiograph after a snowboarding inversion injury?
A: Fracture of the lateral process of the talus ("snowboarder's fracture"), caused by axial loading with dorsiflexion and inversion. It is obscured on the mortise view and CT is required — in the largest epidemiological series it accounted for 2.3 per cent of all snowboarding injuries and 15 per cent of snowboarding ankle injuries, and it is routinely mistaken for an anterior talofibular ligament sprain. Displaced fragments greater than 2 mm warrant fixation to prevent subtalar arthritis.
Q: What single examination finding must be documented before offering a lateral ligament reconstruction?
A: Standing hindfoot alignment. Uncorrected hindfoot varus is the principal cause of failed Broström procedures and mandates a lateralising calcaneal osteotomy, with a dorsiflexion first metatarsal osteotomy if the Coleman block test shows a forefoot-driven deformity.
Q: Where is the traumatic osteochondral lesion of the talus typically located, and how does it differ from the atraumatic one?
A: The lateral lesion is anterolateral, shallow and wafer-shaped, and is strongly associated with trauma. The medial lesion is posteromedial, deeper and cup-shaped, and is more often atraumatic or associated with cyst formation.
Q: A 40-year-old has bilateral lateral ankle pain with morning stiffness lasting an hour and no history of injury. What is the next step?
A: Suspect seronegative spondyloarthropathy. Check inflammatory markers and HLA-B27, examine for enthesitis and other joint involvement, and consider MRI for synovitis. Bilateral, atraumatic, inflammatory-pattern pain is not a mechanical problem.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are shown a weight-bearing mortise radiograph of a 24-year-old semi-professional footballer, eight months after an inversion injury. The film looks normal. He describes deep pain and occasional catching, with swelling after matches, but denies frank giving way.”
“You are shown an oblique radiograph of the foot of a 13-year-old girl with three 'ankle sprains' in a year and persistent lateral pain. Her hindfoot is in valgus and she cannot invert it.”
“You are shown an axial MRI slice at the level of the distal fibula in a 38-year-old runner with a year of pain behind the lateral malleolus, worse on uneven ground, with a sensation of snapping.”
Localise by tenderness
- Anterolateral gutter — impingement or ATFL
- Behind fibula — peroneal tear or subluxation
- Sinus tarsi — sinus tarsi syndrome, subtalar instability, anterior process fracture
- 1 cm below fibular tip — lateral process of talus
- Posterior — os trigonum / FHL
Symptom discriminators
- Giving way = ligament
- Catching plus effusion = intra-articular (OLT, loose body)
- Resisted eversion pain = peroneal
- Stiff subtalar arc = coalition or arthritis
- Night and rest pain = tumour or infection
Imaging sequence
- Weight-bearing AP, mortise, lateral first — always
- Add hindfoot alignment view before any surgery
- Oblique for calcaneonavicular coalition (anteater nose)
- MRI when films normal at 6-8 weeks
- CT for occult bony fracture and coalition
- Dynamic ultrasound for peroneal subluxation
Must-not-miss list
- Osteochondral lesion of the talus
- Lateral process of talus fracture
- Anterior process of calcaneus fracture
- Peroneal split tear or dislocation
- Tumour or infection presenting as a sprain
Before operating
- Have 8-12 weeks of proprioceptive rehabilitation been completed?
- Is the hindfoot neutral, varus or valgus?
- Are the peroneals intact and strong?
- Is there a coexisting intra-articular lesion to address arthroscopically?
- Does a diagnostic injection abolish the pain?