The Engine of the Shoulder and the Reason a Reverse Works
- Origin follows the coracoacromial arch in reverse: lateral third of clavicle, acromion, and the crest of the scapular spine.
- Insertion: deltoid tuberosity on the lateral humeral shaft, roughly at the midpoint of the humerus.
- Innervation: axillary nerve (C5, C6) from the posterior cord, via anterior and posterior branches.
- The anterior branch crosses the deep surface of the deltoid at about 0.20 of arm length from the anterior acromion and 0.16 from the posterior - roughly 5 to 7 cm in an average adult, but it is a RATIO, not a fixed distance, and the posterior margin is the tighter one.
- The deltoid requires a stable fulcrum from the rotator cuff; without one, its force becomes superior shear.
- “Test the deltoid by palpating its contraction, not by testing abduction — the supraspinatus can abduct a denervated shoulder.
- “Regimental badge sensation may be preserved despite a complete motor axillary palsy; sensory testing alone is unreliable.
- “A reverse arthroplasty works by lengthening the deltoid moment arm and recruiting anterior and posterior fibres, not by replacing the cuff.
- “Deltoid dehiscence after an open anterosuperior approach is functionally catastrophic and difficult to salvage.
Overview
The deltoid is the largest and most powerful muscle of the shoulder girdle, a triangular multipennate mass draping the joint from the clavicle, acromion and scapular spine to the deltoid tuberosity of the humerus. Its three heads have genuinely distinct actions rather than being three portions of one uniform sheet.
Two surgical realities. The axillary nerve crosses its deep surface at a predictable distance from the acromion, and every lateral approach, portal and plate placement is designed around that number. In the cuff-deficient shoulder the deltoid is the only motor left, which is why the entire reverse arthroplasty concept is a deltoid-tensioning operation and why an axillary nerve palsy is a contraindication to it.
Why the deltoid needs the cuff. With the arm at the side the deltoid's line of pull is almost parallel to the humeral shaft, so its resultant force is predominantly superior shear, not rotation. The rotator cuff, supraspinatus superiorly, subscapularis anteriorly, infraspinatus and teres minor posteriorly, compresses the head into the glenoid and creates a fulcrum, and only against that fulcrum does deltoid shear become a rotational moment. This is the coronal force couple: deltoid pulling superiorly, the inferior cuff pulling inferiorly and medially, their resultant being rotation about a stable centre.
When the cuff fails. The fulcrum goes with it. The deltoid then translates the head superiorly against the acromion instead of elevating the arm: pseudoparalysis, then acetabularisation of the acromion and femoralisation of the head. The reverse arthroplasty answer is to move the centre of rotation medially and distally, so that the prosthesis provides the fulcrum the cuff no longer can.
Attachments, Innervation and Relations
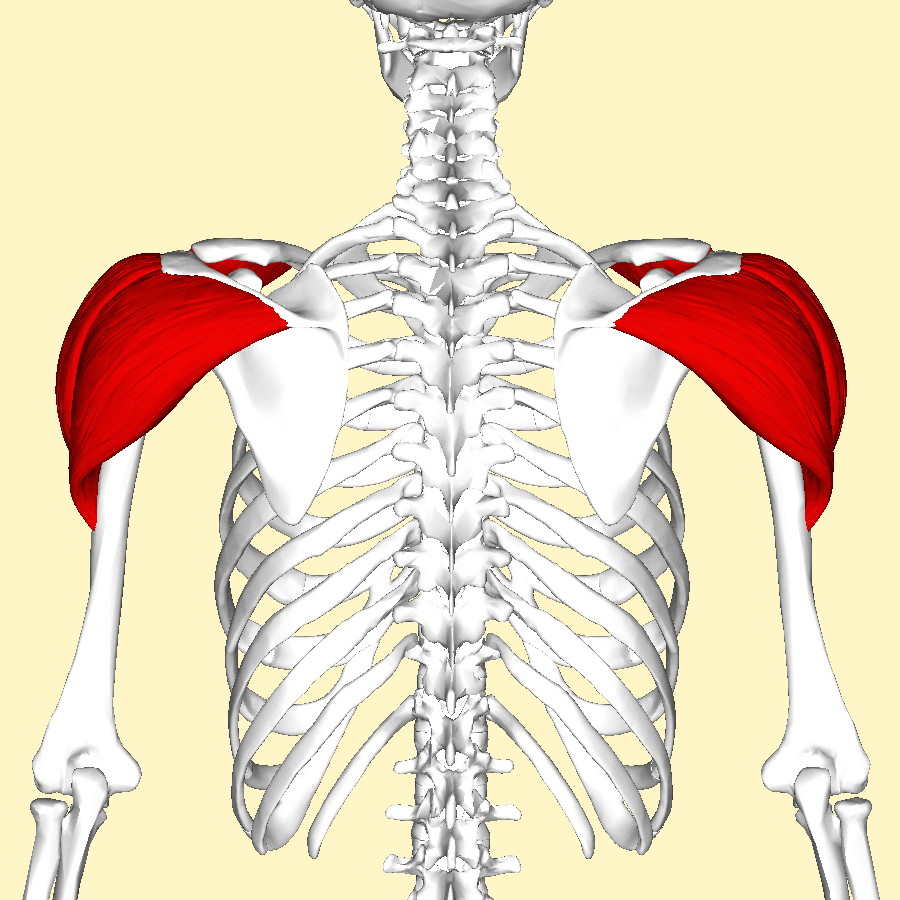
Origin. The origin traces the coracoacromial arch in reverse: the anterior head from the anterior border and superior surface of the lateral third of the clavicle, the middle head from the lateral border and superior surface of the acromion, and the posterior head from the lower lip of the crest of the scapular spine along its whole length. These are the same three bones, in the same order, onto which trapezius inserts; deltoid origin and trapezius insertion mirror each other across the shoulder girdle.
Fibre architecture. The anterior and posterior heads have parallel, relatively long fibres and good excursion. The middle head is multipennate: several tendinous septa descend from the acromion and interdigitate with septa ascending from the tuberosity, an arrangement that produces high force over a short excursion and is the reason the middle deltoid is the powerful abductor. The three heads share a common deltoid fascia, and the anterior and posterior heads are joined to the middle head by raphes that are the natural planes of a deltoid split.
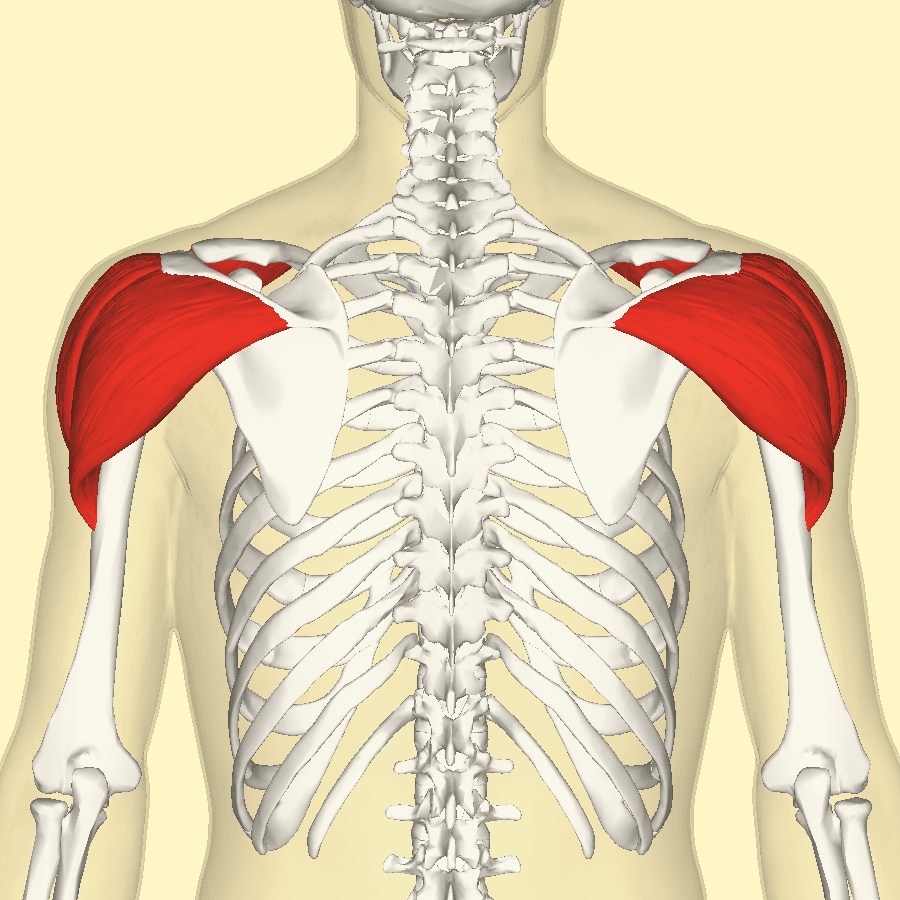
Insertion. The deltoid tuberosity on the lateral aspect of the humeral shaft, roughly at the midpoint of the humerus, a V-shaped roughening whose apex points proximally. Fibres continue distally as an expansion into the brachial fascia, blending with the lateral intermuscular septum.
The deltoid tuberosity index. Measured on an anteroposterior radiograph of the proximal humerus at the level where the lateral cortex first becomes parallel, it is the ratio of the outer to the inner cortical diameter. A value below approximately 1.4 indicates poor local bone quality and predicts fixation failure after proximal humeral osteosynthesis; it is a cheap, radiograph-based surrogate for bone mineral density.
Direct division. A lateral deltoid split carried beyond the safe zone divides the anterior branch, and the result is denervation of the anterior and middle deltoid distal to the split. Measure rather than estimate.
Traction and crush. More common than division. Vigorous retraction of a split, or a self-retaining retractor left in place, stretches the nerve against the surgical neck, and prolonged retraction during a long case produces a neurapraxia that presents as post-operative deltoid weakness with an intact-looking wound. Release retractors intermittently, and use a stay suture rather than deep retraction.
Action and Biomechanics
- Origin
- Lateral third of the clavicle
- Primary actions
- Forward flexion
- Secondary actions
- Internal rotation, horizontal adduction, assists abduction above 90 degrees
- Fibre architecture
- Parallel, long fibres, good excursion
- Origin
- Lateral border of the acromion
- Primary actions
- Abduction in the coronal and scapular planes
- Secondary actions
- Little rotational effect
- Fibre architecture
- Multipennate: high force, short excursion
- Origin
- Crest of the scapular spine
- Primary actions
- Extension
- Secondary actions
- External rotation, horizontal abduction, assists abduction above 90 degrees
- Fibre architecture
- Parallel, long fibres, good excursion
The middle head. Loss of the middle head, whether from axillary nerve injury or a failed deltoid repair, causes profound abduction weakness despite an intact rotator cuff.
Torque and moment arm. The deltoid as a whole contributes approximately 50 per cent of abduction torque, rising as elevation increases. Its abduction moment arm grows from roughly a centimetre at 0 degrees to around three centimetres at 60 to 90 degrees, the mechanical mirror image of the supraspinatus, whose moment arm is largest in the low range and diminishes with elevation.
The other two heads. The anterior and posterior heads become abduction synergists above 90 degrees, when their lines of pull cross the axis of rotation. Below 90 degrees they are respectively a flexor and an extensor, and in the very low range they can even oppose abduction.
Length-tension and the reverse. The multipennate middle head operates over a short excursion, so it is sensitive to changes in resting length: both under-tensioning and over-tensioning move it away from the optimum of its length-tension curve. A reverse arthroplasty deliberately manipulates this. Medialising the centre of rotation increases the deltoid moment arm, and distalising the humerus increases deltoid resting tension and recruits anterior and posterior fibres into elevation.
Synergists and antagonists. Supraspinatus abducts and compresses alongside it, the rest of the cuff provides the fulcrum, trapezius and serratus anterior rotate the scapula upward to provide the platform, the clavicular head of pectoralis major flexes with the anterior deltoid, and latissimus dorsi extends with the posterior deltoid. Against it, latissimus dorsi and pectoralis major adduct, and the inferior cuff depresses the head, opposing deltoid shear.
Scapulohumeral rhythm. Deltoid force is useless without a stable scapular base. The overall 2:1 glenohumeral to scapulothoracic ratio across the arc of elevation means that of 180 degrees of elevation roughly 120 degrees is glenohumeral and 60 degrees scapulothoracic, and the setting phase, in the first 30 degrees, is variable and predominantly glenohumeral. Upward rotation of the scapula by trapezius and serratus anterior keeps the glenoid beneath the head and keeps the deltoid at a favourable length, so a patient with serratus anterior palsy or trapezius palsy has a normal deltoid and a normal cuff and still cannot elevate properly. Always examine the scapula from behind before attributing weakness to the deltoid.
Surface Anatomy and Examination
Inspection and palpation. All three heads are subcutaneous and directly palpable. Compare contour with the opposite side from the front, side and back: the squared-off shoulder of a dislocation and the flattened contour of deltoid wasting are inspection diagnoses.
Finding the landmarks. The deltopectoral groove is found by asking the patient to adduct against resistance, and the cephalic vein is often visible within it in a thin patient. The posterior border is best seen with the arm extended against resistance, which is also how the swallow-tail sign is elicited. The anterolateral acromial corner is the landmark from which all safe-zone measurements are made; mark it before draping.
- How to perform
- Support the arm in slight abduction and ask the patient to abduct isometrically while you palpate all three heads
- Positive finding
- No palpable firm contraction in one or more heads
- What it means
- Axillary nerve motor deficit
- False positives and pitfalls
- The single most reliable test; do not substitute abduction range
- How to perform
- Light touch and pinprick over the lateral deltoid
- Positive finding
- Reduced or absent sensation
- What it means
- Superior lateral cutaneous nerve of the arm involvement
- False positives and pitfalls
- A normal result does not exclude injury
- How to perform
- With the patient's arm passively placed in maximal extension behind the body, ask them to hold it
- Positive finding
- The arm drops forward
- What it means
- Posterior deltoid and axillary nerve deficit
- False positives and pitfalls
- Shoulder stiffness prevents the starting position
- How to perform
- Ask the patient to extend both arms behind the back and compare the posterior deltoid contours
- Positive finding
- Asymmetric posterior deltoid contour
- What it means
- Posterior deltoid weakness, usually axillary nerve
- False positives and pitfalls
- Constitutional asymmetry; compare with the pre-injury photograph if available
- How to perform
- Resist abduction at 90 degrees in the coronal plane with the arm internally rotated
- Positive finding
- Weakness
- What it means
- Middle deltoid deficit
- False positives and pitfalls
- Painful cuff pathology inhibits effort; consider a subacromial local anaesthetic test
- How to perform
- Observe the scapula from behind during elevation and on a wall push-up
- Positive finding
- Winging or dyskinesis
- What it means
- Serratus anterior or trapezius palsy mimicking deltoid weakness
- False positives and pitfalls
- The commonest reason a normally innervated deltoid appears weak
- Palpate, do not measure range. A patient with a complete deltoid palsy can often abduct to 90 degrees using the supraspinatus and the scapular rotators, so range of abduction is not a test of the deltoid.
- Do not rely on sensation. The regimental badge patch is frequently normal in a complete motor axillary palsy, and it can be abnormal without motor loss. Sensation is corroborative, never diagnostic.
- Test before and after reduction, and document it. An axillary palsy discovered only after a shoulder reduction is a medicolegal problem that a pre-reduction note solves entirely.
Complications
Axillary nerve injury. The surgical mechanisms are:
- A deltoid split carried beyond the safe zone
- Retraction of a split without a stay suture
- Blind plate passage in minimally invasive osteosynthesis
- Inferior capsular release or inferior anchor placement close to the inferior glenoid rim
- Over-lengthening in reverse arthroplasty
The consequence is permanent deltoid palsy, which removes both active elevation and the option of a reverse arthroplasty. This is one of the few genuinely unsalvageable complications in shoulder surgery. Avoid it by measuring the safe zone from the lateral acromion, using stay sutures, identifying the nerve where the exposure requires it, avoiding deep self-retaining retractors, and respecting lengthening limits.
Deltoid dehiscence. It follows inadequate reattachment of the deltoid origin after an anterosuperior approach, or premature active use, and produces loss of abduction power, a visible contour defect and pain. Established dehiscence is one of the most difficult problems in shoulder surgery: direct reattachment to bone can be attempted, sometimes with a local fascial or allograft augmentation, but results are unpredictable and there is no reliable salvage. Prevention is everything, and this is the strongest argument for arthroscopic and mini-open techniques wherever they will do the job.
Acromial and scapular spine stress fracture after reverse arthroplasty. Increased deltoid tension after distalisation is the mechanism, magnified by lateralised designs and by osteoporotic bone. It typically presents at 3 to 12 months with new pain over the acromion and loss of elevation, and the investigation is CT, since radiographs are often normal. Management is usually non-operative with immobilisation; fixation is technically difficult and unreliable, so prevention through correct tensioning is the meaningful intervention.
Stiffness and disuse. Prolonged immobilisation for any reason, in a patient whose deltoid is the only motor, produces rapid disuse atrophy and stiffness. Maintain passive range even while protecting a repair.
Post-injection deltoid contracture. The fibrous band in the middle deltoid tethers the arm in abduction, so that adduction to the side is impossible and the scapula wings as the child attempts it. Treatment is surgical release of the band, with careful preservation of the axillary nerve, which lies deep to the fibrotic segment.
Cosmetic and sensory sequelae. Supraclavicular nerve injury during an anterior approach produces a numb patch below the incision that patients notice more than surgeons expect; warn about it at consent. Loss of anterior deltoid bulk after harvest or dehiscence is visible and distressing.
Clinical Relevance
Axillary nerve palsy after dislocation is the commonest nerve injury in shoulder trauma. An anterior glenohumeral dislocation stretches the nerve, which is tethered proximally at the posterior cord and distally in the quadrangular space and on the deep surface of the deltoid; fracture-dislocations and high-energy injuries add a direct component. The incidence is reported widely, from around 5 per cent of clinically detected cases to substantially higher proportions when electromyography is used, and it rises markedly with age over 60 and with fracture-dislocation.
Presentation and natural history. Deltoid weakness, wasting appearing over weeks, and variable sensory change over the lateral deltoid; isolated teres minor involvement occurs with posterior branch injury. The great majority are neurapraxic and recover spontaneously, typically within 3 to 6 months.
Investigation and management. Electromyography at 3 to 4 weeks establishes a baseline, because fibrillation potentials take that long to appear, and is repeated at 3 months to look for reinnervation. Management is observation with a maintained passive range and prevention of stiffness. If there is no clinical or electrophysiological recovery by 3 to 6 months, exploration is considered, applying the regeneration principle of roughly one millimetre per day so that the motor end plates are reached before irreversible atrophy. The reconstructive options are:
- Neurolysis
- Direct repair
- Interpositional grafting
- Triceps branch to axillary nerve transfer, which shortens the regeneration distance and avoids a graft
- Typical Patient
- Post-operative
- Presentation
- Anterior contour defect, weakness, sometimes a palpable gap on elevation
- Key finding
- Loss of the anterior deltoid origin from the acromion
- Management
- Difficult; attempt reattachment to bone through drill holes, but results are unpredictable
- Typical Patient
- Children, historically after repeated intramuscular injections
- Presentation
- Fixed abduction contracture, scapular winging on attempted adduction
- Key finding
- Palpable fibrous band in the middle deltoid; the arm cannot be adducted to the side
- Management
- Surgical release of the fibrous band
- Typical Patient
- Post-operative
- Presentation
- Loss of elevation despite a well-positioned implant
- Key finding
- Contour defect, no palpable contraction
- Management
- Prognosis poor; a functioning deltoid is essential to a reverse arthroplasty
- Typical Patient
- After reverse arthroplasty, especially with over-lengthening
- Presentation
- New onset pain over the acromion 3 to 12 months post-operatively, loss of elevation
- Key finding
- Tenderness at the acromion; fracture on CT, often occult on radiographs
- Management
- Usually non-operative; occasionally fixation; prevention is correct tensioning
- Typical Patient
- Overhead athletes
- Presentation
- Posterolateral pain, sometimes with paraesthesia
- Key finding
- Isolated teres minor atrophy with a normal deltoid on MRI
- Management
- Activity modification; decompression only when refractory and corroborated
- Typical Patient
- Rare, high-energy
- Presentation
- Lateral arm pain and weakness of abduction
- Key finding
- Avulsion at the tuberosity on imaging
- Management
- Fixation if displaced in an active patient
Imaging. Radiographs assess the acromion and scapular spine for stress fracture after reverse arthroplasty, and the anteroposterior view is where the deltoid tuberosity index is measured before proximal humeral fixation. MRI demonstrates deltoid denervation as diffuse oedema-like T2 signal in the subacute phase followed by fatty replacement, shows deltoid detachment or dehiscence directly, and shows isolated teres minor change in posterior branch lesions. Ultrasound gives a dynamic assessment of deltoid contraction and identifies a dehiscence at the acromion. Electromyography, timed as above, is the definitive investigation for a suspected nerve lesion.
Surgical Relevance
- What is done to the deltoid
- Nothing is divided; the deltoid is retracted laterally
- Interval or plane
- Internervous plane between deltoid (axillary nerve) and pectoralis major (medial and lateral pectoral nerves)
- Structure at risk
- Cephalic vein; axillary nerve at the inferior border of subscapularis
- Distance rule
- Axillary nerve lies about 1 to 2 cm from the inferior border of subscapularis
- What is done to the deltoid
- A sliver of anterior deltoid may be elevated from the clavicle for exposure
- Interval or plane
- Same interval, extended proximally
- Structure at risk
- Deltoid origin integrity
- Distance rule
- Reattach to bone; do not rely on fascial repair
- What is done to the deltoid
- Middle deltoid split longitudinally from the anterolateral acromial corner
- Interval or plane
- Between the anterior and middle heads at the raphe
- Structure at risk
- Anterior branch of the axillary nerve on the deep surface
- Distance rule
- Split no more than 5 cm distally, 3.5 to 4 cm in a short patient; stay suture at the apex
- What is done to the deltoid
- Anterior deltoid origin detached from the acromion with a cuff of tissue or a bone flake
- Interval or plane
- Split extended from the acromion
- Structure at risk
- Deltoid dehiscence; axillary nerve if the split is long
- Distance rule
- Repair to bone through transosseous drill holes; protect for six weeks
- What is done to the deltoid
- Posterior deltoid split or reflected from the scapular spine
- Interval or plane
- Between posterior and middle heads
- Structure at risk
- Axillary nerve exiting the quadrangular space
- Distance rule
- Split no more than about 5 cm below the scapular spine
- What is done to the deltoid
- Two small deltoid splits, proximal and distal, with the plate slid beneath
- Interval or plane
- Submuscular tunnel deep to the deltoid
- Structure at risk
- Anterior branch of the axillary nerve crossing the plate path
- Distance rule
- Identify and protect the nerve with a finger or a retractor before sliding the plate; keep the proximal split within 5 cm
- What is done to the deltoid
- Deltoid pierced, not split under vision
- Interval or plane
- Posterior soft spot, lateral and anterior portals
- Structure at risk
- Axillary nerve for low lateral and inferior portals
- Distance rule
- Lateral portals no more than about 5 cm distal to the acromial edge
Measure from the lateral edge of the acromion, not from the skin incision, and not by eye.
- Always place a stay suture at the distal apex of the split before retracting. Retraction propagates the split distally, and it is the propagation, not the incision, that divides the nerve.
- In minimally invasive plating, palpate the nerve through the proximal window and slide the plate beneath it under direct control. A plate passed blind can lie directly on the nerve.
- If in doubt, extend the exposure and see the nerve. Identifying it takes minutes; a permanent deltoid palsy does not recover.
Detaching and repairing the origin. The anterosuperior approach requires deltoid origin detachment. The origin must be taken with a continuous cuff of periosteum and fascia, or with a thin flake of acromial bone, and repaired through transosseous drill holes in the acromion at closure. Fascia-to-fascia repair fails, because the deltoid origin is under continuous load from the moment the patient starts using the arm. Protect the repair for six weeks with a sling and passive motion only, avoiding active abduction and resisted elevation.
Deltoid tensioning in reverse arthroplasty. A reverse arthroplasty is a deltoid operation. Tension is set by the combination of glenoid component position, humeral component height and polyethylene thickness. Too loose, and the result is instability and dislocation, with weak elevation because the deltoid works below its optimum length. Too tight, and the result is acromial and scapular spine stress fracture, axillary nerve and brachial plexus traction neurapraxia, pain, and loss of the last degrees of elevation.
The target. Roughly 1 to 2 cm of arm lengthening compared with the contralateral side. Beyond 2 to 3 cm the neurological and acromial risks rise sharply. Lateralised designs reduce scapular notching and improve rotation but increase the load transmitted to the glenoid baseplate and to the acromion; their tensioning target differs from a classic medialised Grammont design and must follow the specific implant system.
Judging tension on the table. Intra-operative assessment rests on:
- Tension of the conjoined tendon, which should be taut but not bowstringing
- The ability to distract the components a few millimetres with a trial in place
- Stability through a full range including adduction and internal rotation
- Comparison of humeral length on an intra-operative or immediate post-operative radiograph
- 1Look at the contourA visible defect at the acromion or a step in the anterior contour suggests dehiscence rather than denervation. Palpate all three heads during isometric contraction.
- 2Separate denervation from detachmentDenervation affects the whole distribution of the involved branch and is accompanied by teres minor change if the posterior branch is involved. Detachment produces a mechanical defect with an intact nerve on EMG.
- 3Time the electromyographyFibrillation potentials take three to four weeks to appear. An EMG performed in the first fortnight will be falsely reassuring.
- 4Decide the pathwayTraction neurapraxia: observe with maintained passive motion, repeat EMG at three months. Dehiscence: consider early reattachment to bone before retraction and fatty change. No recovery by three to six months: consider exploration or nerve transfer.
Guidelines, Registries & Global Practice
Anatomical variation across populations
- The distance from the acromion to the axillary nerve scales with arm length, correlating strongly in cadaveric measurement, so a fixed 5 cm rule applied without adjustment is less safe in populations of smaller average stature and in any short-armed patient. Measuring against the patient in front of you is the correct practice everywhere.
- Accessory heads of the deltoid and variations in the raphes between heads are described in cadaveric series and can make the plane of a split less obvious.
- Os acromiale, an unfused acromial epiphysis, alters the deltoid origin mechanically and has variously reported prevalence between populations. It matters both as a cause of pain after decompression and as a site of failure after reverse arthroplasty, where deltoid tension is increased.
Side-by-side guidance
- Position Relevant to the Deltoid
- Supports arthroplasty for cuff tear arthropathy in appropriately selected patients and recognises deltoid competence as a prerequisite for reverse arthroplasty.
- Position Relevant to the Deltoid
- Recommend documented neurological assessment before and after reduction of a shoulder dislocation, and structured rehabilitation with maintained passive range for axillary nerve palsy.
- Position Relevant to the Deltoid
- Defines the deltoid-splitting safe zone and mandates identification and protection of the axillary nerve in minimally invasive plate osteosynthesis of the proximal humerus.
- Position Relevant to the Deltoid
- Emphasise deltoid tensioning targets in reverse arthroplasty and the recognition of acromial stress fracture as a distinct complication of over-lengthening.
Registry and outcome signals
- National joint registries (AOANJRR, NJR, AJRR) show reverse total shoulder arthroplasty as the fastest-growing category of shoulder replacement, with good medium-term survivorship and an expanding set of indications including proximal humeral fracture in the elderly.
- Registries record revision, not deltoid function, so complications such as acromial stress fracture and deltoid weakness are under-represented; their true incidence comes from institutional series and is meaningfully higher than registry revision rates suggest.
- Signal across registries and cohorts: lateralised designs reduce scapular notching and improve rotation, at the cost of greater load at the baseplate and the acromion. The tensioning target is design-specific.
- Documented neurological assessment before and after reduction of a shoulder dislocation is an established quality standard in most systems, driven as much by medicolegal experience as by clinical evidence.
High-resource versus limited-resource practice
- Well-resourced settings: routine CT for suspected acromial stress fracture, electromyography for nerve assessment, reverse arthroplasty available for the cuff-deficient shoulder, and nerve transfer surgery for failed axillary nerve recovery.
- Limited-resource settings: the assessment that matters most, palpation of deltoid contraction in all three heads, requires nothing but hands and is more informative than any imaging. Where reverse arthroplasty is unavailable, preserving deltoid function through meticulous approach selection is even more important, since there is no salvage for a deltoid palsy.
- Wherever practice occurs, the two universal rules are the same: measure the split from the acromion, and document deltoid contraction before and after any shoulder reduction.
MCQ Practice Points
Q: How far distal to the lateral acromion does the anterior branch of the axillary nerve cross the deep surface of the deltoid? A: Roughly 5 to 7 cm. Cetik measured a mean of 6.08 cm from the anterior acromial edge and 4.87 cm from the posterior edge, both correlating with arm length rather than being fixed. Use a 5 cm limit conventionally and 3.5 to 4 cm in a short-armed patient.
Q: What is the single most reliable bedside test of axillary nerve motor function? A: Palpation of deltoid contraction during isometric abduction. Range of abduction is not a deltoid test, because the supraspinatus and scapular rotators can abduct a denervated shoulder.
Q: Does normal regimental badge sensation exclude an axillary nerve injury? A: No. Sensation over the lateral deltoid is frequently preserved despite complete motor loss. It is corroborative, never diagnostic.
Q: Which head of the deltoid is multipennate and what does that mean functionally? A: The middle (acromial) head. Pennate architecture gives high force over a short excursion, which is why it is the powerful abductor and why it is sensitive to changes in resting length.
Q: What is the internervous plane of the deltopectoral approach? A: Deltoid (axillary nerve) and pectoralis major (medial and lateral pectoral nerves).
Q: How does a reverse arthroplasty improve deltoid function? A: By medialising the centre of rotation, which lengthens the deltoid moment arm, and by distalising the humerus, which tensions the muscle and recruits anterior and posterior fibres into elevation.
Q: How much arm lengthening is acceptable in a reverse arthroplasty? A: Roughly 1 to 2 cm. Beyond 2 to 3 cm the risks of acromial and scapular spine stress fracture and of axillary nerve and brachial plexus traction rise sharply.
Q: What is the deltoid tuberosity index and what value indicates poor bone quality? A: The ratio of outer to inner cortical diameter on the anteroposterior radiograph at the level where the lateral cortex first becomes parallel. A value below about 1.4 indicates poor local bone quality and predicts fixation failure.
Q: How should the deltoid origin be repaired after an anterosuperior approach? A: Through transosseous drill holes in the acromion, using an origin taken with a cuff of periosteum and fascia or a thin bone flake. Fascia-to-fascia repair fails.
Q: Why can a patient with a normal deltoid and a normal cuff still fail to elevate the arm? A: Because scapular upward rotation by the trapezius and serratus anterior provides the platform. Long thoracic or spinal accessory nerve palsy destroys scapulohumeral rhythm and makes a normal deltoid ineffective.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 68-year-old woman has had a first-time anterior shoulder dislocation reduced in the emergency department. On review the following day she cannot abduct the arm. How do you assess her and what do you tell her?”
“You are plating a proximal humeral fracture through a lateral deltoid-splitting approach with a minimally invasive technique. Describe exactly how you protect the axillary nerve.”
“Eight months after a reverse total shoulder arthroplasty that initially went well, a 74-year-old man develops new pain over the top of the shoulder and has lost 40 degrees of active elevation. Radiographs look unchanged. What is your differential and what do you do?”
Attachments
- Anterior head: lateral third of the clavicle
- Middle head: lateral border of the acromion, multipennate
- Posterior head: crest of the scapular spine
- Insertion: deltoid tuberosity, mid lateral humeral shaft
- Deltoid tuberosity index below 1.4 equals poor bone quality
Nerve and Vessels
- Axillary nerve C5-C6 from the posterior cord
- Anterior branch: middle and anterior deltoid, around the surgical neck
- Posterior branch: posterior deltoid, teres minor, regimental badge sensation
- Posterior circumflex humeral artery is the dominant pedicle
- Thoracoacromial deltoid branch runs with the cephalic vein
Safe Zones
- Nerve sits at about 0.20 of arm length from the anterior acromion, 0.16 from the posterior - it is a RATIO, not a fixed distance
- That is 5 to 7 cm in an average adult; the POSTERIOR margin is the tighter one, around 4 cm in a 25 cm arm
- Stay suture at the apex of every split
- Nerve about 2 cm distal to the inferior glenoid rim
- Nerve 1 to 2 cm from the inferior border of subscapularis
Function
- About 50 per cent of abduction torque
- Moment arm grows from about 1 cm at 0 degrees to 3 cm at 60 to 90 degrees
- Anterior and posterior heads assist abduction above 90 degrees
- Needs a cuff-generated fulcrum or its force becomes shear
- Scapulohumeral rhythm 2:1 provides the platform
Pitfalls
- Test contraction, not abduction range
- Normal regimental badge sensation does not exclude palsy
- Deltoid origin must be repaired to bone, never fascia to fascia
- Reverse lengthening 1 to 2 cm; over 2 to 3 cm risks acromial fracture
- New acromial pain after a reverse means CT, not reassurance
Evidence Base
Is There a Safe Area for the Axillary Nerve in the Deltoid Muscle? A Cadaveric Study
- Twenty-four embalmed adult cadaveric shoulders; distance from the anterior and posterior acromial edges to the course of the axillary nerve measured and related to arm length
- Mean anterior distance 6.08 cm and mean posterior distance 4.87 cm, with a mean arm length of 30.40 cm
- Both distances correlated significantly with arm length (r equals 0.79 anteriorly, 0.61 posteriorly); the anterior index was 0.20 and the posterior index 0.16 of arm length
- The nerve does not lie at a constant distance from the acromion along its course; the safe area is quadrangular with lateral edges dependent on the individual's arm length
Grammont Inverted Total Shoulder Arthroplasty in the Treatment of Glenohumeral Osteoarthritis with Massive Rupture of the Cuff
- 80 shoulders in 77 patients reviewed at a mean of 44 months after a Grammont inverted prosthesis
- Mean Constant score improved from 22.6 to 65.6 points, with no or only minimal pain in 96 per cent
- Mean active forward elevation improved from 73 to 138 degrees
- The integrity of teres minor was essential for recovery of external rotation and significantly influenced the Constant score; five glenoid loosenings and seven glenoid component dissociations occurred
2014 Neer Award Paper: Neuromonitoring the Latarjet Procedure
- Continuous intra-operative neuromonitoring during 34 Latarjet procedures divided into nine defined stages
- 26 of 34 patients (76.5 per cent) had a total of 45 nerve alert episodes
- The axillary nerve was involved in 35 alerts and the musculocutaneous nerve in 22; glenoid exposure and graft insertion were the highest-risk stages
- 7 of 34 patients (20.6 per cent) had a clinically detectable post-operative deficit, all involving the axillary nerve, and all resolved by 28 to 165 days
Classification of Postoperative Acromial Fractures Following Reverse Shoulder Arthroplasty
- Sixteen acromial fractures identified in 18 patients presenting with acromial or scapular spine pain after reverse arthroplasty
- Radiographs were unreliable both for detecting the fracture at presentation and for confirming union; CT was required
- A three-type classification based on how much of the deltoid origin is involved showed excellent interobserver reliability
- All fractures were treated non-operatively and functional outcomes were limited
Nerve Lesions in Primary Shoulder Dislocations and Humeral Neck Fractures: A Prospective Clinical and EMG Study
- Prospective study of 101 patients with a primary shoulder dislocation or humeral neck fracture
- Electrophysiological evidence of nerve injury in 45 per cent - far more than clinical examination detected
- Most involved the axillary, suprascapular, radial and musculocutaneous nerves; injuries were significantly more common in older patients and in those with a haematoma
- Most recovered partially or completely in under four months, and only eight patients had persistent motor loss
Deltoid Tuberosity Index: A Simple Radiographic Tool to Assess Local Bone Quality in Proximal Humerus Fractures
- Ratio of outer cortical to inner endosteal diameter measured on the anteroposterior radiograph just above the deltoid tuberosity, where the cortical borders become parallel
- Strong correlation with local bone mineral density on peripheral quantitative CT (r equals 0.80)
- A cut-off of 1.44 gave sensitivity 0.88 and specificity 0.80; values consistently below 1.4 indicated low local bone mineral density
- Measurable on 96 per cent of fracture radiographs, outperforming the Tingart measurement whose landmarks are often obscured by fracture lines