Proximal ablative surgery — last-resort but potentially curative operations demanding meticulous vascular control, durable soft-tissue coverage and honest counselling
- Absolute oncologic indications: encasement of the major neurovascular bundle where resection cannot achieve a functional limb, fungating/infected tumour, local recurrence after failed limb salvage, and pathological state precluding reconstruction
- Hip disarticulation: racquet incision based on the ASIS, femoral vessels ligated individually in the femoral triangle BEFORE deep dissection, posterior gluteus maximus flap sewn forward to the pubis/adductor origin for a weight-tolerant stump
- Forequarter amputation removes the entire upper limb with scapula and lateral clavicle; anterior (Berger) approach gives early subclavian vessel control, posterior (Littlewood) approach gives superior exposure for posteriorly based tumours
- Ligate the subclavian artery and vein separately (never en masse — risk of arteriovenous fistula) and divide the brachial plexus sharply under gentle traction with local anaesthetic infiltration
- Oncologic handling: never enter the tumour, take the biopsy tract with the specimen, orientate and ink margins with the pathologist
- Prosthetic reality must be discussed pre-operatively: Canadian-type hip disarticulation socket has very high energy cost; a forequarter prosthesis is essentially a cosmetic shoulder cap
- “The corona mortis — a retropubic anastomosis between obturator and external iliac/inferior epigastric systems — can retract into the pelvis if avulsed during obturator dissection and cause life-threatening haemorrhage
- “Pre-emptive multimodal analgesia (regional catheter, gabapentinoids, ketamine) reduces the severity of phantom limb pain; targeted muscle reinnervation at the index amputation is an emerging preventive strategy
- “Chest-wall preservation is the key intra-operative constraint in forequarter amputation — breach of the pleura converts the case to an intrathoracic emergency
Indications and Decision-Making
Proximal amputation is chosen only when it offers something limb salvage cannot: oncologic clearance, source control of infection, or removal of a painful, useless limb. In specialist centres fewer than 5% of malignant bone and soft-tissue tumours now require amputation, and when none of the thresholds below is met the default is continued limb salvage with reconstruction and adjuvant therapy.
Staging first. MRI of the whole limb, CT of the chest, and PET or bone scan as indicated, with the histology and any prior radiotherapy field reviewed. The case is presented to the sarcoma or limb-reconstruction MDT with the oncologist, radiologist, pathologist, plastic surgeon and rehabilitation physician in the room. Staging must be current; never amputate on stale imaging.
Major neurovascular encasement. The question is true encasement, not mere abutment: the sciatic nerve plus the femoral vessels at the hip, the brachial plexus at the shoulder. If resection would leave a limb without useful function, proceed toward hip disarticulation or forequarter amputation. Abutment alone, with a reconstructable vessel or a preserved motor nerve, keeps salvage on the table.
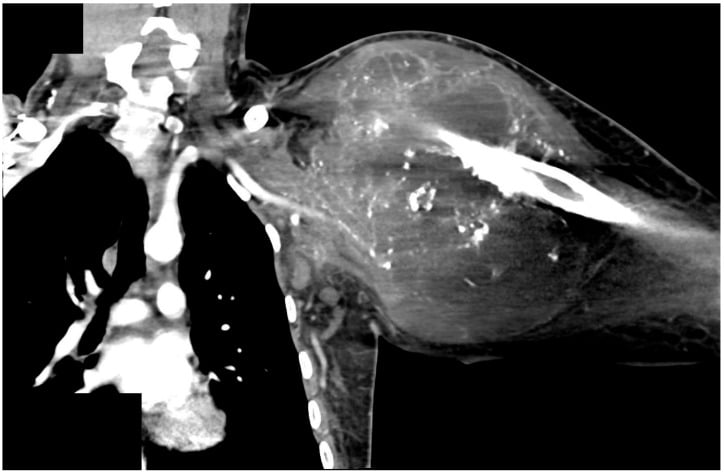
Tumour hygiene. A fungating, infected or haemorrhagic tumour whose dressings, odour and bleeding cannot be controlled justifies a palliative-intent 'toilet' amputation for wound control and quality of life. Ablation is justified here even without cure as the goal.
Recurrence and multicompartment disease. Proximal amputation is chosen where further salvage would leave an unreconstructable defect; re-resection is considered only if a durable soft-tissue envelope and a functional limb remain possible. The patterns that bring this on:
- Local recurrence after limb salvage, especially in a previously irradiated field
- Massive tumours crossing compartments with skip lesions or extensive skin involvement
- Pathological fracture through a chemotherapy-unresponsive sarcoma with compartmental contamination
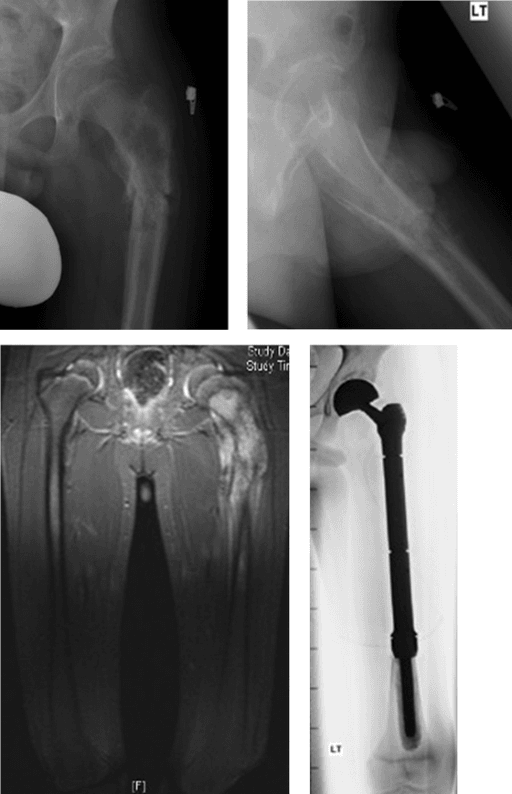
Sepsis, trauma and ischaemia. Here the operation is source control, and hip disarticulation can be life-saving in proximal necrotising infection. The indications:
- Necrotising fasciitis of the thigh, buttock or shoulder girdle failing serial debridement
- Chronic osteomyelitis in a nonfunctional, insensate or painful limb
- A mangled proximal limb with an unreconstructable vascular injury, or a dead limb with systemic toxicity
- Critical ischaemia extending above any possible transfemoral level
The mortality of proximal necrotising infection is high, and ischaemic cases in this frail cohort carry very high perioperative mortality. Emergency hip disarticulation for necrotising infection or ischaemia carries markedly higher perioperative mortality than elective oncologic disarticulation, and the consent should reflect this.
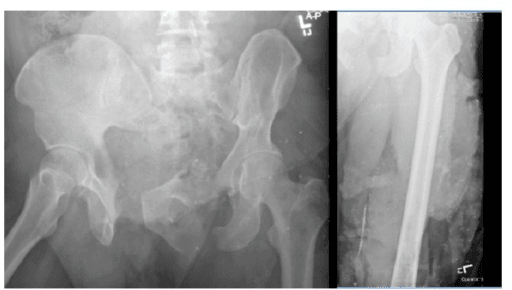
The important negative. Metastatic disease is not an automatic contraindication. Forequarter amputation for a fungating recurrent sarcoma can be justified for palliation and quality of life; the systemic burden is balanced against symptom relief in an explicit palliative discussion, and a futile lesion is not amputated without one.
Preparing the patient. Body image, phantom phenomena normalised in advance, realistic prosthetic expectations, sexual function and continence perception after hip disarticulation, and return to work are all discussed before the operation. A clinical psychologist and a peer amputee visitor are involved pre-operatively, and early contact with the prosthetic and rehabilitation team improves adjustment. Consent explicitly for:
- Haemorrhage and transfusion
- Wound necrosis
- Phantom pain
- Possible pleural breach in forequarter amputation
- Intra-operative change of flap design
Applied Anatomy
The femoral triangle. Bounded by the inguinal ligament, adductor longus and sartorius, it holds the femoral nerve, artery and vein from lateral to medial (NAVeL toward the lymphatics), and it is the site of primary vascular control in hip disarticulation.
The obturator bundle and the corona mortis. The obturator vessels and nerve exit the obturator foramen deep to pectineus. The corona mortis connects the obturator and external iliac/inferior epigastric systems over the superior pubic ramus in roughly 20 to 40 percent of patients.
The sciatic nerve emerges below piriformis with the inferior gluteal vessels. It carries a substantial arterial companion, the artery to the sciatic nerve, which must be ligated separately.
Gluteus maximus with its inferior gluteal pedicle is the workhorse posterior flap. Its blood supply, the superior and inferior gluteal arteries from the internal iliac, is independent of the femoral system, which is why the flap survives femoral ligation.
The forequarter specimen comprises the entire upper limb, scapula and lateral two-thirds of the clavicle. The limb is attached to the trunk only by the clavicle, a bony strut, and by its muscular envelopes.
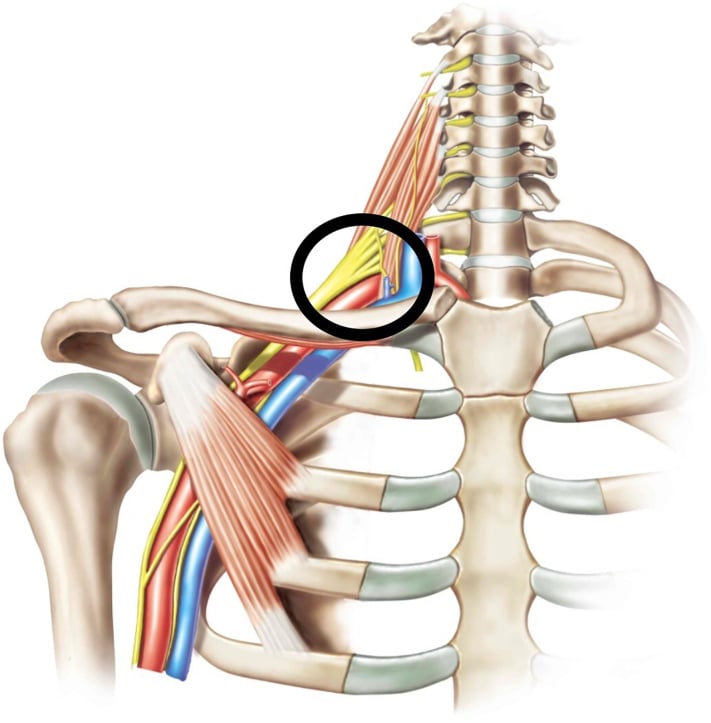
The neurovascular bundle. The subclavian vessels and brachial plexus cross the first rib around scalenus anterior, the artery behind the muscle and the vein in front of it. Resecting or dividing the clavicle unroofs them.
The muscles that hold the quarter on. Dividing the posterior group "drops" the scapula away from the chest wall.
- Anterior: pectoralis major and minor, subclavius, omohyoid, the latissimus dorsi insertion
- Posterior: trapezius, rhomboids major and minor, levator scapulae, serratus anterior
Structures to protect on the chest wall.
- Pleura and first rib
- Thoracic duct on the left (chylous leak at the venous confluence)
- Phrenic nerve on scalenus anterior
- External jugular and transverse cervical vessels
Hip Disarticulation — Operative Technique
The classic technique is Boyd's: the femoral vessels are controlled before the deep dissection, the muscles come off the femur in turn, the joint is disarticulated, and the gluteal flap is brought forward.
Position and preparation. Supine with the ipsilateral buttock elevated on a sandbag, or lateral or semi-lateral if a large posterior flap is needed for a posterior tumour. The whole limb, hemipelvis, flank and perineum are prepped, the limb draped free, and the perineum is then excluded with an adhesive drape, with a urinary catheter in situ. Cross-match at least 2 to 4 units, with cell salvage available where oncologically appropriate (it is contraindicated with tumour contamination or infection), vascular instruments and warmed fluids. Prophylactic antibiotics are given and an epidural or regional catheter placed for pre-emptive analgesia. Review the MRI to confirm the flap territories are tumour-free, and mark the racquet incision with the flaps drawn on the awake or anaesthetised patient and re-checked against the imaging.
The racquet incision begins at the ASIS, passes distally and medially parallel to the inguinal ligament to a point on the medial thigh roughly 5 cm below the origin of adductor longus, sweeps around the posterior thigh as the apex of the posterior flap, then returns laterally up over the greater trochanter to the ASIS.
Vascular control. Raise the anterior flap and open the femoral triangle: divide the femoral sheath and isolate the femoral artery and vein individually. Doubly ligate and suture-ligate the artery, then ligate the vein separately, never the two en masse, which risks an arteriovenous fistula. Delaying the venous ligation until after arterial occlusion can decompress the limb, and early venous ligation also limits tumour embolisation in oncologic cases. A slipped femoral artery tie is catastrophic; an unsecured femoral or profunda stump is the source of massive haemorrhage. Divide the femoral nerve sharply under gentle traction after infiltration with long-acting local anaesthetic, so that it retracts proximally away from the scar.
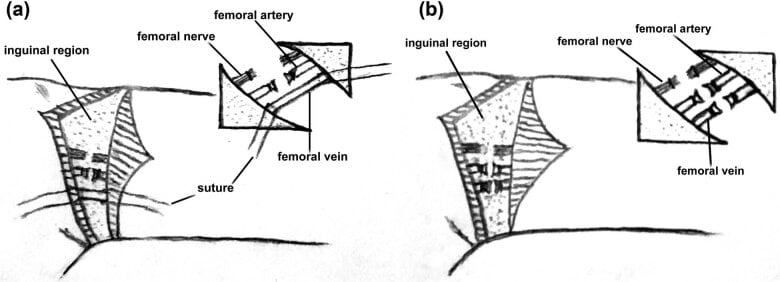
Anterior and medial dissection. Detach sartorius from the ASIS and rectus femoris from the AIIS, and divide iliopsoas at the lesser trochanter. Divide pectineus near the pubis to expose obturator externus and the obturator neurovascular bundle, and ligate the obturator vessels deliberately near the foramen. Do not avulse them: an avulsed vessel retracts through the obturator foramen into the pelvis via the corona mortis and the haemorrhage is very difficult to control, so control it before it disappears, and have pelvic packing and a vascular set available. Release the adductors from the pubis, or divide them in bulk distally if margins demand muscle on the specimen, and divide gracilis and the hamstring origins from the ischial tuberosity. The pudendal structures and perineum are at risk in the medial dissection, and the bladder and spermatic cord beneath the medial flap.
Lateral and posterior release. Externally rotate the limb and divide the abductors from the greater trochanter, then the short external rotators, ligating the branches of the medial and lateral circumflex vessels and the cruciate anastomosis as they are met. Identify the sciatic nerve below piriformis and ligate its accompanying artery first, then infiltrate the nerve with local anaesthetic, apply gentle traction and divide it sharply so that it retracts under gluteus maximus.
Disarticulation. A circumferential capsulotomy, then division of the ligamentum teres: flexion, adduction and external rotation opens the joint and delivers the head, completing the disarticulation. Remove the specimen, orientate it and ink it for pathology. Secure haemostasis and irrigate copiously.
The gluteus maximus flap. Bring the posterior gluteus maximus myofasciocutaneous flap forward and myodese it to the pubis, inguinal ligament and adductor origins. This converts the buttock into a durable, weight-distributing end-bearing pad over the ischium and acetabulum and obliterates the dead space; the flap gives sensate, padded, muscle-backed skin able to tolerate socket end-bearing. Consider tacking the flap into the acetabulum or covering the acetabulum with residual capsule. The inferior gluteal pedicle is the lifeline of this flap and must not be skeletonised or kinked at myodesis. An anteriorly based quadriceps flap is the salvage option when the posterior tissues are involved by tumour or infection, and this is planned from the pre-operative MRI, not on the table. Large-bore suction drains, a layered tension-free closure and a light compressive spica-type dressing complete the operation.
Aftercare. Drains stay until output settles, with stump haemostasis checked and pressure care over the ischium; ischial pressure necrosis of the flap is the hazard. The phantom pain protocol starts from day zero. Prosthetic assessment follows once the wound is sound, typically at 6 to 12 weeks.
Forequarter (Interscapulothoracic) Amputation — Operative Technique
Choosing the approach. Tumour location and how highly the surgeon prizes early haemorrhage control decide between Berger's anterior and Littlewood's posterior approach. Many surgeons use a combined approach: an anterior first stage for vascular control, then reposition or roll the patient to complete the posterior release.
- Anterior (Berger)
- Early — clavicle resected first, subclavian vessels ligated before mobilisation
- Posterior (Littlewood)
- Late — scapula mobilised first, vessels reached from behind at the end
- Anterior (Berger)
- Anteriorly based tumours; surgeons prioritising early haemorrhage control
- Posterior (Littlewood)
- Posteriorly based tumours (scapular, posterior chest-wall sarcoma); wider posterior margin
- Anterior (Berger)
- Lower once vessels controlled early
- Posterior (Littlewood)
- Potentially greater during muscular dissection before ligation
- Anterior (Berger)
- Supine/semi-lateral
- Posterior (Littlewood)
- Lateral, limb draped free and rotated forward over the chest
Anterior (Berger) sequence: preparation and incision. Supine with the shoulder elevated and the limb draped free, blood cross-matched, and the anaesthetist warned about pleural breach and vessel control. The incision runs along the clavicle from the sternoclavicular joint, curving over the deltopectoral groove into the axilla anteriorly, with a posterior limb along the scapular spine and lateral scapular border to meet it in the axilla.
Unroofing and ligating the vessels. Detach pectoralis major from the clavicle, then divide or resect the middle third of the clavicle (an osteotomy or claviculectomy at the medial extent), which unroofs the subclavian vessels. Divide subclavius and pectoralis minor. Identify and ligate the subclavian artery first, with double ligation plus suture-ligation, then the subclavian vein separately, never the two together.
Dividing the plexus. Infiltrate the trunks of the brachial plexus with local anaesthetic and divide them sharply and proximally, allowing them to retract behind scalenus anterior. Protect the phrenic nerve and, on the left, the thoracic duct.
Freeing the scapula. Divide latissimus dorsi and the remaining axillary soft tissue, then pass posteriorly: divide trapezius, omohyoid, levator scapulae, the rhomboids and finally serratus anterior, freeing the scapula from the chest wall and delivering the specimen.
Posterior (Littlewood) sequence. Lateral position, tumour side up, with the entire quarter prepped. The posterior incision runs along the vertebral border of the scapula and the scapular spine; trapezius, rhomboids, levator scapulae and serratus anterior are divided, hinging the scapula laterally and forward off the chest wall like an open book. Blood loss is potentially greater during this muscular dissection before any vessel is tied, and the pleura is at risk during the serratus and rhomboid release. Retract the specimen anteriorly, identify the neurovascular bundle at the apex of the axilla and first rib from behind, ligate the subclavian artery then the vein, and divide the plexus as for the anterior approach. Complete the anterior musculocutaneous division (the pectorales and the clavicular osteotomy) and remove the specimen.
Chest-wall preservation. The dissection plane hugs the chest wall, on serratus anterior and the ribs, and it stays superficial to the ribs and intercostal fascia except where the tumour dictates en bloc chest-wall resection. That is planned pre-operatively with thoracic colleagues, because rib resection needs mesh or flap chest-wall reconstruction. Check for a pleural breach whether or not one was suspected: fill the wound with saline and have the anaesthetist give a Valsalva breath. If the pleura is breached, insert a chest drain; a breach converts the case to an intrathoracic emergency.
Closure. After haemostasis and drains, close by advancing the posterior/medial skin flap over the chest-wall defect. In tumour cases where the skin must go with the specimen, a fillet forearm free flap from the amputated limb is the elegant spare-parts solution for coverage. A post-operative chest radiograph is mandatory.
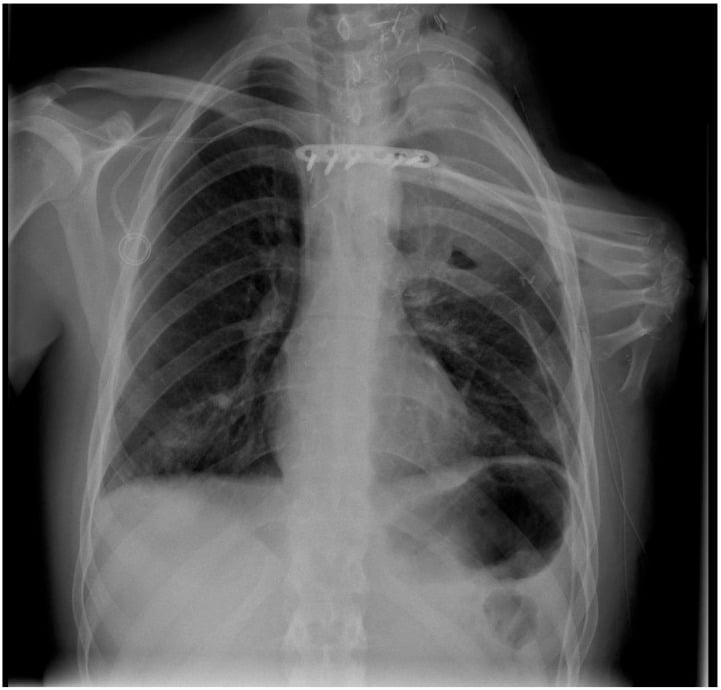
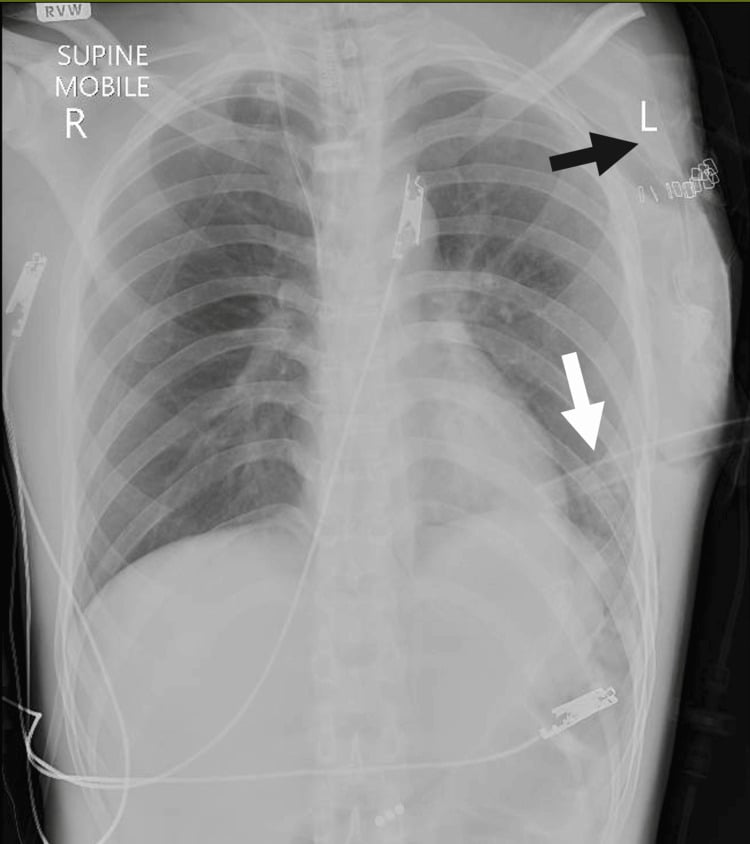
These are usually curative-intent operations for tumours failing limb salvage, and contaminating the field converts a curative amputation into a palliative one. The biopsy tract must be excised en bloc with the specimen in both operations. Never rupture the tumour or dissect within its reactive zone; if margins are in doubt, sacrifice the planned flap and take more tissue — closure problems are solvable, a contaminated margin is not. Orientate the specimen with sutures and ink margins with the pathologist; send separate marginal samples from any area of concern.
Complications
The table sets out the six structures at risk, where each lies, how it is injured, how the injury is avoided and what to do if it happens.
- Where
- Retropubic, crossing the superior pubic ramus between obturator and external iliac systems
- Mechanism
- Avulsed on retraction or blind division of the pubic attachments during hip disarticulation
- Avoid by
- Deliberate obturator dissection; identify and double ligate with suture-ligature before dividing pubic structures
- If injured
- Pack and apply pressure, gain proximal iliac control or pelvic packing, call vascular surgery
- Where
- Femoral triangle beneath the inguinal ligament, medial to the nerve
- Mechanism
- Slipped or single tie retracting proximally beneath the ligament after division
- Avoid by
- Individual double ligation with suture-ligature, divided distal to a secure proximal tie; early vascular control before flap elevation
- If injured
- Extend proximally for iliac control, retrieve the vessel, re-ligate; do not blindly clamp
- Where
- Within or alongside the sciatic nerve in the posterior thigh and buttock
- Mechanism
- Nerve divided sharply without first ligating its accompanying vessel, causing brisk delayed bleeding
- Avoid by
- Ligate the companion artery before traction neurectomy; divide the nerve sharply under traction with local anaesthetic so it retracts into muscle
- If injured
- Retrieve the retracted nerve stump, suture-ligate the vessel, reimplant the nerve into muscle
- Where
- Thoracic inlet, crossing the first rib behind the clavicle
- Mechanism
- Tie slips off the short stump after clavicular division in forequarter amputation
- Avoid by
- Obtain proximal control at the thoracic inlet first; double ligate plus transfix suture with generous stump length
- If injured
- Immediate digital pressure on the inlet, sternotomy or supraclavicular extension for proximal control
- Where
- Deep to the first and second ribs and the scalene insertions
- Mechanism
- Dissection carried deep to the ribs during scapulothoracic release, or thoracic duct injury on the left
- Avoid by
- Stay superficial to the ribs; identify the thoracic duct on the left; saline test before closure
- If injured
- Chest drain for pneumothorax; low-fat diet plus or minus duct ligation for chylous leak
- Where
- Between the scalenes, entering the axilla with the subclavian vessels
- Mechanism
- Traction division leaving long stumps in the wound bed, or nerves cut without ligating vasa nervorum
- Avoid by
- Ligate the plexus stumps, divide sharply under traction with local anaesthetic so ends retract into soft tissue; consider targeted muscle reinnervation at index surgery
- If injured
- Excise and reimplant into muscle; TMR or regenerative peripheral nerve interface for refractory neuroma pain
Wound necrosis and dehiscence. Prevented by tension-free, well-vascularised flaps planned on the pre-operative imaging, and by not skeletonising the inferior gluteal pedicle. A failed wound is debrided and dressed with negative pressure, then closed secondarily or with a flap: spare-parts fillet, or latissimus if it is still available.
Seroma and haematoma. Meticulous haemostasis, obliteration of the dead space by myodesis and suction drains are the prevention. Aspiration and compression are the first response, with re-exploration if the collection is infected or expanding.
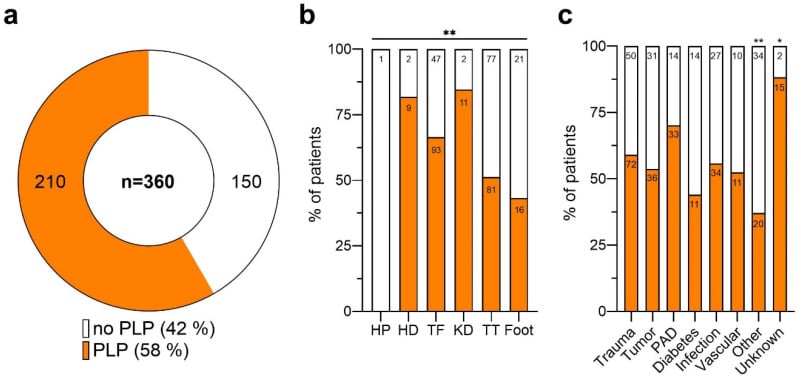
Phantom limb pain. Between 60 and 80 percent of patients experience phantom phenomena. Prevention starts before the incision with pre-emptive regional analgesia, gabapentinoids and ketamine, continues with sharp proximal nerve division under traction after local anaesthetic infiltration, and may include targeted muscle reinnervation at the index operation, which is emerging. Established pain is treated multimodally with gabapentinoids, tricyclics, mirror therapy, graded motor imagery and desensitisation, with TMR or nerve capping for refractory neuroma pain.
Neuroma. Traction neurectomy so that the nerve ends retract into muscle, or targeted muscle reinnervation, is the prevention. A symptomatic neuroma is excised and the nerve reimplanted into muscle, or treated by TMR or a regenerative peripheral nerve interface.
Psychological morbidity. Body-image disturbance and depression are prevented as far as they can be by pre-operative psychology input, peer support and honest expectation-setting, and treated with ongoing psychological support, amputee groups and early prosthetic and rehabilitation engagement.
Phantom sensation (non-painful awareness of the limb — near universal, needs only reassurance), phantom pain (pain perceived in the absent limb — central), and residual limb/stump pain (local, peripheral — think neuroma, infection, bony prominence, poor socket fit). The management pathways differ, so name which one the patient has.
Prosthetic Reality and Rehabilitation
The Canadian prosthesis. The standard device after hip disarticulation is the Canadian-type hip disarticulation prosthesis, Colin McLaurin's design: a moulded socket embracing the hemipelvis and bearing weight on the ischium and gluteal pad, an anteriorly placed free hip joint, a stance-stable knee and a dynamic foot. Placing the hip joint anteriorly gives inherent alignment stability in stance.
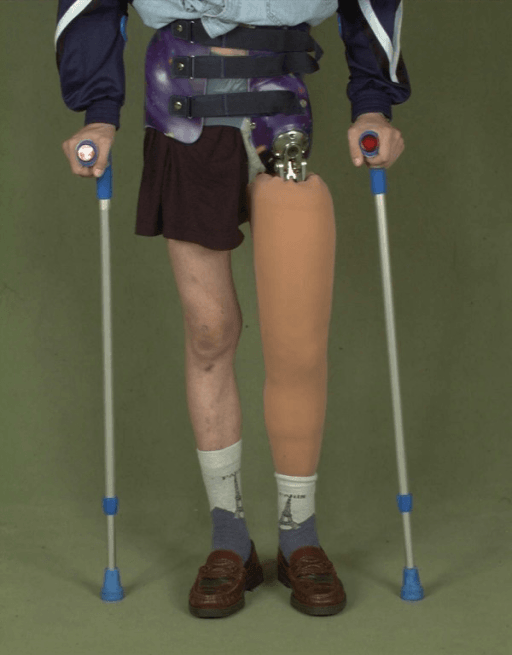
Gait and what it costs. The pattern is a stiff, tilting, step-to or slow step-through gait. The measured cost, from the only study of this level (Nowroozi 1983, 8 hip disarticulation and 10 hemipelvectomy amputees), is 80 to 125 percent more energy per metre walked than able-bodied controls, and the figure is cost per distance, not per minute. Oxygen uptake per minute was no different from controls at comfortable speed; what fell was speed, to just 51 to 61 percent of normal. Pushed to walk fast, the amputees reached only 70 to 75 percent of the controls' comfortable speed and paid 40 to 50 percent more oxygen to do it. So the patient does not feel more breathless: they go half as far for the same effort, and run out of reserve when hurried. This is the trade patients make without being told to.
Honest counselling. Many patients ultimately abandon the prosthesis in favour of elbow crutches or a wheelchair, because crutch gait is faster and less exhausting. Younger, fitter patients and those with strong motivation do best.
The rehabilitation sequence. Sitting balance and trunk strengthening from day one, oedema control and stump shaping, then a standing frame; casting for the socket once the wounds are sound and the volume stable; then gait training with the rehabilitation team.
After forequarter amputation. Functional prostheses, body-powered or myoelectric, have almost no useful control sources at this level and are very rarely used functionally; the loss of the scapular platform means there is no useful powered prosthesis. The practical prescription is a lightweight cosmetic shoulder cap that restores shoulder contour, lets clothing hang normally and improves body image. The rehabilitation goals are one-handed independence training, with dominance transfer if needed; management of shoulder-girdle asymmetry and neck pain with physiotherapy and sometimes a counterweight; and psychological adjustment. Occupational therapy and driving and work adaptations matter more to outcome than any device.
Outcomes. Oncologic outcome is determined by tumour biology and margin status, not by the amputation itself, and survival after amputation for high-grade sarcoma parallels stage-matched limb salvage. Quality-of-life studies show amputees adapt substantially over time; pain control and psychological support are stronger determinants of reported quality of life than prosthetic sophistication.
Guidelines, Registries & Global Practice
- Global epidemiology: in high-resource sarcoma centres, limb salvage is achieved in well over 90 percent of extremity sarcomas, so proximal amputations are rare, concentrated operations best done in specialist units. In lower-resource settings, late presentation with fungating or massive tumours makes primary hip disarticulation and forequarter amputation proportionally far more common, and they remain essential curative operations where advanced reconstruction and radiotherapy are unavailable.
- Society guidance: sarcoma pathways from ESMO/EURACAN, NCCN and national sarcoma guidelines (including UK NICE sarcoma service guidance) converge on the same principles — management within a specialist sarcoma MDT, image-guided biopsy along a planned resectable tract, and amputation reserved for tumours where salvage cannot achieve adequate margins with a functional limb. BOA/BAPRAS ortho-plastic principles (as in open-fracture standards) apply to flap planning and combined soft-tissue decision-making in trauma indications.
- Registries: national amputee rehabilitation datasets (e.g. UK limb-fitting service data, Scandinavian amputation registers) consistently show hip disarticulation and hindquarter levels form a very small fraction of lower-limb amputations, with low sustained prosthetic use compared with transfemoral levels — evidence to quote when counselling.
- Practice variation: targeted muscle reinnervation and osseointegration expertise is concentrated in a few centres; mirror therapy and multimodal pharmacological phantom-pain management are deliverable in any resource setting and should be universal. Spare-parts (fillet flap) reconstruction is particularly valuable where free-flap microsurgery for separate donor sites is unavailable.
Controversies & Areas of Uncertainty
Amputation versus heroic limb salvage at the extremes. With modern vascular grafting and nerve-tolerant strategies, even encased vessels can sometimes be reconstructed, but a salvaged limb that is insensate, painful and functionless serves the patient worse than a well-rehabilitated amputation. The decision remains individualised MDT judgement, not algorithm.
Targeted muscle reinnervation at the index amputation. Growing evidence supports primary TMR for reducing neuroma and phantom pain, but data at hip-disarticulation and forequarter levels are limited, target muscles are scarce, and it adds operative time in often-frail patients.
Palliative "toilet" forequarter amputation for fungating incurable disease. There is a strong quality-of-life rationale, set against the burden of major surgery in patients with a short prognosis; small series support it in selected patients, but patient selection criteria are poorly defined.
Anterior versus posterior forequarter approach. No comparative trial exists; choice is driven by tumour location and surgeon training.
Osseointegration has transformed transfemoral prosthetic use but has no role at disarticulation levels; whether pelvic-anchored solutions will ever be viable is speculative.
MCQ Practice Points
Q: Why must the subclavian artery and vein be ligated separately? A: En masse ligation risks arteriovenous fistula formation. The artery is doubly ligated and suture-ligated first, then the vein separately.
Q: Which flap covers a standard hip disarticulation and why does it survive femoral ligation? A: A posterior gluteus maximus myofasciocutaneous flap myodesed to the pubis/adductor origin; it is supplied by the superior and inferior gluteal arteries from the internal iliac system, independent of the ligated femoral system.
Q: What is the corona mortis and why does it matter here? A: A retropubic anastomosis between the obturator and external iliac/inferior epigastric systems, present in roughly a fifth to a third of patients; avulsion during obturator vessel dissection causes haemorrhage from a vessel that retracts into the pelvis and is difficult to control.
Q: Which forequarter approach gives early vascular control? A: The anterior Berger approach — clavicular resection first unroofs and allows early ligation of the subclavian vessels; the posterior Littlewood approach mobilises the scapula first and reaches the vessels late, but gives better exposure for posteriorly based tumours.
Q: Name three perioperative strategies to reduce phantom limb pain. A: Pre-emptive regional analgesia (epidural or perineural catheter), perioperative gabapentinoids plus or minus ketamine, and sharp traction neurectomy with local anaesthetic infiltration so nerve ends retract into muscle; targeted muscle reinnervation at the index operation is an emerging fourth option.
Q: Define the forequarter specimen. A: The entire upper limb en bloc with the scapula and the lateral portion of the clavicle (interscapulothoracic amputation), with preservation of the chest wall unless en bloc rib resection is oncologically required.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“A 54-year-old presents with local recurrence of a high-grade soft-tissue sarcoma of the proximal thigh two years after wide excision and radiotherapy. MRI shows the recurrence encasing the femoral vessels and abutting the sciatic nerve, with skin tethering in the irradiated field. Staging CT chest is clear. How do you proceed?”
“During the medial dissection of a hip disarticulation for necrotising fasciitis, brisk bleeding erupts from behind the superior pubic ramus and the vessel retracts out of sight. The anaesthetist reports falling blood pressure. What is happening and what do you do?”
“A 47-year-old presents with a massive, fungating, malodorous recurrent sarcoma of the shoulder girdle encasing the brachial plexus and axillary vessels, with a flail painful arm. Staging shows two small lung nodules. She asks whether anything can be done.”
“A 28-year-old awaiting hip disarticulation for pelvic-girdle-sparing proximal femoral osteosarcoma asks: 'Will I walk again, and what will the leg be like?' How do you counsel him?”
Indications
- Tumour: neurovascular encasement precluding a functional limb, fungation, recurrence after failed salvage, massive multicompartment disease
- Infection: necrotising fasciitis failing debridement, chronic osteomyelitis in a nonfunctional limb
- Trauma/ischaemia: unreconstructable proximal injury or non-viable limb above transfemoral level
- Metastases do not preclude palliative toilet amputation for quality of life
Hip disarticulation key steps
- Racquet incision from ASIS; femoral artery and vein ligated individually in the femoral triangle first
- Deliberate obturator vessel ligation — beware corona mortis retraction
- Iliopsoas off lesser trochanter, abductors/rotators off greater trochanter, adductors/hamstrings off pelvis
- Capsulotomy, divide ligamentum teres, deliver head
- Gluteus maximus posterior flap myodesis to pubis/adductor origin — protect the inferior gluteal pedicle
Forequarter key steps
- Specimen: whole upper limb plus scapula plus lateral clavicle; preserve chest wall
- Anterior Berger: clavicle resected first, early subclavian control — artery then vein, separately
- Posterior Littlewood: scapular release first, best for posterior tumours
- Sharp brachial plexus division with local anaesthetic; protect phrenic nerve, pleura, thoracic duct (left)
- Saline test for pleural breach; mandatory post-op chest radiograph; consider fillet spare-parts flap for coverage
Oncologic principles
- MDT decision with current staging; excise biopsy tract and previous scars en bloc
- Never breach the tumour; sacrifice planned flaps rather than margins
- Orientate and ink the specimen with the pathologist
Complications & rehabilitation
- Haemorrhage (corona mortis, slipped ties), wound necrosis, seroma, pneumothorax/chyle leak (forequarter)
- Phantom pain in the majority — pre-emptive regional analgesia, gabapentinoids, mirror therapy, TMR emerging
- Canadian hip disarticulation prosthesis: ischial/gluteal bearing, very high energy cost, many abandon for crutches
- Forequarter prosthesis is essentially a cosmetic shoulder cap; rehabilitation targets one-handed independence and psychological adjustment
Evidence Base
The Treatment of Soft-Tissue Sarcomas of the Extremities - Prospective Randomized Evaluations of Limb-Sparing Surgery Plus Radiation Therapy Compared with Amputation, and the Role of Adjuvant Chemotherapy
- 43 adults with HIGH-GRADE extremity soft-tissue sarcoma randomised 2:1 - 27 to limb-sparing resection plus radiotherapy, 16 to amputation at or above the joint proximal to the tumour; both arms received postoperative doxorubicin, cyclophosphamide and high-dose methotrexate
- Four local recurrences in the limb-sparing arm and none after amputation (p = 0.06)
- No difference in five-year disease-free survival (71 versus 78 per cent, p = 0.75) or overall survival (83 versus 88 per cent, p = 0.99)
- On multivariate analysis the ONLY correlate of local recurrence was the final margin - positive margins recurred more often (p less than 0.0001) even with postoperative radiotherapy
- A parallel randomisation of 65 patients found adjuvant chemotherapy improved three-year continuous disease-free survival (92 versus 60 per cent) and overall survival (95 versus 74 per cent)