The periosteum has one response — new bone — but the SPEED of the insult decides the pattern
- Periosteal reaction is non-specific for aetiology but highly specific for AGGRESSIVENESS. Slow lesions give the periosteum time to lay down a solid, continuous shell; fast lesions outrun it and leave lamellae, spicules or a Codman triangle.
- Continuous and uninterrupted equals benign or healed. Interrupted equals aggressive — tumour, infection or trauma in evolution.
- A Codman triangle is NOT diagnostic of osteosarcoma. It is seen in Ewing sarcoma, osteomyelitis, subperiosteal abscess and subperiosteal haematoma.
- Onion-skin (lamellated) reaction classically means Ewing sarcoma or osteomyelitis, but also appears in osteosarcoma, Langerhans cell histiocytosis and healing stress fracture.
- Sunburst/spiculated (perpendicular) reaction implies Sharpey fibre mineralisation along a rapidly expanding soft tissue mass — osteosarcoma first, then Ewing, metastasis and meningioma of skull.
- Periosteal reaction in an infant under 6 months may be entirely physiological (symmetrical, diaphyseal, 1-4 months of age) — do not call it abuse.
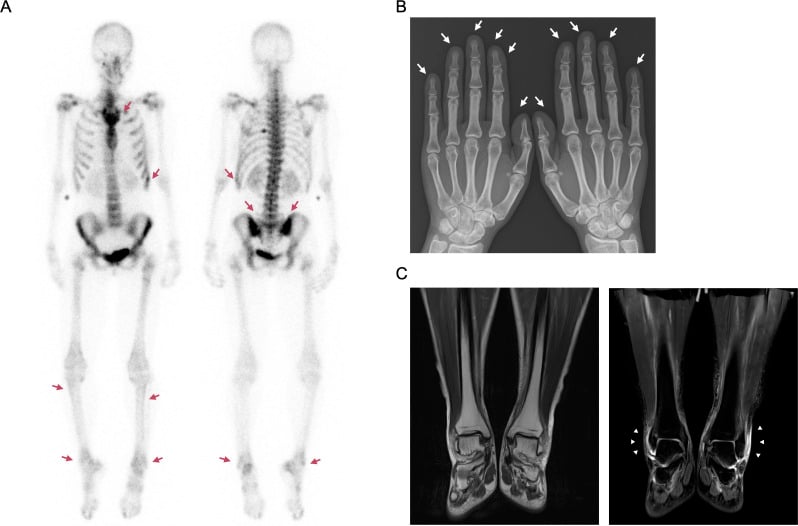
- In an adult with painful symmetrical periostitis of the distal long bones, think hypertrophic pulmonary osteoarthropathy and image the chest.
- “Say the pattern before you say the diagnosis: 'There is an interrupted, lamellated periosteal reaction along the diaphysis, indicating an aggressive process.'
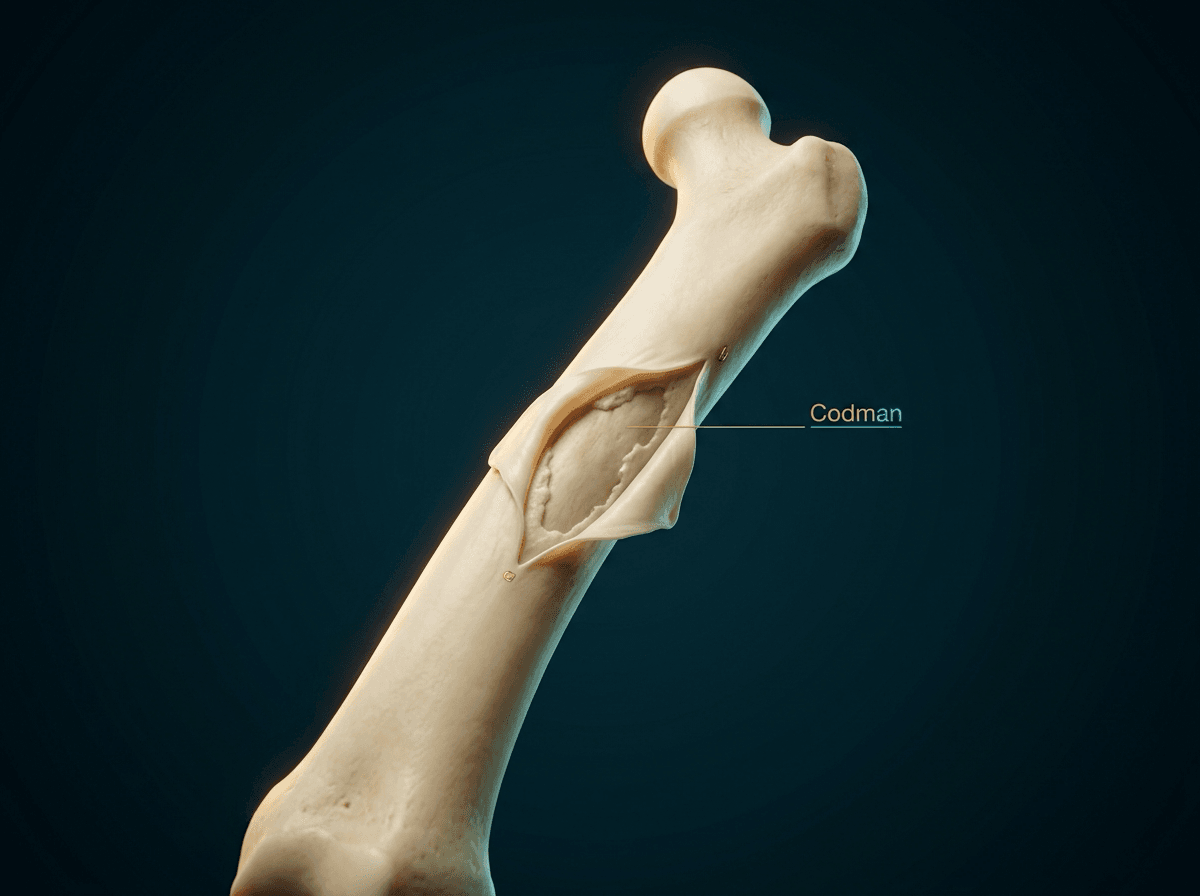
- “Codman triangle is the ossified elevated periosteum at the EDGE of the lesion — the centre has been destroyed.
- “Thick, undulating, asymmetric periostitis of a single long bone in a middle-aged adult: consider venous stasis or chronic osteomyelitis before tumour.
- “Periosteal reaction with a lytic diaphyseal lesion in a child aged 5-15 = Ewing sarcoma until excluded, and osteomyelitis is the great mimic.
Recognising the Pattern
What it is. Periosteum is a bilaminar membrane, and its inner cambium layer contains osteoprogenitor cells. Any process that lifts, irritates or inflames the periosteum triggers osteoid deposition.
Why the first film can be normal. Newly laid osteoid is radiolucent, so periosteal reaction is invisible on plain film for approximately 10-21 days after the insult. That is why the film in an early stress fracture or early osteomyelitis may be normal.
Is it really there? Look for a line of mineralised density lying parallel to the cortex and separated from it by a lucent gap, best appreciated tangentially at the bone margin. Confirm it on the orthogonal view: a genuine reaction persists, while an overlying structure moves. Then describe it: continuous (unbroken along its length) or interrupted, thin or thick, and whether it has an intact outer margin.
The only classification that matters is by aggressiveness, and each pattern carries a rate:
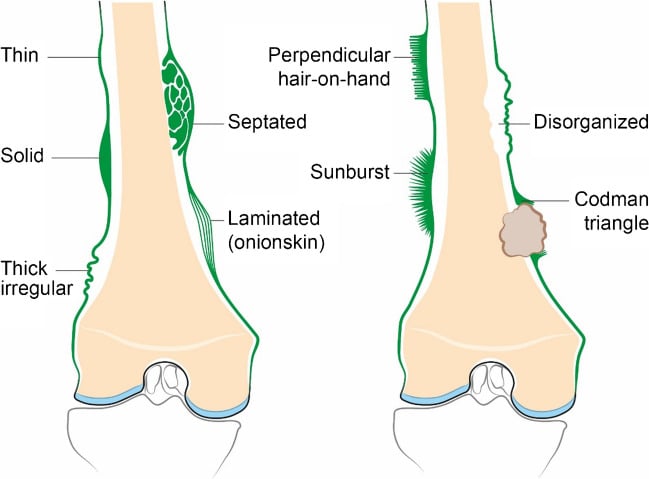
Naming the pattern. Use the descriptive term, then say what it implies:
- Solid — a homogeneous, thick band fused to cortex, from slow processes lasting more than 2 months
- Single lamella or thin shell — one thin line, the earliest visible reaction, and indeterminate at that moment
- Lamellated (onion-skin) — multiple concentric layers, implying repeated cycles of lifting and ossification
- Spiculated perpendicular (hair-on-end) — fine parallel spicules at 90 degrees to cortex, along Sharpey fibres
- Spiculated divergent (sunburst) — spicules radiating from a focal point
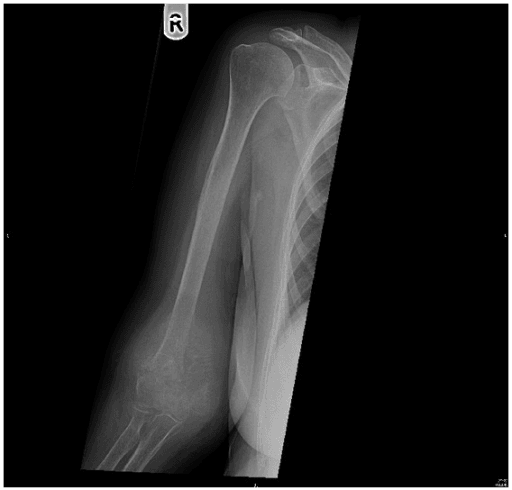
- Codman triangle — an angled cuff of ossified periosteum at the margin of the lesion, the central portion having been destroyed
- Undulating or wavy — thick, irregular and mature, seen in venous stasis, chronic infection and hypertrophic osteoarthropathy
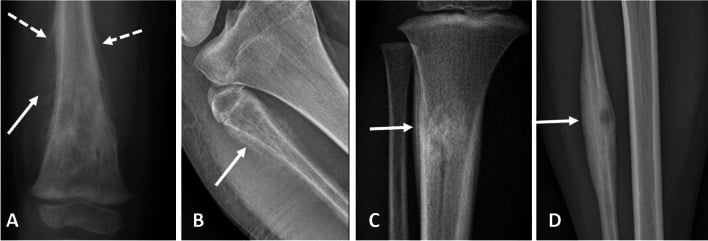
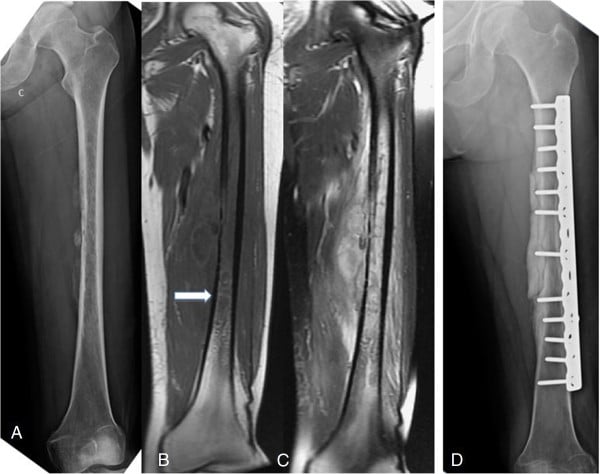
It signals only that periosteum has been lifted faster than it can ossify. Subperiosteal abscess, and subperiosteal haematoma in haemophilia or scurvy, produce identical triangles. Commit to "aggressive", not to a histology.
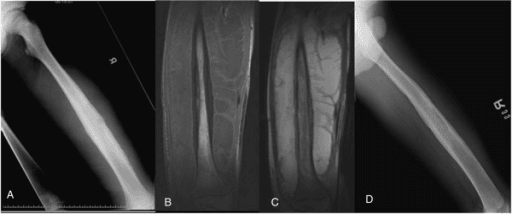
Saying it out loud. Pattern first, then extent and associated findings, then what it means and what you would do: "There is an interrupted, lamellated periosteal reaction along the mid-diaphysis of the femur over approximately 8 cm, with an associated permeative lytic lesion and a soft tissue mass. The pattern indicates an aggressive process; my differential is Ewing sarcoma, osteosarcoma and osteomyelitis, and I would want an MRI of the whole bone and a chest CT."
Mimics. Several things look like periosteal reaction and are not:
- Nutrient foramen or vascular groove — a lucent line, not a dense one, oblique and unicortical
- Cortical striations of hyperparathyroidism — intracortical tunnelling, not a separate outer line
- Overlapping soft tissue folds, skin folds, plaster or dressing edges — cross the bone margin and continue into soft tissue
- Myositis ossificans — mineralisation in the soft tissue, with a lucent cleft from an intact cortex and a mature peripheral rim (zoning)
- Parosteal osteosarcoma — a dense juxtacortical mass with a cleft, not a layered reaction
- Ossifying haematoma or avulsive cortical irregularity at the distal posteromedial femur in adolescents — a benign, self-limiting cortical desmoid
- Periosteal chondroma — cortical saucerisation with a buttress of mature periosteal bone at each end
Next Investigation
Plain films first. Orthogonal films of the whole bone come first, always, and always include both joints. They confirm the reaction is real, define matrix and zone of transition, and may make the diagnosis outright: stress fracture, venous stasis, physiological infantile periostitis. They change management by determining whether anything further is needed at all.
MRI of the whole affected bone, with contrast, is mandatory for every interrupted pattern. It defines marrow extent, skip lesions, soft tissue mass, neurovascular involvement and joint invasion, all of which determine the resection plan, and it distinguishes a rim-enhancing subperiosteal abscess from a solid enhancing tumour mass.
Thin-slice CT of the lesion is for the questions of matrix, cortical integrity, sequestrum or the nidus of an osteoid osteoma. It is superior to MRI for mineralisation, and it does not replace MRI for staging.
Chest radiograph, then CT chest, has two indications: staging any suspected primary bone sarcoma, and finding the lung primary in bilateral symmetrical hypertrophic osteoarthropathy. It changes management by upstaging, or by redirecting the whole workup away from the limb.
Bloods. FBC, CRP, ESR, ALP, LDH, calcium and a myeloma screen separate infection from tumour imperfectly but usefully. Raised ALP and LDH carry prognostic weight in osteosarcoma and Ewing sarcoma, and a myeloma screen is mandatory in any adult over 50 with permeative bone lesions.
Biopsy, at the treating sarcoma centre only. Image-guided core biopsy is taken along the future resection incision, and never before MRI staging is complete. A biopsy tract placed by a non-specialist can convert a limb-salvage case into an amputation.
When no further imaging is needed. These films need nothing further:
- Physiological periostitis of infancy in a well 3-month-old with a normal examination
- Unilateral undulating tibial periostitis in a patient with obvious venous ulceration and lipodermatosclerosis
- A solid fusiform reaction at a known fracture site, healing as expected
The Differential
Where the causes come from. Tumour (osteosarcoma, Ewing sarcoma, metastasis, leukaemia, lymphoma), haemorrhage and haematological disease (subperiosteal haematoma, scurvy, haemophilia, thalassaemia), infection (acute and chronic osteomyelitis, subperiosteal abscess, syphilis) and hypertrophic pulmonary osteoarthropathy, with physiological, pressure and traumatic causes alongside.
- Typical age / setting
- 10-20 years; metaphysis of distal femur, proximal tibia, proximal humerus
- Discriminating feature
- Sunburst or Codman triangle WITH cloud-like mineralised osteoid matrix inside the lesion and in the soft tissue mass
- What confirms it
- MRI whole bone plus biopsy through a planned resection corridor; chest CT for metastases
- Typical age / setting
- 5-20 years; diaphysis of femur, pelvis, ribs
- Discriminating feature
- Lamellated onion-skin reaction with permeative lysis and a soft tissue mass far larger than the bony change; no matrix
- What confirms it
- MRI plus biopsy; EWSR1 rearrangement on molecular testing
- Typical age / setting
- Any age; children under 5 and immunocompromised adults; metaphysis
- Discriminating feature
- Fever, raised CRP, and reaction that becomes MORE organised on serial films over 2-3 weeks; sequestrum or involucrum later
- What confirms it
- MRI with contrast showing rim-enhancing subperiosteal collection; aspiration and culture
- Typical age / setting
- Over 50 years; known primary; axial skeleton, proximal femur, humerus
- Discriminating feature
- Multiple lesions; periosteal reaction is unusual and when present is thin or absent — its ABSENCE with permeative lysis in an older adult points here
- What confirms it
- Bone scan or whole-body imaging, CT chest/abdomen/pelvis, myeloma screen
- Typical age / setting
- Under 2 years
- Discriminating feature
- Periosteal reaction of DIFFERENT ages at multiple sites, with classic metaphyseal lesions and posterior rib fractures
- What confirms it
- Skeletal survey with 11-14 day repeat films; safeguarding referral
- Typical age / setting
- Athletes, military recruits; tibial shaft, second and third metatarsal, femoral neck
- Discriminating feature
- Focal, fusiform, solid reaction centred on a cortical lucency; pain reproducible at one point and relieved by rest
- What confirms it
- Repeat film at 2-3 weeks, or MRI showing periosteal and marrow oedema with a hypointense fracture line
- Typical age / setting
- Any age; tibial metaphysis
- Discriminating feature
- Thick undulating solid reaction with cortical thickening and a lucent nidus with a sclerotic rim; night pain relieved variably by NSAIDs
- What confirms it
- MRI showing penumbra sign; CT for sequestrum; culture at curettage
- Typical age / setting
- 10-25 years; femoral neck, tibial diaphysis
- Discriminating feature
- Dense fusiform solid reaction around a lucent nidus of less than 1.5 cm; night pain dramatically relieved by NSAIDs
- What confirms it
- Thin-slice CT to demonstrate the nidus; treated by radiofrequency ablation
- Typical age / setting
- Over 50 years; smokers, bronchial carcinoma, cyanotic heart disease, IBD
- Discriminating feature
- SYMMETRICAL, bilateral, smooth or undulating periostitis of distal radius, ulna, tibia and fibula, with clubbing and aching
- What confirms it
- Chest radiograph then CT chest to find the underlying lung lesion
- Typical age / setting
- Over 50 years; chronic oedema, lipodermatosclerosis of the leg
- Discriminating feature
- Irregular undulating periostitis of tibia and fibula only, with soft tissue phleboliths and skin change; painless
- What confirms it
- Clinical appearance plus venous duplex; no biopsy needed
- Typical age / setting
- 5-15 years; skull, femur, vertebra plana
- Discriminating feature
- Lamellated reaction with a well-defined lytic lesion and bevelled edge in skull; can look aggressive but often resolves spontaneously
- What confirms it
- Biopsy: CD1a and langerin positive; skeletal survey for other lesions
- Typical age / setting
- 1-4 months of age
- Discriminating feature
- Symmetrical, single-layer, diaphyseal, sparing metaphyses; child well with no fractures elsewhere
- What confirms it
- No further imaging; reassure and document
- Typical age / setting
- 6 months to 2 years; restricted diet, autism spectrum, neglect
- Discriminating feature
- Subperiosteal haemorrhage with dense metaphyseal white line of Frankel, Wimberger ring, and refusal to weight bear with gum bleeding
- What confirms it
- Serum ascorbate; rapid response to vitamin C within days
- Typical age / setting
- Children; skull vault
- Discriminating feature
- Hair-on-end skull with widened diploe and small maxillary sinuses due to marrow hyperplasia
- What confirms it
- Full blood count, haemoglobin electrophoresis
- Typical age / setting
- Under 6 months
- Discriminating feature
- Massive periosteal new bone of the MANDIBLE and clavicle with soft tissue swelling and irritability; self-limiting
- What confirms it
- Clinical and radiographic; resolves over months without treatment
The infant. Symmetrical, smooth, single-layer periosteal new bone along the femora, tibiae and humeri between roughly 1 and 4 months of age is normal. Labelling it non-accidental injury without metaphyseal corner fractures or rib fractures is a serious error.
Narrowing It Down
Work through the film in this order.
1. Is the reaction continuous or interrupted? Trace the outer margin of the new bone along its whole length before looking at anything else, and ask only whether it is unbroken. Continuous with an intact outer margin means the periosteum kept pace: benign, healed or slow. Interrupted, lamellated, spiculated or a Codman triangle means the lesion outran it: aggressive. This single question sorts the differential into two halves before you consider age or site.
2. Is it solitary or multifocal, unilateral or symmetrical? Look at the opposite limb and at any other available films, and ask specifically whether lesions are of the same age or different ages.
Symmetrical bilateral periostitis of the distal long bones in an adult means hypertrophic osteoarthropathy, so image the chest, not the leg; symmetrical diaphyseal periostitis in a 2-month-old is physiological. Multiple lesions of different ages in an infant mean non-accidental injury, and multiple lesions in an adult over 50 mean metastasis or myeloma.
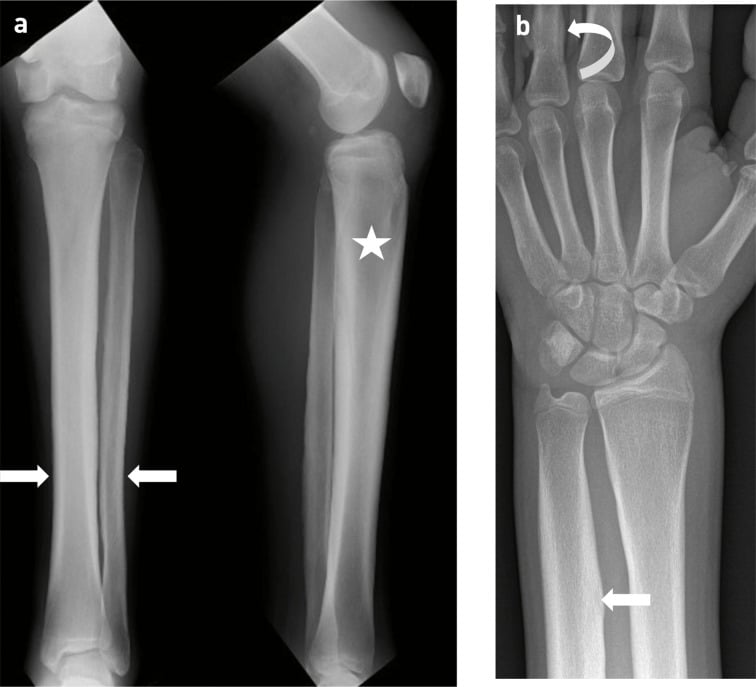
3. Where in the bone is it, and how old is the patient? Name the segment (epiphysis, metaphysis, diaphysis) and pair it with the decade; do not skip the age. Epiphyseal lesions rarely produce periosteal reaction at all.
- Metaphysis, aged 10-20, aggressive reaction: osteosarcoma
- Diaphysis, aged 5-20, onion-skin: Ewing sarcoma or osteomyelitis
- Metaphysis, under 5, with fever: acute osteomyelitis
- Diaphysis, over 40, with cortical destruction: metastasis or lymphoma
4. Is there matrix, and what kind? Look inside the lesion and inside any soft tissue mass for mineralisation, and classify it as osteoid, chondroid or absent, with CT if the plain film is equivocal. Fluffy, cloud-like amorphous mineralisation extending into the soft tissue mass is osteoid, and means osteosarcoma. Rings-and-arcs or popcorn calcification is chondroid, and means chondrosarcoma, which classically causes endosteal scalloping greater than two-thirds of cortical thickness rather than florid periostitis. No matrix with permeative lysis favours Ewing sarcoma, lymphoma or infection.
5. Is there a soft tissue mass, and is it out of proportion? Compare the size of the soft tissue component with the amount of bone destruction, and look for a rim-enhancing collection tracking beneath the periosteum. A large mass with relatively modest bone destruction is characteristic of Ewing sarcoma and lymphoma of bone. A rim-enhancing subperiosteal collection with adjacent muscle oedema is a subperiosteal abscess, and no mass at all with a fusiform solid reaction favours stress fracture or osteoid osteoma.
The mass, not the spicules. A spiculated reaction with no soft tissue mass is far less worrying than the same reaction with a large mineralised mass. The mass drives the diagnosis and the biopsy.
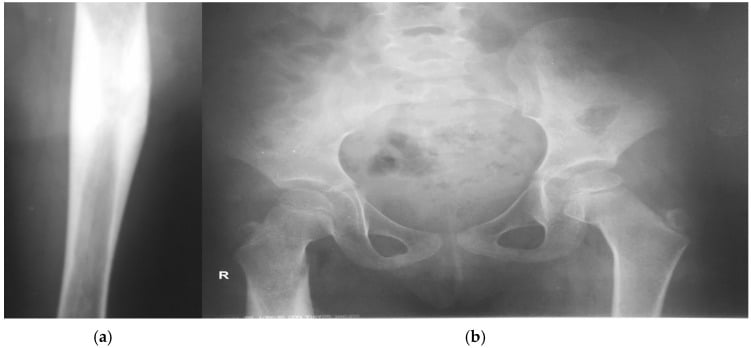
6. What are the systemic and biochemical features? Take the temperature, send CRP, white cell count and ESR, examine for clubbing, and ask directly about night pain, weight loss, smoking and diet. Fever with a raised CRP and white cell count points to infection, but Ewing sarcoma produces fever and a raised ESR and is the classic mimic, so this finding narrows nothing on its own. Clubbing means hypertrophic osteoarthropathy, bleeding gums and dietary restriction in a toddler mean scurvy, and night pain abolished by aspirin means osteoid osteoma.
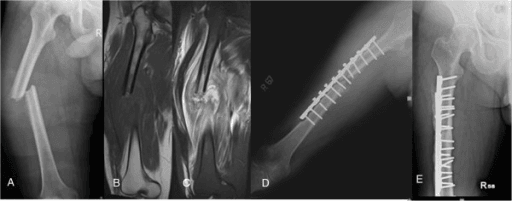
7. What did it look like before, and what does it look like now? Serial films are the most underrated discriminator. Find the old films; if there are none, take a new one at a defined interval rather than guessing, and 2 to 3 weeks is enough to answer the question. An aggressive pattern that consolidates over 3-6 weeks on antibiotics was infection, a pattern that progresses despite treatment is tumour, and any reaction that changes appreciably over 2 weeks is by definition an active, rapid process.
Healing changes the pattern. An aggressive lamellated reaction that is treated, with antibiotics, chemotherapy or rest, consolidates into a solid shell. A solid reaction on a single film may be an aggressive lesion caught late, so always ask for the old films.
MCQ Practice Points
Q: What determines the pattern of periosteal reaction?
A: The RATE of the underlying process, not its nature. Slow insults allow continuous solid new bone; rapid insults produce lamellated, spiculated or interrupted patterns because the periosteum is lifted faster than it can ossify. Ragsdale put it as the configuration being "an index of the nature and intensity of the inciting process" — and where demand outstrips the periosteum, extraperiosteal soft tissue supplies additional cells, exactly as it does for fracture callus.
Q: Why can a plain film be normal in early osteomyelitis or stress fracture?
A: New osteoid is unmineralised and therefore radiolucent, so periosteal reaction is not radiographically visible for roughly 10 to 21 days after the insult. Wenaden makes the same point from the other side: the reaction is demonstrable on ultrasound, CT, MRI and scintigraphy BEFORE it mineralises. MRI detects marrow and periosteal oedema within 24 to 48 hours and is the investigation of choice when early diagnosis matters.
Q: Which single radiographic feature best distinguishes osteosarcoma from Ewing sarcoma?
A: Mineralised osteoid matrix — cloud-like amorphous density within the lesion and within the soft tissue mass — is present in osteosarcoma and absent in Ewing sarcoma. Site also helps: metaphyseal for osteosarcoma, diaphyseal for Ewing. Note what does NOT separate them: the periosteal pattern itself, since both produce lamellated and spiculated reactions and both produce Codman triangles.
Q: A 3-month-old has symmetrical single-layer periosteal reaction along both femoral and tibial diaphyses and is thriving. Next step?
A: No further imaging. This is physiological periostitis of infancy. Non-accidental injury requires reactions of DIFFERING AGES, classic metaphyseal lesions or posterior rib fractures — symmetry and a single layer in a thriving baby are the reassuring combination.
Q: Which juxtacortical mineralisation is NOT periosteal reaction, and how is it recognised?
A: Myositis ossificans. The mineralisation lies in soft tissue, is separated from an intact cortex by a lucent cleft, and matures from the PERIPHERY INWARDS (the zoning phenomenon) — the reverse of a surface sarcoma, which mineralises centrally. Get the direction of maturation the wrong way round and a benign lesion becomes a sarcoma referral.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are shown this radiograph of the left femur of a 13-year-old boy with 6 weeks of thigh pain, a low-grade fever and an ESR of 60. There is a permeative lytic lesion of the mid-diaphysis with a multilayered lamellated periosteal reaction and a large soft tissue mass.”
“You are shown this radiograph of the knee of a 16-year-old girl with 3 months of pain and a firm swelling. There is a mixed lytic and sclerotic metaphyseal lesion with cloud-like density extending into the soft tissues and a triangular cuff of ossified periosteum at the proximal margin.”
“You are shown radiographs of both lower legs in a 62-year-old smoker with aching ankles and wrists. There is smooth, undulating periosteal new bone along the distal tibiae and fibulae bilaterally, sparing the epiphyses. He has finger clubbing.”
Benign / slow patterns
- Solid thick continuous — chronic osteomyelitis, healed fracture, osteoid osteoma, venous stasis
- Single thin lamella — earliest reaction; indeterminate, repeat in 2-3 weeks
- Undulating thick — venous stasis, hypertrophic osteoarthropathy, chronic infection
- Buttress at lesion margin — slow-growing surface lesion such as periosteal chondroma
Aggressive / fast patterns
- Lamellated onion-skin — Ewing sarcoma, osteomyelitis, LCH, osteosarcoma
- Spiculated hair-on-end — thalassaemia skull, Ewing sarcoma, syphilis
- Sunburst divergent — osteosarcoma first; also metastases and skull meningioma
- Codman triangle — osteosarcoma, Ewing sarcoma, subperiosteal abscess, subperiosteal haematoma
Age-anchored shortcuts
- Under 6 months symmetrical diaphyseal — physiological or Caffey disease (mandible)
- 6 months to 2 years with bleeding gums — scurvy
- Under 2 years, reactions of different ages — non-accidental injury
- 5-20 years diaphysis, onion-skin — Ewing sarcoma versus osteomyelitis
- 10-20 years metaphysis with osteoid matrix — osteosarcoma
- Over 50 years, symmetrical distal long bones, clubbing — hypertrophic osteoarthropathy
- Over 50 years, permeative, multiple — metastasis, myeloma, lymphoma
Investigation rules
- Orthogonal films of the whole bone including both joints, always first
- Any interrupted pattern — whole-bone MRI with contrast plus chest CT
- Matrix, sequestrum or nidus questions — thin-slice CT
- Bilateral symmetrical periostitis — image the chest, not the limb
- Biopsy only at the sarcoma centre, along the planned resection corridor
- No further imaging: infantile physiological periostitis, venous stasis with typical skin change, expected fracture healing
Viva phrases that score
- 'Continuous and uninterrupted — the periosteum kept pace, so this is slow'
- 'Interrupted — the lesion outran the periosteum, so this is aggressive'
- 'The Codman triangle tells me rate, the matrix tells me histology'
- 'The soft tissue mass is disproportionate to the bone destruction'
- 'I would like the previous films — change over time is my best discriminator'
Evidence Base
Radiologic and Pathologic Analysis of Solitary Bone Lesions. Part II: Periosteal Reactions
- The foundational radiologic-pathologic correlation of periosteal reaction, from the Armed Forces Institute of Pathology series
- States the governing principle in the authors' own words: THE CONFIGURATION OF A PERIOSTEAL REACTION IS AN INDEX OF THE NATURE AND INTENSITY OF THE INCITING PROCESS
- Describes the periosteum as having 'a deceptive anatomic constancy amidst change' - the layer looks the same while its cell population is being spent producing matrix
- Where the demand exceeds what the periosteum can supply, nearby EXTRAPERIOSTEAL SOFT TISSUE recruits additional modulating cells, exactly as it does for fracture callus
Imaging of Periosteal Reactions Associated with Focal Lesions of Bone
- Pictorial review from a national orthopaedic oncology centre, covering the patterns of periosteal reaction with particular reference to bone tumours
- States plainly that periosteal reaction is manifest in a LIMITED NUMBER of histological and radiological patterns - the periosteum has few ways of responding to many insults
- THE KEY SENTENCE FOR THIS PAGE: periosteal reaction is 'not specific for a particular diagnosis', but its appearance aids radiological characterisation of the lesion
- Once ossified, periosteal reaction is shown well on plain radiography - but it can be seen EARLIER on ultrasound, CT, MRI and scintigraphy, before it mineralises
Periosteal Reaction
- The widely used modern classification review, organising periosteal reaction by radiographic morphology rather than by disease
- Divides reactions into CONTINUOUS and INTERRUPTED, then subdivides continuous reactions by whether the underlying cortex is destroyed
- Groups the aggressive interrupted forms - lamellated, spiculated (hair-on-end and sunburst) and the Codman triangle - as expressions of a process outpacing the periosteum
- Presents the differential for each pattern as a LIST rather than a diagnosis, consistent with the non-specificity established elsewhere
Overview of Periosteal Reaction by Imaging
- Current overview linking the anatomy, histology and physiology of the periosteum to the imaging appearance of its reactions
- Frames the periosteum as a living membrane covering almost all bone that 'attracts little attention unless it reacts excessively'
- Covers the stimuli that provoke reaction and the main underlying conditions, with a radiological-pathological rather than purely descriptive approach
- Written with a pathologist as co-author, keeping the imaging pattern tied to the tissue behaviour that produces it