The Flat Rotator That Guards the Femoral Head's Blood Supply
- Quadratus femoris runs from the lateral border of the ischial tuberosity to the quadrate tubercle on the intertrochanteric crest.
- It is supplied by the nerve to quadratus femoris (L4, L5, S1), which runs deep to the gemelli and obturator internus, against the hip capsule.
- The deep branch of the medial circumflex femoral artery — the dominant supply to the femoral head — runs at the superior border of quadratus femoris, deep to the obturator externus tendon.
- Ischiofemoral impingement is compression of the muscle between the ischial tuberosity and the lesser trochanter; the ischiofemoral space and the quadratus femoris space are the two measurements.
- Preserving obturator externus, and dividing the short external rotators well away from their femoral insertion, protects the femoral head blood supply.
- “The nerve to quadratus femoris also supplies the inferior gemellus and gives an articular branch to the hip joint — a source of referred hip pain.
- “Obturator externus, not piriformis, is the true protector of the medial circumflex femoral artery deep branch.
- “Meta-analysis gives working MRI cutoffs of an ischiofemoral space of 15 mm or less and a quadratus femoris space of 10 mm or less, each with sensitivity and specificity below about 80 per cent.
- “Posterior soft tissue repair after total hip arthroplasty cuts the dislocation risk about EIGHTFOLD (relative risk 8.21 without repair, 95 per cent CI 4.05 to 16.67; pooled rates 0.49 versus 4.46 per cent) - but the structures repaired in those series are the piriformis, conjoint tendon and capsule, NOT quadratus femoris, which is usually left intact.
Overview
Quadratus femoris is the lowest and the most substantial of the short external rotators of the hip. Unlike the tendinous piriformis and the conjoint tendon of the gemelli and obturator internus, it is a flat, quadrangular, almost entirely muscular structure bridging horizontally from the ischium to the back of the proximal femur.
Its own action is unremarkable and it is functionally expendable. It matters for three reasons, all of them positional.
It marks the vascular danger zone. The deep branch of the medial circumflex femoral artery (MFCA), which supplies almost the entire femoral head in the adult, runs at the superior border of quadratus femoris before turning to enter the femoral neck. A release of the short external rotators taken flush against the femur, or a dissection carried too far superiorly across the quadratus, can divide it.
It occupies a corridor that can close. The muscle passes through the narrow gap between the ischial tuberosity and the lesser trochanter. Narrowing of that gap produces ischiofemoral impingement, a genuine and under-recognised cause of deep buttock and groin pain.
It sits at the lower edge of the posterior soft tissue sleeve. It is not, though, the structure the dislocation evidence is about. What those series actually repaired is set out under the posterior approach below, and it is not this muscle.
Attachments, Innervation and Relations
Attachments
Origin. Quadratus femoris arises from the upper part of the lateral border of the ischial tuberosity, on its lateral (external) aspect, just anterior and superior to the hamstring origin. The origin is short, flat and muscular, roughly 2-3 cm in vertical height. Because it lies anterosuperior to the semimembranosus and conjoint hamstring footprints, it is the muscle encountered above the tuberosity as a proximal hamstring repair is carried proximally.
Insertion. It inserts on the quadrate tubercle, which sits roughly at the midpoint of the intertrochanteric crest between the greater trochanter above and the lesser trochanter below, and on the bone immediately below it, extending distally onto the proximal shaft for a few centimetres. The fibres run transversely and slightly downward from ischium to femur, the most horizontal of all the short external rotators.
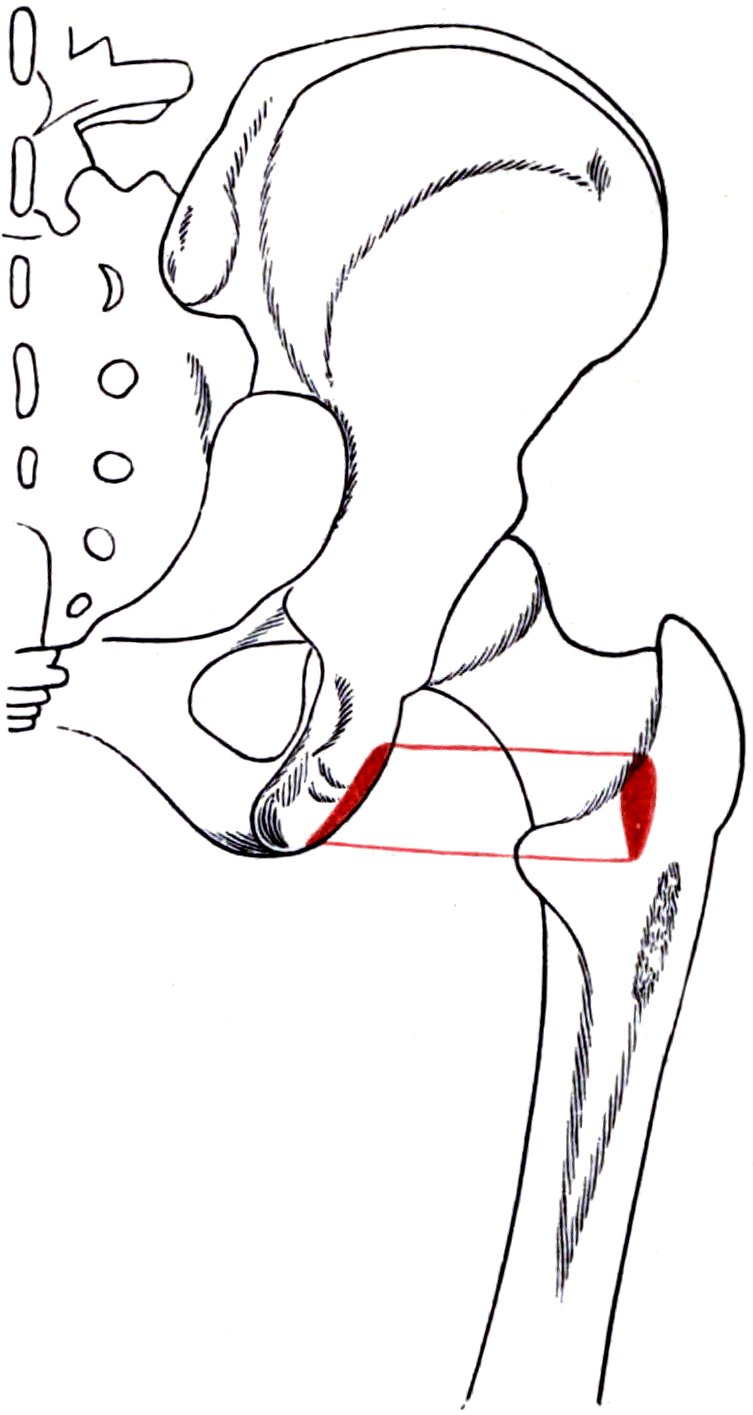
Shape. A flat, quadrangular sheet a few centimetres in each dimension and around a centimetre thick, it is the bulkiest of the short external rotators. It is also the only one that is purely muscular at its femoral end; the others insert as tendons on or near the greater trochanter. The practical consequence is that a quadratus femoris release bleeds and does not hold a suture well, so it is often left alone or repaired only loosely.
Innervation
The nerve to quadratus femoris. Its roots are L4, L5 and S1, from the anterior divisions of the sacral plexus, and it arises from the anterior surface of the plexus. Besides quadratus femoris it supplies the inferior gemellus and gives an articular branch to the hip joint.
The deep route. The nerve leaves the pelvis through the greater sciatic foramen below piriformis, lying anterior (deep) to the sciatic nerve. It passes deep to the tendons of obturator internus and the gemelli, directly against the posterior hip capsule, and descends on the capsule to enter the deep (anterior) surface of quadratus femoris.
Why the route matters. The nerve is not encountered when the rotators are reflected posteriorly in a standard posterior approach, because it lies on the far side of them. It is at risk when the capsule itself is dissected, in deep gluteal space surgery, and in fixation of posterior column and posterior wall acetabular fractures.
The articular branch. The branch to the hip joint is Hilton's law in action: the nerve supplying a muscle acting across a joint also supplies the joint and the overlying skin. It is one anatomical route by which hip joint pathology refers pain to the posterior buttock and the posteromedial thigh, and part of the explanation for the deep, hard-to-localise buttock pain of ischiofemoral impingement.
The whole group. From superior to inferior the short external rotators run P-GO-GO-Q: piriformis, the landmark for the sciatic nerve; superior gemellus; obturator internus, the middle of the triceps coxae; inferior gemellus; obturator externus; and quadratus femoris. Obturator externus is out of sequence: it lies deep and its tendon crosses beneath the conjoint tendon, which is exactly why it shields the MFCA. Their nerve supply is the exam table.
- Nerve
- Nerve to piriformis
- Roots
- S1, S2
- Note
- Direct branches from the sacral plexus
- Nerve
- Nerve to obturator internus
- Roots
- L5, S1
- Note
- Shares its nerve with obturator internus
- Nerve
- Nerve to obturator internus
- Roots
- L5, S1
- Note
- The nerve crosses the ischial spine lateral to the pudendal nerve
- Nerve
- Nerve to quadratus femoris
- Roots
- L4, L5, S1
- Note
- Shares its nerve with quadratus femoris
- Nerve
- Posterior division of obturator nerve
- Roots
- L3, L4
- Note
- The only one from the lumbar plexus, not the sacral plexus
- Nerve
- Nerve to quadratus femoris
- Roots
- L4, L5, S1
- Note
- Plus an articular branch to the hip joint
Blood Supply
Supply to the muscle. The MFCA is the dominant supply, through muscular branches from its deep and transverse branches. The inferior gluteal artery supplies the proximal (ischial) part and the first perforating branch of the profunda femoris the distal and inferior part.
The cruciate anastomosis. These three vessels, with the lateral circumflex femoral artery, form the cruciate anastomosis at the level of the lower border of quadratus femoris. It is a named collateral pathway that becomes clinically important when the femoral artery is occluded, and a source of substantial and surprising bleeding during subtrochanteric surgery.
The femoral head. Every question about releasing the short external rotators is, underneath, a question about the femoral head's blood supply. The dominant supply to the adult femoral head is the deep branch of the MFCA, via the lateral epiphyseal (superior retinacular) arteries; the lateral circumflex femoral artery and the artery of the ligamentum teres are minor contributors in adults.
Course of the MFCA. It arises from the profunda femoris in most limbs and directly from the common femoral artery in a substantial minority. It passes between pectineus and iliopsoas, then between iliopsoas and obturator externus, to reach the posterior aspect of the hip. The deep branch runs along the inferior border of obturator externus, crosses posterior to the obturator externus tendon, and passes anterior to the tendons of the superior gemellus, obturator internus and piriformis before ascending on the posterosuperior femoral neck beneath the synovial reflection as the retinacular vessels.
The critical relationship. The deep branch is deep (anterior) to the obturator externus tendon and superficial (posterior) to the conjoint tendon. Dividing piriformis, obturator internus and the gemelli is therefore safe for the artery provided obturator externus is preserved, while dividing obturator externus exposes the artery directly and is the single most dangerous release.
Where quadratus femoris fits. The deep branch lies at and just above the superior border of the muscle, so quadratus femoris is the inferior boundary of the danger zone. A release of quadratus femoris carried superiorly along the femur approaches the artery from below, and a release taken flush against the intertrochanteric crest can divide the ascending terminal branches. Release it from the middle of the muscle, not from bone, if release is required at all.
The trochanteric anastomosis. The MFCA, the lateral circumflex femoral artery and the superior and inferior gluteal arteries form it on the posterior aspect of the greater trochanter. Dividing the short external rotators away from the femur, leaving a cuff of tendon on the bone, leaves this anastomosis and the terminal MFCA branches undisturbed.
Bleeding at the superior border. Brisk bleeding when working at the superior border of quadratus femoris, or from the intertrochanteric crest, is a warning, not a nuisance. It usually means the deep branch or one of its terminal branches has been injured, and it should be assumed to be from them. Do not blindly diathermy or clip deep in this interval: pack, obtain exposure and control the vessel under direct vision, because blind cautery in this corridor is a described mechanism of avoidable osteonecrosis.
Relations
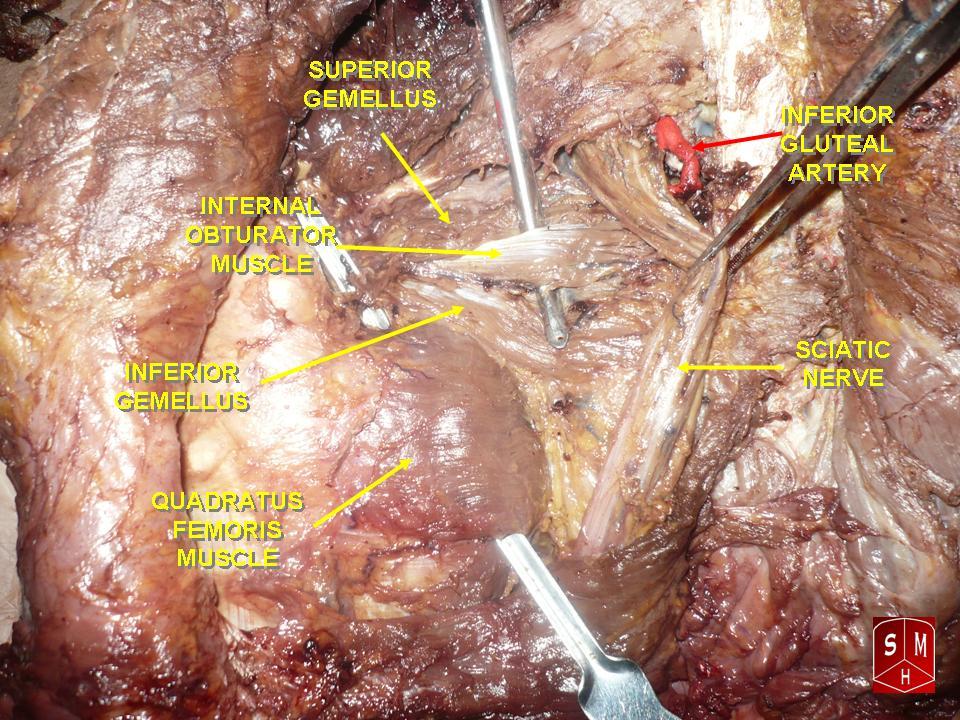
Superficial (posterior). Gluteus maximus and its tendon lie over the muscle with the ischial bursa. The sciatic nerve crosses the posterior surface of quadratus femoris as it descends into the thigh, and that is the reliable landmark: the nerve is superficial to quadratus femoris and the other short rotators, and deep to gluteus maximus. The posterior femoral cutaneous nerve is more superficial and medial, and the inferior gluteal artery and nerve lie at the superomedial corner of the field.
Deep (anterior). The obturator externus tendon crosses the neck of the femur, with the posterior hip capsule and the lesser trochanter, and the nerve to quadratus femoris lies on the capsule. The muscle passes through the ischiofemoral corridor, the gap between the lateral cortex of the ischial tuberosity and the medial cortex of the lesser trochanter.
Superior border. Above lies the inferior gemellus, then obturator internus, superior gemellus and piriformis in ascending order. The superior border is separated from the inferior gemellus and the obturator externus tendon by a fat-filled interval containing the deep branch of the MFCA, and this interval is the anatomical key to the whole page.
Inferior border. Below lies adductor magnus (the hamstring part), separated by a similar interval containing the first perforating branch of the profunda femoris and the terminal (transverse) branch of the MFCA, which anastomose in the cruciate anastomosis.
- Preserve the obturator externus tendon. It is the structure that shields the deep branch of the MFCA.
- Divide away from the femoral insertion, leaving a cuff of tendon on bone. Stripping flush strips the trochanteric anastomosis and the terminal MFCA branches with it.
- Do not strip quadratus femoris off the intertrochanteric crest. If it must be released, divide it in its substance, leaving a cuff on the femur.
- Tag the tendons before dividing them. They retract medially and are difficult to find again for the repair, and it is the repair that reduces dislocation.
- Keep the hip in extension and neutral rotation while working superiorly; internal rotation tensions the rotators and pulls the artery closer to the field.
Action and Biomechanics
Actions. The primary action is external rotation of the extended hip. Quadratus femoris is the most powerful of the short external rotators by cross-sectional area, and its horizontal fibre orientation gives it the most efficient rotational moment arm. Its line of pull is directed medially as well as posteriorly, so it also adducts the hip.
The rotator cuff of the hip. With the other short rotators it forms a posterior dynamic sleeve that compresses the head into the acetabulum and resists posterior translation. The group is frequently described as the rotator cuff of the hip: small, deep, dynamically stabilising muscles inserting close to the joint, deep to a large superficial mover in gluteus maximus, the hip's deltoid. In this force couple the deep rotators compress and centre the head while gluteus maximus and the abductors generate gross movement.
The effect of flexion. In extension the short external rotators, quadratus femoris included, are efficient external rotators. As the hip flexes past about 60-70 degrees, the line of pull of piriformis and the obturator group changes so that they become internal rotators and abductors. Quadratus femoris, being the most horizontal and the most distal, retains its external rotation function longest.
Clinical use of the flexion effect. This is the basis for testing the deep rotators in flexion, in the seated internal rotation and FAIR position tests, and part of why piriformis syndrome is provoked by flexion, adduction and internal rotation.
Consequences of loss. Isolated quadratus femoris loss is functionally silent: external rotation is preserved by gluteus maximus, the remaining rotators and, in extension, the posterior fibres of gluteus medius. Loss of the whole posterior sleeve, as in an unrepaired posterior approach, removes both the passive tether and the dynamic compressive contribution. It produces a measurable increase in the risk of posterior dislocation after arthroplasty and a subjective sense of instability in deep flexion.
On MRI. Fatty infiltration and atrophy of quadratus femoris is the imaging endpoint of chronic ischiofemoral impingement and of chronic denervation.
Surface Anatomy and Examination
Palpation. Quadratus femoris is not directly palpable in most patients, since it lies deep to gluteus maximus and the sciatic nerve. Deep palpation with the patient prone and the hip in slight external rotation, pressing in the interval between the ischial tuberosity and the greater trochanter roughly at the level of the mid intertrochanteric crest, may elicit focal tenderness in ischiofemoral impingement. It is a crude sign.
The bony landmarks. The landmarks that define the corridor are palpable: the ischial tuberosity medially and the greater trochanter laterally, with the lesser trochanter deep and anteromedial to the latter.
Named Clinical Tests
- How to perform
- Patient walks with deliberately long strides, then with short strides
- Positive finding
- Deep buttock pain reproduced with long strides and abolished with short strides
- What it means
- Ischiofemoral impingement — the long stride extends and adducts the hip, narrowing the corridor
- False positives
- Proximal hamstring tendinopathy; lumbar facet pain
- How to perform
- Side-lying or supine; the hip is passively extended in adduction, then repeated in abduction
- Positive finding
- Pain in extension with adduction, relieved by abduction
- What it means
- Narrowing of the ischiofemoral corridor
- False positives
- Hip osteoarthritis; deep gluteal syndrome
- How to perform
- Seated with hips and knees at 90 degrees, resisted external rotation
- Positive finding
- Weakness or pain
- What it means
- Short external rotator involvement, though poorly specific to quadratus femoris
- False positives
- Gluteal tendinopathy; pain inhibition
- How to perform
- Side-lying, hip flexed 60 degrees, then adducted and internally rotated
- Positive finding
- Reproduction of deep buttock pain with or without radiation
- What it means
- Deep gluteal syndrome, classically piriformis-related sciatic irritation
- False positives
- Any posterior hip pathology; lumbar radiculopathy
- How to perform
- Side-lying, patient actively abducts and externally rotates against resistance with the heel pressed into the couch
- Positive finding
- Deep buttock pain
- What it means
- Piriformis-related deep gluteal syndrome
- False positives
- Gluteal tendinopathy; sacroiliac pain
- How to perform
- Ultrasound- or CT-guided local anaesthetic into the quadratus femoris space
- Positive finding
- Substantial temporary relief of the presenting pain
- What it means
- Confirms the quadratus femoris space as the pain generator
- False positives
- Anaesthetic spread to the sciatic nerve or hamstring origin
Interpretation. No isolated grading system exists for quadratus femoris, because it cannot be isolated clinically; external rotation strength is graded 0-5 as a group. The diagnostic weight sits with imaging plus a response to injection, not with a physical sign. It is worth saying explicitly in a viva that ischiofemoral impingement is a clinical-radiological diagnosis confirmed by a diagnostic block, because the clinical tests are sensitive but not specific.
Differential Diagnosis of Deep Posterior Hip Pain
- Key discriminator
- Pain with long strides, relieved by shortening the stride
- Confirmatory finding
- Quadratus femoris oedema with narrowed ischiofemoral and quadratus femoris spaces on MRI
- Key discriminator
- Pain on sitting on hard surfaces, tender exactly on the tuberosity
- Confirmatory finding
- High signal at the conjoint origin on MRI; positive bent-knee stretch test
- Key discriminator
- Radiating sciatic-type pain, positive FAIR and active piriformis tests
- Confirmatory finding
- Sciatic nerve signal change or entrapment on MR neurography
- Key discriminator
- Lateral, not posterior; tender over the greater trochanter; positive single-leg stance
- Confirmatory finding
- Gluteus medius and minimus tendon signal change at the trochanter
- Key discriminator
- Dermatomal distribution, positive straight-leg raise, neurological signs
- Confirmatory finding
- Concordant lumbar MRI findings
- Key discriminator
- Groin pain, C-sign, restricted internal rotation in flexion
- Confirmatory finding
- Radiographic joint space loss or cam/pincer morphology
- Key discriminator
- Acute sprinting or hurdling injury in a skeletally immature patient
- Confirmatory finding
- Radiographic apophyseal separation
Complications
Vascular. Femoral head osteonecrosis follows injury to the deep branch of the MFCA, as described under Clinical Relevance. Uncontrolled bleeding from the cruciate anastomosis at the inferior border of the muscle arises particularly when a posterior approach is extended distally. An injured inferior gluteal artery retracts into the pelvis, and control requires exposure, not blind clamping.
Sciatic nerve. The sciatic nerve, superficial to quadratus femoris, is the most commonly injured structure in the posterior approach, and its injury is the commonest neurological complication of that approach. The mechanisms are direct injury during rotator release, retractor placement, traction during lengthening, and thermal injury from cement or diathermy. The peroneal division is more vulnerable because of its more lateral position, larger fascicles and fewer protective connective tissue elements.
Other nerves. The nerve to quadratus femoris may be injured during capsular dissection or posterior column fixation, producing the selective denervation pattern described above. The pudendal nerve is injured by medial dissection at the ischial spine or by traction on a perineal post.
The impingement corridor. After lesser trochanter resection, a subtrochanteric fracture is the most feared complication of the operation. Iliopsoas weakness follows if the lesser trochanter and the iliopsoas insertion are wholly resected, usually well tolerated in adults but relevant in high-demand patients. Pain persists when the diagnosis was made on measurements rather than a concordant clinical picture, and recurs if the underlying structural cause (offset, version, valgus) is not addressed.
After the posterior approach. Beyond dislocation, heterotopic ossification forms in the split gluteus maximus and the rotator bed, and suture knots and drill holes can cause trochanteric bursitis and pain. Abductor deficiency is not a feature of the posterior approach but of the lateral (Hardinge) approach, a classic examination discriminator.
- Mechanism
- Division of the MFCA deep branch or its terminal branches
- Prevention
- Preserve obturator externus; divide away from the femur, not flush; no blind cautery
- Mechanism
- Retraction, direct injury, traction from lengthening, thermal injury
- Prevention
- Keep hip extended and knee flexed; reflect the rotator sleeve over the nerve; limit lengthening
- Mechanism
- Unrepaired posterior capsule and rotators, component malposition
- Prevention
- Formal transosseous posterior repair; correct component version and offset
- Mechanism
- Over-resection of the lesser trochanter creating a stress riser
- Prevention
- Limited resection with rounded edges; protected weight-bearing
- Mechanism
- Operating on a measurement rather than a diagnosis
- Prevention
- Require muscle oedema and a positive diagnostic injection before surgery
- Mechanism
- Blind dissection or cautery in the interval above quadratus femoris
- Prevention
- Expose, pack, then control under direct vision
Clinical Relevance
Ischiofemoral Impingement
Definition. Ischiofemoral impingement is entrapment of the quadratus femoris muscle within the narrowed corridor between the ischial tuberosity and the lesser trochanter. The corridor narrows with hip extension, adduction and external rotation, which is precisely the position of terminal stance in gait and the reason the pain is described as occurring with long strides.
Who gets it. It is more common in women, attributed to a wider bi-ischial distance and a more medially oriented femoral neck. The corridor is also narrowed by:
- Anatomical variation: a wide bi-ischial distance, a prominent or medially placed lesser trochanter, or coxa valga
- Acquired change: previous proximal femoral osteotomy, hip arthroplasty with excessive offset or version change, ischial or subtrochanteric non-union, or tumour
- Functional causes: hip instability with compensatory external rotation
Presentation. The pain is deep, poorly localised and in the buttock, sometimes radiating to the groin or down the posterior thigh. It is worse with long strides, hip extension and adduction, and relieved by shortening the stride; a snapping or clunking sensation is described in a minority. It is bilateral in a substantial proportion, and frequently misattributed to lumbar spine disease for years before diagnosis.
Imaging. Axial MRI is the diagnostic study, and it provides two measurements.
- Ischiofemoral space (IFS): the narrowest distance between the lateral cortex of the ischial tuberosity and the medial cortex of the lesser trochanter. Reported as roughly 23 mm in controls and about 13 mm in symptomatic patients.
- Quadratus femoris space (QFS): the narrowest space available to the muscle itself, between the superolateral surface of the hamstring tendons and the posteromedial surface of the iliopsoas tendon or the lesser trochanter. Reported as roughly 12 mm in controls and about 7 mm in symptomatic patients.
- Working thresholds from meta-analysis: an IFS of 15 mm or less (sensitivity 76.9 per cent, specificity 81.0 per cent) and a QFS of 10 mm or less (sensitivity 78.7 per cent, specificity 74.1 per cent) support the diagnosis.
What makes the diagnosis. Neither measurement is diagnostic alone: the spaces overlap substantially between symptomatic patients and asymptomatic controls, and narrow spaces occur in asymptomatic people. Oedema in the quadratus femoris muscle on fluid-sensitive sequences is the finding that gives them meaning, progressing in chronic cases to fatty infiltration, partial tearing and atrophy. The measurements support the diagnosis; the muscle oedema and the clinical picture make it.
Diagnose on the combination. A concordant history, muscle oedema on MRI, narrowed spaces and relief from an image-guided diagnostic injection together make the case. Resecting a lesser trochanter on the basis of a measurement alone is how a patient ends up with a subtrochanteric fracture and the same pain.
Positional imaging. Because the corridor narrows with extension and adduction, a neutral supine scan may underestimate the narrowing. Scanning in a functional position, or simply recognising that limitation, improves sensitivity.
After arthroplasty. Ischiofemoral impingement is a recognised and under-diagnosed cause of persistent posterior hip pain after total hip arthroplasty. Increased femoral offset or a change in version can bring the lesser trochanter closer to the ischium, as can a high hip centre or excessive limb lengthening. Investigate with axial CT or MRI with metal-suppression sequences, measuring the ischiofemoral space, plus a diagnostic injection; treat with injection first, and with lesser trochanteric resection or revision to correct offset or version in refractory cases.
Management. The first line is activity modification with deliberate stride shortening, gait retraining, hip abductor and external rotator strengthening, and correction of any compensatory pattern from hip instability or a leg-length difference. The second line is image-guided injection of local anaesthetic, with or without corticosteroid, into the quadratus femoris space. It is both diagnostic and therapeutic, and a good response is the strongest predictor of benefit from surgery.
Surgery for refractory cases. Lesser trochanter resection or partial resection, endoscopic or open, directly widens the corridor; beware the iliopsoas insertion. Quadratus femoris release or debridement is endoscopic, accepting the loss of an expendable muscle. Correcting the underlying deformity, by a valgus or derotation osteotomy or by revising an arthroplasty with excessive offset, is the answer where that is the cause.
- What it does
- Anaesthetises and reduces inflammation in the quadratus femoris space
- Advantages
- Diagnostic and therapeutic; predicts surgical benefit
- Risks
- Temporary; anaesthetic spread to the sciatic nerve causing a transient foot drop
- What it does
- Widens the corridor by removing the lateral wall
- Advantages
- Direct, addresses the mechanical cause, day-case in many units
- Risks
- Subtrochanteric fracture through the defect; iliopsoas weakness; sciatic nerve injury
- What it does
- Removes the impinged tissue rather than widening the corridor
- Advantages
- The muscle is expendable; technically simpler
- Risks
- Does not correct the mechanical cause; bleeding from the MFCA territory
- What it does
- Widens the corridor by removing part of the medial wall
- Advantages
- Preserves the femur
- Risks
- Proximity to the hamstring origin and the sciatic nerve; less commonly performed
- What it does
- Addresses excessive offset, valgus or version abnormality
- Advantages
- Definitive when a clear structural cause exists
- Risks
- Major surgery; must be certain of the cause
Endoscopic access. Endoscopic approaches reach the space through the deep gluteal space with the hip in flexion and internal rotation, which opens the corridor and moves the sciatic nerve away, and they demand meticulous sciatic nerve identification and protection throughout. Endoscopic lesser trochanter resection is performed through a posterior or a modified anterior portal.
Femoral Head Osteonecrosis
Mechanism. Osteonecrosis follows injury to the deep branch of the MFCA or its terminal retinacular vessels. The situations in which it happens:
- Displaced femoral neck fracture, the commonest cause, from the initial injury and from any additional surgical insult
- Surgical hip dislocation performed with division of obturator externus, or with the rotators stripped flush from the femur
- Aggressive posterior capsular and rotator release taken flush against the femur
- Slipped capital femoral epiphysis, particularly after an unmodified open reduction
- Traumatic posterior hip dislocation, where the deep branch may be stretched or thrombosed
Prevention. The Ganz principles apply: preserve obturator externus, avoid dissection on the posterosuperior neck, and use a trochanteric flip osteotomy with the external rotators left intact rather than a posterior rotator release when a full dislocation is required.
In children. The retinacular vessels are the sole supply to the capital epiphysis after the physis closes to transphyseal flow at around 4 years of age and before it fuses, so damage to the deep branch of the MFCA in a child is particularly unforgiving. Slipped capital femoral epiphysis and paediatric femoral neck fracture are the two settings in which this anatomy determines the outcome. Both are reasons the modified Dunn procedure through a surgical hip dislocation is performed with obsessive attention to preserving obturator externus and the posterior rotator sleeve.
Other Pathology
Tear and strain. Isolated quadratus femoris tears are described, usually as a consequence of chronic ischiofemoral impingement rather than an acute event, and an acute strain may follow a forced abduction and external rotation injury. MRI shows muscle oedema and, in complete tears, retraction and a fluid-filled gap. Management is almost always non-operative, because the muscle is expendable.
Denervation. Isolated quadratus femoris denervation produces selective fatty atrophy of quadratus femoris and inferior gemellus, both supplied by the same nerve. The causes are compression in the deep gluteal space, ischiofemoral impingement affecting the nerve as well as the muscle, iatrogenic injury during posterior column fixation or hip arthroplasty, and pelvic tumour. The pattern is a useful clue: selective atrophy of those two with a normal obturator internus and superior gemellus localises the lesion to the nerve to quadratus femoris, not to the whole sacral plexus.
Surgical Relevance
Structures at Risk
- Location relative to a landmark
- At and just above the superior border of quadratus femoris; deep to the obturator externus tendon
- How to protect it
- Preserve obturator externus; divide rotators away from the femur, leaving a cuff on bone
- Location relative to a landmark
- On the intertrochanteric crest at the quadratus femoris insertion
- How to protect it
- Never strip quadratus femoris flush from the crest; divide it in its substance
- Location relative to a landmark
- Crossing the posterior surface of quadratus femoris, deep to gluteus maximus
- How to protect it
- Reflect the divided rotators posteriorly as a protective sleeve; keep the knee flexed and hip extended
- Location relative to a landmark
- On the posterior hip capsule, deep to the gemelli and obturator internus
- How to protect it
- Avoid deep capsular stripping and blind diathermy on the capsule
- Location relative to a landmark
- At the superomedial corner of the field, below piriformis
- How to protect it
- Identify before splitting gluteus maximus deeply; it retracts into the pelvis if torn
- Location relative to a landmark
- At the ischial spine, medial to the nerve to obturator internus
- How to protect it
- Do not dissect medially beyond the ischial spine
- Location relative to a landmark
- At the inferior border of quadratus femoris, in the cruciate anastomosis
- How to protect it
- Anticipate bleeding when extending distally toward the subtrochanteric region
The Posterior Approach
In the posterior (Moore or Southern) approach to the hip, quadratus femoris is the inferior limit of the rotator release, the muscle beneath which the surgeon must not stray. The exposure and the repair run in sequence:
- Position the patient lateral decubitus, secured with pelvic supports.
- Incise centred on the posterior third of the greater trochanter, curving posteriorly and proximally along the fibres of gluteus maximus.
- Split the iliotibial band and the fascia over gluteus maximus in line with the skin incision, then split gluteus maximus bluntly along its fibres, respecting the inferior gluteal neurovascular pedicle entering its deep surface.
- Internally rotate the hip to bring the short external rotators into view, and identify the sciatic nerve on the posterior surface of quadratus femoris.
- Tag piriformis and the conjoint tendon with heavy non-absorbable sutures, then divide them close to but not flush with their insertions, leaving a 1 cm cuff on the femur.
- Reflect the tagged sleeve posteriorly over the sciatic nerve; it protects the nerve for the rest of the case.
- Perform a T-shaped, L-shaped or posterior capsulotomy, tagging the capsule separately at its corners for repair.
- At closure, drill transosseous tunnels in the posterior greater trochanter, or place suture anchors.
- Repair the capsule first, then the rotators, as a single or double layer, with the hip in extension and neutral or slight external rotation.
- Check stability through the arc of flexion, adduction and internal rotation before closing, and document the safe range.
- Repair quadratus femoris loosely if it was released; it holds sutures poorly and a tight repair achieves nothing.
Quadratus femoris in the approach. In most primary arthroplasties it is left intact. It may be partially released for a difficult femoral exposure, for a subtrochanteric osteotomy or in revision, but it should then be released in its substance and never stripped flush from the crest.
The repair evidence. Posterior soft tissue repair is one of the best-supported technical steps in reducing dislocation after a posterior-approach total hip arthroplasty. Kwon's meta-analysis of five directly comparative studies found a relative risk of dislocation 8.21 times higher without repair (95 per cent CI 4.05 to 16.67), with pooled rates of 0.49 per cent with repair against 4.46 per cent without.
Read what was repaired. Those series repair the piriformis, the conjoint tendon and the capsule, transosseously through the greater trochanter. Quadratus femoris is usually left intact, and when it is released it is purely muscular at its femoral end, bleeds, and holds a suture badly. Do not transfer the evidence from one structure to another because they lie in the same sleeve.
Why the repair works. It restores a passive posterior tether, re-establishes the dynamic posterior sleeve, and interposes tissue between the sciatic nerve and the implant.
Piriformis-sparing. The piriformis tendon is preserved and the exposure developed through the interval between piriformis above and the conjoint tendon below, or by dividing only the conjoint tendon. The claimed benefits are preservation of a posterior dynamic restraint and a more anatomical repair.
The viva reality check. The vascular rationale for sparing piriformis is weak: piriformis is superficial to the deep branch of the MFCA, and dividing it does not endanger the artery. If asked why we spare piriformis, the honest answer is soft tissue tension and the quality of the repair, not the femoral head's blood supply. Say this and you separate yourself from the candidate who has learned a slogan.
Obturator externus-sparing is the vascularly meaningful concept, and it is the one that matters in surgical hip dislocation, femoral neck fracture fixation and paediatric hip surgery.
Other Approaches That Involve Quadratus Femoris
Kocher-Langenbeck approach for acetabular fractures. The short external rotators are divided, again preserving obturator externus and leaving a cuff on the femur. Quadratus femoris marks the inferior extent, and the sciatic nerve is protected by keeping the knee flexed and the hip extended.
Surgical hip dislocation (Ganz trochanteric flip). The entire posterior rotator sleeve, including obturator externus, is preserved, and the trochanteric osteotomy is used instead to gain access. This is precisely why the procedure is safe for the femoral head. Of all the ways of dealing with the rotators it is the safest, because they are not divided at all and the artery is shielded by the intact obturator externus.
Deep gluteal space endoscopy. The sciatic nerve is followed from the greater sciatic notch distally, over piriformis and the conjoint tendon, to quadratus femoris, which is the distal landmark of the deep gluteal space.
Guidelines, Registries & Global Practice
Anatomical Variation Across Populations
- The extracapsular course of the deep branch of the medial circumflex femoral artery was constant in all 24 hips in the defining cadaveric study, which is what allows the Ganz principles to be taught as rules rather than as tendencies.
- The origin of the MFCA varies: it arises from the profunda femoris in the majority of limbs but directly from the common femoral artery in a substantial minority. Surgeons approaching the hip anteriorly should expect this variant.
- Ischiofemoral space measurements differ by sex and by population. Reported mean spaces are narrower in women and there is evidence of variation between ethnic groups in bi-ischial width and femoral neck-shaft angle, both of which influence the corridor. This means a single universal threshold is unsafe, and reinforces the need for symptom concordance and muscle oedema before intervening.
- Accessory or bifid quadratus femoris, and fusion of quadratus femoris with the inferior gemellus or adductor magnus, are described variants of no functional significance but occasional confusion at surgery.
Differences in Described Practice
- Position
- Preserve obturator externus absolutely; use a trochanteric flip osteotomy with the external rotators left undivided rather than a posterior rotator release when full dislocation is required.
- Position
- Recognises multiple acceptable approaches; posterior soft tissue repair is standard practice when a posterior approach is used.
- Position
- Posterior approach with formal capsular and short external rotator repair is the most commonly used technique; approach choice is surgeon-dependent.
- Position
- Kocher-Langenbeck approach with rotator release preserving obturator externus and quadratus femoris; sciatic nerve protected by hip extension and knee flexion.
- Position
- Quadratus femoris is the distal landmark of the deep gluteal space; endoscopic lesser trochanter resection for refractory ischiofemoral impingement.
Registry Signals
- National joint registries (the NJR, the AOANJRR, the Swedish and Nordic registries and the AJRR) consistently identify dislocation as a leading indication for early revision after primary total hip arthroplasty, which is the practice argument for a formal posterior repair and for careful component positioning.
- Registry data also show falling dislocation rates over time across all approaches, attributed to a combination of larger femoral head diameters, dual-mobility bearings in high-risk patients, better component positioning and routine posterior soft tissue repair.
- There is no registry for ischiofemoral impingement. The published evidence is imaging case-control studies, small surgical series and systematic reviews of them, and the condition is almost certainly under-diagnosed.
High- and Limited-Resource Practice
- Well-resourced settings: MRI with dedicated axial pelvic sequences and space measurements, image-guided diagnostic injection, endoscopic lesser trochanter resection, and dual-mobility or large-head bearings in patients at high dislocation risk.
- Limited-resource settings: the diagnosis of ischiofemoral impingement can be made clinically on the long-stride history plus a good response to a landmark-guided or ultrasound-guided injection; an open lesser trochanter resection is a straightforward operation where endoscopy is unavailable. For hip arthroplasty, posterior soft tissue repair through transosseous drill holes costs nothing but suture and time and is the highest-value technical step available anywhere in the world.
MCQ Practice Points
Q: Where does quadratus femoris attach? A: From the upper lateral border of the ischial tuberosity to the quadrate tubercle on the intertrochanteric crest. Its fibres run horizontally.
Q: What supplies quadratus femoris? A: The nerve to quadratus femoris, L4, L5, S1, which also supplies the inferior gemellus and gives an articular branch to the hip joint.
Q: Which muscle protects the deep branch of the medial circumflex femoral artery? A: Obturator externus. The deep branch runs posterior to its tendon and anterior to the conjoint and piriformis tendons. Piriformis-sparing does not protect the artery.
Q: Where should the short external rotators be divided, and why? A: Away from the femoral insertion, leaving a cuff of tendon on the bone — this preserves the trochanteric anastomosis and the terminal branches of the medial circumflex femoral artery, and leaves tissue to repair to. Safest of all, as in the Ganz surgical dislocation, is not to divide them at all.
Q: Where is the sciatic nerve relative to quadratus femoris? A: Superficial (posterior) to it. The nerve crosses the posterior surface of the muscle, deep to gluteus maximus. The nerve to quadratus femoris, by contrast, is deep to the rotators, on the capsule.
Q: What are the normal ischiofemoral and quadratus femoris space values? A: In the original case-control study, 23 plus or minus 8 mm and 12 plus or minus 4 mm in controls, falling to 13 plus or minus 5 mm and 7 plus or minus 3 mm in symptomatic patients. Meta-analysis gives working cutoffs of 15 mm and 10 mm, both with accuracy under about 80 per cent, so they are supportive rather than diagnostic.
Q: What hip position narrows the ischiofemoral corridor? A: Extension, adduction and external rotation — terminal stance in a long stride. This is why shortening the stride relieves the pain.
Q: What is the effect of posterior soft tissue repair on dislocation after total hip arthroplasty? A: A substantial reduction — pooled series show a fall from roughly 4 per cent without repair to under 1 per cent with a formal transosseous repair.
Q: Which short external rotator is supplied by the lumbar rather than the sacral plexus? A: Obturator externus, from the posterior division of the obturator nerve, L3-L4.
Q: Which vessels form the cruciate anastomosis? A: The medial and lateral circumflex femoral arteries, the inferior gluteal artery and the first perforating branch of the profunda femoris, at the level of the lower border of quadratus femoris.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are performing a posterior approach for a total hip arthroplasty in a 42-year-old with avascular necrosis. Your trainee asks which short external rotators can be safely divided and why. What do you tell them?”
“A 46-year-old woman has 18 months of deep left buttock pain, worse when she walks with long strides or downhill, and better with short steps. Lumbar MRI and hip radiographs are normal. She has been treated for sciatica without benefit. What is your differential and how do you confirm it?”
“An MRI performed for posterior hip pain shows fatty atrophy confined to the quadratus femoris and inferior gemellus, with normal obturator internus, superior gemellus and piriformis. What does this tell you and what would you do?”
Core Anatomy
- Origin: upper lateral border of the ischial tuberosity
- Insertion: quadrate tubercle on the intertrochanteric crest
- Nerve: nerve to quadratus femoris, L4-S1, plus inferior gemellus and an articular branch
- The lowest and most horizontal short external rotator
Vascular Rules
- MFCA deep branch runs at the superior border of quadratus femoris
- Deep to obturator externus tendon, superficial to the conjoint tendon
- Preserve obturator externus — it is the protector, not piriformis
- Divide rotators away from the femur, leaving a cuff on bone
Ischiofemoral Impingement
- Corridor: lateral ischial tuberosity to medial lesser trochanter
- Narrowed by extension, adduction and external rotation
- IFS about 23 mm normal, about 13 mm symptomatic; cutoff 15 mm or less
- QFS about 12 mm normal, about 7 mm symptomatic; cutoff 10 mm or less
- Quadratus femoris oedema plus a positive block make the diagnosis
Posterior Approach
- Sciatic nerve is superficial to quadratus femoris
- Nerve to quadratus femoris is deep, on the capsule
- Tag rotators before dividing; reflect as a protective sleeve
- Transosseous posterior repair cuts dislocation from about 4 per cent to under 1 per cent
Evidence Base
Anatomy of the Medial Femoral Circumflex Artery and Its Surgical Implications
- 24 cadaver hips dissected after neoprene-latex injection of the femoral or internal iliac arteries
- The extracapsular course of the deep branch of the medial femoral circumflex artery was constant, with a trochanteric branch at the proximal border of quadratus femoris in every case
- The deep branch crosses posterior to the obturator externus tendon and then anterior to the conjoint tendon of inferior gemellus, obturator internus and superior gemellus
- It perforates the capsule at the level of the superior gemellus and divides into two to four subsynovial retinacular vessels on the posterosuperior neck
- Obturator externus protected the deep branch from disruption during dislocation in any direction after release of all other soft-tissue attachments
Ischiofemoral Impingement Syndrome: An Entity with Hip Pain and Abnormalities of the Quadratus Femoris Muscle
- 12 hips in 9 symptomatic patients compared with 11 hips in 10 control subjects on axial MRI
- The ischiofemoral space was significantly narrower in affected subjects, 13 plus or minus 5 mm versus 23 plus or minus 8 mm
- The quadratus femoris space was likewise narrower, 7 plus or minus 3 mm versus 12 plus or minus 4 mm
- Quadratus femoris abnormalities comprised oedema in 100 per cent, partial tear in 33 per cent and fatty infiltration in 8 per cent
- All affected subjects were women aged 30 to 71 years
Ischiofemoral Impingement Syndrome: A Meta-Analysis
- Meta-analysis of 217 hip MRIs with ischiofemoral impingement against 140 control hips
- Mean ischiofemoral space was 14.91 plus or minus 4.8 mm in cases versus 26.01 plus or minus 7.98 mm in controls
- Mean quadratus femoris space was 9.57 plus or minus 3.7 mm versus 15.97 plus or minus 6.07 mm
- An ischiofemoral space cutoff of 15 mm or less gave 76.9 per cent sensitivity and 81.0 per cent specificity
- A quadratus femoris space cutoff of 10 mm or less gave 78.7 per cent sensitivity and 74.1 per cent specificity
Posterior Approach to Total Hip Replacement Using Enhanced Posterior Soft Tissue Repair
- Two senior surgeons independently adopted an identical enhanced posterior soft tissue repair
- In the first series the dislocation rate fell from 4 per cent in 395 patients to 0 per cent in a further 395
- In the second series it fell from 6.2 per cent in 160 replacements to 0.8 per cent in 124
- Both reductions were highly statistically significant
Does Surgical Approach Affect Total Hip Arthroplasty Dislocation Rates?
- Meta-analysis of five studies directly comparing the posterior approach with and without soft tissue repair
- Dislocation rates were 0.49 per cent with repair and 4.46 per cent without
- The posterior approach without repair carried an 8.21 times greater relative risk of dislocation
- A separate review of 11 studies gave comparable dislocation rates for the anterolateral (0.70 per cent), direct lateral (0.43 per cent) and repaired posterior (1.01 per cent) approaches
Surgical Dislocation of the Adult Hip: A Technique with Full Access to the Femoral Head and Acetabulum Without the Risk of Avascular Necrosis
- Technique of anterior dislocation through a posterior approach with a trochanteric flip osteotomy, based on detailed anatomical studies of the blood supply
- The external rotator muscles are not divided, and the medial femoral circumflex artery is protected by the intact obturator externus
- Reported in 213 hips over seven years, including 19 with simultaneous intertrochanteric osteotomy
- Femoral head perfusion was verified intra-operatively and no patient had developed avascular necrosis at the time of reporting
- Morbidity was low and the exposure permitted treatment of conditions not amenable to other methods