The Upper Twin of the Triceps Coxae
- Superior gemellus arises from the dorsal surface of the ischial spine and inserts with obturator internus and inferior gemellus as the conjoint tendon on the medial surface of the greater trochanter.
- It is supplied by the nerve to obturator internus, L5 and S1, which also supplies obturator internus.
- Superior gemellus, obturator internus and inferior gemellus together form the triceps coxae.
- The deep branch of the medial circumflex femoral artery passes anterior (deep) to the conjoint tendon and posterior to the obturator externus tendon — so the conjoint tendon may be divided safely if obturator externus is preserved.
- The nerve to obturator internus crosses the ischial spine lateral to the pudendal nerve and internal pudendal vessels.
- “The gemelli are accessory to obturator internus: they compensate for the mechanical loss caused by the tendon turning around the lesser sciatic notch.
- “Obturator internus turns roughly 90 degrees around the lesser sciatic notch, which acts as a trochlear pulley lined by a bursa.
- “Superior gemellus is the smaller and more variable twin, and is absent or hypoplastic in a proportion of specimens.
- “The nerve to obturator internus leaves the pelvis through the greater sciatic foramen and re-enters through the lesser sciatic foramen — one of only three structures that do so.
Overview
Superior gemellus is the upper of the two small, flat, triangular muscles, the gemelli (Latin for twins), that flank the tendon of obturator internus as it emerges from the lesser sciatic foramen. Together the three form the triceps coxae, and their fibres fuse into a single conjoint tendon inserting on the medial surface of the greater trochanter.
On its own, superior gemellus is a small and functionally trivial muscle. Its importance is entirely relational, and there are four relationships an examiner will test:
- It is part of the conjoint tendon, the structure divided and repaired in the posterior approach to the hip.
- Its tendon lies posterior to the deep branch of the medial circumflex femoral artery, which is what makes it safe to divide provided obturator externus is preserved.
- Its nerve, the nerve to obturator internus, crosses the ischial spine immediately lateral to the pudendal nerve, the anatomical fact that underpins pudendal nerve blocks and explains combined injuries at the spine.
- It arises from the ischial spine, the key palpable landmark in pelvic and deep gluteal surgery and the site of the sacrospinous ligament attachment.
Why the gemelli exist. Obturator internus arises inside the pelvis, on the inner surface of the obturator membrane and the surrounding pelvic bone. Its tendon must leave through the lesser sciatic foramen, turning through roughly 90 degrees around the smooth, cartilage-covered groove on the posterior surface of the ischium at the lesser sciatic notch.
The pulley and its price. The notch acts as a trochlea, with a bursa, the bursa of obturator internus, to reduce friction and grooves in the bone corresponding to the tendon's slips. Turning a tendon through a right angle wastes force and reduces its effective excursion. The gemelli arise outside the pelvis on either side of the tendon and add muscle fibres to it distal to the pulley, restoring the power lost at the turn.
Accessory muscles. That is why the classical description calls the gemelli "accessory to obturator internus". Restoring force at the pulley, not any independent action, is what they are for.
Attachments, Innervation and Relations
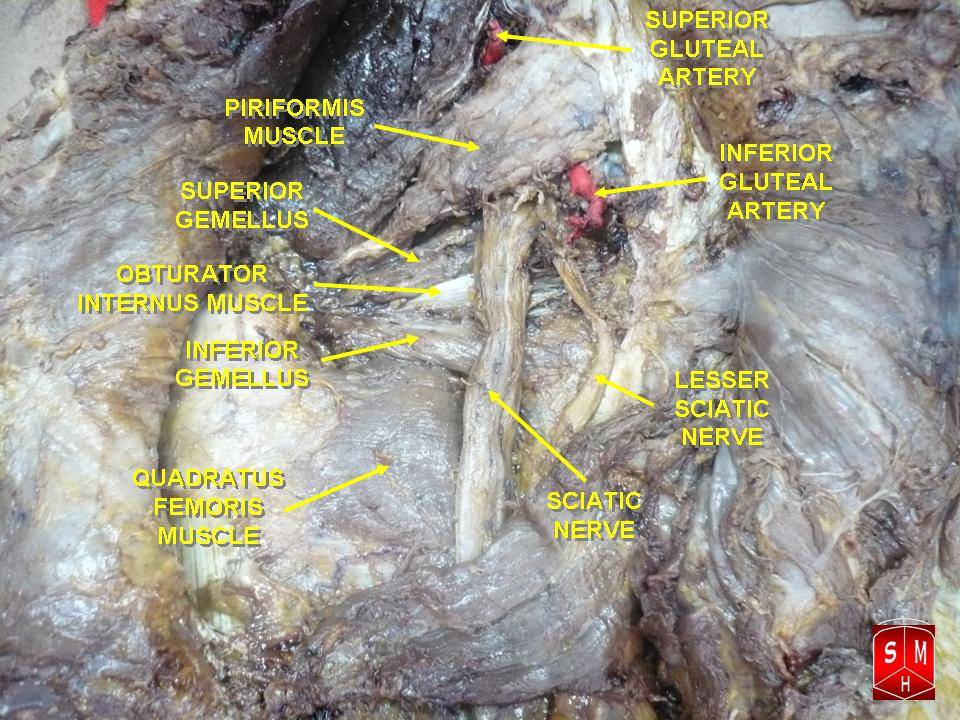
Origin. Superior gemellus arises by short fibres from the dorsal (external) surface of the ischial spine and the adjacent margin of the greater sciatic notch. It is typically 2-3 cm in its longest dimension.
The ischial spine. The spine gives attachment to the sacrospinous ligament medially and forms the boundary between the greater and lesser sciatic foramina. It is the point around which the pudendal neurovascular bundle and the nerve to obturator internus hook. It is also a radiographic landmark for acetabular version: on an anteroposterior pelvic radiograph a visible ischial spine sign indicates acetabular retroversion, provided the film is well centred and not rotated.
Insertion. The fibres run laterally and fuse with the upper surface of the obturator internus tendon, and with inferior gemellus below it, to form the conjoint tendon. The conjoint tendon inserts on the medial surface of the greater trochanter, below and slightly anterior to the piriformis insertion, through a footprint roughly 1.5-2 cm in vertical dimension immediately anterior to the trochanteric fossa.
Variants. Superior gemellus is the smaller and more variable twin, hypoplastic or absent in a proportion of anatomical specimens, whereas inferior gemellus is more consistently present and larger. Its absence is of no functional consequence and the conjoint tendon is present regardless, but at surgery the tendon may then appear to have only two contributors. Accessory slips between superior gemellus and piriformis or the capsule are also described.
The trochanteric insertion map
- Insertion site on the proximal femur
- Superomedial aspect of the greater trochanter, at its tip
- Surgical note
- The most superior; the landmark for the piriformis fossa and for antegrade nailing entry
- Insertion site on the proximal femur
- Medial surface of the greater trochanter, anterior to the trochanteric fossa
- Surgical note
- The structure tagged and divided in the posterior approach
- Insertion site on the proximal femur
- Trochanteric fossa, posterior to the conjoint tendon
- Surgical note
- Must be preserved — it shields the MFCA deep branch
- Insertion site on the proximal femur
- Quadrate tubercle on the intertrochanteric crest
- Surgical note
- Purely muscular; do not strip it flush from bone
- Insertion site on the proximal femur
- Lateral and anterior facets of the greater trochanter
- Surgical note
- Not part of the posterior release; abductor mechanism
Piriformis-sparing is not what protects the femoral head: piriformis, like the conjoint tendon, lies superficial to the MFCA deep branch. It is obturator externus preservation that protects the artery, and that corollary is what gets candidates marks.
- Dissection medial to the ischial spine, or aggressive medial retraction, enters the territory of the pudendal nerve and internal pudendal vessels. Perineal numbness, faecal or urinary incontinence and sexual dysfunction are the price, a far more distressing complication than a small muscle deficit.
- The pudendal nerve is the most medial of the three structures at the spine and the one you must not injure. The nerve you are entitled to be near, the nerve to obturator internus, is the most lateral.
- In deep gluteal space endoscopy, work lateral to the sciatic nerve and lateral to the spine, and identify the nerve to obturator internus as your medial boundary marker.
- The sacrospinous ligament attaches to the spine, and a sacrospinous fixation suture placed too laterally can injure the pudendal bundle, the gynaecological equivalent of the same error.
Action and Biomechanics
Actions. Superior gemellus externally rotates the extended hip as one component of the triceps coxae, and abducts the flexed hip because its line of pull changes as the hip flexes. With the other short rotators it forms the posterior dynamic sleeve, which compresses the femoral head into the acetabulum and resists posterior translation, the hip's functional analogue of the rotator cuff.
The flexion reversal. In extension the short external rotators are efficient external rotators. Beyond about 60-70 degrees of hip flexion the line of pull of piriformis and the obturator group swings so that they become internal rotators and abductors. The reversal explains:
- why testing rotation in flexion gives different information from testing in extension
- why the FAIR position (flexion, adduction, internal rotation) tensions piriformis and the obturator group against the sciatic nerve
- why deep gluteal syndrome is provoked in flexion
Its share of the torque. Superior gemellus contributes a very small fraction of total external rotation torque. Gluteus maximus is by far the largest external rotator, with the posterior fibres of gluteus medius and the obturator group contributing the remainder.
What its loss costs. Isolated loss is silent: no measurable deficit in strength or function follows division of superior gemellus alone, which is why it is divided routinely without hesitation. Loss of the whole posterior sleeve, the situation after an unrepaired posterior approach, removes a passive tether and a dynamic compressive contribution, and is one mechanism behind the increased dislocation rate.
Surface Anatomy and Examination
Palpation. Superior gemellus is not palpable: it lies deep to gluteus maximus and the sciatic nerve, on the ischial spine. What you palpate are the bony landmarks around it.
- The greater trochanter laterally, whose posterior and medial surfaces carry the rotator insertions
- The ischial tuberosity inferomedially
- The posterior superior iliac spine, from which a line to the greater trochanter approximates the upper border of piriformis, and a line to the ischial tuberosity crosses the field of the rotators
The ischial spine itself is palpable per rectum or per vaginam, not externally, and this is how it is located for a pudendal nerve block.
Named clinical tests
- How to perform
- Side-lying, hip flexed 60 degrees, then adducted and internally rotated
- Positive finding
- Deep buttock pain with or without sciatic radiation
- What it means
- Deep gluteal syndrome — piriformis or obturator internus related sciatic irritation
- False positives
- Hip osteoarthritis; lumbar radiculopathy; gluteal tendinopathy
- How to perform
- Side-lying, resisted abduction and external rotation with the heel pressed into the couch
- Positive finding
- Deep buttock pain
- What it means
- Piriformis-related deep gluteal syndrome
- False positives
- Gluteal tendinopathy; sacroiliac pain
- How to perform
- Seated, knee extended, hip adducted and internally rotated while palpating lateral to the ischium
- Positive finding
- Posterior pain reproduced
- What it means
- Deep gluteal syndrome; more sensitive when combined with the active piriformis test
- False positives
- Hamstring tendinopathy
- How to perform
- Prone, knee flexed 90 degrees, resisted external rotation
- Positive finding
- Weakness or pain
- What it means
- Short external rotator group involvement — cannot isolate superior gemellus
- False positives
- Pain inhibition; gluteus maximus weakness
- How to perform
- Deep palpation lateral to the ischial tuberosity toward the lesser sciatic notch
- Positive finding
- Focal deep tenderness
- What it means
- Obturator internus bursitis
- False positives
- Ischial bursitis; proximal hamstring tendinopathy
- How to perform
- Ultrasound- or CT-guided local anaesthetic to the obturator internus bursa or the deep gluteal space
- Positive finding
- Substantial temporary relief
- What it means
- Confirms the deep gluteal structures as the pain source
- False positives
- Anaesthetic spread to the sciatic nerve causing transient weakness
No test isolates it. External rotation strength is graded 0-5 for the group, and an examiner asking for an isolation test for superior gemellus is testing whether you know that one does not exist. The clinically useful discrimination is between the deep external rotator group (deep, posterior, provoked in flexion and internal rotation) and the abductor mechanism (lateral, provoked by single-leg stance), and between both of those and the hip joint itself (groin pain, C-sign, restricted internal rotation in flexion).
Differential diagnosis of deep buttock pain
- Key discriminator
- Sitting-related pain with sciatic radiation; positive FAIR and active piriformis tests
- Confirmatory finding
- Sciatic nerve signal change or entrapment on MR neurography; response to diagnostic injection
- Key discriminator
- Focal tenderness deep to the ischium, worse on resisted external rotation
- Confirmatory finding
- Fluid in the obturator internus bursa on MRI
- Key discriminator
- Long-stride pain relieved by short strides
- Confirmatory finding
- Quadratus femoris oedema with narrowed ischiofemoral space
- Key discriminator
- Pain on sitting on hard surfaces, tender on the tuberosity
- Confirmatory finding
- High signal at the conjoint hamstring origin
- Key discriminator
- Perineal and genital pain in a sitting position, relieved on standing or sitting on a toilet seat
- Confirmatory finding
- Response to a pudendal nerve block at the ischial spine
- Key discriminator
- Pain below the PSIS, positive cluster of provocation tests
- Confirmatory finding
- Response to an image-guided intra-articular block
- Key discriminator
- Dermatomal pain, positive straight-leg raise, neurological signs
- Confirmatory finding
- Concordant lumbar MRI
Complications
Sciatic nerve. Sciatic nerve injury is the commonest neurological complication of the posterior approach. Its mechanisms are direct trauma during the release, retractor pressure, traction from limb lengthening and thermal injury, so limiting lengthening belongs with protecting the nerve. The peroneal division is more vulnerable because of its more lateral position, larger fascicles and less protective connective tissue.
Pudendal nerve. Injury presents as perineal numbness and, in severe cases, sexual and continence dysfunction. The commonest cause is traction against a perineal post during hip arthroscopy or fracture table use. The others are medial dissection beyond the ischial spine in a Kocher-Langenbeck approach, and retractor placement on the quadrilateral surface or over the ischial spine.
Preventing pudendal injury. Prevention is the answer. Use a well-padded, large-diameter post, or a post-free or lateral traction system where available, minimise traction force, limit traction time to the minimum and document it, and stop dissecting when you reach the spine.
Nerve to obturator internus. It is injured during deep dissection at the ischial spine, posterior column acetabular fixation, pelvic and gynaecological surgery, and sacrospinous ligament fixation. Isolated injury is functionally silent, since the muscles it supplies are expendable, but its proximity to the pudendal nerve makes it a warning marker: an injury to it should prompt a careful assessment of pudendal function.
Other nerves. Deep capsular dissection can injure the nerve to quadratus femoris, producing selective quadratus femoris and inferior gemellus atrophy. Extending the dissection above piriformis can injure the superior gluteal nerve, with abductor weakness and a Trendelenburg gait.
Vascular. Femoral head osteonecrosis follows injury to the MFCA deep branch if obturator externus is divided or the release is taken flush against the femur. An avulsed inferior gluteal artery retracts into the pelvis and cannot be controlled through the posterior wound: it needs packing and, if uncontrolled, angiographic embolisation or a pelvic approach. The superior gluteal artery can be injured at the notch with the same problem of proximal retraction, and the internal pudendal vessels at the ischial spine by medial dissection.
The repair. Dislocation is the risk the repair addresses, and follows if the repair is omitted or fails. Repairs fail when sutures are placed in poor-quality tendon, when the tendon is divided flush at the bone so there is no cuff, or when the repair is tensioned in internal rotation. Suture knots can irritate over the posterior trochanter, and heterotopic ossification can form in the split gluteus maximus and the rotator bed, particularly after acetabular fracture surgery.
Clinical Relevance
Deep gluteal syndrome
The space. Deep gluteal syndrome is extrapelvic entrapment of the sciatic nerve in the space bounded by gluteus maximus posteriorly, the posterior acetabular column and hip capsule anteriorly, the sacrotuberous and falciform fascia medially, the linea aspera laterally, the sciatic notch superiorly and the hamstring origin inferiorly. Superior gemellus and the conjoint tendon form part of the floor of this space, immediately deep to the nerve.
Causes. The classical named cause is piriformis syndrome, but the term has broadened because the nerve can be tethered by fibrous bands, the obturator internus and gemelli complex, the hamstring origin, vascular structures and post-traumatic scar. The obturator internus and gemellus complex is a recognised cause distinct from piriformis: the nerve passes over the conjoint tendon, and fibrous adhesions or a hypertrophied complex can tether it.
Presentation. Buttock pain is worse on sitting and radiates down the posterior thigh, without a clear dermatomal pattern and with a normal lumbar spine. The obturator complex is distinguished from piriformis by pain reproduced on resisted external rotation with the hip flexed and on direct palpation lower and more lateral than the piriformis point, closer to the lesser sciatic notch.
Investigation. Four tests contribute, and of them a positive response to image-guided diagnostic injection is the most useful single test.
- MRI of the pelvis, to exclude a mass, assess the rotators for asymmetry, hypertrophy or atrophy, and evaluate the hamstring origin
- MR neurography where available, looking for sciatic nerve signal change, calibre change and loss of the normal perineural fat plane
- Electrophysiology, which is usually normal and is used mainly to exclude a radiculopathy or a more proximal lesion
- Image-guided diagnostic injection into the deep gluteal space or the obturator internus bursa
Management. Treatment is non-operative first: activity and sitting modification, neural mobilisation, hip external rotator and abductor rehabilitation, and image-guided injection. Refractory cases go to endoscopic sciatic nerve decompression, in which the nerve is followed from the sciatic notch distally over piriformis, the conjoint tendon and quadratus femoris and all tethering bands are released. Piriformis and, if implicated, the conjoint tendon may be released, which is well tolerated because these muscles are expendable.
Outcome. Outcomes from endoscopic decompression series are generally good, but selection is everything. Patients with a clear positive diagnostic injection and no significant lumbar pathology do best.
Obturator internus bursitis
The lesion. Inflammation of the bursa between the obturator internus tendon and the lesser sciatic notch produces deep buttock pain, worse on resisted external rotation and on sitting. It is a recognised and often-missed cause of posterior hip pain, occasionally associated with a snapping sensation as the tendon moves over the notch.
Diagnosis and treatment. MRI shows fluid distending the bursa, best seen on axial fluid-sensitive sequences. Image-guided corticosteroid injection into the bursa is usually effective, and surgery is rarely needed.
The mimic. An infected obturator internus bursa or a pyomyositis of obturator internus presents in children and young adults with fever, limp and hip pain, and is a genuine mimic of septic arthritis. MRI distinguishes them, and missing it delays treatment of a septic collection.
Denervation patterns
Reading the atrophy. Recognising the pattern of selective atrophy on MRI is a high-yield way to localise a pelvic or deep gluteal lesion, and to distinguish a focal nerve injury from a radiculopathy.
- Nerve to obturator internus: obturator internus and superior gemellus, sparing inferior gemellus and quadratus femoris (nerve to quadratus femoris) and piriformis (its own nerve)
- Nerve to quadratus femoris: quadratus femoris and inferior gemellus
- Nerve to piriformis: isolated piriformis atrophy
- All of them plus the hamstrings: a sacral plexus or proximal sciatic lesion, not an individual nerve
Surgical Relevance
The conjoint tendon in the posterior approach. In the posterior (Moore or Southern) approach to the hip, the conjoint tendon is the principal structure released, along with piriformis. The release and repair run in this order.
- Position the patient lateral decubitus with the pelvis rigidly held, and confirm the pelvis has not rolled before assessing component version.
- Split the iliotibial band and gluteus maximus fascia, and split gluteus maximus bluntly along its fibres.
- Internally rotate the hip to bring the rotators into view and tension their tendons.
- Palpate the sciatic nerve, which lies superficial to the rotators and deep to gluteus maximus, rather than dissecting it out or skeletonising it.
- Tag piriformis and the conjoint tendon with heavy braided non-absorbable suture before dividing them.
- Divide them a short distance medial to the trochanteric footprint, leaving a cuff on bone. Obturator externus should be preserved, and quadratus femoris is usually left intact.
- Reflect the tagged sleeve posteriorly, where it protects the sciatic nerve for the remainder of the case.
- Perform the capsulotomy, tagging its corners.
- At closure, repair the capsule first, then the tendon sleeve, through transosseous drill holes in the posterior greater trochanter or with suture anchors. Hold the hip in extension with neutral or slight external rotation, so the repair is not tensioned in the position that will later be avoided.
- Check stability through the dislocating arc of flexion, adduction and internal rotation before closing, and document the safe range.
Why the repair matters. The posterior capsule and the short external rotators together act as a passive checkrein against the flexion, adduction and internal rotation position that dislocates a posterior-approach hip, and as a dynamic compressor centring the head. Their repair is the best-evidenced technical step against posterior dislocation: pooled series report a dislocation rate of roughly 4 per cent without repair, falling to under 1 per cent with a formal transosseous repair.
What the repair does not fix. Component malposition. A posterior repair does not rescue a retroverted cup or inadequate offset, so correct version, offset and head size and a formal repair are complementary, not alternatives.
Piriformis-sparing modification. The approach works through the piriformis interval, dividing only the conjoint tendon, or in some descriptions only a portion of it. Superior gemellus is therefore the first structure divided, the upper border of the released sleeve. The justification is soft tissue preservation, better repair quality and possibly faster early recovery; it is not a vascular one.
Kocher-Langenbeck approach. The same rotator release exposes the posterior column and posterior wall of the acetabulum. Keep the hip extended and the knee flexed throughout to protect the sciatic nerve, and palpate the ischial spine as the medial landmark for the quadrilateral surface rather than dissecting it aggressively or medial to it. Some surgeons use a trochanteric flip osteotomy rather than a rotator release, which preserves the entire posterior sleeve including obturator externus and gives better access to the superior acetabulum.
Ganz surgical hip dislocation. The external rotators are not divided at all: the entire posterior sleeve, including superior gemellus and obturator externus, is preserved, access is gained through the trochanteric flip osteotomy instead, and the MFCA is shielded by the intact obturator externus. This is why the technique has such a low osteonecrosis rate.
Antegrade femoral nailing. The piriformis fossa entry point sits just medial to the tip of the greater trochanter and superior to the conjoint tendon footprint. A malpositioned entry point damages the rotator insertions and can breach the medial trochanteric cortex.
Structures at risk
- Location relative to a landmark
- Superficial to the conjoint tendon, descending below piriformis onto quadratus femoris
- How to protect it
- Reflect the tagged rotator sleeve posteriorly over it; hip extended, knee flexed
- Location relative to a landmark
- Medial to the internal pudendal vessels at the ischial spine
- How to protect it
- Do not dissect medial to the ischial spine; pad the perineal post and limit traction
- Location relative to a landmark
- Between the pudendal nerve and the nerve to obturator internus at the spine
- How to protect it
- Same medial limit; avoid blind retraction over the spine
- Location relative to a landmark
- Anterior (deep) to the conjoint tendon; posterior to the obturator externus tendon
- How to protect it
- Preserve obturator externus; divide the conjoint tendon short of the femur, leaving a cuff
- Location relative to a landmark
- Emerging below piriformis at the superomedial corner of the field
- How to protect it
- Identify before deep blunt splitting of gluteus maximus
- Location relative to a landmark
- Emerging above piriformis at the greater sciatic notch
- How to protect it
- Do not extend the dissection above piriformis; the artery retracts into the pelvis if torn
- Location relative to a landmark
- Deep to the conjoint tendon, on the posterior hip capsule
- How to protect it
- Avoid blind cautery and stripping of the capsule
Guidelines, Registries & Global Practice
Anatomical Variation Across Populations
- Superior gemellus is the most variable of the short external rotators. It is reported as hypoplastic or absent in a minority of cadaveric specimens across European, North American and Asian series, with wide variation in reported prevalence reflecting differing definitions of what counts as absent. The inferior gemellus is more consistently present and larger.
- Sciatic nerve variants relative to piriformis are described in all populations. A meta-analysis of 44 cadaveric studies gave a pooled prevalence of 90 per cent for the typical pattern, with variants more common in East Asian populations (31 per cent pooled prevalence of total variants) and no significant difference by sex or laterality. The surgical message is to expect a variant in roughly one in ten patients, and more often in East Asian populations.
- The extracapsular course of the deep branch of the medial circumflex femoral artery was constant in all 24 hips in the defining cadaveric study, which is what permits the Ganz principles to be taught as rules.
- Ischial spine morphology varies, and a prominent spine is associated with acetabular retroversion — the basis of the radiographic ischial spine sign.
Differences in Described Practice
- Position
- Preserve the whole posterior sleeve using a trochanteric flip osteotomy with the external rotators left undivided; where rotators are divided, leave a cuff on the femur and never divide obturator externus.
- Position
- Multiple approaches acceptable; posterior soft tissue repair is standard when the posterior approach is used.
- Position
- Posterior approach with formal capsular and rotator repair is the most widely used technique in the United Kingdom.
- Position
- Kocher-Langenbeck with rotator release preserving obturator externus and quadratus femoris; ischial spine as the medial landmark; hip extended and knee flexed throughout.
- Position
- Divide only the conjoint tendon, beginning with superior gemellus, and preserve the piriformis tendon; justified on soft tissue grounds rather than vascular ones.
- Position
- The conjoint tendon forms part of the deep gluteal space floor and may be released to decompress the sciatic nerve; patient selection by diagnostic injection.
Registry and Practice Signals
- National joint registries (NJR, AOANJRR, the Nordic registries and the AJRR) consistently list dislocation among the leading indications for early revision after primary total hip arthroplasty, which is the practice-level argument for the posterior repair.
- Registries also show declining dislocation rates over time across all approaches, attributable to larger femoral heads, dual-mobility bearings in high-risk patients, improved component positioning and the widespread adoption of posterior soft tissue repair.
- There is no registry for deep gluteal syndrome or for endoscopic sciatic nerve decompression. The evidence base is single-centre case series, and the consistent signal is that outcomes depend on selection — a positive diagnostic injection and the absence of significant lumbar pathology.
High- and Limited-Resource Practice
- Well-resourced settings: MR neurography for suspected deep gluteal syndrome, image-guided diagnostic blocks, endoscopic sciatic nerve decompression, dual-mobility bearings and navigation or robotics for component positioning.
- Limited-resource settings: the anatomical rules cost nothing and matter most. Tagging the conjoint tendon before dividing it, dividing short of the femur to leave a cuff, preserving obturator externus, and performing a transosseous repair with a drill and a suture are available in every operating theatre in the world and deliver the single largest reduction in dislocation risk. Diagnosis of deep gluteal syndrome can be made clinically with the FAIR and active piriformis tests plus a landmark-guided injection.
MCQ Practice Points
Q: Where does superior gemellus arise and insert? A: From the dorsal surface of the ischial spine, inserting via the conjoint tendon on the medial surface of the greater trochanter, anterior to the trochanteric fossa.
Q: What innervates superior gemellus? A: The nerve to obturator internus, L5 and S1, which also supplies obturator internus. The inferior gemellus, by contrast, takes the nerve to quadratus femoris.
Q: What is the triceps coxae? A: Superior gemellus, obturator internus and inferior gemellus, fusing into the conjoint tendon.
Q: Which three structures leave the pelvis through the greater sciatic foramen and re-enter through the lesser? A: The pudendal nerve, the internal pudendal vessels and the nerve to obturator internus. Medial to lateral in that order at the ischial spine.
Q: What is the functional purpose of the gemelli? A: They are accessory to obturator internus. They add muscle fibres to the tendon distal to the trochlear pulley at the lesser sciatic notch, restoring force lost when the tendon turns through 90 degrees.
Q: Where does the MFCA deep branch run relative to the conjoint tendon? A: Anterior (deep) to it, and posterior to the obturator externus tendon. This is why the conjoint tendon can be divided safely and obturator externus cannot.
Q: What happens to the short external rotators beyond 60-70 degrees of hip flexion? A: They become internal rotators and abductors. This underlies the FAIR test and the flexion-provoked nature of deep gluteal syndrome.
Q: MRI shows selective atrophy of obturator internus and superior gemellus. Where is the lesion? A: The nerve to obturator internus. If quadratus femoris and inferior gemellus were atrophic instead, the lesion would be the nerve to quadratus femoris.
Q: Which of the two gemelli is more often absent? A: The superior gemellus. It is the smaller and more variable twin; the conjoint tendon is present regardless.
Q: What does a visible ischial spine on a well-centred anteroposterior pelvic radiograph suggest? A: Acetabular retroversion — the ischial spine sign. It is only valid on a well-centred, non-rotated film.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are teaching a registrar the posterior approach to the hip. They have split gluteus maximus and can see the short external rotators. Talk them through what happens next and why.”
“During a Kocher-Langenbeck approach for a posterior column acetabular fracture, your assistant asks how far medially they can safely retract and dissect. What is your answer and what is the anatomy behind it?”
“A 38-year-old cyclist has six months of right buttock pain radiating to the posterior thigh, much worse after 20 minutes of sitting. Lumbar MRI is normal. Straight-leg raise is negative but the FAIR test reproduces the pain. What is your working diagnosis and how do you proceed?”
Core Anatomy
- Origin: dorsal surface of the ischial spine
- Insertion: conjoint tendon on the medial greater trochanter
- Nerve: nerve to obturator internus, L5-S1
- Triceps coxae = superior gemellus + obturator internus + inferior gemellus
The Ischial Spine
- Medial to lateral: pudendal nerve, internal pudendal vessels, nerve to obturator internus
- All three exit the greater and re-enter the lesser sciatic foramen
- Sacrospinous ligament attaches here
- Medial limit of safe posterior dissection
Vascular Rules
- MFCA deep branch is anterior to the conjoint tendon
- It is posterior to the obturator externus tendon
- Conjoint tendon safe to divide; obturator externus is not
- Divide short of the femoral insertion, leaving a cuff on bone
Clinical
- Gemelli are accessory to obturator internus, compensating for the trochlear pulley
- Beyond 60-70 degrees of hip flexion the rotators become internal rotators
- Posterior repair drops dislocation from about 4 per cent to under 1 per cent
- Selective obturator internus and superior gemellus atrophy = nerve to obturator internus lesion
Evidence Base
Anatomy of the Medial Femoral Circumflex Artery and Its Surgical Implications
- 24 cadaver hips dissected after neoprene-latex injection of the femoral or internal iliac arteries
- The extracapsular course of the deep branch of the medial femoral circumflex artery was constant, with a trochanteric branch at the proximal border of quadratus femoris in every case
- The deep branch crosses posterior to the obturator externus tendon and then anterior to the conjoint tendon of inferior gemellus, obturator internus and superior gemellus
- It perforates the capsule at the level of the superior gemellus and divides into two to four subsynovial retinacular vessels on the posterosuperior neck
- Obturator externus protected the deep branch from disruption OR STRETCHING during dislocation in any direction after serial release of all other soft-tissue attachments of the proximal femur INCLUDING A COMPLETE CIRCUMFERENTIAL CAPSULOTOMY - the release was total, which is what makes the protective claim striking
- The trochanteric branch is the intra-operative landmark the paper offers: it marks the level of the obturator externus tendon, which the deep branch crosses posteriorly
Surgical Dislocation of the Adult Hip: A Technique with Full Access to the Femoral Head and Acetabulum Without the Risk of Avascular Necrosis
- Technique of anterior dislocation through a posterior approach with a trochanteric flip osteotomy, based on detailed anatomical studies of the blood supply
- The external rotator muscles are not divided, and the medial femoral circumflex artery is protected by the intact obturator externus
- Reported in 213 hips over seven years, including 19 with simultaneous intertrochanteric osteotomy
- Femoral head perfusion was verified intra-operatively and no patient had developed avascular necrosis at the time of reporting
- Morbidity was low and the exposure permitted treatment of conditions not amenable to other methods
Posterior Approach to Total Hip Replacement Using Enhanced Posterior Soft Tissue Repair
- Two senior surgeons independently adopted an identical enhanced posterior soft tissue repair
- In the first series the dislocation rate fell from 4 per cent in 395 patients to 0 per cent in a further 395
- In the second series it fell from 6.2 per cent in 160 replacements to 0.8 per cent in 124
- Both reductions were highly statistically significant
Does Surgical Approach Affect Total Hip Arthroplasty Dislocation Rates?
- Meta-analysis of five studies directly comparing the posterior approach with and without soft tissue repair
- Dislocation rates were 0.49 per cent with repair and 4.46 per cent without
- The posterior approach without repair carried an 8.21 times greater relative risk of dislocation (95 per cent confidence interval 4.05 to 16.67, fixed-effects model) - a fourfold-wide interval, which is why the direction is more trustworthy than the magnitude
- A separate review of 11 studies gave comparable dislocation rates for the anterolateral (0.70 per cent), direct lateral (0.43 per cent) and repaired posterior (1.01 per cent) approaches
The Endoscopic Treatment of Sciatic Nerve Entrapment / Deep Gluteal Syndrome
- 35 patients with sciatic nerve entrapment treated by endoscopic decompression of the subgluteal space
- Entrapment was addressed by resection of fibrovascular scar bands, piriformis tendon release, obturator internus or quadratus femoris release, or release of hamstring tendon scarring
- Mean modified Harris Hip Score improved from 54.4 to 78.0 and mean visual analogue pain score fell from 6.9 to 2.4
- 83 per cent of patients had no postoperative sciatic sitting pain
- Mean symptom duration before surgery was 3.7 years
Sciatic Nerve Variants and the Piriformis Muscle: A Systematic Review and Meta-Analysis
- Systematic review and meta-analysis of 44 cadaveric studies of sciatic nerve variants relative to piriformis
- The typical pattern, with the undivided sciatic nerve passing below piriformis, had a pooled prevalence of 90 per cent
- In greater than 10 per cent of the population the nerve coursed through or above the piriformis
- Variants were more common among East Asian populations, with a 31 per cent pooled prevalence of total variants
- No significant differences were found with respect to sex or laterality