Amorphous mineral versus organised bone — the single distinction that reorders the entire differential
- Calcification = amorphous, cloudy, punctate or sheet-like mineral with no internal architecture. Ossification = true bone with cortex and trabeculae, and it remodels over time.
- Myositis ossificans matures from the periphery inwards (zoning phenomenon). Extraskeletal osteosarcoma mineralises most densely centrally with an immature periphery. This reversal is the exam point — but know its status: the zoning phenomenon is a widely reproduced PATTERN DESCRIPTION and no study found gives it a sensitivity or specificity. It raises and lowers suspicion; it does not exclude malignancy.
- The commoner error is the opposite of the one you expect. In 60 published paediatric cases the pre-emptive diagnosis was neoplasia in 21.7 per cent and surgical excision was first-line in 46.7 per cent — for a lesion that resolves on its own. Absence of remembered trauma is what drives clinicians to operate, and idiopathic (pseudomalignant) myositis ossificans is precisely the form with no injury.
- For prophylaxis, NSAIDs and radiation are EQUIVALENT on randomised evidence: pooled risk ratio 0.96 (0.88-1.06) across nine trials and 1,295 patients, with no difference in complications. Choose on the individual's contraindications, not on a claim of superiority.
- Serial radiographs at 4-6 weeks are a legitimate and often sufficient investigation: benign heterotopic bone matures and shrinks; sarcoma enlarges.
- “Biopsy of early myositis ossificans is the classic diagnostic trap — the proliferative zone is mitotically active and is misread as osteosarcoma. Delay biopsy, image instead.
- “Calcium pyrophosphate deposition calcifies fibrocartilage (menisci, triangular fibrocartilage, symphysis); hydroxyapatite calcifies tendon (supraspinatus).
Recognising the Pattern
Calcification. Soft-tissue calcification is deposition of calcium salts, predominantly hydroxyapatite or calcium pyrophosphate, within soft tissue without any cellular organisation. Radiographically it is amorphous, cloudy, punctate, linear or sheet-like, with no internal architecture.
Ossification. Soft-tissue ossification is the formation of genuine lamellar bone in an extraskeletal site by metaplastic osteoblasts. It therefore possesses the two features of bone, a peripheral cortical rim and internal trabeculation, and it obeys Wolff's law by remodelling over months.
Why the word matters. The two terms are not interchangeable. Describe a lesion with cortex and trabeculae as calcification and you have discarded the diagnosis, so confirm that ossification is genuinely present before you commit.
- Look for a thin, dense, continuous outer rim that is denser than the lesion's interior. Calcification is either uniform or densest centrally.
- Look for internal linear striations, the trabeculae, running through a less dense marrow-equivalent interior.
- Look for change over time. Ossification matures, condenses and often contracts by 6-12 months. Dystrophic calcification is static.
- On CT, measure the distribution of density: which way the zoning runs is Step 5 below.
- Ask whether the lesion abuts or bridges bone. Heterotopic ossification often forms a bridge from a bony surface; calcification does not respect osseous anatomy.
The exact words for a viva. "This radiograph demonstrates mineralisation within the soft tissues of the [site]. It is [amorphous / organised]. There is [no] discernible peripheral cortex and [no] internal trabecular pattern, so I would describe this as [calcification / heterotopic ossification]. The underlying bone is [intact, with no periosteal reaction or cortical destruction]. My differential is led by [the commonest cause for this site], but I must exclude a mineralising soft-tissue sarcoma."
Mimics and false positives. Each of these can be mistaken for pathological soft-tissue mineralisation.
- Phleboliths: round, 2-5 mm, with a lucent centre, indicating a venous malformation. In a compressible swelling of a limb in a young patient, requesting a bone scan or biopsy is a wasted answer.
- Overlying skin lesions, ECG leads, dressings, ointments and barium residue: repeat the film or shift the projection. True intramuscular mineral does not move relative to bone on obliques, but external artefact does.
- Bone island (enostosis) or accessory ossicle projected over soft tissue on a single view, resolved with an orthogonal projection.
- Post-injection granuloma at deltoid or gluteal sites in older patients.
- Vascular medial calcinosis: parallel "tramline" tubular calcification of arterial walls, especially diabetic tibial vessels, and not a mass at all.
- Calcified lymph nodes in the axilla or groin, reniform with a lucent hilum.
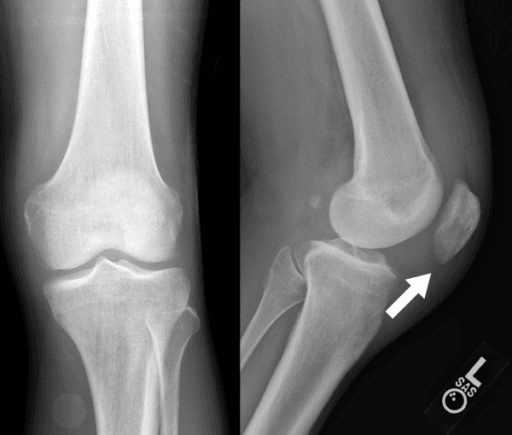
Next Investigation
Orthogonal plain radiographs, always first. They confirm the mineral lies in the soft tissue and is not artefact or a projected bone island, define cortex and trabeculae, and assess the underlying bone. They change management by excluding an aggressive primary bone lesion.
Serum calcium, phosphate, PTH, alkaline phosphatase, urea and creatinine. These are mandatory whenever deposits are multiple or symmetrical. A raised calcium-phosphate product or raised PTH converts a surgical problem into a medical one: phosphate binders, dialysis adequacy or parathyroidectomy, not excision.
CT, the best test for the mineral itself. It defines the zoning phenomenon, the cortical rim, trabeculation and the fluid-calcium levels of tumoural calcinosis. Peripheral maturation reassures and permits observation; reverse zoning mandates sarcoma referral. CT also maps mature heterotopic bone before excision.
MRI with contrast, for the soft tissue rather than the mineral. It is indicated for any solitary enlarging mass, and shows the non-mineralised component, compartmental extent, neurovascular relations and the triple sign of synovial sarcoma. Early myositis ossificans has florid oedema and enhancement and is readily over-called as malignant, so read MRI alongside CT, never alone.
Ultrasound. It is first line for suspected calcific tendinopathy of the rotator cuff or gluteal tendons and for guiding barbotage or lavage. It also confirms compressibility and phleboliths in a venous malformation, ending the workup.
Three-phase bone scan. It was historically used to assess the maturity of neurogenic heterotopic ossification before excision, increased uptake indicating ongoing activity. Modern practice increasingly relies on serial CT and clinical plateau, but the principle, operate on mature bone, is the exam point.
Biopsy, and when not to. Reserve it for a solitary enlarging deep mass after MRI, performed through a planned incision at the treating sarcoma centre. Do NOT biopsy immature myositis ossificans, and never biopsy suspected fibrodysplasia ossificans progressiva.
When no further imaging is needed. The workup can stop at these:
- Classic phleboliths in a compressible limb swelling
- Chondrocalcinosis in an elderly knee with typical CPPD features
- Brooker-graded heterotopic ossification after hip arthroplasty in an asymptomatic patient
- Rice-grain parasitic calcification with a matching travel history
- Vascular medial calcinosis
The Differential
- Typical age / setting
- Age 50-70, deep thigh or buttock, may follow prior radiotherapy
- Discriminating feature
- Reverse zoning — dense amorphous mineral centrally, immature or absent periphery; enlarging soft-tissue mass with no continuity with the parent bone
- What confirms it
- MRI plus core biopsy at a sarcoma centre; staging CT chest
- Typical age / setting
- Age 15-40, periarticular but extra-articular, lower limb around the knee
- Discriminating feature
- Small eccentric punctate/stippled calcification in only about a third of cases, within a slow-growing mass often present for years and often painful
- What confirms it
- MRI showing triple sign and fluid-fluid levels; biopsy with SS18 (SYT) rearrangement
- Typical age / setting
- Dialysis-dependent or malignancy-associated hypercalcaemia, any adult age
- Discriminating feature
- Multiple, symmetrical, periarticular deposits plus visceral and vascular calcification; abnormal serum calcium-phosphate product
- What confirms it
- Serum calcium, phosphate, PTH, urea and creatinine, vitamin D
- Typical age / setting
- Decades after compartment syndrome or sciatic/peroneal nerve injury, anterior compartment of leg
- Discriminating feature
- Fusiform expansile mass replacing a single compartment with plaque-like peripheral calcification and central liquefaction; painless slow enlargement
- What confirms it
- MRI or CT showing a fluid-filled compartment; recognition avoids catastrophic incision and chronic sinus
- Typical age / setting
- Young athletic males 15-35, quadriceps, brachialis, adductors; 2-8 weeks after blunt trauma
- Discriminating feature
- Zoning phenomenon — mature peripheral bone with immature centre; separated from cortex by a lucent cleft; matures and contracts on serial films
- What confirms it
- Serial radiograph or CT at 4-6 weeks demonstrating peripheral maturation
- Typical age / setting
- Weeks to months after spinal cord or traumatic brain injury, or after burns; hips then knees, elbows, shoulders
- Discriminating feature
- Bilateral periarticular bone below the neurological level, always outside the joint capsule with the joint space preserved; presents as loss of range plus warmth
- What confirms it
- Rising alkaline phosphatase and three-phase bone scan; CT for surgical mapping of maturity
- Typical age / setting
- Adults after total hip replacement, especially lateral/direct approaches, males, ankylosing spondylitis
- Discriminating feature
- Ossification bridging from greater trochanter towards ilium; graded by Brooker; occurs in the abductor mass, not diffusely
- What confirms it
- AP pelvis radiograph and Brooker grading; no further imaging usually needed
- Typical age / setting
- Age 40-60, women; supraspinatus, gluteus medius, longus colli
- Discriminating feature
- Homogeneous globular calcification within the tendon substance, no trabeculae; acutely painful phase as it resorbs and becomes ill-defined and cloudy
- What confirms it
- Ultrasound showing intratendinous echogenic focus; often needs no further imaging
- Typical age / setting
- Age over 60; or younger with haemochromatosis, hyperparathyroidism, hypomagnesaemia
- Discriminating feature
- Linear calcification parallel to the articular surface within fibrocartilage — menisci, triangular fibrocartilage, symphysis pubis, labrum
- What confirms it
- Knee, wrist and pelvis radiographs; synovial fluid showing positively birefringent rhomboid crystals
- Typical age / setting
- Middle-aged men, first MTP joint, olecranon, Achilles insertion
- Discriminating feature
- Soft-tissue mass of intermediate density that is usually NOT calcified unless long-standing; adjacent punched-out para-articular erosions with overhanging edges
- What confirms it
- Dual-energy CT showing urate colour-coding; serum urate; aspiration
- Typical age / setting
- Adolescents and young adults, African descent, hip, shoulder, elbow
- Discriminating feature
- Large lobulated periarticular calcific mass with fluid-calcium levels on erect or cross-table views; normal calcium, raised phosphate
- What confirms it
- Serum phosphate and FGF23; CT demonstrating the sedimentation sign
- Typical age / setting
- Children with juvenile dermatomyositis; adults with scleroderma
- Discriminating feature
- Subcutaneous and intramuscular sheet-like or reticular calcification over extensor surfaces, plus acro-osteolysis and tuft calcification in the fingers
- What confirms it
- Autoantibody panel (anti-Jo-1, anti-centromere, anti-Scl-70); clinical skin signs
- Typical age / setting
- Onset in the first decade, cervical and paraspinal soft tissues first, descending axial to appendicular
- Discriminating feature
- Progressive ribbons and plates of ossification bridging joints, with congenital short great toe (hallux valgus with monophalangism) present at birth
- What confirms it
- Clinical toe deformity plus ACVR1 mutation testing — biopsy is contraindicated and provokes flares
- Typical age / setting
- Endemic exposure, any adult age, thigh and calf musculature
- Discriminating feature
- Multiple small elongated 'rice grain' calcifications aligned with the long axis of the muscle fibres
- What confirms it
- Radiograph pattern plus travel history and serology; no further imaging required
TIC MTVCauses of soft-tissue calcification and ossification
Narrowing It Down
Step 1 — calcification or ossification? Interrogate the mineral specifically for a peripheral cortical rim and internal trabeculae, on a bright monitor and with CT if the radiograph is equivocal. This single split removes roughly half the differential and is the sentence to say first.
- Ossification points to myositis ossificans, neurogenic or post-arthroplasty heterotopic bone, fibrodysplasia ossificans progressiva, or extraskeletal osteosarcoma
- Calcification points to crystal deposition, metabolic, collagen vascular or parasitic disease
Step 2 — solitary or multiple, unilateral or symmetrical? Look at the contralateral side. A solitary lesion is a mass until proven otherwise and demands MRI. Multiple deposits in a neurological distribution suggest neurogenic heterotopic ossification below a cord level.
Multiple and symmetrical means metabolic. Multiple, symmetrical, periarticular deposits are metastatic calcification until proven otherwise: renal failure, hyperparathyroidism, hypervitaminosis D and malignancy-related hypercalcaemia all present this way, and the treatment is medical, not surgical. If there is any suggestion of multiplicity, send the biochemistry listed under Next Investigation BEFORE ordering more imaging.
Step 3 — where is it relative to the tissue planes? Assign the mineral to a compartment: tendon, fibrocartilage, muscle belly, subcutis, or bridging two bones.
- Intratendinous and globular: hydroxyapatite deposition
- Linear within fibrocartilage: calcium pyrophosphate
- Intramuscular and fusiform along the belly: myositis ossificans or calcific myonecrosis
- Subcutaneous and reticular over extensor surfaces: connective tissue disease
- Bridging trochanter to ilium: post-arthroplasty heterotopic ossification, which is present in 30 per cent of hips and usually asymptomatic
Step 4 — what is the age, and what is the trigger, or its absence? Take the injury history explicitly, and note when there is NOT one.
- Adolescent athlete with a thigh haematoma four weeks ago: myositis ossificans
- Child with a short great toe and neck stiffness: fibrodysplasia ossificans progressiva
- Dialysis patient: metastatic calcification or tumoural calcinosis
- Age 50 to 70 with a deep enlarging thigh mass, especially after radiotherapy: extraskeletal osteosarcoma until biopsy says otherwise
The trap in the middle. No remembered trauma is what pushes clinicians to operate, yet idiopathic pseudomalignant myositis ossificans is defined by having none.
Step 5 — which way does the zoning run? Get a CT, which is far superior to radiograph and to MRI for this question, and state where the mineral is densest. Peripheral mature bone with an immature centre is the zoning phenomenon of benign heterotopic ossification. Central dense mineral with an immature or absent rim is reverse zoning, the radiological signature of extraskeletal osteosarcoma.
How far to trust it. Use zoning to weight suspicion, not to exclude. No study found gives the zoning phenomenon a sensitivity or specificity, and both imaging and histology may be non-characteristic in the early phase.
Step 6 — is the adjacent bone or joint abnormal? Trace the cortex of the neighbouring bone and assess the joint separately from the soft-tissue mineral. Cortical destruction or aggressive periosteal reaction converts this into a bone tumour with a soft-tissue component.
Reading the joint. Preserved joint space with periarticular bone favours heterotopic ossification, and punched-out erosions with overhanging edges favour gout. Chondrocalcinosis with degeneration in unusual joints, radiocarpal or patellofemoral, favours pyrophosphate arthropathy.
Step 7 — how does it behave over six weeks? Book the interval film and say out loud that you are doing so, rather than reaching for a biopsy. Benign heterotopic bone matures, sharpens and often contracts, and calcific tendinopathy may resorb entirely. A lesion that enlarges, becomes more heterogeneous or develops a growing non-mineralised soft-tissue component is a sarcoma and needs urgent referral.
Serial imaging is a legitimate answer, not an evasion, and the alternative is the documented harm. At 2-4 weeks the lesion is cellular, mitotic and osteoid-rich; its histology mimics osteosarcoma, it has been read as osteosarcoma, and patients have been amputated on that error. If the history is trauma and the CT shows peripheral maturation, re-image at 6 weeks instead.
MCQ Practice Points
Q: What single radiographic feature most reliably distinguishes heterotopic ossification from soft-tissue calcification?
A: An organised internal trabecular pattern with a peripheral cortical rim. Calcification is amorphous and architecturally featureless regardless of how dense it appears. Say the word "ossification" only when you can point to both features — describing bone as calcification discards the entire differential.
Q: Describe the zoning phenomenon, its reversal, and how far you would trust it.
A: In myositis ossificans, mineralisation matures from the periphery inwards — a dense mature rim around an immature cellular centre. Extraskeletal osteosarcoma shows reverse zoning: dense disorganised mineral centrally with an immature or absent peripheral rim. CT is the investigation of choice. The honest qualification, which distinguishes a good answer: this is a widely reproduced pattern description, not a validated test — no study gives it a sensitivity or specificity, and in the early phase both imaging and histology may be non-characteristic. It shifts suspicion; it cannot exclude a sarcoma.
Q: What is the likelier mistake on this pattern — missing a sarcoma, or over-treating a benign lesion?
A: Over-treating the benign lesion. Across 60 published paediatric myositis ossificans cases, the pre-emptive diagnosis was neoplasia in 21.7 per cent and surgical excision was first-line in 46.7 per cent — for a condition that resolves spontaneously. The trigger the authors identify is specific and useful: absence of a remembered trauma is what pushes clinicians towards surgery, and idiopathic pseudomalignant myositis ossificans is precisely the variant with no injury. Caveat: these are published cases, which are selected for being difficult, so the true rate in unselected practice is lower.
Q: How often does heterotopic ossification follow total hip arthroplasty, and what predicts it?
A: 30 per cent — 1,939 of 6,468 hips across 14 studies. It is expected rather than exceptional, most of it low-grade and asymptomatic, so the clinical question is whether it restricts movement rather than whether it is present. The dominant risk factor is a pre-operatively ankylosed hip (odds ratio 9.85), then male sex (2.11), ankylosing spondylitis (1.90) and bilateral surgery (1.74). Rheumatoid arthritis is protective (0.51). Age, osteophytes and hypertrophic osteoarthritis were NOT risk factors, which is worth saying because all three are commonly assumed to be. The pooled figure does not separate Brooker grades — that is its main weakness.
Q: Which is more effective for heterotopic ossification prophylaxis around the hip, NSAIDs or radiation?
A: Neither. Nine randomised trials, 1,295 patients: pooled risk ratio for effectiveness 0.96 (95 per cent CI 0.88 to 1.06), and for complications 0.79 (0.45 to 1.41) — no significant difference either way, independent of arthroplasty versus fixation, sex, age and year. So choose on the patient: NSAIDs are out with renal impairment, peptic ulceration or anticoagulation; radiation is unattractive in the young, needs logistics, and carries a theoretical malignancy risk. Note what this evidence does NOT show — both arms are active treatments, so it says nothing about whether either beats no prophylaxis.
Q: Which tissue does calcium pyrophosphate preferentially calcify, and which does hydroxyapatite?
A: Calcium pyrophosphate deposits in fibrocartilage and hyaline cartilage — menisci, triangular fibrocartilage complex, symphysis pubis, acetabular labrum — producing linear calcification parallel to the joint surface. Hydroxyapatite deposits in tendon and periarticular soft tissue — supraspinatus, gluteus medius, longus colli — producing globular homogeneous calcification.
Q: A child presents with progressive stiffness, ribbons of ossification bridging the paraspinal soft tissues, and bilateral short great toes. What is the diagnosis and what is contraindicated?
A: Fibrodysplasia ossificans progressiva, caused by an activating ACVR1 mutation. Biopsy, intramuscular injection, dental blocks and attempted excision are all contraindicated because tissue trauma provokes catastrophic flares of new ossification. The short great toe is present from birth and is the diagnosis before any imaging.
Q: In which clinical settings is neurogenic heterotopic ossification most likely, and where does it form?
A: After traumatic brain injury, spinal cord injury and extensive burns. It forms in periarticular soft tissue below the neurological level — hip most commonly, then knee, elbow and shoulder — always outside the joint capsule with preservation of the joint space. Presentation is loss of range with local warmth and swelling, often mistaken for deep vein thrombosis or infection.
Q: What is calcific myonecrosis and why does it matter surgically?
A: A late sequela of compartment syndrome or peripheral nerve injury, typically decades later, in which an entire compartment — classically the anterior compartment of the leg — is replaced by a fusiform mass with peripheral plaque-like calcification and a liquefied centre. It matters because incision or biopsy commonly results in chronic infection, a non-healing sinus and amputation. Recognise it and leave it alone.
Exam Viva Scenarios
Practise clinical reasoning and management decisions out loud
“You are shown this radiograph of the femur of a 19-year-old rugby player with a firm, tender anterior thigh mass. He sustained a direct blow to the quadriceps six weeks ago. There is an ovoid area of mineralisation in the anterior soft tissues separated from the femoral cortex by a thin lucent line.”
“You are shown this AP pelvis of a 42-year-old man on haemodialysis for eight years, with bilateral lobulated periarticular calcific masses around both hips and reduced hip movement.”
“You are shown this radiograph of a 63-year-old woman with a deep, painless, enlarging buttock mass present for four months. There is a 9 cm soft-tissue mass containing dense amorphous mineralisation that is most confluent centrally, with an ill-defined faintly mineralised periphery. The underlying ilium and femur are intact.”
The core distinction
- Calcification: amorphous, cloudy, punctate or sheet-like, no internal architecture, static over time
- Ossification: peripheral cortical rim plus internal trabeculae, remodels and contracts over months
- Say which one it is before you offer any differential
Zoning
- Peripheral maturation, immature centre = myositis ossificans (benign)
- Central dense mineral, immature periphery = reverse zoning = extraskeletal osteosarcoma
- CT is the best modality to demonstrate zoning; MRI alone over-calls early myositis ossificans
Site pointers
- Intratendinous globular — hydroxyapatite deposition disease
- Linear in fibrocartilage — CPPD
- Intramuscular fusiform after trauma — myositis ossificans
- Whole compartment, decades post injury — calcific myonecrosis
- Trochanter to ilium after THR — Brooker heterotopic ossification
- Subcutaneous extensor surfaces plus acro-osteolysis — connective tissue disease
- Round, lucent centre, less than 5 mm — phlebolith, venous malformation
Must-not-miss
- Extraskeletal osteosarcoma — deep, greater than 5 cm, enlarging, age over 40, reverse zoning
- Synovial sarcoma — young adult, periarticular, punctate calcification, long history of pain
- Metastatic calcification — bilateral symmetrical periarticular, check calcium/phosphate/PTH/renal function
- Calcific myonecrosis — do not incise
- FOP — do not biopsy or inject
Investigation ladder
- Orthogonal radiographs first, always
- Bloods for any multiple or symmetrical deposits
- CT for the mineral and zoning; MRI with contrast for the soft-tissue mass
- Ultrasound for tendon calcification and vascular malformation
- Serial radiographs at 4-6 weeks are a valid answer for suspected myositis ossificans
- Biopsy only after MRI, only at the sarcoma centre, never in immature heterotopic bone
Management principles
- Operate on heterotopic ossification only when mature and only for functional block or nerve compression
- Prophylaxis after high-risk hip surgery: single-dose radiotherapy or NSAIDs such as indometacin
- Correct the metabolic driver before excising metabolic calcification
- Calcific tendinopathy: analgesia, ultrasound-guided barbotage or lavage; most resorb spontaneously
Evidence Base
Myositis Ossificans in the Paediatric Population: A Systematic Scoping Review
- PRISMA-guided scoping review, two independent reviewers, 60 paediatric cases published between 2002 and 2023; mean age 9.5 years (range 0.2-17), male-to-female 1:1
- The subtype split explains the surgical drift: 23 of 60 (38.3 per cent) were idiopathic/pseudomalignant and 37 (61.7 per cent) circumscribed - so nearly two in five had no trauma to anchor the diagnosis
- THE PRE-EMPTIVE DIAGNOSIS WAS NEOPLASIA IN 13 OF 60 (21.7 PER CENT) - better than one in five children with a benign self-limiting lesion were initially thought to have a tumour
- Biopsy was performed in 16 (percutaneous in 9, incisional in 7) and histological analysis in 35 of 60 cases (57 per cent)
- SURGICAL EXCISION WAS FIRST-LINE TREATMENT IN 46.7 PER CENT, for a condition the authors describe as self-resolving
- The authors find NO CONSENSUS on the appropriate imaging for diagnosis, note that absence of a triggering trauma pushes clinicians towards surgery, and conclude conservative management is key
- Their caveat against complacency: recurrence is NOT excluded, so close clinical follow-up is advised in every case - conservative management means watching, not discharging. Excision may be offered case by case once the lesion has matured
Post-Traumatic Myositis Ossificans: A Benign Lesion That Simulates Malignant Bone and Soft Tissue Tumours
- Multidisciplinary review by orthopaedic, radiology and pathology authors of the lesion and the tumours it imitates
- The post-traumatic subtype is the commonest, typically in young males after trauma or a sports injury
- It can simulate extra-skeletal and surface osteosarcoma, and soft tissue sarcomas including synovial sarcoma and undifferentiated pleomorphic sarcoma
- IN THE EARLY PHASE BOTH IMAGING AND HISTOPATHOLOGY MAY BE NON-CHARACTERISTIC - the difficulty is not a failure of technique but a property of the lesion at that stage
- The authors' recommendation is combined: history, examination, FOLLOW-UP imaging and histological assessment together, rather than any single test
Extra-Skeletal Osteosarcoma: A Review
- Review from a national orthopaedic hospital's radiology and histopathology departments covering demographics, presentation, imaging, differential, management and outcome
- Extra-skeletal osteosarcoma is a RARE malignant soft tissue sarcoma whose soft tissue mineralisation is the source of the diagnostic difficulty
- The authors name myositis ossificans explicitly as the condition it mimics
- Presentation is non-specific, which is why the mineralisation pattern carries so much diagnostic weight
- Written as a reference for radiologists and clinicians managing soft tissue tumours and tumour-like lesions
Incidence and Risk Factors for Heterotopic Ossification After Total Hip Arthroplasty: A Meta-Analysis
- 14 studies, 6468 total hip arthroplasties, quality-assessed with the Newcastle-Ottawa Scale
- HETEROTOPIC OSSIFICATION OCCURRED IN 1939 HIPS - 30.0 PER CENT. This is a common finding, not a rare complication
- Strongest risk factor by far was an ANKYLOSED HIP (odds ratio 9.85, 95 per cent CI 2.61-37.24)
- Also significant: male sex (OR 2.11), bilateral operation (OR 1.74), ankylosing spondylitis (OR 1.90), cemented implant (OR 1.48, CI 1.00-2.17 - touching unity)
- RHEUMATOID ARTHRITIS WAS PROTECTIVE (OR 0.51, 0.33-0.80). Age, femoral neck fracture, previous hip fracture, hypertrophic osteoarthritis and osteophytes were NOT risk factors
Prophylaxis of Heterotopic Ossification of the Hip: Systematic Review and Meta-Analysis
- Systematic review of MEDLINE, EMBASE, CINAHL and the Cochrane register, restricted to RANDOMISED CONTROLLED TRIALS, after formally ruling out publication bias and data heterogeneity
- Nine randomised trials, 1295 patients, comparing NSAIDs against radiation for prevention of heterotopic ossification
- POOLED RISK RATIO FOR EFFECTIVENESS 0.96 (95 per cent CI 0.88 to 1.06) - NO DIFFERENCE between the two modalities
- Risk ratio for associated complications 0.79 (95 per cent CI 0.45 to 1.41) - again no significant difference
- Results were independent of the type of surgery (arthroplasty versus open reduction and internal fixation), gender, age, length of follow-up and year of publication